

What the Tumescent Solution Does in Tumescent Liposuction: Bleeding, Bruising and Comfort

Key Takeaways
- Tumescent solution is dilute saline carrying lidocaine and epinephrine; it swells and firms the fat, numbs the nerves and constricts small vessels so liposuction causes markedly less bleeding than earlier techniques.
- Fat has poor blood flow and epinephrine slows absorption further, so the anesthetic in the fluid is released gradually, producing numbness that commonly lasts many hours and a peak blood level that arrives late.
- Bruising is leaked blood breaking down in tissue; by reducing bleeding during the procedure, the solution usually makes bruises smaller and lighter, but it does not eliminate them.
- The solution is used whether a person is awake, sedated or under general anesthesia; the anesthetic approach reflects how much is being treated and personal preference, not the seriousness of the surgery.
- Risks specific to the fluid include local anesthetic toxicity, fluid overload in people with heart or kidney disease, and epinephrine-related heart rate and blood pressure changes, all of which teams monitor for.
- Swelling typically subsides within a few weeks, but mainstream sources describe the final contour taking several months, with the NHS noting up to about six months for the area to settle.
Tumescent solution is a large volume of very dilute salt water carrying a local anesthetic and epinephrine, infused into the fat before liposuction. It firms and swells the tissue so the cannula moves more predictably, numbs the area for hours, and constricts small blood vessels so far less blood is lost and bruising is usually lighter. It does not dissolve fat or change how much fat can safely be removed.
The consent form sits on the kitchen table, and one line keeps catching her eye: “tumescent technique.” She knows what liposuction is. She has no idea why her surgeon spent ten minutes talking about fluid, and why the nurse said the first part of the appointment would feel like “being slowly inflated.” Her question is the one almost everyone asks the night before: what does tumescent solution do, exactly, and why does so much of the procedure depend on it?
The honest answer is that the fluid is not a side detail. It is the reason modern liposuction can be done with a fraction of the blood loss that early techniques produced, the reason many people stay awake and comfortable through it, and a large part of why the bruising afterward tends to look like a fading map rather than a single dark field.
This explainer walks through the mechanism, the comfort trade-offs, the real risks, and what the weeks afterward usually hold, so that the conversation with your team starts from evidence rather than internet folklore.
What does tumescent solution do, in plain language?
The word tumescent simply means swollen and firm. A tumescent solution is dilute salt water (normal saline or a balanced electrolyte fluid) with two active ingredients added: a local anesthetic, most often lidocaine, and epinephrine, which is the pharmaceutical form of adrenaline. Many surgeons also add a small amount of sodium bicarbonate, a buffering agent that makes the fluid less acidic and therefore less stinging on the way in.
Before any fat is removed, the surgeon infuses this fluid into the layer of fat under the skin until the area becomes taut, pale and cool to the touch. The volume is deliberately generous. In many techniques the amount of fluid infused is similar to, or larger than, the amount of fat the surgeon expects to remove, according to descriptions of the method from the Cleveland Clinic and MedlinePlus.
Three things happen at once. The tissue swells, which lifts the fat away from the muscle beneath and spreads it into a firmer, more even layer that a cannula (the thin hollow tube used to suction fat) can pass through smoothly. The anesthetic bathes the nerve endings in that layer, so sensation fades. The epinephrine narrows the small blood vessels running through the fat, so when the cannula moves, very little blood follows it.
The fluid does not melt fat, shrink skin or change the physics of how much tissue can be safely removed in one session. Those limits are set by your anatomy and by the judgment of your treating team. What the solution does is make the removal cleaner, calmer and more controlled, which is why nearly every form of liposuction performed today uses some version of it, whether the patient is awake or under general anesthesia.
What actually happens during tumescent infiltration
Infiltration is the slow part, and knowing that in advance makes it easier to tolerate. After the skin is cleaned and the surgeon marks the area, a few very small incisions are made, usually in creases or spots that are easy to hide. Through these, a blunt infiltration cannula is passed into the fat and the solution is delivered, typically by a pump that controls the rate.
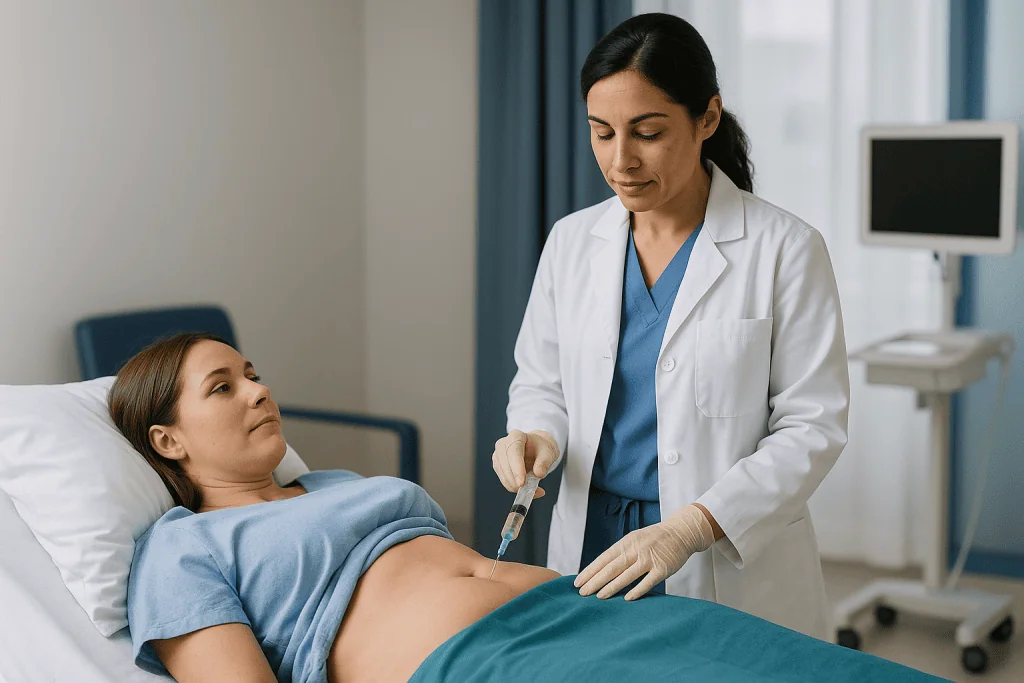
People commonly describe a cool pressure that builds into a feeling of fullness, as if the area were being filled like a water balloon. The first few seconds in each new spot may sting before the anesthetic takes hold; buffered solutions are used partly to soften that moment. Once a region is numb, the surgeon can continue filling adjacent tissue through territory that no longer registers much.
The surgeon then waits. This pause, often described as the time it takes for the tissue to become fully firm and blanched, lets the epinephrine constrict the vessels and the anesthetic saturate the nerves. Rushing this step undermines everything the fluid is meant to achieve. Teams vary in how long they wait, so the typical interval is something to ask your own surgeon rather than take from a general article.
Only after that does suction begin. A separate, finer cannula is moved back and forth through the firmed fat in overlapping tunnels while the vacuum draws the fat and some of the fluid into a canister. The aspirate, the material collected, is often strikingly pale yellow when the technique has worked well, with a thin layer of blood-tinged fluid rather than the deep red that early liposuction without infiltration produced. MedlinePlus notes that less blood is lost with the tumescent approach, which is the single biggest safety gain the method brought.
How the solution reduces bleeding and bruising
The mechanism here is worth understanding because it explains both the benefit and one of the risks. Epinephrine acts on receptors in the walls of small arteries and capillaries, causing the muscle in those walls to tighten. The vessel diameter shrinks, blood flow through the fat drops sharply, and the tissue turns pale. Fat is richly supplied with these tiny vessels, so without constriction the cannula would shear through many of them with each pass.
Bruising is simply blood that has leaked from torn vessels into the surrounding tissue, where it breaks down over days and changes color as it goes. Less bleeding during the procedure means less blood sitting in the tissue afterward, so the bruises that do form are usually smaller and lighter. The fluid also contributes mechanically. A firm, swollen layer compresses the small vessels from the outside, and the surgeon can see and feel the plane of fat more clearly, which reduces accidental passes into deeper or more vascular tissue.
There are two honest caveats. First, bruising is not eliminated. Some blood will always escape, and people who bruise easily in daily life tend to bruise more after liposuction too. Second, the epinephrine effect fades over hours. A small amount of oozing of blood-tinged fluid from the incisions in the first day or two is expected; the Cleveland Clinic and Mayo Clinic both describe this as a normal part of early recovery rather than a complication.
What the evidence does not support is the claim that tumescent technique makes liposuction a “bloodless” or “no-downtime” procedure. The reduction in blood loss is real and clinically meaningful. The idea that there is nothing to recover from is marketing, not medicine.
Comfort: how the numbing works and how long tumescent lidocaine lasts
Lidocaine works by blocking sodium channels on nerve fibers, the tiny gates that have to open for a pain signal to travel. When enough of the drug surrounds a nerve ending, the signal never leaves the tissue. In tumescent solution the anesthetic is extremely dilute, far weaker than the concentration a dentist uses, but the sheer volume means it reaches every nerve in the treated fat.

Two features of this setup change how long the effect lasts. Fat has relatively poor blood flow, so drugs sit in it rather than being whisked away. The epinephrine then constricts the vessels further, slowing absorption into the bloodstream even more. The practical result is that numbness in the treated area commonly persists for many hours after the procedure, often well past the point when a person has gone home, and gradually gives way to soreness rather than switching off abruptly. The exact window varies with the area treated, the concentration used and the individual, so the right figure is the one your team gives you for your plan.
This slow absorption is also a safety feature. It means the peak level of lidocaine in the blood arrives late and stays relatively low, which is what allows the total amount in the solution to be larger than would be safe if injected rapidly into a single spot. That total is a decision for the surgeon and anesthesia team, calculated against body weight and health status; it is never something a patient should attempt to interpret from online sources.
When the numbness lifts, what most people describe is a deep, bruised ache, similar to the day after an unusually hard workout, concentrated where the cannula moved most. The Mayo Clinic lists pain and soreness among the expected early effects, managed with whatever the treating team prescribes or recommends. Comfort medication choices belong to that team.
Awake liposuction with local anesthesia versus sedation or general anesthesia
One of the most common confusions is between the tumescent solution and the type of anesthesia. The solution is used in almost all liposuction today. What varies is what else is layered on top of it.
In fully awake tumescent liposuction, the dilute local anesthetic in the fluid is the only anesthesia. The person is conscious, can talk, and can sometimes shift position on request, which some surgeons value for assessing contour. The trade-off is that infiltration is felt more vividly, treatment is generally limited to smaller or fewer areas per session, and the experience depends heavily on temperament. Anxiety amplifies sensation.
With sedation, medication given by mouth or intravenously relaxes the person or produces a light sleep while the tumescent fluid still provides the numbing. This blunts the memory of infiltration and suits people treating moderate areas who would find being fully alert stressful.
Under general anesthesia the person is unconscious throughout. The tumescent solution is still infused, but its purpose shifts toward bleeding control, tissue firmness and lasting post-operative comfort, since the anesthetic in the fluid continues working after the person wakes. The Mayo Clinic and Cleveland Clinic both describe liposuction as being performed with local, sedation or general anesthesia depending on the extent of treatment.
No approach is universally superior. General anesthesia carries its own set of risks, requires an anesthesia professional and an appropriately equipped facility, and lengthens the immediate recovery. Fully awake treatment avoids those but is unsuitable for extensive or multi-area work. The decision rests on how much is being treated, your medical history, your own preferences about being awake, and the setting your team works in.
Tumescent fluid ingredients: what each component does
Different surgeons mix their solution slightly differently, and the concentrations are a clinical decision that this article deliberately does not cover. The roles of the ingredients, however, are consistent, and understanding them helps the rest of the explanation fall into place.
| Component | What it does | What you may notice |
|---|---|---|
| Normal saline or balanced electrolyte fluid | Carries the drugs, swells and firms the fat layer, lifts fat away from muscle, improves cannula glide | Cool pressure and fullness during infiltration; clear or pink fluid leaking from incisions for a day or two |
| Lidocaine (local anesthetic) | Blocks nerve signaling in the treated layer; absorbed slowly from fat so numbness is prolonged | Numbness that lasts for hours after the procedure, fading into soreness |
| Epinephrine | Constricts small blood vessels, reducing bleeding and bruising and slowing drug absorption | Pale, cool skin over the area; occasionally a brief racing heartbeat or jitteriness as a small amount enters the circulation |
| Sodium bicarbonate (optional buffer) | Raises the pH of the acidic anesthetic solution, reducing stinging and helping the anesthetic act faster | Less burning during the first seconds of infiltration |
A note on the epinephrine effect. Because the drug is the same molecule your body releases under stress, a small systemic dose can produce a fluttery heart, tremor or a sense of nervousness during infiltration. Teams expect this, monitor for it, and ask about heart conditions and certain medications beforehand precisely because of it. Mention anything unusual you feel during the procedure; it is useful information, not a complaint.
Some practices add other agents, and some use variations on the base fluid. Ask your team what is in your solution and why. A clear answer is a reasonable expectation.
Who tumescent liposuction is usually for, and who is asked to wait
Liposuction is a body-contouring procedure, not a weight-loss treatment, and the tumescent technique does not change that. The Mayo Clinic describes the typical candidate as someone close to a stable weight with localized fat deposits that have not responded to diet and exercise, with reasonably firm, elastic skin and no medical conditions that would make surgery or anesthesia unsafe. The NHS adds that it is not a treatment for obesity, and that the fat removed does not prevent fat gain elsewhere if weight rises later.
Skin quality matters more than people expect. The fluid firms the fat, but it does nothing for the skin above it. Where skin has lost elasticity, removing the fat beneath can leave looseness or rippling. Surgeons sometimes recommend a different procedure, or combining approaches, for that reason.
Several groups are usually asked to wait or to consider alternatives. People who smoke are often asked to stop well in advance because nicotine impairs healing and raises the risk of skin complications. Anyone whose weight is still changing significantly is typically advised to reach a stable point first, since contouring a moving target gives unpredictable results. Pregnancy and recent childbirth are reasons to defer. Bleeding disorders, use of blood-thinning medication, poorly controlled diabetes, significant heart or lung disease, and some liver conditions that affect how lidocaine is cleared all require careful review and may rule the procedure out or change the anesthetic plan.
Medication review is part of this. Some drugs interact with lidocaine metabolism and some increase bleeding risk. Never stop or change a prescribed medicine because of an upcoming procedure without instruction from the prescribing clinician; the surgical team and your regular prescriber should coordinate that.
Finally, expectations are a screening criterion in their own right. Someone hoping for a dramatic weight change, or for the procedure to fix how they feel about their body more broadly, is often gently redirected. That is good practice, not gatekeeping.
How painful is awake tumescent liposuction, really?
Pain is personal, and any article that promises a single answer is overselling. What can be said is where discomfort tends to cluster and why.
During infiltration, the first contact in each new region stings or burns briefly before the anesthetic works. Pressure then dominates. People often rate this phase as uncomfortable but tolerable, and buffering the solution is used specifically to blunt the sting. If sedation is part of the plan, this stage is largely blurred or forgotten.
During suction, properly infiltrated tissue should feel like tugging, vibration or deep pressure rather than sharp pain. If a person who is awake feels a sharp or burning sensation, it usually means the cannula has reached tissue that is not yet fully numb, and the surgeon can add more solution or adjust. Speaking up is expected and helps the procedure, which is one argument surgeons make for the awake approach.
Afterward, the picture changes. The prolonged numbness from the dilute lidocaine means the first several hours are often surprisingly quiet. Soreness builds as it wears off and tends to peak over the first couple of days, described by most people as a severe bruise or deep muscle ache, worse with movement and when pressure is applied. The Cleveland Clinic lists pain, swelling and bruising as the expected early effects and notes that comfort medication is typically prescribed; the choice of medication is the treating team’s.
Factors that push the experience toward the harder end include larger treatment areas, fibrous regions such as the back or male chest, high baseline anxiety, and previous surgery in the same area. Smaller, softer regions and a calm, well-informed patient tend toward the easier end. Discuss your own pain history openly during the consultation; it shapes the anesthetic plan.
Risks that come specifically from the tumescent solution
Most liposuction complications relate to the surgery itself: infection, contour irregularities, fluid collections, numbness, skin changes and, rarely, injury to deeper structures or blood clots. MedlinePlus and the Mayo Clinic list these in detail. A smaller set of risks stems from the fluid, and these deserve their own plain explanation.
The first is local anesthetic toxicity. Although slow absorption from fat keeps blood levels low, the total amount of lidocaine infused in a large case is substantial, and the peak can arrive hours later. Early warning signs include a metallic taste, ringing in the ears, numbness around the mouth, light-headedness, confusion or twitching. Severe toxicity can cause seizures and heart rhythm problems. This is why teams calculate the total against body weight and health, why certain liver conditions and medications matter, and why large treatment plans are often split across sessions rather than crammed into one.
The second is fluid balance. A large volume of saline enters the body; some is removed with the fat, some leaks from the incisions over the following days, and the rest is absorbed into the circulation. In healthy people the kidneys handle this. In those with heart or kidney disease, or when very large volumes are combined with intravenous fluids under general anesthesia, fluid overload becomes possible. Careful accounting of what went in and what came out is standard practice.
The third is the epinephrine itself, which can raise heart rate and blood pressure. People with certain heart conditions or on specific medications need their plan adjusted.
Infection risk is reduced by sterile technique but never zero, and a warm, red, increasingly painful area or fever after the procedure needs assessment rather than watchful waiting. The relative safety of the tumescent approach depends on these details being handled well, which is a reason to ask your team directly how they monitor each of them.
Tumescent liposuction recovery time: what the following days and weeks usually look like
Recovery has a fairly recognizable shape, even though its length varies with how much was treated and how an individual heals.
In the first day or two, numbness fades into soreness and the incisions often leak clear, pink or lightly blood-tinged fluid. This is retained tumescent solution finding its way out, and teams usually advise absorbent pads under the compression garment for this reason. Swelling increases rather than decreases at first; the body adds its own inflammatory fluid on top of what was infused. Walking gently around the house is generally encouraged from the first day because it supports circulation and lowers the risk of blood clots.
Over the first week or two, bruising goes through its color changes and begins to fade, the leaking stops, and many people return to desk-based work. The Cleveland Clinic notes that many people are back to normal routines within a few days to a couple of weeks depending on the extent of treatment, while strenuous exercise is usually held back longer. A compression garment is typically worn for several weeks; the NHS describes this as part of standard aftercare to limit swelling and support the new contour.
Swelling is the slow variable. The Mayo Clinic notes that it typically subsides within a few weeks, by which point the area looks less bulky, but that the final, leaner appearance can take several months to emerge. The NHS gives a similar window, advising that it may take up to about six months for the area to settle fully. Firm, lumpy patches during this period are common as the tissue heals and usually soften with time; your team may suggest gentle massage or simply patience.
None of these timelines is a promise. They are typical ranges from mainstream sources, and the only version that matters for you is the one your treating team gives after seeing your plan and your progress.
Is tumescent liposuction worth it? An honest way to think about results
Nobody can answer this for you, and anyone who claims a percentage of satisfied patients is usually quoting a number without a traceable source. What can be laid out is the structure of the trade-off.
The gain is a change in shape in specific areas, not a change in weight or health. Liposuction removes fat cells from a region, and those particular cells do not return. If weight stays stable, the contour change is durable. If weight rises, fat accumulates in remaining cells throughout the body, including the treated area, and the proportions can shift. The Mayo Clinic is explicit that results are long-lasting only as long as weight is maintained.
The costs, in the non-financial sense, are the recovery period described above, the small but real surgical risks, the chance of contour irregularities or asymmetry that may need revision, altered sensation that sometimes lingers for months, and the possibility that skin does not retract as hoped. Scars from the small incisions usually fade but do not vanish.
The tumescent technique improves the terms of this trade rather than changing its nature. It lowers blood loss, often allows lighter anesthesia, and tends to produce less bruising. It does not make the result better than the surgeon’s skill and your anatomy allow.
A useful test: picture the realistic outcome your surgeon describes, including the worst plausible version, and ask whether you would still want it after a difficult first week and six months of waiting for swelling to resolve. If the answer is clearly yes, that is as close to “worth it” as evidence can get. If the answer depends on the result being perfect, it may be wiser to pause. Alternatives, from doing nothing to non-surgical fat reduction to surgical procedures that also address skin, each have their own evidence base and are worth asking about.
What people often get wrong about tumescent solution
The myths here are persistent, partly because the word itself sounds more technical than it is. A few corrections, each grounded in how the fluid actually behaves.
“The solution dissolves the fat.” It does not. Fat is removed mechanically by suction. The fluid swells and numbs the tissue and constricts vessels; chemically, it leaves fat cells intact.
“Tumescent means a different, newer kind of liposuction.” It describes a preparation step, not a separate device or category. Energy-based tools such as ultrasound, laser or power-assisted cannulas are used after tumescent infiltration, not instead of it. Someone offered a “non-tumescent” alternative should ask exactly what that means.
“If it is tumescent, there is no real downtime.” Reduced bleeding and bruising shorten and soften recovery; they do not remove it. Swelling and soreness still follow, and the final result still waits on months of settling.
“Awake means it is minor surgery.” The anesthetic approach reflects the extent of treatment and patient preference, not the seriousness of the procedure. Fat is still being removed from the body through surgical incisions, with all the usual implications for infection, clots and healing.
“More fluid means more fat can be removed safely.” The limits on how much fat can be removed in one session relate to blood loss, fluid shifts and anesthetic totals, not to how swollen the tissue becomes. More fluid raises some of those risks rather than lowering them.
“The numbness lasting a day means something went wrong.” Prolonged numbness is the expected behavior of a dilute anesthetic absorbed slowly from fat. Numbness or altered sensation that persists for weeks is also common and usually settles, though it should be mentioned at follow-up. Sudden new numbness, or numbness with spreading pain, is a different matter and belongs in the red-flag section below.
Questions to ask your care team
A good consultation leaves you knowing not just what will happen but why each choice was made. These questions are phrased to invite explanation rather than a yes or no.
- What is in the tumescent solution you use, and why do you include each component?
- How do you decide the total amount of local anesthetic for someone of my size and health, and how will I be monitored for signs of toxicity during and after the procedure?
- Will I be fully awake, sedated or under general anesthesia, and what made you recommend that for my plan?
- How much fluid will be infused, how is it tracked against what is removed, and does my medical history change that calculation?
- Which of my current medications or supplements affect bleeding or the way lidocaine is cleared, and who will coordinate any changes with my regular prescriber?
- Roughly how long should I expect numbness to last afterward, and what should the first night feel like?
- How many areas are you treating in one session, and would you ever split this across sessions for safety?
- What does your typical recovery timeline look like, and how long will I wear a compression garment?
- What contour problems or skin changes are realistic risks for my anatomy, and how are revisions handled if they occur?
- Who do I call, at any hour, if I notice something worrying in the first week?
Write the answers down. The value is not only in hearing them but in being able to compare what you were told against what you experience, so that anything unexpected gets reported early rather than explained away.
If any question is met with impatience or vagueness, treat that as information. The procedure is elective, the timeline is yours, and the standard for a team you trust with your body should include being willing to explain the fluid they are about to put into it.
When to call your doctor
Most of the early course after tumescent liposuction is uncomfortable but predictable: soreness, swelling, leaking fluid and colorful bruises. A smaller set of signs means something may be going wrong and needs prompt assessment rather than waiting for the scheduled follow-up. Your team should give you a direct number; use it.
Seek emergency care immediately for chest pain, sudden shortness of breath, coughing up blood, fainting, a seizure, severe confusion or an irregular or very fast heartbeat. These can signal a blood clot that has traveled to the lungs, a fluid or heart problem, or, in the hours after the procedure, local anesthetic toxicity.
Call the same day for signs that suggest anesthetic toxicity developing more gradually: a persistent metallic taste, ringing in the ears, numbness or tingling around the mouth, light-headedness, muscle twitching or unusual drowsiness. Also call the same day for calf pain, warmth or swelling in one leg, which can indicate a clot before it travels.
Contact your team promptly, within a day, for a fever, chills, an area that is becoming more red, hot, hard or painful rather than less, pus or foul-smelling drainage from an incision, bleeding that soaks through dressings and does not slow with pressure, a rapidly enlarging swelling on one side, skin over the treated area turning dark, dusky or blistered, or pain that is escalating despite the medication you were given.
Mention at follow-up, without urgency, lumpy or firm areas, lingering numbness, mild asymmetry and emotional lows in the first weeks, all of which are common and usually settle but are worth tracking.
The threshold for calling should be low. Teams would far rather hear about a symptom that turns out to be ordinary than learn later about one that was not. Every decision about what to do next belongs to the clinicians who treated you and can examine you.
Frequently asked questions
What does tumescent solution do during liposuction?
It prepares the fat for removal. Infused in large volume, the dilute saline swells and firms the fat layer so the cannula glides evenly, the local anesthetic numbs the nerve endings for hours, and the epinephrine constricts small blood vessels so far less blood is lost. The fluid does not dissolve fat; removal is still mechanical, by suction, after the tissue has been prepared.
How long does tumescent lidocaine last after the procedure?
Numbness in the treated area commonly persists for many hours after liposuction, often well into the evening or beyond, because the dilute anesthetic is absorbed slowly from fat and epinephrine slows that absorption further. It fades gradually into soreness rather than stopping abruptly. The exact duration depends on the area, the concentration used and the individual, so ask your treating team what to expect for your plan.
How painful is awake liposuction with local anesthesia?
Most people describe infiltration as a brief sting followed by cool pressure and fullness, and the suction phase as tugging or deep pressure rather than sharp pain when the tissue is fully numb. Sharp or burning sensations usually mean more solution is needed, and speaking up helps. Soreness builds after the numbness fades and typically peaks over the first couple of days, feeling like a deep bruise or heavy muscle ache.
Is tumescent liposuction worth it?
Only you can decide, because the trade is a durable change in shape in specific areas against a recovery period, surgical risks and the chance of contour or skin irregularities. The tumescent technique improves the terms by reducing bleeding and bruising and often allowing lighter anesthesia, but it does not change the nature of the procedure. Results last only while weight stays stable, as the Mayo Clinic notes.
What are the tumescent fluid ingredients?
The base is normal saline or a balanced electrolyte fluid. To this are added a local anesthetic, most commonly lidocaine, and epinephrine, which constricts blood vessels. Many surgeons include sodium bicarbonate, a buffer that reduces stinging and speeds the anesthetic’s onset. Exact concentrations are a clinical decision tailored to the individual and are not something to interpret from general sources.
Why does the skin look pale and feel cold after infiltration?
That is the epinephrine working. It narrows the small vessels in the skin and fat, reducing blood flow so the area blanches and cools. Surgeons often wait for this change before starting suction because it signals that bleeding control is in place. The color and warmth return over the following hours as the drug wears off, which is also when some mild oozing from the incisions becomes expected.
Why is fluid leaking from my incisions after tumescent liposuction?
Clear, pink or lightly blood-tinged fluid draining for a day or two is retained tumescent solution and inflammatory fluid finding its way out through the small incisions. Both the Cleveland Clinic and Mayo Clinic describe this as a normal early feature, and teams usually advise absorbent pads under the compression garment. Drainage that is bright red and does not slow with pressure, or that becomes thick, cloudy or foul-smelling, should be reported promptly.
What is the tumescent liposuction recovery time?
Soreness and leaking dominate the first few days, bruising fades over the first week or two, and many people return to desk work within a few days to a couple of weeks depending on the extent treated, according to the Cleveland Clinic. Compression garments are usually worn for several weeks. The Mayo Clinic notes that swelling typically subsides within a few weeks, while the final contour can take several months to appear.
Can the tumescent solution cause lidocaine toxicity?
It can, which is why the total amount is calculated carefully against body weight and health, why liver conditions and certain medications are reviewed, and why large plans are sometimes split across sessions. Slow absorption from fat keeps blood levels low, but the peak can arrive hours later. A metallic taste, ringing ears, numbness around the mouth, light-headedness, confusion or twitching after the procedure should prompt an immediate call to your team.
Does tumescent liposuction mean I will not need general anesthesia?
Not necessarily. The tumescent solution provides numbing and bleeding control in nearly every liposuction procedure, but what is added on top varies. Small areas are sometimes treated fully awake, moderate ones often with sedation, and extensive or multi-area work frequently under general anesthesia. The choice depends on how much is being treated, your medical history and your own preferences, and it rests with your surgical and anesthesia team.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is Classic Liposuction Right for You? Skin Elasticity, Stable Weight and Realistic Areas
A typical classic liposuction candidate is an adult at or near a stable weight for several months, with localized fat pockets that resist diet…
How Monsplasty Is Performed: Liposuction, Skin Removal and Where the Incision Sits
Monsplasty reshapes the mons pubis, the soft fatty mound over the pubic bone, using one of two approaches or both together. Liposuction removes excess…

Who Is a Candidate for Vaginoplasty? Childbirth Changes, Symptoms and Surgical Timing
A candidate for vaginoplasty is usually someone who has finished childbearing, has persistent looseness or bulging of the vaginal wall (often after vaginal birth),…

What Are the Risks of Monsplasty? Swelling, Numbness and the Signs Worth Reporting Early
Monsplasty risks are mostly the ordinary risks of any skin-and-fat contouring operation: swelling that can last for months, temporary or occasionally lasting numbness, bruising,…
Pectoral Augmentation Recovery: When Chest Training Can Restart Without Risking the Implant
After pectoral augmentation, surgeons typically ask patients to avoid direct chest training for roughly six to eight weeks. Gentle walking usually starts within a…

Tumescent vs Traditional Liposuction: What the Diluted Anesthetic Changes for Patients
Tumescent liposuction infiltrates the fat layer with a large volume of very dilute local anesthetic, a blood-vessel-constricting agent and saline before fat is suctioned,…