

When Is Catheter Carotid Angiography Recommended After Ultrasound Shows Narrowing?

Key Takeaways
- Duplex ultrasound estimates carotid narrowing from blood velocity and is the standard first test, but it cannot see through dense calcium, above the jaw, or reliably separate a near-blocked artery from a fully blocked one.
- Catheter angiography is now reserved for specific gaps: disagreement between ultrasound and CT or MR angiography, the near-occlusion versus occlusion question, and planning or performing carotid stenting.
- The NHS states that surgery is generally considered after a stroke or TIA when the artery is narrowed by 50 percent or more, ideally within 2 weeks of symptoms, and puts the operation's own stroke risk at around 2 in 100.
- A 70 percent narrowing that has caused symptoms is treated far more urgently than a silent 70 percent narrowing, because recent symptoms signal an unstable plaque.
- The most feared complication of catheter angiography is procedural stroke, listed by MedlinePlus alongside puncture-site bleeding, dye allergy and kidney injury, which is why the test is ordered only when the answer would change management.
- No guideline body recommends carotid screening of the general population at any age; imaging is triggered by symptoms, a neck bruit, or a high vascular risk profile.
Catheter carotid angiography is usually reserved for situations where ultrasound and a second noninvasive scan, such as CT or MR angiography, disagree or cannot answer a key question: whether an artery is nearly blocked or fully blocked, how severe the narrowing truly is before surgery or stenting, or whether disease extends into vessels ultrasound cannot see. For most people, noninvasive imaging alone is enough, and the treating team makes the call.
The ultrasound room was quiet except for the whoosh of blood turned into sound. Margaret, 68, had come in because her doctor heard a faint rushing noise in her neck during a routine visit. Forty minutes later she left with a phrase she had never heard before, moderate to severe stenosis, and a follow-up appointment with a vascular specialist. On the drive home the questions piled up. Did she need surgery? Was a stroke coming? And why had the technologist mentioned that a catheter test might be next?
That last question is the one this article answers. Knowing when carotid angiography is needed, and when it is not, matters because the catheter version is an invasive test with a small but real stroke risk of its own. It has become a tool for specific unanswered questions rather than a routine next step.
What follows explains what ultrasound can and cannot show, how the other scans compare, and which findings push a team toward the catheter lab.
What an ultrasound can and cannot tell you about carotid narrowing
The two carotid arteries run up either side of the neck and carry most of the blood the front of the brain uses. Stenosis simply means narrowing, and in the carotids it is almost always caused by plaque, a buildup of cholesterol, calcium and scar tissue inside the artery wall. Duplex ultrasound is the usual first test because it is painless, radiation-free and quick. It combines two things: a grayscale picture of the vessel wall and a Doppler measurement of how fast blood is moving through it.
Speed is the clue. Blood squeezing through a narrowed segment accelerates, much like water through a pinched garden hose, so higher velocities point to tighter narrowing. Labs translate those velocities into ranges, typically reported as under 50 percent, 50 to 69 percent, 70 percent or more, or near-occlusion. Mayo Clinic describes ultrasound as the standard starting point for anyone with a suspected carotid problem.
The test has known blind spots. Heavy calcium in the plaque casts an acoustic shadow that hides the channel beneath it. A very high or deep branching point can sit beyond the probe’s reach. A tight narrowing on one side can make the other side look worse than it is because more blood is being pushed through it. Ultrasound also struggles to tell a hair-thin trickle of flow from a completely closed artery, and that difference changes management entirely. Finally, it sees only the neck. Disease higher up, inside the skull, or lower down near the chest is out of view.
So an ultrasound result is a strong signal, not a final verdict. When the reading lands in a range where treatment decisions change, most teams want a second look with a different method before acting.
When is carotid angiography needed after an ultrasound shows narrowing?
The honest answer is: less often than it used to be. Catheter angiography was once the required step before any carotid operation, because the major surgical trials measured narrowing on those images. Over the past two decades CT angiography (CTA) and magnetic resonance angiography (MRA) have taken over most of that confirming role. A catheter study now tends to be requested for a handful of specific reasons.
The first is disagreement. If ultrasound suggests severe narrowing but CTA or MRA suggests moderate, or the two tests differ by a whole category, the team needs a tiebreaker before recommending an operation that carries its own stroke risk.
The second is the occlusion question. Ultrasound and even CTA can find it hard to distinguish a near-occlusion, where a thread of blood still passes, from a total block. Surgery or stenting can help with the former and generally cannot with the latter. Catheter angiography, which watches contrast dye flow in real time, is the most reliable way to settle it.
The third is planning. When carotid stenting is being considered, the interventional team needs a detailed map of the aortic arch, the bends in the artery and the vessels inside the skull. Often the diagnostic angiogram and the stent placement happen in the same session.
The fourth is uncertainty that noninvasive scans cannot resolve: suspected tandem lesions (a second narrowing further along the same artery), unusual anatomy, a dissection (a tear in the artery wall), or when kidney function or a pacemaker rules out CTA or MRA. Outside those situations, MedlinePlus and Mayo Clinic both describe angiography as an option rather than a routine requirement, and the decision belongs to the treating team.
How catheter carotid angiography actually works
Picture a very thin, flexible tube, narrower than a drinking straw, guided through the body’s arterial highway system. That tube is the catheter. The physician, usually an interventional radiologist, neurointerventionalist or vascular specialist, numbs a spot at the groin or wrist and slides the catheter into the artery there. Using live X-ray, called fluoroscopy, they steer it up through the aorta, the body’s main artery, until its tip rests near the base of the carotid.
Contrast dye, an iodine-based liquid that shows up bright on X-ray, is injected through the catheter while rapid images are taken. A computer then subtracts everything that was in the picture before the dye arrived, leaving only the vessel outline. This is digital subtraction angiography, and it is why the images look like a stark black-and-white roadmap. Because the dye is filmed as it travels, the team sees not just the shape of the narrowing but how blood actually moves through and beyond it, including the smaller branches inside the skull.
People are awake for the study, usually with a light sedative. MedlinePlus notes that the injection often produces a brief warm flush or a metallic taste, and that the head may feel hot for a few seconds. The catheter itself is not felt once it passes the puncture site, because arteries have no pain nerves inside them.
Afterward the catheter is withdrawn and the puncture is sealed with firm pressure or a small closure device. The whole study typically takes under an hour of imaging, though preparation and recovery add several more. What separates this test from the others is not the picture quality alone but that it is dynamic, direct and, when needed, can flow straight into treatment.
Carotid angiogram vs ultrasound: what each test measures
These two tests answer related questions in different languages. Ultrasound infers narrowing from velocity; angiography measures it directly by comparing the width of the tightest point against the width of the normal artery beyond it. That direct measurement is the method the large surgical trials used, which is why angiography is still the reference standard against which the others are judged.
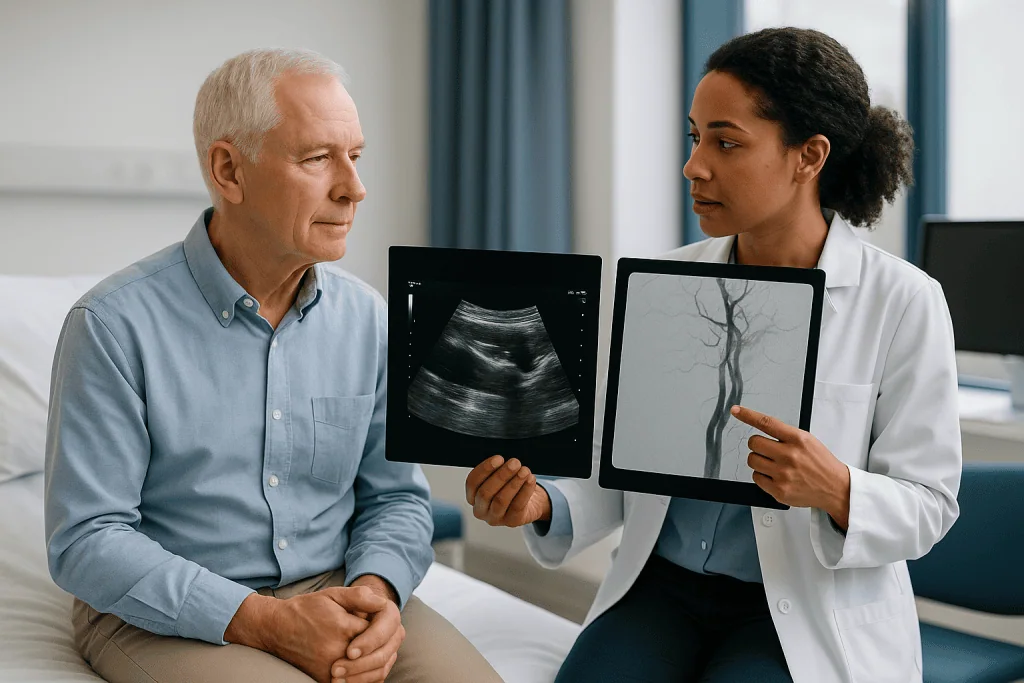
Ultrasound wins on safety and access. There is no needle in an artery, no dye, no radiation, and it can be repeated every year to watch a plaque over time. It also gives some information about plaque texture, such as whether it looks soft or ulcerated, that a pure vessel outline cannot. What it cannot do is see through dense calcium, look above the jaw or below the collarbone, or reliably separate a trickle from a total block.
Angiography wins on completeness. It shows the arch, the neck, the intracranial vessels and the collateral pathways that may be feeding the brain around a blockage. It confirms exact severity. The price is invasiveness: a puncture, contrast exposure and a small risk that the catheter dislodges plaque and causes the very stroke everyone is trying to prevent.
Neither is simply better. Johns Hopkins describes cerebral angiography as a test chosen when other imaging has not given enough detail to guide treatment. The practical relationship is sequential: ultrasound screens and monitors, noninvasive angiography confirms, and catheter angiography resolves what remains unclear or is needed for a procedure. Someone whose ultrasound and CTA agree on moderate narrowing with no symptoms usually stops at the second step and moves to risk-factor management and surveillance.
CTA vs catheter angiography: why noninvasive imaging usually comes first
CT angiography uses a scanner and an intravenous dye injection to build a three-dimensional picture of the arteries in about the time it takes to hold a few breaths. MR angiography does something similar using magnets rather than X-rays, sometimes without any dye at all. Both are noninvasive: nothing goes inside an artery. That is the core reason they come before a catheter study for almost everyone. Mayo Clinic lists all three, plus ultrasound, as tools a doctor may use, chosen according to what remains uncertain.
| Test | How it sees the artery | Radiation | Contrast dye | Typical role |
|---|---|---|---|---|
| Duplex ultrasound | Sound waves and blood velocity | None | None | First test, ongoing surveillance |
| CT angiography | X-ray cross-sections rebuilt in 3D | Yes | Iodine, into a vein | Confirms severity, shows arch to skull |
| MR angiography | Magnetic signal from moving blood | None | Sometimes, into a vein | Alternative when CT dye or radiation is a concern |
| Catheter angiography | Dye filmed in real time inside the artery | Yes | Iodine, into the artery | Tiebreaker, occlusion question, procedure planning |
CTA can overstate narrowing when calcium is heavy, because bright calcium blooms on the image. MRA can exaggerate narrowing where flow becomes turbulent. Catheter angiography has neither problem, but it can understate severity if the plaque is oval and the X-ray is taken from an unlucky angle, which is why several views are filmed.
Kidney function shapes the choice. Both CTA and catheter studies use iodinated dye, which stresses the kidneys, so blood tests are checked beforehand. A metal implant may rule out MRA. When one door closes, another opens, and the team picks the path that answers the question with the least risk.
Who is usually offered catheter angiography, and who is usually asked to wait
The people most likely to be offered a catheter study share one feature: a decision about surgery or stenting is on the table and the noninvasive scans have left a gap. That includes someone who has had a transient ischemic attack (TIA, a temporary stroke-like episode whose symptoms resolve, by NHS definition, within 24 hours) or a minor stroke, whose ultrasound says severe narrowing but whose CTA says moderate. It includes a person whose scans hint at near-occlusion. It includes anyone being lined up for carotid stenting, since the arch and intracranial anatomy must be mapped, and the diagnostic run often doubles as the first step of the procedure.
Less common candidates are those with suspected dissection, fibromuscular dysplasia (an uncommon condition that causes beaded narrowing in medium arteries), or a suspected blockage inside the skull that CTA could not characterize.
Who is usually asked to wait, or never needs the test at all? Someone with no symptoms and narrowing under 50 percent on ultrasound; the NHS notes that surgery is generally not offered at this level even after symptoms, so confirming exact numbers changes nothing. Someone whose ultrasound and CTA or MRA already agree, because a third test adds risk without adding information. Someone whose kidneys are fragile or who has a known severe dye allergy, for whom MRA or careful clinical follow-up may be safer. And anyone too frail or unwell for an operation, since a test whose only purpose is to plan that operation has no purpose.
None of these are rigid rules. A treating team weighs symptoms, imaging, other illnesses and the person’s own priorities. The point is that the catheter lab is a destination reached through a specific need, not a default stop on the way from ultrasound to treatment.
How serious is a 70 percent blockage in a carotid artery?
Seventy percent is the number people remember from the report, and it deserves a careful answer. In the language of these tests, it means the tightest point of the artery is about 70 percent narrower than the normal segment beyond it. That is classified as severe. But severity of the picture and urgency of the situation are not the same thing, and the missing variable is symptoms.
If a 70 percent narrowing has recently caused a TIA or stroke on the matching side, the artery has shown it can shed clot or debris to the brain. The major surgical trials found the greatest benefit from removing plaque in exactly this group, and the NHS advises that when surgery is indicated after symptoms it should ideally happen within 2 weeks, because the risk of a second event is highest in that window.
If the same 70 percent narrowing has never caused symptoms, the calculus changes. Mayo Clinic notes that many people with carotid disease have no warning signs until a stroke or TIA occurs, so the finding still matters. Yet the yearly stroke risk from an asymptomatic plaque is lower, and it has fallen further as cholesterol-lowering and antiplatelet medicines have improved. Guideline bodies now weigh surgery against intensive medical management rather than treating the number alone as a trigger. Plaque features, such as an irregular or ulcerated surface, and whether the narrowing is progressing between scans, feed into that judgment.
Two practical implications follow. A 70 percent reading from ultrasound alone is usually confirmed with CTA or MRA before anyone talks about an operation. And the conversation that follows is about your overall risk, not about hitting a threshold. The treating team, not the report, decides what happens next.
At what point do you need carotid artery surgery?
Carotid endarterectomy is an operation in which a surgeon opens the artery in the neck and removes the plaque. Carotid stenting is a catheter-based alternative that props the narrowing open with a small metal mesh tube. Both aim to lower future stroke risk; neither treats the symptoms of a stroke that has already happened.
The NHS sets out the broad triggers. Surgery is generally considered when a person has had a stroke or TIA and the artery on that side is narrowed by 50 percent or more. Below 50 percent, the operation’s own risks tend to outweigh the benefit even after symptoms. For people with no symptoms, the NHS describes surgery as an option in severe narrowing for those in reasonable health, while acknowledging the benefit is smaller and more debated.
Timing shapes the decision as much as severity. Because a recently symptomatic plaque is unstable, the NHS advises operating within 2 weeks of symptoms where possible. This is one reason a suspected TIA is treated as an emergency rather than something to mention at the next appointment.
Surgery is not risk-free. The NHS puts the chance of a stroke caused by the operation itself at around 2 in 100, with smaller risks of heart attack, nerve injury affecting voice or swallowing, and bleeding. Stenting carries a broadly similar overall risk, with different trade-offs: fewer neck complications but a somewhat higher procedural stroke risk in older people, according to the trial evidence summarized by Mayo Clinic.
Every candidate is also treated medically. Statins lower cholesterol and stabilize plaque; antiplatelet medicines make blood less likely to clot on a roughened surface; blood pressure treatment reduces the shear that damages artery walls. These continue regardless of whether an operation happens, and any change to them is a decision for the prescribing clinician.
Catheter angiography risks: what the evidence actually shows
The paradox of catheter carotid angiography is that the test used to prevent stroke can, rarely, cause one. Understanding how keeps the risk in proportion. As the catheter tip moves through arteries lined with plaque, it can dislodge a fragment, or a small clot can form on the catheter and travel to the brain. MedlinePlus lists stroke among the recognized complications of cerebral angiography, alongside bleeding or a blood clot at the puncture site, allergic reaction to the dye, kidney injury from the dye, and, very rarely, damage to the artery itself.
Most of these are uncommon, and the serious ones are rare in experienced hands using modern equipment. The stroke risk is small in absolute terms but not zero, which is precisely why noninvasive scans have taken over the confirming role. A test that carries even a modest chance of harm is justified only when it changes what happens next.
Puncture-site problems are the most frequent nuisance. A bruise the size of a palm is common and fades over one to two weeks. A tender lump, a pseudoaneurysm (a contained leak from the artery), or persistent bleeding needs assessment. Wrist access has reduced some of these issues compared with the groin, though not every anatomy suits it.
Contrast dye deserves its own note. Kidney function is checked beforehand, extra fluids are often given, and people with prior dye reactions may receive preventive treatment arranged by the team. Anyone taking a blood thinner will have those medicines reviewed in advance; the person should not stop or adjust anything on their own.
Radiation exposure is real but modest and focused. Mayo Clinic and MedlinePlus both frame the overall risk profile as acceptable when the information gained will guide an important decision, and unnecessary when it will not. That is the whole logic of restraint.
What the procedure day and the following days usually look like
The day starts with fasting for several hours, a blood test for kidney function and clotting, and a conversation about medicines, particularly blood thinners and diabetes drugs, following instructions the team gave in advance. A small intravenous line goes in, and the puncture site at the groin or wrist is cleaned and numbed. Sedation is light; most people describe the experience as strange rather than painful, with the warm flush of dye the most memorable sensation.
Imaging itself usually takes well under an hour. Recovery is where the time goes. MedlinePlus advises that after a groin puncture the person lies flat with the leg straight for several hours so the artery seals; wrist access allows sitting up sooner, with a compression band on the forearm. Nurses check the puncture site and the pulses in the foot or hand repeatedly. Drinking fluids helps flush the dye through the kidneys.
Most diagnostic studies are day cases, with discharge the same evening once the site is stable and someone is available to drive. If stenting was done in the same session, an overnight stay is typical for monitoring blood pressure and neurological checks.
Over the next few days the puncture site may bruise and feel tender. MedlinePlus suggests avoiding heavy lifting and strenuous activity for a short period, commonly around a week, and keeping the site clean and dry as instructed. Driving is usually deferred for at least a day. Results are often discussed the same day in outline, with the formal report and the treatment recommendation following at a clinic review.
A useful mindset for that review: the angiogram has answered a question, and the next conversation is about what to do with the answer. Bring your own questions, and ask for the plan in writing.
At what age should you have your carotid arteries checked?
There is no birthday at which everyone should have a carotid ultrasound. Major guideline bodies do not recommend screening the general population, because most people with narrowing found this way have mild disease that would never cause harm, and the follow-up tests and operations triggered by incidental findings carry risks of their own. MedlinePlus describes carotid disease as something typically investigated when there is a reason to look.
Those reasons fall into three groups. The first is symptoms: a TIA, a stroke, or a brief loss of vision in one eye that a clinician suspects came from the carotid. Here the ultrasound is urgent, not optional. The second is a physical sign. A bruit, the whooshing sound Margaret’s doctor heard through a stethoscope, comes from turbulent flow and prompts imaging, though many bruits turn out to be harmless and many significant narrowings make no sound at all.
The third group is risk. Mayo Clinic lists high blood pressure, smoking, diabetes, high cholesterol, obesity, a family history of atherosclerosis and increasing age as the main drivers of carotid plaque. Someone with known coronary or leg artery disease, or who is scheduled for major heart surgery, may be offered a carotid check because plaque tends to appear in more than one artery bed at once. Age raises risk steadily, and carotid disease is far more common after 60, but age alone is not a trigger in guideline language.
If a scan is done and shows mild narrowing, surveillance intervals are set by the team, often yearly, to watch for progression. The most effective carotid check for most people is not an ultrasound at all but knowing their blood pressure, cholesterol and blood sugar numbers, and acting on them.
What people often get wrong about when carotid angiography is needed
The first misunderstanding is that a catheter angiogram is the automatic next step after an abnormal ultrasound. It was, decades ago. Today it is the exception. The routine path is ultrasound, then CTA or MRA, then a decision, with the catheter lab reserved for unresolved questions or for the procedure itself.
The second is that angiography treats the artery. A purely diagnostic angiogram changes nothing about the plaque; it only maps it. Treatment comes afterward, through medicines, surgery or stenting. The confusion is understandable because stenting uses the same access and equipment, and the two are sometimes combined.
The third is that a higher percentage always means more danger. A 60 percent narrowing that caused a TIA last week is more urgent than a 75 percent narrowing that has been stable and silent for three years. Symptoms and plaque behavior carry more weight than the number.
The fourth is that a normal-feeling neck rules out disease. Mayo Clinic is explicit that carotid disease usually produces no symptoms until a TIA or stroke happens. A bruit is a useful clue, not a reliable one.
The fifth is that the dye is the main risk. Allergic reactions and kidney effects are real and are screened for, but the complication that clinicians think hardest about is procedural stroke, which is why the test is not ordered casually.
The sixth is that once an artery is fully blocked, it must be opened. In fact a complete, long-standing occlusion is usually left alone, because the brain has often rerouted its supply and reopening carries more risk than benefit. This is exactly why the near-occlusion versus occlusion distinction is one of the few questions still worth a catheter to answer.
Questions to ask your care team
Consultations move quickly, and the vocabulary is unfamiliar. Writing questions down beforehand turns a passive appointment into a shared decision. These are the ones that most often unlock a clear plan.
- What percentage narrowing did the ultrasound estimate, and which measurement method was used?
- Do you plan a CT or MR angiogram next, and what would each add that the ultrasound has not shown?
- If a catheter angiogram is being suggested, what specific question will it answer that the noninvasive scans cannot?
- Would the result change your recommendation? If both possible answers lead to the same plan, is the test still needed?
- Have I had symptoms that could be from this artery, even brief ones I dismissed, such as a curtain over one eye or a clumsy hand?
- Is the diagnostic angiogram likely to become a stenting procedure in the same session, and what would that mean for consent and recovery?
- How is my kidney function, and does it affect which dye-based test is safest for me?
- Which of my current medicines need reviewing before the test, and who will give me those instructions in writing?
- What is your own team’s approach to access, wrist or groin, and how long would I expect to lie flat afterward?
- If we choose surveillance instead, how often will I be scanned, and what change would prompt action?
Two further questions are worth asking out loud even if they feel awkward. First, what happens if I do nothing beyond taking my medicines? Second, how will we know the plan is working? Good teams welcome both, because they lead straight to the evidence. The answers, and the decision that follows, remain with the clinicians who know your full picture.
When to call your doctor
Some symptoms cannot wait for the next appointment. The American Heart Association’s FAST reminder captures the core stroke warning signs: Face drooping on one side, Arm weakness or numbness, Speech that is slurred or jumbled, and Time to call emergency services immediately. Sudden loss or dimming of vision in one eye, like a shade being drawn, sudden confusion, or sudden severe dizziness with trouble walking belong on the same list. These are emergency signs, not things to monitor overnight, and they apply whether or not you have been told you have carotid narrowing.
A TIA is the same set of symptoms resolving on their own. The NHS is unambiguous that a TIA is a medical emergency even after symptoms fade, because it is a warning that a full stroke may follow, most likely within the first days. Do not drive yourself; call for help.
After a catheter angiogram, contact the team the same day for bleeding from the puncture site that does not stop with firm pressure, a rapidly enlarging or painful lump, a leg or hand that turns cold, pale, numb or painful, fever, a rash or breathing difficulty that could signal a delayed dye reaction, or a marked drop in how much urine you are passing over the next two days, which can point to kidney strain. Any new weakness, speech change or vision loss in the hours after the test needs an emergency call, not a message to the clinic.
Between appointments, call your doctor if a known narrowing is being monitored and you notice new symptoms on either side, if you cannot tolerate a prescribed medicine, or if you simply do not understand the plan. Reaching out early is not overreacting; it is how a surveillance strategy is supposed to work.
Frequently asked questions
Is a carotid angiogram vs ultrasound decision made by the report or by a doctor?
By the treating team, not the report. Ultrasound produces a velocity-based estimate that is then interpreted alongside symptoms, other imaging and overall health. A catheter angiogram is chosen only when it will answer a question that changes management, such as confirming severity before an operation or settling whether an artery is nearly or fully blocked.
Is carotid stenosis 70 percent an emergency?
It depends on symptoms. A 70 percent narrowing that has recently caused a TIA or stroke is urgent, and the NHS advises that indicated surgery ideally happens within 2 weeks. The same narrowing with no symptoms is serious but not an emergency; it is typically confirmed with CTA or MRA and managed with medicines, with surgery discussed case by case.
What are the main catheter angiography risks?
MedlinePlus lists stroke, bleeding or clot at the puncture site, allergic reaction to contrast dye, kidney injury from the dye, and rare artery damage. Stroke is uncommon but is the complication clinicians weigh most heavily, because the catheter can dislodge plaque. Bruising at the groin or wrist is the most frequent minor issue and fades over one to two weeks.
In a CTA vs catheter angiography choice, why not go straight to the catheter test?
Because CTA answers most questions without entering an artery. It shows the arch, neck and skull vessels in three dimensions using a vein injection, with no procedural stroke risk. Catheter angiography adds real-time flow information and finer detail, so it is held back for disagreements between scans, suspected near-occlusion, or when stenting is planned.
At what age should you have your carotid arteries checked?
There is no set age. Guideline bodies do not recommend screening the general population, because incidental mild findings can lead to tests and operations that carry more risk than benefit. Imaging is prompted by symptoms such as a TIA, a bruit heard in the neck, or a high-risk profile including smoking, diabetes, high blood pressure or known artery disease elsewhere.
What are the warning signs of a blocked carotid artery?
Often there are none until a TIA or stroke occurs, according to Mayo Clinic. The signs to act on immediately are captured by the FAST test: face drooping, arm weakness, speech difficulty, and time to call emergency services. Sudden loss of vision in one eye, sudden confusion or severe dizziness with trouble walking are also emergency signs.
At what point do you need carotid artery surgery?
The NHS describes surgery as generally considered after a stroke or TIA when the artery is narrowed by 50 percent or more, and as an option in severe narrowing without symptoms for people fit enough to benefit. Below 50 percent the operation’s risks usually outweigh the gain. The decision weighs symptoms, imaging, other illnesses and the person’s priorities.
Can a carotid angiogram be wrong?
It can understate narrowing if the plaque is oval and only one angle is filmed, which is why multiple views are taken. It is still the reference standard against which ultrasound, CTA and MRA are judged, because it measures the artery directly rather than inferring narrowing from velocity or from a reconstructed image that calcium can distort.
How long does recovery from catheter carotid angiography take?
Most diagnostic studies are day cases. MedlinePlus advises lying flat for several hours after a groin puncture so the artery seals, with earlier mobility after wrist access. Bruising and tenderness are common for a few days, strenuous activity is usually avoided for around a week, and normal routines typically resume once the team has reviewed the site.
If my ultrasound and CT angiogram agree, do I still need a catheter test?
Usually not. When two independent methods place the narrowing in the same category and the treatment plan is clear, a third invasive test adds risk without new information. Exceptions include planned stenting, where the angiogram doubles as the first step of the procedure, and rare situations where anatomy or suspected disease inside the skull remains uncertain.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How the Extracardiac Fontan Procedure Reroutes Blood Flow: A Guide for Parents
The extracardiac Fontan procedure is the usual third stage of surgery for children born with one working heart pump. Surgeons attach a synthetic tube…

Preparing for Cardiothoracic Surgery: Chest Imaging, Stopping Smoking and the Pre-Op Talk
Preparing for cardiothoracic surgery usually means completing chest imaging and heart tests such as a chest X-ray, ECG and echocardiogram, stopping smoking as early…

How Angina Is Treated: Medication, Lifestyle Changes and Procedures to Restore Blood Flow
Angina is treated in three layers: medicines that ease an attack (short-acting nitrates) and prevent attacks (such as beta blockers or calcium channel blockers),…

Recovery After Mitral Valve Clip Repair: Walking Within a Day and the First Two Weeks
Mitral clip recovery time is usually short compared with open heart surgery. Most people are helped to walk within about a day, often go…

Living With Heart Failure: Fluid, Salt and Daily Weighing Explained by the Care Team
Living with heart failure usually means three daily habits: keeping salt low so the body holds less fluid, following any fluid limit your care…

Liver Enzymes Explained: ALT, AST and GGT: What Raised Numbers Mean
Liver enzymes such as ALT, AST and GGT are proteins that leak into the blood when liver cells are stressed or injured. Mildly raised…