

When Is Surgery the Treatment for Cushing Syndrome, and When Is Medication Used First?

Key Takeaways
- Surgery to remove the tumor is the usual first treatment for Cushing syndrome caused by a pituitary or adrenal adenoma, because it addresses the source rather than the symptoms.
- Medication is typically used first as a bridge when cortisol is dangerously high before an operation, when the tumor cannot be located on imaging, or when surgery is not safe for the person.
- The most common cause of Cushing syndrome overall is prescribed glucocorticoid medicine, and its treatment is a gradual, supervised reduction rather than any operation.
- Cortisol-lowering medicines work by blocking adrenal enzymes, reducing pituitary ACTH release, or blocking cortisol receptors, and none of them removes the tumor.
- After successful tumor removal, cortisol usually falls very low, temporary replacement is needed, and the adrenal glands can take a year or longer to recover according to Mayo Clinic.
- Pituitary radiation takes months to years to lower cortisol, so medication continues alongside it, and bilateral adrenalectomy controls cortisol immediately at the price of lifelong hormone replacement.
Surgery to remove the cortisol-producing tumor is usually the first-line treatment for Cushing syndrome caused by a pituitary or adrenal tumor, because it targets the source directly. Medication is generally used first when surgery must be delayed, when the tumor cannot be found or safely removed, when cortisol levels are dangerously high before an operation, or when the syndrome comes from prescribed steroids, which are adjusted rather than operated on.
The scan report is one page long, and the thing that has upended a year of her life is smaller than a grain of rice. A pituitary adenoma, the endocrinologist says, pointing to a faint gray smudge. The word surgery arrives in the same sentence, followed almost immediately by a second word: not yet. Her blood pressure is too high, her blood sugar is uncontrolled, and the operating schedule is weeks away. She leaves with a prescription, a list of blood tests, and a question she keeps turning over on the drive home. Why medicine now, if the tumor is the problem?
That question sits at the heart of Cushing syndrome treatment options. The answer is rarely a simple either-or. Surgery and medication are not rivals so much as tools chosen in a particular order, for a particular person, based on where the excess cortisol is coming from and how much damage it has already done.
What follows is a plain-language walk through that ordering: what surgery involves, what the medicines actually do, and why the same diagnosis can lead two people down different first steps.
What are the Cushing syndrome treatment options?
Cushing syndrome is the name for what happens when the body is exposed to too much cortisol for months on end. Cortisol is a hormone made by the adrenal glands, two small organs perched on top of the kidneys, and in normal amounts it steadies blood sugar, supports blood pressure, and calms inflammation. In excess it does the opposite of steadying anything. The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) estimates that the internally driven form affects roughly 40 to 70 people per million each year, which makes it rare enough that many primary care clinicians will see only a handful of cases in a career.
The treatment menu is short but varied. Depending on the cause, a care team may recommend one or a combination of the following:
- Surgery to remove a tumor that is producing cortisol, or producing the signal that tells the adrenal glands to make it.
- Gradual adjustment of a prescribed steroid medicine, when that medicine is the source.
- Cortisol-lowering medicines, which block the hormone’s production or its action.
- Radiation aimed at the pituitary gland, usually when surgery has not been possible or has not been enough.
- Removal of both adrenal glands, reserved for situations where nothing else has controlled cortisol.
None of these is a universal first choice. What decides the order is the source of the cortisol, the severity of the person’s illness, and whether they are well enough to undergo an operation. Mayo Clinic and the NHS both frame the goal the same way: bring cortisol back to normal levels and, wherever possible, do so by dealing with the root cause rather than managing symptoms indefinitely.
Everything else in this article is a matter of applying that principle to real situations.
Why does the cause of Cushing syndrome decide which treatment comes first?
Two people with identical symptoms can have completely different sources of cortisol, and the source dictates the plan.
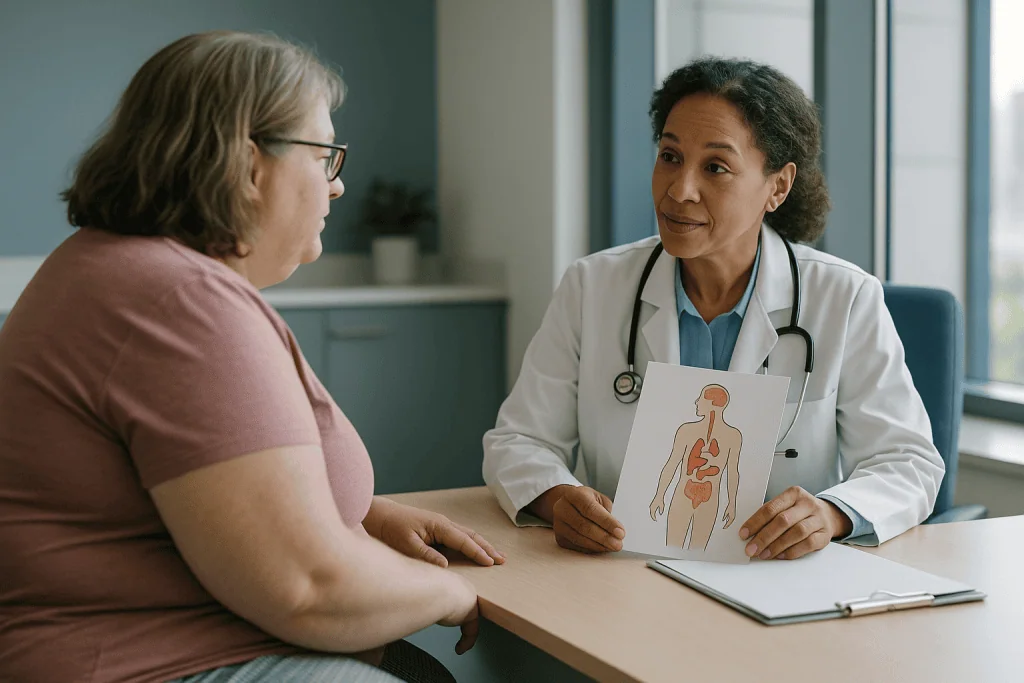
The broadest split is between exogenous and endogenous disease. Exogenous means the cortisol-like hormone is coming from outside the body, almost always from glucocorticoid medicines such as prednisone taken for asthma, arthritis, inflammatory bowel disease, or after a transplant. NIDDK and the NHS agree this is the most common cause overall. No operation can fix it; the treatment is a supervised change to the medicine.
Endogenous means the body is overproducing cortisol on its own. Here the next question is whether the problem is driven by ACTH. ACTH, or adrenocorticotropic hormone, is the chemical message the pituitary gland sends to the adrenals telling them to release cortisol. When a small benign pituitary tumor pumps out too much ACTH, the condition is called Cushing disease, and NIDDK notes it accounts for most endogenous cases. Occasionally the ACTH comes from a tumor elsewhere, often in the lung or pancreas, which is called ectopic ACTH production. When the adrenal gland itself has a tumor making cortisol directly, ACTH is not involved at all.
Working out which of these applies takes time. Clinicians first confirm that cortisol is genuinely high, typically with repeated urine, saliva, or blood tests, and only then hunt for the source with hormone measurements and imaging. Pituitary adenomas are frequently only a few millimeters across, and Cleveland Clinic points out that they do not always show up on MRI. Some people need a specialized procedure that samples blood from veins near the pituitary to prove the signal is coming from there.
This detective work is not a delay for its own sake. Operating on the wrong gland helps no one, so the surgeon usually will not be booked until the source is reasonably certain.
How does surgery for Cushing syndrome actually work?
The operation depends entirely on where the tumor sits.
For Cushing disease, the standard approach is transsphenoidal surgery. The pituitary gland hangs beneath the brain just behind the bridge of the nose, and the sphenoid sinus, an air-filled cavity in the skull, lies directly in front of it. A neurosurgeon works through the nostril, across that sinus, and reaches the gland without opening the skull. Using an endoscope or operating microscope, the surgeon looks for the adenoma, which often has a slightly different color and texture from healthy tissue, and removes it while leaving the rest of the gland in place. The procedure is done under general anesthesia and, according to Mayo Clinic, usually involves a hospital stay of a few days.
For an adrenal tumor, the operation is an adrenalectomy, removal of the affected gland. Most are done laparoscopically, through several small incisions in the abdomen or flank, with a camera guiding the instruments. The remaining adrenal gland is expected to take over cortisol production, though not immediately.
For ectopic ACTH, the surgeon removes the tumor wherever it lies, which may mean lung, chest, or abdominal surgery, and the plan becomes as much about that tumor as about cortisol.
Every one of these carries risks that the surgical team will spell out. Pituitary surgery can cause leakage of the fluid that surrounds the brain, bleeding, infection, temporary disturbance of the body’s water balance, and, in some cases, loss of other pituitary hormones that then need replacing. Adrenal surgery carries the general risks of abdominal surgery, including bleeding and injury to nearby organs. Mayo Clinic also notes that after any of these operations, cortisol typically falls low enough that temporary replacement therapy is needed, a topic covered in the recovery section below.
Who is usually offered surgery first, and who is usually asked to wait?
Guidance from Mayo Clinic, the NHS, and NIDDK converges on a simple rule: when a tumor can be seen and reached, removing it is the preferred first step. Surgery is the only option with a realistic chance of returning cortisol to normal without ongoing medication, and it deals with the tumor rather than working around it.

The people most likely to go straight to the operating room share a few features. Their source has been confirmed. Imaging shows a discrete tumor. Their blood pressure, blood sugar, and heart function are stable enough for general anesthesia. They have no active infection, and their mental state is steady enough to cope with the procedure and the demanding weeks that follow.
Others are asked to wait, and the reasons fall into recognizable groups:
- Cortisol is so high that the person is acutely unwell, with severe hypertension, uncontrolled diabetes, dangerous potassium levels, serious infection, or psychiatric symptoms. Operating in that state raises surgical risk, so cortisol is lowered first.
- The tumor cannot be found. A pituitary MRI may be normal, or an ectopic source may be hiding. Surgery without a target is not surgery anyone wants.
- The person is frail or has other serious illnesses that make an operation unsafe for now.
- Pregnancy, where timing and technique need individual planning with obstetric input.
Waiting in these situations is not the same as doing nothing. It usually means medication to bring cortisol down while the team completes localization, treats infections, stabilizes the heart and metabolism, and prepares the body for surgery. Cleveland Clinic describes this as preparing the patient to be a better surgical candidate.
Who falls into which group is a clinical judgment, and it can change. Someone who is too unwell to operate on in one month may be ready the next.
When is medication used first instead of surgery?
The scenarios where a prescription arrives before a surgical date are more common than many newly diagnosed people expect. Cleveland Clinic and Mayo Clinic describe medication as the first step in several distinct circumstances.
The first is as a bridge. When someone is acutely ill from high cortisol, medicines that lower it can begin working within days, buying the time needed to control blood pressure, correct blood sugar, treat infections, and reduce the risk of complications during anesthesia. The surgery is still the plan; the medicine simply comes first in the calendar.
The second is when the source has not been located. A pituitary MRI can look entirely normal in Cushing disease, and ectopic tumors can be small and slow to appear on scans. Rather than operate blind, clinicians control cortisol medically while repeating imaging over time.
The third is when surgery is not an option at all, because the person cannot safely have an anesthetic, has declined an operation, or has a tumor that has spread and cannot be removed. Here medication becomes the long-term strategy rather than a stopgap.
The fourth is after surgery that did not achieve remission. Remission means cortisol has returned to normal and the syndrome is controlled, and it does not always happen on the first attempt. A second operation may be considered, or radiation may be recommended, and radiation takes months to years to work. Medication fills that gap.
One phrase worth knowing is block and replace. In this approach, a medicine deliberately suppresses the body’s own cortisol production, and a controlled replacement dose of a glucocorticoid is given alongside it, so the person has steady, normal hormone levels without the swings of trying to titrate a blocker precisely. Whether that approach suits any individual is a decision for the endocrinologist managing their care.
How does medication for Cushing syndrome lower cortisol?
The medicines used in Cushing syndrome fall into three mechanistic groups, and understanding the mechanism explains both what to expect and what needs monitoring. None of them shrinks a pituitary or adrenal tumor reliably, which is why they are usually paired with a definitive plan.
Adrenal enzyme blockers, formally called steroidogenesis inhibitors, act inside the adrenal glands on the enzymes that assemble cortisol from cholesterol. Ketoconazole, metyrapone, and osilodrostat belong here. Mayo Clinic notes these agents can lower cortisol relatively quickly, often within days, which is why they are the usual choice for a pre-surgery bridge. Because they interfere with hormone-making machinery, they can push cortisol too low, alter other adrenal hormones, and affect the liver or potassium levels, so regular blood tests are part of the package.
Pituitary-directed agents aim at the ACTH signal rather than the adrenal response. Pasireotide and cabergoline are examples used in Cushing disease. They tend to work more gradually, over weeks to months, and their effect varies considerably between individuals. Pasireotide in particular is known to raise blood sugar, a significant consideration in a condition that already predisposes to diabetes.
Glucocorticoid receptor blockers take a different route entirely. Mifepristone does not lower cortisol in the blood; it prevents cortisol from binding to its receptors in tissues. Blood cortisol may even rise while symptoms improve, which means clinicians judge its effect by clinical response rather than lab values, and recognizing an overshoot into adrenal insufficiency requires experience.
Whichever class is chosen, the prescribing endocrinologist will decide on the agent, the starting point, and adjustments, and will build in a monitoring schedule. Patients are usually asked to learn the signs of cortisol dropping too low, described in the final section of this article, because that is the shared risk across every group.
Cushing syndrome treatment options at a glance
Seeing the options side by side helps clarify why one plan may include several of them in sequence. The table below draws on descriptions from Mayo Clinic, NIDDK, and Cleveland Clinic. Timelines are typical ranges, not promises, and every row ends with the same caveat: the treating team weighs these trade-offs for the individual in front of them.
| Option | Cause it addresses | How it works | Typical timeline | Main trade-offs |
|---|---|---|---|---|
| Transsphenoidal pituitary surgery | Cushing disease (pituitary adenoma) | Removes the ACTH-producing tumor through the nose | Hospital stay of a few days; adrenal recovery may take a year or longer | Fluid leak, bleeding, other hormone deficiencies; recurrence possible over years |
| Adrenalectomy | Adrenal tumor | Removes the affected gland, usually laparoscopically | Short hospital stay; remaining gland recovers over months | Surgical risks; temporary cortisol replacement needed |
| Removal of an ectopic tumor | Ectopic ACTH | Removes the source tumor wherever it lies | Depends on location and extent | Tumor may be hard to find or already spread |
| Steroid adjustment | Medicine-induced disease | Gradual supervised reduction or substitution | Months, guided by the prescriber | Underlying condition may flare; abrupt stopping is dangerous |
| Cortisol-lowering medicines | Any endogenous cause | Block cortisol production or its action | Days to months depending on class | Ongoing monitoring; do not remove the tumor |
| Pituitary radiation | Cushing disease not controlled by surgery | Damages tumor cells over time | Months to years to take effect | Risk of losing other pituitary hormones |
| Bilateral adrenalectomy | Any cause when other treatment fails | Removes both adrenal glands | Immediate cortisol control | Lifelong hormone replacement; pituitary monitoring |
The pattern across the table is that the more definitive a treatment is, the more it asks of the body, and the faster-acting a treatment is, the less permanent it tends to be. Good care is often about pairing one from each end.
What about radiation therapy and removing both adrenal glands?
Two options tend to appear later in the conversation, and both deserve a clear explanation because they sound more drastic than they are in context.
Radiation therapy to the pituitary is generally reserved for Cushing disease that persists or returns after surgery, or for people who cannot have an operation. It may be delivered as a course of conventional treatments spread over several weeks or as a single, highly focused session sometimes called stereotactic radiosurgery. Either way the effect is slow. Mayo Clinic notes that it can take months to years for cortisol to fall, which is why medication is almost always continued in the meantime. The main long-term risk is that healthy pituitary tissue is affected too, leading to deficiencies in thyroid, sex, or growth hormones that then need replacing. Vision and memory are monitored as well.
Bilateral adrenalectomy, removal of both adrenal glands, does something no other option can: it stops cortisol overproduction completely and immediately, regardless of where the ACTH is coming from. NIDDK describes it as an option when other treatments have failed or when cortisol must be controlled urgently and definitively. The price is that the body can no longer make cortisol or aldosterone, the hormone that manages salt and blood pressure, so lifelong replacement of both becomes non-negotiable, along with the discipline of adjusting doses during illness and carrying emergency supplies.
There is one further consideration specific to Cushing disease. With the adrenals gone, the pituitary adenoma loses the cortisol feedback that was partly restraining it, and in some people it grows and produces very high ACTH, a situation called Nelson syndrome that can darken the skin and press on nearby structures. Cleveland Clinic notes this is why ongoing pituitary imaging is part of follow-up after bilateral adrenalectomy.
Neither of these is a failure. Both are recognized parts of the pathway for a condition that does not always yield to the first attempt.
Is Cushing syndrome after steroids treated differently?
Entirely differently, and this is the branch of the family tree where surgery has no role at all.
Glucocorticoid medicines are prescribed for good reasons: severe asthma, rheumatoid arthritis, lupus, inflammatory bowel disease, certain cancers, and to prevent organ rejection after transplant. Taken at high enough amounts for long enough, they mimic excess cortisol, and the body cannot tell the difference. The NHS and NIDDK identify this as the most common cause of Cushing syndrome overall. Oral tablets are the usual culprits, but high-potency skin creams, frequent joint injections, and inhaled steroids in large amounts can contribute.
The treatment is a supervised change to the medicine, and the word supervised carries real weight. Months of external steroid quiet the body’s own cortisol production, so the adrenal glands are effectively asleep. Stopping abruptly can trigger adrenal insufficiency, a dangerous shortage of cortisol that causes weakness, vomiting, low blood pressure, and in severe cases collapse. The prescriber therefore reduces the medicine gradually, on a schedule matched to how long and how much it has been taken, sometimes over many months.
What that schedule looks like is entirely for the prescribing clinician to determine, and it depends as much on the underlying disease as on the Cushing features. Someone whose lupus flares when the steroid is reduced may need a different medicine introduced to control the inflammation, often called a steroid-sparing agent, before the glucocorticoid can come down further. In some cases the underlying condition simply requires ongoing steroid, and the aim shifts to using the lowest effective amount and protecting bones, blood sugar, and blood pressure along the way.
Mayo Clinic notes that Cushing features tend to fade slowly as the medicine is reduced, over months rather than weeks. Anyone worried about steroid side effects should raise it with the prescriber rather than adjusting on their own.
What does Cushing disease surgery recovery look like in the first weeks?
The most counterintuitive fact about recovery is this: feeling worse for a while is often a sign the operation did what it was meant to.
In the first days after transsphenoidal surgery, the nose is congested and sometimes packed, headaches are common, and nurses check sodium levels and urine output closely because the body’s water balance can wobble temporarily. Cortisol is measured repeatedly. Mayo Clinic and NIDDK both explain that a sharp fall in cortisol after surgery is what the team hopes to see, because it suggests the tumor is out and the remaining pituitary, long suppressed, has not yet woken up. That low level means replacement glucocorticoid is started before discharge.
Then comes the part few people are warned about strongly enough. The body has spent months or years bathed in high cortisol and has adapted to it. Dropping to normal feels, paradoxically, like deficiency. Profound fatigue, joint and muscle aches, low mood, nausea, and skin sensitivity are common in the weeks that follow, and they can be disheartening. This is sometimes called steroid withdrawal, and it is expected rather than alarming, though it should always be reported so the team can distinguish it from true adrenal insufficiency.
Recovery of the body’s own cortisol production is measured in months. Mayo Clinic notes it may take a year or longer for the adrenal glands to resume normal function, and the replacement glucocorticoid is reduced step by step under endocrine supervision, with periodic tests to check whether the axis has recovered. During this window, illness, injury, or surgery requires extra cover, and patients are typically taught sick-day rules and given an emergency injection kit.
Follow-up does not end there. Cushing disease can recur years later, so cortisol testing continues at intervals long after the person feels well. Adrenalectomy recovery follows a similar arc, with the remaining gland taking over gradually.
What happens with untreated Cushing syndrome?
The urgency behind every treatment decision comes from what prolonged cortisol excess does to the body, and it is worth being plain about it without being alarmist.
Cortisol raises blood sugar and blood pressure by design; that is its job during genuine stress. Sustained at high levels, those effects become disease. NIDDK, Mayo Clinic, and the NHS list the same consequences: high blood pressure, type 2 diabetes, weight gain concentrated around the trunk and face, thinning bones that fracture easily, muscle wasting in the arms and legs, fragile skin that bruises and tears, slow wound healing, and a heightened risk of infections because cortisol suppresses the immune system. Blood clots in the legs and lungs are more common. Mood changes, anxiety, sleep disruption, and difficulty concentrating are frequent and can be among the most distressing features. Over years, the cardiovascular strain adds up, and NIDDK notes that untreated Cushing syndrome can be life-threatening.
This is exactly why the question in this article’s title has a nuanced answer. If surgery is weeks or months away, those weeks are not neutral. Each one adds to the load on bones, blood vessels, and metabolism. Lowering cortisol with medication in the interim is a way of stopping the clock while the definitive plan is prepared.
The encouraging counterpoint is that many of these changes improve once cortisol is controlled. Blood pressure and blood sugar often ease, muscle strength returns gradually, and mood frequently lifts, though the pace varies and some effects, particularly on bone density, take a long time and may not fully reverse. Cleveland Clinic frames the goal as preventing further harm and allowing the body to recover, which is a realistic way to think about what treatment offers.
Left alone, the condition does not burn itself out. Treated, in whatever order the team decides, it can be controlled.
What people often get wrong about Cushing syndrome treatment
Rare conditions attract confident misinformation, and a few beliefs come up so often in clinic that they are worth correcting directly.
It is just weight gain, so diet will fix it. The weight changes in Cushing syndrome are driven by hormone, not habit. Lifestyle care matters for blood pressure and blood sugar, but it does not lower cortisol from a tumor, and treating the source is what allows the body to change.
Surgery is a one-time fix. Removing a pituitary adenoma often brings cortisol back to normal, but NIDDK and Mayo Clinic both note that Cushing disease can return years later. Lifelong periodic testing is part of the plan, not a sign of doubt about the operation.
Medication is the gentle alternative. Cortisol-lowering medicines require regular blood tests, carry meaningful side effects, and do not address the tumor. They are a valuable tool, sometimes the only one available, but they are not the low-effort option.
Feeling terrible after surgery means it failed. Usually the reverse. The fatigue and aches of the first weeks are the body adjusting to normal cortisol after years of excess. Persistent symptoms should still be reported so the team can rule out genuine deficiency.
Everyone with Cushing syndrome needs an operation. The most common form is caused by prescribed steroids, and its treatment is a supervised medicine adjustment with no surgery at all.
Stopping the steroid quickly will speed things up. Abrupt withdrawal after long-term use can cause adrenal insufficiency and collapse. Reduction is gradual for safety, and only the prescriber should direct it.
Radiation works right away. It does not. Mayo Clinic describes a lag of months to years, which is why medication continues alongside it.
Correcting these ideas does not change the medicine, but it does change how prepared people feel for the road ahead.
Questions to ask your care team
Appointments for a rare hormonal condition move quickly, and the most useful questions are often the ones that seem too basic to ask. Writing them down beforehand helps. The following are the ones endocrinologists and surgeons say patients most often wish they had raised earlier.
About the diagnosis and source:
- Where is my excess cortisol coming from, and how confident are you about that?
- If the tumor has not been found, what further tests are planned, and how long might that take?
About the order of treatment:
- Are you recommending surgery first, medication first, or both, and what is driving that choice for me specifically?
- If medication is being used first, what is it for: to prepare me for surgery, to hold things steady while we look for the source, or as the long-term plan?
- What would need to change for me to become a surgical candidate?
About surgery:
- What are the specific risks of this operation for someone with my other health conditions?
- What happens if the first operation does not bring cortisol down to normal?
About medication:
- How does this medicine work, how will you know it is working, and what monitoring will I need?
- What signs of cortisol dropping too low should I watch for, and who do I call?
About recovery and the long term:
- How long might I need replacement hormone after surgery, and how will you decide when to reduce it?
- What are the sick-day rules, and should I carry an emergency kit or medical alert?
- How often will I need cortisol testing after treatment, and for how many years?
There is no wrong question here. A team that has treated Cushing syndrome before will expect them, and a plan that has been talked through is a plan that is far easier to follow through the difficult weeks after surgery.
When to call your doctor
Most of the treatment journey unfolds at scheduled appointments, but a few situations need same-day contact or emergency care, whether someone is taking cortisol-lowering medicine, recovering from surgery, or reducing a prescribed steroid.
The single most important emergency is adrenal crisis, when cortisol drops too low. It can happen when a blocker works too well, when the body has not yet recovered after surgery and replacement is missed or insufficient, or when a steroid is reduced too fast. The NHS and NIDDK describe the warning signs as severe weakness, persistent vomiting or diarrhea, dizziness or fainting, severe abdominal or back pain, confusion, and drowsiness. This is a call for emergency services, not a wait for the next appointment, and anyone with an emergency injection kit should use it as they have been taught.
After pituitary surgery, seek urgent help for clear, watery fluid dripping from the nose, especially when leaning forward, which may indicate a leak of the fluid around the brain; for fever with severe headache or a stiff neck; for sudden vision changes; and for intense thirst with very frequent urination, which can signal a water-balance problem.
At any stage, contact the team promptly for signs of a blood clot, such as swelling or pain in one leg, sudden chest pain, or breathlessness; for a wound that is red, hot, or leaking; for a fever that does not settle; and for blood sugar readings far outside the range you have been given.
Mental health belongs on this list too. Cushing syndrome and its treatment can bring severe low mood, agitation, or thoughts of self-harm. These are medical symptoms of a hormonal condition, and they warrant an urgent conversation with the care team or a crisis line.
When in doubt, call. The endocrine team would rather hear about a symptom that turns out to be nothing than miss one that mattered.
Frequently asked questions
Is surgery always the first treatment for Cushing syndrome?
No. Surgery is the preferred first step when a pituitary or adrenal tumor has been identified and the person is well enough for an operation. It has no role when the cause is a prescribed steroid, and it is postponed when cortisol is dangerously high, when the tumor cannot be found, or when other illnesses make anesthesia unsafe. In those situations medication usually comes first, often as a bridge to surgery later.
Why would a doctor prescribe medication for Cushing syndrome before operating?
Mainly to make surgery safer. Very high cortisol drives severe high blood pressure, uncontrolled blood sugar, infection risk, and blood clots, all of which raise operative risk. Adrenal enzyme blockers can lower cortisol within days, giving the team time to stabilize the heart and metabolism. Medication is also used while the source is still being located, since operating without a clear target helps no one.
How long does Cushing disease surgery recovery take?
The hospital stay is typically a few days, but full recovery is measured in months. Cortisol usually falls very low after the tumor is removed, so replacement glucocorticoid is started and then reduced gradually. Mayo Clinic notes the adrenal glands may take a year or longer to resume normal function. Fatigue, aches, and low mood in the early weeks are common as the body adjusts to normal cortisol.
What are the different types of medication for Cushing syndrome?
There are three groups. Steroidogenesis inhibitors such as ketoconazole, metyrapone, and osilodrostat block the adrenal enzymes that make cortisol. Pituitary-directed agents such as pasireotide and cabergoline reduce ACTH release. Glucocorticoid receptor blockers such as mifepristone stop cortisol from acting on tissues. The choice, starting point, and monitoring are decided by the prescribing endocrinologist, and all groups carry a risk of pushing cortisol too low.
Can Cushing syndrome come back after surgery?
Yes. Both NIDDK and Mayo Clinic note that Cushing disease can recur years after apparently complete removal of a pituitary adenoma, which is why periodic cortisol testing continues long term. If it returns, options include a second operation, radiation therapy with medication in the interim, or in some cases removal of both adrenal glands. Ongoing follow-up is a standard part of care, not a sign the first surgery went wrong.
What happens if Cushing syndrome is left untreated?
Prolonged cortisol excess causes high blood pressure, type 2 diabetes, bone thinning and fractures, muscle weakness, fragile skin, frequent infections, blood clots, and mood disturbance, and NIDDK notes it can become life-threatening over time. Many of these changes improve once cortisol is controlled, though bone loss may recover slowly or incompletely. This is why medication is used to lower cortisol even while surgery is being arranged.
How is Cushing syndrome caused by steroid medicines treated?
By gradually reducing or substituting the steroid under the prescriber’s supervision, never by stopping suddenly. Long-term steroid use suppresses the body’s own cortisol production, so abrupt withdrawal can cause adrenal insufficiency and collapse. The reduction schedule depends on how long the medicine has been taken and on the underlying condition, which may need a different treatment introduced first so it does not flare.
Does radiation treat Cushing disease quickly?
No. Pituitary radiation, whether given over several weeks or as a single focused session, takes months to years to bring cortisol down according to Mayo Clinic. It is usually offered when surgery has not achieved remission or cannot be performed, and cortisol-lowering medication continues while it takes effect. The main long-term risk is loss of other pituitary hormones, which are then replaced.
Why do people feel worse after successful Cushing surgery?
Because the body has adapted to years of high cortisol, and a sudden return to normal feels like deficiency. Profound fatigue, joint and muscle aches, nausea, and low mood are common in the first weeks and are sometimes called steroid withdrawal. Symptoms should still be reported, because the care team needs to distinguish this expected adjustment from true adrenal insufficiency, which requires a change in replacement therapy.
What is adrenal crisis and why does it matter during treatment?
Adrenal crisis is a dangerous shortage of cortisol that can occur when a blocker medicine works too strongly, when replacement is missed after surgery, or when a steroid is reduced too fast. Warning signs include severe weakness, persistent vomiting, dizziness or fainting, confusion, and severe abdominal pain. It is a medical emergency, and people at risk are usually taught sick-day rules and given an emergency injection kit.
References
- Cushing's Syndrome (NIH NIDDK)
- Cushing's syndrome (NHS)
- Cushing's Syndrome (Cleveland Clinic)
- Cushing's Syndrome (MedlinePlus)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Happens Inside a Medical Longevity Program? Risk Assessment, Screening and the Plan
A medical longevity program usually involves three stages: a detailed history and physical exam, a set of blood tests and screenings chosen to estimate…
Hyperthyroidism With Heart Disease or in Pregnancy: How Treatment Is Adapted
Hyperthyroidism treatment is adapted in pregnancy and heart disease because the usual options carry different risks in each situation. In pregnancy, radioactive iodine is…

Diagnosing Gigantism: Growth Hormone and IGF-1 Tests, Glucose Suppression Testing and MRI
Gigantism is diagnosed by combining a child's growth record with blood tests and imaging. Doctors usually measure IGF-1, a steadier marker of growth hormone…

Adrenalectomy for Pheochromocytoma: How Surgeons Remove the Adrenal Tumor Safely
Pheochromocytoma adrenalectomy is surgery to remove an adrenal gland tumor that overproduces adrenaline-type hormones. Because handling the tumor can trigger dangerous blood pressure swings,…

How Do Test Results Shape a Hashimoto Treatment Plan? TSH, Antibodies and Ultrasound
Hashimoto diagnosis tests work as a set, not one number. A high TSH with low free T4 usually signals an underactive thyroid that clinicians…

Diabetes Insipidus: Confusion, Severe Weakness and When Dehydration Needs Urgent Care
Diabetes insipidus becomes a dehydration emergency when the body loses large volumes of dilute urine faster than fluid can be replaced, pushing blood sodium…