

Blood Pressure Watches and Hypertension Alerts: What They Detect, and Why They Are Not a Cuff

Key Takeaways
- The Apple Watch hypertension notification analyzes roughly 30 days of optical pulse data and issues an alert; it never displays a systolic or diastolic number.
- Validation figures released with the September 2025 clearance indicate the feature identifies roughly four in ten people with hypertension and correctly reassures more than nine in ten without it, so a quiet watch is not a clean bill of health.
- The feature is intended only for adults 22 and older who are not pregnant and have not already been diagnosed with hypertension, because those are the groups it was tested on.
- A cuff measures pressure by occluding an artery and sensing when blood flow returns; a wrist sensor infers patterns from light, which is why cuffless estimates drift and no major guideline accepts them for diagnosis.
- After an alert, guidelines call for two upper-arm cuff readings twice daily for seven days, averaged, with a home average of about 135/85 or higher warranting a clinician's review.
- The WHO estimates nearly half of the 1.28 billion adults with hypertension worldwide are unaware of it, which is why a coarse screening net can still matter despite its misses.
Blood pressure watches such as the Apple Watch do not measure blood pressure. The Apple Watch hypertension notification uses an optical pulse sensor to look for patterns over about 30 days that suggest sustained high blood pressure, then prompts you to confirm with an arm cuff. It gives no numbers, misses a large share of cases, and is not a substitute for a validated cuff or a clinician's assessment.
A nurse friend of mine got a buzz on her wrist in October and laughed, then stopped laughing. The message said her watch had noticed signs consistent with hypertension over the past month. She has taken thousands of blood pressure readings on other people. She had never taken one on herself. A week of morning and evening cuff readings later, her average sat comfortably above the line her own hospital uses, and she booked an appointment.
That small scene is playing out in a lot of households right now. Since the feature launched with the Series 11 in September 2025 and cleared its regulatory review days later, searches for apple watch blood pressure have climbed with every rumor about what the next model might add. As of early 2026, the feature has rolled out to dozens of countries and to older models running the current software, and social feeds are full of screenshots, celebration, and some sharp misunderstanding.
This piece is the calm version. What the sensor sees, what it cannot, and why the humble upper-arm cuff is still the device that actually decides anything.
What changed recently: why apple watch blood pressure is trending
Three things landed within a few weeks of each other, and together they explain the search spike.
The first was the product itself. In September 2025, a hypertension notification feature arrived on the Apple Watch, and the US Food and Drug Administration cleared it through the 510(k) pathway, which is the route for devices judged to be substantially similar to something already on the market. The feature works on Series 9 and newer and on Ultra 2 and newer once the current software is installed, so millions of existing wrists gained it overnight rather than only new buyers.
The second was a guideline. In August 2025, the American College of Cardiology and the American Heart Association published an updated high blood pressure guideline that kept the definition of hypertension at 130/80 mm Hg or higher and leaned harder than ever on home measurement with a validated cuff. Wearables were mentioned in the same breath as promising but unproven for measurement. The AHA’s public guidance on home monitoring still starts with a cuff, not a watch (heart.org).
The third is the background problem that makes any screening tool newsworthy. The World Health Organization estimates that around 1.28 billion adults aged 30 to 79 live with hypertension and that nearly half do not know it (WHO). In the United States, the CDC puts the figure at close to half of all adults (CDC). A condition that common, that silent, and that treatable is exactly the kind of thing a device on 100 million wrists could plausibly help with, and exactly the kind of thing a headline can oversell.
Then came the rumor cycle. Reports that a future model might attempt something closer to a real reading have kept the topic warm. Nothing of that kind has been announced, cleared, or validated as of this writing, and we will come back to why it is so hard.
What an apple watch hypertension notification actually is
Start with what it is not. It is not a number. You will not open the app and see 142 over 91. The watch does not display systolic pressure (the higher figure, the force when the heart contracts) or diastolic pressure (the lower figure, the pressure between beats). It never will, on the current hardware, because it is not measuring pressure at all.

What it does is closer to a smoke detector than a thermometer. Running quietly in the background, the watch collects optical pulse data during periods when you are still, feeds roughly 30 days of that data through an algorithm trained on people whose blood pressure was known, and asks one question: does this pattern look more like someone with sustained high blood pressure than someone without? If the answer is yes, you get a notification and a prompt to confirm with a cuff for seven days.
Hypertension, for the plain-language record, is a persistently elevated pressure inside the arteries, and it matters because that pressure slowly damages the heart, brain, kidneys and eyes (Mayo Clinic). The word sustained is doing real work in that sentence. A single high reading after a flight of stairs is not hypertension; a month of readings that average high is.
That is why the feature looks at a month rather than a moment. It is deliberately slow. The delay filters out the coffee, the argument, the workout, and looks for the baseline underneath. The trade-off is that a fast-developing problem, or a dangerously high spike, is invisible to it. The feature is designed for the silent, chronic kind of hypertension, which is also the most common kind.
There is also a deliberate absence. The notification comes without severity, without trend arrows, without a nudge toward any treatment. It hands you a task, confirm with a cuff and talk to a clinician, and then steps back. Given how easily wrist data gets over-interpreted, that restraint is one of the better design decisions in the whole feature.
How the sensor works: light, not pressure
Flip the watch over and you will see the green and infrared lights. They are the whole story.
The technique is photoplethysmography, usually shortened to PPG, and in one sentence it is this: shining light into the skin and measuring how much bounces back, which changes with every pulse as blood surges through the small vessels beneath. Each heartbeat produces a waveform, a little hill with a distinctive shape. The shape depends on how much blood arrives, how quickly, how stiff the artery walls are, and how the pressure wave reflects back from the branching vessels downstream.
People with long-standing high blood pressure tend to have stiffer arteries, and stiffer arteries change the shape and timing of that little hill. The algorithm is not reading pressure. It is reading the fingerprint that chronic pressure leaves on the waveform, then comparing that fingerprint against a library built from people whose cuff readings were known during training.
Think of it like a mechanic listening to an engine. An experienced ear can tell you something is probably wrong with the timing without ever putting a gauge on the engine. That is a real and useful skill. It is also not the same as a measurement, and it cannot tell you the exact number the gauge would show.
Several things muddy the signal, which is why the watch needs so many samples. Skin tone, wrist hair, tattoos and fit affect how much light returns. Cold hands narrow the vessels. Movement swamps the waveform, which is why the watch only trusts readings taken while you are still. Irregular heart rhythms distort the pattern. Medications that relax or constrict blood vessels change the waveform independently of pressure.
None of these are flaws unique to one product. Every optical wearable on the market shares them, because they are properties of light passing through living tissue. The honest framing is that PPG is very good at counting beats, reasonably good at spotting certain rhythm problems, and still in its early days for anything that requires knowing the actual force inside an artery.
Why doesn't the Apple Watch do blood pressure? The physics problem
People ask this as if it were a business decision. It is mostly a physics one.
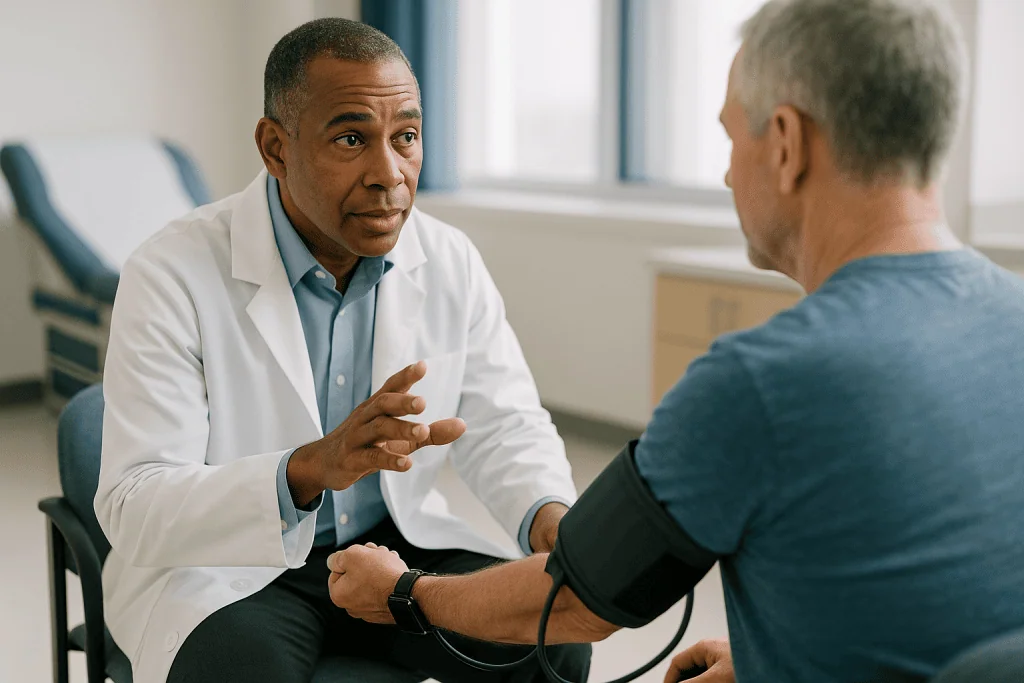
A cuff measures blood pressure by doing something a watch cannot: it squeezes the artery shut and then listens, or senses, as the vessel reopens while the pressure is released. The point at which blood first squirts through again is systolic; the point at which flow becomes smooth is diastolic. Pressure in, pressure out. The method has been refined for more than a century, and its units, millimeters of mercury, literally describe how high the pressure would push a column of mercury (MedlinePlus).
A wrist sensor with no cuff has to infer pressure from something else. The main candidate is pulse transit time, in plain terms the tiny delay between the heart contracting and the pressure wave arriving at the wrist; a stiffer, higher-pressure system moves that wave faster. The relationship is real. The problem is that it is different in every person and drifts within the same person over weeks. Arterial stiffness changes with age, temperature, hydration, medication and posture. A device that estimates pressure this way needs frequent recalibration against a cuff, and a device that needs a cuff to stay honest has not replaced the cuff.
Accuracy standards make the gap concrete. A validated home cuff is expected to land within a few millimeters of mercury of a reference measurement on average. Cuffless estimates in published studies often wander far wider than that, and they tend to track the calibration reading rather than the true value when pressure changes. For a screening question, is this person likely hypertensive or not, that wobble is tolerable. For deciding whether someone’s treatment is working, it is not.
There is a regulatory dimension too. A device that displays a blood pressure number is held to the standard of a blood pressure monitor. A device that flags a pattern and tells you to go get a cuff is held to a different, lower bar. Choosing the notification route was a way to ship something useful without claiming something the technology cannot yet deliver. That is a reasonable choice. It also means the answer to the headline question is: because doing it properly is genuinely hard, and doing it badly would be worse than not doing it.
What the evidence actually says, and how strong it is
Grade the evidence in three tiers, because they are not equal.
Strongest: the cuff itself. Decades of randomized trials show that lowering blood pressure with lifestyle change and medication reduces strokes, heart attacks and deaths, and every one of those trials measured pressure with a cuff. Guidelines from the AHA, the NHS and the WHO rest on this foundation (AHA; NHS). Home cuff monitoring specifically has good observational and trial support for improving diagnosis and control.
Moderate: PPG can detect patterns linked to hypertension. The algorithm behind the notification was trained on data from more than 100,000 participants and then tested in a separate clinical validation study of roughly 2,000 people whose status was confirmed against reference measurements. The figures released with the clearance indicate that the feature identified roughly four in ten people who truly had hypertension, while correctly leaving alone more than nine in ten who did not. In the language of screening, that is modest sensitivity (the share of true cases it catches) and high specificity (the share of healthy people it correctly reassures). Apple itself has said publicly that the feature will not detect every case. This is validation data from the manufacturer reviewed by a regulator, which is a legitimate tier of evidence, but it is not an independent randomized trial, and it does not tell us whether people who receive alerts end up healthier.
Weakest: outcome evidence for any wearable. There is, so far, no published randomized trial showing that a wrist-based hypertension alert reduces strokes, hospitalizations or deaths. There are plausible mechanisms and encouraging early data from the atrial fibrillation work on the same sensors, but plausibility is not proof. Expert opinion is cautiously positive about wearables as a nudge toward cuff measurement and cautiously negative about them as a replacement for it.
A missed-case rate around six in ten deserves a moment. It means a quiet watch is not a clean bill of health. It also means that in a population where nearly half of adults with hypertension do not know it, even a coarse net will pull in a very large number of people who would otherwise have found out through a stroke. Both statements are true. Holding them together is the entire skill of reading this feature correctly.
Blood pressure watch vs cuff vs other devices: a comparison
The clearest way to see where a blood pressure watch sits is to line it up against the alternatives on the questions that matter to a patient and a clinician.
| Device | What it measures | Gives a number? | Validated for diagnosis? | Best use |
|---|---|---|---|---|
| Upper-arm cuff (validated, automatic) | Arterial pressure by occluding the brachial artery | Yes, systolic and diastolic | Yes; the reference standard for home use | Diagnosis, monitoring, treatment decisions |
| Wrist cuff | Arterial pressure at the wrist | Yes | Some models; more position-sensitive than arm cuffs | When arm cuffs do not fit or are painful; check with clinician |
| Optical smartwatch with hypertension notification | PPG waveform patterns over about 30 days | No | Cleared as a screening alert only | Prompting a cuff check in people not yet diagnosed |
| Cuffless wearables estimating pressure | Pulse transit time or waveform features, calibrated to a cuff | Yes, estimated | Not accepted by major guidelines for diagnosis | Research; trend curiosity with heavy caveats |
| 24-hour ambulatory monitor | Arterial pressure via cuff at intervals day and night | Yes, dozens of readings | Yes; often the gold standard for confirming diagnosis | Confirming hypertension, catching night-time and masked patterns |
Two rows repay a closer look. The wrist cuff row surprises people: a wrist cuff is a real cuff, it does occlude an artery and it does produce a pressure reading, but the wrist artery is smaller and the reading swings if the hand is above or below heart level. Guidance from the AHA and Mayo Clinic favors upper-arm devices for this reason (Mayo Clinic).
The ambulatory row is the one clinicians love and patients tolerate. Wearing a cuff that inflates every 20 to 30 minutes for a full day is tedious, but it settles arguments. It catches white-coat hypertension, meaning readings high only in the clinic, and masked hypertension, meaning readings normal in the clinic but high at home or at night. If a watch alert leads to a cuff week and the cuff week is ambiguous, this is often the next step.
Who the feature is for, and who it is not
The eligibility rules are not fine print. They are a description of what the algorithm was and was not tested on.
The notification is intended for adults aged 22 and older who have not already been diagnosed with hypertension. It is not intended for people who are pregnant, and the manufacturer’s own guidance excludes them. Each exclusion has a reason.
Age matters because arterial stiffness, the very thing the algorithm reads, changes with age, and the training data concentrated on adults. Below 22 the pattern library is thin and the risk of false alarms or false reassurance is unknown rather than measured.
Pregnancy is the important one. Blood pressure disorders in pregnancy, including preeclampsia, can develop over days rather than months and can become dangerous quickly. A tool that needs 30 days of background data and looks for chronic patterns is the wrong instrument for a condition that can change between one prenatal visit and the next. Anyone who is pregnant and worried about blood pressure needs a cuff and their maternity team, not a wearable.
The already-diagnosed exclusion trips people up. Many users with known hypertension turn the feature on hoping it will tell them how well their treatment is working. It cannot. It was not designed to track pressure moving up or down in response to medication, and it produces no number that could be compared week to week. Someone whose treatment has brought their pressure to normal may still carry the arterial fingerprint of years of hypertension and trigger an alert, while someone whose pressure has crept up on treatment may receive nothing at all. For monitoring treatment, guidelines are unambiguous: a validated cuff, taken correctly, logged and shared with the prescribing clinician (CDC).
People with certain heart rhythm conditions, notably atrial fibrillation, may get less reliable results because the irregular beat distorts the waveform the algorithm depends on. And anyone with symptoms, which we cover in detail below, should not be waiting a month for a watch to make up its mind.
Put simply: the feature is a net for the unaware. If you already know, you already have a better tool.
Do cardiologists recommend Apple Watch? What guidelines say about wearables
The honest answer is that most cardiologists neither recommend nor discourage it, because the question is slightly off. Ask them whether they recommend home blood pressure monitoring and the answer is a resounding yes. Ask whether a wearable can do that job and the answer is not yet.
The 2025 US guideline, echoing its 2017 predecessor, places validated home cuff monitoring at the center of diagnosis and long-term management, and it treats cuffless wearable estimates as investigational. The NHS takes a similar line, describing home cuff readings and 24-hour ambulatory monitoring as the confirmation tools after a raised clinic reading (NHS). The WHO’s global guidance is built entirely around cuff measurement, largely because it has to work in clinics with no smartphones at all (WHO).
Where clinicians have warmed to wearables is in the role of prompt. A person who would never think to buy a cuff might buy one after a notification. A person who ignores a leaflet might not ignore a buzz on the wrist. The atrial fibrillation experience taught the field that optical sensors can surface real, previously unknown disease in a meaningful number of people, and also that they generate false alarms, anxiety, and unnecessary testing in others. Both lessons carry over.
There is a practical concern clinicians raise quietly. A wave of alerts arriving in primary care all at once can crowd out other work, and some of those alerts will be false. The high specificity of the feature helps here; most people without hypertension will not be flagged. But even a small false-alarm rate across tens of millions of users is a lot of appointments. The system works best when the person arrives with seven days of cuff readings already in hand, which turns a vague worry into a data-driven ten-minute conversation.
So: do cardiologists recommend it? Many would say the same thing about the watch that they say about a bathroom scale. Useful, occasionally motivating, not the thing that decides anything, and no substitute for the measurement that does.
You got an alert. What happens next
The notification comes with instructions, and for once they are worth following to the letter.
The prompt asks you to take cuff readings twice a day for seven days, morning and evening, and log them. Seven days is not arbitrary. Blood pressure varies enough day to day that a two-day sample can mislead; a week smooths out a bad night, a stressful meeting or a salty dinner. Most guidelines suggest discarding the first day, when people are still fiddling with the cuff, and averaging the rest (AHA).
If you do not own a cuff, this is the moment to get one. Choose an upper-arm model that has been independently validated; several professional organizations maintain lists of devices that have passed standardized accuracy testing, and a clinician or pharmacist can point you to them. Cuff size matters more than brand. A cuff too small for the arm reads high; too large reads low. Measure the circumference of the upper arm and match it to the range printed on the cuff.
Then take the readings and bring them, or a photo of them, to a clinician. What happens after that is a clinical decision, not a device decision. A home average at or above 135/85, the threshold many guidelines use for home readings because they run slightly lower than clinic readings, will usually lead to a conversation about confirmation, sometimes with ambulatory monitoring, and about causes and next steps. An average well below that may end the matter, or lead to a plan to recheck in a few months.
What not to do is equally clear. Do not start, stop or adjust any medication on the strength of an alert or a week of home readings. Do not assume the watch has diagnosed you; it has not, and cannot. Do not, on the other hand, dismiss it because you feel fine. Feeling fine is what hypertension usually feels like. That is why it is dangerous.
And if the cuff readings are alarmingly high on the very first day, especially with any symptoms, skip the seven-day plan and seek care the same day.
How to take a home cuff reading that a clinician will trust
Most home readings are taken wrong, and wrong in a direction that overstates pressure. Fixing the technique is the cheapest accuracy upgrade in medicine.
The setup matters more than the button. Sit in a chair with back support, feet flat on the floor, legs uncrossed. Rest the arm on a table so the cuff sits at roughly heart level; an unsupported arm can add several points. Wait five quiet minutes before the first reading, no phone, no conversation. Empty your bladder first, because a full one can nudge readings up. Avoid caffeine, exercise and smoking for 30 minutes beforehand (CDC).
Place the cuff on bare skin, not over a sleeve, with the lower edge about an inch above the elbow crease and the tubing running down the inside of the arm. It should be snug enough that you can slide only a fingertip underneath. Take two readings a minute apart and record both. If they differ by a lot, take a third.
Keep the same arm each time. Readings can legitimately differ between arms, and a consistent difference of more than 10 to 15 points is itself something to mention to a clinician (Mayo Clinic). Morning readings are best taken before any medication and before breakfast; evening readings before bed.
Bring the cuff to an appointment once a year and ask to have it checked against the clinic device. Home monitors drift, and a monitor that reads consistently five points high or low quietly corrupts every decision built on it.
There is a psychological trap worth naming. Some people, once they own a cuff, start checking hourly and chasing every number. This raises anxiety and raises the numbers, since worry itself pushes pressure up. The guideline pattern, two readings twice a day for a defined week, then a break until the next scheduled check, exists partly to protect people from their own devices. Treat the cuff as an occasional witness, not a live feed.
Done this way, a week of readings is a document a clinician can act on. Done casually, it is noise.
Understanding the numbers the watch will not give you
Because the watch stays silent on figures, you will be reading them off a cuff, and it helps to know what they mean before the first one appears.
The AHA’s categories for clinic-style readings, which the 2025 guideline preserved, run roughly as follows. Normal is below 120 systolic and below 80 diastolic. Elevated is 120 to 129 systolic with diastolic still below 80. Stage 1 hypertension is 130 to 139 systolic or 80 to 89 diastolic. Stage 2 is 140 or higher, or 90 or higher. A reading above 180 or above 120, especially with symptoms, is a hypertensive crisis and a reason to seek care immediately (AHA).
Home readings tend to run a little lower than clinic readings for the same person, which is why many guidelines treat a home average of 135/85 as roughly equivalent to a clinic 140/90. Your clinician will interpret your numbers against whichever threshold applies; the point is not to memorize cut-offs but to recognize that a single reading is a snapshot and an average is the picture.
The NHS frames it slightly differently, using 140/90 in the clinic and 135/85 at home as the usual thresholds for diagnosis, with lower targets for some groups. The numbers differ at the margins between countries. The principle does not: hypertension is defined by sustained readings, confirmed with a proper device, interpreted by a clinician who knows the rest of your history (NHS).
Two patterns deserve a mention because a watch alert sometimes uncovers them. White-coat hypertension is pressure that runs high only in medical settings and normal at home; it is common, mostly benign, and one of the reasons home readings are so valued. Masked hypertension is the reverse, normal in the clinic and high at home or overnight, and it carries real risk precisely because it hides. An optical sensor collecting data across ordinary days and nights is, in principle, better placed to notice masked patterns than a once-a-year clinic visit, and that is one of the more genuinely interesting possibilities the technology raises.
Whether it delivers on that possibility is a question for future studies, not for a notification.
Is Apple coming out with a blood pressure watch? Rumors and cuffless technology
Every few months a report suggests that the next model will finally measure blood pressure. As of early 2026, no manufacturer of a mainstream smartwatch has a cleared, guideline-accepted feature that displays a blood pressure reading without a cuff, and none has been announced.
What exists instead is a spectrum. Some smartwatches sold in certain markets offer a blood pressure estimate that must be calibrated against a cuff every few weeks. Reviews of these devices in the medical literature consistently find that they track the calibration reading closely and the true pressure loosely, drifting as the weeks pass and struggling when pressure actually changes. Regulators in the United States have not accepted them as diagnostic devices, and no major guideline recommends them for diagnosis or management.
The research pipeline is active. Groups are working on multi-wavelength optical sensors, on pressure-sensitive arrays that press gently against the wrist artery, on combining the electrical signal of the heart with the optical pulse at the wrist to time the pressure wave more precisely, and on algorithms that need calibration less often. Some of this will probably reach consumers. Whether it reaches the accuracy standard a cuff meets, within a few millimeters of mercury across a range of pressures without recalibration, is an open question and a hard one.
A useful test for any future announcement: does the device display a number, and has that number been validated against a reference standard in a published study across a diverse population, including people whose pressure is high, low and changing? If the answer to the second half is no, the number is a guess with a decimal point.
None of this makes the current notification approach a consolation prize. In some ways it is the more honest product. It claims only what it can support, it points people at the tool that actually works, and it does not tempt anyone to skip a medication because a wrist said 118 today. If a future model does deliver a validated reading, it will be big news and this article will need rewriting. Until then, the realistic answer to the question is: not yet, and the thing on your wrist now is a prompt, not a monitor.
Common myths about apple watch blood pressure, corrected
Viral posts have moved faster than the fine print. Here are the claims circulating most, and what is actually true.
Myth: the watch now measures blood pressure. It does not. It analyzes optical pulse patterns over about 30 days and issues a yes-or-no style alert. No systolic or diastolic figure is generated or displayed. The confirmation step, a week of cuff readings, exists because the watch cannot supply the number itself.
Myth: no alert means my blood pressure is fine. The validation data suggests the feature misses more cases than it catches. Silence is not clearance. Anyone over 40, or younger with risk factors, still needs periodic cuff checks whether or not a watch is involved (CDC).
Myth: an alert means I have been diagnosed. An alert is a screening signal with a meaningful false-positive rate. Diagnosis requires confirmed readings from a validated cuff, usually over a week, sometimes over 24 hours, interpreted by a clinician.
Myth: I can use it to see if my medication is working. The feature is not intended for people already diagnosed and produces no trend data. Monitoring treatment is a job for a cuff and the prescribing clinician. Never adjust a prescribed medicine on the strength of a wearable.
Myth: it works the same for everyone. Optical sensors are affected by skin, tattoos, fit, temperature, movement and heart rhythm. Performance across different skin tones has been a live concern for pulse-based wearables generally, and the manufacturer’s validation reported testing across a range of participants, but real-world performance in every group remains something independent studies will need to confirm.
Myth: it is useless because it misses cases. A screening tool that catches four in ten of a silent, common, treatable disease among people who would otherwise not be checked is not useless. It is limited, and the limits are exactly why the cuff step exists.
Myth: cardiologists are against it. Most are neutral to mildly positive about anything that gets an unaware person to a cuff, and firmly opposed to anything that keeps a diagnosed person away from one.
The pattern across all of these is the same. The device is being credited with the job of the cuff, either to praise it or to dismiss it. It has a different job.
The quiet danger of a quiet watch: false reassurance
Of all the ways this feature could go wrong, the loudest, a flood of false alarms, is not the one that worries public health people most. The quiet one is.
Hypertension earns its nickname, the silent killer, honestly. In the great majority of people it causes no symptoms for years while it stiffens arteries, thickens the heart muscle, scars the kidneys and weakens the small vessels of the brain (Mayo Clinic). The first sign is often the stroke. That is why every guideline body recommends periodic measurement in adults regardless of how they feel.
Now imagine a person who wears a watch daily, has heard it can detect hypertension, and receives nothing for two years. It is very natural to conclude that all is well and to let the routine check slide. Given a sensitivity in the region of four in ten, that person has roughly a 60 percent chance of being missed if they do in fact have the condition. The watch did nothing wrong; it never promised to catch everyone. The reasoning did.
The same problem shadowed early wearable heart-rhythm features, and clinicians learned to say a specific sentence to patients: the absence of an alert is not the presence of health. It bears repeating here in exactly those words.
A practical rule of thumb from mainstream guidance: adults with normal readings should have their blood pressure checked at least every couple of years, more often with age or risk factors such as excess weight, diabetes, kidney disease, a family history, or a previous elevated reading. Many pharmacies and community settings offer cuff checks. None of this changes because a watch is on the wrist.
The feature works best as one more reason to own a cuff, not as a reason not to. The most useful thing the notification does may not be the alert at all. It may be the conversation it starts, in which someone who never thought about blood pressure learns that they should be checking it anyway.
When to see a doctor: red flags that should never wait for a notification
Everything above concerns slow, silent hypertension, which is what the watch is built to find. Some situations are neither slow nor silent, and no wearable, quiet or alarming, should factor into the decision to get help.
Seek emergency care immediately, by calling emergency services, if any of the following occur, whether or not you have a cuff reading:
- Sudden severe headache unlike any you have had before, particularly with confusion, vision changes or difficulty speaking.
- Chest pain, pressure or tightness, especially spreading to the arm, jaw or back, or accompanied by sweating, nausea or shortness of breath.
- Weakness or numbness on one side of the face or body, a drooping face, slurred speech or sudden loss of balance, which are signs of a possible stroke.
- Sudden shortness of breath at rest or inability to lie flat.
- A cuff reading above 180 systolic or above 120 diastolic, repeated a few minutes later, especially with any of the symptoms above.
- In pregnancy: severe headache, visual disturbance, upper abdominal pain, sudden swelling of the face or hands, or a reading of 140/90 or higher, all of which need same-day assessment by the maternity team.
Book a prompt but non-emergency appointment if you receive a hypertension notification; if your seven-day home average is at or above 135/85; if home readings vary wildly from day to day; if you notice a consistent difference of more than 10 to 15 points between arms; if you have persistent morning headaches, nosebleeds, dizziness or palpitations; or if you already have hypertension and your home readings have drifted upward despite treatment (NHS).
Bring the cuff readings, the dates and times, the arm used, and a list of every medicine and supplement you take, including over-the-counter decongestants and anti-inflammatories, which can raise pressure.
Every decision that follows belongs to the clinician who examines you. Whether to confirm with ambulatory monitoring, whether to test for underlying causes, whether lifestyle change alone is enough, whether any medication is warranted and which one: these are judgments that require your full history, an examination and often blood and urine tests. A watch cannot make them and a magazine article should not try. Our job is only to make sure the alert, or the absence of one, gets you to the person who can.
Frequently asked questions
Can an Apple Watch measure blood pressure?
No. The watch does not measure blood pressure and displays no systolic or diastolic reading. Its hypertension notification uses the optical heart sensor to analyze pulse-wave patterns over about 30 days and alerts you if those patterns resemble sustained high blood pressure. Confirming whether you actually have hypertension still requires a validated upper-arm cuff and a clinician’s interpretation of the readings.
What does an apple watch hypertension notification actually mean?
It means the algorithm found a month-long pattern in your pulse data that is more typical of people with chronic high blood pressure than of people without it. It is a screening signal, not a diagnosis. The recommended next step is seven days of morning and evening cuff readings, then a conversation with a clinician who decides whether further confirmation, such as 24-hour ambulatory monitoring, is needed.
Is Apple coming out with a blood pressure watch that shows numbers?
Nothing of that kind has been announced or cleared as of early 2026. Reports about future models surface regularly, but no mainstream smartwatch currently has a validated, guideline-accepted feature that displays a blood pressure reading without a cuff. Cuffless estimation remains a research area because pressure inferred from light or pulse timing drifts and needs frequent recalibration against a real cuff.
Do cardiologists recommend Apple Watch for blood pressure?
Most take a middle position: they strongly recommend home monitoring with a validated cuff and view wearables as a useful prompt rather than a measurement tool. Guidelines from the American Heart Association, NHS and WHO all rest on cuff readings, and the 2025 US guideline describes cuffless wearables as investigational. A watch that sends someone to buy a cuff is welcome; a watch that replaces one is not.
Why doesn't the Apple Watch do blood pressure like it does heart rate?
Counting heartbeats only requires detecting each pulse, which light through the skin does well. Measuring pressure requires knowing the force inside the artery, which a cuff obtains by squeezing the vessel shut and sensing when flow returns. A wrist sensor can only infer pressure from indirect features such as pulse timing, and that relationship varies from person to person and shifts over weeks, so the estimates are not accurate enough for diagnosis.
How do I check my blood pressure with my iPhone?
A phone alone cannot measure blood pressure; camera-based apps that claim to are not validated for that purpose. The reliable method is a validated upper-arm cuff, and many models connect wirelessly so readings appear in the phone’s health app alongside the watch’s data. That log, showing dates, times and both numbers, is exactly what a clinician wants to see after a hypertension notification.
How accurate is a blood pressure watch compared with a cuff?
A validated upper-arm cuff is expected to land within a few millimeters of mercury of a reference measurement. A blood pressure watch that only issues alerts has no accuracy figure in that sense, because it produces no number; its validation is described by sensitivity, roughly four in ten cases caught, and specificity, more than nine in ten healthy people correctly reassured. Watches that estimate a number typically drift and track their calibration reading rather than true pressure.
Who should not rely on the hypertension notification feature?
Anyone under 22, anyone who is pregnant, and anyone already diagnosed with hypertension, because the feature was not designed or tested for those groups. People with irregular heart rhythms such as atrial fibrillation may also get less reliable results. Pregnancy is the critical exclusion: blood pressure disorders in pregnancy can develop over days, far faster than a feature that needs 30 days of data can respond.
If I get an alert, should I change my blood pressure medication?
No. Never start, stop or adjust any prescribed medicine on the basis of a wearable alert or home readings. The feature is not intended for people already on treatment and produces no number that could guide a change. Record a week of cuff readings, bring them to the clinician who prescribes for you, and let that person decide whether anything about your care should change.
My watch has never alerted me. Does that mean my blood pressure is normal?
Not necessarily. The validation data suggests the feature misses more cases than it catches, so silence is not reassurance. Adults should still have blood pressure checked with a cuff at least every couple of years, and more often with age or risk factors such as diabetes, kidney disease, excess weight or a family history. Treat the watch as one more reason to own a cuff, not a reason to skip one.
References
- CDC: About High Blood Pressure
- World Health Organization: Hypertension fact sheet
- NHS: High blood pressure (hypertension)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Can Immunotherapy Cure Stage 4 Cancer? What a Durable Response Means
Immunotherapy does not reliably cure stage 4 cancer, but for a minority of patients with certain cancers it has produced remissions lasting many years,…

How Long a Pacemaker Lasts: Battery Life and Longevity
A pacemaker's battery typically lasts somewhere between about 5 and 15 years, with many lasting around 6 to 10, depending on how often the…

Is Chemotherapy Painful? What Treatment Actually Feels Like
Chemotherapy is usually not painful while it is being given; most people feel only the needle and perhaps a cool sensation from the drip.…

Ewing Sarcoma vs Osteosarcoma: The Difference, When Each Is Used and How to Decide
Ewing sarcoma and osteosarcoma are both rare primary bone cancers that mostly affect young people, but they are distinct diseases. Osteosarcoma arises from bone-forming…

Signs of Leukemia in Kids: What to Watch for and When to Seek Care
Signs of leukemia in kids most often include unusual tiredness, pale skin, fevers or infections that keep returning, easy bruising or tiny red skin…
Stage 4 Lung Cancer Life Expectancy with Treatment: What It Means, What to Expect and When to See a Specialist
With treatment, stage 4 lung cancer life expectancy varies widely from person to person. Population data show roughly 9 percent of people diagnosed with…