

Can You Swim With Molluscum Contagiosum? Sports, Shared Towels and Ways to Limit Spread

Key Takeaways
- The CDC reports no evidence that molluscum spreads through chlorinated pool water; the risk sits with shared towels, kickboards, goggles and skin contact at the poolside.
- Neither the NHS nor the CDC requires children with molluscum to miss school, nursery or swimming; covering bumps with watertight bandages and using a personal towel is the recommended approach.
- Bumps are typically 2 to 5 millimeters across and usually clear on their own within 6 to 12 months, with some cases lasting up to 4 years according to the CDC.
- The incubation period is typically 2 to 7 weeks and can stretch to 6 months, which is why pinpointing a single pool visit as the source is rarely possible.
- Shaving through bumps, scratching them and having eczema are the main reasons a few lesions become dozens, through a process called autoinoculation.
- Treated bumps can shed virus while they blister and heal, so covering, towel and equipment habits should continue until the skin is completely clear.
In most cases, yes. Public health guidance does not require people with molluscum contagiosum to stay out of swimming pools, because the virus has not been shown to spread through properly treated water. It spreads through skin-to-skin contact and shared items such as towels, kickboards and goggles. Covering bumps with watertight bandages, using your own towel and skipping close-contact sports until bumps heal limits spread.
The swim bag is already packed when a parent notices it: a cluster of small, pearly bumps along a child’s upper arm, each with a tiny dimple in the center. The lesson starts in forty minutes. Is this contagious? Will the pool make it worse? Will other parents mind? That scramble at the kitchen table is where most questions about swimming with molluscum begin.
Adults face a version of it too. A swimmer who trains five mornings a week finds a few bumps on the inner thigh. A triathlete wonders whether to pull out of the relay. The instinct is often to assume the water itself is the problem, and that instinct turns out to be mostly wrong.
What follows lays out what the virus actually does on skin, where the real transmission risk sits in a pool complex, how to cover bumps so a child can still take the lesson, and the handful of situations where it is sensible to pause and ask a clinician first.
What molluscum contagiosum is and how the virus actually works
Molluscum contagiosum is a skin infection caused by a poxvirus, a family of viruses that live in the outer layer of skin rather than circulating through the body. The result is a crop of small, firm, dome-shaped bumps, usually flesh-colored or pink, often with a dimple in the middle. The Centers for Disease Control and Prevention (CDC) describes them as typically 2 to 5 millimeters across, roughly the size of a pinhead to a pencil eraser.
The mechanism is unusually local. The virus infects keratinocytes, the cells that make up most of the epidermis, and persuades them to build a tiny, walled-off factory. That factory is the bump. Its waxy core is packed with viral particles, which is why a scratched or squeezed lesion is far more contagious than an intact one. The virus does not travel in blood, does not cause fever, and does not leave a person feeling unwell.
Because the infection stays in the skin, the immune system can be slow to notice it. This explains the long timeline. According to the CDC, bumps usually clear on their own within 6 to 12 months, although some people carry them for up to 4 years. Each individual bump may last a couple of months before flattening and fading, while new ones appear elsewhere through a process called autoinoculation, meaning the person spreads the virus to their own skin by touch.
Children between the ages of roughly 1 and 10 are the most frequently affected group, partly because of close play and shared bath or pool items, and partly because their immune systems have not met the virus before. Adults get it too, often through sexual contact or contact sports, and people with weakened immune systems can develop larger or more numerous bumps.
How molluscum spreads from skin to skin (and from towel to skin)
Transmission needs the virus to move from one patch of skin to another. The National Health Service (NHS) lists three routes: direct skin contact, contact with objects that have touched the bumps, and sexual contact in adults. None of these requires water.
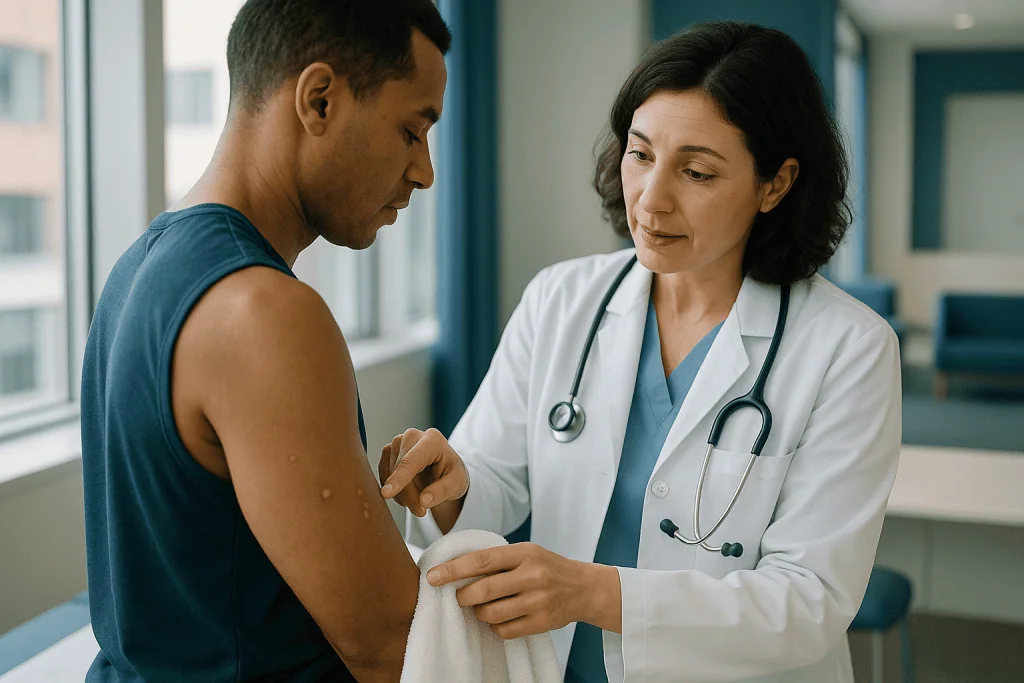
Direct contact is the simplest. A child with bumps on the forearm wrestles with a sibling, and viral particles from a cracked lesion settle on the sibling’s skin. The virus then needs a way in, usually a microscopic break, a scratch or softened, waterlogged skin. This matters for swimmers, because skin that has been soaking for an hour is more permeable than dry skin.
Indirect contact is where pools come into the conversation. Poxviruses are relatively stable outside the body, and the CDC notes that molluscum can spread via shared towels, clothing, pool toys and kickboards. A damp towel left in a shared bin, then used to dry a different child’s face, is a plausible vehicle. So is a pair of borrowed goggles pressed against the skin around the eyes.
Autoinoculation deserves its own mention. Scratching a bump and then rubbing another part of the body is the most common way the number of lesions grows. Shaving through bumps is another well-documented accelerator: the blade opens several lesions at once and drags virus across a wide area. For swimmers who shave legs, arms or chest before competition, this is a practical concern.
Incubation, the gap between exposure and visible bumps, is long. The CDC gives a typical range of 2 to 7 weeks, with some cases taking up to 6 months. That delay is why families often cannot pinpoint where the infection came from, and why blaming a particular pool is rarely justified.
Does pool water spread molluscum contagiosum?
This is the question most people type first, and the honest answer has two parts. The first part is reassuring: the CDC states that there is no evidence the virus spreads through properly chlorinated swimming pool water. Chlorine and other disinfectants used in regulated pools inactivate many viruses, and the sheer dilution of a pool makes transmission through the water itself very unlikely.
The second part is where the nuance lives. Pools have been associated with molluscum in observational studies, and public health agencies are candid that the reason is not fully settled. The leading explanation, which the CDC describes, is that the pool environment, rather than the water, drives spread: shared kickboards, pool noodles, towels, benches, and warm wet skin pressed together in a crowded shallow end. Swimming lessons involve instructors steadying children’s bodies and children clinging to the same lane rope. Those are skin contacts and object contacts, not water contacts.
In plain terms, a molluscum contagiosum swimming pool risk exists, but it sits at the poolside and in the changing room. The water is the least worrying part of the trip.
Hot tubs and poorly maintained pools are a different matter for general hygiene, and the CDC’s healthy swimming guidance covers the organisms that do spread through water, such as those causing diarrheal illness. Molluscum is not on that list. A pool with a strong chemical smell is not necessarily cleaner; that odor often comes from chloramines, compounds formed when chlorine reacts with sweat and urine, and it signals a pool working harder than it should.
So the water itself is not the reason to keep a child home. The question becomes how to manage the bumps, the towel and the kickboard.
Swimming with molluscum: who usually keeps swimming and who is asked to wait
Neither the CDC nor the NHS advises excluding people with molluscum from swimming. The NHS specifically says children with molluscum do not need to stay away from school, nursery or swimming. That is the baseline, and it covers the large majority of cases: a handful of bumps, no inflammation, a person who feels well.
Many facilities still ask that visible lesions be covered. The CDC recommends covering bumps with watertight bandages before swimming and removing them afterward so the skin can dry. Where bumps sit under a swimsuit, the suit itself does the job. A long-sleeved rash guard covers arms and torso and has the side benefit of reducing sun exposure.
There are situations where a clinician may suggest a pause rather than a bandage:
- Bumps that are red, swollen, weeping or crusted, which can indicate a secondary bacterial infection and should be assessed before pool exposure.
- Bumps on the face or eyelids that cannot be covered.
- Very extensive lesions in someone with eczema, where skin barrier damage makes both spread and irritation more likely.
- A weakened immune system, for example from chemotherapy, organ transplant medicines or advanced HIV, where molluscum can behave more aggressively and warrants a tailored plan.
- Recently treated bumps that are still raw or blistered from cryotherapy or a topical agent.
Competitive swimmers face an added layer: governing bodies and coaches may have their own skin-check policies, particularly for events with shared warm-up areas. Those rules are organizational, not medical, and the treating clinician can usually provide a note that describes the condition in neutral terms.
For most families, the realistic plan is this: cover what can be covered, pack a personal towel, skip the shared toys for a while, and keep the lesson. The decision for any individual, especially a child with other health conditions, belongs with the person’s own doctor or nurse.
How to cover molluscum while swimming (the same approach works for warts)
Covering a bump does two things. It stops viral particles shedding onto shared surfaces, and it protects the lesion from being knocked or scratched, which is when it becomes most contagious. Done well, it takes a few minutes and lasts a lesson.
Start with dry, clean skin; adhesive does not grip damp skin. Choose a bandage labeled waterproof or watertight, sized so the adhesive border sits on healthy skin all the way around. Press the edges down firmly for several seconds to let the adhesive warm and seal. For clusters, one larger dressing is better than several small ones that leave gaps.
Film dressings, the thin transparent sheets used over intravenous lines, are a useful option for awkward areas such as the inner elbow, because they flex with movement. Some people reinforce the edges with a strip of waterproof medical tape.
For the torso and limbs, clothing is the simplest cover. A rash guard or swim leggings keeps bumps enclosed without any adhesive, which matters for children whose skin reacts to bandages or who pick at them.
After the swim, the CDC’s advice is to remove the bandage and let the area dry. Leaving a wet dressing in place for hours softens the skin underneath, which is the opposite of what the lesion needs. Dry with a personal towel, patting rather than rubbing, and dress the bump fresh if it is going to be exposed again.
A few things not to do: do not squeeze or pop bumps to speed things along, do not use a dressing that has lifted at one corner, and do not share the roll of tape or the tube of ointment between affected and unaffected family members. Warts, caused by a different virus, benefit from the same routine; the logic of containment is identical.
Molluscum and shared towels, kickboards and changing rooms: where the real risk hides
If pool water is the wrong place to look, the right places are easy to list. They are the objects and surfaces that touch bare, wet skin and then touch someone else’s.
Towels sit at the top. The NHS and CDC both single out towel sharing as a route for molluscum. A towel does more than carry virus; it is used with friction on exactly the areas where bumps form, and it is often shared casually between siblings or teammates. One towel per person, washed after each use, is the single most effective habit a family can adopt.
Kickboards, pull buoys and pool noodles are gripped under the arms and between the thighs, two classic molluscum sites in children. Where a facility supplies these, wiping them is helpful, but a personal set is better during an active outbreak. Goggles and swim caps should never be borrowed.
Changing-room benches and floors matter less for molluscum than for plantar warts and athlete’s foot, which are more adapted to surfaces. Even so, sitting bare-skinned on a wet bench is avoidable: a towel laid down first, or shorts kept on until the last moment, removes the contact.
Showers are often shared too. Soap and running water reduce the number of viral particles on skin, so a rinse before and after swimming is sensible for everyone, and pool operators request it for water quality reasons anyway. Flip-flops in the shower protect against unrelated fungal infections.
At home, the same logic applies to bath toys and washcloths. The NHS advises not sharing towels, flannels or clothes with someone who has molluscum, and bathing children separately while bumps are present when that is practical. None of this requires disinfecting the house; it requires ending the habit of items passing from one body to another while damp.
Contact sports, gyms and mats: how different settings compare
Swimming is a low-contact sport. The more skin presses against other skin, the higher the transmission risk, which is why wrestling, judo and rugby appear more often than swimming in reports of molluscum spreading through teams. The table below compares common settings by the type of contact involved and the practical precaution that matters most.
| Setting | Main route of spread | Precaution that matters most |
|---|---|---|
| Swimming pool water | No evidence of water transmission (CDC) | None needed for the water itself |
| Swimming lessons, shallow end | Skin contact, shared kickboards and toys | Cover bumps, bring personal equipment |
| Changing rooms and showers | Shared towels and benches | One towel per person, sit on a towel |
| Wrestling, judo, rugby | Prolonged skin-to-skin contact, mats | Cover lesions; many programs ask athletes to sit out until healed |
| Gym and weight rooms | Equipment and benches touched by bare skin | Long sleeves or a towel barrier, wipe equipment |
| Dance, gymnastics | Bare feet and hands on shared apparatus | Cover bumps on hands and feet, personal grips and towels |
For mat-based sports, the standard approach in many sports medicine policies is that athletes with uncovered, active molluscum are held out of competition until lesions have been treated or resolved, because a bandage rarely survives a wrestling round. That is a sporting-body rule rather than a public health requirement, and clubs vary. A clinician’s letter describing the lesions and their coverage can help coaches make a consistent decision.
The pattern across the table is clear: the risk tracks skin contact and shared damp objects, not water. Swimming, with its personal lane and chlorinated environment, sits toward the lower end, provided the towel rule holds.
Can I swim in a pool with a wart, and can STIs spread in a swimming pool?
Two neighboring questions come up constantly alongside molluscum, and they deserve straight answers.
Warts are caused by human papillomavirus (HPV), a different virus that also infects the outer skin. Like molluscum, HPV spreads through skin contact and contaminated surfaces, not through chlorinated water. Plantar warts on the soles are strongly linked to walking barefoot on wet poolside floors and changing-room tiles, where softened skin meets viral particles shed by others. The NHS does not require people with warts to avoid swimming but recommends covering them with a waterproof plaster and wearing flip-flops in communal areas. So yes, you can swim with a wart; the floor, not the water, is the concern.
Sexually transmitted infections (STIs) do not spread in swimming pools. Organisms such as chlamydia, gonorrhea and HIV cannot survive dilution and disinfection in pool water, and they require intimate mucosal contact to transmit. Molluscum in adults is sometimes classed alongside STIs because genital bumps are commonly acquired during sexual contact. The CDC notes this, and it is worth stating plainly: that transmission happens through skin-to-skin contact during sex, not through sharing a pool or a hot tub with someone who has bumps.
A related worry is pubic lice or scabies in pools. Both need prolonged close body contact or shared bedding and clothing; neither is a water-borne risk in a chlorinated pool.
What this cluster of questions shares is a reasonable fear about communal water that the evidence does not support. The organisms that genuinely travel through pool water are mostly those causing gastrointestinal illness, which the CDC’s healthy swimming program addresses with advice about not swimming while having diarrhea and not swallowing water. Skin viruses travel by touch.
Eczema, shaving and scratching: why spread speeds up on some skin
Two children can sit in the same swim class with the same exposure, and one ends up with 6 bumps while the other has 60. The difference is usually the skin barrier.
Eczema, also called atopic dermatitis, is a condition in which the outer skin layer is dry, inflamed and leaky. The Mayo Clinic lists eczema as a factor that makes molluscum more likely and more widespread. The reasons are mechanical and immunological. Cracked, itchy skin provides many entry points for the virus; scratching moves viral particles from bump to bump; and the local immune response in eczematous skin is skewed in a way that handles this particular virus poorly. Children with eczema frequently develop molluscum in the folds of elbows and knees, exactly where their eczema flares.
For these children, pool time brings a trade-off. Chlorinated water can dry and irritate eczema-prone skin, though some people find swimming soothes itching. Rinsing in fresh water immediately after swimming and applying an emollient, a plain moisturizing cream or ointment, within a few minutes of drying helps restore the barrier. Keeping eczema well controlled, under the guidance of the child’s clinician, is one of the more effective ways to limit how far molluscum spreads.
Shaving is the adult equivalent. A razor glides over several bumps, opens them, and seeds the virus across a limb. Swimmers who shave for competition may want to leave affected areas unshaved until bumps resolve, or switch to clippers that do not cut the surface. The same applies to waxing and to exfoliating scrubs.
Scratching unites both groups. Keeping nails short, treating itch rather than tolerating it, and covering bumps that are being picked at all reduce autoinoculation. None of these steps is dramatic; collectively they are the difference between a brief episode and a long one.
Treatment options for molluscum: what each one does and does not do
Because molluscum clears on its own in most otherwise healthy people, both the NHS and CDC describe watchful waiting as a legitimate option, particularly for children. Treatment is considered when bumps are extensive, troublesome, in sensitive locations, causing distress, or in someone with a weakened immune system. Each approach targets the bump rather than the virus in the body, and each has trade-offs that a clinician weighs against the person’s age and skin.
Physical destruction methods include cryotherapy, in which liquid nitrogen freezes the lesion, and curettage, in which the core is scraped out with a small instrument. The Mayo Clinic notes these can be painful and may leave small scars or color changes, which is why they are used selectively in young children.
Topical agents applied by a clinician include cantharidin, a blistering agent derived from beetles that lifts the lesion off, and acids such as salicylic or trichloroacetic acid. Prescription creams used at home include retinoid-type agents and podophyllotoxin. Imiquimod, an immune-response modifier, is sometimes mentioned, although the CDC points out that clinical trials in children did not show benefit. A nitric oxide-releasing gel has also been approved in the United States for molluscum. How any of these is used, and whether at all, is a decision for the prescribing clinician.
What treatment cannot do is make a person non-contagious the next day. Treated bumps often blister or crust for a week or two, and during that time they shed virus and should stay covered. New bumps may appear from earlier exposures even after a successful session. Several visits spaced weeks apart are common.
Treatment does not shorten the incubation of lesions already brewing beneath the surface, and it does not prevent reinfection from another person. It is a way of managing visible bumps, not of removing the virus from the household.
What the following weeks and months usually look like
Molluscum operates on a slower clock than most skin infections, and knowing the shape of the timeline removes a lot of anxiety.
In the first weeks after bumps appear, the count often rises. This is not treatment failure or pool contamination; it reflects lesions from the original exposure surfacing after their 2 to 7 week incubation, plus autoinoculation. A family may see a few bumps become a dozen over a month.
Individual bumps then follow a cycle. A lesion grows over a few weeks, sits at full size, and at some point becomes red and slightly swollen. The CDC and NHS both describe this inflamed phase as a sign the immune system has recognized the bump and is clearing it, provided there is no spreading redness, pus or pain. Within days to a couple of weeks of that reaction, the bump flattens and fades, sometimes leaving a small pink mark that settles over months.
The whole episode, from first bump to last, typically runs 6 to 12 months according to the CDC, and the NHS gives up to 18 months as a common range. A minority of people, more often those with eczema or weakened immunity, carry bumps for longer, with the CDC citing up to 4 years at the outer end.
For swimmers, this means planning for the long haul rather than a two-week break. Covering bumps, keeping a personal towel and avoiding shared equipment are habits for a season, not a weekend. Children can usually keep up every lesson throughout.
Scarring is uncommon when bumps are left to resolve without squeezing. Scratched or infected lesions, and some aggressive treatments, carry a higher chance of small pitted scars. Once the last bump has gone, a person is considered no longer contagious, and the virus does not reactivate later in the way herpes viruses do. Reinfection from a new exposure remains possible.
What people often get wrong about swimming with molluscum
Some myths about molluscum are harmless. Others lead to children missing months of swimming lessons or adults scrubbing their skin raw. Here are the ones clinicians hear most, with what the evidence actually says.
“The pool gave my child molluscum.” Possibly the poolside did, through a towel or a kickboard, but the water almost certainly did not. The incubation period of weeks to months also makes it hard to assign blame to any single outing.
“Chlorine will kill the bumps.” Chlorine acts on viral particles in water, not on virus sealed inside skin cells. Swimming has no treatment effect on existing lesions.
“Molluscum means the child must be kept home.” The NHS explicitly states that exclusion from school, nursery or swimming is not needed. Covering bumps and not sharing towels is the recommended approach.
“Popping the bumps gets rid of them faster.” Squeezing releases a core full of virus onto the surrounding skin and under the fingernails, which is the most reliable way to multiply lesions and risk bacterial infection.
“It is a sexually transmitted infection, so adults should be ashamed of it.” In adults, genital molluscum is often acquired through sexual contact, but the same virus spreads through sport, shared gym towels and household contact. It carries no implication about anyone’s behavior, and in children it is unrelated to sexual contact.
“Over-the-counter wart remedies work on molluscum.” Evidence for self-applied products is limited, and the NHS advises against treating molluscum at home without clinical advice because of irritation and scarring risk, particularly on children’s skin.
“Once treated, you are no longer contagious.” Treated lesions shed virus while healing, and new ones may still surface. The towel and bandage habits continue until the skin is clear.
Can swimming improve skin health? Chlorine, dryness and the upside of exercise
People searching about molluscum and pools often ask a broader question: is swimming good or bad for the skin? The honest answer is that the exercise is good for almost everyone and the chemistry is neutral to mildly drying, depending on the skin.
Regular physical activity improves circulation, sleep and stress regulation, all of which show up in skin over time, and swimming is one of the few activities that is low-impact, full-body and accessible across ages and weights. The CDC’s healthy swimming resources frame water-based exercise as a valuable option for people with joint pain and for older adults. None of this translates into a direct effect on molluscum, but it is a reason not to abandon the pool over a self-limiting skin infection.
Chlorine and its by-products do strip some natural oils from the skin surface. For most swimmers this is barely noticeable. For people with eczema or very dry skin, it can mean tightness and itching after a session. A quick fresh-water shower, a pat dry with a personal towel and an emollient within a few minutes address most of this. Swimmers who notice persistent redness or stinging on healthy skin may be reacting to chloramines rather than chlorine itself, and a well-ventilated or well-maintained pool often makes a noticeable difference.
There is no good evidence that salt water, chlorinated water or hot tubs treat molluscum, warts or any viral skin infection. Claims that a particular pool type or water temperature clears bumps are not supported by mainstream medical sources.
Taken together, swimming during a molluscum episode is a matter of containing a nuisance, not of weighing a health risk. The exercise benefit is real; the water risk is not; the towel risk is manageable.
Questions to ask your care team
A short appointment goes further when the questions are ready. These are the ones that matter most for a swimmer or an active child with molluscum, phrased so a clinician can answer directly.
- Are these bumps definitely molluscum, or could they be something else such as warts, milia or a different rash?
- Is it reasonable to keep swimming lessons and training going, and are there specific bumps you would want covered or that cannot be covered?
- Do any of the bumps look inflamed or infected in a way that needs attention before the next pool session?
- Given my child’s eczema (if relevant), how should we adjust the skin care routine around swimming?
- Is watchful waiting appropriate here, or is there a reason to consider treatment now, such as location, number of bumps or distress?
- If treatment is offered, what does each option involve, how many visits are typical, and what are the risks of scarring or color change?
- How long after a treatment session should treated areas stay covered and out of the pool?
- Are there signs that would mean we should come back sooner than planned?
- Could you provide a short letter for the swim club or school explaining that exclusion is not required and describing how lesions are being covered?
- For adults: should a sexual partner be checked, and is screening for other infections sensible in my situation?
- Does anyone else in the household need to change habits, such as bathing or towel use?
Writing down the answers, including the expected timeline, makes the next conversation with a coach or a worried relative far easier. The treating team sees the lesions in person and knows the person’s history; their judgment on any of these points takes precedence over general guidance.
When to call your doctor
Most molluscum episodes never need urgent care. Still, a few patterns should prompt a call to a doctor or nurse rather than another week of waiting, especially in someone who is swimming regularly.
- A bump or the skin around it becomes hot, increasingly painful, swollen or streaked with spreading redness, or starts to leak pus. These are signs of a bacterial skin infection, which can develop when lesions are scratched and then soaked.
- Bumps on or near the eyelid or eye, which can irritate the eye surface and are difficult to cover for swimming.
- Fever, feeling generally unwell or swollen lymph nodes alongside the skin changes. Molluscum on its own does not cause these.
- Rapid spread or very large bumps, particularly in anyone with a weakened immune system from illness or medicines, where the Mayo Clinic notes that molluscum can be more extensive and harder to manage.
- Bumps that bleed easily, look unusual in color, or do not match the typical pearly, dimpled appearance. Other conditions can mimic molluscum and a clinician should confirm the diagnosis.
- Bumps in the genital area in an adult, which warrant assessment and possibly screening for other infections acquired the same way.
- Lesions that have not changed at all after 18 months, or that are causing significant distress, embarrassment or disrupted sleep from itching.
- A reaction to a treatment, such as blistering far beyond the treated spot, severe pain or signs of allergy.
For anyone, a child or an adult, who develops a fever with a rapidly spreading red, tender area of skin, same-day medical attention is appropriate. Otherwise, a routine appointment is the right setting to confirm what the bumps are, agree on whether to wait or treat, and settle the practical questions about pools and sport. Those decisions, including whether and when to pause swimming, rest with the treating team.
Frequently asked questions
Can kids swim with molluscum?
Yes, in most cases. The NHS states that children with molluscum do not need to be kept away from school, nursery or swimming. Public health advice is to cover visible bumps with watertight bandages or a rash guard, give the child their own towel, and avoid shared kickboards and pool toys while bumps are present. A clinician may suggest a pause if bumps are inflamed, infected, on the eyelids or very extensive.
Does molluscum contagiosum spread in a swimming pool?
Not through the water itself, according to the CDC, which reports no evidence of transmission via properly treated pool water. Pools have been linked to molluscum in studies, and the likely explanation is poolside contact: shared towels, kickboards, benches and wet skin pressed together during lessons. Managing those contacts, rather than avoiding the water, is what limits spread.
How do I cover molluscum while swimming?
Apply a waterproof bandage to clean, dry skin, making sure the adhesive border sits on healthy skin all around, and press the edges firmly. Flexible film dressings suit joints; a rash guard or swim leggings covers torso and limbs without adhesive. After swimming, remove the bandage and let the skin dry, as the CDC advises, then re-cover if needed.
Can molluscum spread through shared towels?
Yes. Both the CDC and NHS list shared towels, clothing and personal items as routes of transmission, because the virus is relatively stable on damp fabric and towels are rubbed over exactly the areas where bumps form. One towel per person, not shared and washed after use, is the most effective single habit for a household or swim team during an outbreak.
Can I swim in a pool with a wart?
Yes. Warts, caused by human papillomavirus, spread through skin contact and wet floors rather than pool water. The NHS does not require people with warts to avoid swimming but recommends covering them with a waterproof plaster and wearing flip-flops in changing rooms and showers, where plantar warts are most often picked up from softened bare feet.
Can STIs spread in a swimming pool?
No. Organisms such as chlamydia, gonorrhea and HIV do not survive dilution and disinfection in pool water and require direct intimate contact to transmit. Molluscum in adults is sometimes grouped with STIs because genital bumps are often acquired during sex, but that is skin-to-skin transmission. Sharing a pool or hot tub with someone who has molluscum is not how it spreads.
How long is molluscum contagious?
For as long as bumps are present on the skin. The CDC describes a typical course of 6 to 12 months, with some cases lasting up to 4 years, and the NHS gives up to 18 months as a common range. Once the last bump has fully resolved, the person is no longer considered contagious. Treated bumps remain contagious while they blister and heal.
Should I stop swimming after molluscum treatment?
Often only briefly. Treated bumps may blister or crust for a week or two and shed virus during that time, so they should stay covered and dry, and some clinicians advise a short break from pools until the skin has settled. The right interval depends on the treatment used and where the bumps are, so follow the instructions from the person who performed the treatment.
Can swimming improve skin health?
Indirectly, yes. Swimming is low-impact, full-body exercise, and regular activity supports circulation, sleep and stress control, which benefit skin over time. Chlorine can dry the skin surface, especially in people with eczema, so a fresh-water rinse and a moisturizer soon after leaving the pool help. There is no evidence that chlorinated or salt water treats molluscum or warts.
Why is molluscum worse in children with eczema?
Eczema leaves the skin barrier dry, cracked and inflamed, giving the virus many entry points, while scratching carries particles from bump to bump. The Mayo Clinic lists eczema as a factor linked to more widespread molluscum. Keeping eczema well controlled with a clinician’s guidance, moisturizing after swimming and keeping nails short all help limit how far the bumps spread.
References
- CDC: About Molluscum Contagiosum
- NHS: Molluscum contagiosum
- MedlinePlus: Molluscum contagiosum
- CDC: About Healthy Swimming
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Does Allergy Testing Help With Eczema? When Dermatologists Recommend It and What It Can Show
Allergy testing does not diagnose eczema, and it helps only in specific situations. Dermatologists usually suggest it when eczema stays severe despite good skin…
Repairing the Skin Barrier After Contact Dermatitis: Moisturizers, Gloves and Gentle Cleansing
Repairing the skin barrier after contact dermatitis rests on three habits: removing or avoiding the trigger, applying a plain fragrance-free emollient generously and often,…

Impetigo Myths Corrected: Why It Is Not a Sign of Poor Hygiene and Still Needs Treatment
Impetigo is a contagious skin infection that begins when common bacteria, usually Staphylococcus aureus or group A Streptococcus, enter skin through a scratch, insect…

Is It Irritant or Allergic Contact Dermatitis? How Dermatologists Tell the Two Apart
Irritant contact dermatitis is direct chemical or physical damage to the skin barrier and can affect anyone after enough exposure, often within minutes to…

How Medicated Dandruff Shampoos Are Meant to Be Used: Contact Time, Rotation and Rinsing
Medicated dandruff shampoo works best when it is applied to a wet scalp rather than the hair lengths, left in contact for the time…

When Folliculitis Needs a Doctor: Bumps That Spread, Recur or Turn Into Painful Boils
See a doctor for folliculitis when the bumps keep spreading after a few days of gentle self-care, keep coming back, grow into a painful…