

Chemotherapy Port vs PICC Line: How Each Is Placed, Maintained and Removed

Key Takeaways
- Both a port and a PICC line deliver drugs to the same wide vein above the heart, where chemotherapy is diluted in seconds instead of irritating a small arm vein.
- MedlinePlus describes PICC lines as suited to weeks or months of treatment and implanted ports as able to stay in place for years when needed.
- A PICC needs a dressing change about weekly and regular flushing; a port that is not in use needs only a flush roughly every four weeks.
- Once a port has healed you can shower, bathe and swim; a PICC line must stay dry and rules out swimming and submerging the arm.
- Evidence comparing central venous devices in people on chemotherapy generally shows fewer infections and clots with ports than with PICC lines over longer courses, though neither is risk-free.
- A PICC comes out in minutes at the bedside, while port removal is a short outpatient procedure under local anesthetic that leaves a small chest scar.
A chemo port is a small reservoir implanted under the skin of the chest and connected to a large vein; a PICC line is a thin tube threaded from an arm vein to the same place, with an external tail. Ports suit longer treatment and carry fewer day-to-day restrictions; PICC lines are quicker to place and remove and suit shorter courses. Your treating team weighs treatment length, vein health, clotting and infection risk, and your preferences.
The nurse has just said the sentence that lands harder than it sounds: your veins may not hold up for six months of infusions, so it is time to talk about a line. On the table between you are two leaflets. One shows a coin-sized disc that sits beneath the skin of the chest. The other shows a slender tube taped to the inside of an upper arm. You are asked to think about which you would prefer, and you realize you have never thought about your veins at all.
The chemo port vs PICC line question comes up in almost every infusion suite, and it is rarely a medical emergency. It is a practical decision about months of living: showers, sleeves, swimming, a toddler who climbs on your chest, a job that needs both arms. Both devices deliver medicine to the same destination, a wide vein near the heart, where drugs that would scald a hand vein are diluted in seconds.
What follows is the honest version of that conversation: how each device is placed, what the weekly upkeep really involves, what the evidence says about safety, and how each comes out again when treatment ends.
Chemo port vs PICC line: what each device actually is
Both devices are central venous catheters, meaning a soft plastic tube whose tip rests in a large vein just above the heart, usually the superior vena cava. Blood flow there is fast and high-volume, so irritating chemotherapy drugs are diluted almost instantly instead of sitting against a small vein wall. That single fact is the reason both devices exist.
An implanted port (also called a port-a-cath or portacath) has two parts. The reservoir is a disc about the size of a large coin with a dense silicone top, called the septum, that a special needle can pierce hundreds of times without leaking. The catheter runs from that reservoir under the skin and into the vein. Nothing sits outside the body. When you are not being treated, the only visible sign is a small bump beneath the skin, most often below the collarbone.
A PICC line, short for peripherally inserted central catheter, starts in a vein of the upper arm and travels inward until its tip reaches the same central vein. Several inches of the catheter remain outside, ending in one or more capped connectors that must be covered with a sterile dressing at all times. According to MedlinePlus, a PICC is designed to stay in place for weeks to months, while a port can remain for years if it is working well and still needed.
Neither device is a drug. Neither changes how chemotherapy works. They are plumbing, and the choice between them is largely about how long the plumbing is needed and how it fits your daily life.
How is a chemo port placed, and how does it work?
Port placement is a minor surgical procedure, most often done by an interventional radiologist (a doctor who performs procedures guided by imaging) or a surgeon. Cleveland Clinic describes it as an outpatient procedure that usually takes under an hour. You typically go home the same day.
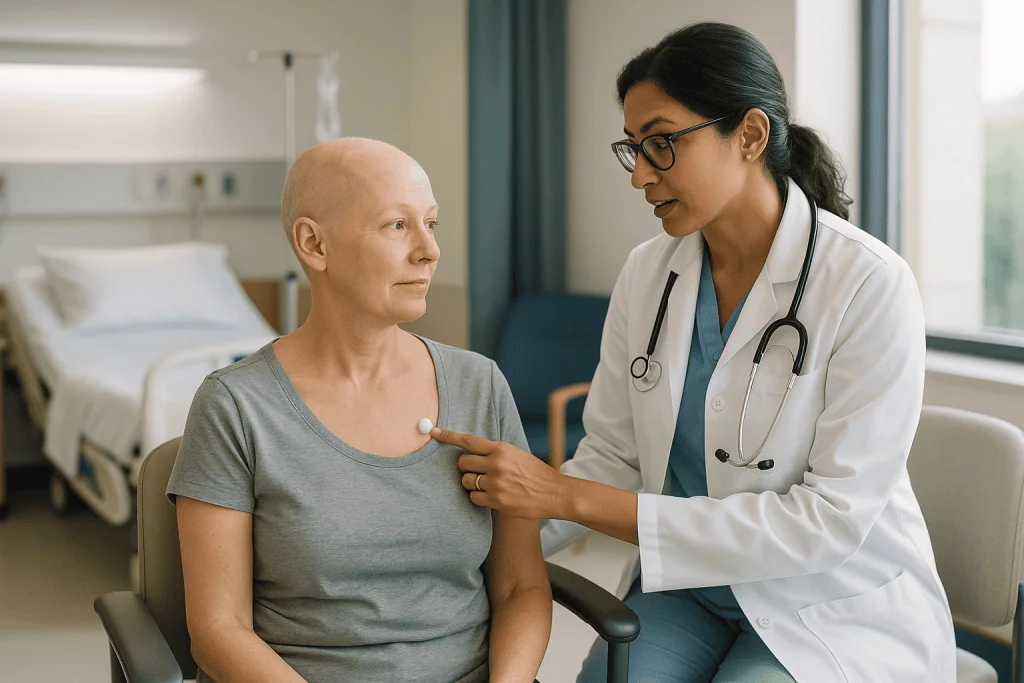
Here is what happens. You lie on a table, monitors are attached, and the skin of the upper chest is cleaned with antiseptic. Most people receive a local anesthetic to numb the area, often with light sedation through an ordinary IV so you feel relaxed rather than asleep. General anesthesia is uncommon for adults but may be used for children or for specific medical reasons; that decision belongs to the placing team.
Using ultrasound, the doctor finds a suitable vein, commonly the internal jugular in the neck or the subclavian beneath the collarbone, and threads the catheter toward the heart, checking its tip position with X-ray. A second small incision, usually a few centimeters long, creates a shallow pocket under the skin of the chest where the reservoir sits. The catheter is tunneled between the two sites and connected, the pocket is closed with stitches or skin glue, and a dressing is applied.
From then on, using the port means a nurse cleans the skin, feels for the reservoir’s edges, and pushes a bent needle (a non-coring or Huber needle) through the skin into the septum. The needle can stay in for the length of an infusion or, with a dressing, for several days of continuous treatment. Between uses, the port is flushed with saline and sometimes a diluted anticoagulant, and the skin heals over completely.
How is a PICC line placed?
PICC placement is faster and lighter than port placement, and it is often performed at the bedside or in a treatment room rather than an operating suite. MedlinePlus notes it is usually done by a specially trained nurse or a radiologist and does not typically require sedation.
The nurse first measures your arm to estimate how far the catheter must travel to reach the central vein. Ultrasound identifies a vein in the upper arm, most often the basilic or brachial vein, and the skin is numbed with a local anesthetic. A small needle enters the vein, a guidewire follows, and the catheter is fed along the wire until the estimated length is inside. A chest X-ray, or a sensor that reads the heart’s electrical signal from the catheter tip, confirms the tip is sitting where it should.
The external segment is secured with a sutureless anchoring device or adhesive, then covered with a transparent sterile dressing. The whole process commonly takes well under an hour, and you can usually leave shortly afterward. There is no incision to heal, only a puncture site, which is why PICC lines are often chosen when treatment needs to start within a day or two.
Some PICC lines have a single channel, called a lumen; others have two or three, allowing different fluids to run at once without mixing. Your team picks the number of lumens based on the treatment plan, since more lumens mean a slightly larger catheter and a slightly higher clot risk. A PICC can be used immediately after placement is confirmed, which is a real advantage when a first cycle is already scheduled.
Port vs PICC line for chemo: side-by-side comparison
People remember tables better than paragraphs when they are tired and frightened, so here is the comparison most patients say they wish they had seen first. Everything in it reflects general guidance from MedlinePlus, NHS and Cleveland Clinic rather than any single center’s practice.
| Feature | Implanted port | PICC line |
|---|---|---|
| Where it sits | Under the skin of the upper chest | Inside an upper-arm vein, with an external tail |
| How it is placed | Minor procedure with local anesthetic, often light sedation | Bedside procedure with local anesthetic, no sedation |
| Typical duration | Months to years | Weeks to months |
| Visible outside the body | Small bump only | Yes, dressing and capped connectors |
| Access | Needle through skin each time | Connect to external cap, no needle |
| Routine upkeep | Flush roughly monthly when not in use | Weekly dressing change and regular flushing |
| Bathing and swimming | Normal once healed; swimming usually allowed | Keep dry; no swimming or submerging |
| Removal | Minor procedure to open the pocket | Pulled out at bedside in minutes |
The pattern is easy to see. A port asks more of you at the start and the end, then largely disappears in between. A PICC asks little at the start and the end, then asks something of you every single week. Which trade you prefer depends on how long treatment will run and how much you value uninterrupted normality. Neither column is universally better; the honest answer to the picc line vs port pros and cons debate is that they solve the same problem on different timelines.
Who is usually offered a port, and who is asked to wait?
Ports tend to be suggested when treatment is expected to last many months, when cycles are spread weeks apart, or when the drugs involved are known to damage small veins. NHS guidance on how chemotherapy is given lists the implanted port as one of the standard options for people who need repeated treatment over a longer period. Regimens that run continuously through a portable pump for two or more days at a time also favor a port, because a single needle can stay accessed for that stretch under a dressing.
Body shape and vein history matter too. Someone whose arm veins are already scarred from earlier treatment, or who has had lymph nodes removed from one armpit and been told to protect that arm, may have limited options for a PICC and be steered toward a chest port instead. People who swim, care for small children, or work with their hands often ask for a port specifically because nothing dangles.
Who is asked to wait? Anyone with an active bloodstream infection, since implanting a foreign device during an infection risks seeding it. Anyone whose platelet count or clotting is temporarily too low for even a small incision may be asked to defer until counts recover or be given a PICC as a bridge. If treatment must begin within a day or two and the procedure schedule cannot accommodate a port yet, the team may start with a PICC and convert later. Skin problems over the planned pocket site, or radiotherapy planned for that exact area, can also change the location or the timing.
None of these are refusals. They are sequencing decisions, and the treating team makes them by looking at your bloodwork, your scans and your calendar together.
Who is usually offered a PICC line instead?
A PICC line is the workhorse of shorter or more urgent treatment. When chemotherapy is planned for a few weeks to a few months, when it needs to start almost immediately, or when someone is admitted for a course of intravenous antibiotics or nutrition alongside cancer care, a PICC is frequently the first suggestion. MedlinePlus lists exactly these situations: long courses of antibiotics, nutrition through a vein, and chemotherapy.
It is also the default when a port procedure is medically unwise for now. Low platelet counts, a recent infection, or fragile skin over the chest all push toward the arm. Someone who is very unwell and cannot tolerate lying flat under sedation may find a bedside PICC far easier. Patients in the middle of a hospital stay often have one placed simply because it can be done today, on the ward, without a procedure slot.
There are people for whom a PICC is a poorer fit. Anyone with limited arm veins from previous cannulas, anyone told to protect an arm after lymph node surgery, and anyone with a history of clots in the arm veins may be steered away. Dialysis patients, or people who may need dialysis in future, are often advised against a PICC because it can damage veins that would later be needed for a fistula. Confusion or a tendency to pull at tubing is another reason teams hesitate.
Many treatment journeys use both devices at different moments: a PICC to get started, replaced by a port once the plan is clear and counts allow. The order is decided cycle by cycle, not once and forever.
What is safer, a port or a PICC line?
Safety here means three things: infection, blood clots, and mechanical problems such as blockage or displacement. Both devices carry all three risks, and the evidence points to a consistent difference in direction rather than a dramatic gap.
Infection risk tracks with exposure. A PICC has an external opening covered only by a dressing, touched every time it is used, and living on an arm that sweats and bends. A port sits sealed beneath intact skin between uses. For that reason, guidance from MedlinePlus and Cleveland Clinic describes ports as having a lower infection risk when treatment stretches over months, and randomized comparisons of central venous devices in people receiving chemotherapy have generally found fewer overall complications with ports than with PICC lines. That is a tendency across groups, not a guarantee for any individual. Ports do get infected, and when they do the whole device usually has to come out.
Clot risk follows vein size. The arm veins a PICC occupies are narrower than the chest and neck veins a port uses, so a PICC fills a larger share of the vessel and disturbs flow more. Arm swelling from a catheter-related clot is a recognized PICC complication; ports can also cause clots, but the studies referenced above suggest less often.
Mechanical problems run both ways. A PICC can slip, kink or crack, particularly if the external segment catches on clothing. A port can flip in its pocket or its catheter tip can migrate, and the needle can occasionally miss or pull out during an infusion, letting drug leak into the tissue of the chest.
So, which is safer? For treatment lasting many months, the weight of evidence leans toward the port. For treatment lasting weeks, the difference narrows and the lighter insertion of a PICC may tip the balance. Your team will place those odds against your own history.
How painful is a port for chemo, and does a PICC line hurt?
Ask a room of patients and you get two answers about ports: the first week is sore, and after that most forget it is there. Placement itself is done under local anesthetic, so people commonly describe pressure and tugging rather than sharp pain. Once the numbing wears off, the chest pocket feels bruised and tight for several days. Cleveland Clinic describes soreness that generally settles within about a week, and most people manage it with the simple pain relief their team suggests; those decisions sit with the prescribing clinician, not with a magazine.
Accessing the port afterward means a needle through skin every cycle. Many describe it as a quick pinch, similar to a blood draw, that lasts a second or two. A numbing cream applied to the skin an hour beforehand is commonly offered, and a small spray that chills the skin is another option. Ask about both; neither is a favor, both are routine.
PICC placement hurts less at the start because there is no incision and no pocket. The numbing injection stings briefly, then the arm may feel achy for a day or so. After that, there are no needles at all; the nurse connects to the external cap. Some people describe an awareness of the line inside the arm when they bend the elbow, and the adhesive dressing can irritate skin over weeks.
Pain that grows rather than fades is the signal that matters with either device. A port that stays tender past the first couple of weeks, or a PICC arm that becomes sore and swollen, is not something to tolerate; it is something to report.
What can't you do with a chemo port or a PICC line?
The honest list is shorter for a port and longer for a PICC, and it changes as the port heals.
With a port, the first week or two comes with common-sense limits while the incision closes: keep the dressing dry as instructed, avoid heavy lifting or vigorous overhead reaching that strains the chest, and skip soaking in a tub. Once the skin has healed and stitches have dissolved or been removed, MedlinePlus and Cleveland Clinic both describe a near-normal life. You can shower, bathe and swim. You can wear seatbelts, though a small pad between strap and port makes long drives more comfortable. Contact sports that could deliver a direct blow to the chest are usually discussed with your team; many people continue running, cycling, yoga and weight training without issue. A magnet on your phone case will not harm it, and modern ports are compatible with MRI, though you should always tell the imaging staff it is there.
With a PICC, the rules are firmer because the line is open to the world. The dressing must stay dry: shower with the arm covered by a waterproof sleeve, and do not swim, soak in a hot tub or submerge the arm. Avoid heavy lifting with that arm, repetitive strenuous movements such as rowing or pull-ups, and having blood pressure taken or blood drawn from it. Tight sleeves or watch straps over the site are out. You will need someone, usually a nurse, to change the dressing weekly.
Everyday activities like cooking, typing, driving and gentle exercise are fine with either. What can’t you do with a chemo port? Once healed, remarkably little.
Maintenance: flushing, dressing changes and who does them
Upkeep is where the two devices diverge most sharply in lived experience, so it deserves plain numbers. According to MedlinePlus, a PICC line dressing is changed about once a week, or sooner if it becomes loose, wet or soiled. The line is flushed with saline after every use and, when not in use, on a regular schedule your team sets, often daily or several times a week. The caps on the connectors are also replaced at set intervals to keep the system sealed.
Most of this is done by an infusion nurse or a community nurse who visits your home. Some patients or family members are taught to flush the line themselves after training, using pre-filled saline syringes supplied by the care team. Either way, it is a standing appointment in the calendar for as long as the PICC is in.
A port needs almost nothing between cycles. Once the incision has healed, there is no dressing. When the port is in regular use, it is flushed at the end of each treatment. When treatment pauses or finishes but the port stays in, MedlinePlus advises flushing roughly every four weeks to keep the catheter clear, and some teams extend that interval; the schedule is set by your clinic, not by convention. Each flush is a brief clinic visit with a single needle pass.
Both devices rely on the same habit from everyone who touches them: hand hygiene and clean technique. Ask the person accessing your line whether they have washed their hands and are wearing gloves. Good nurses welcome the question, and the CDC-endorsed prevention bundles used in hospitals depend on exactly that culture of speaking up.
What the first days and weeks usually look like
Timelines below are typical ranges drawn from MedlinePlus and Cleveland Clinic patient guidance, not promises, and your own team may adjust them.
After a port is placed, you go home the same day with a dressing over the chest incision and usually a smaller one at the neck. The area feels bruised and swollen for several days. Most people are told to keep the dressing dry for the first day or two, then shower normally while avoiding scrubbing the site. Stitches are typically absorbable or removed at a check within about a week or two. Many teams are willing to use the port on the day of placement or within a day or two, so treatment often starts on schedule. By around two weeks, swelling has usually settled and the bump becomes something you notice only when you look for it. Numbness or tingling around the pocket can linger for a few weeks and generally fades.
After a PICC is placed, there is often a small amount of oozing at the site for the first day, which is normal. The arm may feel heavy or achy for a day or two. The first dressing change is commonly done within 24 to 48 hours because of that early oozing, then weekly. You learn the shower routine quickly: sleeve on, arm out of the spray, sleeve off. Within a week, most people have a rhythm.
Both devices settle into background noise by the end of the first cycle. Your job in these weeks is to look at the site each day in good light and to report anything that looks or feels different from the day before.
How each is removed, and what happens afterward
Removal is the mirror image of placement. A PICC comes out in minutes at the bedside or in clinic. A nurse removes the dressing and anchor, asks you to hold your breath or hum, and draws the catheter out steadily. You feel a sliding sensation, rarely pain. Pressure is held over the puncture for a few minutes and a small dressing is applied, usually for a day. The nurse measures the removed catheter against the length recorded at insertion to confirm it came out whole. Most people return to normal activity the same day.
Port removal is a minor procedure, again under local anesthetic and often light sedation. The doctor reopens the pocket incision, frees the reservoir from the thin capsule of scar tissue that forms around it, withdraws the catheter from the vein, and closes the skin. Cleveland Clinic describes this as a brief outpatient procedure; you go home the same day with a dressing and mild soreness for a few days. A thin scar remains where the pocket was.
When is a port removed? Usually when treatment is complete and the team is confident it will not be needed again soon. Some people keep a port in for a period after treatment ends, particularly if the plan includes scans and blood tests that are easier through the port, or if there is a chance further treatment could follow. Keeping it means committing to flushes roughly monthly, as described earlier, so the decision is a genuine trade-off you and your oncologist make together.
Either device is also removed promptly if it becomes infected, clotted beyond clearing, or damaged.
What people often get wrong about ports and PICC lines
The port is a drug delivery pump. It is not. A port is a passive reservoir; nothing happens until a nurse puts a needle in it. Portable pumps sometimes connect to a port for continuous infusions, but the pump is a separate device.
Choosing a port means you are sicker. Device choice reflects treatment length, vein condition and logistics, not prognosis. People with highly treatable conditions receive ports because their course runs many months; people with advanced disease receive PICC lines because they start treatment tomorrow.
You cannot have an MRI with a port. Modern implanted ports are designed to be MRI-compatible. Always tell imaging staff it is there; they will check the device details, and contrast can often be injected through some ports designed for that purpose.
Airport scanners are a problem. Metal detectors and body scanners do not damage either device. A port may occasionally trigger a metal detector, and a card or letter from your team explaining the implant smooths the moment.
Once the port is in, infusions are painless. Access still means a needle through skin. It is brief and numbing cream helps, but honesty here beats disappointment later.
A PICC is the cheap or temporary option and a port is the serious one. Both are standard, guideline-supported devices used across cancer care. A PICC can serve an entire course of treatment perfectly well when that course is measured in weeks.
You must protect the port arm. That rule belongs to the PICC arm. With a chest port, both arms are free for blood pressure cuffs, blood draws and lifting once healed.
The thread running through these myths is the same: both devices are tools, and neither says anything about how your treatment is going.
Questions to ask your care team before choosing
The most useful conversations happen before the procedure is booked, when you still have the leaflets in your hand. These questions tend to surface the details that matter for daily life.
- How long do you expect I will need a central line, and does that estimate favor one device?
- Will any of my drugs run continuously over several days through a pump, and how does that change the choice?
- Have I had lymph nodes removed, or is there any arm I should be protecting? Does that rule out a PICC?
- Are my platelet counts and clotting results acceptable for a port procedure now, or would you suggest starting with a PICC?
- Who will place the device, where, and what kind of anesthesia or sedation is planned?
- Can the device be used the same day, or is there a waiting period before my first cycle?
- For a PICC, who will change the dressing each week and where will that happen? Can a nurse come to my home?
- For a port, how often will it need flushing during treatment breaks, and where is that done?
- Will you offer numbing cream or a cold spray before port access, and should I apply it at home beforehand?
- What activities do you want me to avoid, and for how long after placement?
- If I swim, garden, lift weights or care for young children, does that change your recommendation?
- Will the port sit on the side away from any planned radiotherapy or surgery?
- What is your plan for the device when treatment finishes: remove it promptly, or keep it for follow-up?
- What signs would make you take the device out early?
Write the answers down or ask a companion to. Decisions made in an infusion chair are easier to live with when you understand the reasoning behind them.
When to call your doctor: red-flag signs with a port or PICC line
Most people finish treatment without a serious device problem, but the complications that do occur move quickly, so the rule is to call early and let the team decide it was nothing. Keep the treatment unit’s number saved in your phone and know which number to use after hours.
Call your care team the same day if you notice any of the following at the site: redness that spreads or feels hot, new swelling, pus or cloudy fluid, a bad smell, or pain that is getting worse rather than better. For a PICC, add: the external length looks longer than before (the catheter may have slipped), the dressing is loose or wet and you cannot get it changed, the line will not flush or fluid leaks when it is flushed, or the catheter appears cracked or split. For a port, add: swelling or burning in the chest during an infusion, which can mean the needle is not seated and drug is leaking into tissue; tell the nurse immediately if you feel this while connected.
Seek urgent care, calling emergency services if needed, for signs that suggest a bloodstream infection or a clot. These include a fever or shaking chills, especially within an hour or two of the line being used or flushed; feeling suddenly very unwell, faint or confused; swelling, pain or a purple tinge of the arm, neck or face on the side of the device; new shortness of breath or chest pain, which can signal a clot that has traveled to the lungs; or a fast heartbeat that does not settle. Do not wait to see if a fever passes. During chemotherapy, infection-fighting white cells can be low, and NHS and Mayo Clinic guidance treats fever in that setting as an emergency.
If a PICC is accidentally pulled partway or fully out, press firmly on the site with a clean cloth, keep the arm still and raised, and call for advice. Never try to push it back in. The device is replaceable; your safety is the priority, and every one of these decisions belongs with your treating team.
Frequently asked questions
What is safer, a port or a PICC line?
Over months of treatment, ports tend to have fewer infections and clots because they sit sealed under the skin and use wider chest veins. For treatment lasting weeks, the gap narrows and the simpler PICC insertion can tip the balance. Both devices can become infected, blocked or clotted, and both are standard, guideline-supported options. Your team weighs your treatment length, vein history and blood counts to decide which risk profile fits you.
How painful is a port for chemo?
Placement is done under local anesthetic, usually with light sedation, so most people feel pressure rather than sharp pain. The chest is bruised and tight for several days and generally settles within about a week. Each time the port is used, a needle passes through the skin, which most describe as a brief pinch similar to a blood draw. Numbing cream or a cold spray applied beforehand is commonly offered and worth asking about.
What can't you do with a chemo port?
Very little once it has healed. For the first week or two you keep the incision dry as instructed and avoid heavy lifting or vigorous overhead movement. After that, showering, bathing and swimming are usually fine, seatbelts are safe with a small pad for comfort, and both arms can be used for blood pressure and blood draws. Contact sports that could strike the chest directly are worth discussing with your team.
Is it better to have a port for chemo?
It depends mostly on how long treatment will last and how it fits your life. A port makes sense for many months of cycles, continuous pump infusions, or when arm veins are scarred or an arm must be protected. A PICC makes sense when treatment is measured in weeks, must start within a day or two, or when a chest procedure is unwise right now. Many people use both at different stages.
How is a chemo port placed?
An interventional radiologist or surgeon numbs the upper chest, often adds light sedation, and uses ultrasound to guide a catheter into a neck or collarbone vein, checking its tip with X-ray. A small pocket is made under the skin for the reservoir, the catheter is tunneled to it and connected, and the skin is closed with stitches or glue. It is usually an outpatient procedure lasting under an hour.
How often does a PICC line dressing need changing?
About once a week, and sooner if the dressing becomes loose, wet or dirty. The first change is often done within a day or two of placement because of early oozing. A nurse in clinic or at home usually performs it using sterile technique, and the connector caps are replaced on a schedule your team sets. The line is also flushed after each use and regularly when not in use.
Can you shower or swim with a PICC line?
You can shower if the arm and dressing are fully covered with a waterproof sleeve and kept out of the spray. Swimming, soaking in a bath or hot tub, and any submerging of the arm are not advised because water can carry bacteria into the line. If the dressing does get wet, it should be changed as soon as possible rather than left to dry.
Do ports and PICC lines set off airport scanners or affect MRI?
Modern implanted ports are designed to be MRI-compatible, and neither device is harmed by airport metal detectors or body scanners. A port may occasionally trigger a detector, so carrying a card or letter from your team describing the implant helps. Always tell imaging staff about the device before any scan so they can check its details and decide whether contrast can be given through it.
How is a port removed, and does it hurt?
Removal is a brief outpatient procedure under local anesthetic, often with light sedation. The doctor reopens the pocket incision, frees the reservoir from the thin scar capsule around it, withdraws the catheter from the vein and closes the skin. Soreness lasts a few days and a small scar remains. A PICC, by contrast, is simply drawn out at the bedside in minutes with pressure held over the site.
What are the picc line vs port pros and cons for daily life?
A port is invisible under the skin, needs no dressing, allows swimming once healed and needs only occasional flushes, but placement and removal are minor procedures and each use involves a needle. A PICC is quick to place and remove with no incision and no needles during use, but it must stay dry, needs weekly dressing changes and restricts that arm for lifting, blood pressure and blood draws.
References
- MedlinePlus: Central venous catheters – ports
- MedlinePlus: Peripherally inserted central catheter – insertion
- NHS: Chemotherapy – What happens
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Who May Be a Candidate for Proton Therapy: Tumors Near Critical Organs and Younger Patients
People most often considered for proton therapy have a tumor sitting close to organs that tolerate radiation poorly, such as the brainstem, spinal cord,…

Autologous vs Allogeneic Stem Cell Transplant: Own Cells or Donor Cells, and Who Gets Which
An autologous stem cell transplant returns a person's own previously collected blood-forming cells after high-dose treatment, while an allogeneic transplant uses cells from a…

Life After Thyroid Cancer Surgery: Hormone Replacement, Energy and Daily Routine
After a total thyroidectomy for thyroid cancer, the body can no longer make thyroid hormone, so most people take a daily synthetic version of…
Low Blood Counts During Lymphoma Treatment: Precautions and the Symptoms That Need a Call
Lymphoma chemotherapy and some immunotherapies temporarily lower white cells, platelets and red cells, and the infection risk usually peaks about one to two weeks…

How a Basal Cell Carcinoma Excision Heals: Dressings, Stitches and Scar Maturation
After a basal cell carcinoma excision, a stitched wound usually has a sealed surface within about two weeks, with surface sutures removed anywhere from…

Hot Flashes and Fatigue on Hormone Therapy: Practical Ways the Care Team Helps
Hot flashes and fatigue are among the most common side effects of cancer hormone therapy because these treatments lower or block estrogen or testosterone,…