

Does Amniocentesis Hurt? What the Needle Feels Like and Whether Local Anesthetic Is Used

Key Takeaways
- The NHS describes amniocentesis as usually uncomfortable rather than painful, with period-like cramping and pressure the most common sensations.
- The needle is typically in place for about a minute within a procedure lasting roughly 10 minutes, according to the NHS.
- Local anesthetic is not used everywhere because trials show a skin injection does little to reduce the cramp that comes from the uterus itself.
- Anxiety before the procedure predicts reported pain more reliably than needle size or the clinician's experience.
- The NHS quotes a miscarriage risk of up to 1 in 100, while the Mayo Clinic cites more recent estimates of about 0.1 to 0.3 percent for second-trimester amniocentesis.
- Rapid results for common chromosomal conditions usually arrive within about three working days, with full analysis taking up to three weeks (NHS).
Amniocentesis is usually described as uncomfortable rather than painful. Most people feel a brief sting as a thin needle passes through the skin, then pressure or period-like cramping while fluid is drawn, and the needle is typically in place for about a minute. Numbing injections are offered at some clinics but not others, because trials show they make little measurable difference. Mild cramping may follow for a day or so.
The appointment letter says fifteen minutes. The night before, that number feels impossible, how can something with a needle that long take fifteen minutes and be described as “a bit uncomfortable”? So you do what most people do at eleven at night: you type does amniocentesis hurt into a search bar and read strangers’ stories until the pictures in your head are worse than anything the procedure will actually do.
Here is a calmer place to land. The needle is thinner than the one used to draw blood at your first antenatal visit. It goes in once, under ultrasound guidance, and it comes out fast. The sensation people report most often is not sharp pain but a deep, strange pressure, like a pinch inside a cramp.
This explainer walks through what happens, whether you will be numbed, how amniocentesis compares with CVS, what recovery looks like, and the signs that warrant a call. Every decision about whether to have the test stays with you and the team looking after your pregnancy.
Does amniocentesis hurt? The honest short answer
Most people who have had amniocentesis say the same thing afterward, in slightly different words: “I braced for something much worse.” The NHS describes the procedure as usually uncomfortable rather than painful, with sensations compared to period pain or a feeling of pressure, particularly as the needle is withdrawn. The Mayo Clinic describes a stinging sensation when the needle enters the skin and menstrual-like cramping while the needle is in the uterus.
That does not mean it feels like nothing. A needle passing through the abdominal wall and the muscular wall of the uterus produces a distinct sensation, and the uterus can respond with a brief, tight cramp. The difference between this and, say, a bad injury is duration and intensity. The needle is in place for around a minute (NHS), and the cramping typically eases within minutes of the needle coming out.
Pain is also personal. Two people can have the same procedure with the same clinician on the same morning and rate it a two and a six out of ten. Anxiety, how tense the abdominal muscles are, how many attempts are needed and where the placenta sits all shape the experience, and we cover those below.
So the honest answer has three parts. Yes, you will feel it. No, for most people it is not what they would call painful. And the fear beforehand is, in study after study of patient pain scores, consistently larger than the sensation itself. If you remember only one thing from this article, let it be that last point.
What actually happens during an amniocentesis, step by step
Amniocentesis is a diagnostic test in which a small sample of amniotic fluid, the liquid surrounding the baby, is drawn through a needle and sent to a laboratory. That fluid contains cells shed by the baby, which is why it can be used to look at chromosomes and specific genes. According to the NHS, it is usually carried out between the 15th and 20th week of pregnancy, and the whole appointment takes about 10 minutes, although you will spend longer in the building.

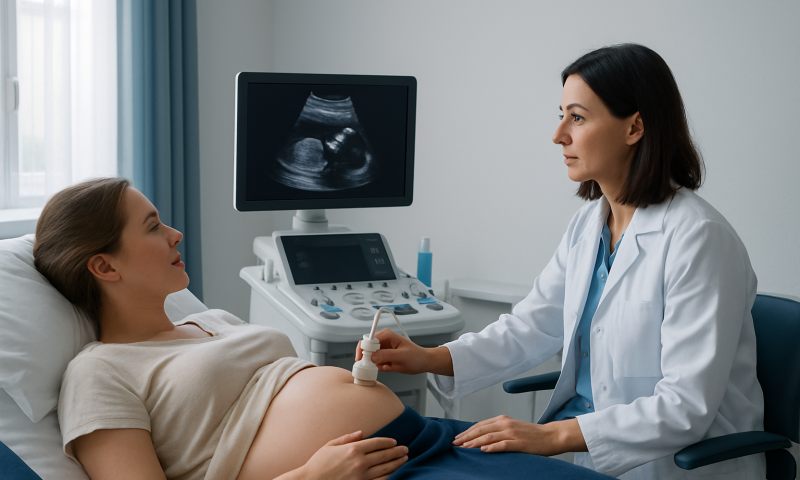
You lie on your back on an examination couch with your abdomen exposed. A sonographer or doctor first performs an ultrasound to check the baby’s position, find the placenta and locate a pocket of fluid that is well clear of both. The skin is cleaned with antiseptic, which often feels cold, several people report this as the most startling moment of the day.
With the ultrasound probe held on one part of the abdomen, the clinician inserts a long, thin needle through the skin, the abdominal wall and the wall of the uterus into that pocket of fluid, watching the needle tip on screen the entire time. A syringe attached to the needle draws off the sample. The needle is then withdrawn and a small dressing placed over the puncture site.
Afterward, the clinician usually checks the baby’s heartbeat on the ultrasound before you sit up. The MedlinePlus description of the test notes the same sequence: ultrasound, needle, sample, check. There is no incision, no stitches and, in almost every case, no visible mark beyond a pinprick a day later.
Do they numb you for amniocentesis?
Sometimes, and it depends on where you are and who is doing it. Local anesthetic is a numbing medicine injected into the skin so that the area loses sensation for a short while. The Mayo Clinic notes that a clinician may use a numbing medication before the procedure, while the NHS explains that it is not usually given because the injection itself can sting and research suggests it does not reduce overall discomfort by much.
That second point surprises people, so it deserves unpacking. The skin has plenty of pain receptors, and numbing it does stop the sting of the amniocentesis needle passing through. But the sensation people notice most, the pressure and the cramp, comes from the uterus, which a skin injection cannot reach. Trials that compared amniocentesis with and without local anesthetic found pain ratings that were similar either way, which is why many units skip a step that adds a second needle for little gain.
Some clinicians take a middle path: a topical anesthetic cream or a cold spray applied to the skin before the procedure. Evidence for these is limited too, but they avoid a second puncture, and some people simply feel steadier knowing the skin has been treated.
If numbing matters to you, ask before the day. Ask whether the unit routinely offers it, what form it takes, and what the clinician has observed about its usefulness. There is no right answer here, only a preference, and a reasonable team will discuss it with you. Whatever is chosen, it does not change the medical result of the test.
What the needle feels like, moment by moment
People remember the procedure in phases, so it helps to know them in advance.

The antiseptic is first. It is cold and wet, and because the abdomen is already tense, several people describe flinching at the swab rather than at anything sharp. Then a warm hand or a gloved fingertip presses to find the spot, followed by the ultrasound gel and probe, which most people already know from earlier scans.
The skin puncture is a sharp, brief sting, commonly compared to a blood draw or an injection. It lasts a second or two. The amniocentesis needle is thinner than many people imagine; its length, not its width, is what looks alarming in photographs.
Next comes the sensation most searched about: a deep pressure as the needle passes through the uterine wall. The uterus is muscle, and it often answers with a cramp, described by the NHS as similar to period pain. Some people feel a single strong twinge, others a dull ache, and a few feel almost nothing at that stage. The fluid draw itself is usually painless; you may be aware of a faint pulling.
Withdrawal can produce another wave of pressure, the NHS specifically mentions this moment, followed by relief. The dressing goes on. Most people describe lying still for a minute while a cramp fades, then feeling normal enough to chat.
One detail worth knowing: many people say the hardest part was holding still while feeling the urge to tense. Slow breathing out through the mouth genuinely helps the abdominal wall relax, and clinicians often coach you through it.
Does amniocentesis hurt more if you are anxious? Why experiences differ so widely
Read any forum thread and the range is striking: “barely felt it” sits beside “worst cramp of my life.” Both are true accounts. Several factors explain the spread, and understanding them can lower your own score.
Anxiety is the best-studied. Research on pain during amniocentesis has repeatedly found that the level of worry before the procedure predicts how much pain is reported afterward more reliably than needle size or the clinician’s experience. Fear tightens the abdominal muscles, and a tense wall is harder to pass through and more likely to spasm. This is not a matter of “being brave”; it is physiology, and it is why units invest in explanation and calm rooms rather than stronger painkillers.
Body composition plays a role. A thicker abdominal wall means a longer path for the needle and sometimes a second attempt to reach the fluid pocket, and repeat attempts are a recognized reason for higher discomfort.
Placental position matters. When the placenta lies on the front wall of the uterus, the clinician may need to choose a less convenient angle to avoid it, which can mean more pressure during entry.
Number of passes matters most of all. Most procedures need one; occasionally the baby moves or the pocket shifts and a second insertion is required. Two punctures will naturally be remembered as more uncomfortable than one.
Finally, the sensation of the uterus contracting afterward varies from person to person. Some feel a run of mild cramps for an hour; others feel nothing after the couch. None of this predicts the test result or the health of the pregnancy, only how the morning felt.
Who amniocentesis is usually for, and who is usually asked to wait
Amniocentesis is offered, not routine. The NHS and Mayo Clinic describe the common reasons: a screening test, such as the combined first-trimester test or cell-free DNA (NIPT) blood screening, returned a higher-chance result; an ultrasound found a feature that raises the possibility of a genetic condition; a previous pregnancy was affected by a chromosomal or genetic condition; or one or both parents carry a known inherited condition. Later in pregnancy it is occasionally used to check for infection in the fluid or, rarely, to assess the baby’s lung maturity before an early delivery.
The distinction that matters most is between screening and diagnosis. NIPT, however sophisticated, estimates a probability; amniocentesis examines the baby’s own cells and gives an answer. That is why a high-chance NIPT result typically leads to an offer of a diagnostic test rather than a decision on its own.
Who is asked to wait? Timing is the main gate. Amniocentesis is not usually performed before 15 weeks, because early procedures carry a higher risk of complications, including miscarriage and a foot-positioning condition sometimes called club foot (NHS, Mayo Clinic). Someone at 13 weeks who wants a diagnostic answer will generally be offered CVS instead, or asked to return in two weeks.
A current infection, certain bleeding problems or a placenta that makes safe access difficult can also lead a team to delay or discuss alternatives. People living with a blood-borne virus should tell the team so the approach can be planned; it is not a reason for refusal.
Above all, amniocentesis is optional. Declining it, or choosing to wait for birth, is a legitimate decision your team should support without pressure.
How long does amniocentesis take, from check-in to leaving?
The needle part is short. The NHS puts the procedure itself at about 10 minutes, with the needle in place for roughly a minute. The appointment around it is longer, and knowing the shape of it helps.
Before the procedure, expect a conversation. A doctor or genetic counselor confirms why the test is being offered, what it can and cannot find, and the risks, then asks you to sign a consent form. This is the moment to raise numbing, to ask about the clinician’s routine and to say if you would like a partner or friend in the room. Many units allow this; some ask companions to sit slightly back so the sonographer has space.
An ultrasound follows, often ten minutes, to confirm the baby’s gestational age, position and the placenta’s location. Some units combine this with a detailed anatomy scan if one is due.
Then the procedure: cleaning, needle, sample, dressing, heartbeat check. Ten minutes on the couch, one of them with a needle.
Afterward, most people rest on the couch or in a waiting area for a short while. The NHS advises being able to go home the same day and suggests arranging for someone to drive you if possible, as you may prefer not to drive while feeling crampy or shaky.
In total, plan for one to two hours in the building, with the clinical steps documented on the NHS “what happens” page. The wait for results is separate: the NHS describes a rapid result for the most common chromosomal conditions within about three working days and a fuller analysis taking up to three weeks. That wait, many say, is harder than the needle.
Amniocentesis vs CVS pain: which is more uncomfortable?
Chorionic villus sampling (CVS) is the other diagnostic test in pregnancy; it takes a tiny sample of placental tissue rather than fluid. The NHS describes it as carried out between the 11th and 14th week, through the abdomen with a needle or, less often, through the cervix with a thin tube. People often ask which of the two hurts more, expecting a clear ranking. The evidence does not give one.
Both are described in the same language by the NHS: uncomfortable rather than painful, with cramping the most common sensation. Transabdominal CVS involves a needle passing into the placenta, which is a more vascular, denser tissue than a fluid pocket, and some people report a stronger pressure sensation. Transcervical CVS avoids the abdominal wall entirely but involves a speculum, similar to a cervical screening test. Pain ratings across studies overlap considerably, and individual anxiety again predicts scores more than the test type.
| Feature | Amniocentesis | CVS |
|---|---|---|
| Usual timing (NHS) | 15 to 20 weeks | 11 to 14 weeks |
| What is sampled | Amniotic fluid | Placental tissue |
| Route | Needle through abdomen | Needle through abdomen or tube through cervix |
| Common sensation | Sting, pressure, period-like cramp | Pressure or cramp; speculum discomfort if transcervical |
| Local anesthetic | Varies by unit; evidence of little benefit | Varies by unit |
| Miscarriage risk (NHS / Mayo Clinic) | Up to 1 in 100; recent estimates about 0.1 to 0.3 percent | Up to 1 in 100 |
The practical takeaway is that the choice between them is usually made by gestational age and clinical circumstances, not by which is thought to hurt less. If you are at 12 weeks and want an answer sooner, CVS is the option on the table; at 16 weeks, amniocentesis is.
Has anyone miscarried after an amnio? What the risk numbers actually show
Yes, and it is the fear that sits under almost every pain question. Miscarriage after amniocentesis does happen, and any honest account has to say so. What the numbers show is that it is uncommon, and that the figure you may have heard from an older relative is likely higher than current estimates.
The NHS states that the risk of miscarriage after amniocentesis is estimated to be up to 1 in 100. The Mayo Clinic, drawing on more recent analyses, describes the procedure-related risk for second-trimester amniocentesis as about 0.1 to 0.3 percent: that is, roughly 1 to 3 in 1,000. The gap between those two figures reflects how estimates have shifted as ultrasound guidance and technique have improved and as studies have become better at separating procedure-related losses from losses that would have happened anyway in the same weeks.
That last point is the hardest to hold in mind. Some pregnancies that undergo amniocentesis were already at higher chance of complications: that is often why the test was offered. Distinguishing a loss caused by the needle from one that coincided with it requires comparison groups, and the studies that do this carefully tend to produce the lower figures.
Other risks are rarer still. The NHS puts the chance of a serious infection at fewer than 1 in 1,000, and notes that the needle very rarely touches the baby because the tip is watched on ultrasound throughout. If you are rhesus negative, you will be offered an injection of anti-D immunoglobulin: a blood product that prevents your immune system from reacting to the baby’s blood cells, because the procedure can allow tiny amounts of the baby’s blood to cross into yours (NHS).
None of these numbers tells you what will happen to you. They tell you the scale, which is what a decision needs.
Amniocentesis recovery time: what the next days and weeks look like
Recovery from amniocentesis is measured in hours and days, not weeks, and most of it is about being gentle with yourself rather than treating anything.
The first few hours are when cramping is most likely. The NHS describes mild cramping and slight spotting from the puncture site as common and expected. Many people notice a dull ache low in the abdomen, a little like the first day of a period, that fades over the afternoon. The dressing can come off later that day or the next morning.
For the rest of the day, the NHS advises resting and avoiding strenuous activity. The Mayo Clinic suggests avoiding vigorous exercise and sexual activity for a day or two. Neither source asks for bed rest, and there is no evidence that lying flat lowers the risk of complications; the advice is about comfort and about noticing symptoms without distraction.
By the second and third day, most people feel entirely normal. If cramps linger, they are usually mild and intermittent. Persistent or worsening pain is not part of ordinary recovery and belongs in the red-flag section below.
The longer timeline is emotional rather than physical. The NHS describes a rapid result for common chromosomal conditions within about three working days and full results taking up to three weeks. People often describe this stretch as the true recovery period: the body has moved on while the mind is still on the couch. Planning for it helps: decide in advance how you want results delivered, who you want beside you, and what you will do with the intervening days. Units usually offer a phone call or an appointment, and you can ask for whichever suits you.
Practical ways to make the procedure easier
Small preparations change how the morning feels, and none of them require a prescription.
Ask about the bladder. Some units prefer a moderately full bladder for the initial scan and then have you empty it before the needle; others want it empty throughout. Following the instruction you are given avoids a last-minute dash and an unnecessarily tense abdominal wall.
Wear clothes that separate at the waist. A two-piece outfit means only your abdomen is exposed, which most people find more comfortable than a gown.
Eat normally unless told otherwise. Amniocentesis does not usually require fasting, and arriving light-headed from skipping breakfast makes cramps feel worse.
Bring someone if you can. A companion can drive you home, hold a hand and remember the parts of the conversation you will not. The NHS specifically suggests arranging for someone to take you home.
Decide in advance whether you want to watch the screen. Some people find seeing the needle on ultrasound reassuring: it makes the pocket of fluid and the safe distance from the baby visible. Others prefer to look at the ceiling and count breaths. Tell the sonographer which you are.
Practice a slow exhale. Breathing out for longer than you breathe in relaxes the abdominal muscles, and clinicians often cue this right as the needle goes in. Practicing beforehand means it will come naturally when it matters.
Ask about pain relief afterward. Some teams suggest a simple pain reliever considered appropriate in pregnancy if cramps are bothersome later in the day. Which one, and whether you need it at all, is a question for the team who knows your history, not for a search engine.
What people often get wrong about amniocentesis pain
Myths gather around any procedure that involves a needle and a pregnancy. These are the ones that cause the most unnecessary dread.
“The needle is huge.” It is long, because it must reach a fluid pocket through the abdominal and uterine walls, but it is thin. Length is what photographs show; width is what you feel, and the puncture is comparable to a blood draw.
“They always numb you, so it can’t hurt.” Many units do not use local anesthetic, and the NHS explains why: the injection stings and the cramping comes from the uterus, which a skin injection does not reach. Expecting total numbness and then feeling pressure is a common route to disappointment.
“If it hurts, something is wrong.” A cramp during and shortly after the needle is the uterus responding normally to being touched. Persistent or worsening pain over the following hours is different and should prompt a call, but a strong twinge on the couch is not a warning sign.
“The needle can hit the baby.” The tip is watched on ultrasound throughout, and the clinician chooses a pocket of fluid away from the baby and the placenta. The NHS describes needle injury to the baby as very rare.
“Bed rest afterward prevents miscarriage.” No guideline recommends bed rest; the advice is to avoid strenuous activity for a day or so for comfort and observation.
“Miscarriage risk is 1 in 100, full stop.” That figure appears in NHS materials as an upper estimate. More recent analyses cited by the Mayo Clinic put the procedure-related risk closer to 0.1 to 0.3 percent. Both are honest numbers; they answer slightly different questions.
“A normal amnio means a healthy baby.” It rules out the conditions it tests for. It does not check every possible outcome, and your team can explain the limits.
Questions to ask your care team
A good appointment leaves room for questions, and having them written down means the nerves of the day will not steal them. These are the ones people most often wish they had asked.
About the test itself: What exactly will this sample be tested for, and what will it not tell us? Will you run a rapid test first, and when should we expect each set of results? How will results be delivered, by phone, letter or appointment, and can we choose?
About comfort: Do you use local anesthetic, a topical cream or nothing, and why? Can my partner or a friend be in the room? Is there anything you would like me to do with my breathing or position?
About risk: What is your unit’s own experience with complications after amniocentesis? How often is a second needle pass needed? What is your advice if I am rhesus negative?
About afterward: What should I avoid today and tomorrow? Which symptoms should make me call, and which number do I ring, daytime and out of hours? Is a follow-up scan planned?
About alternatives: If I decide not to have this test, what are my options for further screening or for waiting until birth? Is there any reason to delay rather than proceed today?
About meaning: If the result shows a condition, who will talk it through with us, and when? Is a genetic counselor available?
You are allowed to ask for a moment to think, to reschedule, or to decline. Teams who offer this test every week expect all three responses and will not be surprised by any of them.
When to call your doctor: red flags after amniocentesis
Ordinary recovery is mild cramping and perhaps a spot of blood at the puncture site, fading over a day. Anything beyond that deserves a phone call, and the NHS and Mayo Clinic list the same warning signs.
Contact your maternity unit or the number you were given without delay if you notice any of the following: persistent or severe abdominal pain, or cramping that is getting worse rather than better; contractions, tightenings that come and go in a pattern; vaginal bleeding, particularly if it is more than light spotting or continues; a leak or gush of clear or straw-colored fluid from the vagina, which may indicate amniotic fluid; a fever, chills or feeling generally unwell, which can signal infection; redness, swelling or discharge at the needle site; or a change in the baby’s movements if you are far enough along to be feeling them regularly.
Do not wait until morning to report fluid leaking or bleeding, and do not assume that pain must be normal because pain was mentioned as possible. The cramps of a normal recovery ease with rest and time; those that intensify do not.
Most calls after amniocentesis end with reassurance. Making the call is still the right decision, because the rare complications, infection, leaking membranes, early labor, are exactly the ones where hours matter. Your team would far rather hear from you about a symptom that turns out to be nothing than not hear about one that was something. If you cannot reach the unit, seek urgent care and tell whoever assesses you that you had an amniocentesis and when.
Frequently asked questions
Does amniocentesis hurt more than a blood test?
Slightly, for most people, but in a different way. The skin puncture feels similar to a blood draw. What a blood test does not have is the pressure and brief cramp as the needle passes through the uterine wall, which the NHS compares to period pain. That part lasts about a minute and fades within minutes of the needle coming out. Most people rate the whole experience as uncomfortable rather than painful.
Do they numb you for amniocentesis?
It varies by unit. The Mayo Clinic notes that a numbing medication may be used, while the NHS explains that local anesthetic is not usually given because the injection stings and does not reduce overall discomfort much, since the cramping comes from the uterus rather than the skin. Some clinicians use a topical cream or cold spray instead. Ask your team beforehand what they routinely offer and why.
Which is more painful, CVS or amnio?
The evidence does not rank one clearly above the other. The NHS describes both as uncomfortable rather than painful, with cramping the most common sensation. Transabdominal CVS involves a needle into the denser tissue of the placenta, and some people report stronger pressure; transcervical CVS involves a speculum instead. Pain ratings across studies overlap, and the choice between them is normally made by gestational age, not comfort.
How long does it take to recover from amniocentesis?
Physically, a day or two. The NHS advises resting and avoiding strenuous activity for the rest of the day, and mild cramping or slight spotting is common in the first hours. The Mayo Clinic suggests avoiding vigorous exercise and sex for a day or two. Most people feel normal by the following day. The wait for results, about three working days for rapid results and up to three weeks for full analysis, is often the harder part.
Has anyone miscarried after an amnio?
Yes; miscarriage after amniocentesis is uncommon but real. The NHS estimates the risk at up to 1 in 100, while the Mayo Clinic cites more recent analyses putting the procedure-related risk for second-trimester amniocentesis at about 0.1 to 0.3 percent. The difference reflects improved ultrasound guidance and studies that better separate procedure-related losses from those that would have occurred anyway. Your team can discuss what these figures mean for your situation.
How long does amniocentesis take from start to finish?
The NHS puts the procedure itself at about 10 minutes, with the needle in place for roughly a minute. The appointment is longer because it includes a consent discussion, an ultrasound to locate the baby and placenta, the procedure, a heartbeat check and a short rest. Plan for one to two hours in the building and arrange for someone to take you home if possible.
Is cramping after amniocentesis normal?
Mild cramping in the hours afterward is common and expected, according to both the NHS and the Mayo Clinic, and it usually eases with rest by the end of the day. Cramping that persists, worsens, or comes in a regular pattern like contractions is not part of ordinary recovery and should prompt a call to your maternity unit, as should any bleeding, leaking fluid or fever.
Can the needle hurt the baby during amniocentesis?
It is very rare. The clinician watches the needle tip on ultrasound throughout and chooses a pocket of fluid away from the baby and the placenta, and the NHS describes needle injury to the baby as very rare. The baby’s heartbeat is usually checked immediately afterward. If the baby moves toward the needle, the clinician can pause or reposition before continuing.
Why is amniocentesis not done before 15 weeks?
Because earlier procedures carry higher risks. The NHS and Mayo Clinic note that amniocentesis before 15 weeks is associated with a greater chance of miscarriage and with a foot-positioning condition sometimes called club foot, likely because there is less fluid and the membranes are more fragile. Someone wanting a diagnostic answer earlier is usually offered CVS, which the NHS describes as performed between 11 and 14 weeks.
What can I do to make amniocentesis hurt less?
Reduce tension. Anxiety and a tight abdominal wall are the strongest predictors of higher pain scores, so a slow exhale as the needle goes in, a companion in the room and knowing the steps in advance all help. Follow the unit’s bladder instructions, eat normally, and decide whether you want to watch the screen. Ask your team whether they offer numbing and what they suggest for cramps afterward.
References
- NHS: Amniocentesis: Overview
- NHS: Amniocentesis: What happens
- NHS: Amniocentesis: Risks
- MedlinePlus: Amniocentesis (amniotic fluid test)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

After Fetal Surgery: Contraction Monitoring, Rest and the Weekly Checks Until Delivery
Recovery after fetal surgery means resting the uterus, not just the mother. For open procedures, expect a hospital stay of several days, medicines that…
Pregnancy Monitoring Visits: Records to Bring and When Fasting Is Required Beforehand
Bring photo ID, your insurance card, a written list of every medicine and supplement you take, your vaccination record, previous pregnancy and surgical history,…

What Happens During a Water Birth: Pool Temperature, Monitoring and the Moment of Delivery
During a water birth, the laboring person sits or kneels in a deep pool of water kept near body temperature, no warmer than 37.5…

Cesarean Delivery Recovery Week by Week: Walking, Incision Healing and Lifting Limits
Most people spend two to four days in the hospital after a cesarean, walk short distances within the first day, and feel steadier by…

Eating Well With Gestational Diabetes: Building Meals, Snacks and Movement Into Your Day
A gestational diabetes diet plan spreads carbohydrates evenly across three modest meals and two or three snacks, pairs every carbohydrate with protein, fiber or…