

Endoscopic Kidney Stone Removal Step by Step: Anesthesia, the Scope and the Stent
Key Takeaways
- Ureteroscopy reaches the stone through the urethra, bladder and ureter with no skin incision, which is why most people go home the same day according to the Cleveland Clinic.
- Holmium and thulium lasers fragment stones by energy absorbed in water within a fraction of a millimeter, so they break crystal without burning the ureter wall and involve no ionizing radiation.
- A ureteral stent is a planned precaution against swelling, not a sign the operation went badly, and is typically left for a few days to a few weeks before removal by a clinician.
- Blood-tinged urine is expected for a few days and intermittently while a stent is in; thick dark red urine, large clots or feeling faint are the signals to call the same day.
- Fever above 38 °C after ureteroscopy is treated as a potential infection behind the kidney until proven otherwise and warrants same-day medical assessment.
- The NIDDK notes that one stone raises the risk of another, so the fragment analysis and the prevention conversation afterward matter as much as the operation itself.
A ureteroscopy kidney stone removal procedure passes a thin telescope through the urethra and bladder into the ureter or kidney, with no incision. Under anesthesia, the surgeon sees the stone, breaks it with a laser or removes it in a tiny basket, and often leaves a temporary stent to keep urine draining. Most people go home the same day and recover over several days.
The ultrasound tech has gone quiet, the emergency physician is scrolling through the scan, and someone finally says the number: 7 millimeters. The stone sitting in your ureter is not going to pass on its own, and the urologist on call mentions a word you have never heard spoken aloud before. Ureteroscopy. Then comes a stent, a laser, a date, and a stack of questions you did not know to ask.
This explainer walks through the ureteroscopy kidney stone removal procedure the way a careful surgeon would if they had a free hour: what the anesthesia does, where the scope actually goes, how a laser breaks rock inside a living body, why the stent exists and why it is so unpopular. The aim is not reassurance for its own sake. The aim is to replace the fog with mechanism.
Nothing here replaces the conversation with your own urology team. It should make that conversation shorter and sharper.
What is the ureteroscopy kidney stone removal procedure, in plain language?
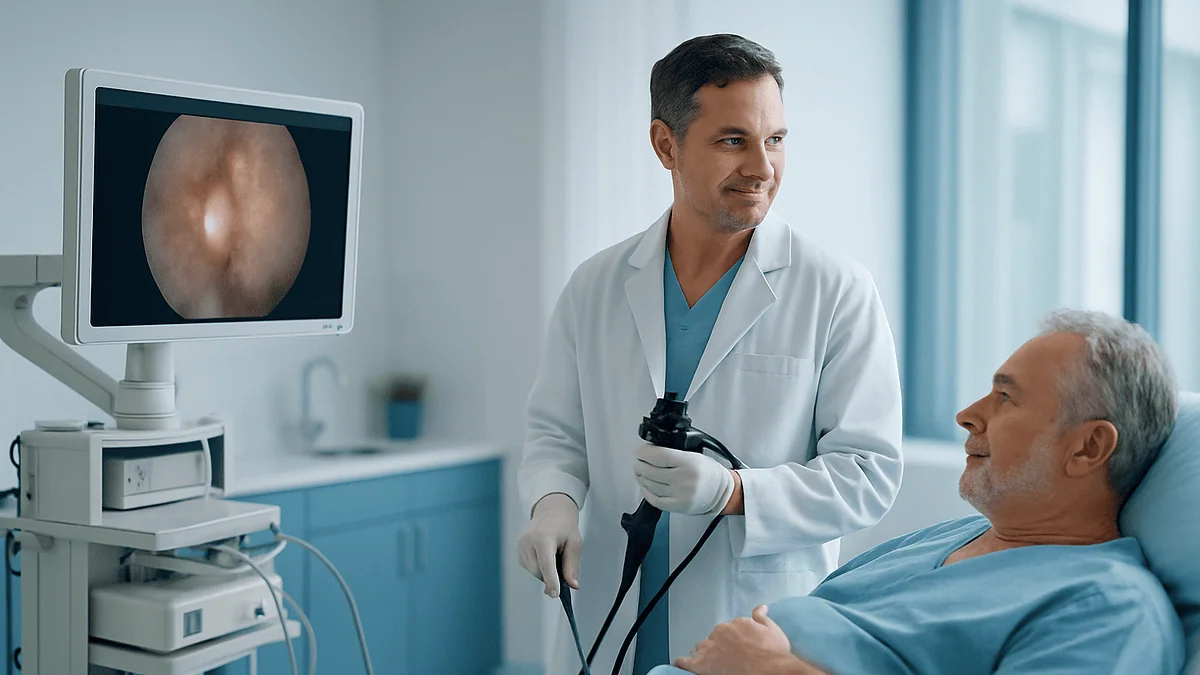
Ureteroscopy is an endoscopic operation, meaning the surgeon works through a natural opening with a camera rather than cutting through skin. The instrument is a ureteroscope: a narrow tube, roughly the width of a cooked spaghetti strand, carrying a lens, a light and a working channel. It enters through the urethra, the tube you urinate through, crosses the bladder and climbs the ureter, the muscular pipe that drains each kidney. The ureter is about 25 to 30 centimeters long in an adult and only a few millimeters wide, which is exactly why stones get stuck in it.
Two kinds of scope exist. A semi-rigid scope is used for stones in the lower and middle ureter. A flexible scope, which can bend its tip like a snake’s neck, reaches the upper ureter and the branching inner chambers of the kidney itself. Many operations use both.
Once the stone is in view, the surgeon has a choice. Small stones can be captured whole in a wire basket, a tiny cage that opens around the stone and closes to grip it. Larger stones are fragmented with a laser fiber passed down the working channel, a technique called lithotripsy, from the Greek for “stone crushing”. The pieces are then basketed out or left as fine dust to pass with urine. The National Institute of Diabetes and Digestive and Kidney Diseases describes this as the standard approach for stones lodged in the ureter or kidney that are too large, too stubborn or too painful to pass naturally.
Nothing is stitched because nothing is cut. The body’s own plumbing is the surgical corridor, which explains both the quick recovery and the particular aftereffects, from stinging urine to the sensation that the stent is a permanent houseguest.
Who is ureteroscopy usually for, and who is usually asked to wait?
Not every stone needs an operation. The NHS notes that most stones small enough, typically under about 4 millimeters, pass on their own within a few weeks, helped by fluids and pain relief, and that larger stones are progressively less likely to do so. Guideline bodies therefore frame ureteroscopy around a few questions rather than a single size cut-off.

Ureteroscopy is commonly offered when a stone has lodged in the ureter and is not moving, when pain cannot be controlled, when the kidney behind the stone is swelling with trapped urine (hydronephrosis), or when a kidney stone is too large or awkwardly positioned for a reasonable chance of passing. It is also favored over shock wave treatment for stones in the lower part of the kidney, for very hard stones, in people who take blood thinners, and in pregnancy, where X-ray guided alternatives are avoided. People with a single functioning kidney are often treated sooner because there is no backup.
Some people are asked to wait, and the waiting is a medical decision, not a queue. A small stone in someone with manageable pain, normal kidney blood tests and no infection may be given a trial of passage first. Mayo Clinic describes medical expulsive therapy, in which an alpha-blocker, a drug class that relaxes the muscle of the ureter wall, is sometimes prescribed to ease passage; whether it is appropriate is for the prescribing clinician.
The one situation that reverses the order is infection. A stone blocking a kidney that has become infected is an emergency. In that case surgeons typically drain the kidney first with a stent or a nephrostomy tube, treat the infection, and return for the stone days or weeks later. Operating on an infected, obstructed kidney risks pushing bacteria into the bloodstream.
Before the day: what preparation actually involves
Preparation is less about rituals and more about three things the team wants to know: what the stone is doing, whether your urine is sterile, and whether anesthesia is safe for you.
Imaging usually means a low-dose CT scan without contrast, which shows the stone’s size, position and density. Density matters because very hard stones take longer to fragment. A urine culture is sent beforehand; if bacteria grow, the operation is often postponed until a course of antibiotics has cleared them, because instruments passed through infected urine can seed infection upward. Blood tests check kidney function and clotting.
You will be asked about every medicine you take, and the question is not polite box-ticking. Anticoagulants and antiplatelet drugs, the classes that thin blood, raise bleeding risk in the ureter and kidney. Whether to pause one, and for how long, is a decision made jointly by the urologist, the anesthesiologist and whoever prescribed it, weighing stroke or clot risk against bleeding. Do not stop anything on your own. Diabetes medicines, blood pressure tablets and herbal supplements all get the same review.
Fasting instructions come from the anesthesia team. Typically that means no food for several hours before the operation and clear fluids until closer to the time, but your own written instructions override anything you read here.
Practical preparation is simpler. Arrange a ride home; you cannot drive after a general anesthetic. Bring a list of allergies. Expect to sign a consent form that mentions a stent, even if a stent is only a possibility, because surgeons prefer not to wake you to ask. The Cleveland Clinic describes ureteroscopy as usually a same-day procedure, so pack for a long afternoon rather than a stay, while knowing that an overnight bed is sometimes needed.
Anesthesia for ureteroscopy: what you will and will not feel
Ureteroscopy is almost always done under general anesthesia, where you are fully unconscious, breathing with the help of an airway device, and remember nothing. Occasionally a spinal anesthetic is used instead: a single injection in the lower back numbs everything below the waist while you stay awake or lightly sedated. The choice depends on your health, the expected length of the operation and the anesthesiologist’s judgment, and it is worth asking which is planned.

Why not local anesthetic, as with a simple bladder inspection? Because the ureter is a muscular tube that spasms when instruments pass, and because a flexible scope working inside the kidney needs a completely still patient. Even a small cough can move the kidney by a centimeter or more, which is a long way when a laser is firing inside it. General anesthesia keeps the field motionless and lets the surgeon work without the clock pressure of a patient in discomfort.
Modern general anesthesia is a controlled process rather than a single injection. A short-acting intravenous drug sends you to sleep in under a minute; an inhaled or infused agent keeps you there; a breathing device, often a soft mask that sits above the voice box, maintains oxygen. Monitoring covers heart rhythm, blood pressure, oxygen level and the carbon dioxide you exhale. Mayo Clinic notes that serious anesthetic complications are uncommon in otherwise healthy people, and the pre-operative assessment exists precisely to identify those who need extra precautions.
Afterward, expect the ordinary hangover of anesthesia: a dry throat from the airway device, grogginess for several hours, sometimes nausea, which anti-sickness drugs given during the operation are designed to blunt. The stinging you notice on first urinating is from the scope, not the anesthetic. Both fade, but on different timetables.
Step by step: where the scope goes and what the surgeon sees
With you asleep and positioned with legs supported in stirrups, the operation unfolds in a predictable sequence. Knowing it demystifies the operative note you may read later.
First, a cystoscope, a short rigid telescope, inspects the urethra and bladder. The surgeon finds the ureteral orifice, the small slit where the affected ureter enters the bladder, and threads a soft guidewire up it under X-ray guidance. The wire is the safety line: if anything goes wrong higher up, it guarantees a path for a stent.
Second, the scope itself follows. For a lower ureteral stone, the semi-rigid scope may reach it within minutes. For a kidney stone, the surgeon often first places a ureteral access sheath, a thin hollow tube that sits in the ureter and lets the flexible scope slide in and out repeatedly without re-threading the whole channel. Sterile saline flows continuously through the scope to keep the view clear, which is why you may feel bloated or urinate larger volumes afterward.
Third comes the stone. On the screen it looks like a yellow-brown or grey pebble, sometimes smooth, sometimes spiky, often sitting in a pocket of inflamed tissue. The surgeon decides between basketing and lasering, described in the next section.
Fourth, inspection. After fragmentation, the flexible scope tours each kidney chamber, called a calyx, looking for leftover pieces. Residual fragments are a recognized reason stones recur, so this sweep is deliberate rather than quick.
Finally, the stent decision, and withdrawal of everything. Johns Hopkins Medicine describes a typical ureteroscopy as taking somewhere between about 30 minutes and two hours, depending on stone size, hardness and how many stones there are. Then you wake in recovery with, usually, nothing visible on the outside at all.
Laser lithotripsy for kidney stones: how a stone is broken inside the body
The laser used in most operating rooms today is a holmium laser, named for the rare earth element inside it. Its energy travels down a glass fiber thinner than a human hair, which the surgeon rests directly on the stone’s surface. Each pulse is absorbed by the water inside and around the stone, creating a tiny, violent vapor bubble and a shock that chips the crystal structure. Because the energy penetrates only a fraction of a millimeter into tissue, a fiber held correctly damages the stone and not the ureter wall. Newer thulium-based lasers work on a similar principle with a different energy profile; which machine is used is a matter of equipment and surgeon preference, not something that should drive your choice of treatment.
Two strategies exist, and surgeons mix them. Fragmentation uses higher-energy pulses to split the stone into chunks, which are then captured in a basket and pulled out. Dusting uses lower-energy, higher-frequency pulses to grind the stone into particles fine enough to flush out in urine over the following days. Dusting avoids repeated basket trips up and down the ureter; fragmentation gives the surgeon a stone sample to analyze and a cleaner kidney at the end. The choice depends on stone size, composition and location, and on how much the ureter will tolerate.
Why not simply pull every stone out whole? Because a stone that fits through the ureter whole usually would have passed by itself. Anything much larger than a few millimeters needs to be reduced first, or it will tear the lining on the way out. The NHS lists ureteroscopy with laser fragmentation as one of the main treatments for stones that cannot pass, alongside shock wave lithotripsy and keyhole kidney surgery. Stone fragments retrieved are typically sent for chemical analysis, which shapes the diet and prevention advice that follows.
The ureteral stent after ureteroscopy: why it is placed and what it feels like
A ureteral stent is a soft, hollow plastic tube, roughly the length of a pencil and the width of a thin drinking straw, with a curl at each end. One curl sits in the kidney, the other in the bladder, and urine drains through and around it. Its job is to keep the ureter open while the lining, which has just been stretched, scraped and sometimes lasered, swells and then settles. Without it, that swelling can block the kidney for a few days, bringing back the exact pain the operation was meant to end.
Not everyone gets one. Surgeons weigh how much the ureter was instrumented, whether an access sheath was used, whether fragments remain, whether there was infection, and whether you have a single kidney. The Cleveland Clinic notes that a stent is often left for a few days to a few weeks; the NHS gives a similar range. The precise duration is set by your surgeon and should be written on your discharge paperwork, because a forgotten stent can encrust with crystals and become a problem of its own.
Stents are the part of the operation people complain about most, and the complaints are legitimate. The bladder curl rubs the bladder lining, producing urgency, frequency, a sense of incomplete emptying and, commonly, a dull flank ache when you urinate as a little urine refluxes up the tube. Blood-tinged urine is usual while a stent is in. Some people barely notice theirs; others find a week of it exhausting. Medicines from the alpha-blocker and anticholinergic classes are sometimes prescribed to relax the ureter and quiet bladder spasm; whether they suit you is for the prescribing clinician.
Removal is quick. Some stents have a string left trailing from the urethra so the stent can be pulled out at home or in clinic; others are removed with a brief office cystoscopy under local anesthetic. Either way, most of the discomfort ends within a day of the stent leaving.
Ureteroscopy vs shock wave lithotripsy vs PCNL: how the main stone treatments compare
Three procedures treat most stones that will not pass. Each has a job it does best, and the right one depends on the stone, the kidney and the person. The comparison below summarizes the general picture described by the NHS and Mayo Clinic, not a league table.
| Feature | Ureteroscopy | Shock wave lithotripsy (ESWL) | Percutaneous nephrolithotomy (PCNL) |
|---|---|---|---|
| How it reaches the stone | Scope through urethra, bladder and ureter | Focused sound waves from outside the body | Small incision in the back directly into the kidney |
| Typical stone size | Small to medium, ureter or kidney | Small to medium, best in upper kidney | Large or complex kidney stones |
| Anesthesia | Usually general | Sedation or general | General |
| Hospital stay | Usually same day | Usually same day | Usually one or more nights |
| Stent commonly needed | Often | Sometimes | Often, plus possible drain |
| Main limitations | Stent symptoms; ureter injury rare | Less effective on hard or lower-pole stones; fragments must pass | Larger wound; bleeding risk higher |
Shock wave lithotripsy is the gentlest to the body on the day, since nothing enters it, but the fragments still have to travel the ureter and may need a second session. Percutaneous nephrolithotomy, often shortened to PCNL, is the most invasive and is reserved for stones too large for the other two, where its ability to clear a kidney in one operation outweighs the incision. Ureteroscopy sits between them and has gradually become the most frequently performed of the three in many health systems, partly because scopes and lasers have become finer and more flexible.
Watchful waiting with pain control remains the fourth option for small stones in a well person. Your team may reasonably propose any of these, and a second ureteroscopy is sometimes planned from the outset for a very large stone burden. The sensible question is not which procedure is best, but which fits this stone in this kidney.
Ureteroscopy recovery time: the first days and the following weeks
Recovery from a ureteroscopy kidney stone removal procedure is measured in days for the body and sometimes longer for the mood, because the stent dominates the early experience.
The first evening is about the anesthetic wearing off and the first few trips to the bathroom. Expect burning when you urinate, pink or rusty urine, urgency, and a cramping ache in the flank or lower abdomen. Pain relief is usually from the acetaminophen and anti-inflammatory classes, chosen and dosed by your team; opioids are not routinely needed. Drinking enough to keep urine pale helps flush fragments and dust and dilutes the blood, which looks dramatic in the bowl at even tiny concentrations.
Days two to four are typically the plateau. Many people are moving around normally and off regular painkillers, though stent symptoms persist. The Cleveland Clinic advises that most people can return to ordinary daily activities within a few days, with heavier exertion deferred until the stent is out and any bleeding has settled. Desk work is often possible within that window; physically demanding jobs usually wait a week or more. A dull ache during urination, caused by urine briefly backing up the stent, can last the entire time the stent is in place.
Stent removal, somewhere between a few days and a few weeks after the operation depending on your surgeon’s plan, is for most people the real finish line. Mild bleeding and stinging may return for a day or two afterward and then stop.
Weeks later comes the follow-up that matters most: imaging, usually an ultrasound or X-ray, to confirm the kidney has cleared and is draining, and stone analysis results that steer prevention. Passing small gritty fragments for a couple of weeks after dusting is expected and not a sign of failure. Persistent severe pain, fever or inability to urinate are not part of normal recovery and belong in the red-flag section below.
Blood in urine after ureteroscopy: how long is normal?
Hematuria, the medical word for blood in urine, is close to universal after ureteroscopy, and the color alarms people out of proportion to the volume. A single milliliter of blood turns a whole toilet bowl visibly pink; a few milliliters make it look like weak red wine. The blood comes from the ureter and kidney lining, which has been scraped by the scope, and from the bladder wall, which the stent rubs with every movement.
What the evidence and clinical guidance describe is a predictable pattern. The Cleveland Clinic and Johns Hopkins Medicine both describe blood-tinged urine as typical for a few days after the procedure, with intermittent pinkness for as long as a stent stays in place, usually worse after activity, after a long walk or at the end of the day. A stent-free ureteroscopy generally clears faster. Small dark clots the size of a grain of rice can appear and are usually old blood leaving rather than new bleeding.
Hydration matters here more than anywhere else in recovery. Dilute urine is less irritating to a raw lining and keeps small clots from forming into larger ones that can plug the bladder outlet. Rest tends to turn the urine clearer; exertion, including sex and heavy lifting, tends to turn it red again while the stent is in. Neither change is dangerous in itself.
The pattern that should prompt a call is different in kind, not just degree. Urine that is thick and dark red like cranberry juice rather than pink, clots that are large or passing repeatedly, bleeding that is increasing rather than easing after the first few days, feeling faint or light-headed, or being unable to pass urine because of clots: these need same-day advice. People taking blood thinners should ask their team specifically what level of bleeding warrants a call, since their threshold is lower and their restart timing is individualized.
What can go wrong: risks and complications explained without drama
Ureteroscopy is among the safer operations in urology, but it is still an operation inside a narrow tube next to a vital organ, and honest consent names the risks. Guideline summaries from the NHS and Mayo Clinic group them roughly as follows.
Infection is the most clinically important. Urinary infection after ureteroscopy ranges from a mild bladder infection to urosepsis, where bacteria enter the bloodstream and cause fever, shaking chills, a racing heart and confusion. Pre-operative urine cultures and a dose of preventive antibiotics during the operation exist to reduce this; they do not eliminate it. Fever after ureteroscopy is treated as a potential emergency until proven otherwise.
Injury to the ureter sits next. Minor scrapes are expected and heal within days. A perforation, a small hole through the ureter wall, is uncommon and is usually managed simply by leaving a stent in longer while it seals. A ureteral avulsion, where the ureter tears through, is rare and serious, requiring reconstructive surgery; surgeons avoid it by never pulling a basket against a stone that will not move. Stricture, a scar that narrows the ureter months later, is another uncommon late problem and one reason follow-up imaging is scheduled.
Residual fragments are the most common imperfection rather than a complication. Pieces hidden in a kidney pocket may need a second procedure or a period of monitoring. Stent-related symptoms, discussed earlier, are nearly universal rather than rare, and a stent that migrates or is forgotten can calcify.
Bleeding significant enough to need transfusion, anesthetic reactions, blood clots in the legs and failure to reach the stone because the ureter is too tight, in which case a stent is placed and the operation repeated after a couple of weeks, round out the list. None of these are reasons to refuse treatment of a stone that is damaging a kidney; they are the reasons to ask your surgeon how often each happens in their hands and what the plan is if one does.
What people often get wrong about ureteroscopy
Misconceptions cluster around this operation, partly because the word “laser” invites science fiction and partly because online forums amplify the worst stent stories.
The first myth is that the laser burns a hole or is a kind of radiation. It is neither. Holmium and thulium lasers deliver pulses of light energy absorbed almost entirely by water within a fraction of a millimeter, which is why they can fragment a stone resting against living tissue. There is no ionizing radiation from the laser; the only radiation in the room is the brief X-ray used to guide the wire.
The second is that “the stone was removed, so I am done.” Stone disease is a tendency, not an event. The NIDDK notes that people who have formed one stone are at increased risk of forming another, which is why the fragments are analyzed and why fluid, diet and sometimes medication advice follows. Treating the stone is not the same as changing the chemistry that made it.
The third is that a stent means something went wrong. In most cases a stent is a planned precaution against post-operative swelling, decided before the first incision would have been made if there were one. Its presence says nothing about how well the operation went.
The fourth is that drinking enormous volumes of water will dissolve a stone or wash out a stent. Water dilutes urine and helps small fragments pass; it does not dissolve calcium stones, which make up the majority, and a stent stays until a clinician removes it. The opposite error, deliberately drinking less to reduce bathroom trips with a stent, concentrates urine and worsens irritation.
The last is that ureteroscopy is “minor.” It is minimally invasive, which describes the route, not the significance. A general anesthetic, instruments inside a kidney and a recovery that includes a foreign body in the bladder deserve the same seriousness as any operation, including the follow-up appointment people are most tempted to skip.
Questions to ask your care team before you agree
A good surgeon welcomes questions; a good patient brings the ones that change decisions rather than the ones that merely soothe. These are the questions that experienced urology nurses say they wish more people asked.
- What size and position is my stone, and why is ureteroscopy preferred over waiting, shock wave lithotripsy or PCNL in my case?
- What type of anesthesia is planned, and is there anything in my history that makes it riskier?
- Will you use a basket, a laser or both, and will you aim to fragment or to dust? What are the chances fragments will remain?
- Do you expect to place a stent? If so, for how long, will it have a string, and how and where will it be removed?
- If the ureter is too narrow to pass the scope, what happens next, and how long is the wait for a second attempt?
- Which of my current medicines should I pause, who decides, and when do I restart them?
- What should I expect my urine to look like, and at what point does bleeding become a reason to call?
- What is your threshold for fever? Who do I call at night or on a weekend, and will there be an open bed if I need one?
- When can I drive, return to work, exercise and have sex?
- What follow-up imaging is planned, when will I get the stone analysis, and will someone discuss prevention with me?
Write the answers down or bring someone who will. Anesthesia fogs memory for the rest of the day, and the discharge nurse’s instructions are often the ones people later cannot recall. Ask for everything in writing, including the stent removal date. A stent that is forgotten is not a hypothetical problem; it is a well-documented one, and the simplest safeguard is a date on the fridge.
The decision to proceed, to wait, or to choose a different procedure sits with you and your treating team together. These questions are how you make that decision an informed one rather than a nervous one.
When to call your doctor: red-flag signs after a ureteroscopy kidney stone removal procedure
Most of what you feel after ureteroscopy is uncomfortable but expected: stinging, urgency, pink urine, a flank ache on urinating while the stent is in. A shorter list of symptoms is different, and the difference is urgency. The NHS and Mayo Clinic guidance on post-procedure warning signs converges on the following.
Seek care the same day, or go to an emergency department, if you develop a fever above 38 °C (100.4 °F), shaking chills, or feel suddenly unwell, confused or very drowsy. Infection behind a recently instrumented kidney can escalate to sepsis within hours, and antibiotics started early change the course. Do not wait to see if it settles overnight.
Call urgently for severe pain that is not controlled by the pain relief you were given, especially if it resembles the original stone pain and keeps building. This can signal a blocked ureter from swelling, a clot or a fragment, or a stent that has shifted.
Treat the following as same-day problems as well: inability to pass urine or only dribbling, urine that is thick dark red rather than pink, large or repeated clots, vomiting that prevents you from keeping fluids down, a stent string that has been pulled and a stent you can see or feel at the urethra, and any sign of a leg clot such as a swollen, painful calf, or chest pain and breathlessness, which need emergency services.
Less urgent but still worth a call within a day or two: bleeding that is increasing instead of easing after the first few days, burning that worsens rather than improves, cloudy foul-smelling urine, or stent symptoms you cannot tolerate.
When in doubt, ring the number on your discharge sheet. Urology teams expect these calls and would far rather hear about a false alarm at midnight than a true one at noon the next day. Every judgment about what your symptoms mean, and what to do about them, belongs to the clinicians who know your operation.
Frequently asked questions
What is ureteroscopic stone removal?
Ureteroscopic stone removal is an endoscopic procedure in which a thin telescope is passed through the urethra and bladder into the ureter or kidney to locate a stone, then either lift it out in a wire basket or break it into fragments with a laser. No incision is made. It is usually performed under general anesthesia and often finishes with a temporary stent to keep the kidney draining while the ureter settles.
How long do you pee blood after ureteroscopy?
Pink or rusty urine is typical for a few days after ureteroscopy, and intermittent blood-tinged urine often continues as long as a stent is in place, usually worse after activity. Drinking enough to keep urine pale dilutes it. Thick dark red urine, large or repeated clots, bleeding that increases rather than eases, or feeling faint are not expected and need same-day advice from your team.
What are things to worry about after a ureteroscopy?
The symptoms that genuinely matter are fever above 38 °C or shaking chills, severe pain that pain relief does not touch, inability to pass urine, heavy bleeding with clots, and a swollen painful calf or chest pain. These can indicate infection, obstruction or a blood clot and need same-day assessment. Stinging, urgency, mild flank ache on urinating and pink urine are expected while a stent is in.
How long does it take to recover from ureteroscopy and laser lithotripsy?
Most people are back to ordinary daily activities within a few days, with heavier exertion deferred until the stent is removed and bleeding has settled, according to Cleveland Clinic guidance. Stent symptoms can persist for the whole time it is in, typically a few days to a few weeks. Full recovery is usually judged at a follow-up visit with imaging to confirm the kidney has cleared.
Is laser lithotripsy for kidney stones painful?
The operation itself is not felt because it is done under general or spinal anesthesia. Afterward, people describe burning when urinating, bladder urgency and a cramping flank ache, mostly related to the stent rather than the laser. These are usually managed with pain relievers from the acetaminophen and anti-inflammatory classes, chosen by the treating team, and ease markedly once the stent is removed.
Why do I need a ureteral stent after ureteroscopy?
A stent keeps the ureter open while its lining, stretched and scraped by the scope, swells and then heals, preventing a temporary blockage that could bring back stone-like pain or back up an infected kidney. Not everyone needs one; surgeons weigh how much the ureter was instrumented, whether fragments remain and whether infection was present. It is removed by a clinician or via a string after a planned interval.
What is the ureteroscopy recovery time for returning to work?
Desk-based work is often possible within a few days, while physically demanding jobs usually wait a week or more, and sometimes until the stent is out. The timing depends on how you feel, how much blood is in your urine and how tolerable the stent is. Your surgeon can give a range tailored to your operation; most hospital guidance frames return to normal activity in days rather than weeks.
Can ureteroscopy be done on both kidneys at the same time?
Bilateral ureteroscopy, treating stones in both ureters or kidneys in one anesthetic, is sometimes performed when stone burden on each side is modest and the person is otherwise well. It avoids a second anesthetic but means stents on both sides, which doubles stent symptoms and can raise the risk of complications. Many surgeons prefer staged operations for larger stones; the decision rests with your treating team.
What happens if the scope cannot reach the stone?
In some people the ureter is too narrow for the scope to pass safely. Rather than force it and risk injury, the surgeon places a stent and stops. Over the following couple of weeks the stent gently dilates the ureter, and a second ureteroscopy is scheduled, which usually succeeds. This is a recognized and planned-for scenario rather than a failure, and it is worth asking beforehand how your surgeon handles it.
Does ureteroscopy stop kidney stones from coming back?
No. Ureteroscopy treats the stone that is present; it does not change the urine chemistry that formed it, and the NIDDK notes that having one stone raises the risk of another. Prevention depends on stone analysis, fluid intake, diet adjustments and sometimes medicines that alter urine chemistry, all discussed with your clinician at follow-up. The operation is one step; the prevention plan is the longer project.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When PKD Advances: How Dialysis or Kidney Transplant Planning Begins Before It Is Urgent
As polycystic kidney disease advances, planning for dialysis or a kidney transplant usually begins when kidney function falls into the later stages of chronic…

What Does the Urethrogram Show Before Urethral Reconstruction? Mapping the Stricture
A urethrogram before urethroplasty is an X-ray study in which contrast dye outlines the inside of the urethra to map a stricture, the scar…
Hereditary Nephropathy and Relatives: How Family Screening and Counseling Are Arranged
Family screening for hereditary kidney disease usually begins when one relative receives a confirmed genetic diagnosis. The care team then identifies who else shares…

Questions to Ask Before Testosterone Treatment: Fertility, Monitoring and Alternatives
Before starting testosterone treatment, ask whether low testosterone was confirmed on at least two separate morning blood tests, whether an underlying cause was looked…

How to Choose Among Erectile Dysfunction Treatment Options: Questions for Your Urologist
Choosing among erectile dysfunction treatments starts with a urologist's assessment of causes, heart health, and the medicines you already take. Options range from lifestyle…

When Testicle Pain and Swelling Need a Urologist the Same Day: The Orchitis Pathway
Testicle pain with swelling should be assessed the same day, and sudden severe pain that begins over minutes to hours is an emergency, because…