

Ethnic Rhinoplasty Results: How Surgeons Refine the Nose While Preserving Heritage Features

Key Takeaways
- Ethnic rhinoplasty is a planning philosophy, not a distinct operation: it adjusts proportion while keeping the features that mark you as yourself and as part of your family.
- Many heritage-preserving rhinoplasties add structure with cartilage grafts rather than removing tissue, because thick skin only shows definition when the framework beneath is strong.
- Septal, ear and rib cartilage each have trade-offs in supply, strength and donor-site recovery, and synthetic implants carry a lifelong low risk of infection or extrusion.
- The external splint typically comes off at about a week, most people return to desk work in one to two weeks, and strenuous exercise is usually avoided for four to six weeks, per Mayo Clinic and the NHS.
- Final results can take up to a year to appear, and the tip is the slowest area to settle in thicker skin, so early photographs are a poor guide.
- Post-inflammatory darkening at visible incisions is more common in darker skin, and consistent sun protection during healing is the most useful preventive step a patient controls.
Ethnic rhinoplasty results depend on reshaping the nose in proportion to a person's own face while keeping the features that signal their heritage, rather than copying a single ideal. Surgeons typically add structure with cartilage grafts, refine the tip and narrow the nostril base conservatively. Swelling settles over months, and the final shape can take about a year to appear. Outcomes vary and are never guaranteed.
She had two folders on her phone. One held noses she admired; the other held photographs of her mother, her grandmother and two aunts, all sharing the same soft bridge and generous tip. She wanted the first folder without losing the second. That tension, between change and belonging, is the question that brings most people to a consultation about ethnic rhinoplasty results.
For decades, textbooks described one “ideal” nose, and it belonged to one narrow slice of humanity. People of African, East Asian, South Asian, Middle Eastern, Hispanic and Indigenous heritage who had surgery in that era sometimes emerged with a nose that looked borrowed. Modern practice has moved on, and the goal now is harmony with your own face.
This explainer walks through what the operation actually involves, why anatomy shapes the plan, what the weeks of healing look like, and which risks deserve a frank conversation before anyone books a date.
What does "ethnic rhinoplasty" actually mean?
Rhinoplasty is surgery that changes the shape of the nose, whether for appearance, breathing or both. “Ethnic rhinoplasty” is not a separate operation. It is a label for rhinoplasty planned around anatomy that differs from the thin-skinned, high-bridged nose that older surgical teaching treated as the default.
The term is imperfect, and many surgeons dislike it. Every nose belongs to someone with an ethnicity, so the phrase can imply that one group is the norm and everyone else is the exception. What the label is really trying to capture is a shift in philosophy: the surgeon adjusts proportion and definition while deliberately keeping the traits that mark a person as themselves and as part of their family.
In practical terms, that shift changes three things. First, the goals move from reduction to balance. Where a classic Western rhinoplasty often removes a hump, many noses in these groups need structure added rather than taken away. Second, the skin is treated as a design constraint. Thicker skin drapes differently and hides fine detail, so the plan under the skin has to be bolder to show through. Third, the surgeon plans with the whole face in mind, including cheekbones, lip projection and chin, because a nose that suits one facial framework can look out of place on another.
MedlinePlus describes rhinoplasty broadly as reshaping the bone and cartilage of the nose, sometimes with grafts, and notes that the operation can be tailored to many aims. Ethnic rhinoplasty simply sharpens that tailoring so the result reads as a refined version of the original, not a replacement.
How ethnic rhinoplasty works: what actually happens during surgery
Most rhinoplasty is performed under general anesthesia or deep sedation and takes a few hours, according to Mayo Clinic. The surgeon reaches the framework of the nose in one of two ways. A closed approach uses incisions hidden inside the nostrils. An open approach adds a small cut across the columella, the strip of skin between the nostrils, which lets the surgeon lift the skin and see the cartilage directly. Open approaches are common when grafts must be placed precisely, which is often the case in heritage-preserving work.
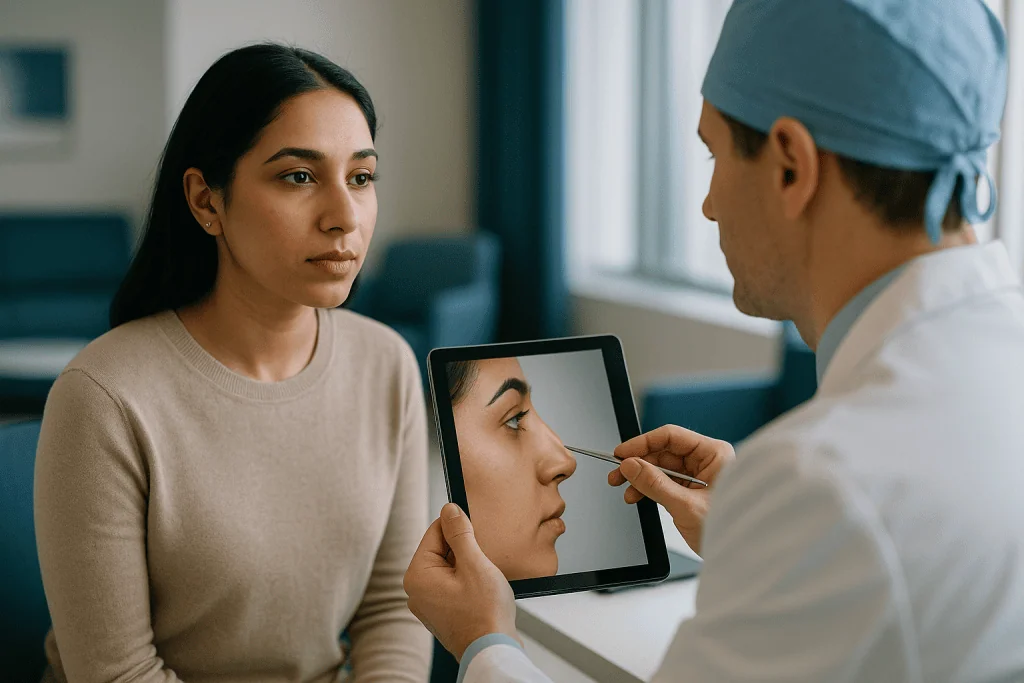
Once inside, the operation is a series of small, deliberate steps rather than one dramatic change. The bridge may be raised with a graft if the radix, the spot where the nose meets the forehead, sits low. The tip cartilages may be sutured together or supported by a strut to give more definition without making the tip pinched. If the nostrils are wide relative to the rest of the face, the surgeon may remove a sliver of tissue at the alar base, the point where each nostril meets the cheek, and stitch it closed so the base narrows modestly.
Breathing is checked at the same time. A deviated septum, the wall dividing the two nasal passages, may be straightened, and enlarged turbinates, the fleshy ridges that warm and humidify air, may be reduced. Cleveland Clinic notes that functional and cosmetic goals are frequently combined in one procedure.
At the end, the surgeon closes the incisions with fine sutures and places a splint over the bridge to protect the new shape. Internal packing is used less often than it once was. You wake with a stuffy, tender nose and a splint that comes off at the first follow-up visit, usually within about a week per Mayo Clinic.
Why nasal anatomy differs, and why that changes the surgical plan
There is no such thing as an “African nose” or an “Asian nose” in a single template. Variation within any group is wide, and many people have mixed heritage. Still, certain patterns are common enough that surgeons plan around them, and knowing the vocabulary helps you follow your own consultation.
Skin thickness matters more than almost anything else. Thick skin with abundant oil glands, common in many people of African, South Asian and some Hispanic backgrounds, blunts fine changes to the cartilage beneath. A surgeon who shaves a millimeter here and there will see nothing show through. Instead, the framework often needs to be built up so it can push against the skin and create definition.
Bridge height varies. A low radix and a flatter dorsum, the visible ridge of the nose, are frequent in East Asian and some African and Southeast Asian noses. Raising the bridge usually means adding tissue rather than removing it, which is the opposite of the classic hump reduction.
Tip support also differs. Softer, thinner tip cartilages provide less structural push, which is why the tip may look rounded or under-projected. Strengthening that support is a recurring theme.
Finally, nostril shape and the angle between the columella and the upper lip vary widely. Wider, more horizontally set nostrils are common in African and some Hispanic noses, and a narrower nostril flare may suit the face only if it is kept in proportion. Over-narrowing is one of the classic errors that produces an artificial look.
A careful surgeon measures these features against the whole face, not against a chart, and explains which ones they propose to change and which they intend to leave alone.
What realistic ethnic rhinoplasty results look like
The honest answer is: subtle, and slow to reveal themselves. A well-planned heritage-preserving rhinoplasty tends to make the nose look more defined and better balanced, while relatives still recognize you instantly. If a result is startling from across the room, something in the planning probably overshot.
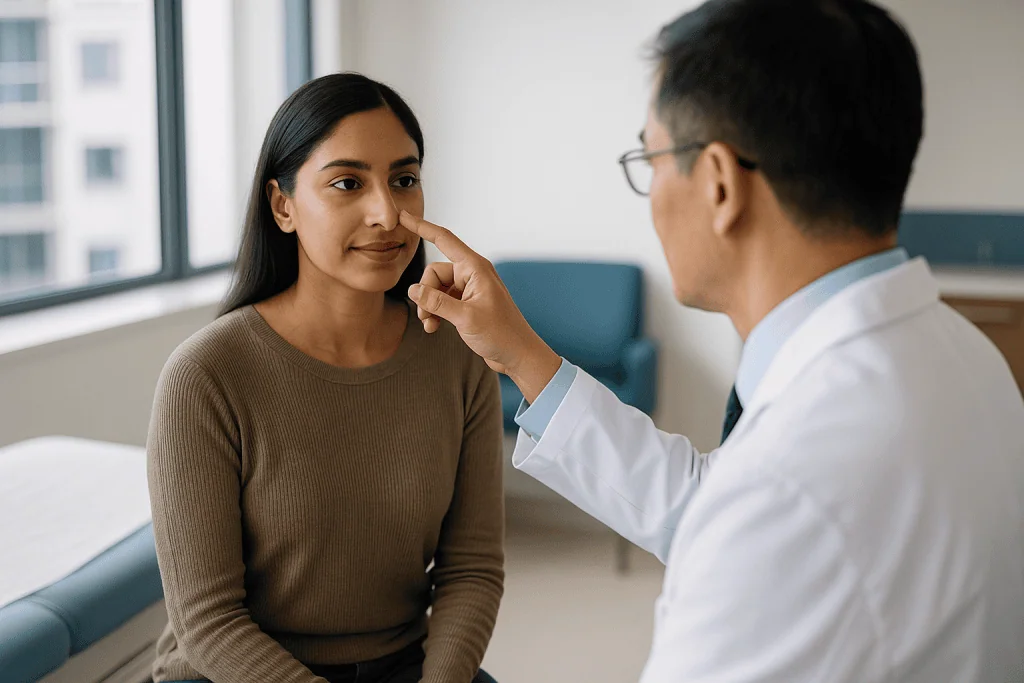
Changes people commonly notice include a slightly higher, smoother bridge; a tip that looks more defined when they smile or look down; nostrils that sit a little closer to the width of the face; and, if the septum was corrected, easier breathing through both sides. Changes people should not expect include a completely different profile, skin that is suddenly thin, or a tip so crisp it belongs on a different face.
Timing shapes perception. Swelling hides the shape for weeks. Mayo Clinic notes that while most swelling resolves in weeks, subtle swelling can persist for up to a year, and the NHS gives a similar expectation, stating that it can take up to a year to see the final result. In thicker-skinned noses, surgeons often warn that the tip is the last place to settle.
Outcomes are not guaranteed. Cartilage can shift as scar tissue matures, skin may not contract as hoped, and a small asymmetry can appear once swelling recedes. Mayo Clinic acknowledges that some people need a second operation to correct residual issues, and it is reasonable to ask how your surgeon handles that scenario before you commit.
Think of the goal as a version of your nose that looks rested and well proportioned, the way a good haircut frames a face without changing who is in the mirror. Anything promising more than that deserves scepticism.
Who is usually a candidate, and who is usually asked to wait
Surgeons generally look for three things: a nose whose shape or function bothers you consistently rather than fleetingly, a face that has finished growing, and general health that makes anesthesia and healing safe. Mayo Clinic advises that facial growth should be complete, which typically means the mid to late teens, before cosmetic rhinoplasty is considered.
Good candidates also have specific, realistic goals. “I want the bridge a little higher and the tip a bit more defined, but I want to keep my nostril shape” is the kind of statement surgeons can plan around. “I want to look like the person in this photograph” is not, particularly when that person has an entirely different facial framework.
Several groups are commonly asked to wait or to reconsider. People who smoke or vape nicotine are often asked to stop well before surgery, because nicotine narrows blood vessels and impairs healing; the timing is a decision for the surgical team. Those with uncontrolled diabetes, bleeding disorders or certain autoimmune conditions may need optimization first. People who are pregnant or trying to conceive are usually asked to defer.
A history of thick or raised scarring, known as keloid formation, does not rule out surgery, but it warrants a specific conversation, especially if an alar base reduction or open approach is planned. Mental health matters too: surgeons are trained to recognize body dysmorphic disorder, a condition in which distress about appearance is out of proportion to any visible feature, and surgery is not a treatment for it.
Finally, anyone who feels pressured by a partner, a parent or an online trend rather than by their own long-standing wish is usually encouraged to pause. Rhinoplasty is elective, and the decision should sit comfortably with you and your treating team.
Preserving heritage features: what the planning conversation should cover
The most important part of a heritage-preserving rhinoplasty happens before anyone picks up a scalpel. It is a conversation, sometimes two or three, in which you and the surgeon agree on what “better” means for your face specifically.
Expect to be photographed from several angles and to see those images on a screen. Many surgeons use imaging software to sketch a proposed change. Treat the sketch as a communication tool, not a promise; software cannot model how your skin will heal. It is useful mainly for saying “that is too much” or “that still looks like me.”
Bring the photographs that matter. Pictures of family members can help the surgeon understand which features you consider part of your identity. Some people bring images of noses they like; a thoughtful surgeon will explain which elements translate to your anatomy and which do not.
Ask about the surgeon’s approach to specific features. Do they intend to change the nostril shape or only narrow the base slightly? Will they alter the angle between the nose and lip? Do they plan to raise the bridge, and if so, with what material? The answers reveal whether the plan is additive and conservative or reductive and aggressive.
Discuss breathing separately from appearance. Cleveland Clinic notes that rhinoplasty can correct structural problems that block airflow, and Johns Hopkins describes assessment of the internal nasal valves and septum as part of planning. If breathing is an issue, make sure it is addressed rather than treated as an afterthought.
Finally, say out loud what you fear. If you are worried about looking “generic” or losing a family resemblance, name it. Surgeons cannot protect a feature they do not know you value.
Cartilage grafts: where the extra structure comes from
Because many heritage-preserving procedures build rather than subtract, grafts are central. A graft is a piece of tissue, usually cartilage, moved from one place to another to add height, support or definition.
The first choice is usually septal cartilage, taken from inside the nose itself. It is firm, straight and lies conveniently in the surgical field. Its limitation is quantity: a smaller septum, common in lower-bridged noses, may not yield enough for both a bridge augmentation and tip support.
Ear cartilage is the next option. It is harvested from the bowl of the ear through an incision hidden behind or inside the ear, and the ear’s shape is unchanged. Ear cartilage is naturally curved and softer, which suits tip work but is less ideal for a long, straight bridge graft unless it is layered or diced.
Rib cartilage provides the largest, strongest supply and is often used when a substantial bridge lift is planned or in revision surgery. It requires a small chest incision, adds chest soreness to recovery, and carries a small risk of warping over time as the cartilage settles. Surgeons have techniques to minimize this, but the possibility is worth knowing.
Synthetic implants made of medical-grade silicone or porous polyethylene are used in some practices, particularly for bridge augmentation. Their advantage is that no donor site is needed. Their disadvantage is a lifelong, though low, risk of infection, extrusion through the skin or visible edges, and they can be harder to correct if problems arise. Mayo Clinic notes that grafts and implants both carry risks specific to the material, and the choice between your own tissue and an implant is one to discuss carefully with your surgeon rather than decide from an online forum.
Ethnic rhinoplasty recovery time: the first days and weeks
Recovery follows a fairly predictable arc, though the pace varies with skin thickness, how much work was done and whether rib cartilage was harvested. The figures below are typical ranges from the cited sources, not promises.
| Timeframe | What most people experience | Source |
|---|---|---|
| First 24–72 hours | Stuffy nose, mild oozing, bruising around eyes, sleeping with head raised | Mayo Clinic |
| About 1 week | External splint removed at follow-up; most bruising fading | Mayo Clinic, NHS |
| 1–2 weeks | Many people return to desk work and light activity | NHS, Cleveland Clinic |
| 4–6 weeks | Strenuous exercise and contact sports usually still avoided | NHS |
| 3–6 months | Most swelling gone; shape becoming clear | NHS |
| Up to 12 months | Residual tip swelling settles; final result visible | Mayo Clinic, NHS |
In the first week, the aim is to protect the new framework. You will be asked to sleep propped up, avoid blowing your nose, skip glasses that rest on the bridge for several weeks, and use cold compresses around, not on, the nose. Pain is usually described as pressure rather than sharp pain, and your team will advise on pain relief; do not take anything that thins the blood without asking, since Mayo Clinic notes that aspirin and similar medicines increase bleeding risk.
If rib cartilage was used, the chest incision adds a few weeks of soreness with deep breaths and twisting. Ear cartilage donor sites are usually mildly tender for a week or two.
Nasal congestion can last several weeks as internal swelling recedes. Saline rinses are commonly recommended, and your surgeon will tell you when it is safe to start them. Follow-up visits are typically scheduled at one week, a few weeks, and then at intervals through the first year.
Asian rhinoplasty healing and thicker skin: why swelling takes longer
People with thicker nasal skin often report that their nose looks “the same” or even fuller for months, and they worry the operation did nothing. Usually it did; the skin is simply slow to shrink down onto the new framework.
Thick skin contains more sebaceous glands and a denser layer of fat and connective tissue. After surgery, this layer holds fluid longer, and the space between the new cartilage shape and the skin fills with a soft scar layer before it matures. The tip, where the skin is thickest, is the last area to settle. Mayo Clinic’s guidance that swelling can persist up to a year applies with particular force here, and some surgeons counsel patients with very thick skin that tip definition may continue evolving beyond that.
This has two practical consequences. First, resist judging the result early. Photographs at six weeks are a poor guide to the shape at twelve months. Second, follow post-operative instructions on taping or pressure if your surgeon uses them; some teams apply thin tape over the tip at night for weeks to encourage the skin to contract evenly. Whether this is used, and for how long, is the surgeon’s decision.
In some cases, surgeons may offer an injection of an anti-inflammatory steroid medication into a persistently swollen area of the tip during follow-up. The mechanism is to calm scar tissue and reduce fluid, and the timing and appropriateness depend entirely on the treating team’s assessment. It is not something to request on a schedule found online.
For bridge augmentation, the healing sequence differs slightly: the new dorsal line often looks defined early, then softens as swelling spreads, then sharpens again over months. Knowing that pattern in advance spares a great deal of anxiety.
African American rhinoplasty results: scars, pigmentation and what the evidence says
Two concerns come up repeatedly in consultations with people of African heritage: visible scarring and dark marks. Both deserve a direct, evidence-based answer rather than reassurance.
Most rhinoplasty incisions are hidden inside the nostrils or on the columella, where scars usually fade to a fine line. Alar base reduction, however, places a small incision in the crease where the nostril meets the cheek, and this is the scar people ask about most. In darker skin, healing scars may pass through a phase of post-inflammatory hyperpigmentation, a temporary darkening caused by extra melanin production at the site of healing. It commonly lightens over months, and diligent sun protection during that period is the single most useful thing a patient can do, since ultraviolet exposure deepens the discoloration. The NHS notes generally that scars from nose reshaping are usually small and well hidden, and that scarring risk varies between individuals.
Keloids, thick raised scars that grow beyond the original wound, are more common in people with darker skin, but they are rare on the nose compared with the chest, shoulders and earlobes. A personal or family history of keloids should be disclosed, because it affects where incisions are placed and whether an ear cartilage harvest is advisable.
Beyond scarring, the results themselves hinge on the same principles as any heritage-preserving rhinoplasty: building tip support, raising a low bridge if desired, and narrowing the nostril base in proportion. The historical error was to narrow too much. Contemporary teaching emphasizes keeping nostril shape recognizable and avoiding a pinched tip that reads as artificial against fuller lips and cheekbones. Ask your surgeon to show you how they decide how much base to remove and what they consider too much.
Ethnic nose job risks and complications to weigh honestly
Rhinoplasty is generally safe, but it is surgery, and Mayo Clinic, MedlinePlus and the NHS all list a consistent set of risks. Some apply to any operation; others are specific to the nose; a few carry extra weight in heritage-preserving work.
General surgical risks include bleeding, infection at the incision or graft site, and a reaction to anesthesia. Serious bleeding is uncommon but can occur in the first days or, less often, a week or two later as internal scabs loosen.
Nose-specific risks include persistent congestion, numbness of the skin over the tip that usually improves over months, a small hole in the septum called a perforation, asymmetry, a shape that differs from what was planned, and the possibility of a further operation. Mayo Clinic states plainly that revision surgery is sometimes needed and that the final shape may not match expectations.
Graft-related risks depend on material. Your own cartilage can resorb slightly or warp; rib cartilage adds a chest scar and a small risk of injury to the lining of the lung during harvest. Synthetic implants carry a lifelong risk of infection or extrusion.
In thicker-skinned noses, a specific risk is a soft tissue pollybeak, a fullness above the tip caused by scar tissue filling space, which can blunt the definition the surgery aimed for. In darker skin, prolonged hyperpigmentation at visible incisions is a possibility discussed above.
Alternatives exist. Doing nothing is always an option. Filler injections can temporarily camouflage a low bridge or small irregularity, but they cannot narrow a nose or improve breathing, and they carry their own serious, if rare, risk of blocking blood vessels. Discuss all options, including no treatment, with your treating team, who will weigh them against your health and goals.
What people often get wrong about ethnic rhinoplasty results
Myths cluster around this topic, partly because so much of what people see online is filtered, staged or selected.
“The nose will look done at six weeks.” It will not, especially with thicker skin. Both Mayo Clinic and the NHS put the final result at up to a year. Early photographs mislead in both directions, hiding good work and exaggerating minor swelling.
“Ethnic rhinoplasty means making the nose look European.” That was the historical failure, not the goal. The modern aim is proportion with your own face. If a surgeon describes your nose only in terms of what needs to be “fixed,” that is a signal to keep looking.
“Thick skin cannot be refined.” It can, but refinement comes from stronger structure beneath, not thinning the skin, and it takes patience. The limits are real, and a good surgeon will state them.
“A closed approach is always better because there is no scar.” The columellar scar from an open approach usually heals to a barely visible line, and the visibility it gives the surgeon often matters more for precise graft placement. The choice is about the job, not the scar.
“Liquid rhinoplasty is a safe rehearsal.” Filler can preview a higher bridge, but it adds volume, cannot narrow anything, and carries a small risk of blocking an artery that supplies the skin or eye. It is not a harmless trial run.
“Surgeons in a particular country get better results.” Skill is individual, and travel complicates follow-up, which matters enormously in the first year. Continuity of care with the operating team is the variable that consistently helps.
“Once healed, the result is permanent and fixed.” The nose keeps aging with the rest of the face, and grafts can shift subtly over years. Long-term follow-up is part of the deal.
Questions to ask your care team before you decide
Consultations go faster when you arrive with a list. These questions are designed to surface the surgeon’s philosophy, not to test them.
- Which features of my nose do you propose to change, and which do you intend to keep unchanged? Can you point to each one on my photographs?
- Will you be adding structure, removing it, or both? If adding, what graft material do you plan to use and why that one for me?
- How do you decide how much to narrow the nostril base, and how do you avoid over-narrowing?
- How does my skin thickness affect what is realistically achievable, and how long do you expect my swelling to last?
- Do you plan an open or closed approach, and what drives that choice in my case?
- Will my breathing be assessed and, if needed, treated in the same operation?
- What is your approach if I have a history of keloids or dark marks after healing?
- What complications have you seen in patients with anatomy like mine, and how were they managed?
- How often do your patients need a second procedure, and how do you handle that conversation?
- What is your follow-up schedule over the first year, and who do I contact after hours if something worries me?
- What would you advise if I decided not to have surgery at all?
Listen for specificity. A surgeon who answers in terms of your anatomy, cites real limits and describes how they manage problems is giving you the information you need. A surgeon who answers only in terms of how good the result will be is not. Take notes, bring a companion if you can, and give yourself time between the consultation and any decision; the NHS suggests taking time to reflect and seeking a second opinion for cosmetic surgery. The decision, in the end, belongs to you and your treating team together.
When to call your doctor after rhinoplasty
Most recovery is uneventful, and a stuffy, bruised, slightly weeping nose is expected in the first week. Some signs, however, mean you should contact your surgical team the same day, and a few mean going to an emergency department.
Call your surgeon promptly if you notice bleeding that soaks through dressings repeatedly or does not slow with gentle pressure and head elevation; a fever, especially with increasing redness, warmth or swelling around the incisions or graft donor sites; thick, discolored or foul-smelling discharge from the nose or an incision; pain that is worsening rather than easing after the first few days; sudden new asymmetry or a change in the shape of the nose after a bump or fall; or any sign that an implant edge is becoming visible or the skin over the bridge is thinning or breaking down.
Seek emergency care if you have difficulty breathing that is not simply nasal congestion, chest pain or shortness of breath after a rib cartilage harvest, a large volume of bright red bleeding that will not stop, sudden vision change or severe eye pain, or signs of a severe allergic reaction such as facial swelling or hives with breathing difficulty.
MedlinePlus and Mayo Clinic both emphasize keeping every scheduled follow-up appointment, even when things feel fine, because small problems such as a shifted graft or early infection are far easier to manage when caught early. If you had surgery away from home, arrange in advance who will see you for follow-up and how you will reach the operating surgeon.
Trust your instincts. If something feels wrong, calling is always the right choice, and no reasonable surgical team will mind hearing from you.
Frequently asked questions
How long does ethnic rhinoplasty recovery time usually take?
Most people are back to desk work within one to two weeks and avoid strenuous exercise for four to six weeks, according to the NHS. The splint comes off at about a week. Visible swelling fades over three to six months, but Mayo Clinic notes that subtle swelling, especially at the tip in thicker skin, can persist up to a year before the final shape is clear.
Will ethnic rhinoplasty results make me look like a different person?
They should not. The goal of heritage-preserving rhinoplasty is a nose that fits your face and keeps recognizable family traits, so changes tend to be subtle: a slightly smoother bridge, a more defined tip, nostrils in better proportion. If a proposed plan looks like a different face on the imaging screen, say so; that is exactly what the planning conversation is for.
Why does Asian rhinoplasty healing seem slower than in thinner noses?
Thicker nasal skin holds fluid longer and takes more time to shrink down onto the new cartilage framework, so the nose can look full or unchanged for months. The tip settles last. This is normal and expected; both Mayo Clinic and the NHS put final results at up to a year, and surgeons often counsel thicker-skinned patients to expect the longer end of that range.
Do African American rhinoplasty results involve visible scars?
Most incisions are hidden inside the nostrils or on the columella, where scars usually fade to a fine line. The one visible incision is at the nostril crease if the base is narrowed. In darker skin this can darken temporarily during healing; sun protection helps it fade. Keloids on the nose are rare but any history of them should be disclosed before surgery.
What are the main ethnic nose job risks I should know about?
Risks listed by Mayo Clinic and MedlinePlus include bleeding, infection, anesthesia reactions, persistent congestion, numbness, septal perforation, asymmetry and the possibility of a further operation. Specific to heritage-preserving work are graft warping or resorption, implant infection or extrusion, scar-tissue fullness above the tip in thick skin, and prolonged darkening of visible incisions in darker skin.
Can a low bridge be raised without a chest scar?
Often, yes. Septal cartilage from inside the nose is the first choice when enough is available, and ear cartilage can be layered or diced for moderate augmentation without a chest incision. Rib cartilage is reserved for larger lifts or revision surgery. Synthetic implants avoid a donor site but carry a lifelong low risk of infection or extrusion, so the trade-off is one to discuss with your surgeon.
Is a liquid rhinoplasty with filler a good way to test the result first?
Filler can preview a higher bridge or camouflage a small dip, but it adds volume, cannot narrow the nose or improve breathing, and carries a small but serious risk of blocking an artery that supplies the skin or eye. It is a separate treatment with its own risks rather than a harmless rehearsal, and it is not a substitute for a surgical consultation.
At what age can someone have ethnic rhinoplasty?
Surgeons generally wait until facial growth is complete, which Mayo Clinic places in the mid to late teens, and many prefer later. Operating on a nose that is still growing risks a result that changes with development. Beyond age, the more important factors are stable goals, good general health, and a decision that comes from you rather than outside pressure.
What happens if I am unhappy with the result?
First, wait. Mayo Clinic and the NHS both note that the shape keeps changing for up to a year, and many early concerns resolve. If a real problem remains, revision surgery is sometimes performed, typically after the tissues have fully healed. Ask before your first operation how your surgeon approaches revisions, since scar tissue and reduced cartilage supply make second procedures more complex.
Can breathing problems be corrected at the same time?
Yes, frequently. Cleveland Clinic and Johns Hopkins describe combining cosmetic reshaping with correction of a deviated septum, reduction of enlarged turbinates or support of collapsing nasal valves in one operation. Make sure breathing is assessed as a distinct goal during planning, because structural changes for appearance can affect airflow if function is not considered alongside them.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Is Ethnic Rhinoplasty Right for You? Skin Thickness, Cartilage Strength and Goals Weighed
You may be a reasonable ethnic rhinoplasty candidate if you are in good general health, your nose has finished growing, you have a specific…

CT and MRI Before Orbit Surgery: How Imaging Maps the Eye Socket and Guides the Approach
Before orbit surgery, a CT scan maps the bony walls of the eye socket in fine detail, showing fractures, wall thickness, sinus anatomy and…

Microtia and Ear Reconstruction: How the Condition Is Assessed and When Surgery Is Timed
Microtia is a congenital condition in which the outer ear is small, misshapen or absent. Assessment begins soon after birth with hearing tests and…
When Does a Neck and Face Lift Make Sense Together? Jowls, Neck Bands and Skin Laxity
A combined neck and face lift usually makes sense when jowls, vertical neck bands and loose skin under the jaw appear together, because the…
How Bichectomy (Cheek Reduction) Is Performed: The Incision Inside the Mouth Explained
A bichectomy procedure, also called buccal fat removal, slims the lower cheeks by removing part of the buccal fat pad through a small incision…

Blood Thinners, Smoking and Rhytidectomy: What Surgeons Ask You to Stop Before a Facelift
Before a facelift, surgeons usually ask patients to stop anything that raises bleeding risk or starves healing skin of oxygen. That typically means blood-thinning…