

Hair Transplants for Diffuse Thinning: Why It Is the Hardest Case to Plan
Key Takeaways
- Thinning usually becomes visible only after a scalp region has lost close to half its density, so diffuse loss is typically further along than the mirror suggests.
- Telogen effluvium, the most common cause of sudden diffuse shedding, begins two to three months after a trigger and usually resolves within about six to nine months.
- In diffuse unpatterned alopecia (DUPA), the donor zone itself is miniaturizing, which is why most surgeons consider it a contraindication to transplantation.
- A transplant relocates existing follicles rather than creating new ones, and the lifetime donor supply is commonly estimated at only a few thousand grafts.
- Placing grafts between fragile, miniaturized hairs can trigger shock loss, and hairs that were already weakening may never regrow.
- Careful surgeons typically require a confirmed diagnosis and six to twelve months of documented stability — often on medical therapy — before operating on a diffuse case.
A hair transplant is sometimes possible with diffuse thinning, but only after careful evaluation. Surgery works best when the donor zone at the back of the scalp is stable. If thinning affects the entire scalp — a pattern called diffuse unpatterned alopecia — transplanted hair may thin too, and grafting between fragile existing hairs can trigger shedding. Most clinicians recommend diagnosing the cause and stabilizing the loss first.
Nobody with diffuse thinning has a dramatic before photo. There is no horseshoe of bare scalp, no island of loss at the crown. There is only a part line that seems a little wider than last spring, a ponytail that wraps one extra turn, and that unkind moment under a fitting-room light when the scalp glows through.
That subtlety is exactly what makes this the trickiest scenario in all of hair restoration. A receding hairline hands the surgeon a map: here is the loss, there is the reserve. Diffuse thinning hands over a fog. The loss is everywhere and nowhere, the diagnosis is often unsettled, and — most awkwardly — the very hair a surgeon would harvest may itself be on the way out.
So before anyone quotes you a graft count, it is worth understanding why careful clinicians slow down here, and what the medical evidence says a transplant can and cannot do.
What is diffuse thinning, exactly?
Diffuse thinning means hair density drops across a broad area of the scalp rather than in one defined patch or pattern. The hairline may sit exactly where it always did. What changes is the crowd behind it: fewer hairs per square centimeter, finer strands, more scalp showing when the hair is wet or the light is harsh.
A little arithmetic explains why it sneaks up on people. The scalp carries roughly 100,000 hair follicles, and shedding 50 to 100 hairs a day is completely normal, according to the Mayo Clinic. Because the head starts with such reserves, dermatologists often observe that thinning does not become obvious to the eye until a region has lost somewhere near half its density. By the time the mirror confirms your suspicion, the process has usually been running for a while.
Diffuse thinning is a description, not a diagnosis — and that distinction drives everything that follows. Behind the same widened part line could sit androgenetic (pattern) hair loss expressed diffusely, a temporary shedding condition called telogen effluvium, a thyroid or iron problem, a medication effect, or an autoimmune process. Each has a different natural course, a different treatment path, and a very different answer to the question of surgery. Treating the description without identifying the cause is how people end up disappointed — or operated on when they never should have been.
Is diffuse thinning the same as a receding hairline?
No — and the difference matters more here than almost anywhere else in hair medicine. A receding hairline is the classic opening move of male pattern hair loss: the temples retreat, the frontal edge drifts back, and the crown may follow. It is patterned, predictable, and — crucially — it spares a horseshoe of hair at the back and sides of the head. Those follicles are relatively resistant to the hormonal signaling that drives pattern loss, which is precisely why they make dependable transplant donors, as MedlinePlus notes in its overview of the procedure.
Diffuse thinning plays a different game. Density falls across the top, the crown, sometimes the whole scalp, while the hairline itself may hold its ground for years. Women experience this presentation far more often than the receding-temple pattern; the part line widens in what clinicians sometimes compare to a Christmas-tree shape.
The two can also coexist. Plenty of men have both a retreating hairline and a general drop in density behind it, and plenty of people with pattern loss go through a bout of stress-related shedding on top of it. Untangling which process is doing what is a genuine diagnostic task, not a glance-and-quote exercise. For transplant planning, the receding hairline is the easy chapter of the textbook. Diffuse thinning is the chapter with the asterisks.
Why is diffuse thinning the hardest transplant case to plan?
Three problems stack on top of each other, and any one of them alone would complicate surgery.
First, the diagnosis is often unsettled. Patterned loss usually announces itself; diffuse loss has a long list of look-alikes, several of which are temporary or medically treatable. Operating before the cause is confirmed risks transplanting into a scalp that would have recovered on its own — or that will keep shedding regardless.
Second, the donor supply is in question. A transplant does not create hair; it relocates follicles from a stable zone to a thin one. If the back and sides of the scalp are thinning too, the surgeon is being asked to borrow from a bank that is quietly going insolvent.
Third, the target keeps moving. In patterned loss, an experienced surgeon can reasonably forecast where the loss is heading and design around it. Diffuse loss offers no such map. Place grafts among today’s surviving hairs, and if those native hairs continue to miniaturize over the next five years, the result thins from within — leaving sparse transplanted hairs standing alone where a full head once camouflaged them.
None of this means surgery is impossible. It means the planning burden is heavier, the evaluation must be longer, and the honest answer at the end of a consultation is sometimes not yet. A clinician who reaches that answer quickly and cheerfully has probably skipped the hard parts.
DPA vs. DUPA: the distinction that decides almost everything
Hair restoration specialists sort diffuse cases into two broad camps, and which camp you fall into largely determines whether surgery is even on the table.
Diffuse patterned alopecia (DPA) is pattern hair loss wearing a disguise. Density drops across the top of the scalp, but the back and sides — the donor zone — remain thick and stable. Under magnification, the miniaturized, shrinking hairs cluster in the classic pattern-loss territory while donor hairs stay uniform and sturdy.
Diffuse unpatterned alopecia (DUPA) spares nothing. Miniaturization shows up in the donor zone itself. Harvest from that area and you are moving follicles that carry the same vulnerability as the ones they are meant to replace — grafts that may thin and fail in their new home, leaving visible extraction marks in a donor area too sparse to hide them.
| DPA (patterned) | DUPA (unpatterned) | |
|---|---|---|
| Where density drops | Top and crown; donor zone spared | Entire scalp, donor zone included |
| Donor hair under magnification | Uniform, stable caliber | Miniaturized hairs mixed in |
| Transplant suitability | Often possible once loss is stable | Generally considered a contraindication |
| Usual first step | Medical stabilization, then reassess | Diagnosis, medical management, no surgery |
The sorting is done with scalp magnification (trichoscopy), not with the naked eye — which is one concrete reason a video call or a photo sent to a clinic abroad cannot properly qualify a diffuse-thinning patient for surgery.
How long does diffuse hair thinning last? The telogen effluvium question
Sometimes the honest answer is: about six months, and then it gets better on its own. That is the typical arc of telogen effluvium, the most common cause of sudden, diffuse shedding — and the single best reason not to rush anyone with new thinning toward surgery.
Here is the mechanism. At any moment, roughly 90 percent of your scalp hairs are in a growth phase, with the remainder resting before they shed. A significant physiological jolt — high fever, major illness or surgery, childbirth, crash dieting, intense psychological stress, starting or stopping certain medications — can shove an unusually large share of follicles into the resting phase at once. Because resting hairs take a few months to release, the shedding shows up two to three months after the trigger, which is why people so often cannot connect the two events.
The Cleveland Clinic notes that telogen effluvium is usually self-limited, with shedding that settles and density that gradually rebuilds over roughly six to nine months once the trigger has passed. Full cosmetic recovery can take longer, simply because hair grows about a centimeter a month.
A smaller group develops chronic telogen effluvium, where shedding waxes and wanes beyond six months; that variant deserves a proper workup. But the planning lesson is blunt: transplanting a scalp that is mid-effluvium means operating on a condition that was going to resolve, while adding surgical stress that can worsen the shed. Time, in this scenario, is the treatment.
The rule-out list: medical causes that must be checked first
Before anyone talks grafts, a diffuse-thinning workup should walk through the medical causes that no operation can fix — several of which are common and correctable.
- Thyroid disease. Both an underactive and an overactive thyroid can produce diffuse shedding; hair often improves once thyroid levels are managed, per Mayo Clinic guidance on hair loss causes.
- Iron deficiency. Low iron stores are a well-recognized contributor to diffuse loss, particularly in premenopausal women. A simple blood test settles the question.
- Nutritional shortfalls. Rapid weight loss, restrictive dieting, and inadequate protein intake can all trigger shedding months later.
- Medications. A range of prescriptions list hair shedding among their possible effects; a clinician can review whether timing fits — never stop a medication on your own.
- Hormonal transitions. Postpartum shedding and the menopausal transition both commonly present as diffuse thinning.
- Autoimmune and scalp conditions. Some forms of alopecia areata mimic diffuse thinning, and certain scarring scalp disorders destroy follicles permanently — a scenario in which transplantation into inflamed skin can fail outright.
The NHS makes the broader point plainly: most hair loss does not need treatment at all, because it is either temporary or a normal part of aging — but persistent or unexplained loss warrants a diagnosis. Blood work, a scalp exam, and occasionally a small biopsy cost little compared with a misdirected operation. The rule-out list is not bureaucracy. It is where a meaningful number of diffuse-thinning stories quietly end well, without a scalpel.
Shock loss: the risk of transplanting into hair that is still there
Here is the paradox at the heart of diffuse-thinning surgery: the very hairs you are trying to reinforce can be casualties of the reinforcement.
In a typical transplant for patterned baldness, grafts go into skin that is smooth and empty. In a diffuse case, they must be threaded between thousands of surviving native hairs. Every incision, every pass of local anesthetic, every hour of surgical handling stresses the neighborhood — and stressed follicles respond the way follicles always do, by dropping into the resting phase and shedding. Clinicians call this shock loss, and it is essentially a localized, surgically induced telogen effluvium.
For healthy, robust hairs, shock loss is usually temporary; they shed, rest, and regrow over several months. The trouble is that a diffusely thinning scalp is not populated by robust hairs. Many are miniaturized — shrunken, fine, running on borrowed time. Push a hair that was already nearing the end of its productive life into a shock shed, and it may simply not come back. The net result of surgery, in a poorly chosen case, can be a scalp that looks thinner than before the procedure.
Skilled surgeons mitigate the risk with careful angling, smaller incisions, and conservative graft density among existing hairs. But mitigation is not elimination, and every candid consent conversation for a diffuse case should include this possibility in plain language. If it doesn’t, ask why.
The donor math: numbers that do not negotiate
Strip away the marketing and a hair transplant is a redistribution exercise. MedlinePlus describes it simply: healthy follicles are moved from one part of the scalp to another. Nothing is manufactured. The lifetime budget is whatever the donor zone can safely spare, and surgeons commonly estimate that budget at a few thousand grafts — figures in the range of 4,000 to 6,000 over a lifetime are widely quoted for a strong donor area, less for a weak one.
Now look at what diffuse thinning asks of that budget. A patterned case needs coverage in a defined territory: a hairline, a crown. A diffuse case needs density lifted everywhere — and density is expensive. Adding visible thickness across an entire thinning scalp can demand more grafts than any donor zone can supply, which is why realistic diffuse-case plans talk about reinforcing the areas that matter most cosmetically (typically the frontal zone and part line) rather than restoring the whole head.
There is also a spending-order problem. Grafts used today are gone tomorrow. A person in their late twenties with progressive diffuse loss who spends half their lifetime donor supply on early, marginal improvement may have nothing left when the loss advances — precisely when they would want reserves most. Good planning treats the donor zone like a retirement account: drawn down slowly, deliberately, and only once the trajectory of the loss is understood. Any plan that spends aggressively before the diagnosis is settled has the sequence backward.
How clinicians actually assess a diffuse-thinning candidate
A proper evaluation looks less like a sales consultation and more like a dermatology visit — because that is what it should be.
It starts with history: when the thinning began, whether it came on gradually or as a sudden shed, what happened in the three months before it started, family patterns, medications, diet changes, recent illness, and menstrual or hormonal history where relevant. Mayo Clinic lists these as core elements of a hair-loss workup for good reason; the story often points to the diagnosis before any instrument does.
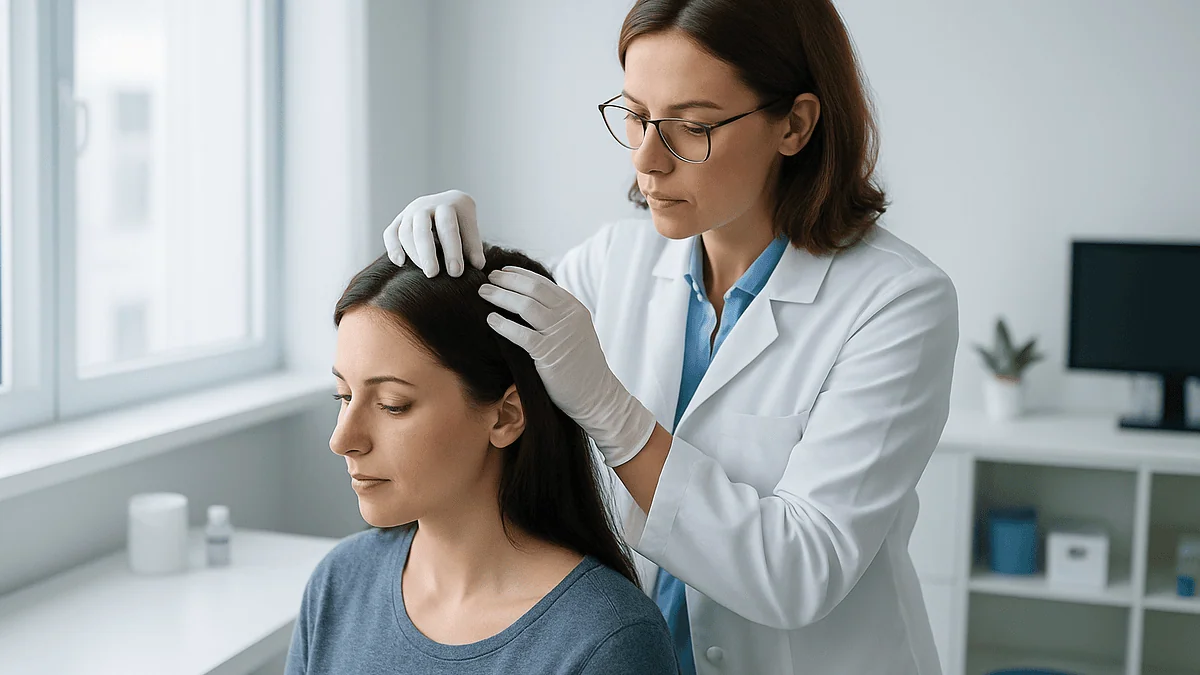
Then comes the exam. A gentle pull test — grasping small sections of hair to see how many strands release — gives a rough read on active shedding. Trichoscopy, examining the scalp under magnification, reveals what the naked eye cannot: the proportion of miniaturized hairs, their distribution, and critically, whether the donor zone is affected. This single observation separates DPA from DUPA and, with it, surgical candidates from non-candidates.
Blood tests screen for thyroid dysfunction, iron deficiency, and other contributors. When the picture stays murky — or when scarring or inflammation is suspected — a small scalp biopsy can settle it.
Finally, the most underrated tool of all: time. Standardized photographs repeated over six to twelve months show whether the loss is active, stable, or recovering. It is slower than anyone wants. It is also how careful surgeons avoid operating on a scalp that was about to heal itself, or one that is deteriorating too fast for surgery to keep up.
Why 'stabilize first' is the rule, not a stalling tactic
Almost every reputable protocol for diffuse thinning puts medical management before surgical planning, and the logic is straightforward: a transplant into an unstable scalp is an investment into a declining market.
For pattern-driven loss — including its diffuse presentation — clinician-prescribed treatments with regulatory approval for hair loss can slow further miniaturization and, in many people, modestly thicken hairs that were shrinking. Harvard Health notes that these therapies generally work better at holding ground than at rebuilding it, and that they require ongoing use to maintain benefit. That is not a cure, and no honest source will call it one. It is stabilization — and stabilization changes the surgical math entirely.
Consider the difference. Transplant into an untreated, actively miniaturizing scalp, and the native hairs around each graft keep fading; within a few years the transplanted hairs stand exposed, and the patient is back asking for more grafts from a shrinking reserve. Transplant into a scalp that has been stable on treatment for a year, and the grafts land in a defended position: the existing density holds, the new density adds to it, and the result has a fighting chance of lasting.
This is why many surgeons ask diffuse-thinning patients to commit to medical therapy and demonstrate six to twelve months of stability — documented, ideally, with photographs — before scheduling anything. A clinic that frames this waiting period as unnecessary caution is not offering you a faster path to the same result. It is offering a different, worse result sooner.
When a transplant genuinely can help diffuse thinning
After all the caveats, it is worth saying clearly: some diffuse-thinning patients are good surgical candidates, and for them the results can be meaningful.
The favorable profile looks like this. The diagnosis is diffuse patterned alopecia, confirmed under magnification, with a donor zone that shows uniform, healthy hair caliber. The loss has been stabilized — usually with medical therapy the patient intends to continue — and photographs across at least six months show a flat trajectory. Reversible causes have been ruled out with blood work. The goals are specific and modest: a denser frontal zone, a narrower-looking part, a hairline that frames the face, rather than a return to the density of age nineteen.
Execution matters as much as selection. In diffuse cases, surgeons typically work at conservative densities, angle incisions to run parallel with existing hairs, and prioritize the zones that carry the most visual weight. The frontal third of the scalp does a disproportionate share of the cosmetic work; strengthening it can transform how the whole head reads, even when total graft numbers are limited.
Patience is part of the prescription, too. Transplanted follicles shed their initial hairs, rest, and begin regrowing over three to four months, with the mature result emerging across twelve to eighteen months. Anyone who has done the diagnostic homework, stabilized the loss, and set targeted goals has stacked the odds well. Anyone who skipped those steps is gambling with a nonrenewable resource.
When to see a doctor about diffuse thinning
Some versions of this story should route you to a clinician promptly — a primary care physician or a dermatologist, well before any transplant consultation.
- Sudden or heavy shedding. Handfuls in the shower brush or on the pillow, especially over weeks rather than years, suggests an active process worth diagnosing — and often a treatable or self-resolving one.
- Shedding that persists beyond six months. Typical telogen effluvium should be settling by then; ongoing loss deserves blood work and a proper exam.
- Patches, breakage, or an unusual distribution. Circular bald spots, broken hairs, or loss along the frontal band can signal autoimmune or scarring conditions that need specific treatment.
- Scalp symptoms. Itching, burning, pain, redness, or scaling alongside thinning points away from ordinary pattern loss and toward inflammatory causes.
- Whole-body clues. Fatigue, unexplained weight change, feeling unusually cold or hot, brittle nails, or menstrual irregularities can indicate thyroid, iron, or hormonal contributors, as the NHS and Mayo Clinic both flag.
- Hair loss after starting a new medication. Raise it with your prescriber rather than stopping on your own.
There is also a quieter reason to go: distress. Hair loss is medically minor and personally major, and that gap is real. A clinician can offer a diagnosis, a plan, and honest odds — three things a mirror at 7 a.m. never provides. Early evaluation also protects your surgical options later, because the best transplant candidates are the ones whose cause was identified and managed first.
Red flags in a diffuse-thinning consultation
Because diffuse cases are the hardest to plan, they are also where the gap between careful medicine and volume-driven salesmanship shows most clearly. A few warning signs deserve attention wherever in the world you are considering treatment.
- A graft count quoted from photos alone. DPA cannot be distinguished from DUPA without magnified examination of the donor zone. No image sent over a messaging app substitutes for that.
- No interest in the cause. If nobody asks about your health history, medications, recent stressors, or orders blood work, the evaluation is incomplete by any mainstream standard.
- Guaranteed outcomes. Biology does not sign contracts. Reputable clinicians discuss probabilities, graft survival ranges, and the specific risk of shock loss in diffuse cases.
- Pressure to book quickly. Diffuse thinning rewards observation over six to twelve months. Urgency serves a sales calendar, not your scalp.
- No mention of medical stabilization. A surgical plan for progressive loss that includes no strategy for slowing that loss is a plan to sell you a second surgery.
- Silence about DUPA. Any clinic that treats every diffuse case as operable has either never heard of unpatterned alopecia or has decided it is bad for business.
The most reassuring thing a surgeon can say in a diffuse-thinning consultation is some version of you might not be a candidate, and here is how we will find out. That sentence costs them revenue. It is also the sound of someone planning your case rather than your invoice.
So — is diffuse thinning fixable?
It depends entirely on what is driving it, which is a more hopeful answer than it sounds.
When the cause is telogen effluvium, the fix is usually built in: remove or outlast the trigger, and density typically recovers over the following six to twelve months without any procedure at all. When the cause is thyroid disease, iron deficiency, or a nutritional gap, correcting the underlying problem often allows substantial regrowth. These are genuinely reversible chapters, and they are common.
When the cause is pattern hair loss in diffuse form, “fixable” becomes “manageable.” Evidence-based medical treatment can slow the process and thicken miniaturized hairs in many people, though it maintains rather than cures, and benefits fade if treatment stops. For the right patient — patterned loss, strong donor zone, stable trajectory, realistic goals — a transplant can then add real, lasting density where it counts most.
And when the diagnosis is diffuse unpatterned alopecia, honesty matters most: surgery is generally off the table, medical management and cosmetic strategies become the mainstays, and a clinician who says so plainly is doing right by you.
The through-line is sequence. Diagnose, then treat, then stabilize, then — and only then — decide about surgery. Diffuse thinning punishes shortcuts more brutally than any other hair-loss scenario, because every shortcut spends either time, money, or irreplaceable donor follicles. Taken in order, though, the steps are neither mysterious nor hopeless. They are just medicine, done properly, at the speed the biology demands.
Frequently asked questions
Can I get a hair transplant with diffuse thinning?
Sometimes, but only after a thorough evaluation. Surgery is realistic when magnified examination shows your donor zone at the back of the scalp is healthy and stable — a picture called diffuse patterned alopecia — and when the loss has been diagnosed and stabilized, usually with medical therapy, for at least six to twelve months. If the donor area is thinning too, most surgeons will advise against operating.
Is diffuse thinning fixable?
It depends on the cause. Shedding from telogen effluvium, thyroid problems, or iron deficiency often recovers substantially once the trigger or deficiency is addressed. Diffuse pattern hair loss is manageable rather than curable: medical treatment can slow it and thicken miniaturized hairs, and selected patients may later benefit from surgery. Diffuse unpatterned alopecia is generally not correctable with a transplant.
Is diffuse thinning the same as a receding hairline?
No. A receding hairline is patterned loss concentrated at the temples and frontal edge, typically sparing the back and sides — which is what makes those areas reliable transplant donors. Diffuse thinning is a broad drop in density across the scalp, often with the hairline intact. The two can occur together, and distinguishing them under scalp magnification is a key step in transplant planning.
How long does diffuse hair thinning last?
If the cause is telogen effluvium, shedding usually starts two to three months after a trigger such as illness, childbirth, or major stress, and settles within roughly six to nine months, with density rebuilding gradually afterward. Shedding that continues beyond six months, or thinning driven by pattern hair loss, tends to persist or progress and deserves a medical evaluation rather than watchful waiting.
What is the difference between DPA and DUPA?
Diffuse patterned alopecia (DPA) thins the top of the scalp while sparing the donor zone at the back and sides, so transplantation is often feasible once the loss is stable. Diffuse unpatterned alopecia (DUPA) involves miniaturization across the entire scalp, donor area included; grafts taken from an unstable zone can thin in their new location, which is why DUPA is widely considered a contraindication to surgery.
What is shock loss after a hair transplant?
Shock loss is temporary shedding of existing hairs around transplant sites, triggered by the physical stress of incisions and anesthetic. Healthy hairs usually regrow within months, but in diffuse thinning many surrounding hairs are already miniaturized and fragile — and those may not return. This is a central risk of operating on thinning rather than bald scalp, and it belongs in every honest consent discussion.
Will transplanted hair thin out too?
It can, if the follicles came from an unstable donor zone. Transplanted hairs keep the characteristics of their origin: grafts from a healthy, pattern-resistant donor area typically persist, while grafts harvested from a scalp with unpatterned diffuse loss carry the same vulnerability they had before the move. This is exactly why magnified donor-zone assessment comes before any graft count.
What tests should I have before deciding on surgery?
A proper workup includes a detailed history, a scalp examination with magnification (trichoscopy) to map miniaturization and check the donor zone, a gentle hair pull test, and blood tests screening for thyroid dysfunction and iron deficiency, among others. When the picture is unclear or a scarring condition is suspected, a small scalp biopsy may be added. Serial photographs over several months help confirm whether the loss is stable.
Can women with diffuse thinning have hair transplants?
Some can, but candidacy tends to be more restrictive. Women’s hair loss is more often diffuse and more often involves the donor zone, and reversible contributors — thyroid disease, iron deficiency, hormonal transitions — are more frequent, so a medical workup comes first. Women whose donor area proves stable under magnification and whose loss has plateaued can be reasonable candidates for targeted density work, particularly along the part line.
How long until you see results from a diffuse-thinning transplant?
Expect twelve to eighteen months for the full picture. Transplanted hairs typically shed within the first few weeks, rest, and begin regrowing around three to four months after surgery, with density building steadily thereafter. Because grafts in diffuse cases are threaded among existing hairs, any shock loss in the surrounding hair can make the early months look worse before the combined result matures.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Hair Transplant Success Rates: What the Numbers Mean and What They Hide
Most credible estimates put hair transplant graft survival at roughly 85 to 95 percent when an experienced surgical team treats a well-selected candidate. That…

Eyebrow Transplants Before and After: Realistic Results and Their Upkeep
An eyebrow transplant moves roughly 50 to 400 hair follicles per brow, usually taken from the scalp, into thin or missing eyebrows. Transplanted hairs…

Can You Stop a Receding Hairline? What Works and What Does Not
A receding hairline caused by hereditary pattern hair loss can usually be slowed and sometimes partly reversed, but not cured. Prescription treatments that lengthen…
Norwood 4–5: Mid-Stage Hair Loss and What a Transplant Can Realistically Cover
Norwood 4 and 5 describe moderate-to-advanced male pattern hair loss: deep frontal recession plus a thinning or bare crown. A hair transplant is still…

Hair Transplant Scars: FUE Dots vs FUT Line, and How Each Ages
Every hair transplant leaves permanent scarring. FUE creates hundreds to thousands of tiny round dot scars scattered across the donor zone, while FUT leaves…

Norwood 7: When Is It Too Late for a Transplant — and When It Is Not
Norwood 7 — a horseshoe of hair around the sides and back with a bald crown and top — is the most advanced stage…