

Receding Hairline: The Norwood Stages, Temple Thinning and the Options at Each Stage

Key Takeaways
- A mature hairline typically rises about one finger-width above the forehead and then stops, while a receding hairline keeps retreating and hollows the temples into an M shape.
- The Norwood scale runs from 1 to 7, and stage 3 is the first that dermatologists formally classify as balding.
- Topical minoxidil (approved 1988) and oral finasteride (approved 1997) remain the only FDA-approved medicines for androgenetic alopecia, with the strongest randomised trial evidence of any option.
- Medicines act on miniaturized follicles that are still alive, which is why they hold ground more reliably than they reclaim it, and why the crown responds better than the frontal hairline.
- Temple recession in a postmenopausal woman, especially with eyebrow thinning, raises concern for frontal fibrosing alopecia, a scarring condition in which lost follicles do not recover.
- No population study shows Gen Z balding earlier than previous generations; pattern loss has long been visible in roughly a quarter of men by their mid-twenties.
A receding hairline is the gradual backward movement of the front hairline, usually starting at the temples, and in most men it is the first visible sign of androgenetic alopecia (male pattern hair loss). Dermatologists grade it with the Norwood scale from stage 1 to 7. Early stages often respond to approved medicines such as minoxidil and finasteride; advanced stages typically rely on hair transplantation. A clinician should confirm the cause first.
The video has a familiar shape: a twenty-three-year-old tilts his head toward the bathroom light, pulls his fringe back with two fingers, and asks the camera whether that angle at the temple was there last summer. As of mid-2025, clips like this sit under hashtags claiming that an entire generation is going bald early, and searches for “receding hairline” have climbed alongside them, boosted by social media interest in oral minoxidil and in hair transplant travel.
Most of what circulates is anecdote. Some of it is dangerous. Almost none of it explains the one thing a worried person actually needs: where their hairline sits on a recognised scale, what that stage usually means, and which options have real evidence behind them.
That is the job of this piece. We will walk the Norwood stages from the first temple notch to a horseshoe of remaining hair, separate a maturing hairline from a receding one, and grade the evidence for every option, from the two medicines approved in the United States to the procedures and devices that people ask about most.
What is a receding hairline, and how is it different from a mature hairline?
Nearly every boy has a hairline that sits low and rounded, sometimes almost touching the eyebrows at its lowest point. Between the late teens and the late twenties, that juvenile hairline lifts by roughly a finger’s width and squares off slightly at the corners. Dermatologists call the result a mature hairline. It is a normal developmental change, it happens in most men, and it stops on its own.
A receding hairline is different in two ways. First, it keeps going. Second, it moves unevenly, carving deeper at the temples than at the center so that the front of the scalp takes on an M shape. The hairs at the retreating edge do not simply vanish; they shrink. Each hair follicle, the small pocket in the skin that grows a hair, produces progressively finer, shorter, paler hairs over successive growth cycles, a process called miniaturization. Eventually the follicle produces a hair too small to see.
A simple home check helps separate the two. Place a fingertip flat against the top of your forehead, directly above the nose, and raise your eyebrows. In a mature hairline the front edge usually sits about one finger-width above the highest forehead crease, and the temples are only slightly set back from the center. If the center has stayed put while the temples have hollowed noticeably, or if the retreat has continued over months, that pattern points toward androgenetic alopecia, the medical term for hormone-and-gene-driven pattern hair loss.
Photographs matter more than memory. Comparing the same angle, under the same light, a year apart tells you far more than a worried glance in the mirror, and it is exactly what a dermatologist will ask for.
What are the Norwood stages of a receding hairline?
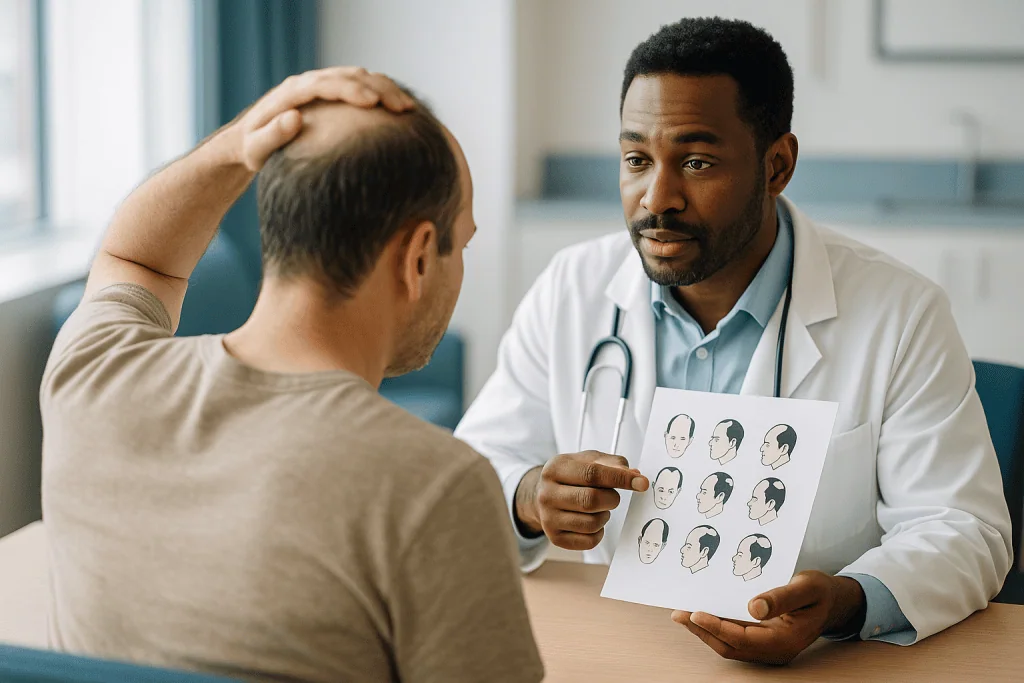
The Hamilton-Norwood scale, usually shortened to the Norwood scale, is the classification clinicians use to describe how far male pattern hair loss has progressed. It runs from stage 1, no meaningful recession, to stage 7, in which only a band of hair remains around the sides and back. Think of it less as a verdict than as a map reference: it tells you where you are and which routes are still open.
| Norwood stage | What it typically looks like | Options usually discussed at this stage |
|---|---|---|
| 1 | Juvenile or mature hairline, no recession beyond normal maturing | Monitoring, photographs, scalp care |
| 2 | Mild, symmetrical temple recession; early M shape | Minoxidil, finasteride, annual photo comparison |
| 3 | Deep temple recession; this is the first stage classed as balding | Medicines; transplant discussed only if loss is stable |
| 3 vertex | Stage 3 front plus thinning at the crown | Medicines for both zones; combined approach |
| 4 | Severe frontal loss plus a crown patch, separated by a bridge of hair | Medicines to protect the bridge; transplant planning |
| 5 | Bridge narrows; front and crown nearly meet | Transplant with realistic density goals; medicines to hold remaining hair |
| 6 | Bridge gone; one large bald area | Transplant limited by donor supply; camouflage options |
| 7 | Horseshoe of hair at sides and back only | Camouflage, scalp micropigmentation, acceptance-based options |
Two caveats keep the table honest. The scale was built from men, and it maps poorly onto women, who more often thin across the top while keeping the front edge. It is also a snapshot, not a forecast. A man at Norwood 3 at 25 may stay there for twenty years or reach Norwood 5 by 32, and no chart can tell which. Family history offers a rough guide, speed of change over the previous two years a better one.
What causes a receding hairline in the first place?
The short answer is genes acting through a hormone. Testosterone is converted in the skin into dihydrotestosterone, or DHT, by an enzyme called 5-alpha reductase. In people who inherit sensitivity to DHT, follicles along the front hairline and crown respond to it by shortening their growth phase and shrinking. The sides and back of the scalp carry follicles that largely ignore DHT, which is why that horseshoe of hair survives even at Norwood 7, and why those follicles can be moved to the front in a transplant and keep growing.
The inheritance is not the simple “it comes from your mother’s father” story that circulates online. Many genes contribute, from both sides of the family, and a man whose father kept a full head of hair can still recede early. Mayo Clinic lists heredity, hormonal changes and age as the dominant drivers of pattern hair loss, with medical conditions and medicines as separate categories.
Those separate categories deserve attention, because not every retreating hairline is androgenetic. Thyroid disease, iron deficiency, significant illness or surgery, rapid weight loss and certain medicines can trigger telogen effluvium, a diffuse shedding that can make a hairline look thinner without the characteristic M shape. Traction alopecia, caused by hairstyles that pull hard on the front hairs over years, produces recession at the temples that can be mistaken for pattern loss and, if caught early, stops when the pulling does.
Stress is a frequent suspect and an occasional culprit. Severe emotional or physical stress can push a large share of follicles into their resting phase at once, with shedding two to three months later. It does not, on current evidence, cause classic pattern recession, though it can unmask thinning that was already under way.
What is frontal thinning, and why does hair thinning at temples appear first?
Frontal thinning describes reduced density across the front third of the scalp, from the hairline back toward the mid-scalp. It is a broader term than receding hairline: a hairline can hold its position while the hairs just behind it grow finer and the scalp starts to show through under bright light. Many men notice frontal thinning first as a wider-looking parting or as a forehead that photographs as larger in flash pictures.

Hair thinning at the temples appears early because of the geography of DHT sensitivity. Follicles in the frontotemporal corners are among the most androgen-responsive on the scalp. They tend to miniaturize before the central tuft, which is why the typical early pattern is a pair of deepening notches with a peninsula of hair left in the middle. Hair stylists call that surviving peninsula the forelock, and its persistence is one of the clues that distinguishes pattern loss from diffuse shedding, in which the whole front thins evenly.
In women the pattern usually differs. Female pattern hair loss most often widens the central parting in a Christmas-tree shape while sparing the hairline itself. When a woman does develop frontotemporal recession, especially after menopause, clinicians consider frontal fibrosing alopecia, a scarring condition in which inflammation destroys follicles along the hairline and often the eyebrows. Scarring alopecias are a different disease with a different urgency, because follicles destroyed by scarring do not recover.
Practical takeaway for the mirror: the location of thinning, the shape of what remains and the state of the eyebrows are all diagnostic information. A dermatologist will use a handheld magnifier called a dermatoscope to look for miniaturized hairs, which confirms androgenetic alopecia within minutes in most cases.
Why is Gen Z balding so fast? Separating signal from social media
The claim that a generation born after 1997 is losing hair faster than its parents is one of the most shared hair-loss ideas of the past two years. The honest answer is that there is no robust population study showing a shift in the age of onset of androgenetic alopecia. Pattern hair loss has always begun early for a sizeable minority: MedlinePlus notes that it can start in the teens or early twenties, and classic observational surveys have found visible recession in roughly a quarter of men by their mid-twenties.
What has changed is visibility. Front-facing phone cameras, harsh ring lights and the habit of filming oneself from a slightly elevated angle all exaggerate the temples. A hairline that would have gone unexamined in 1995 now appears in high resolution several times a day, and is compared against filtered or transplanted hairlines in the same feed.
Several real factors could plausibly contribute to earlier noticing, even if they do not change the underlying biology. Crash dieting and very low-calorie eating patterns can trigger telogen effluvium. Iron deficiency is common in young people who eat little red meat. Tight styling, from slicked-back looks held with strong product to high ponytails and braids, can produce traction recession at the temples. Anabolic steroid and some supplement use raises androgen exposure and can accelerate pattern loss in those predisposed.
None of this adds up to a generational epidemic, and framing it as one tends to drive two unhelpful behaviors: panic purchases of unproven products and avoidance of a clinician who could confirm what is actually going on. If you are in your early twenties and noticing temple change, the evidence-based move is unglamorous. Take standardized photos, look at your relatives, and book a dermatology appointment if the change continues over six to twelve months.
Which race is the least bald? What population data actually show
People ask this question bluntly, and the medical literature answers it cautiously. Observational studies, mostly from clinic populations rather than whole countries, have reported that androgenetic alopecia is most common and tends to start earliest in men of European ancestry, is somewhat less prevalent in men of East Asian ancestry, and appears lower again in some African and Indigenous American populations. These are tendencies across groups, not predictions for an individual, and the quality of the evidence is modest: sample sizes vary, definitions of “balding” differ, and few studies follow the same men over decades.
Why would ancestry matter at all? Pattern hair loss depends on inherited sensitivity to DHT and on the genetics of the androgen receptor, and the frequency of relevant gene variants differs between populations. Hair shaft diameter, curl pattern and the typical density of follicles per square centimeter also vary, which affects how quickly thinning becomes visible even when the underlying follicle loss is similar. A tightly coiled hair of larger diameter conceals scalp more effectively than a fine, straight one.
There is an important flip side. In populations where pattern loss is less common, other causes of temple recession are proportionally more significant. Traction alopecia from braiding, locs and extensions is a leading cause of frontotemporal thinning in Black women and some men, and central centrifugal cicatricial alopecia, a scarring hair loss beginning at the crown, is also more frequent. These are conditions where early recognition changes the outcome, because stopping the traction or treating the inflammation early can preserve follicles that would otherwise be lost permanently.
The useful conclusion is not a ranking. It is that your relatives tell you more than your ancestry does, and that a clinician should consider the full range of causes rather than assume pattern loss.
What changed recently in how receding hairline is treated
The two medicines at the center of hair-loss care are not new. Topical minoxidil, first developed as a blood pressure drug, was approved by the FDA for male pattern hair loss in 1988. Oral finasteride, which blocks 5-alpha reductase and so lowers DHT, was approved for hair loss in 1997. As of mid-2025, these remain the only two medicines the FDA has approved specifically for androgenetic alopecia, a point both Mayo Clinic and MedlinePlus make in their current patient guidance.
What has shifted is practice around them. Over the past several years, dermatologists have increasingly prescribed minoxidil as an oral tablet for pattern hair loss. This use is off-label, meaning the medicine is approved for a different purpose and the prescriber takes responsibility for using it outside the label. Interest surged after mainstream press coverage in 2022 and has continued on social media since. The supporting evidence consists mainly of observational series and a small number of randomised trials; a prescribing clinician weighs that evidence against blood pressure and heart considerations for each patient.
Topical finasteride formulations received marketing approval in several European countries from 2022 onward, but as of mid-2025 no topical finasteride product is FDA-approved in the United States; what circulates there comes from compounding, which is outside the scope of this article and not something to source independently. Dutasteride, a related 5-alpha reductase inhibitor, is approved for hair loss in Japan and South Korea but not in the United States or the United Kingdom, where any use for hair is off-label.
Device and procedure trends have moved too. Low-level laser devices hold FDA clearance, a lower regulatory bar than approval, and platelet-rich plasma injections have become widely offered despite inconsistent trial results. Hair transplantation has grown as a travel industry, which brings its own cautions discussed later. The NHS continues to classify pattern hair loss treatment as largely outside routine funded care, a position unchanged in its current guidance.
What the evidence actually says, graded by strength
Grading matters because a dramatic before-and-after photo and a randomised controlled trial sit at opposite ends of the reliability spectrum. Here is where each major option stands.
Strongest evidence: topical minoxidil and oral finasteride. Both have multiple large randomised, placebo-controlled trials over a year or more. Across those trials a majority of men using either medicine stopped losing hair, and a meaningful minority gained measurable density, with the crown responding more reliably than the frontal hairline. Benefit depends on continued use; shedding resumes within months of stopping. Mayo Clinic and MedlinePlus both describe finasteride’s sexual side effects as uncommon and usually reversible, and note that it is not for use by women who are or may become pregnant.
Moderate evidence: oral minoxidil, dutasteride and combination use. Oral minoxidil for hair loss rests on observational cohorts and a limited number of trials, which consistently show benefit but with less long-term safety data in this population. Dutasteride has randomised trials showing at least comparable effect to finasteride, but with fewer long-term participants. Using minoxidil with a 5-alpha reductase inhibitor appears additive in trials, though the data are smaller than for either alone.
Modest or mixed evidence: low-level laser therapy and platelet-rich plasma. Several randomised trials of laser combs and caps show small increases in hair count against sham devices; study quality varies and effect sizes are modest. Platelet-rich plasma trials conflict, with differences in preparation and injection schedules making comparison hard.
Weak or no evidence: most supplements, caffeine shampoos, scalp massage, derma-rolling alone, pumpkin seed oil, rosemary oil. Where trials exist they are small, short and often unblinded. Biotin helps only people with a true deficiency, which is rare.
Hair transplantation sits in its own category: a surgical procedure with decades of clinical experience and strong technical evidence that transplanted follicles survive, but with no placebo comparator, and with outcomes that depend heavily on surgeon skill and on medicines to protect surrounding native hair.
Can a receding hairline grow back?
Partly, sometimes, and only within limits set by biology. The crucial distinction is between a follicle that has miniaturized and one that has disappeared. A miniaturized follicle is still alive and still cycling; it is simply making a hair too fine to count. Minoxidil and finasteride act on these follicles, lengthening the growth phase and allowing thicker hairs to return. That is why trial participants gain density mainly in zones that look thin rather than bald, and why a receding temple that still carries visible fine hairs has a better outlook than one that is smooth and shiny.
Once a follicle has been dormant long enough, it can be replaced by fibrous tissue and no medicine currently available will bring it back. Nobody can say exactly how long that takes; it varies between people and between regions of the scalp, and the frontal hairline tends to reach that point sooner than the crown. In practice, dermatologists often describe medicines as more effective at holding ground than at reclaiming it, and most trial data support that framing.
Realistic expectations look something like this. At Norwood 2 to 3, treatment commonly slows or halts recession and can soften the corners. At Norwood 4 and beyond, medicines protect the remaining hair and may thicken the crown, while meaningful restoration of the frontal hairline usually requires transplantation.
Hair that has been lost to a reversible cause behaves differently. Telogen effluvium after illness or iron deficiency typically regrows fully within six to twelve months once the trigger is addressed. Early traction alopecia often recovers when the pulling stops. Scarring alopecias do not regrow, which is the single strongest argument for seeing a clinician early rather than experimenting for a year.
Options at Norwood 1 to 2: watch, document and decide
At these stages the most valuable intervention costs nothing: standardized photographs. Take them in the same room, under the same lighting, with hair combed back and damp, from the front and from a 45-degree angle on each side. Repeat every three to six months. Many Norwood 2 hairlines are simply mature hairlines that have finished moving, and the photos will show that.
If the pictures show continued recession, or if you have close relatives who thinned early, this is the stage at which medicines have their best chance, because the follicles at the retreating edge are still mostly miniaturized rather than gone. Topical minoxidil is available without a prescription in the United States and the United Kingdom; finasteride requires a prescription. Both are used indefinitely to maintain effect, and both take at least four to six months to show change, often with a temporary increase in shedding during the first weeks as follicles reset their cycles. A clinician can explain which, if either, fits your situation and health history, and that conversation is worth having before starting.
Styling at this stage is underrated. A slightly longer, textured front with a side part reads as deliberate; a hard, slicked-back line draws the eye to the exact corners you are worried about. Avoid prolonged tension on the frontal hairs from tight caps or hair ties, which can add traction loss to pattern loss.
What not to do matters as much. Do not start a hair transplant at Norwood 2. Reputable surgeons rarely operate on young men with early recession, because the future shape of the loss is unknown and transplanted hairs may end up as an island in front of a receding native hairline.
Options at Norwood 3 to 4: the stage where decisions carry weight
Norwood 3 is the first stage dermatologists formally classify as balding, and it is also the stage at which most men first seek help. By now the temple recession is deep and, in the 3 vertex and 4 patterns, the crown has begun to thin as well. The follicles here are a mix: some fully miniaturized, some gone, and many in between. That mix explains why results from medicines become more variable and why clinicians often raise combination treatment.
Randomised trial evidence supports using minoxidil and finasteride together for a larger effect than either alone, and this combination is the standard medical approach at these stages. For men who cannot or prefer not to take finasteride, a clinician may discuss alternatives, including off-label options whose evidence we graded earlier. Any such decision belongs to the prescribing clinician, who will consider heart health, blood pressure, mood history, plans for children and other medicines.
Transplantation enters the conversation at Norwood 3 and 4, with two conditions. First, the loss should be stable or medically controlled, ideally documented for a year or more. Second, the plan must account for future recession: a surgeon will usually design a slightly higher, more conservative hairline than the patient’s teenage one, so that it still looks natural if the surrounding hair continues to retreat. The donor area at the back of the scalp holds a finite number of follicles, typically enough for one to three sessions over a lifetime, and spending them on a 25-year-old’s temples can leave nothing for the crown at 40.
Camouflage products, including keratin fibres and tinted scalp powders, have no effect on follicles but are entirely reasonable and widely used at these stages. They work best where there is still some hair to cling to, which makes Norwood 3 to 4 their natural territory.
Options at Norwood 5 to 7: realistic goals and what surgery can and cannot do
At the advanced stages, the bridge between frontal and crown loss has narrowed or disappeared, and the question changes from “can I stop this” to “what do I want the result to look like, and what resources do I have.” Medicines still have a role, mainly in protecting the horseshoe of remaining hair and any surviving mid-scalp density, but they rarely produce visible regrowth across a bald expanse.
Hair transplantation at Norwood 5 to 7 is a planning exercise in scarcity. Two techniques dominate. Follicular unit excision, often shortened to FUE, removes individual follicle groups from the back and sides and places them in the thinning zones. Follicular unit transplantation, or FUT, removes a strip of scalp and dissects it into grafts, leaving a linear scar. Both move hair rather than create it. A surgeon with a Norwood 6 patient and an average donor supply cannot restore full coverage; a good result is typically a framing hairline and moderate density across the front half, with the crown accepted or lightly covered.
The travel-for-surgery trend deserves a plain word. Outcomes depend on the surgeon’s skill, the time spent per graft and the aftercare, and some high-volume settings have been reported to over-harvest donor areas or to delegate surgery to unlicensed staff. Ask who will perform the procedure, how many grafts they consider safe to take, and what happens if there is a complication after you return home.
For men who prefer not to operate, scalp micropigmentation tattoos tiny dots that mimic a closely shaved head, and a fully shaved style remains the choice many find simplest. None of these is a lesser option. The evidence on quality of life suggests that the best outcome is the one a person stops thinking about.
Receding hairline in women: when the pattern is not the usual pattern
Women develop pattern hair loss too, and after menopause it is common, but it rarely eats into the hairline the way it does in men. Female pattern hair loss typically shows as a widening parting and a thinner ponytail while the frontal edge holds. So when a woman notices her temples or front hairline moving back, clinicians look harder for other explanations.
Frontal fibrosing alopecia is the condition that most concerns dermatologists in this setting. It mostly affects postmenopausal women, although younger women and occasionally men are affected. The hairline recedes in a smooth band, the skin there often looks pale and slightly shiny, the eyebrows thin or disappear, and some women notice itching or small bumps along the edge. This is a scarring alopecia, meaning inflammation destroys the follicle permanently, so the aim of treatment is to halt progression rather than regrow lost hair. It is reasonably common, its cause is not fully understood, and it warrants prompt dermatology assessment.
Traction alopecia is the other leading cause of temple recession in women. Years of tight ponytails, braids, weaves, extensions or heavy locs put chronic pull on the frontal and temporal hairs. Early on, the hairs break and the follicles recover once the tension is released. Over long periods the follicles can scar. Fine short hairs along the very front, sometimes called a fringe sign, suggest traction rather than frontal fibrosing alopecia.
Treatment options differ sharply from the male picture. Minoxidil is the only medicine approved for female pattern hair loss in the United States. Finasteride carries a strict warning against use in pregnancy and is prescribed to women only in selected postmenopausal cases, off-label, by specialists. Blood tests for iron, thyroid function and, where indicated, androgens are a standard part of the workup, because treatable contributors are more common in women than in men.
Common myths about receding hairline, corrected
“Baldness comes from your mother’s side.” One gene on the X chromosome contributes, but dozens on other chromosomes do too. Your father’s hairline is as informative as your maternal grandfather’s.
“Wearing hats causes a receding hairline.” A normal hat does not. Only sustained, tight tension on the frontal hairs, from very tight caps worn for hours daily over years, could contribute to traction loss, and even then the pattern differs from androgenetic recession.
“Shampooing often makes you lose hair.” Washing removes hairs that had already finished their cycle and were about to fall. Losing 50 to 100 hairs a day is normal, and seeing them in the drain is not evidence of a problem.
“High testosterone means you will go bald.” Men who bald do not have higher testosterone on average. Their follicles are more sensitive to DHT. Deliberately lowering testosterone would not help, and raising it with anabolic steroids can accelerate loss in the predisposed.
“Rosemary oil works as well as minoxidil.” This claim traces to a single small, unblinded trial. It has not been replicated in a well-designed study, and the evidence does not support equivalence.
“If you start finasteride you must take it forever or you will lose everything.” Stopping any hair-loss medicine returns you to the trajectory you were on; it does not cause extra loss beyond what the condition would have produced. The hair maintained by the medicine is gradually lost over the following months.
“A transplant gives you a permanent full head of hair.” Transplanted hairs usually persist, but surrounding native hair keeps thinning unless protected, which is why most surgeons recommend continuing medicines after surgery.
“Scalp massage regrows hair.” It feels pleasant and may improve blood flow briefly. Trial evidence for regrowth is minimal.
When to see a doctor about a receding hairline
Most pattern hair loss is not a medical emergency, and plenty of people choose simply to observe it. There are, however, clear situations in which an appointment with a primary care clinician or dermatologist should come before any product purchase.
Book an appointment promptly if you notice any of these red flags: hair loss that is sudden or occurs in patches rather than a gradual pattern; redness, scaling, pain, itching, pustules or a shiny, pale band of skin along the hairline, which can indicate a scarring or inflammatory condition; thinning of the eyebrows or eyelashes alongside hairline recession; hair loss accompanied by fatigue, weight change, feeling cold or hot, heavy periods or other symptoms that could point to thyroid disease or iron deficiency; recession in a woman, particularly after menopause, where frontal fibrosing alopecia needs to be considered; hair loss beginning soon after a new medicine; or loss that is affecting your mood, sleep or willingness to socialize.
Seek advice before starting or continuing finasteride if you develop persistent changes in sexual function, breast tenderness or enlarged male breast tissue (gynecomastia), or low mood. Anyone taking minoxidil, particularly as an oral medicine, should report dizziness, a racing heartbeat, ankle swelling, chest pain or shortness of breath. Women who are pregnant, planning pregnancy or breastfeeding should not handle finasteride and should discuss any hair treatment with their clinician.
What a good consultation includes: a history of onset and family patterns, examination with a dermatoscope, a gentle pull test and, where indicated, blood tests for ferritin, thyroid function, vitamin D and androgens. A scalp biopsy is reserved for suspected scarring alopecia. Every decision about starting, combining, changing or stopping a medicine, and about whether surgery is appropriate, rests with the clinician who has examined you. Do not stop a prescribed medicine on the strength of a social media post; raise the concern with the prescriber instead.
Frequently asked questions
Can a receding hairline grow back on its own?
Androgenetic recession does not reverse without treatment, because the follicles keep shrinking under the influence of DHT. Hair lost to a reversible cause, such as telogen effluvium after illness, iron deficiency or early traction from tight hairstyles, often regrows fully within six to twelve months once the trigger is removed. A dermatologist can tell the two apart with a dermatoscope and, if needed, blood tests.
What is frontal thinning, and is it the same as a receding hairline?
Frontal thinning is reduced hair density across the front third of the scalp, which can happen while the hairline itself stays put. A receding hairline is the front edge physically moving backward, usually fastest at the temples. The two often occur together in male pattern hair loss, but frontal thinning alone, especially when evenly spread, can also signal diffuse shedding from a medical cause that deserves checking.
Why does hair thinning at temples happen before the rest of the scalp?
Follicles in the frontotemporal corners are among the most sensitive to dihydrotestosterone, the hormone that drives pattern hair loss. They miniaturize earlier than follicles at the center of the hairline, producing the classic notches with a surviving central tuft. Follicles at the sides and back largely ignore DHT, which is why they persist and can be used as donor hair in transplantation.
Is a mature hairline the same as Norwood 2?
Not quite, although they can look similar in a photograph. A mature hairline is a normal developmental change in which the whole front edge rises slightly and the corners square off, then stops moving. Norwood 2 describes mild but genuine temple recession that may progress. The deciding factor is time: if standardized photos taken a year apart show further retreat, the hairline is receding rather than maturing.
Why is Gen Z balding so fast?
There is no robust evidence that people born after 1997 are losing hair earlier than previous generations. Pattern hair loss has always begun in the teens or twenties for a sizeable minority of men. What has changed is visibility from front-facing cameras, ring lights and constant comparison online. Crash diets, iron deficiency, tight styling and steroid use can add real but separate causes of thinning in young people.
Which race is the least bald?
Observational studies suggest male pattern hair loss is most common and starts earliest in men of European ancestry, is somewhat less frequent in East Asian men and lower again in some African and Indigenous populations. These are group tendencies from modest-quality data, not individual predictions. Family history is a far better guide, and in populations with less pattern loss, traction alopecia and scarring conditions account for a larger share of temple recession.
Does finasteride or minoxidil work better for a receding hairline?
Both have strong randomised trial evidence, and head-to-head data suggest finasteride produces somewhat greater regrowth on average, with the crown responding better than the frontal hairline for either medicine. Trials also show the two work additively when combined. They differ in how they act and in their side-effect profiles, so the choice depends on health history and preferences, and it belongs to the prescribing clinician.
At what Norwood stage should someone consider a hair transplant?
Most reputable surgeons prefer to operate once loss is stable or medically controlled, usually from Norwood 3 onward and rarely before the late twenties. Transplanting too early risks an island of grafted hair in front of a hairline that keeps retreating, and it spends finite donor follicles that may be needed later. A conservative, slightly higher hairline design and continued medical treatment of surrounding hair are standard recommendations.
Can women get a receding hairline?
Yes, although female pattern hair loss more often widens the parting while sparing the front edge. When a woman’s hairline does recede, particularly after menopause or with thinning eyebrows, clinicians consider frontal fibrosing alopecia, a scarring condition that needs early assessment because lost follicles do not recover. Traction alopecia from tight hairstyles is the other common cause and improves if the tension is stopped early.
Do hats, stress or frequent washing cause a receding hairline?
Ordinary hats do not; only years of sustained tight tension on the frontal hairs can contribute to traction loss. Severe stress can trigger diffuse shedding two to three months later but does not cause the M-shaped recession of pattern hair loss. Washing simply removes hairs that had already completed their cycle; shedding 50 to 100 hairs a day is normal and not a sign of disease.
References
- MedlinePlus: Male pattern baldness
- MedlinePlus: Minoxidil topical
- MedlinePlus: Finasteride
- NHS: Hair loss
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Hair Loss Concealers and Fibres: What They Do Well, and What They Cannot
Hair loss concealers, keratin fibers, tinted powders, sprays, and cream sticks, genuinely improve the appearance of thinning hair by reducing the color contrast between…

Traction Alopecia: How Tight Hairstyles Cause Hair Loss and Whether It Grows Back
Traction alopecia is hair loss caused by repeated pulling on the hair roots from tight braids, buns, ponytails, extensions, weaves or locs. It usually…

Keratin Treatments and Hair Botox: What the Salon Treatments Do and the Formaldehyde Question
A keratin treatment coats hair with a protein-rich solution and seals it with a flat iron to reduce frizz for roughly 2–5 months; so-called…

How to Stop Hair Loss: The Treatments With Evidence, Ranked
The best-supported ways to stop or slow hair loss depend on its cause. For male and female pattern hair loss, topical minoxidil and, in…

Oral Minoxidil: Why Dermatologists Now Prescribe the Blood-Pressure Pill for Hair
Oral minoxidil is a prescription tablet approved to treat severe high blood pressure that dermatologists increasingly prescribe off-label, in amounts far below the blood-pressure…

Scalp Psoriasis vs Dandruff: How to Tell Them Apart and Treat Each
Scalp psoriasis is an immune-driven condition that produces thick, sharply bordered, silvery plaques that often extend past the hairline, while dandruff is a mild,…