

How a Baclofen Pump Is Implanted: The Abdominal Pocket, the Spinal Catheter and the Programmer

Key Takeaways
- A baclofen pump is implanted in a procedure that typically takes one to two hours, followed by a hospital stay of a few days, according to Cleveland Clinic.
- The catheter tip is deliberately placed at a spinal level matched to whether the legs alone or the trunk and arms also need treatment, because the medicine concentrates near the tip.
- The pump senses nothing; a handheld programmer held over the skin sets a fixed flow pattern, and changes are made gradually over weeks at clinic visits.
- Refills are done in clinic with a needle through the skin into a self-sealing port, roughly every one to six months depending on reservoir size and flow rate.
- The pump battery is sealed and lasts several years, typically five to seven, after which the pump is replaced while the spinal catheter is often left in place.
- Abrupt interruption of intrathecal baclofen can cause a withdrawal reaction with rebound spasticity, high fever and confusion that MedlinePlus describes as potentially life-threatening.
A baclofen pump is implanted under general or spinal anesthesia in a procedure that typically takes one to two hours. A surgeon places a thin catheter into the fluid-filled space around the spinal cord through the lower back, tunnels it under the skin to the abdomen, and connects it to a small pump set in a pocket beneath the skin. A handheld programmer then adjusts the medicine flow.
The physical therapist had stopped mid-stretch and looked up. Her patient, a young man whose legs had locked into a scissor pattern since a car crash three years earlier, had just asked the question his family had been circling for months: what would it actually be like to have a pump put inside him? Not the brochure version. The real one.
It is a fair thing to want to know. Anyone told that oral muscle relaxants are no longer doing enough, or that the drowsiness they cause has become its own disability, eventually hears about intrathecal baclofen. The name sounds forbidding. The device is roughly the size and shape of a hockey puck. The surgery involves three separate pieces of engineering that most people have never had explained in order.
So this is that explanation, step by step: how is a baclofen pump implanted, what sits where, and what happens in the weeks that follow, with the evidence stated plainly and the decisions left where they belong, with the treating team.
How is a baclofen pump implanted, and what actually happens in the operating room?
Strip away the vocabulary and the operation is three tasks done in sequence. First, a surgeon places a catheter, a soft plastic tube about the width of a strand of spaghetti, into the intrathecal space, which is the fluid-filled channel that surrounds the spinal cord inside the spinal canal. Second, the surgeon creates a pocket under the skin of the abdomen and settles a battery-powered pump into it. Third, the two are joined by tunneling the catheter under the skin around the flank so that no tube is visible on the outside.
The patient is usually asleep under general anesthesia, although some centers use spinal or regional anesthesia depending on the person and the surgeon. Cleveland Clinic describes the operation as typically lasting one to two hours, with the person lying on their side so both the lower back and the abdomen can be reached without repositioning.
Why go to such lengths? Baclofen works by calming overactive nerve signals in the spinal cord that cause muscles to stay tight and jerk involuntarily, a problem doctors call spasticity. Swallowed as a tablet, most of the medicine circulates through the whole body and only a small share crosses into the spinal fluid where it acts. Delivering it directly into that fluid means the spinal cord sees the medicine at a concentration that tablets cannot safely reach, while the brain and the rest of the body see far less. The National Institute of Neurological Disorders and Stroke lists intrathecal baclofen among the standard options for spasticity that has not responded adequately to other treatments.
The pump itself holds a reservoir of medicine and a tiny motor that pushes it down the catheter at a rate set from outside the body. Nothing about it is automatic in the sense of sensing the muscles; it simply does what it was last told to do.
Who is a baclofen pump usually for, and who is usually asked to wait?
The pump is a treatment for spasticity, not for weakness, pain on its own, or any single diagnosis. It tends to be considered when muscle tightness is severe, affects large regions of the body such as both legs or one whole side, and either is not controlled by oral muscle relaxants or is controlled only at the cost of side effects like heavy sedation. The NHS lists it as an option for cerebral palsy when tightness affects the legs and trunk broadly, and Mayo Clinic describes it as an option for cerebral palsy when oral medicines have not worked well enough. The underlying causes most often involved are cerebral palsy, multiple sclerosis, spinal cord injury, traumatic brain injury and stroke.

Candidacy is rarely decided by the surgeon alone. A physiatrist, which is a doctor who specializes in rehabilitation medicine, a neurologist, physical and occupational therapists, and often a nurse coordinator weigh in. They ask a question that surprises many families: is some of this stiffness useful? A person who relies on leg tone to stand for a transfer from wheelchair to bed can lose that ability if tone drops too far. Goals are written down beforehand, whether that is easier positioning, less pain, better sleep, easier hygiene or improved walking.
People are commonly asked to wait, or are not offered the pump, when there is an active infection anywhere in the body, when the skin or soft tissue over the abdomen is too thin to cover the device safely, when a child is still too small for the pump to fit without pressing on the ribs or hip, when a bleeding disorder is not yet controlled, or when the person and family cannot realistically commit to the lifelong schedule of refill visits. None of these is a judgment; each is a safety question the team is obliged to answer first.
The screening trial: the test that comes before the surgery
Almost everyone offered a pump goes through a trial first, and it is worth understanding because it is a small procedure of its own. A clinician performs a lumbar puncture, which is a needle placed between two bones of the lower spine to reach the intrathecal space, and injects a single test amount of baclofen. The needle comes out, and the person is then watched, usually in a hospital or day unit, as the medicine takes effect over the following hours.
Therapists examine muscle tone at set intervals using standardized scales, and the family is asked to notice things that scales miss: did the ankles relax enough to put shoes on, did the fists open, did transfers feel different. Cleveland Clinic describes this trial step as the way teams confirm that spasticity responds to baclofen delivered this way before committing to surgery. Some centers place a temporary catheter for a trial lasting a few days rather than a single injection; the choice depends on the person and local practice.
The trial answers two questions. Does the muscle tightness ease when baclofen reaches the spinal fluid? And does easing it help, or does it uncover weakness that the stiffness had been masking? A response is expected in most people whose spasticity is genuinely spinal in origin, but the trial is not a formality. Occasionally it shows that loosening the muscles makes standing harder, and the team may recommend against the pump or adjust the goals.
Side effects during the trial mirror those of the therapy: drowsiness, headache from the lumbar puncture, nausea or a temporary drop in blood pressure. The person is monitored until these settle. The trial does not predict exactly what setting the pump will eventually need; it simply confirms that the approach is worth taking.
The abdominal pocket: where the pump sits and why it goes there
Once the person is positioned and anesthetized, the surgeon marks a spot on the lower abdomen, usually on one side, below the rib cage and above the belt line. The location is not arbitrary. It needs to be somewhere with enough fat and skin to cushion the device, away from the hip bone so it does not rub when the person sits or bends, and reachable with a needle from the front so that future refills are straightforward. For a person who spends most of the day in a wheelchair, the surgeon may also check that the pump will not sit under a lap belt or a brace edge.
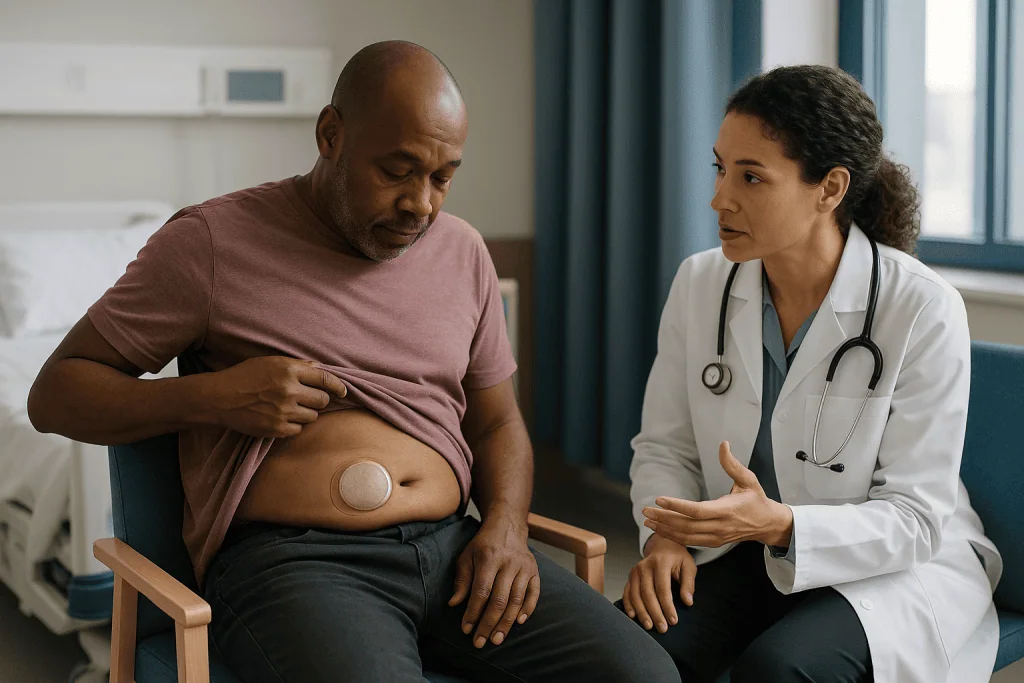
An incision of a few inches is made and a pocket is fashioned between the skin and the muscle wall of the abdomen, roughly the size of the pump. The pump is a flat metal disc; Cleveland Clinic compares its size to a hockey puck. It is slid in, oriented so the refill port, a self-sealing rubber center that a needle can pass through, faces outward toward the skin, and it is often stitched to the underlying tissue so it cannot flip over or migrate. A pump that turns face-down would make refills impossible without another operation, which is why surgeons take care with this step.
In thinner adults and in children, the surgeon may place the pump partly beneath the muscle layer rather than just under the skin, trading a slightly more involved operation for better padding and less risk of the device pressing through. The choice belongs to the surgical team and depends on body build.
After surgery the pump is visible as a raised, rounded contour, more obvious in slim people. Over weeks the swelling around it settles and most people describe the outline as something they stop noticing rather than something that disappears.
The spinal catheter: how it is threaded and anchored
The catheter is the part of the system most likely to cause problems later, so surgeons spend disproportionate care on it. With the person lying on their side, a needle is introduced between two bones of the lower spine, in the lumbar region below the level where the spinal cord itself ends, into the sac of spinal fluid. The catheter is fed through this needle and, under X-ray guidance, advanced upward inside the fluid until its tip rests at a level chosen in advance.
That level matters. Baclofen concentrates near the catheter tip and thins out with distance, so a tip left low in the spine mainly affects the legs, while a tip advanced higher toward the mid-back delivers more effect to the trunk and arms. For someone whose arms and legs are all involved, the surgeon may aim higher; for legs alone, lower. This is a judgment the team makes based on the pattern of spasticity documented before surgery.
The needle is withdrawn over the catheter, and the catheter is then anchored to the tough tissue over the spine with a small clip or sutures so that bending and twisting do not pull it out over the years. A second small incision in the back is needed for this. From here the surgeon uses a blunt tunneling rod to pass the catheter under the skin, around the side of the body, into the abdominal pocket, where it is connected to the pump and the connection is secured.
Both incisions are closed with stitches or surgical glue and dressed. Before waking the person, many surgeons check with X-ray that the catheter follows a smooth path with no kinks, since a kinked catheter would slow or stop the medicine.
The programmer: how the pump is told what to do
People often imagine the pump as a smart device that senses stiffness and responds. It does not. It is a precise but obedient machine, and the intelligence lives in a separate handheld unit called the programmer, held over the skin during clinic visits. The programmer communicates with the pump through the skin using a short-range wireless signal, reads out how much medicine remains, the current flow settings, the battery status and any alarms, and lets the clinician change the rate at which the motor pushes medicine down the catheter.
Programming happens for the first time in the operating room or recovery area, when the pump is set to a cautious starting rate. Over the following weeks it is adjusted gradually at clinic visits, guided by how the muscles feel to the therapist, what the person and family report, and whether side effects such as sleepiness or weakness appear. The pump can be set to deliver a steady flow around the clock or a pattern that changes across the day, for example more overnight for someone whose spasms disturb sleep and less in the morning when they need tone for transfers. Adjustments are tiny and deliberate; this is not a dial anyone turns quickly.
Some systems also include a small patient-controlled device that can trigger an extra pulse within limits the clinician has locked in advance. Whether a person is given one, and what limits are set, is entirely the prescribing clinician’s decision.
Every change is logged, and the programmer calculates when the reservoir will run low, which is how the refill date is set. The device sounds an alarm when the reservoir approaches empty or the battery approaches its end, but teams do not rely on the alarm; the calendar comes first.
Who inserts the baclofen pump, and how long is surgery for a baclofen pump?
The implantation is performed by a surgeon, in most cases a neurosurgeon, and in some centers an orthopedic spine surgeon or a pain specialist with training in implanted drug-delivery systems. Anesthesia is managed by an anesthesiologist, and a device specialist or nurse familiar with the pump is usually present to program it before the person wakes. The referring physiatrist or neurologist who ran the trial commonly remains the person who manages settings and refills afterward, so families often find they have two doctors for one device: one who put it in and one who keeps it running.
Cleveland Clinic gives one to two hours as the typical operating time. The variable parts are how easily the catheter passes into the spinal fluid, which can be harder in people with previous spine surgery, scoliosis or metal rods, and how much tissue needs to be prepared for the pocket. Add time before for anesthesia and after for recovery, and the family should expect the whole day to be spoken for.
Most people stay in hospital afterward. Cleveland Clinic describes a stay of a few days, during which the team watches for headache related to spinal fluid leakage, checks that the incisions are dry, begins gentle programming and involves the therapists early. Some centers keep the person flat or with the head only slightly raised for the first day to reduce the chance of spinal headache; others allow sitting up sooner. Practice varies, and the surgeon’s instructions apply.
Before discharge, the person and caregivers are usually shown the alarm sounds, given a card identifying the implant, and told the date of the first refill and programming visit. That card matters for airport security, emergency departments and MRI scanning, all of which are discussed later.
Baclofen pump surgery recovery: what the first days and weeks usually look like
The first sensation most people describe is a sore, bruised feeling over the abdomen and an ache in the lower back at the catheter site. Both are expected. Pain relief is given as the surgical team decides, and moving in bed is encouraged early to reduce the risk of blood clots, with the caveat that twisting and bending at the waist are limited for several weeks so the catheter and pump anchors can heal into place.
Headache on sitting up, easing when lying down, is the signature of a small spinal fluid leak around the catheter entry point. It is common in the first days and usually settles with fluids, lying flat and time; a persistent one is reported to the team. Swelling around the pump is normal and may feel fluid-filled; a rapidly enlarging, tense or hot swelling is not, and should prompt a call.
In the first two to four weeks the team focuses on wound healing. Dressings are usually kept dry, showering is permitted when the surgeon says so, and soaking in a bath or pool waits until incisions have closed fully. Lifting, contact sports and deep bending are restricted. Wheelchair users are usually advised to check that seating and belts do not press on the pump.
Programming visits begin within the first weeks and continue at intervals as the rate is edged upward. Therapists reassess tone and often adjust braces and stretching programs, because muscles that were tight for years behave differently once released. Families sometimes notice the change before the clinic does: a hand that opens, legs that fit into a car more easily, a night without spasms. Others see little for several weeks. Both are within the normal range; the pump is set slowly on purpose.
How is a baclofen pump filled? The refill visit explained
The reservoir inside the pump holds a finite amount of medicine, so it has to be topped up for as long as the pump is used. This is done in an outpatient clinic, not an operating room, by a trained clinician, usually the physiatrist, neurologist or a specialist nurse.
The visit follows a set routine. The programmer is held over the pump to read how much medicine should remain and to confirm the settings. The skin over the pump is cleaned with antiseptic. The clinician locates the refill port by feel, often with a plastic template that outlines the pump and marks the center, and sometimes with ultrasound in people where the pump sits deeper. A fine needle is passed through the skin and through the self-sealing rubber center of the port. The remaining medicine is drawn out first and measured against what the programmer predicted; a large mismatch is a warning that the catheter or pump may not be delivering properly. Fresh medicine is then injected, the needle is removed, the pump is reprogrammed with the new volume and the next refill date is set.
Most people describe the sensation as a brief sting similar to a blood draw. The whole appointment often takes less than half an hour. Cleveland Clinic describes refills as occurring roughly every one to six months depending on the reservoir size and the flow rate, so a person on a low rate may visit far less often than someone on a higher one.
The refill schedule is not optional. Missing it risks the reservoir running dry, and abrupt interruption of intrathecal baclofen can trigger a withdrawal reaction that MedlinePlus lists among the serious risks of the medicine. Teams build in a safety margin, but the calendar entry is the person’s single most important responsibility.
Are baclofen pumps permanent? Batteries, replacements and removal
The honest answer is that the therapy is intended to be long term but no single pump is permanent. The pump contains a sealed battery that cannot be recharged through the skin. Cleveland Clinic describes the battery as lasting several years, typically in the range of five to seven, after which the pump must be replaced. Replacement is a smaller operation than the original: the surgeon reopens the abdominal pocket, disconnects the old pump from the catheter, connects a new pump and closes. The spinal catheter is usually left in place if it is working well, which spares the person a second spine incision.
The catheter has no battery but can fail in its own ways: a kink, a crack, a tip that has drifted, or a slow blockage. When that happens, part or all of it is replaced, sometimes together with a pump change and sometimes separately. Over a lifetime of therapy, a person may go through several pumps and one or more catheters.
The system can also be removed entirely. Reasons include infection that cannot be cleared, a change in the underlying condition, a decision that the benefit no longer justifies the visits, or a wish to stop. Removal is not done abruptly. Because sudden loss of intrathecal baclofen can cause withdrawal, the team lowers the rate gradually and may reintroduce oral medicines before the device comes out.
Children are a special case. A pump placed in a small child is sized for that body, and growth may eventually require a larger pump or a repositioned catheter. Families of children are usually told from the start that surgery will recur at intervals, so it does not arrive as a surprise.
Baclofen pump complications and risks, in plain terms
Every implanted device trades one set of problems for another, and it serves no one to soften this. The complications fall into three groups.
Surgical and mechanical problems come first. Cleveland Clinic lists infection of the pocket or the catheter track, spinal fluid leak with headache, bleeding, and catheter kinking, disconnection or migration among recognized complications. Infection around an implant is treated seriously because bacteria can adhere to the device; sometimes antibiotics are enough, and sometimes the system has to come out. Skin over the pump can thin and break down in very slim people.
Medicine-related effects come second. Too much baclofen reaching the spinal cord produces drowsiness, weakness, nausea, low blood pressure and, at the extreme, slowed breathing and loss of consciousness. Too little, whether from an empty reservoir, a failed catheter or a programming error, produces withdrawal: a rebound of spasticity worse than before, itching, high fever, confusion and agitation. MedlinePlus describes abrupt withdrawal as potentially life-threatening, which is why it is taught as an emergency rather than an inconvenience.
Functional surprises come third. Loosening muscles can reveal weakness, alter balance, change bladder patterns or make previously useful stiffness disappear. These are addressed by programming and therapy, and are the reason the goals conversation before surgery matters so much.
What the evidence does not support is a single tidy percentage for how often any of this happens. Rates differ between adults and children, between conditions and between centers, and the mainstream patient sources cited here deliberately avoid quoting one. The right move is to ask the surgeon for their own program’s experience with infection and catheter problems, and to weigh that against the burden of spasticity as it currently stands.
How a baclofen pump compares with other spasticity treatments
The pump sits within a spectrum of options, and most people will have tried several before reaching it. The National Institute of Neurological Disorders and Stroke groups spasticity treatments into physical approaches, oral medicines, targeted injections, intrathecal delivery and, less often, surgery on nerves or tendons. Stretching, splinting and positioning remain the foundation at every stage and continue alongside whatever else is chosen.
| Approach | Where it acts | Typical pattern of use | Main trade-offs |
|---|---|---|---|
| Stretching, bracing, positioning | Muscles and joints | Daily, lifelong, all severities | Time-intensive; alone may not control severe tone |
| Oral muscle relaxants (baclofen, tizanidine, others) | Whole body via bloodstream | Mild to moderate, widespread tone | Drowsiness, weakness; limited by side effects |
| Botulinum toxin injections | Individual muscles injected | Focal tone in a few muscles; repeated every few months | Wears off; impractical for many large muscle groups |
| Intrathecal baclofen pump | Spinal cord via spinal fluid | Severe, widespread tone in legs, trunk or both sides | Surgery, implant risks, lifelong refills, withdrawal risk if interrupted |
| Selective dorsal rhizotomy | Sensory nerve rootlets at the spine | Chiefly children with cerebral palsy affecting the legs | Irreversible; intensive rehabilitation afterward |
| Orthopedic tendon or muscle surgery | Specific tendons or joints | Fixed contractures rather than dynamic tone | Corrects position, not the cause of tightness |
The table is descriptive, not a ranking. Mayo Clinic and the NHS both frame these as options selected by the care team according to which muscles are involved, how severe the tone is, the person’s goals and how earlier treatments were tolerated. Many people use more than one at once; a pump for the legs and trunk with occasional injections for a stubborn arm is a common combination. The decision about which rung to try next is always the treating team’s.
What people often get wrong about baclofen pumps
The pump fixes the underlying condition. It does not. It manages one symptom, spasticity, and leaves the cerebral palsy, multiple sclerosis or injury that caused it unchanged. Weakness, poor coordination and sensory loss are not addressed, and some people are disappointed when muscles that relax do not also become strong.
Once it is in, the hard part is over. In truth the operation is the shortest chapter. The longer work is the months of gradual programming, the changed therapy plan, and a refill calendar that continues for as long as the therapy does.
The pump releases medicine in response to spasms. It cannot sense anything. It delivers exactly the pattern last programmed, which is why a change in symptoms should prompt a call rather than a wait for the device to catch up.
If the pump alarms, it can simply wait until the next appointment. Alarms are designed with a safety margin, but an empty-reservoir or motor alarm is a same-day call. MedlinePlus is explicit that sudden interruption of baclofen can be dangerous.
MRI scans are off limits forever. Most current pumps can be scanned under specified conditions, but the magnet may pause the motor, and the pump usually needs to be checked with the programmer afterward. The implant card and a call to the pump team before any scan are what matter.
Airport scanners will damage it. Security screening is generally fine; the person should carry the implant card and may be offered a manual check.
Children outgrow the need for it. Some children with cerebral palsy do have their spasticity reassessed as they grow, and a few have the system removed, but growth more often means a pump replacement rather than the end of therapy. The NHS describes intrathecal baclofen as a longer-term option for children with widespread tone, not a temporary bridge.
Questions to ask your care team before a baclofen pump
A good consultation leaves room for the person and family to steer. These questions tend to produce the most useful answers, and none of them is out of bounds.
- What specific changes are we hoping the pump will bring for me, and how will we measure whether they happened?
- Is any of my current stiffness helping me stand, transfer or hold a position, and how will we protect that?
- What did my screening trial show, in your words, and were there any findings that give you pause?
- Who will perform the implantation, and who will manage programming and refills afterward? How do those two teams communicate?
- Where exactly will the pump sit on my body, and have you considered my wheelchair, braces or clothing?
- How high will the catheter tip be placed, and why that level for my pattern of spasticity?
- How long do you expect me to be in hospital, and what movement restrictions will apply in the first weeks?
- How often will I need refills at the start, and how might that change as settings are adjusted?
- What is your program’s own experience with infection and catheter problems, and how are they handled?
- What are the signs of too much medicine and of withdrawal, and whom do I call, day or night, if I notice them?
- How will MRI scans, dental work, other operations and travel be handled while the pump is in?
- When will the pump likely need replacing, and what does that operation involve?
- If we decide to stop, how is the system removed safely?
Writing the answers down during the visit, or asking whether a nurse coordinator can send them afterward, turns a stressful conversation into a reference the whole household can use. Teams generally welcome the questions; they signal a family that will keep its refill appointments.
When to call your doctor: red-flag signs after a baclofen pump
Two patterns need urgent attention, and both can begin subtly. The first is withdrawal, meaning the spinal cord is suddenly getting less baclofen than it was. The second is overdose, meaning it is getting more. Either can arise from a catheter problem, a programming error, a missed refill or, rarely, a pump fault. Anyone with a pump, and every caregiver, should know both lists.
Seek emergency care or call the pump team immediately for:
- Spasticity that returns or becomes worse than before the pump, especially if it comes on over hours rather than weeks
- High fever with confusion, agitation or hallucinations, or itching all over without a rash, which MedlinePlus lists among signs of baclofen withdrawal
- Unusual drowsiness that is hard to rouse from, slurred speech, floppy weakness, slow or shallow breathing, or fainting, which suggest too much medicine
- A pump alarm of any kind
- Redness, warmth, spreading swelling, pus or an opening at either incision, or fever after surgery
- A severe headache that does not ease when lying down, a stiff neck, or clear fluid leaking from the back incision
- New numbness, new weakness or loss of bladder or bowel control
Call during clinic hours, the same day, for a positional headache lasting beyond the first few days, a soft swelling over the pump that is growing, a noticeable change in tone in one part of the body, a pump that seems to have shifted or turned, or any planned MRI, surgery or long trip so the team can advise. Anyone attending an emergency department for any reason should show the implant card on arrival.
None of these signs means the pump has failed, but each is a reason the team needs to know now rather than at the next scheduled visit. The device is designed to be safe when supervised; the supervision is the part the person carries with them.
Frequently asked questions
How is a baclofen pump filled?
A trained clinician fills it in an outpatient clinic with a fine needle passed through the skin into a self-sealing port on the pump. The programmer first reads the expected remaining volume, the old medicine is drawn out and measured, fresh medicine is injected, and the pump is reprogrammed with the new date. Most people describe a brief sting similar to a blood draw.
Who inserts the baclofen pump?
A surgeon, most often a neurosurgeon, and in some centers a spine surgeon or pain specialist trained in implanted delivery systems. An anesthesiologist manages anesthesia and a device specialist programs the pump before the person wakes. Afterward, a physiatrist or neurologist usually takes over programming and refills, so people often have one doctor who implanted the device and another who maintains it.
How long is surgery for a baclofen pump?
Cleveland Clinic describes the operation as typically lasting one to two hours. Time varies with how easily the catheter enters the spinal fluid, which can be harder after previous spine surgery or with scoliosis, and how the abdominal pocket is prepared. Anesthesia and recovery add several hours, and a hospital stay of a few days usually follows.
Are baclofen pumps permanent?
The therapy is intended to be long term, but no single pump is permanent. The sealed battery lasts several years, typically five to seven, and the pump is then replaced in a smaller operation that often leaves the spinal catheter in place. The entire system can be removed if needed, but only after the rate is lowered gradually to avoid withdrawal.
What is baclofen pump surgery recovery like in the first weeks?
Expect soreness over the abdomen and lower back, possible headache on sitting up from a small spinal fluid leak, and restrictions on bending, twisting and lifting while the anchors heal. Incisions are kept dry until the surgeon clears showering. Programming visits begin within weeks and the rate is increased slowly, so changes in muscle tone may appear gradually rather than immediately.
What are the most common baclofen pump complications?
Cleveland Clinic lists infection at the pocket or catheter, spinal fluid leak with headache, bleeding, and catheter kinking, disconnection or migration. Medicine-related problems include drowsiness and weakness from too much baclofen, and rebound spasticity, fever and confusion from too little. Rates vary between conditions and centers, so ask your surgical team about their own experience.
How does an intrathecal baclofen pump differ from taking baclofen tablets?
Tablets deliver baclofen through the bloodstream to the whole body, and only a small share reaches the spinal fluid where it acts, so side effects like drowsiness limit how far the amount can be raised. The pump delivers it directly into the spinal fluid, reaching the spinal cord at levels tablets cannot safely achieve while the rest of the body sees far less.
Can you have an MRI with a baclofen pump?
Often yes, under conditions specified for that pump model, but the magnet may pause the motor and the pump usually needs to be checked with the programmer afterward. Always tell the imaging department about the implant, carry the implant card, and contact the pump team before the scan so they can advise on timing and follow-up.
Will a baclofen pump help weakness or improve walking?
It treats spasticity only, not weakness or coordination, and it leaves the underlying condition unchanged. Some people walk or transfer more easily once tightness eases; others discover weakness the stiffness had masked. That is why teams test during the screening trial and set written goals beforehand. Whether walking improves depends on the individual and is never something the surgery can promise.
What happens if a baclofen pump runs out or stops working?
Sudden loss of intrathecal baclofen can trigger withdrawal, with spasticity worse than before, itching, high fever, confusion and agitation, which MedlinePlus describes as potentially life-threatening. Any pump alarm, missed refill or rapid return of stiffness is a same-day call to the pump team or emergency department. Clinicians build a safety margin into refill dates, but the calendar must be kept.
References
- MedlinePlus: Baclofen
- NIH National Institute of Neurological Disorders and Stroke: Spasticity
- NHS: Cerebral palsy: Treatment
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Dysautonomia (Autonomic Disorders): How a Neurologist Builds a Symptom-Control Plan
Dysautonomia is treated by identifying which part of the autonomic nervous system is misfiring, then layering measures in order: fluids, salt, compression garments, and…

Compression Stockings, Salt and Hydration: Daily Habits in Autonomic Neuropathy Care
Living with autonomic neuropathy usually means building a daily routine around three physical levers: waist-high compression garments that limit blood pooling, a supervised increase…

When Does Memory Loss Warrant an Alzheimer’s Disease Evaluation? What a Neurologist Rules Out
Memory loss usually warrants an Alzheimer's evaluation when it is new, progressive, noticed by others, or interferes with daily tasks such as managing money,…

Alzheimer’s Disease Myths: Normal Aging, Family History and What Neurologists Actually Say
Most Alzheimer's disease myths collapse under evidence. Alzheimer's is not normal aging: it is a progressive brain disease in which abnormal protein deposits damage…

Microvascular Decompression vs Gamma Knife vs Percutaneous Procedures for Trigeminal Neuralgia
Microvascular decompression, Gamma Knife radiosurgery and percutaneous procedures all treat trigeminal neuralgia by interrupting or relieving pressure on the trigeminal nerve, but they differ…

Why Neurologists Ask a Family Member to Attend Cognitive Disorder Visits, and How to Prepare
Neurologists ask a family member to attend cognitive disorder visits because memory or thinking problems can make it hard for a person to describe…