

How a Vitrectomy Is Performed: Tiny Ports, Removing the Gel and Repairing the Retina

Key Takeaways
- Modern vitrectomy enters the eye through three self-sealing ports well under a millimeter wide, so most patients have no stitches in the eye wall.
- The vitreous gel does not grow back and does not need to; the eye refills with its own watery fluid within days and vision does not depend on the gel.
- What fills the eye at the end of surgery, saline, gas or silicone oil, determines whether you will need head positioning, how blurry the first weeks will be, and whether flying is forbidden.
- A gas bubble can expand dangerously at altitude or with nitrous oxide anesthesia, which is why air travel and mountain driving are off limits until your surgeon confirms it has cleared.
- Cataract is the most common long-term consequence of vitrectomy in people with a natural lens, often arriving within a year or two and usually treated with routine cataract surgery.
- Central vision after macular hole or membrane surgery commonly keeps improving for six months or more, so early blur does not mean the operation has failed.
A vitrectomy is performed through three tiny ports in the white of the eye, usually under local anesthesia with sedation. The surgeon inserts a light, an infusion line and a cutting probe, removes the vitreous gel, then repairs the retina with peeling, laser or freezing as needed, and fills the eye with saline, a gas bubble or silicone oil to hold the retina in place while it heals.
The sentence that stops most people is not the diagnosis. It is the line that follows it: “We’ll need to go inside the eye.” You can sit with a torn retina or a macular hole for a few minutes and still feel composed. Then someone explains that the gel filling your eye is coming out, and the room gets a little quieter.
This article is about exactly that moment, and about what actually happens next. Understanding how vitrectomy surgery is performed does not make the decision for you; that sits with your retina surgeon. It does take away the fog. The operation has a logic to it, three small ports and three small instruments, and once you see the sequence the whole thing stops sounding like science fiction.
We will walk through the ports, the gel, the repair, the bubble that may be left behind, and the honest list of things that can go wrong, with no mythology and no sales pitch.
What is the vitreous gel, and why would a surgeon remove it?
The back two thirds of your eye is filled with vitreous, a clear jelly that is roughly 98 percent water held together by a fine mesh of collagen fibers. Think of a very soft gel dessert that has been poured into a sphere the size of a large grape. In youth it is firm and sits snugly against the retina, the light-sensing wallpaper lining the inside of the eye. With age it liquefies and shrinks, which is why floaters become more common in midlife.
Here is the awkward part: the vitreous is attached to the retina in places. When it pulls away unevenly, it can tear the retina, open a hole in the macula (the center of the retina responsible for reading-level detail), or form sheets of scar tissue that wrinkle the surface. The gel can also fill with blood after a hemorrhage from diabetic eye disease, or cloud over with inflammation or infection, so that light simply cannot reach the retina.
Removing the gel solves two problems at once. It clears whatever is blocking the view, and it releases the traction, the pulling force, that is distorting or detaching the retina. The eye does not grow new vitreous. Instead, the space gradually fills with aqueous, the watery fluid the eye already produces, and vision does not depend on the gel being there. That is the single most reassuring fact about the whole operation: the thing being removed is not something you need.
MedlinePlus lists the common reasons: retinal detachment, macular hole, epiretinal membrane (scar tissue on the macula), vitreous hemorrhage, severe diabetic retinopathy, certain infections, and injuries or retained lens fragments after cataract surgery.
How vitrectomy surgery is performed, step by step
The modern procedure is called pars plana vitrectomy. The pars plana is a narrow band of the eye wall, a few millimeters behind the colored iris, where instruments can enter without hitting the lens in front or the retina behind. Every step hangs off that one anatomical fact.
Once you are comfortable and the eye is numb, the surgeon places three small cannulas, hollow tubes about the width of a hypodermic needle, through the white of the eye at the pars plana. One carries a steady drip of balanced salt solution so the eye keeps its shape and pressure as gel is removed. One carries a fiber-optic light. The third is the working port for the vitrector, a probe that sucks gel into a tiny side opening and shears it off with a guillotine blade moving thousands of times a minute.
Looking through an operating microscope fitted with a wide-angle viewing system, the surgeon removes the central gel first, then works carefully toward the edges, often after a dye or staining agent is used to make the clear vitreous visible. With the gel gone, the retinal repair itself begins: peeling membranes, flattening a detachment, sealing tears with laser or freezing. The eye is then filled with saline, a gas bubble or silicone oil, the cannulas are withdrawn, and the small openings usually seal on their own without stitches.
Timing varies with the problem being fixed. MedlinePlus describes the operation as typically taking one to a few hours, and Johns Hopkins notes that most people go home the same day. A simple membrane peel is at the short end; a complex diabetic detachment is at the long end.
Tiny ports: what the 23, 25 and 27 gauge numbers mean
If you read your operation note you may see “25-gauge PPV” or “27G.” Gauge is the same measuring system used for needles, and it runs backward: the higher the number, the thinner the instrument. A 25-gauge cannula has an outer diameter of roughly half a millimeter, about the thickness of a pencil lead. A 27-gauge port is thinner still, and 23 gauge is slightly wider but still well under a millimeter.
Why does this matter to the person on the table? Three reasons.
- Wound size. Openings this small usually self-seal when the cannula is removed, so most patients have no stitches in the eye wall. Larger older-style incisions needed sutures, which added irritation and a longer healing phase.
- Conjunctival sparing. The cannulas pass straight through the conjunctiva, the thin membrane over the white of the eye, rather than requiring it to be cut open and sewn back. Less tissue handling means less redness and a quieter eye afterward.
- Control. Smaller probes with faster cut rates take tinier bites of gel, which lets the surgeon work close to a delicate detached retina with less tugging.
Smaller is not automatically better in every case. Thinner instruments are more flexible, which can be a disadvantage when dense scar tissue or thick blood needs to be cleared, so surgeons choose the gauge for the job rather than chasing the smallest number. What you can take from the shift to small-gauge surgery is this: the entry wounds are genuinely tiny, and the long-feared image of an eye being “cut open” does not describe how vitrectomy surgery is performed today.
Removing the gel: the light pipe, the cutter and the view
Watching a vitrectomy on a screen is oddly calm. There is a bright circle of retina, a thin wand of light coming in from one side, and the cutting probe nibbling at something you mostly cannot see. That invisibility is the central technical challenge. Healthy vitreous is as clear as the saline replacing it, so the surgeon relies on subtle cues: the way strands move in the fluid current, the shimmer of a stained surface, the gentle lift when traction releases.
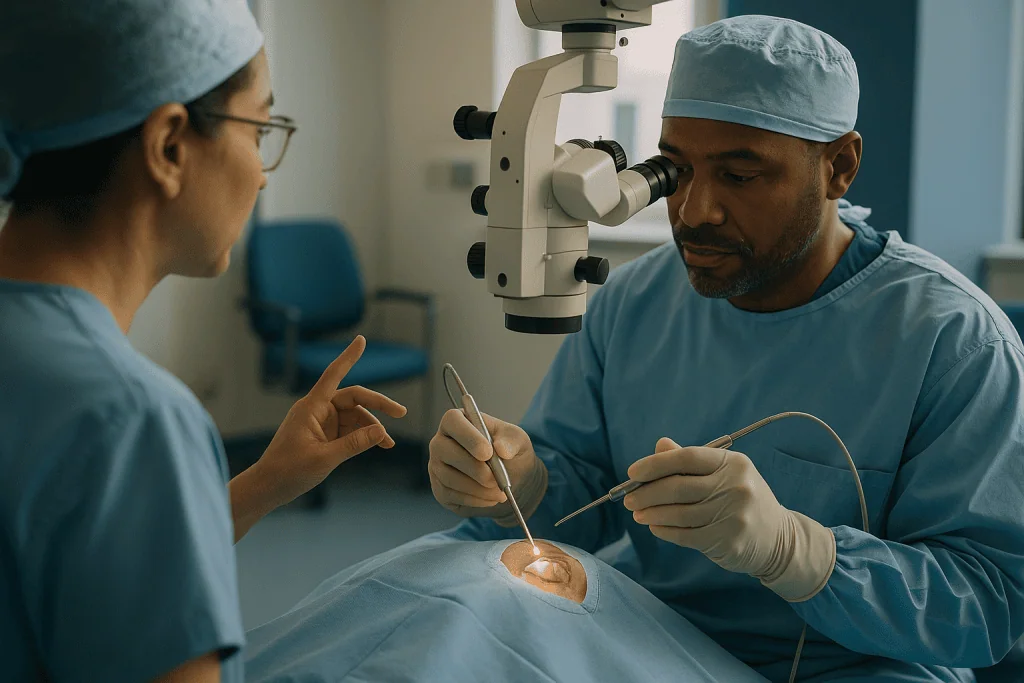
Two ideas govern the gel removal. The first is pressure balance. The infusion line pushes salt solution in at the same rate the cutter draws gel out, so the eye never collapses or over-inflates. A sudden pressure drop can cause bleeding; a surge can starve the optic nerve of blood flow for a moment. The machine monitors and adjusts this continuously.
The second is traction control. The vitrector’s opening faces sideways and its blade cuts so quickly that each bite is minuscule, which means the probe removes gel without pulling hard on whatever that gel is attached to. Near the retina, surgeons often lower suction and raise the cut rate further, a technique sometimes described as “shaving” rather than “sucking.”
Where the vitreous is attached to the back of the eye, the surgeon may deliberately lift it off to create a posterior vitreous detachment, separating the gel from the retina so no residual tug remains. In eyes with bleeding, the dark blood is removed until the retina comes into clear view, which is sometimes the first time anyone has been able to see it properly in months. Only then does the real repair begin.
Repairing the retina: peeling, laser, freezing and the scleral buckle
Once the gel is out, the surgeon has an open workspace. What happens next depends entirely on the diagnosis, and this is where the operation branches.
For a macular hole or an epiretinal membrane, the task is peeling. Using forceps with tips finer than an eyelash, the surgeon lifts a membrane that may be only a few thousandths of a millimeter thick off the surface of the macula. In macular hole surgery, the inner limiting membrane, the innermost layer of the retina, is often peeled as well to relax the edges of the hole so they can draw together. A blue or green dye is commonly used to make these transparent layers visible.
For a retinal detachment, the retina must first be flattened. The surgeon drains the fluid trapped beneath it, sometimes through the original tear, sometimes through a tiny new opening, often using a temporary heavy liquid that sinks and presses the retina back into place. Tears are then sealed. Laser retinopexy creates a ring of small burns around each break that scar into a weld over days to weeks. Cryotherapy, freezing applied through the eye wall from outside, does the same job with cold and is sometimes preferred for breaks far to the periphery.
Some detachments are also treated with a scleral buckle: a silicone band sewn around the outside of the eye that indents the wall inward, supporting the retina from behind. Mayo Clinic describes it as a procedure that may be used alone or combined with vitrectomy. The buckle is not visible from the front and usually stays in place permanently.
None of these steps closes the hole or reattaches the retina by itself. They set the conditions. The seal forms as the eye heals, which is why what fills the eye afterward matters so much.
Vitrectomy gas bubble, silicone oil or saline: what fills the eye afterward
At the end of the operation the surgeon chooses a filler, called a tamponade, whose job is to press gently against the repaired retina while laser or freezing scars mature. The choice shapes your next few weeks more than almost anything else about the surgery.
| Filler | What it is | How long it stays | What it means for you |
|---|---|---|---|
| Balanced salt solution | Sterile fluid similar to the eye’s own aqueous | Replaced naturally within days | Vision clears fastest; no positioning or flying restrictions linked to the filler |
| Gas bubble (air or an expanding gas) | A bubble that floats upward and presses on the retina | Days to several weeks depending on the gas, per NHS and Mayo Clinic | Vision is very blurry until it absorbs; head positioning may be required; no flying or high altitude until it is gone |
| Silicone oil | A clear, viscous liquid that does not absorb | Months, until removed in a second procedure | Vision remains altered while oil is in; chosen for complex or recurrent detachments |
Gas is the workhorse for detachments and macular holes. Because a bubble floats, the surgeon may ask you to hold your head so the bubble rests against the area being treated, which is the origin of the famous face-down instruction. As the bubble shrinks you will see a wobbling line across your vision that gradually drops lower each day; this is normal and expected.
The altitude warning is not a formality. Gas expands as air pressure falls, and a bubble that expands inside a closed eye can raise the pressure to dangerous levels. The NHS advises against air travel while a gas bubble is present, and the same caution applies to mountain driving and to nitrous oxide anesthesia, which can also enlarge the bubble. Many surgeons give patients a wristband or card stating this. Your team will tell you when the bubble has cleared and the restriction ends.
Who usually has a vitrectomy, who is asked to wait, and what the alternatives are
Vitrectomy is a treatment for mechanical problems at the back of the eye: things pulling, lifting, bleeding or blocking. It is not a treatment for the underlying disease that caused them, which is why someone with diabetic retinopathy will still need diabetes care afterward.
The groups most often offered surgery, according to MedlinePlus and Johns Hopkins, include people with a retinal detachment that cannot be managed by simpler means, a full-thickness macular hole, an epiretinal membrane distorting vision enough to interfere with daily life, a vitreous hemorrhage that is not clearing, severe diabetic traction, certain eye infections, and complications after cataract surgery such as a dislocated lens fragment.
Who is asked to wait? Often the person whose problem may resolve on its own. A fresh vitreous hemorrhage frequently clears over weeks as the body reabsorbs blood, and surgeons commonly observe first unless the retina is at risk underneath. A mild epiretinal membrane that is barely affecting reading may be monitored for years. Floaters alone, however annoying, are usually not a reason to operate, because the risks of entering the eye outweigh the benefit for most people.
Alternatives depend on the diagnosis. For some retinal tears and small detachments, laser or cryotherapy alone in the clinic may suffice. Pneumatic retinopexy, injecting a gas bubble in the office and positioning the head without removing the gel, suits selected detachments. A scleral buckle alone remains a reasonable option for certain younger patients. For diabetic hemorrhage, anti-VEGF injections, a class of medicine that blocks a growth signal driving abnormal vessels, are sometimes used to reduce bleeding before or instead of surgery. Each of these trades something for something, and the right choice is a judgment your retina specialist makes with you after examining the eye.
Is a vitrectomy a major surgery? Anesthesia and what the day is like
Yes and no, and the honest answer depends on which word you weight. In terms of delicacy and skill, it is among the most intricate operations in medicine; the surgeon is working on tissue a fraction of a millimeter thick inside a space the size of a grape. In terms of what your body goes through, it is remarkably contained. There is no large incision, blood loss is negligible, and Johns Hopkins describes it as usually performed as an outpatient procedure.
Most adults have local anesthesia with sedation. An anesthetist gives medicine through a vein so you are relaxed and drowsy, and the surgeon numbs the eye with an injection around it that also stops it moving. You remain able to breathe on your own and answer questions, though many people remember little. General anesthesia is used for children, for people who cannot lie still, for very long operations, and when the patient strongly prefers it. The choice is made at your pre-assessment, taking your heart, lungs and medicines into account.
A typical day looks like this. You arrive having followed fasting instructions, your eye is dilated with drops, and a nurse confirms which eye is being operated on. In theater you lie flat with a drape over your face and a flow of fresh air underneath. During surgery you may see lights, shapes and color, but no pain. Afterward you wake with a pad and a shield over the eye, rest for an hour or two, and go home with someone who can drive you.
Where the “major” label earns its place is in the follow-up. Positioning, drops, several clinic visits and weeks of blurred vision ask more of you than many operations with far larger scars.
How painful is vitrectomy recovery, and what is the typical vitrectomy recovery time?
Most people are surprised that the operation itself is not the painful part. Severe pain is uncommon and is treated as a warning sign rather than an expected phase. What is common is a gritty, scratchy, sore sensation for several days, as if an eyelash were trapped under the lid, together with a dull ache around the brow and some tenderness when you look to the side. The eye is usually red and the lids may be puffy, particularly if freezing or a scleral buckle was used, since both involve the outside of the eye.
Cleveland Clinic and MedlinePlus describe the discomfort as generally manageable with over-the-counter pain relief recommended by your team; your clinician will tell you what is appropriate for you and when to stop. The surface irritation tends to settle within the first one to two weeks as the small port sites heal.
Recovery time is a different and longer story, and it splits into three layers:
- The eye wall heals in days to a couple of weeks.
- A gas bubble clears over days to weeks, and vision stays blurry until it does, as the NHS and Mayo Clinic describe.
- The retina itself keeps recovering for months. After macular hole or membrane surgery, central vision commonly continues to sharpen for six months or longer, according to the National Eye Institute.
The NHS advises that most people take around two to six weeks before returning to work and normal activity after retinal detachment repair, with the longer end for physical jobs and for anyone with a gas bubble. Driving is off limits until your surgeon confirms your vision meets the legal standard, which for a gas-filled eye may be several weeks. None of this is a promise. It is the typical shape of recovery, and your own version will be set by your diagnosis and your surgeon.
Face down after vitrectomy: what the first days and weeks usually look like
The day after surgery you return to clinic, the pad comes off, and someone checks the pressure inside your eye and the position of the retina. Vision at this point is usually poor, especially with gas; some people see only light and movement through the bubble. This is expected and does not predict the final result.
If you have a gas bubble and your repair is at the back of the eye, you may be asked to position. Face-down posturing means keeping your face parallel to the floor so the bubble floats up against the macula. How long varies widely by surgeon and diagnosis. The National Eye Institute notes that for macular holes the period may range from a day or so to a week or more, while some surgeons now use shorter protocols or no posturing for smaller holes. Side-lying or upright positions are used for tears in other locations. Practical tips that patients pass on: a massage chair or a face-down pillow rented or borrowed, audiobooks instead of screens, and a cushion to wedge yourself at night.
Drops are the other daily ritual, typically an antibiotic to reduce infection risk and a steroid to control inflammation, used on a schedule your team sets and tapers over the first few weeks. You will be told not to rub the eye, to wear the shield at night, and to avoid swimming, heavy lifting and bending with your head below your waist for a period your surgeon specifies.
Visits usually cluster at one day, one to two weeks, and around four to six weeks, with more if oil is in place or a second procedure is planned. Expect the wobbling bubble line to drop lower each morning and vision to clear from the top down as it shrinks. It is one of the stranger and more satisfying things to watch.
Can you lose vision permanently after vitrectomy? Risks and downsides explained
The question deserves a straight answer: yes, it is possible, and no, it is not the usual outcome. The reason to understand the risks is not to frighten you but to make the follow-up instructions make sense.
The downsides fall into a few groups described by MedlinePlus, Mayo Clinic and Johns Hopkins.
- Cataract. In people who still have their natural lens, vitrectomy speeds up clouding of the lens, often within a year or two. This is so common that many surgeons discuss cataract surgery as a likely second step rather than a complication.
- Raised eye pressure. Gas, oil, inflammation or steroid drops can push pressure up, which is why it is checked at every visit. Sustained high pressure can damage the optic nerve, and it is treatable when caught.
- Bleeding inside the eye, usually small and self-clearing, occasionally significant.
- Retinal re-detachment or a new tear, since the retina is handled during surgery and scar tissue can form afterward in a process called proliferative vitreoretinopathy.
- Infection inside the eye (endophthalmitis). Rare, serious, and the main reason sudden pain and worsening vision in the first days is treated as an emergency.
- Macular hole that fails to close, or a membrane that regrows.
- Permanent loss of vision from any of the above, or from the original disease itself.
Two honest points of context. First, for most conditions treated this way, the alternative to surgery is also loss of vision; a detached retina left alone does not reattach. Second, a successful operation does not always mean sharp vision. If the macula was detached for a long time, or diabetic damage was extensive, the retina may reattach perfectly yet remain limited in what it can see. Your surgeon should be able to tell you, in your specific case, what a realistic range of outcomes looks like.
What people often get wrong about vitrectomy
Some beliefs circulate widely enough that they deserve a direct correction.
“They take your eye out to work on it.” No. The eye stays in its socket throughout. The instruments enter through ports less than a millimeter wide, and the surgeon looks in through the pupil with a microscope.
“The gel grows back.” It does not, and it does not need to. The eye refills with its own watery fluid within days, and vision does not depend on vitreous being present.
“You’ll be blind for weeks.” With saline, vision often clears within days. With gas, it is very blurry while the bubble is present, but you can usually see light, movement and increasingly detail as it shrinks. It is temporary and expected.
“Face-down means lying on your stomach for a week straight.” Positioning instructions vary, breaks are usually permitted, and many protocols are now shorter than they were. Ask your surgeon exactly what your instructions mean rather than assuming the worst-case version.
“Surgery will fix my floaters, so I should ask for it.” Vitrectomy does remove floaters, but entering the eye carries risks that most specialists judge not worth taking for floaters alone. The vast majority of floaters become less noticeable over time without any treatment.
“If my vision is still blurry after a month, it failed.” Retinal recovery is slow. The National Eye Institute notes that improvement after macular surgery continues for months. A month is early.
“Once it’s repaired, I’m done.” Cataract commonly follows in the years after surgery, and the underlying condition, whether diabetes or a tendency to retinal tears, still needs attention. The operation treats the problem in front of you; it does not change why it happened.
Questions to ask your care team before vitrectomy
A good consultation leaves you knowing not just that you need surgery but what kind, what for, and what the next month will demand. These questions tend to draw out the answers that matter.
- What exactly is wrong with my retina, and what will you be doing inside the eye to repair it?
- Will you use a gas bubble, silicone oil or saline, and what does that mean for my vision, positioning and travel in the weeks after?
- If I need to position, in what direction, for how many hours a day, and for how long?
- Will you combine this with a scleral buckle, laser, cryotherapy or cataract surgery?
- What is a realistic range of visual outcomes for someone with my diagnosis and its duration?
- What anesthesia do you recommend for me, and why?
- Which of my regular medicines should I continue, and who decides about any blood thinners?
- How will I know the difference between normal soreness and a problem, and who do I call out of hours?
- When can I drive, work, exercise, swim and fly?
- Is a second operation likely, for example to remove oil or treat a cataract?
- What happens if the retina detaches again or the hole does not close?
Write the answers down or bring someone who will. Dilating drops and anxiety both make it hard to retain detail, and the instructions about positioning and altitude are the ones that most often get garbled on the way home.
One more question is worth asking of yourself: what will I need at home? Someone to drive on day one, a way to put in drops if you struggle with that, and a plan for work. Surgery goes better when the week after it is already arranged.
When to call your doctor after vitrectomy
Most of the discomfort after surgery is expected and settles. A short list of signs is not, and each should prompt a same-day call to your surgical team or an emergency eye service, not a wait for the next appointment.
- Pain that is severe, worsening, or not eased by the pain relief you were advised to take, especially with nausea or vomiting, which can signal dangerously high eye pressure.
- Vision that was improving and then suddenly worsens, or a new dark curtain or shadow spreading across your sight, which may indicate the retina has detached again.
- A sudden shower of new floaters or flashes of light.
- Increasing redness, discharge, or swelling of the lids that is getting worse rather than better after the first few days, which can be an early sign of infection inside the eye.
- Light sensitivity so marked you cannot open the eye.
- Any blow to the eye, or a fall onto the face.
Two situations deserve a special word. If you have a gas bubble and you develop sudden deep aching pain during or after a car journey over hills, or if you are about to receive any anesthesia for another procedure, tell the clinicians about the bubble immediately; gas expands at altitude and with certain anesthetic agents. And if you are unsure whether a symptom is serious, call. Retina teams would far rather hear about ten normal recoveries than miss one infection, because endophthalmitis, infection inside the eye, is treated most effectively in its first hours.
Everything in this article describes the usual course. Your surgeon knows the state of your retina, the filler in your eye and the risks that apply to you. Their instructions override anything written here.
Frequently asked questions
What is a vitrectomy, in plain terms?
A vitrectomy is an operation that removes the clear jelly, called vitreous, from inside the eye so the surgeon can reach and repair the retina. It is done through three tiny ports in the white of the eye with a light, a fluid line and a cutting probe. The space is then refilled with saline, a gas bubble or silicone oil while the retina heals.
Is a vitrectomy a major surgery?
It is a technically demanding operation, performed under a microscope on tissue a fraction of a millimeter thick, yet physically contained for the patient. Most adults have local anesthesia with sedation and go home the same day, with no large incision and minimal blood loss. The demanding part is often the recovery: drops, possible head positioning, several clinic visits and weeks of blurred vision.
How painful is vitrectomy recovery?
Severe pain is uncommon and is treated as a warning sign. The usual experience is a gritty, scratchy soreness for several days, a dull ache around the brow, and redness, which generally eases over one to two weeks as the small port sites heal. Pain that is severe, worsening, or accompanied by nausea should be reported to your surgical team the same day.
How long is the typical vitrectomy recovery time?
Recovery has layers. The eye surface heals in days to a couple of weeks; a gas bubble clears over days to weeks; and the retina itself keeps recovering for months. The NHS describes around two to six weeks before most people return to work after retinal detachment repair, longer for physical jobs. Your surgeon sets your own timeline based on the repair and filler used.
Why do I have to stay face down after vitrectomy?
Positioning is used when a gas bubble has been placed and the repair is at the back of the eye. Gas floats, so keeping your face toward the floor makes the bubble press against the macula while laser scars mature. The duration varies by surgeon and diagnosis, from a day or so to a week or more, and breaks are usually allowed. Not every vitrectomy requires it.
What does the vitrectomy gas bubble feel like, and when does it go away?
You see rather than feel it: a dark wobbling line or ball across the lower part of your vision that drops a little each day as the bubble shrinks, with vision clearing from the top down. Depending on the gas chosen, it absorbs over days to several weeks. Until your surgeon confirms it has gone, do not fly, drive over mountains, or have nitrous oxide anesthesia.
Can you lose vision permanently after vitrectomy?
It is possible but not the usual outcome. Permanent loss can follow infection inside the eye, uncontrolled high pressure, severe bleeding, or a retina that re-detaches and cannot be flattened again. Vision can also remain limited if the macula was damaged for a long time before surgery. For most conditions treated this way, leaving the problem untreated also leads to vision loss.
What are the downsides of vitrectomy surgery?
The most common is accelerated cataract in people who still have their natural lens. Others include raised eye pressure, bleeding, re-detachment or new tears, scar tissue formation, a macular hole that fails to close, and rare but serious infection. Add the practical costs: blurred vision while gas is present, possible positioning, travel restrictions and several follow-up visits over the first weeks.
Will I be awake during a vitrectomy?
Usually you will be sedated and drowsy rather than fully asleep, with the eye numbed by an injection that also stops it moving. You may notice lights, colors and shapes but not pain, and many people remember little afterward. General anesthesia is used for children, for very long operations, and for people who cannot lie still or who strongly prefer it.
Does the vitreous gel grow back after a vitrectomy?
No, and it does not need to. The eye continuously produces a watery fluid called aqueous, which fills the space within days and maintains normal pressure and shape. Vision relies on the cornea, lens and retina, not on the gel, so its absence does not blur sight. One benefit is that floaters, which live in the gel, are removed along with it.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Questions to Ask Before Laser Treatment for Farsightedness (and What the Answers Mean)
Before laser treatment for farsightedness, ask your care team which procedure they propose and why, how high and how stable your prescription is, how…

How Eye Muscle Surgery for Strabismus Works: Loosening, Tightening and Adjustable Sutures
Strabismus surgery realigns the eyes by repositioning one or more of the six small muscles attached to the outside of each eyeball. A surgeon…

How Laser Treatment Corrects Myopia: Flattening the Cornea to Refocus Distant Objects
Laser treatment corrects myopia by reshaping the cornea, the clear front window of the eye. In a nearsighted eye, light focuses in front of…

Is Super LASIK Only for Complex Prescriptions? Who Actually Benefits From Custom Treatment
No. Custom or wavefront-guided LASIK, often marketed as Super LASIK, is not reserved for complex prescriptions. It uses a detailed optical map of each…

When Does a Drooping Eyelid Need Oculoplastic Surgery? Vision, Comfort and Timing
A drooping eyelid usually needs surgery when the lid margin sits low enough to block the upper or central field of vision, when it…
Who Is Steered Toward LASEK PRK? Thin Corneas, Contact Sports and Dry Eye Explained
LASEK and PRK are surface laser treatments that reshape the cornea without cutting a flap, so eye surgeons often suggest them for people whose…