

How Do Test Results Shape a Hashimoto Treatment Plan? TSH, Antibodies and Ultrasound

Key Takeaways
- Treatment decisions in Hashimoto's rest on TSH and free T4; antibodies confirm the autoimmune cause and shape follow-up rather than triggering treatment on their own.
- A mildly raised TSH is usually repeated after several weeks before any diagnosis, because a meaningful share of such values return to normal without treatment.
- After starting or changing thyroid hormone, TSH is typically rechecked about 6 to 8 weeks later, and roughly once a year once levels are stable.
- Ultrasound is reserved for goiter, suspected nodules or unclear cases; it is not required to diagnose Hashimoto's when blood tests are clear.
- High-dose biotin supplements can falsely alter TSH and thyroid hormone readings on common assays, so supplements belong on the request form before a blood draw.
- Pregnancy lowers TSH targets and raises hormone requirements, so anyone with Hashimoto's who is pregnant or planning to be needs earlier and more frequent testing.
Hashimoto diagnosis tests work as a set, not one number. A high TSH with low free T4 usually signals an underactive thyroid that clinicians commonly treat with thyroid hormone replacement. Thyroid antibodies confirm the autoimmune cause and raise the chance of future hypothyroidism, while ultrasound mainly matters when the gland is enlarged or has nodules. Results are rechecked over weeks and years; the treating team weighs them against symptoms and life stage.
The patient portal pings at 9:40 on a Tuesday. Four lines of results, two of them flagged in red, and no appointment for another nine days. One number is called TSH and sits just above the range. Another says “TPO antibodies” and is many times higher than the cutoff. Somewhere in the fatigue and the cold hands and the hair in the shower drain, there is now a name for it, and a wait.
This is how most people meet hashimoto diagnosis tests: as a column of figures that arrive before the explanation does. The temptation is to treat each line as a verdict. In practice, clinicians read them the way a mechanic reads a dashboard, as several gauges describing one engine.
What follows is a walk through those gauges, what each one can and cannot say, and how the combination shapes the plan your care team eventually proposes.
What are hashimoto diagnosis tests, and why does one blood test rarely settle it?
Hashimoto’s disease is an autoimmune condition in which the body’s immune system attacks the thyroid, the butterfly-shaped gland at the front of the neck that sets the pace of metabolism. In the United States it is the most common cause of an underactive thyroid, and the National Institute of Diabetes and Digestive and Kidney Diseases puts its reach at roughly 5 in 100 people.
Hashimoto diagnosis tests fall into three groups. Blood tests of thyroid function measure what the gland is producing right now. Antibody tests look for the immune fingerprint of the disease. Imaging, almost always ultrasound, looks at the gland’s texture and size. Each answers a different question, which is why a single result can be misleading.
Consider the mismatch that puzzles so many patients. Antibodies can be strongly positive while hormone levels remain entirely normal. The reverse happens too: a clearly underactive thyroid with antibodies that never show up on a standard assay. Neither pattern is an error. The first describes an immune process that has started but not yet damaged enough tissue to shift hormone output. The second describes damage from a cause that may be autoimmune but is not leaving the expected marker.
Clinicians therefore ask two separate questions. Is the thyroid underactive, and if so, how much? And is Hashimoto’s the reason? Treatment decisions hang mostly on the first question. The second shapes how closely you are followed, what else is screened for, and what the future is likely to hold.
Keeping those two questions apart is the single most useful thing a patient can do when reading a results page.
How does Hashimoto's actually work inside the thyroid?
Picture a factory with a quality-control team that has turned against the machinery. In Hashimoto’s, immune cells called lymphocytes move into the thyroid and settle there. Over months and years they damage the follicles, the tiny sacs where thyroid hormone is assembled and stored. The gland tries to compensate, often swelling into a goiter, a visible or palpable enlargement of the thyroid. Eventually, in many people, there is simply not enough working tissue left to meet demand.
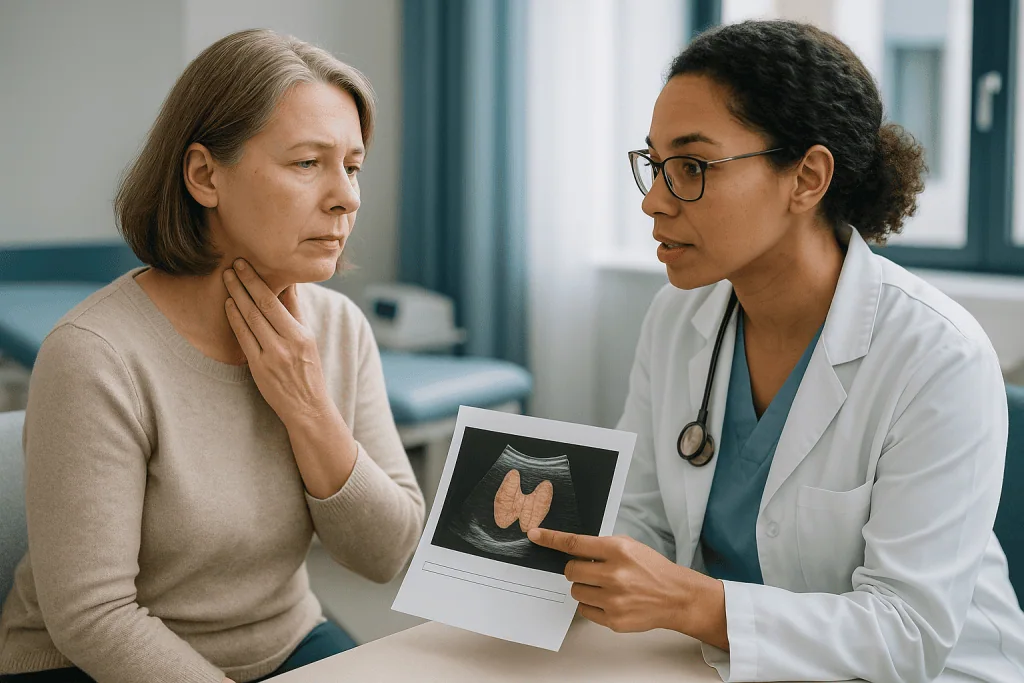
Two hormones carry the gland’s output. Thyroxine, written T4, is the main product and acts as a reservoir. Triiodothyronine, or T3, is the more active form, mostly made by converting T4 in other tissues. Above both sits the pituitary gland at the base of the brain, which releases thyroid-stimulating hormone, TSH, to tell the thyroid how hard to work.
This is a thermostat. When thyroid hormone falls, the pituitary senses the drop and pushes out more TSH. When hormone levels rise, TSH falls. That inverse relationship is what makes TSH such a sensitive early warning: the pituitary notices a struggling thyroid before the hormone levels themselves fall out of range.
The antibodies in Hashimoto’s target two proteins inside the factory. Thyroid peroxidase, TPO, is the enzyme that attaches iodine to the hormone backbone. Thyroglobulin is the storage protein that holds hormone in the follicles. Antibodies against either are a sign that the immune system has registered the thyroid as foreign.
The process is slow, which cuts both ways. Symptoms creep rather than crash, so people often live with them for years. On the other hand, the gradual pace gives clinicians time to watch, retest and act at the right moment rather than on the first flagged value.
What does the TSH test tell your care team?
TSH is where almost every thyroid workup starts, and for a sensible reason. Because the pituitary reacts to small changes in circulating hormone, TSH shifts earlier and more dramatically than T4 does. A thyroid running at 90 percent capacity may still keep T4 inside the normal range while TSH is already climbing in protest.
Reference ranges vary by laboratory and by the assay used, so the printed range on your own report is the one that counts. Many labs set the upper boundary somewhere around 4 to 5 milli-international units per liter, with the lower edge near 0.4, though these are lab conventions rather than treatment thresholds. MedlinePlus notes that a high TSH most often means the thyroid is underactive, while a low TSH points to an overactive gland or to over-replacement in someone already on treatment.
Several things nudge TSH without any thyroid disease behind them. Acute illness, recovery from illness, very poor sleep and some medicines can move it. The hormone also follows a daily rhythm, running higher overnight and in the early morning. Mayo Clinic and professional bodies therefore generally advise that a single mildly raised TSH be repeated before anyone is labeled hypothyroid, typically after several weeks.
High-dose biotin supplements deserve a specific mention. The NIH Office of Dietary Supplements notes that biotin can interfere with many immunoassays, producing falsely low TSH or falsely high hormone readings. Telling the clinic about any supplement before a blood draw avoids a confusing result.
What TSH cannot do is say why the thyroid is struggling. It is a measure of demand, not of cause. That is the job of the next two groups of tests.
Free T4 and T3: the hormones behind the number
If TSH is the pituitary shouting instructions, free T4 is what the thyroid is actually delivering. The word “free” matters. Most thyroid hormone in the blood is bound to carrier proteins and unavailable to cells. Free T4 measures the small unbound fraction that does the work, which is why it is preferred over older total T4 tests that fluctuate with protein levels, pregnancy or oral estrogen.

Free T4 and TSH are read as a pair. The table in a later section lays out the main patterns, but the central logic is simple. High TSH with low free T4 means the gland has failed to keep up: this is overt hypothyroidism. High TSH with normal free T4 means the gland is compensating under strain, a state called subclinical hypothyroidism. Normal TSH with normal free T4, even with antibodies present, means the thyroid is currently doing its job.
T3 is measured less often in suspected Hashimoto’s than many patients expect. Because tissues convert T4 to T3 as needed, T3 tends to stay normal until hypothyroidism is advanced, so it adds little to the early diagnosis. The NHS describes the standard diagnostic approach as TSH plus T4, with T3 reserved for specific situations, mainly when an overactive thyroid is the question.
Patients sometimes ask for reverse T3 or for very detailed hormone panels promoted online. Mainstream guidelines do not use reverse T3 to diagnose or manage Hashimoto’s, and its value in routine care has not been shown. A clinician who does not order it is following the evidence, not cutting corners.
One practical note: free T4 can be affected by the same biotin interference as TSH, and by some medicines, so the full list of what you take belongs on the request form.
What do TPO antibodies with a normal TSH mean?
Here is the result that generates the most anxious searches. Thyroid peroxidase antibodies, often abbreviated anti-TPO, are positive in the large majority of people with Hashimoto’s. MedlinePlus describes them as the most common marker of autoimmune thyroid disease. Thyroglobulin antibodies are the second marker and are often ordered alongside.
A positive antibody with a normal TSH tells you the immune process is present and the thyroid is, for now, coping. It does not diagnose hypothyroidism, and under mainstream guidelines it does not by itself call for thyroid hormone. The NHS and Mayo Clinic frame this as a reason for periodic monitoring rather than immediate treatment, because people with antibodies progress to an underactive thyroid at a higher rate than those without, but many never do.
Antibody tests have limits that the number on the page does not convey. A minority of healthy people carry low-level TPO antibodies with no thyroid disease. Levels rise and fall over time without clear meaning, so tracking them month to month rarely changes a decision. And a small group of people with classic Hashimoto’s on ultrasound test negative on standard assays.
What antibodies do change is context. They confirm the cause of an underactive thyroid when one is found, which matters because autoimmune hypothyroidism is usually permanent whereas some other causes, such as thyroiditis after a viral illness, can resolve. They also prompt clinicians to be alert for related autoimmune conditions, since the same immune tendency can involve other organs.
In pregnancy planning the stakes shift, which is why antibody status earns its own section further down. For everyone else, a positive TPO result with a normal TSH is a reason for a calendar reminder, not alarm.
When does a thyroid ultrasound help with Hashimoto's?
Ultrasound uses sound waves to build a picture of the gland. It involves gel on the neck, a handheld probe and about fifteen minutes on a couch; there is no radiation and no injection. In a thyroid affected by Hashimoto’s, the images typically show a gland that is darker than normal, with a coarse, uneven texture that radiologists describe as heterogeneous. Blood flow may look increased early on. Later the gland can shrink and become fibrous.
Despite these recognizable features, ultrasound is not a routine requirement for diagnosing Hashimoto’s. Mayo Clinic lists it as a test used when the examination suggests a goiter or nodules, when the diagnosis remains unclear after blood tests, or when antibodies are negative but the clinical picture still points to autoimmune disease. Blood tests, not pictures, decide whether treatment is needed.
Where ultrasound earns its keep is the lump question. Hashimoto’s glands are bumpy, and the autoimmune texture can mimic or hide a nodule on examination. Imaging separates a lumpy but uniformly inflamed gland from a discrete nodule that may need measuring, follow-up or sampling with a fine needle. That distinction is one your care team will want if your neck feels irregular or if you notice swelling, trouble swallowing or a change in your voice.
Ultrasound reports can be unsettling to read. Words like “hypoechoic” or “micronodular pattern” sound ominous but often simply describe the expected appearance of an inflamed gland. The radiologist’s structured scoring for any nodules, and the clinician’s reading of it, carry more weight than any single adjective.
If no goiter or nodule is suspected, a normal workup without imaging is complete, not incomplete.
Reading hashimoto blood test results together
Individual values become useful when laid side by side. The table below shows the combinations clinicians encounter most often and the direction each typically points. It is a map of how results are interpreted in mainstream guidance, not a decision tool; your own team adds symptoms, age, pregnancy plans, other conditions and repeat values before proposing anything.
| TSH | Free T4 | TPO antibodies | Usual interpretation | Typical next step in guidelines |
|---|---|---|---|---|
| Normal | Normal | Positive | Autoimmune process present, thyroid coping | Periodic retesting; no hormone treatment |
| Mildly high | Normal | Positive or negative | Subclinical hypothyroidism | Repeat test; treatment weighed case by case |
| High | Low | Positive | Overt hypothyroidism due to Hashimoto’s | Thyroid hormone replacement usually offered |
| High | Low | Negative | Overt hypothyroidism, cause to clarify | Treatment plus review of other causes, sometimes ultrasound |
| Low | High or normal | Positive | Possible early inflammatory release of stored hormone | Retest; distinguish from Graves’ disease |
| Low | Low | Any | Pattern suggesting a pituitary rather than thyroid problem | Further hormone testing |
Two patterns surprise people. The first is the brief overactive phase, sometimes called Hashitoxicosis, when damaged follicles leak stored hormone and TSH dips temporarily. The second is the low-TSH, low-T4 combination, which points away from the thyroid itself and toward the pituitary, and which a TSH-only screen would miss.
Notice that antibodies change the label and the follow-up, while TSH and free T4 drive the treatment column.
Who is usually treated for Hashimoto's, and who is usually asked to wait?
The clearest case is overt hypothyroidism: a TSH above range with a free T4 below it. The NHS, Mayo Clinic and the NIDDK all describe thyroid hormone replacement as the standard treatment here, regardless of whether antibodies are present. The reasoning is physiological. The gland cannot make enough hormone, so the hormone is supplied from outside.
Subclinical hypothyroidism is where judgment enters. Guidelines generally recommend confirming the result on a repeat test some weeks later, because a meaningful share of mildly raised TSH values normalize on their own. If the elevation persists, clinicians weigh how high the TSH is, whether antibodies are positive, whether symptoms are present, the person’s age, heart health and any plan for pregnancy. Guideline bodies set a TSH level above which treatment is usually offered even without symptoms, and a gray zone below it where watchful waiting is a legitimate choice. Older adults are often monitored rather than treated for small elevations, partly because TSH drifts upward with age and partly because over-treatment carries risks to heart rhythm and bone.
People with positive antibodies and normal thyroid function are usually asked to wait and retest. Treating a normally functioning thyroid has not been shown to prevent progression in the general population, and it exposes people to the hazards of excess hormone.
Who gets a different conversation? Anyone pregnant or trying to conceive, where thresholds are lower and monitoring more frequent. People with a large goiter causing pressure symptoms. Those whose results are hard to interpret because of other illness or medicines. In each case the plan is individual, and “wait” is an active decision with a scheduled follow-up, not a dismissal.
What actually happens in the weeks after a prescription
When treatment is offered, it is almost always levothyroxine, a synthetic form of T4 that the body converts to active T3 exactly as it would its own hormone. Because the medicine replaces what the gland cannot make rather than stimulating the gland, it does not change the autoimmune process. It fills the gap.
The first weeks are quieter than many people expect. Levothyroxine has a long half-life, meaning it takes several weeks for blood levels to reach a steady state. Mayo Clinic notes that symptoms such as fatigue and cold intolerance commonly begin to improve over a few weeks, with TSH typically rechecked about 6 to 8 weeks after starting or changing treatment. Adjustments are made in small steps and then rechecked again, so the early phase can involve two or three blood tests before the level settles.
Practical matters shape results during this period. The medicine is absorbed best on an empty stomach, and absorption is reduced by calcium, iron, some antacids and high-fiber meals taken close by. The prescribing clinician or pharmacist will explain the timing that fits your routine; consistency matters more than any particular hour.
Some people feel distinctly better quickly, others notice gradual change, and a minority feel no different despite a normalized TSH. That last group deserves honest counseling: not every symptom attributed to the thyroid turns out to be thyroid-related, and persistent tiredness prompts a wider look rather than ever-higher hormone levels.
Weight is a frequent question. Treatment typically reverses the modest fluid-related weight gain of hypothyroidism, but it is not a weight-loss treatment and guidelines caution against using it as one. Any change to the prescription belongs with the treating team.
How often are Hashimoto's tests repeated over the years?
Monitoring is where Hashimoto’s care really lives. Because the disease progresses slowly and the treatment is adjusted to a number, the schedule of repeat tests matters as much as the first diagnosis.
During the adjustment phase, TSH is checked roughly every 6 to 8 weeks after each change until it sits in the target range and symptoms are stable. Mayo Clinic describes the subsequent routine as a check about once a year for most people on a stable regimen, with free T4 added when the picture is unclear. Antibodies are rarely rechecked once positive; they have already answered their question.
Some situations call for an earlier test. Pregnancy, a new medicine that affects absorption or metabolism, a significant change in weight, the start of menopause, or a return of symptoms all justify a check outside the annual cycle. So does any switch in how the medicine is formulated, since small differences in absorption can shift levels.
For people with positive antibodies but normal thyroid function who are not on treatment, guidance commonly suggests TSH checks at intervals of about a year, sooner if symptoms appear. The purpose is to catch the transition to hypothyroidism while it is still mild.
Timing around the blood draw affects interpretation. Taking levothyroxine shortly before the test can transiently raise free T4 without changing TSH, so some clinics ask that the morning dose wait until after the sample; follow your own team’s instruction. Testing at a consistent time of day keeps the daily TSH rhythm from muddying comparisons.
Many people find it helpful to keep their own log of dates and values. Trends over years tell a clearer story than any single result, and a tidy record makes every appointment more productive.
Pregnancy, planning a pregnancy and Hashimoto's testing
Pregnancy changes the rules in two ways. The developing baby depends entirely on the mother’s thyroid hormone in the first trimester, before its own gland works, and the demands of pregnancy raise the mother’s hormone requirement by a substantial margin. A thyroid already weakened by Hashimoto’s may not meet that increase.
The NIDDK notes that untreated hypothyroidism in pregnancy is associated with higher risks of miscarriage, preterm birth, high blood pressure in pregnancy and effects on the baby’s development. For that reason, clinicians use lower TSH targets during pregnancy than for the general population, and the first-trimester TSH reference range itself is shifted downward because pregnancy hormones naturally suppress it.
Women known to have Hashimoto’s are usually advised to have a TSH check when planning a pregnancy or as soon as it is confirmed, and those already on levothyroxine often need their prescription reviewed early. Mayo Clinic describes more frequent monitoring through pregnancy, commonly every few weeks in the first half and periodically thereafter, with the prescribing clinician making each adjustment.
Positive TPO antibodies with normal thyroid function occupy a particular niche here. Women with antibodies have a higher chance of developing hypothyroidism during pregnancy and of thyroiditis after delivery. Guidelines generally recommend closer monitoring rather than automatic treatment, and the evidence on treating antibody-positive women with normal TSH to improve pregnancy outcomes has been mixed, so this is a conversation to have with an obstetric or endocrine team rather than a decision to make from a search result.
After birth, a check in the following months helps distinguish the ordinary exhaustion of new parenthood from postpartum thyroid changes, which can swing in either direction.
What people often get wrong about hashimoto diagnosis tests
Myth: positive antibodies mean you need thyroid medicine. Antibodies describe cause, not function. Treatment follows TSH and free T4. Many people carry antibodies for years, sometimes for life, without ever becoming hypothyroid.
Myth: a normal TSH rules Hashimoto’s out. It rules out current hypothyroidism on that day. It says nothing about the immune process, which is why antibodies are tested when the clinical suspicion is there.
Myth: TSH alone is enough forever. For most routine monitoring it is, but the pattern of low TSH with low free T4 points to a pituitary problem that a TSH-only screen would miss, and early inflammatory phases can temporarily suppress TSH. Pairing with free T4 when results or symptoms do not fit is standard practice.
Myth: the goal is to make antibodies go to zero. No guideline sets that target, and no treatment reliably achieves it. Antibody levels drift without clinical meaning, and chasing them leads to unnecessary testing and sometimes to unproven interventions.
Myth: a special diet or supplement can replace testing and treatment. Selenium, iodine and gluten-free approaches are widely promoted. The evidence that any of them restores thyroid function in established Hashimoto’s is weak, and excess iodine can worsen autoimmune thyroid disease. A balanced diet is sensible; it is not a substitute for monitoring.
Myth: once the number is normal, everything else is in your head. Residual symptoms despite a normal TSH are common and deserve a proper review for anemia, vitamin D or B12 deficiency, sleep disorders, mood and other causes. Dismissing them is as unhelpful as blaming the thyroid for everything.
Myth: ultrasound is needed to confirm the diagnosis. It helps with lumps and unclear cases; it is not a routine requirement.
Questions to ask your care team about your results
A short list, brought to the appointment, turns a confusing results page into a conversation. These questions are the ones endocrinologists and primary care clinicians say they are glad to be asked.
- Is my thyroid underactive now, or do my results show antibodies with normal function? Which of my numbers drove that conclusion?
- Will you repeat the TSH before deciding anything, and roughly when?
- If I have subclinical hypothyroidism, what factors in my case tip the balance toward treatment or toward monitoring?
- Do I need an ultrasound? If one was done, were any nodules found that need follow-up, and on what schedule?
- Which of my current medicines or supplements could affect the test results or the absorption of treatment, including biotin, calcium and iron?
- If I start treatment, when will the next blood test be, and what symptoms should prompt an earlier call?
- I am planning a pregnancy, or might be: how does that change my targets and the frequency of testing?
- Should I be checked for related conditions such as celiac disease, type 1 diabetes, vitamin B12 deficiency or adrenal problems?
- If my TSH normalizes but I still feel unwell, what will you look for next?
- How should I take and store the medicine so that each test reflects a steady level?
Write the answers down, or ask whether they can be summarized in the visit notes. Thyroid care unfolds over years, and the clinician you see in five years will thank you for a clear record of what was decided and why.
Finally, ask what the plan is if you simply want to wait. A good team will tell you what they are watching for and when they want to see you again.
When to call your doctor
Most of Hashimoto’s unfolds slowly enough to be handled at scheduled visits. A few situations should not wait for the next appointment.
Call urgently, or seek emergency care, if someone with known or suspected hypothyroidism becomes confused, unusually drowsy or hard to rouse, develops a very low body temperature, slowed breathing or a very slow heartbeat, especially during an infection or in cold weather. This rare but dangerous state, called myxedema crisis, is a medical emergency.
Seek same-day advice for a rapidly enlarging neck swelling, new difficulty swallowing or breathing, a hoarse voice that persists for more than a couple of weeks, or a hard, fixed lump in the neck. These are not typical of Hashimoto’s alone and need prompt assessment.
Contact the clinic promptly, without waiting for the routine recheck, if you are on treatment and notice palpitations, a racing or irregular heartbeat, tremor, unexplained weight loss, heat intolerance, anxiety or chest discomfort. These can signal over-replacement and warrant a blood test and review. Chest pain or shortness of breath at rest should be treated as an emergency regardless of cause.
Let your team know within days if you become pregnant, start a medicine that can interfere with thyroid hormone, or notice symptoms returning after a long stable period.
For everything else, the annual check and an honest list of how you feel will do most of the work. The decisions that follow, whether to start, adjust, continue or simply watch, rest with the clinician who knows your full history. The tests set the frame; the treating team paints the picture.
Frequently asked questions
What do high TPO antibodies with a normal TSH mean?
They mean the autoimmune process of Hashimoto’s is present but the thyroid is currently producing enough hormone. Under mainstream guidelines this is monitored with periodic TSH checks rather than treated, because many antibody-positive people never develop an underactive thyroid. The result does raise the long-term chance of hypothyroidism and matters more in pregnancy, so it is worth a scheduled follow-up with your clinician.
How are hashimoto blood test results interpreted?
Clinicians read TSH and free T4 together to judge thyroid function, then use antibodies to identify the cause. High TSH with low free T4 indicates overt hypothyroidism; high TSH with normal free T4 indicates subclinical hypothyroidism; normal values with positive antibodies indicate autoimmune disease without current underactivity. Results are compared against the lab’s own reference range and usually repeated before a diagnosis is settled.
Is a thyroid ultrasound needed to diagnose Hashimoto's?
Not routinely. Blood tests for TSH, free T4 and thyroid antibodies are usually enough. Ultrasound is added when the gland feels enlarged or lumpy, when a nodule is suspected, or when antibodies are negative but the picture still suggests autoimmune disease. On imaging, Hashimoto’s typically shows a darker, uneven gland texture, but the scan does not decide whether treatment is needed.
When is subclinical hypothyroidism treated?
Treatment is weighed case by case after the raised TSH is confirmed on a repeat test. Guidelines consider how high the TSH is, whether antibodies are positive, symptoms, age, heart health and pregnancy plans. Higher persistent TSH levels and pregnancy generally favor treatment; small elevations in older adults are often monitored instead. The decision belongs with the treating clinician, and watchful waiting with scheduled rechecks is a legitimate option.
Can Hashimoto's be present if thyroid antibodies are negative?
Yes. A small proportion of people with Hashimoto’s test negative for both TPO and thyroglobulin antibodies on standard assays. In those cases the diagnosis rests on the pattern of thyroid function tests, the clinical picture and sometimes the characteristic appearance of the gland on ultrasound. Negative antibodies also prompt a look at other causes of an underactive thyroid, such as previous thyroiditis, medicines or iodine imbalance.
Why does my TSH change between tests?
TSH follows a daily rhythm, running higher overnight and early morning, and shifts with illness, recovery, poor sleep and some medicines and supplements. High-dose biotin can distort results on many assays. Small changes within the reference range are normal and rarely meaningful. Consistent timing of blood draws and a full list of what you take help your clinician separate real trends from background noise.
How long after starting thyroid hormone is the blood test repeated?
Usually about 6 to 8 weeks after starting or changing treatment, according to Mayo Clinic, because levothyroxine takes several weeks to reach a steady level in the blood. Adjustments are followed by another check on the same timescale until TSH is in the target range and symptoms are stable. Once settled, most people are tested roughly once a year, sooner if symptoms change or pregnancy occurs.
Should antibody levels be rechecked to see if treatment is working?
Generally no. Antibody levels fluctuate without clear clinical meaning, and no guideline sets a target for lowering them. Once antibodies have confirmed the autoimmune cause, treatment is monitored through TSH and, when needed, free T4. Repeating antibody tests rarely changes a decision and can add anxiety and cost without benefit.
Does Hashimoto's testing change if I am planning a pregnancy?
Yes. Pregnancy raises thyroid hormone requirements and uses lower TSH targets, so clinicians usually check TSH when pregnancy is planned or confirmed and monitor more often through the first half of pregnancy. Women with positive antibodies but normal function are watched more closely because of a higher chance of developing hypothyroidism during pregnancy and thyroiditis after delivery. An obstetric or endocrine team guides the specifics.
What symptoms with a normal TSH should still be investigated?
Persistent fatigue, low mood, hair loss or weight change despite a normal TSH deserve a wider review rather than more thyroid hormone. Common contributors include iron-deficiency anemia, low vitamin B12 or vitamin D, sleep apnea, depression and celiac disease, which occurs more often alongside autoimmune thyroid disease. Your clinician can decide which checks fit your history.
References
- NIDDK (NIH): Hashimoto's Disease
- MedlinePlus: Thyroid Antibodies
- MedlinePlus: TSH (Thyroid-stimulating hormone) Test
- NHS: Underactive thyroid (hypothyroidism)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Happens Inside a Medical Longevity Program? Risk Assessment, Screening and the Plan
A medical longevity program usually involves three stages: a detailed history and physical exam, a set of blood tests and screenings chosen to estimate…
Hyperthyroidism With Heart Disease or in Pregnancy: How Treatment Is Adapted
Hyperthyroidism treatment is adapted in pregnancy and heart disease because the usual options carry different risks in each situation. In pregnancy, radioactive iodine is…

When Is Surgery the Treatment for Cushing Syndrome, and When Is Medication Used First?
Surgery to remove the cortisol-producing tumor is usually the first-line treatment for Cushing syndrome caused by a pituitary or adrenal tumor, because it targets…

Diagnosing Gigantism: Growth Hormone and IGF-1 Tests, Glucose Suppression Testing and MRI
Gigantism is diagnosed by combining a child's growth record with blood tests and imaging. Doctors usually measure IGF-1, a steadier marker of growth hormone…

Adrenalectomy for Pheochromocytoma: How Surgeons Remove the Adrenal Tumor Safely
Pheochromocytoma adrenalectomy is surgery to remove an adrenal gland tumor that overproduces adrenaline-type hormones. Because handling the tumor can trigger dangerous blood pressure swings,…

Diabetes Insipidus: Confusion, Severe Weakness and When Dehydration Needs Urgent Care
Diabetes insipidus becomes a dehydration emergency when the body loses large volumes of dilute urine faster than fluid can be replaced, pushing blood sodium…