

How IUD Placement Works: The Outpatient Visit Step by Step and How Long It Takes
Key Takeaways
- The placement itself takes about five minutes, while the full appointment usually runs 20 to 30 minutes, according to NHS guidance.
- Both hormonal and copper IUDs are more than 99% effective, so the choice between them usually rests on bleeding patterns and preference about hormones.
- A copper IUD protects immediately and can serve as emergency contraception within five days, while a hormonal IUD placed outside the first seven days of a period needs about a week to become effective.
- Expulsion affects roughly 2% to 10% of users, mostly in the first year, which is why string checks and a follow-up visit at 3 to 6 weeks matter.
- Irregular spotting for 3 to 6 months is expected with a hormonal IUD, and heavier periods in the same window are common with a copper one.
- The CDC now asks clinicians to discuss pain and pain-relief options, including local anesthetic, with every patient before an IUD is placed.
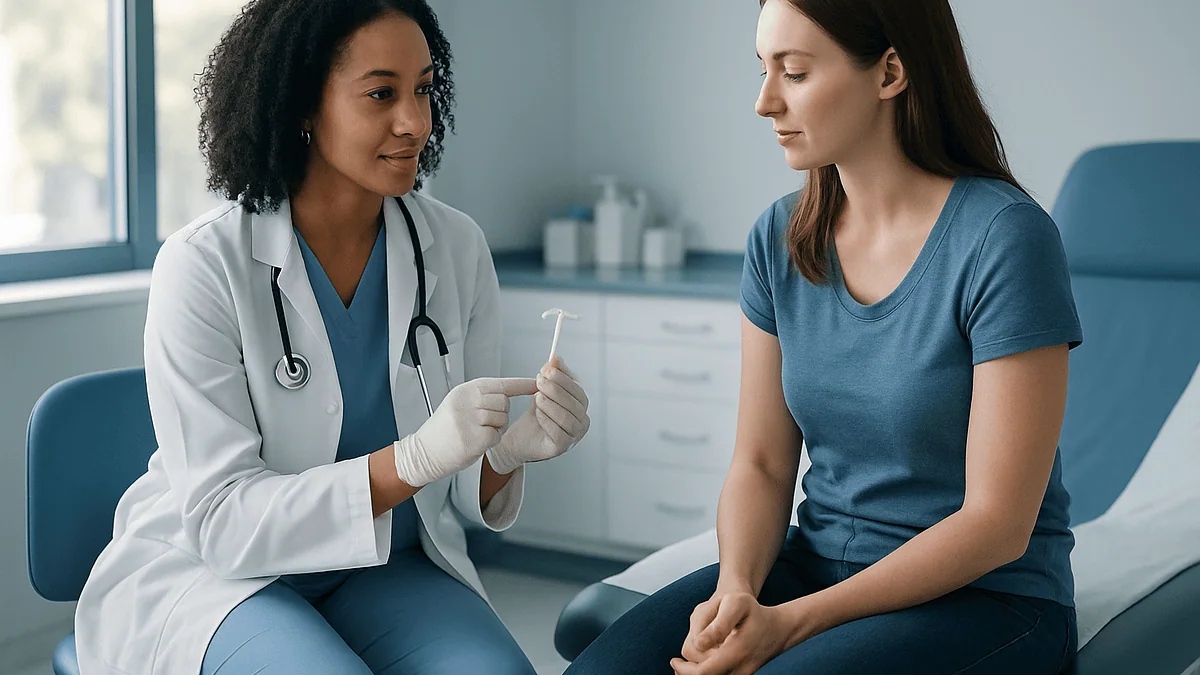
An IUD insertion procedure is a short outpatient visit in which a clinician places a small T-shaped device into the uterus through the cervix using a thin inserter tube. The placement itself usually takes about five minutes, and the whole appointment commonly runs 20 to 30 minutes including checks and questions. Cramping is common afterward and typically eases over the following days.
The appointment reminder arrives, and suddenly a decision that felt abstract at the pharmacy counter becomes very concrete: a chair, a speculum, and a device the size of a paper clip. Most people who book an iud insertion procedure spend far more time wondering about those few minutes than the years of contraception that follow. That imbalance is worth correcting.
An intrauterine device (IUD) is a small, flexible piece of plastic, sometimes wrapped in copper, that sits inside the uterus and prevents pregnancy for years at a time. Fitting one is an outpatient task done in an exam room rather than an operating theater, with no anesthesia machine and no overnight stay.
What follows is the visit laid out in order, with the timings, sensations, and aftercare tied to what mainstream evidence actually shows. Where the research is uncertain, this article says so, and every decision along the way belongs with you and the clinician doing the fitting.
How the IUD insertion procedure works, in plain language
Start with the geography. The uterus is a muscular, pear-shaped organ roughly the size of a fist, and the cervix is its narrow neck, the part that opens into the top of the vagina. An IUD has to travel through the cervical canal, a passage only a few millimeters wide, to reach the uterine cavity where it will stay.
The device itself is T-shaped, about 3 centimeters long, with two flexible arms that fold down inside a slender inserter tube. Once the tip of the tube reaches the top of the uterus, the clinician releases the device, the arms spring open to hold it in place, and the tube is withdrawn. Two thin threads, usually called the strings, trail through the cervix into the vagina so the IUD can be checked and later removed.
There are two families. A hormonal IUD releases a small, steady amount of a progestin (a synthetic form of the hormone progesterone) called levonorgestrel directly into the uterus. It thickens cervical mucus so sperm struggle to pass, thins the uterine lining, and in some users suppresses ovulation. A copper IUD contains no hormones; copper ions create an environment that is toxic to sperm and interferes with fertilization, as MedlinePlus describes.
Neither type requires anything to be cut or stitched. The fitting is a placement, not a surgery, which is why it happens in an ordinary clinic room and why most people walk out on their own afterward. The skill lies in handling a sensitive cervix gently and measuring the uterus correctly so the device sits where it should.
Who an IUD is usually for, and who is usually asked to wait
The short list of people who can have an IUD is far longer than many expect. Guidance from the CDC’s Medical Eligibility Criteria places IUDs in the safest categories for most people of reproductive age, including teenagers, people who have never been pregnant, those who are breastfeeding, and those who want contraception immediately after childbirth or an abortion. The old idea that an IUD is only for someone who has finished having children has not matched the evidence for decades.

Certain situations lead a clinician to postpone or choose another method. A known or suspected pregnancy is the clearest one. A current pelvic infection, such as untreated chlamydia or gonorrhea, is another; placement usually waits until the infection has been treated, because introducing a device could carry bacteria upward. Unexplained vaginal bleeding is generally evaluated first rather than covered over with a new device. Some conditions that change the shape of the uterine cavity, such as large fibroids that distort it, can make a secure fit unlikely.
Type-specific limits matter too. A copper IUD is generally avoided in someone with Wilson’s disease (a rare disorder in which copper builds up in the body) or a copper allergy, and in those whose periods are already very heavy. A hormonal IUD is usually not offered to someone with current breast cancer, because progestin-sensitive tumors may respond to hormones.
None of these is a judgment about a person; each is a risk calculation the clinician makes using published criteria. Someone asked to wait today is often a good candidate a few weeks later, once a test result is back or a treatment is complete. If a method is declined, asking why and what the alternative timeline looks like is entirely reasonable.
Hormonal vs. copper IUD: how the two types compare
Choosing between the two families shapes the years after the visit more than the visit itself. The placement steps are nearly identical; the experience afterward is not. The table below summarizes the points patients most often weigh, using figures from Mayo Clinic, the NHS, and the CDC.
| Feature | Hormonal IUD | Copper IUD |
|---|---|---|
| Active ingredient | Levonorgestrel, a progestin | Copper wire, no hormones |
| How long it can stay | About 3 to 8 years, depending on the device (Mayo Clinic) | Up to 10 years (Mayo Clinic; NHS quotes 5 to 10 years) |
| Effect on periods | Often lighter and shorter; some users stop bleeding; irregular spotting is common in the first 3 to 6 months (Mayo Clinic) | Periods may become heavier, longer, or more painful, especially in the early months (NHS) |
| Starts working | Immediately if placed within the first 7 days of a period; otherwise back-up contraception for 7 days (Mayo Clinic) | Immediately after placement (NHS) |
| Emergency contraception | Not typically used this way | Can be fitted within 5 days of unprotected sex (NHS) |
| Typical effectiveness | More than 99% (NHS) | More than 99% (NHS) |
| Common side effects | Headache, breast tenderness, acne, mood changes, small ovarian cysts in some users | Heavier bleeding, cramping |
Two observations deserve emphasis. First, the effectiveness numbers are essentially a tie, so the decision usually turns on bleeding pattern and a person’s feelings about hormones. Someone who dreads heavy periods often leans hormonal; someone who wants to avoid any hormonal effect accepts the trade-off of heavier bleeding with copper.
Second, the durations in the table are the maximum approved spans, not a requirement. An IUD can be removed at any point, and fertility returns quickly after removal for both types, according to the NHS. The clinician fitting the device will discuss which option matches your history.
Before the appointment: preparing for the IUD insertion procedure
Preparation is lighter than for most medical procedures, but a few things smooth the day. The clinic will want to be reasonably certain you are not pregnant. That may mean a urine pregnancy test on arrival, a conversation about your last period and recent contraception, or both. Under CDC guidance an IUD can be placed at any point in the menstrual cycle when pregnancy can reasonably be excluded, so waiting for a period is not usually necessary.

Screening for sexually transmitted infections may be offered, particularly for anyone at higher risk. Results do not always have to come back before placement; the CDC notes that testing can happen on the same day as fitting, with treatment afterward if a result is positive. Your clinician will explain how that works locally.
Pain relief deserves a conversation in advance rather than in the chair. Ask what options the clinic offers, whether a local anesthetic is available, and whether they suggest taking anything beforehand. This article does not give doses or products; that is a decision for the prescribing clinician, who knows your history.
Practical points help too. Eat normally, since arriving hungry can make lightheadedness more likely. Wear something easy to change, and bring a sanitary pad for spotting afterward. Some people appreciate a companion in the waiting room or a driver, although most are able to travel home alone. Write down your questions; visits move quickly, and the moment to ask is before the speculum, not after.
Finally, know that you can pause or stop at any point. Consent is not a signature on a form but a continuing conversation throughout the visit.
Step by step: what happens during the IUD insertion procedure
The visit follows a predictable order, and knowing the sequence removes much of its mystery. After consent and any last questions, you lie on an exam table with your feet in supports, much as for a routine pelvic exam. A gown or sheet covers you throughout.
The clinician begins with a bimanual exam, feeling the size and position of the uterus with gloved fingers on the abdomen and inside the vagina. This tells them which way the uterus tilts, which matters for guiding the inserter. Next comes the speculum, a smooth, duckbill-shaped instrument that gently holds the vaginal walls apart so the cervix can be seen. It is the same instrument used for a cervical screening test.
The cervix is cleaned with an antiseptic solution. If a local anesthetic is being used, it is applied at this stage as a gel or a small injection into the cervix. The clinician then usually attaches a tenaculum, a slender clamp that steadies the cervix and straightens the canal. Many people feel a sharp pinch here.
A thin, flexible measuring rod called a uterine sound is passed through the cervix to the top of the uterus to check its depth, typically between 6 and 9 centimeters. This step often brings the first real cramp. The IUD, already loaded in its inserter, is set to that depth and passed through the cervix. At the top, the arms are released, the tube is withdrawn, and the device settles into place. Another cramp is common at this moment.
The strings are trimmed to a few centimeters, the tenaculum and speculum are removed, and the active part of the visit is over. You rest on the table for a few minutes before sitting up.
How long does IUD insertion take?
The honest answer separates the placement from the appointment. The placement, from speculum in to speculum out, usually takes about five minutes, according to the NHS, which describes the fitting itself in exactly those terms. Cleveland Clinic gives a similar picture of a procedure measured in minutes rather than the better part of an hour.
The appointment is longer because it includes the conversation before, the exam, the pregnancy test, the fitting, and a short rest. The NHS estimates the whole visit at roughly 20 to 30 minutes. Add check-in and waiting time and most people are in and out of the building within about an hour, though that varies widely with how busy a clinic is.
Several factors can stretch the fitting. A cervix that is tightly closed, a condition sometimes called cervical stenosis, may need extra time and gentle dilation. A uterus that tilts sharply backward or forward can make the angle harder to find. If a clinician uses ultrasound to confirm position, that adds a few minutes. Someone who has never given birth vaginally or who is well past menopause may have a narrower canal, and the clinician will slow down accordingly.
Occasionally a fitting cannot be completed on the day. The cervix may not allow the inserter to pass comfortably, or a person may feel faint and choose to stop. This is not a failure. The clinician will suggest options, which might include returning another day, using a local anesthetic or a different approach, or considering another method entirely.
Plan for a morning or afternoon rather than a lunch break. The minutes on the table are few, but rushing back to a demanding schedule while cramping is rarely pleasant.
Does IUD insertion hurt? What the evidence says about pain relief
Yes for many people, briefly, and to a degree that varies more than almost any other aspect of the visit. Cleveland Clinic and the NHS both describe the sensation as cramping, often compared with a strong period cramp, concentrated at the moments the cervix is clamped, sounded, and passed. Some people report mild discomfort only; others describe intense pain for a minute or two. Those who have not given birth vaginally tend to report more, though individual experience is unpredictable.
For years the standard advice was a simple pain reliever beforehand and encouragement to breathe. The research on pre-medication has been mixed: studies summarized in the CDC’s Selected Practice Recommendations suggest some medicines may help with cramping afterward more than with the pain of placement itself. Reflecting that, the CDC’s updated recommendations ask clinicians to discuss pain and pain management with every patient before placement, including local anesthetic options such as lidocaine applied to the cervix or injected around it.
Which option, if any, is used should be a joint decision with the clinician fitting the device. This article deliberately gives no doses, brands, or instructions to take anything; ask the clinic what they offer and what they suggest for you.
A separate issue is the vasovagal response, a reflex in which stimulation of the cervix slows the heart and drops blood pressure, causing dizziness, sweating, nausea, or brief fainting. It is not dangerous in an exam room but is unpleasant, and it is why clinicians ask you to lie still for a few minutes afterward. Eating beforehand and telling the clinician if you feel lightheaded both help.
Anxiety amplifies pain. Knowing the steps, bringing a support person, and asking the clinician to narrate as they go are low-tech tools with real value.
What to expect after IUD insertion: the first day, weeks, and months
The first few hours often bring cramping that comes in waves, similar to a period, along with light spotting. A heating pad, rest, and a quiet evening are the usual comforts. Many people return to work or school the same day or the next; the NHS notes that most can resume normal activities immediately, though a lighter day is sensible if you have the choice.
Over the first week, cramping usually fades and spotting tapers. Cleveland Clinic describes cramping and irregular bleeding as common for several days after placement. If you use tampons or a menstrual cup, ask your clinician when to resume; practice differs, and some prefer pads for the first days while the cervix settles.
The following months depend on the type. Mayo Clinic notes that irregular bleeding and spotting are common with a hormonal IUD during the first 3 to 6 months, after which periods often become lighter and, for some users, stop altogether. With a copper IUD, the NHS says periods may be heavier and more painful, particularly in the first 3 to 6 months, and may settle somewhat after that.
A follow-up check is usually arranged. The NHS suggests a visit about 3 to 6 weeks after fitting to confirm the device is in place and to talk through any problems. Between visits, you may be shown how to feel for the strings at the top of the vagina after each period.
Sex can resume when you feel comfortable, unless your clinician advises otherwise. Whether you need back-up contraception in the first week depends on the type and timing of placement, so confirm this before leaving the clinic rather than guessing later.
Risks and complications of IUD placement, in plain terms
IUDs are among the most studied contraceptives in use, and their complications are well characterized. Knowing the numbers puts the risks in proportion.
Expulsion, meaning the device slips partly or fully out of the uterus, is the most common problem. Cleveland Clinic puts the chance at roughly 2% to 10%, mostly in the first year and often during a period. A partially expelled IUD may not prevent pregnancy, which is why string checks and the follow-up visit matter.
Perforation, in which the device pushes through the uterine wall during placement, is rare. The NHS estimates it at fewer than 1 in 1,000 fittings. It is more likely when placed soon after childbirth or during breastfeeding, and may require a procedure to retrieve the device.
Pelvic infection is a small risk concentrated in the first 20 days after fitting, according to the NHS, and is linked to bacteria present at the time of placement rather than to the device itself. This is the reason infection screening is offered beforehand.
Pregnancy is uncommon; the NHS describes both types as more than 99% effective. If pregnancy does occur with an IUD in place, the chance that it is ectopic (developing outside the uterus, usually in a fallopian tube) is higher than in a pregnancy without an IUD, so any positive test needs prompt assessment.
Side effects differ by type. Hormonal IUDs may bring headaches, breast tenderness, acne, or mood changes, and small ovarian cysts that usually resolve on their own, as Mayo Clinic notes. Copper IUDs mainly affect bleeding and cramping. Neither type is linked to weight gain in good-quality evidence, though individual experiences vary. Your clinician will weigh these against your own history.
When the IUD starts working, and how you know it is in place
Timing depends on the type and on where you are in your cycle. A copper IUD is effective from the moment it is placed, according to the NHS, which is also why it can serve as emergency contraception when fitted within five days of unprotected sex. Nothing further is needed.
A hormonal IUD works immediately if placed within the first seven days of the start of a period, Mayo Clinic notes. Placed at any other time, it needs about seven days to become fully effective, and back-up contraception such as condoms is advised during that week. Because so much rides on this detail, confirm your own start date with the clinician before you leave.
Knowing the device is still where it belongs is the next question. The clinician trims the strings so they sit just outside the cervix, at the top of the vagina. Many clinics teach patients to feel for them with a clean finger after each period, when expulsion is most likely. Strings that suddenly feel longer, a hard plastic edge at the cervix, or no strings at all are reasons to use back-up contraception and arrange a check.
Strings that cannot be felt are more often curled up out of reach than a sign of expulsion, but only an exam or ultrasound can tell the difference. The follow-up visit at 3 to 6 weeks, as the NHS suggests, is the formal confirmation.
A partner who can feel the strings during sex is common and not a problem; if it bothers either of you, the strings can be trimmed shorter. If a partner feels something hard rather than soft threads, that is worth a check, as the device may have shifted.
Alternatives if an IUD is not the right fit
Choosing a method is a matter of fit rather than ranking, and it helps to see the IUD alongside its neighbors. The CDC’s Medical Eligibility Criteria and the NHS both describe the full menu without favoring one option for everyone.
The contraceptive implant is the closest cousin: a small progestin-releasing rod placed under the skin of the upper arm, effective for several years, and removable at any time. It shares the set-and-forget quality of an IUD without a pelvic procedure, though irregular bleeding is a common trade-off.
The contraceptive injection delivers a progestin every few months. It requires repeat visits and, for some users, brings changes in bleeding and a delayed return of fertility after stopping, which the NHS notes can take up to a year.
Combined hormonal methods, meaning the pill, patch, and vaginal ring, contain estrogen as well as progestin. They offer cycle control and are quickly reversible, but they depend on daily, weekly, or monthly attention and are not suitable for everyone, particularly those with certain clotting or migraine histories. Progestin-only pills avoid estrogen but still require daily use.
Barrier methods such as condoms protect against sexually transmitted infections, something no IUD does, and are often used alongside other methods for that reason. Fertility awareness methods require careful tracking and have higher typical-use failure rates.
For those certain they do not want future pregnancies, sterilization for either partner is a permanent option with its own procedure and recovery. Emergency contraception, whether a copper IUD or a pill, addresses a single episode rather than ongoing needs.
Which of these suits you depends on health history, bleeding preferences, and how you feel about hormones and procedures. The clinician’s job is to lay them out clearly; the choice is yours.
What people often get wrong about IUD placement
Misunderstandings about IUDs travel fast, and several persist despite decades of contrary evidence. Correcting them changes how the visit feels.
Only people who have had children can get one. The CDC and NHS both consider IUDs appropriate for people who have never been pregnant, including adolescents. The cervix may be a little narrower, which can make placement more uncomfortable, but that is a comfort question, not a safety one.
An IUD causes infertility. This belief traces to a device withdrawn in the 1970s and to infections that were poorly understood at the time. Modern devices are not linked to infertility; the NHS notes fertility returns to normal soon after removal.
The IUD works by causing abortions. Both types act before a pregnancy is established, chiefly by preventing sperm from reaching or fertilizing an egg, as MedlinePlus explains. They do not end an established pregnancy.
It can wander around the body. An IUD sits inside the uterus. The rare exception is perforation at the time of placement, fewer than 1 in 1,000 fittings according to the NHS, which is why clinicians measure carefully and check afterward.
The whole visit is an ordeal lasting an hour. The placement takes about five minutes. The build-up is often longer than the event.
You must wait for your period. Placement can happen at any point in the cycle once pregnancy is reasonably excluded, per CDC guidance.
Hormonal IUDs flood the body with hormones. The progestin acts mainly within the uterus; blood levels are far lower than with pills, which is why systemic side effects are generally milder, though not absent.
You need a break between devices. A new IUD can be placed at the same visit an old one is removed. There is no medical reason for a gap.
Questions to ask your care team before and after the visit
A good consultation is a two-way exchange, and clinicians generally welcome specific questions. These are the ones that tend to change decisions or ease the day.
- Which type of IUD do you suggest for me, and what in my history points that way?
- How long would this device stay in, and what happens when it reaches the end of its approved span?
- What pain relief options does this clinic offer during placement, including local anesthetic, and what do you suggest for me?
- Do I need any tests first, and will results delay the fitting?
- From what date will the IUD protect me, and do I need back-up contraception in the first week?
- What bleeding pattern should I expect in the first six months, and what would you consider unusual?
- How will I check that the device is still in place, and when is my follow-up visit?
- What symptoms should prompt me to call you, and what number do I use out of hours?
- If placement cannot be completed today, what are the options?
- How is removal done, and can I have a new device fitted at the same appointment?
After the visit, a second set of questions becomes relevant: whether a particular side effect is expected, how long to give irregular bleeding before revisiting the choice, and whether any new medicines or conditions change the picture. Writing down what you notice in the first three months gives the follow-up appointment something concrete to work with.
The point is not to interrogate anyone. It is to leave the room understanding what was done, when it starts working, and what would signal a problem. Any answer you do not understand deserves a plainer one, and any decision you are not ready to make can wait.
When to call your doctor after an IUD insertion
Cramping for a few days and spotting for a few weeks fall within the expected range. A smaller set of signs means the device or your body needs a look sooner rather than later. Seek urgent care or contact your clinician the same day if you notice any of the following, which the NHS and Cleveland Clinic list among the reasons to be assessed promptly:
- Pain in the lower abdomen that is severe, worsening, or not easing with the measures your clinician suggested, especially in the first few weeks.
- Fever or chills, or vaginal discharge that is unusual in color or smell, which can point to a pelvic infection, most likely in the first 20 days after fitting.
- Bleeding heavy enough to soak through a pad every hour for several hours, or bleeding accompanied by dizziness or fainting.
- Strings that feel noticeably longer or shorter, a hard plastic edge you can feel at the cervix, or strings you can no longer find, all of which can mean the device has shifted.
- A missed period when your periods had been regular, a positive pregnancy test, or symptoms such as one-sided pelvic pain with faintness, because a pregnancy with an IUD in place carries a higher chance of being ectopic and needs same-day assessment.
- Pain during sex that is new, or a partner who feels the device itself rather than soft threads.
- A rash, widespread itching, or difficulty breathing after a copper IUD, which are rare but possible signs of an allergic reaction.
If you cannot feel your strings or suspect the device has moved, use another form of contraception until you have been examined. None of these signs means something has definitely gone wrong; each means someone with a speculum and, if needed, an ultrasound should check. The clinician who fitted the device, or the clinic’s out-of-hours line, is the right first call, and the decisions about what happens next belong with them.
Frequently asked questions
How long does IUD insertion take from start to finish?
The placement itself usually takes about five minutes, according to the NHS, and the whole appointment commonly lasts 20 to 30 minutes once the pre-fitting exam, pregnancy check, and a short rest are included. Allowing about an hour for check-in and waiting is realistic. A tightly closed cervix, a sharply tilted uterus, or the use of ultrasound guidance can extend the fitting by several minutes.
Does IUD insertion hurt, and for how long?
Most people feel cramping, often compared to a strong period cramp, at the moments the cervix is clamped, measured, and passed. The intense part lasts a minute or two; milder cramping commonly continues for several hours to a few days. Pain varies widely between individuals. The CDC recommends that clinicians discuss pain relief options, including local anesthetic, before placement, so raise the question when booking.
What is the typical IUD insertion recovery time?
Most people return to normal activities the same day or the next, as the NHS notes. Cramping generally settles within a few days and spotting within a few weeks, though the bleeding pattern keeps changing for 3 to 6 months depending on the type. A follow-up check about 3 to 6 weeks after fitting confirms the device is in place. Recovery here means adjustment rather than healing from a wound.
What should I expect after IUD insertion in the first week?
Expect wave-like cramping on the first day, light spotting, and gradually easing discomfort over the week. Cleveland Clinic describes irregular bleeding and cramps as common in this period. A heating pad and a quieter schedule help. Ask your clinician about tampon use and whether you need back-up contraception during the first seven days, which depends on the type of IUD and where you were in your cycle.
Can I get an IUD if I have never been pregnant?
Yes. The CDC’s Medical Eligibility Criteria and the NHS both consider IUDs suitable for people who have never been pregnant, including adolescents. The cervical canal may be slightly narrower, which can make placement more uncomfortable, but this is a comfort issue rather than a safety one, and local anesthetic options can be discussed. The belief that IUDs are only for those who have had children is outdated.
When does an IUD start working?
A copper IUD works immediately after placement, according to the NHS. A hormonal IUD is effective at once if placed within the first seven days of the start of a period; placed at any other time, Mayo Clinic advises back-up contraception for seven days. Confirm your own start date with the clinician before leaving, since the answer depends on the type of device and your cycle timing.
How do I know if my IUD has moved or come out?
Warning signs include strings that feel longer or shorter than before, a hard plastic edge at the cervix, strings you cannot find, new pain, or a change in bleeding. Expulsion occurs in roughly 2% to 10% of users, mostly in the first year and often during a period. If you suspect movement, use another form of contraception and arrange an exam; an ultrasound can confirm the device’s position.
Can I have an IUD placed at any time in my cycle?
Yes, provided the clinician can reasonably exclude pregnancy, as CDC guidance states. Waiting for a period is not required. Placement during a period has two minor advantages: the cervix is slightly more open, and a hormonal IUD is effective immediately. Outside that window a hormonal IUD needs about seven days of back-up contraception, while a copper IUD works right away regardless of timing.
Does an IUD protect against sexually transmitted infections?
No. Neither hormonal nor copper IUDs offer any protection against infections such as chlamydia, gonorrhea, or HIV. Condoms remain the only contraceptive method that reduces transmission, and many people use them alongside an IUD for that reason. Screening for infections may be offered before placement, because bacteria present at the time of fitting account for the small infection risk in the first 20 days.
What happens when it is time to remove or replace an IUD?
Removal is usually quicker and less uncomfortable than placement: the clinician grasps the strings with a small instrument and gently pulls, and the arms fold as the device exits. It can be done at any time, not only at the end of the approved span. A new device can be placed in the same visit. Fertility returns to normal quickly after removal for both types, according to the NHS.
References
- MedlinePlus – Intrauterine devices (IUD)
- NHS – Intrauterine device (IUD or coil)
- Cleveland Clinic – Intrauterine Device (IUD)
- CDC – U.S. Selected Practice Recommendations for Contraceptive Use
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Why Hysteroscopy Is Scheduled After Your Period Ends: Timing, Medicines and Preparation
Hysteroscopy is usually scheduled in the days just after a period ends because the uterine lining is at its thinnest then, giving the clearest…

PCOS Myths: Do You Need Cysts to Have It, and Does It Always Affect Fertility?
No. Despite the name, you do not need ovarian cysts to be diagnosed with PCOS. The "cysts" are small, stalled egg follicles, and diagnosis…
How Uterine Fibroids Develop and Grow: Why Size and Location Decide the Care Plan
Uterine fibroids are benign muscle growths that enlarge mainly under the influence of estrogen and progesterone, which is why they usually grow during the…

Hot Flashes: The Physiology and What Measurably Helps
Hot flashes occur when shifting estrogen levels narrow the brain's temperature-regulation zone, so tiny rises in core body temperature trigger sudden flushing, sweating, and…

Is PCOS Genetic, and How Common Is It? Family Risk, Prevalence and Diagnosis
PCOS has a strong inherited component, but no single gene causes it. A large twin study estimated that genetics accounts for roughly 70% of…

What an Ovarian Cyst Feels Like, and Whether You Can Feel It from the Outside
Most ovarian cysts cause no sensation at all and are found by chance on an ultrasound. When a cyst does cause symptoms, people usually…