

How Lip Reconstruction Rebuilds the Lip: Local Flaps, Staged Repair and Restoring Function

Key Takeaways
- A flap keeps its own blood supply while it is moved, which is why it can rebuild all three layers of the lip where a graft cannot.
- Defects of up to roughly a third of lip width are commonly closed directly; larger ones need local flaps, and near-total loss may need tissue from the forearm.
- The Abbe cross-lip flap is a deliberate two-stage operation in which the lips are temporarily joined by a vessel bridge that is divided weeks later.
- The Karapandzic flap preserves the muscle ring and its nerves at the cost of a smaller mouth opening, a trade made to protect the lip's seal.
- Scars keep changing for months and can take up to two years to mature, so symmetry and any revision are best judged late rather than early.
- A pale, dusky or cold flap in the first days is a red flag that needs a same-day call, because the window to rescue its circulation is short.
Lip reconstruction rebuilds a missing part of the lip by moving nearby tissue that keeps its own blood supply, called a flap, from the remaining lip, the opposite lip, or the cheek. Small defects are closed directly; larger ones use local flaps, sometimes in two operations weeks apart. The goals are a mouth that seals, opens, speaks and looks balanced, with details decided by the treating team.
The pathology report was clean, which was the good news. The other news arrived in the mirror: a wedge missing from the lower lip, roughly the width of a fingertip, where a skin cancer had been. Sipping coffee now meant tilting the head. Saying the word paper felt oddly effortful. The question that followed was not really about appearance at all. It was about whether a mouth can be put back together so that it works.
Lip reconstruction flap surgery is the branch of plastic surgery that answers that question, and it has been refining its answers for more than two centuries. The techniques carry surnames from the past, but the reasoning behind them is practical and surprisingly easy to follow.
This explainer walks through how the lip is built, how surgeons decide between a simple closure, a local flap or a staged repair, what the weeks afterward usually look like, and which questions are worth asking before anyone picks up a scalpel.
What lip reconstruction flap surgery actually does
Strip the vocabulary away and the idea is simple. When part of the lip is gone, the surgeon borrows tissue from somewhere close that can spare it, moves that tissue into the gap while it stays attached to its own arteries and veins, and stitches the borrowed area closed. The borrowed tissue is called a flap. Because it arrives with living blood vessels, it heals as lip rather than as a patch.
Why not simply pull the edges together? For small gaps, surgeons do exactly that. The lip is elastic, and a defect that involves roughly a third of its width or less can often be closed directly in a wedge or V shape, a rule of thumb that runs through the surgical literature on this topic. Past that point, pulling harder creates a tight, small mouth and a lip that no longer lines up with its partner.
Flaps solve the problem by redistributing tissue rather than stretching it. A rotation flap swings remaining lip around the corner of the mouth. An advancement flap slides cheek tissue inward. A cross-lip flap borrows a slice of the opposite lip and, in a second operation weeks later, cuts the bridge that fed it. For the largest losses, tissue from the forearm can be transplanted with its vessels reconnected under a microscope, a free flap.
The Mohs technique, a method of removing skin cancer layer by layer with each layer checked under the microscope before the next is taken, is one of the most common reasons a lip needs reconstruction, because it removes only what is necessary and confirms the edges are clear before repair begins, as the Mayo Clinic describes. The reconstruction that follows is where the real craft lies.
Why the lip is harder to rebuild than it looks
A lip is not a flap of skin. It is a three-layer sandwich, and every layer does a job. On the outside is ordinary facial skin, with hair follicles in adults. In the middle is the orbicularis oris, the ring-shaped muscle that lets the mouth pucker, seal and shape sounds. On the inside is mucosa, the moist pink lining that continues into the mouth. Where the skin meets the mucosa runs the vermilion, the red part of the lip, and the sharp line between vermilion and skin is called the white roll because of the way light catches it.

Each of those boundaries matters. A vermilion border that is off by a millimeter or two is visible across a room, because the eye is tuned to faces. A muscle ring that is sewn together out of sequence may look fine at rest and fail when the person tries to whistle, drink from a straw or say the letter b. Mucosa that is pulled outward dries and cracks; skin that is pulled inward looks like a scar on the lip itself.
Landmarks add another layer of difficulty. The upper lip carries the philtrum, the two vertical ridges beneath the nose, and the Cupid’s bow, the double curve at the center of the vermilion. The lower lip is plainer, which is one reason surgeons say lower lip reconstruction is more forgiving. Both lips meet at the commissures, the corners of the mouth, which must stay mobile and symmetrical for the mouth to open fully and smile evenly.
Finally, the lip must stay sensate and competent. Competence is the surgical word for a seal that keeps saliva and food inside. Sensation tells you where the cup is. Rebuild the shape and lose either of those, and the result is a lip that photographs well and frustrates daily.
How surgeons choose a lip flap: the rule of thirds
The decision tree begins with a measurement: how much of the lip width is missing, and which layers. Surgical teaching groups defects into rough thirds, and the table below summarizes how the options line up. The ranges are guides, not laws; a surgeon weighs the person’s age, tissue laxity, prior radiotherapy, dental status and which side of the mouth is involved.
| Option | How it works | Typical defect | Stages | Main trade-off |
|---|---|---|---|---|
| Direct wedge closure | Edges of remaining lip are sewn together in layers | Up to about one third of lip width | One | Slight shortening of the lip |
| Abbe cross-lip flap | Segment of opposite lip swung across on a vessel bridge | Central defects of one to two thirds | Two | Lips are joined for several weeks |
| Estlander flap | Opposite lip tissue rotated around the corner of the mouth | Defects involving the commissure | One, sometimes with later corner revision | Rounded corner of the mouth |
| Karapandzic flap | Remaining lip and cheek rotated around the mouth with nerves and vessels kept intact | Lower lip defects of one to two thirds | One | Smaller mouth opening |
| Cheek advancement (Bernard-Burow type) | Cheek tissue slid inward and lined with mucosa | Large or near-total lower lip loss | One | Reduced sensation and muscle function in the new lip |
| Free tissue transfer | Tissue from the forearm or elsewhere transplanted with microsurgery | Total or near-total lip loss | One long operation, often with revisions | Donor scar, longer stay, no native muscle |
Notice the pattern. As the defect grows, the reconstruction borrows from further away and gives up more function. A direct closure keeps everything native. A Karapandzic flap keeps the muscle ring alive but shrinks the opening. A cheek advancement restores bulk but not much movement. Free flaps rebuild volume and lining while relying on the remaining lip and cheek muscles for whatever seal is possible.
That is why surgeons chase the smallest reconstruction that will genuinely close the gap, and why a discussion about lip reconstruction flap surgery usually starts with a ruler rather than a brochure.
What is a local flap, and how is it different from a skin graft?
People often use the two words interchangeably, and the difference explains most of what follows in this article. A graft is tissue lifted completely free of its blood supply and laid on a wound, where it must survive by soaking up nutrients from the bed beneath it until new vessels grow in. MedlinePlus describes the process in its skin graft entry: the graft is taken from a donor site, placed over the wound and held until it takes. A flap never loses its connection. It is moved while still fed by its own vessels, so it survives from the first minute.
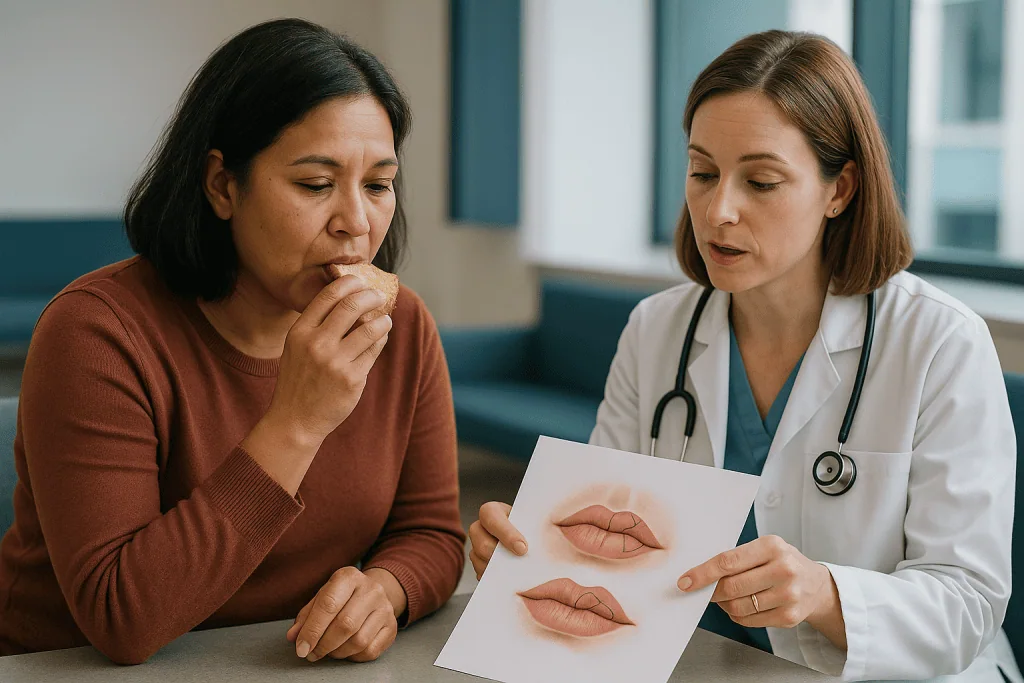
For the lip that distinction is decisive. Grafts are thin, contract as they heal and never contain muscle. A graft can resurface the skin of the lip after a shallow cancer removal, but it cannot rebuild the layered sandwich. Flaps can carry skin, muscle and mucosa together, and they hold their bulk because the blood flowing through them is normal.
Local means the flap comes from tissue immediately next to the defect. Regional means it comes from nearby on the face or neck. Free means it comes from a distant site, its artery and vein cut and then reconnected to vessels in the neck under a microscope. Local flaps dominate lip work because the best match for lip is lip, and the second best is cheek.
The price of moving tissue is a second wound. Every flap leaves a donor site that must also be closed, and every donor site leaves a scar. Skilled planning hides those scars in existing lines: the fold between nose and cheek, the crease beneath the lower lip, the vertical lines of the philtrum. The trade is one visible defect for two well-placed lines, and for most lip defects that trade is worth making.
Abbe flap lip reconstruction: how the cross-lip flap works
The cross-lip flap, usually credited to Sabattini and popularized by Abbe, is the technique that surprises people most when they hear it described. A full-thickness wedge of the healthy lip, skin and muscle and mucosa together, is cut so that it stays attached at one end by a narrow bridge containing the labial artery, the vessel that runs along the inside of each lip. The wedge is then rotated across the mouth and sewn into the defect in the opposite lip. For a period of weeks the two lips are joined by that small bridge.
It sounds alarming; in practice it is the tissue equivalent of borrowing exactly what you need. The upper lip usually has more width to spare than the lower, and a wedge taken from the center of the upper lip can be closed in a line that mimics the philtrum. Meanwhile the defect in the lower lip receives tissue of matching color, thickness and vermilion, including a length of muscle that can be sewn into the ring.
The bridge is divided in a second, shorter operation once the transferred wedge has grown its own blood supply from the surrounding lip. Surgeons time that division by clinical judgment and by testing the flap, and it generally falls within a matter of weeks after the first stage rather than months; the exact timing is set by the operating team. The vermilion is then trimmed and aligned.
The gains are proportion and a lip that moves. The costs are a period of eating and speaking around a tethered mouth, two anesthetics and, sometimes, a slightly numb segment while nerves grow back in. When surgeons discuss Abbe flap lip reconstruction with someone facing a central defect, this is the balance they are weighing.
Karapandzic flap and other options for lower lip reconstruction surgery
The lower lip takes most of the sun and therefore most of the skin cancer, which the NHS notes is the most common form of cancer overall and is strongly linked to ultraviolet exposure. It follows that lower lip reconstruction surgery is the more frequent problem, and surgeons have several ways to approach it.
The Karapandzic flap is a favorite for mid-sized losses because it protects function. The surgeon makes curved incisions around the mouth through skin and mucosa, but deliberately preserves the nerves and vessels running into the orbicularis muscle, then rotates the remaining lip and adjacent cheek inward to meet in the middle. The muscle ring stays intact and innervated, so the reconstructed lip can still purse and seal. The trade is that the mouth becomes smaller, a condition called microstomia, because the circle has been drawn from less material. For people who wear dentures or need wide opening for dental care, that matters, and the surgeon will discuss it beforehand.
The Estlander flap is the cross-lip technique adapted for defects that include the corner of the mouth. Tissue from the opposite lip is rotated around the commissure in a single stage. The corner ends up rounded, and a later small procedure called a commissuroplasty can sharpen it if needed.
For near-total loss, cheek advancement flaps of the Bernard-Burow family bring in large amounts of cheek skin, excising small triangles alongside the nose or chin to allow the tissue to slide. Mucosa from inside the cheek is turned outward to create a new vermilion. These flaps restore bulk and cover but contain little functioning muscle, so competence depends on how much native lip remains.
A staged approach is common: a larger flap first, followed by smaller revisions to sharpen the vermilion line, release tightness or refine the corner.
Why staged repair takes more than one operation
Staged repair means planning two or more operations from the outset rather than treating the second as a failure of the first. In lip work there are three reasons a surgeon might build the plan that way.
The first is blood supply. A cross-lip flap survives initially only through its bridge. Cutting that bridge too early risks the transferred tissue dying; leaving it in place forever is not an option. Waiting for new vessels to grow in from the recipient lip, then dividing the pedicle, is a two-stage sequence by design.
The second is swelling. Freshly moved tissue is puffy for weeks, and a vermilion line trimmed to look perfect on day one can sit unevenly once the swelling settles. Many surgeons prefer to do the major move first, let the tissues declare their final shape, and then make fine adjustments to the vermilion, the white roll or the corner of the mouth when what they see is closer to what will stay.
The third is scar behavior. Scars tighten as they mature, and the NHS notes that a scar can continue to change for up to two years before it settles. A lip that seals well at three months may pull slightly at nine. Rather than over-correcting at the outset, a surgeon may schedule a review and, if needed, a small release such as a Z-plasty, a technique that rearranges a straight scar into a zigzag to lengthen it and hide it in natural lines.
For the person on the receiving end, the practical message is that a second appointment in the operating room is often part of a good plan, not a sign that the first attempt went wrong. Asking early how many stages are anticipated, and what each one is for, removes much of the anxiety that surrounds the word revision.
Who lip reconstruction flap surgery is usually for, and who is asked to wait
Most adults who need lip reconstruction arrive by one of three routes. The largest group has had a skin cancer removed, most often a basal cell or squamous cell carcinoma on the lower lip, frequently by the Mohs technique described by the Mayo Clinic. A second group has had trauma: lacerations, animal bites, burns or avulsion injuries where tissue is lost rather than simply cut. A third group has lip cancer of the mucosa or a tumor that required a larger resection along with treatment of the neck.
Children with cleft lip form a separate pathway. A cleft is a gap in the upper lip present at birth, repaired in infancy in staged operations as the NHS and Cleveland Clinic describe, and refined in later childhood or adolescence. The principles overlap with adult flap surgery, but the timing, team and goals are different, and families are guided through a dedicated program.
Not everyone is operated on immediately. Reconstruction usually waits until the cancer margins are confirmed clear under the microscope, because rebuilding over residual tumor means undoing the work later. An active wound infection is treated first. People who smoke are typically asked to stop well before surgery, because nicotine narrows small blood vessels and flap survival depends on those vessels; surgeons are candid that this is one of the few modifiable risks under a patient’s control.
Uncontrolled diabetes, recent radiotherapy to the area, blood-thinning medication that has not yet been reviewed by the prescribing clinician, and any unstable heart or lung condition can also prompt a pause. In each case the delay is about improving the odds of the flap healing, and the treating team decides when the balance has shifted in favor of going ahead.
Is flap surgery a major surgery? The downsides, honestly
The honest answer is that it depends which flap. A direct closure or a small local flap after Mohs surgery is often done under local anesthetic in an outpatient setting, and people go home the same day. A Karapandzic or cross-lip flap is a more involved procedure, commonly under general anesthesia, though still frequently a short stay. A free flap for total lip loss is unambiguously major surgery: several hours, a hospital stay with hourly checks on the flap’s circulation, and a second wound on the forearm or thigh.
The downsides worth knowing fall into predictable groups.
- Flap problems: partial or complete loss of the moved tissue if its blood supply fails, which is the reason for the emphasis on not smoking and on early monitoring.
- Wound problems: bleeding, infection, or the edges separating, more likely in irradiated tissue or in people with diabetes.
- Shape problems: a notch in the vermilion, a step at the white roll, a rounded corner of the mouth, or asymmetry that becomes more obvious as swelling goes down.
- Function problems: a smaller mouth opening, drooling from an incomplete seal, altered speech, and numbness that can take months to improve as nerves regrow.
- Scar problems: thickened or raised scars, which the NHS notes are more common in some skin types and on areas under tension, and which may need later treatment.
None of these is a reason to avoid reconstruction; leaving a large lip defect open carries its own consequences for eating, speech and skin health. They are reasons to expect a candid conversation about which flap is proposed and why, to plan for the possibility of a revision, and to understand that the goal is a working, balanced lip rather than an invisible repair. The alternative of a graft alone or of healing by secondary intention exists for small superficial defects, and a surgeon should be willing to explain why it does or does not fit.
Lip reconstruction recovery time: what the first days and weeks look like
Recovery unfolds in phases, and knowing the phases helps more than any single number. In the first days the lip is swollen, tight and numb. Bruising around the mouth and chin is expected. Stitches on the skin are usually fine and removed within the first week or two; stitches inside the mouth are often dissolvable. Eating is soft and lukewarm, taken in small amounts, and many people find a spoon easier than a cup. Oral hygiene is gentle but not optional, because the mouth is full of bacteria and the inner lining of the flap is exposed to them.
If a cross-lip flap has been used, this period includes living with the lips joined by the pedicle. Speech is muffled, food goes in at the side of the mouth, and the pedicle must be protected from being pulled. Surgeons typically see people frequently during this window to check the flap’s color and warmth.
Over the following weeks swelling subsides and the shape starts to emerge. Sensation returns unevenly, often as tingling before touch. Activities that strain the mouth wide, such as biting into an apple or a wide yawn, are usually limited until the team gives the go-ahead. Sun protection over the new scar is emphasized, both because scars darken with ultraviolet exposure and because the same sun caused most of the cancers that led here in the first place, a link the NHS spells out plainly.
Scar maturation is the slow phase. The NHS advises that scars are usually red and raised at first, then soften and fade over a period that can extend to two years. Final assessment of symmetry, and any decision about a small revision, is generally left until the scar has settled rather than judged in the early months.
How function comes back: eating, speech and sensation
Ask a reconstructive surgeon what success looks like and few will begin with appearance. They talk about competence, opening and feeling.
Competence returns first when the muscle ring has been repaired in continuity. If the orbicularis was sewn end to end in a direct closure or preserved in a Karapandzic rotation, the lip can usually purse and seal once swelling and pain allow. Where the flap contains no functioning muscle, as with cheek advancement or free tissue, the seal depends on the remaining native lip and on the cheek muscles learning to compensate. Some people notice minor leakage at the corner when drinking, and a speech and language therapist can teach strategies for cup position and swallow timing.
Speech recovers along a similar line. The sounds p, b and m need both lips to meet and release; f and v need the lower lip to touch the upper teeth. Early on these sound soft. As tightness eases and the person adapts, clarity improves. A tethered cross-lip flap distorts speech obviously until it is divided, and people are usually advised to plan around that period.
Sensation is the slowest. Local flaps carried on their own nerves keep feeling from the start; flaps moved from further away are numb until nerves grow in from the edges, a process measured in months rather than weeks. Numbness in the lip is more than a curiosity: it changes how a person judges temperature and the position of a cup, and it raises the chance of an unnoticed bite. Teams usually counsel caution with hot drinks until protective feeling is back.
Mouth opening, finally, is a matter of measuring. If a reconstruction has narrowed the mouth, stretching exercises or a later widening procedure may be offered, particularly when dental work or dentures require it.
What people often get wrong about lip reconstruction
Myths gather around any surgery with a two-hundred-year history, and lip repair has collected its share.
The first is that filler or a graft would have done the job more simply. Filler adds volume to an intact lip; it cannot replace missing skin, muscle and lining. Grafts resurface but do not rebuild layers, and on the lip they contract and mismatch in color. For anything deeper than a shallow skin loss, a flap is the mainstream answer, and it is not the more aggressive option for its own sake.
The second is that the second operation means the first failed. As explained above, cross-lip flaps are designed in two stages, and many surgeons schedule refinements deliberately once swelling and scar have settled. Revision is often part of the plan, not a rescue.
The third is that a smaller mouth after a Karapandzic flap is a mistake. It is a known, expected trade made to keep the muscle ring working, and the surgeon will have judged that a functioning smaller mouth beats a larger one that cannot seal.
The fourth is that numbness is permanent. Sensation frequently returns over months as nerves grow in; persistent numbness can happen, especially with flaps from far away, but early numbness is not the final state.
The fifth is that the scar seen at six weeks is the scar for life. The NHS is explicit that scars change for many months and can take up to two years to mature. Judging the result early leads to unnecessary distress and sometimes to premature requests for revision.
The last is that once the lip is rebuilt, the sun no longer matters. The reconstructed lip and the rest of the face remain at risk, and consistent protection is the single most useful habit to carry forward.
Questions to ask your care team before lip flap surgery
A good consultation is a two-way exchange, and the person facing surgery is entitled to specifics. These questions tend to surface the information that matters most.
- How much of the lip is missing, and which layers? Is this a skin-only defect or full thickness?
- Which reconstruction are you proposing, and what alternatives did you consider? Why this one for my anatomy?
- Is the plan one stage or more? If staged, what happens at each stage and roughly how far apart are they expected to be?
- What will happen to my mouth opening, my ability to seal my lips and my speech, in the short term and once healed?
- Where will the scars sit, and how do you plan to hide them in natural lines?
- What is the chance of needing a revision, and what would that typically involve?
- What could go wrong with the flap, and what signs should I watch for at home in the first days?
- Are there things I should do or stop beforehand, such as smoking, that change how the flap heals? Should any of my regular medicines be reviewed by the clinician who prescribes them?
- What should I eat, how do I clean my mouth, and when can I return to work, exercise and normal chewing?
- Will I see a speech therapist, and is there a dietitian if eating is difficult?
- Who do I call out of hours if something looks wrong?
It helps to bring someone to listen, and to ask whether the team will draw the plan on a photograph or diagram. Most surgeons welcome the request, because a person who understands why the tissue is being moved copes far better with the strange interval when their lips are joined or their mouth feels tight. The decisions remain with the treating team, but they are better decisions when the questions have been asked.
When to call your doctor after lip reconstruction
Most recovery days are uneventful, and the team will describe what normal swelling and bruising look like before discharge. Certain changes, however, should prompt a same-day call to the surgical team or, out of hours, urgent care, because the window to rescue a struggling flap is short.
- The flap turns pale white, dusky purple or blue, or feels cold compared with the surrounding lip; these can be signs its blood supply is compromised.
- Bleeding that soaks through dressings or does not stop with gentle, steady pressure for the time your team specified.
- Spreading redness, increasing warmth, foul-smelling discharge or a wound edge that opens, which can signal infection or separation.
- Fever, chills or feeling generally unwell in the days after surgery.
- Rapidly increasing swelling of the lip, tongue or floor of the mouth, or any difficulty breathing or swallowing; this warrants emergency services rather than a routine call.
- Severe pain that is escalating rather than settling, or pain not controlled by what has been prescribed; the team should be told rather than the dose adjusted at home.
- Accidental pulling on a cross-lip pedicle, a fall onto the face, or any sudden change in the flap’s position.
- New numbness spreading beyond the operated area, or inability to close the eye on the same side, which the team will want to assess.
In the longer term, a reconstructed lip that develops a new lump, a sore that does not heal within a few weeks, a crusted or bleeding patch on the vermilion, or a change in a scar’s texture should be seen without delay, because the skin that produced one cancer can produce another. The NHS advises that any skin change that does not heal or that grows should be checked by a clinician.
When in doubt, call. Reconstructive teams would rather hear about a flap that turned out to be fine than learn too late about one that was not, and the decision about what to do next belongs to them.
Frequently asked questions
What are the downsides of flap surgery on the lip?
The main downsides are a second wound at the donor site, the risk that the moved tissue loses its blood supply, and functional trade-offs such as a smaller mouth opening or temporary numbness. Shape problems like a notch in the vermilion or a rounded corner can appear as swelling settles, and thickened scars are possible. Many of these can be improved with a later revision, which surgeons often plan for.
How long does it take to recover from lip reconstruction surgery?
Early recovery, with swelling, soft food and stitch removal, spans the first weeks, while sensation and scar appearance continue to change for months. The NHS notes scars can take up to two years to mature fully, and surgeons usually wait for that settling before judging symmetry. Your own timeline depends on the flap used and your general health, so ask your team for the range they expect.
How long does flap surgery take to heal?
The skin edges of a well-vascularized flap typically knit within the first couple of weeks, which is when external stitches are removed. Internal healing, return of feeling and softening of the scar take considerably longer. Cross-lip flaps have an added waiting period before the connecting bridge is divided, and that interval is set by the surgeon based on how well the flap has established its new blood supply.
Is flap surgery a major surgery?
It ranges widely. A small local flap after Mohs surgery is often done under local anesthetic as a same-day procedure. A Karapandzic or Abbe flap is more involved and usually performed under general anesthesia with a short stay. A free flap for total lip loss is major surgery lasting several hours with inpatient monitoring. Your surgeon can tell you where your proposed operation sits on that spectrum.
What is an Abbe flap lip reconstruction?
It is a two-stage repair in which a full-thickness wedge of the healthy opposite lip is rotated into the defect while still attached by a narrow bridge carrying its artery. The two lips remain joined for several weeks while the transferred tissue grows new vessels, then the bridge is divided in a second, shorter operation. It restores matching tissue and muscle for central defects of one to two thirds of the lip.
What is a Karapandzic flap and why does it make the mouth smaller?
The Karapandzic flap rotates the remaining lip and adjacent cheek around the mouth while deliberately preserving the nerves and vessels to the lip muscle. Because the same circle of muscle now has to close a gap, the mouth ends up with a smaller opening, a condition called microstomia. Surgeons accept that trade to keep the lip able to purse and seal, and can later widen the opening if dentures or dental care require it.
Will lower lip reconstruction surgery affect my speech?
Usually only temporarily. Sounds that need both lips to meet, such as p, b and m, are softer while the lip is swollen or tight, and a cross-lip flap distorts speech until it is divided. As swelling settles and the muscle recovers, clarity generally improves. If the flap contains little functioning muscle, a speech and language therapist can teach compensating techniques, and your team will say whether that referral is likely.
What is the typical lip reconstruction recovery time before eating normally?
Most people start with soft, lukewarm foods taken in small mouthfuls, and progress as pain and swelling allow over the following weeks. Wide biting, such as into an apple, is usually restricted until the team confirms the repair is strong enough. With a cross-lip flap, eating happens at the side of the mouth until the bridge is divided. Ask your surgeon for the specific stages they want you to follow.
Can a skin graft or filler be used instead of a flap for the lip?
For shallow, skin-only losses a graft can resurface the area, but grafts contract, mismatch in color and cannot rebuild muscle or the inner lining. Filler only adds volume to an intact lip and cannot replace missing tissue. For any full-thickness defect, a flap that brings skin, muscle and mucosa together is the mainstream option, and your surgeon can explain why one is or is not suitable for your case.
Why did my surgeon ask me to stop smoking before flap surgery?
Nicotine narrows small blood vessels, and a flap survives entirely on the blood flowing through vessels of exactly that size. Smoking raises the chance that part or all of the moved tissue dies, that wound edges separate and that the scar heals poorly. Stopping well in advance is one of the few risk factors a person can change themselves, which is why teams emphasize it so firmly.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Buccal Fat Removal Recovery Week by Week: Liquids, Soft Foods and When Cheeks Settle
Buccal fat removal recovery time is usually measured in weeks for the visible part and months for the final shape. Most people manage daily…
How a Combined Neck and Face Lift Is Performed: Incisions, Deeper Tissue Work and Closure
A combined neck and face lift is one operation, usually under general anesthesia and typically lasting two to four hours or longer. The surgeon…

Do Facial Augmentation Results Last? Implants vs Fat Transfer Over the Years
Facial augmentation results vary by method. Solid cheek and chin implants are designed to stay in place indefinitely and usually keep their shape for…

Preparing for Face Aesthetics Surgery: Blood Tests, Anesthesia Review and Medicine Changes
Preparing for facial surgery usually means a pre-assessment visit where blood tests check clotting, blood count and kidney function, an anesthesia review covers your…

Supporting Someone After a Neck and Face Lift: Drains, Dressings and the First Days Home
In the first days after a neck and face lift, a helper's main tasks are keeping the head raised, emptying and recording any drains,…

Facial Augmentation With Fat Transfer or Implants: Which Option Suits Which Face?
Facial fat transfer uses a person's own fat, taken by gentle liposuction and injected into the face, to add soft, natural-looking volume; facial implants…