

How OCT and Fundus Examination Map Macular Disease Before Any Treatment Is Planned
Key Takeaways
- OCT builds a cross-section of the retina from reflected infrared light, measuring layers and fluid in micrometers without touching the eye or using radiation.
- A dilated fundus exam covers the whole retina in color and stereo, catching peripheral tears, hemorrhages and diabetic changes that a central macular scan cannot show.
- Fluorescein angiography remains the test that proves active leakage, but OCT now detects and tracks most fluid-driven macular disease without the dye or the needle.
- The National Eye Institute describes dry age-related macular degeneration as the more common form and as typically progressing slowly over years, so drusen on a scan are a reason to monitor, not a forecast.
- OCT thickness numbers matter mainly as comparisons with your own earlier scans on the same machine; a single reading is not a diagnosis.
- New bending of straight lines or a central blank patch on an Amsler grid warrants a same-day call to the eye team, because fluid can appear between scheduled scans.
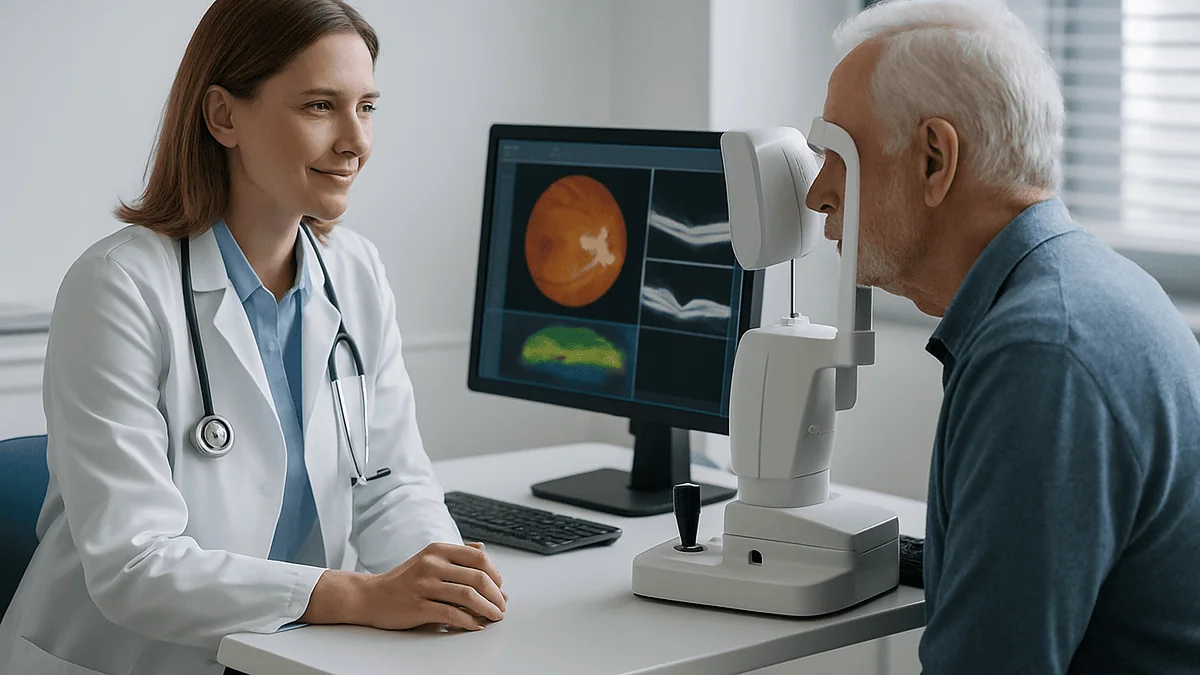
Optical coherence tomography (OCT) and a dilated fundus examination together map macular disease by showing the retina in two complementary ways: the fundus exam gives the clinician a direct, colored, wide view of the back of the eye, while OCT adds a painless cross-sectional scan that measures retinal layers and any fluid in micrometers. Dye angiography is added when blood-vessel leakage needs confirming. The treating team then decides on monitoring or treatment.
The chair tilts back, the room dims, and a small red target blinks somewhere in the dark. “Look straight at the light and try not to blink,” the technician says. Fifteen seconds later, a cross-section of your retina is glowing on the screen beside you, its layers stacked like sediment in a riverbank. Nobody has touched your eye. This is the moment many people first encounter OCT macular disease diagnosis, and it usually arrives at an anxious time: after words in a letter have started to bend, or a routine check found something the optometrist wanted “looked at properly.”
What happens on that screen matters enormously, because no clinician plans treatment for a macular problem without first mapping it. The map has to answer specific questions. Is there fluid, and in which layer? Is tissue thinning or thickening? Are new blood vessels growing where they should not?
This explainer walks through how the two core tools, the dilated fundus exam and the OCT scan, answer those questions, where dye angiography still fits, and what the results can and cannot tell you.
What actually happens at a macular imaging visit
Most visits follow a predictable rhythm, even when the reason for them feels anything but routine. A vision check comes first: reading letters on a chart with each eye separately, often followed by an Amsler grid, which is a square of straight lines that reveals distortion when a person looks at the central dot. Many clinics also measure eye pressure and take a brief history of when the symptoms started and whether one eye or both are affected.
Dilating drops usually follow. These widen the pupil so the clinician and the cameras can see the whole macula, the small central area of the retina responsible for sharp, detailed vision. The drops sting for a moment, then blur near vision and make daylight uncomfortable for several hours, according to Mayo Clinic’s patient guidance on macular degeneration testing. Bringing sunglasses and arranging a lift home is sensible.
Imaging happens while the drops take effect. A technician positions your chin and forehead against a machine, asks you to fixate on a target, and captures the OCT scan. A color fundus photograph may be taken at the same sitting, and in some clinics an autofluorescence image, which uses the retina’s own faint glow to highlight stressed or missing cells.
Then comes the part that no machine replaces. The ophthalmologist examines the dilated fundus directly, using a slit lamp and a handheld lens, or a headset with a bright light. The fundus is simply the inside back surface of the eye: the retina, its blood vessels, the optic nerve head and the macula. Only after seeing the tissue with their own eyes and reviewing the scans does the clinician sit down and explain what the map shows.
How does OCT macular disease diagnosis actually work?
Optical coherence tomography sounds forbidding, but the principle is close to ultrasound with light instead of sound. A beam of near-infrared light enters the eye, bounces off each retinal layer at a slightly different depth, and returns to the machine. By comparing the returning light with a reference beam, the scanner works out how far each reflection traveled. Stack thousands of those depth readings side by side and you have a cross-section, a slice through the retina that shows its layers in order.
Nothing touches the eye. The light is not felt, and because the measurement is optical, the scale is extraordinarily fine: distances are recorded in micrometers, thousandths of a millimeter. That resolution is the whole point. The macula is thin, and the changes that matter in early disease are thinner still. A pocket of fluid, a small blister of lifted retinal pigment cells, a membrane wrinkling the surface: each has a distinctive shape in cross-section that a clinician learns to recognize.
Modern scanners take dozens of parallel slices across the macula in a few seconds and combine them into a thickness map, colored like a weather chart. Warm colors mark thicker retina, cooler colors mark thinner. Software compares the map against a database of healthy eyes and, crucially, against the same eye’s previous scans. This is where OCT macular disease diagnosis becomes monitoring: two scans months apart can show whether a swelling has grown, shrunk or stayed the same.
One limitation deserves an early mention. OCT shows structure, not function. A retina can look anatomically calm while vision is poor, or slightly swollen while a person reads fine print comfortably. The scan is one voice in the conversation, not the verdict.
What does an OCT scan show that a photograph cannot?
A color fundus photograph is a portrait of the retinal surface. It captures the pattern of drusen, the yellowish deposits under the retina that Mayo Clinic describes as an early sign of age-related macular degeneration, along with hemorrhages, pigment changes and the shape of blood vessels. What it cannot show is depth. A photograph tells you something is there; it does not tell you which layer it occupies or how thick the tissue beneath it has become.
OCT answers the depth question directly. Clinicians look for several things on the cross-section:
- Fluid within the retina, which appears as dark, rounded spaces between the layers and often signals leaking vessels or swelling.
- Fluid beneath the retina, a shallow dark band lifting the photoreceptors off their supporting cells.
- Elevation of the retinal pigment epithelium, the single layer of dark cells that nourishes the photoreceptors, which can dome upward over deposits or new vessels.
- Thinning or loss of the outer retinal layers, the structural footprint of advanced dry degeneration.
- A wrinkled or tented inner surface, the signature of an epiretinal membrane, a sheet of scar-like tissue on the retina.
- A full-thickness gap at the center, the appearance of a macular hole.
The thickness map adds a quantitative layer. Where a photograph offers “the macula looks swollen,” OCT offers a measured thickness at the center and in each surrounding zone, and a change from the last visit. That number is not an outcome or a promise, but it is a repeatable observation, and repeatability is what turns a single diagnosis into a tracked condition.
Neither image is complete alone. The photograph gives context and breadth; the scan gives depth and measurement. Together they form the map the treating team works from.
Why the dilated fundus exam still matters
It can feel odd to sit through a high-resolution scan and then have a doctor peer into your eye with a lens, as if the technology had not just done that job. It has not, quite. The dilated fundus exam covers ground that a macular scan, by design, leaves out.
Field of view is the first reason. A standard macular OCT captures a square a few millimeters across, centered on the fovea, the pinpoint at the heart of the macula. The retina extends far beyond that. A tear at the edge, a tumor, an area of poor blood supply in diabetes, or a cluster of hemorrhages away from the center can all change the plan, and none of them appear on a central scan. During the fundus exam the clinician sweeps the whole retina, asking you to look up, down, left and right.
Color and texture come second. Blood looks red, exudates look yellow-white, old scarring looks pale and pigment looks brown or black. OCT renders everything in shades of reflectivity, which is superb for structure and poor for telling a fresh hemorrhage from an old one. The eye of an experienced examiner still reads those cues faster than any algorithm.
Movement and depth perception are the third reason. Through a slit lamp, the retina is seen stereoscopically, so a subtle elevation or a vitreous strand tugging on the surface becomes visible in a way a flat image cannot convey.
Finally, the exam is a safety net for the scan. If the OCT was captured slightly off center, or the patient blinked, the fundus exam catches what the software missed. Guidance from the NHS on age-related macular degeneration still describes examination of the back of the eye as the starting point, with scans and photographs as the tools that build on it.
Fluorescein angiography vs OCT: when dye still earns its place
Fluorescein angiography is the older test, and for decades it was the gold standard for proving that abnormal vessels were leaking under the macula. A yellow dye is injected into a vein in the arm, and a camera photographs the retina as the dye flows through its vessels over several minutes. Leaky or abnormal vessels glow and blur; blocked ones stay dark.
The trade-off is that it involves a needle, a dye and time. MedlinePlus notes that fluorescein commonly turns the skin faintly yellow for a few hours and the urine dark orange for up to a day, and that nausea and, rarely, allergic reactions can occur. Indocyanine green angiography works on the same principle with a different dye that shows the deeper choroidal vessels, the blood supply beneath the retina.
OCT changed the balance. Because fluid and vessel-related lifting of the retinal layers show clearly on a cross-section, many clinicians can identify a wet, or neovascular, process on OCT and then track its response without repeated dye tests. A newer variant, OCT angiography, maps blood flow by detecting movement between rapid repeat scans, producing a vessel map with no injection at all. It is excellent at showing that vessels exist, and less reliable at showing that they leak, which is precisely what the dye tests do best.
So the question is rarely fluorescein angiography vs OCT as an either-or. Mayo Clinic lists both among the tests used to evaluate wet macular degeneration. In practice, OCT is the workhorse for detection and follow-up; dye angiography is reserved for cases where the diagnosis is genuinely uncertain, where leakage needs confirming before an invasive step, or where the pattern of leakage will change what is done. Your clinician’s decision to order or skip the dye reflects that specific question, not a shortcut.
Which macular conditions get mapped this way?
The same two tools are used across a wide family of conditions, but the map looks different for each. Knowing the names helps when the report arrives.
Age-related macular degeneration is the most common reason for a macular scan in older adults. The NHS notes it usually first affects people in their 50s and 60s. The dry form, which the National Eye Institute says accounts for the large majority of cases, shows drusen and, over time, thinning of the outer retina. The wet form shows fluid, hemorrhage and lifted pigment epithelium caused by new vessels growing from the choroid beneath.
Diabetic macular edema is swelling from leaking capillaries damaged by prolonged high blood sugar. OCT shows the intraretinal fluid and measures the thickening; fundus exam and wider imaging assess the rest of the retina for the broader picture of diabetic retinopathy.
Retinal vein occlusion is a blocked vein, and the macula often swells as a result. Here the fundus exam reveals scattered hemorrhages that OCT cannot color, while OCT quantifies the edema.
Macular hole is a small gap at the very center, which the NHS explains can cause blurred and distorted central vision. OCT confirms the hole, measures its width and shows whether the vitreous gel is still pulling on it, details that shape the discussion about surgery.
Epiretinal membrane, sometimes called cellophane maculopathy, is a fine sheet of tissue that contracts on the retinal surface. Central serous chorioretinopathy is a pocket of fluid under the retina, more common in younger adults and linked to stress and corticosteroid exposure. Inherited dystrophies, inflammatory conditions and drug-related toxicity each leave their own patterns too.
In every case the principle holds: the fundus exam frames the problem, OCT measures it, and the combination lets the team name it with confidence before anything else is decided.
How the tests compare at a glance
People often leave clinic with three or four test names and no sense of how they fit together. The table below sets out what each one involves and the question it is best at answering. None of these replaces another; they are chosen to suit the question of the day.
| Test | What it involves | What it shows best | Typical role |
|---|---|---|---|
| Amsler grid | Looking at a grid of lines, one eye at a time | Distortion or missing patches in central vision | Home self-monitoring between visits |
| Dilated fundus exam | Drops to widen the pupil; clinician views the retina with a lens and light | Whole-retina view, color, hemorrhage, peripheral findings | Foundation of every assessment |
| Color fundus photography | Flash photograph of the back of the eye | Baseline record of drusen, pigment and vessels | Documentation and comparison over time |
| OCT | Chin rest, fixation on a target, infrared light; no contact | Retinal layers, fluid location, thickness in micrometers | Diagnosis and repeat monitoring |
| OCT angiography | Same machine, longer scan; no dye | Presence and shape of blood-flow networks | Detecting abnormal vessels without injection |
| Fluorescein angiography | Dye injected into an arm vein; timed photographs | Active leakage and blocked circulation | Confirming uncertain or complex cases |
| Fundus autofluorescence | Blue-light photograph of the retina’s natural glow | Areas of stressed or missing pigment cells | Mapping dry degeneration and dystrophies |
Two points are worth drawing out. First, only one test in this list involves a needle, and it is the one most likely to be omitted when OCT has already answered the question. Second, the humble grid at the top is the only tool you take home, which is why clinicians spend time teaching it. A change noticed on the grid is often what prompts the next scan.
Who is usually scanned, and who is usually asked to wait?
Not everyone with a macular concern is scanned on the day, and not everyone scanned is treated. Understanding the sorting logic helps make sense of an appointment that ends with “we’ll see you again in a while” rather than a plan.
Same-day or urgent imaging is usually arranged when symptoms have changed recently: new distortion of straight lines, a sudden central blur or blank patch, or a rapid drop in reading vision in one eye. These are the patterns that can indicate fluid or bleeding, and the NHS advises seeking prompt advice when vision changes suddenly. Referral from an optometrist who has spotted hemorrhage or suspicious elevation on a routine check falls into the same category.
Planned, non-urgent imaging suits people with known early or intermediate dry degeneration, stable diabetic changes, a small epiretinal membrane that is not bothering them, or a family history that warrants a baseline. For these people the OCT is a reference point, and the interval between scans is set by the treating team according to the findings and the guidelines they follow.
Being asked to wait is not the same as being dismissed. Watchful monitoring is an active decision, taken because the current map shows no feature that treatment would change. The NHS notes, for example, that some small macular holes can close on their own, and that surgery is not automatically offered for every hole. Early dry degeneration has no injection or operation that alters it, so monitoring and lifestyle discussion are the plan, not a placeholder for one.
A few groups need extra care around the tests themselves. Very dense cataract or bleeding in the vitreous can degrade an OCT image. People with a history of severe allergy, kidney impairment or pregnancy will have a longer conversation before any dye test. Someone who cannot hold steady fixation may need repeated attempts or a different imaging protocol. None of these prevents a diagnosis; they change how the team reaches it.
Diagnosis, prognosis and how accurate the map really is
Clinicians often describe three kinds of diagnosis. A clinical diagnosis rests on symptoms and examination alone. An imaging or test-based diagnosis adds objective measurements, which is where OCT sits. A differential diagnosis is the shortlist of conditions that could explain the picture, narrowed as each result comes in. A macular workup moves through all three in a single afternoon: the story and Amsler grid, the fundus exam, the scan, and then the shortlist reduced to one name.
Diagnosis and prognosis are different questions. Diagnosis names what is present now. Prognosis is the expected course over time, and it depends on factors the scan cannot see, including how a condition behaves in a given person and how they respond to any treatment. An OCT can show that fluid exists; it cannot promise how a particular eye will look next year. The National Eye Institute describes dry degeneration as typically progressing slowly over years and the wet form as capable of changing faster, but those are population patterns, not individual predictions, and clinicians are careful to say so.
How accurate are the tests? OCT is highly sensitive to structural change and very reproducible, which is why it dominates monitoring. Yet it has known failure modes. A blink, poor fixation or a cataract can produce artifacts that mimic thinning or swelling. Automated layer detection can mis-trace a boundary. OCT angiography can display “projection” shadows of surface vessels onto deeper layers and misreport them as new growth. Fluorescein angiography, meanwhile, can be hard to interpret when scarring or pigment blocks the view.
This is why the fundus exam and the scan are read together, and why clinicians repeat a scan rather than act on a single surprising result. Accuracy in this field comes less from any one instrument and more from cross-checking one view of the retina against another.
How the imaging shapes the treatment conversation
Once the map is drawn, it becomes the shared reference for every decision, and each finding points toward a different kind of discussion. The choices themselves belong to the treating team and the person in the chair; what follows describes the mechanisms they may explain, not recommendations.
When OCT shows fluid from abnormal new vessels, as in wet age-related degeneration, diabetic macular edema or vein occlusion, the conversation often turns to anti-VEGF medicines. VEGF stands for vascular endothelial growth factor, a protein that signals blood vessels to grow and leak. Medicines in this class block that signal and are given as injections into the eye by an ophthalmologist. Mayo Clinic describes them as a mainstay for the wet form, and it is the OCT that shows whether the fluid is responding on follow-up scans. Corticosteroid implants, which reduce inflammation-driven leakage, are another class discussed for some swelling patterns.
When OCT shows a full-thickness macular hole or a membrane distorting the surface, the discussion is surgical. The NHS explains that vitrectomy, removal of the vitreous gel with peeling of the membrane, is the operation offered for a hole that is affecting vision, sometimes with a gas bubble that requires head positioning afterward. The scan’s measurement of the hole’s width and the presence of traction feed directly into that conversation.
When the map shows dry degeneration with drusen and thinning, there is currently no injection or operation that reverses the loss, and the discussion centers on monitoring, smoking cessation, diet, and whether a specific antioxidant supplement formulation studied in NIH-sponsored trials applies to that stage. Whether it does is a decision for the clinician who has seen the scan.
Whatever the path, the same principle applies: the imaging shows the team where they are starting from, and repeat imaging shows whether the plan is doing what they hoped. Any change to a medicine, including stopping one, is for the prescribing clinician to decide.
What the following days and weeks usually look like
The imaging itself leaves little trace, but the visit has an afterlife worth planning for.
The first few hours are about the drops. Pupils stay wide, near vision is blurred and bright light is uncomfortable. Mayo Clinic advises that this typically lasts several hours, so reading, driving and screen work are best postponed until the evening. If a dye test was done, MedlinePlus notes that the skin may look faintly yellow for a few hours and urine may be dark orange for up to a day, which is expected and harmless. Mild nausea can occur during or shortly after the injection.
Results often arrive the same day. Because OCT displays instantly, many clinicians walk through the scan on screen before you leave. If the images are being reviewed by a specialist elsewhere, or if further tests were ordered, a letter or follow-up call is the usual route. Asking how and when you will hear is a fair question at the end of the visit.
The following weeks depend on what the map showed. For monitoring, the team sets an interval for the next scan and typically asks you to use an Amsler grid at home, checking one eye at a time in good light and reporting any new bending, blurring or missing patches rather than waiting for the booked date. For a treatment plan, the OCT becomes the yardstick: scans are repeated at intervals decided by the clinician, and changes in fluid or thickness guide what happens next. Timelines vary widely between conditions and between people, so any figure you are given is a typical range, not a commitment.
One practical habit helps more than most: keep your own record of which eye was affected, what the scan showed and what the next step is. Macular care often runs for years, and a clear personal log makes every future visit shorter and more useful.
What people often get wrong about OCT macular disease diagnosis
Misunderstandings about these tests cause needless worry, and occasionally cause people to skip a scan that mattered. A few deserve correcting.
“The scan uses radiation.” It does not. OCT uses low-power infrared light, similar in energy to a television remote. There is no X-ray, no radioactivity and no known cumulative harm from repeated scans, which is why it can be used as often as monitoring requires.
“If the OCT is normal, my macula is fine.” A normal central scan rules out many things, but not everything. Early dry changes can be subtle, functional problems can exist without structural change, and the scan covers only the central retina. The fundus exam and the vision tests are part of the answer for a reason.
“A thicker or thinner number on the report is a diagnosis.” Retinal thickness varies between healthy people and between machines. The number is meaningful mainly in comparison with your own earlier scans on the same device, interpreted by someone who has also looked at the images.
“Drusen mean I will lose my sight.” Drusen are common with age, and the National Eye Institute describes the dry form as usually progressing slowly over years, with only some people developing the wet form. Finding drusen is a reason for monitoring, not a prediction.
“The dye test is dangerous.” Fluorescein angiography carries real but uncommon risks, mostly nausea and mild allergic reactions, with severe reactions being rare according to MedlinePlus. It is used less often now because OCT answers many questions without it, not because it has become unsafe.
“Once treatment starts, scans stop.” The opposite is true. For fluid-driven conditions, OCT is how the team judges whether a medicine is doing its job, so scanning continues for as long as treatment does.
Questions to ask your care team
A good consultation leaves you able to explain your own scan to a family member. These questions help get there, and none of them is too basic to ask.
- Which part of my macula is affected, and in which layer did you see the change?
- Is there fluid on the scan? If so, is it within the retina or beneath it, and what does that suggest about the cause?
- Do you consider this dry or wet, active or stable, and what on the images led you to that view?
- Was the scan quality good enough to be confident, or is a repeat needed to rule out artifacts?
- Do I need a dye test, and if not, what has already answered the question it would have addressed?
- What is the working diagnosis, and what else was on the list before today’s tests narrowed it?
- If we are monitoring rather than treating, what specific change on a future scan would alter that plan?
- How often will scans be repeated, and how will I be told the results?
- Should I use an Amsler grid at home, and what exactly should prompt me to call before my next appointment?
- Is my other eye affected or at risk, and is it being imaged too?
- Are there lifestyle factors, such as smoking, blood sugar or blood pressure, that would change the course of this condition?
- Can I have a copy of the scan images or the report for my own records?
Bringing a companion who can take notes is worth more than any single question. Dilated eyes make writing difficult, and the volume of information at a first macular visit is considerable. If the answers include figures such as thickness measurements or time intervals, ask what those mean for you specifically; the same number can carry a different meaning in different conditions, and your clinician is the only person who can translate it for your eye.
When to call your doctor
Macular conditions can change between scheduled visits, and the whole point of home monitoring is that you notice before the calendar does. Contact your eye care team promptly, the same day where possible, if you notice any of the following, especially in an eye that has already been diagnosed with a macular problem:
- Straight lines, such as door frames, text lines or the Amsler grid, that have newly started to bend, wave or break.
- A new dark, gray or blank patch in the center of vision in one eye.
- A sudden drop in reading vision or in the ability to recognize faces that was not there the previous day.
- Colors that appear noticeably washed out or different between the two eyes.
- A sudden shower of new floaters, flashes of light, or a shadow or curtain spreading across vision, which can signal a retinal tear or detachment and needs urgent assessment.
- After any eye injection or dye test: increasing pain, marked redness, discharge, worsening vision or sensitivity to light, which can indicate infection or inflammation.
- After a dye test: hives, swelling of the face or lips, wheezing or difficulty breathing, which require emergency care.
The NHS advises seeking advice urgently for sudden changes in vision rather than waiting for a routine appointment, and most retina services have a pathway for exactly this. If you cannot reach your usual team, an emergency department or urgent eye clinic can arrange assessment.
Less urgent but still worth reporting at your next contact: gradual difficulty with fine print in good light, more glare than before, or a sense that one eye is “lazy” when the other is covered. These are not emergencies, but they are the kind of slow drift that a repeat OCT is designed to measure, and mentioning them may bring a scan forward.
Every decision about what these signs mean, and what to do about them, rests with the clinicians who can examine your eye. Calling early gives them the chance to look while there is most to see.
Frequently asked questions
What is an OCT scan for macular degeneration and does it hurt?
An OCT scan for macular degeneration is a painless imaging test that uses infrared light to produce a cross-section of the macula, showing drusen, fluid and thinning in each retinal layer. You rest your chin on the machine and look at a target for a few seconds per eye. Nothing touches the eye and no dye is used. The main discomfort of the visit comes from the dilating drops, which blur near vision and increase light sensitivity for several hours.
What are the three main types of diagnosis in eye care?
Clinicians usually describe clinical, test-based and differential diagnosis. A clinical diagnosis rests on symptoms and examination, such as distortion on an Amsler grid and findings on a dilated fundus exam. A test-based diagnosis adds objective measurements, which is the role OCT and angiography play. A differential diagnosis is the shortlist of conditions that could explain the picture, narrowed with each result until the team can name one condition with confidence.
What is the difference between a diagnosis and a prognosis for macular disease?
A diagnosis names the condition present now, such as wet age-related macular degeneration or a macular hole, based on examination and imaging. A prognosis describes the expected course over time, which depends on the type of disease, its stage, individual factors and any response to treatment. OCT is excellent at diagnosis and monitoring but cannot predict an individual’s future vision, which is why clinicians describe typical patterns rather than promises.
How accurate are OCT and fundus examination for detecting macular disease?
OCT is highly sensitive to structural change and very reproducible, which is why it is the standard tool for detecting fluid and tracking it over time. Its limits come from image quality: blinks, poor fixation, cataract and software errors can create artifacts. The dilated fundus exam adds color and a wide view that OCT lacks. Accuracy in practice comes from reading both together and repeating a scan before acting on a single unexpected result.
Why do I still need dilating drops if the OCT machine can see my retina?
Dilation widens the pupil so the clinician can examine the entire retina, not just the central few millimeters that a macular OCT captures. It also improves the quality of fundus photographs and, in many cases, the OCT itself. Peripheral tears, scattered hemorrhages and diabetic changes away from the center all influence the plan and are only reliably seen through a dilated pupil. The drops wear off over several hours, according to Mayo Clinic.
Is fluorescein angiography still necessary if I have already had an OCT?
Often it is not, but sometimes it is. OCT shows fluid and structural change well enough that many wet macular conditions can be diagnosed and followed without dye. Fluorescein angiography is still used when the diagnosis is uncertain, when active leakage needs confirming before an invasive step, or when the pattern of leakage would change the plan. Your ophthalmologist orders it to answer a specific question that OCT has not settled.
What does fluid on an OCT scan mean?
Fluid on OCT appears as dark spaces within or beneath the retina and indicates that vessels are leaking or that the retina’s normal pumping of fluid has been overwhelmed. Common causes include wet age-related macular degeneration, diabetic macular edema, retinal vein occlusion and central serous chorioretinopathy. Its location and amount help the clinician identify the cause and, on repeat scans, judge whether a condition is stable, improving or worsening.
Can OCT show macular disease before I notice any symptoms?
Yes, and this is one of its strengths. OCT can reveal drusen, early pigment changes, small pockets of fluid or a thin epiretinal membrane before vision is noticeably affected, which is why optometrists sometimes refer people who feel their eyes are fine. Early detection does not automatically mean treatment; many early findings are monitored rather than treated. It does give the team a baseline against which future change can be measured.
How often should OCT scans be repeated for macular disease?
There is no single answer, because the interval depends on the condition, its stage and whether treatment is under way. People with stable dry degeneration may be scanned at longer intervals, while those receiving injections for fluid are typically scanned at each visit to judge response. The treating team sets the schedule according to the findings and the guidelines they follow, and any new symptom on an Amsler grid should prompt an earlier scan.
Does a macular OCT check the whole retina?
No. A standard macular OCT covers a small square centered on the fovea, the very center of the macula. Wider-field OCT protocols exist, but the periphery of the retina is still primarily assessed by dilated fundus examination and, where needed, wide-field photography. This is why a normal macular scan does not rule out problems elsewhere, and why the examination and the scan are always interpreted together rather than either one alone.
References
- NHS: Macular hole
- MedlinePlus: Fluorescein angiography
- National Eye Institute (NIH): Age-Related Macular Degeneration
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Vitrectomy Recovery With a Gas Bubble: Face-Down Positioning, Drops and Weekly Milestones
After a vitrectomy with a gas bubble, the surgeon usually asks you to hold a specific head position, often face down, for several days…
Low Pressure, Leaks and Infection After Glaucoma Surgery: What Your Team Watches For
After glaucoma surgery, care teams watch most closely for eye pressure that drops too low (hypotony), a leak from the small drainage blister called…

Farsightedness Myths: Does Reading in Dim Light or Screen Time Make It Worse?
No. Reading in dim light and spending long hours on screens can tire the eyes and cause temporary blur or headache, but neither changes…

Keratoconus Treatment Ladder: Lenses, Cross-Linking, Rings and When Transplant Is Discussed
Keratoconus treatment options form a ladder rather than a single choice. Glasses and soft lenses help early; rigid gas-permeable, hybrid or scleral lenses restore…

Can a Contact Lens Get Lost Behind Your Eye? Contact Lens Myths, Corrected
No. A contact lens cannot travel behind your eye. The conjunctiva, the thin membrane lining the inside of the eyelids, folds back onto the…

Recovering From Myopia Laser Surgery: Screens, Makeup, Swimming and the Follow-Up Calendar
Myopia laser surgery recovery is usually quick for daily life and slow for fine detail. Patient guides describe most people returning to work and…