

How PCOS Affects Ovulation and Metabolism Over Time and Why Regular Monitoring Matters

Key Takeaways
- PCOS is diagnosed when two of three features are present: irregular ovulation, excess androgens, or polycystic-looking ovaries, so cysts are not required.
- Insulin resistance drives much of the hormonal picture by pushing the ovary to make androgens and lowering the liver protein that keeps testosterone inactive.
- The CDC reports that more than half of women with PCOS develop type 2 diabetes by age 40, making glucose monitoring the most consequential long-term check.
- Fewer than nine periods a year leaves the uterine lining exposed to estrogen without progesterone, raising the risk of endometrial overgrowth over time.
- Cycles often become more regular in the forties because of ovarian aging, not because the metabolic side of PCOS has resolved.
- Around a 5 percent reduction in weight, where excess weight is present, is the modest target the NHS cites for improving symptoms.
PCOS affects the body through two linked problems: higher androgen levels that stall ovulation, and insulin resistance that slowly strains metabolism. Over time, irregular or absent ovulation can affect fertility and the uterine lining, while insulin resistance raises the risk of type 2 diabetes, abnormal cholesterol and high blood pressure. Regular monitoring of cycles, blood sugar, lipids and blood pressure lets a care team catch and manage these changes early.
She is 27, keeps a period tracker app the way other people keep a diary, and has just scrolled back through eighteen months of entries. Four cycles. Not four missed pills or four stressful months, four periods in a year and a half. Her mother says she was the same and it “sorted itself out.” Her sister says it was thyroid. The internet, as always, says everything at once.
Polycystic ovary syndrome, or PCOS, sits in exactly this fog. It is common, affecting roughly one in ten women of reproductive age, yet it is frequently diagnosed years after the first clues appear. Part of the reason is that the condition rarely announces itself with a single dramatic symptom. It works quietly, in two systems at once.
Understanding how PCOS affects the body means following both threads: what happens in the ovary each month, and what happens in muscle, liver and fat tissue over years. The second story is the one most often left untold, and it is the one that explains why a check-up matters even when the periods feel like the only problem.
How PCOS affects the body: what is actually happening
PCOS is an endocrine condition, meaning it involves the glands and hormones that carry chemical messages around the body. The name is a historical accident. Many women with PCOS do not have cysts at all; the small fluid-filled sacs seen on ultrasound are immature egg follicles that paused before release. Some women with clear PCOS have ovaries that look entirely ordinary on a scan.
The condition is diagnosed when at least two of three features are present: irregular or absent ovulation, signs of excess androgens (hormones such as testosterone that all bodies make, but which are higher than expected here), and ovaries that appear polycystic on ultrasound. The NHS uses this two-of-three approach, and so do most international guidelines.
What ties these features together is a feedback loop. The pituitary gland in the brain releases luteinizing hormone, or LH, in a pattern that is often too fast and too frequent in PCOS. The ovary responds by making more androgens. At the same time, many women with PCOS have insulin resistance, meaning the body’s cells respond sluggishly to insulin, so the pancreas compensates by producing more of it. Insulin itself nudges the ovary toward androgen production and lowers a liver protein that normally keeps testosterone bound and inactive.
The result is a self-reinforcing circuit: more insulin, more free androgen, more disrupted ovulation. Nothing in this loop is dramatic on any given day, which is why PCOS so often looks like an inconvenience rather than a condition. Seen over a decade, the picture is different. The same circuit that skips periods also shapes how the body stores fat, handles sugar and carries cholesterol.
Why ovulation stalls: the follicle traffic jam
In a typical cycle, a cohort of follicles begins to grow, one becomes dominant, matures and releases its egg around mid-cycle. The others quietly dissolve. This selection process depends on a delicate rise of follicle-stimulating hormone, FSH, relative to LH.
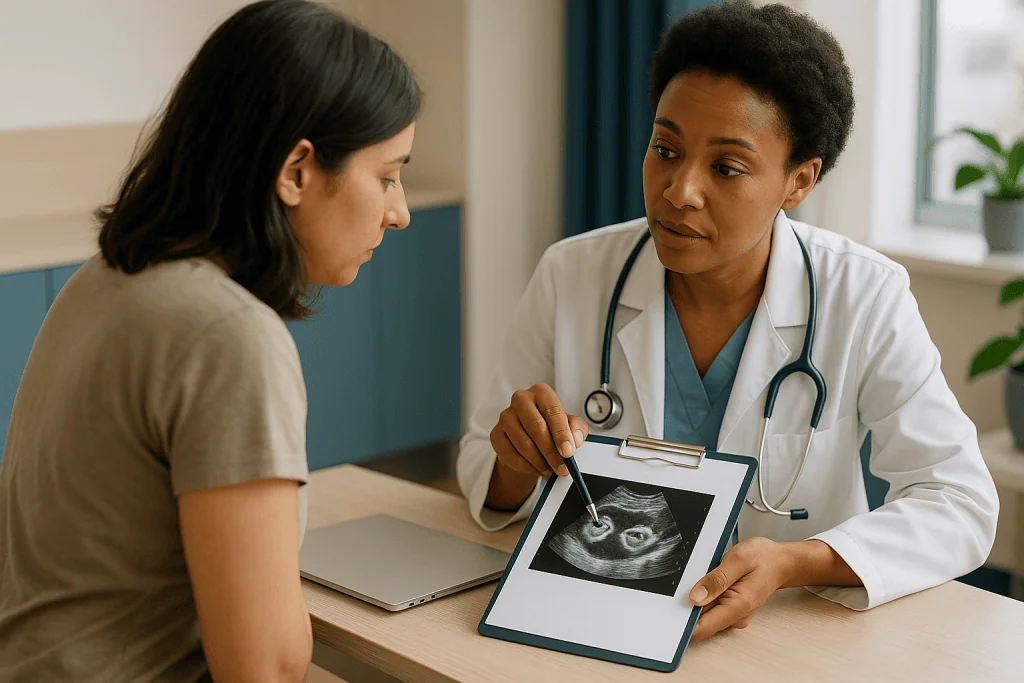
In PCOS, the ovary contains more small follicles than usual, and the hormonal environment does not favor one of them clearly enough. Excess androgen and insulin encourage many follicles to start growing but interfere with the final push to dominance. The Mayo Clinic describes these as follicles that fail to release eggs regularly. Picture a roundabout with a dozen cars edging forward and none pulling out.
When ovulation does not happen, the second half of the cycle, when progesterone would normally rise, never arrives. Progesterone is the hormone that matures the uterine lining and then triggers its shedding as a period. Without it, the lining keeps thickening under the influence of estrogen alone. Periods become unpredictable: sometimes absent for months, sometimes unusually heavy when they finally arrive.
Guidelines generally consider fewer than nine periods a year, or cycles longer than 35 days, as a sign that ovulation is not occurring regularly. Cycles that are shorter than 21 days can also signal disruption.
Ovulation in PCOS is irregular rather than impossible. Many women with the condition ovulate spontaneously some months and not others. That matters for two reasons. It means that contraception is still needed if pregnancy is not wanted, a point the NHS makes explicitly. It also means that tracking cycles over many months, rather than judging from a single one, gives a care team far more useful information than any single blood test taken on a random day.
PCOS and insulin resistance: the engine behind the hormones
Insulin’s job is to unlock cells so glucose can move from the bloodstream into muscle, liver and fat for use or storage. In insulin resistance, the lock is stiff. The pancreas responds by producing more insulin to get the same job done, and for years it usually succeeds. Blood sugar looks normal on a routine test while insulin levels run quietly high.
This compensation is exactly what makes the metabolic side of PCOS easy to miss. The CDC notes that insulin resistance is common in PCOS regardless of body size, and that the condition is a recognized risk factor for type 2 diabetes. Women with PCOS who are at a lower weight can have insulin resistance too, though it is more pronounced when weight is higher.
High insulin does not stay in its lane. In the ovary it acts alongside LH to stimulate androgen production. In the liver it suppresses sex hormone-binding globulin, the carrier protein that keeps testosterone inactive, so a greater fraction of circulating testosterone is free to act on skin and hair follicles. This is the biological route from a metabolic problem to acne, oilier skin and coarser hair growth on the face or body.
Insulin resistance also shifts where fat is stored, favoring the abdomen. Fat around the organs is metabolically active and releases signals that worsen insulin resistance further, another loop within the loop.
There is no single “PCOS test” for insulin resistance in everyday care. Clinicians usually rely on fasting glucose, HbA1c (a measure of average blood sugar over roughly three months) or a glucose tolerance test, interpreted alongside blood pressure, waist measurement and cholesterol. The point is to see the direction of travel before it becomes diabetes.
How PCOS affects the body across the twenties, thirties and forties
PCOS is often described as a reproductive condition, but the reproductive and metabolic threads change places in importance as the years pass.

In the teens and twenties, the visible features tend to dominate: irregular periods, acne that persists beyond the usual age, hair growth in a pattern more typical of men, and sometimes thinning of scalp hair. These features are driven mainly by androgens and are the reason many women first seek help. Insulin resistance is already present in a large share of women at this stage, but it rarely produces symptoms.
In the thirties, fertility questions frequently come to the front. Irregular ovulation makes conception less predictable, though the NHS is clear that most women with PCOS can become pregnant, with or without treatment. This is also the decade when metabolic markers begin to drift for some women: a fasting glucose creeping upward, triglycerides rising, blood pressure edging into the higher-than-ideal range.
In the forties and beyond, the pattern often inverts. Cycles may become more regular as the pool of follicles naturally shrinks, which can feel like improvement. Androgen levels tend to fall gradually. The metabolic story, however, keeps moving. The CDC reports that more than half of women with PCOS develop type 2 diabetes by age 40, a striking figure that has nothing to do with periods and everything to do with the decades of insulin resistance that preceded it.
The practical lesson is that what needs watching changes with age. A twenty-year-old and a forty-five-year-old with the same diagnosis are, in effect, being monitored for different things. A good long-term plan reflects that shift rather than treating PCOS as a fixed list of symptoms.
Does PCOS get worse with age? What the evidence actually shows
The honest answer is that some parts tend to ease and others tend to progress, and the two can be mistaken for each other.
The reproductive features often soften. As women approach their late thirties and forties, the number of small follicles in the ovary declines, LH patterns become less erratic, and many report that cycles settle into something closer to regular. Acne and excess hair growth may also lessen as androgen production falls. The Cleveland Clinic notes that symptoms can change and that the condition persists across the lifespan rather than disappearing at menopause.
The metabolic features generally do not follow that gentler path. Insulin resistance tends to persist and, if weight increases or activity falls, to deepen. Blood pressure and cholesterol naturally rise with age in the general population, and PCOS adds to that baseline. Whether this translates into a measurably higher rate of heart attack or stroke is still debated in the research literature; the risk factors are clearly elevated, while the long-term event data are less consistent. Saying so plainly is better than overstating either way.
There is also a psychological dimension that does not simply age out. Anxiety and depression are more common among women with PCOS than in the general population, and body-image distress linked to skin and hair changes can persist. Mental health is a legitimate part of PCOS care, not an afterthought.
So PCOS does not uniformly get worse. It changes shape. The woman who no longer worries about her cycle may be the very person who most benefits from a glucose test and a blood pressure check, precisely because the visible reminder has faded.
PCOS long-term effects: diabetes, blood pressure, cholesterol and the uterine lining
Four longer-term consequences are well established enough to appear in mainstream guidance, and each has a clear mechanism.
Type 2 diabetes is the most documented. Years of insulin resistance can exhaust the pancreas’s ability to compensate, and blood glucose finally rises. The CDC and the MedlinePlus summary both list diabetes as a principal long-term risk. Gestational diabetes, the form that appears in pregnancy, is also more common.
Blood pressure and cholesterol tend to move in an unfavorable direction. Insulin resistance is associated with higher triglycerides, lower HDL (the protective cholesterol fraction) and higher blood pressure, a cluster sometimes called metabolic syndrome. These are the classic upstream contributors to cardiovascular disease.
Sleep apnea, in which breathing repeatedly pauses during sleep, is more frequent in PCOS, particularly when weight is higher. It worsens insulin resistance and blood pressure, so it feeds back into the metabolic loop. Loud snoring, gasping in sleep or unrefreshing sleep are worth mentioning to a clinician.
The uterine lining deserves particular attention. Without regular ovulation there is no regular progesterone, so the endometrium is exposed to estrogen for long stretches without being shed. Over years this raises the risk of endometrial hyperplasia, an overgrowth of the lining, and of endometrial cancer. The NHS notes this risk and it is a central reason clinicians pay attention to how many periods a woman has each year, even when fertility is not a goal. Ensuring the lining sheds at intervals is protective, and it is one of the more actionable pieces of PCOS care.
None of these outcomes is inevitable. They are risks that monitoring is designed to catch early, while they are still numbers on a page rather than diagnoses.
Who is usually diagnosed, and who is usually asked to wait
Diagnosis is straightforward in principle and messy in practice, because the features of PCOS overlap with ordinary life and with other conditions.
A clinician will typically ask about menstrual history over at least the past year, look for physical signs of androgen excess, and order blood tests. Those tests usually include testosterone, sometimes with SHBG so that free androgen can be estimated, along with thyroid function, prolactin and other hormones to rule out conditions that mimic PCOS. An ultrasound may or may not be needed; the NHS notes that if irregular cycles and androgen excess are both present, a scan is not strictly required to make the diagnosis.
Adolescents are the group most often asked to wait, and for good reason. Irregular periods are normal in the first two to three years after a first period, acne is near-universal, and ovaries in the teenage years often appear polycystic on ultrasound without any disease being present. Applying adult criteria too early produces false diagnoses and unnecessary anxiety. Most guidance recommends holding off on a firm PCOS label until several years past the first period, while still treating troublesome symptoms and keeping an eye on the pattern. Clinicians sometimes describe this as being “at risk of PCOS,” a deliberately provisional phrase.
Women using hormonal contraception are another group where timing matters. These medicines regularize bleeding and suppress androgens, so they mask the very features being assessed. A clinician may suggest a period off contraception before testing, or may make a working diagnosis from history alone.
Finally, PCOS is a diagnosis of exclusion in the sense that other causes of the same picture must be considered. Thyroid disorders, high prolactin and rarer adrenal conditions can produce similar symptoms and need different care.
What regular monitoring for PCOS actually involves
Monitoring sounds ominous. In practice it is a handful of measurements repeated at sensible intervals, most of them already part of ordinary preventive care. What changes with PCOS is the starting age and the frequency, because the risks begin earlier.
| What is checked | Why it matters in PCOS | Typical approach |
|---|---|---|
| Cycle pattern | Fewer than nine periods a year raises endometrial risk | Self-tracking, reviewed at each visit |
| Blood glucose or HbA1c | Insulin resistance progresses silently toward diabetes | At diagnosis, then every one to three years depending on results and risk factors |
| Blood pressure | Rises earlier than in the general population | At every visit |
| Lipid profile | Triglycerides and HDL often unfavorable | At diagnosis, then periodically |
| Weight and waist | Abdominal fat worsens insulin resistance | Tracked over time, framed neutrally |
| Mood and sleep | Depression, anxiety and sleep apnea more common | Asked about routinely; screened if concerns |
The intervals in the table reflect the general approach described by the CDC and by mainstream clinical guidance; the exact schedule is set by the treating team based on individual results. Someone with normal glucose and no family history of diabetes may be retested less often than someone whose fasting glucose is already borderline.
Two things are not routinely monitored, and patients sometimes ask why. Repeated ultrasounds add little once the diagnosis is made, because the ovarian appearance does not track risk. Repeated testosterone levels are likewise rarely useful unless symptoms change sharply.
The value of monitoring is cumulative. A single HbA1c is a snapshot; five of them over a decade are a trajectory, and it is the trajectory that tells a clinician when to act.
What the first weeks and months after a PCOS diagnosis usually look like
The diagnosis itself often arrives as relief tangled with worry: relief that the irregular periods and stubborn skin finally have a name, worry about the words “diabetes” and “fertility” that tend to follow.
The first appointment after diagnosis usually establishes a baseline. That means the blood tests in the monitoring table if they have not already been done, a blood pressure reading, and a frank conversation about which symptoms matter most to the individual. PCOS care is unusually goal-dependent. Someone hoping to conceive in the next year, someone who wants clearer skin, and someone who mainly wants to protect long-term health will be offered different paths from the same diagnosis.
Over the following weeks, most people are asked to keep tracking cycles, since ovulation patterns emerge over months rather than days. If lifestyle changes are part of the plan, this is when they begin, and it is worth knowing the realistic timescale. The NHS notes that a modest weight reduction of around 5 percent can improve symptoms in those who carry excess weight; changes in cycle regularity, when they come, typically appear over several months rather than the first few weeks.
If a medicine is started, the timeline depends on its class. Hormonal contraceptives regularize bleeding within the first cycles and improve acne over roughly three to six months. Insulin-sensitizing medicines act more gradually on metabolic markers. Ovulation-inducing medicines are used cycle by cycle under monitoring. All of these decisions, and the follow-up intervals, sit with the prescribing clinician.
A follow-up visit in the first few months is common, less to expect dramatic results than to check that the plan fits, that side effects are tolerable, and that the person feels heard.
How lifestyle changes act on ovulation and metabolism
Lifestyle advice in PCOS is often delivered as a throwaway line, which is a shame, because the mechanism behind it is precise and worth understanding.
Physical activity improves insulin sensitivity directly. Contracting muscle takes up glucose through pathways that do not depend on insulin, and regular training increases the number of glucose transporters in muscle cells. Lower insulin means less stimulation of ovarian androgen production and more SHBG from the liver, so free testosterone falls. This is why exercise can, over months, improve cycle regularity in some women even without weight change. The Johns Hopkins overview places lifestyle measures at the foundation of PCOS management for exactly this reason.
Dietary pattern matters more than any single food. Guidelines do not endorse one named diet for PCOS. What the evidence supports is a pattern that moderates rapid glucose spikes and supports a healthy weight where relevant: whole grains over refined ones, adequate protein and fiber, fewer sugar-sweetened drinks. Claims that specific supplements or eliminating whole food groups “treat” PCOS outrun the evidence, and the NIH Office of Dietary Supplements is a sober place to check what has actually been studied.
Sleep and stress are not soft extras. Short or fragmented sleep worsens insulin resistance within days in experimental studies, and untreated sleep apnea can undo the benefit of other efforts.
Where weight reduction is appropriate, the NHS figure of around 5 percent is the one to hold onto. It is a modest, achievable target, and it is associated with improvements in ovulation and insulin markers. Weight is a lever in PCOS, not a moral scorecard, and for women at a lower weight it is not the relevant lever at all.
Medicines for PCOS: what each class does and how long it typically takes
No medicine treats every feature of PCOS, so prescribing follows the goal. What follows describes mechanism and typical timelines only; whether any of these is appropriate is a decision for the treating clinician.
Combined hormonal contraceptives supply estrogen and a progestin. They suppress LH, which lowers ovarian androgen production, raise SHBG, and ensure the uterine lining is shed regularly. Bleeding becomes predictable within the first cycles; skin and hair changes take longer, commonly three to six months, because hair follicles cycle slowly. They are not suitable for everyone, particularly those with certain clotting or migraine histories, which is why the assessment matters.
Progestin-only approaches can be used to induce a withdrawal bleed at intervals for endometrial protection when combined pills are not wanted or not safe.
Metformin, an insulin-sensitizing medicine originally developed for diabetes, reduces glucose production by the liver and improves insulin action in tissues. In PCOS it is used off-label in many countries to improve metabolic markers and, in some women, cycle regularity. Effects on glucose measures appear over weeks to months; effects on ovulation are more modest and variable. Gastrointestinal side effects are common early on.
Ovulation induction, used when pregnancy is the goal, relies on letrozole or clomifene, generic medicines that alter estrogen signaling so the pituitary releases more FSH and a dominant follicle emerges. They are used under monitoring, cycle by cycle, and carry a raised chance of twins.
Anti-androgens such as spironolactone block testosterone at the receptor and can reduce excess hair growth over many months. They require reliable contraception because of risk to a developing fetus.
Each of these has alternatives and trade-offs. The Mayo Clinic’s treatment overview is a fair summary of how clinicians weigh them.
What people often get wrong about PCOS
“If I don’t have cysts, I don’t have PCOS.” The name misleads. Ovarian appearance is one of three criteria, and diagnosis can be made without it. Conversely, polycystic-looking ovaries alone, especially in young women, do not make the diagnosis.
“PCOS means I can’t get pregnant.” The NHS states that most women with PCOS are able to conceive with or without treatment. Ovulation is irregular, not absent, which is also why contraception remains necessary when pregnancy is not wanted.
“Only women with a higher weight get PCOS.” The condition occurs across all body sizes. Insulin resistance is present in many women with PCOS at lower weights too, and their metabolic monitoring is just as relevant.
“It’s a hormone problem, not a sugar problem.” It is both, and the metabolic side is the one with the longest reach. The CDC’s finding that over half of women with PCOS develop type 2 diabetes by 40 is the clearest correction to this myth.
“My periods came back, so it’s gone.” Cycles often regularize with age as follicle numbers fall. That reflects ovarian aging, not resolution of insulin resistance. PCOS persists through menopause.
“A supplement or a special diet will fix it.” No supplement has evidence strong enough to be recommended as a treatment in mainstream guidelines. Some have small studies with mixed results. Presenting them as effective would be presenting an unproven therapy as proven, and that is a disservice.
“It’s caused by something I did.” PCOS has strong genetic and developmental components. The WHO fact sheet describes it as a condition of unclear cause with familial clustering. Lifestyle influences its expression; it does not create it.
Questions to ask your care team about how PCOS is affecting you
A good consultation is a two-way exchange, and the right questions turn a list of results into a plan. These are the ones that tend to unlock the most useful conversations.
- Which of the three diagnostic features do I have, and how confident are you in the diagnosis? Has anything that mimics PCOS been ruled out?
- What do my glucose, HbA1c, cholesterol and blood pressure results show today, and how often should each be rechecked given my results and family history?
- How many periods a year should I be aiming for to protect the uterine lining, and what are my options if I fall below that?
- If I want to conceive in the next year or two, what should we do now, and what would a fertility pathway look like if it comes to that?
- If I do not want pregnancy, which contraceptive approaches fit my health history, and which would you avoid?
- Are there lifestyle changes with realistic evidence for my situation, and what timescale should I expect before noticing any difference?
- Should I be screened for sleep apnea, depression or anxiety, and how would that happen?
- Which of my symptoms will likely change with age, and what will need closer attention as I get older?
- Who coordinates my long-term monitoring, and what should prompt me to come back sooner than the scheduled review?
Writing the answers down during the visit is not overkill. PCOS care unfolds over decades, and the notes from an early appointment often become the baseline a clinician refers back to years later. It also helps to bring the cycle tracker, since a year of real data beats memory every time.
When to call your doctor
Most of PCOS care happens on a schedule. A few situations should move the conversation forward without waiting for the next planned review.
Contact your care team promptly if you have gone more than three months without a period and are not pregnant or using a contraceptive that stops bleeding, or if bleeding becomes very heavy, prolonged beyond a week, or occurs between periods. These patterns can signal an overgrown uterine lining and warrant assessment.
Seek advice soon if you notice rapid onset or sudden worsening of androgen-type changes, such as a deepening voice, marked increase in facial or body hair over a few months, or significant scalp hair loss. Fast change is not typical of PCOS and may point to a different cause that needs its own evaluation.
Symptoms of high blood sugar deserve a same-week appointment: unusual thirst, passing urine far more often, unexplained weight loss, blurred vision or recurrent infections.
Treat the following as urgent, meaning emergency services or the nearest emergency department: severe lower abdominal pain, particularly with faintness or one-sided pain, which can indicate ovarian torsion, a ruptured cyst or ectopic pregnancy; chest pain, sudden breathlessness, or a swollen, painful calf, especially in anyone using combined hormonal contraception; and thoughts of self-harm or a mental health crisis, which are medical emergencies in their own right.
Low mood, anxiety or distress about body changes that persist for more than a couple of weeks are also a reason to reach out, not a reason to wait. Support is part of standard PCOS care.
When in doubt, call. Every decision about what to test, what to change and what to start or stop rests with the clinicians who know your history, and they would rather hear from you early than late.
Frequently asked questions
How does PCOS affect the body over the long term?
Over years, PCOS mainly affects the body through persistent insulin resistance and irregular ovulation. The metabolic thread raises the risk of type 2 diabetes, unfavorable cholesterol and higher blood pressure, while infrequent ovulation increases the chance of endometrial overgrowth. Sleep apnea and mood disorders are also more common. None of these is inevitable, and regular monitoring exists to catch shifts early.
Do PCOS symptoms change over time?
Yes. Reproductive and skin symptoms often ease with age as follicle numbers and androgen levels fall, and cycles may become more regular. Metabolic features tend to persist or progress, so the focus of care usually shifts from periods and acne in the twenties toward glucose, blood pressure and cholesterol in the forties and beyond.
What is the link between PCOS and insulin resistance?
Insulin resistance means cells respond sluggishly to insulin, so the pancreas produces more. High insulin stimulates the ovary to make androgens and lowers a liver protein that keeps testosterone bound, raising free androgen. It also favors abdominal fat storage. This is why a metabolic problem produces skin, hair and cycle changes, and why glucose monitoring is central to PCOS care.
Does PCOS get worse with age?
It changes rather than uniformly worsening. Cycle irregularity and androgen-related symptoms often improve toward the forties, but insulin resistance and cardiovascular risk factors typically continue to rise, partly with ordinary aging and partly because of PCOS itself. The condition does not end at menopause, so metabolic checks remain relevant even when periods are no longer a concern.
Can you have PCOS without cysts on your ovaries?
Yes. Diagnosis requires two of three features, and ovarian appearance is only one of them. A woman with irregular ovulation and signs of excess androgens meets the criteria without a scan. Conversely, polycystic-looking ovaries alone, especially in adolescents, do not confirm PCOS, because many young women have that appearance without the condition.
Can women with PCOS get pregnant?
Most can. The NHS states that the majority of women with PCOS are able to conceive with or without treatment. Ovulation is irregular rather than absent, which can make timing less predictable. When help is needed, clinicians may discuss lifestyle measures or ovulation-inducing medicines, with the plan tailored to the individual by the treating team.
Why do I still need contraception if I have PCOS?
Because ovulation in PCOS is unpredictable, not impossible. Many women ovulate in some cycles and not others, and there is no reliable way to know which month is which without testing. The NHS explicitly advises that contraception is still needed to prevent pregnancy. Some hormonal contraceptives also help protect the uterine lining and reduce androgen effects.
How often should someone with PCOS have blood tests?
It depends on results and risk factors, and the treating team sets the schedule. Mainstream guidance generally suggests glucose or HbA1c at diagnosis and then roughly every one to three years, more often if results are borderline or diabetes runs in the family. Blood pressure is usually checked at every visit, and lipids periodically.
What are the long term effects of PCOS on the uterus?
Without regular ovulation there is little progesterone, so the uterine lining thickens under estrogen without being shed. Over years this raises the risk of endometrial hyperplasia and endometrial cancer. Ensuring the lining sheds at intervals, whether naturally or with the help of a medicine chosen by a clinician, is a protective part of long-term care.
Can PCOS be treated with diet or supplements alone?
Lifestyle changes are the foundation of PCOS management and can improve insulin sensitivity, cycle regularity and symptoms over months, but they are not a guaranteed fix and are often combined with other measures. No supplement has evidence strong enough for mainstream guidelines to recommend it as a treatment. Claims that a product resolves PCOS outrun what studies show.
References
- NHS: Polycystic ovary syndrome
- CDC: PCOS (Polycystic Ovary Syndrome) and Diabetes
- Cleveland Clinic: Polycystic Ovary Syndrome (PCOS)
- MedlinePlus: Polycystic Ovary Syndrome
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Diagnostic vs Operative Hysteroscopy: When Looking Becomes Treating in the Same Session
A diagnostic hysteroscopy uses a thin lighted telescope passed through the cervix to look inside the uterus and find the cause of symptoms such…

What to Expect After Fibroid Treatment: Symptom Relief, Follow-Up Scans and Regrowth Checks
After fibroid treatment, heavy bleeding and pressure symptoms usually ease over weeks to months rather than overnight, and the pace depends on the method…

Is Cystitis a UTI? The Difference Explained
Yes. In everyday medical use, cystitis is a type of urinary tract infection (UTI): specifically, a UTI affecting the bladder. UTI is the broader…

When Is Pelvic Organ Prolapse Surgery Considered? After Pessaries and Pelvic Floor Therapy
Pelvic organ prolapse surgery is usually considered when a woman has bothersome symptoms, such as a bulge, pressure, or bladder and bowel problems, and…
What Happens During a Hysterectomy: Anesthesia, Removal of the Uterus and Time in Surgery
During a hysterectomy you are given anesthesia, usually a general anesthetic, then the surgeon reaches the uterus through the vagina, through small keyhole incisions,…

After a Hysterectomy: Fever, Heavy Bleeding or Wound Changes That Need a Call to Your Team
After a hysterectomy, call your surgical team the same day for a temperature of 100.4°F (38°C) or higher, vaginal bleeding that soaks a pad…