

How Peripheral Angiography Maps Leg and Arm Arteries to Find Narrowing or Blockage
Key Takeaways
- Peripheral angiography produces moving X-ray images of contrast dye flowing through leg or arm arteries; it maps disease but does not treat it unless a balloon or stent step is added and consented to.
- The NHS estimates an angiogram usually takes 30 minutes to 2 hours, with the total day extended by preparation and a few hours lying flat if the groin artery was used.
- The four Fontaine stages of peripheral artery disease run from silent plaque, through walking-induced cramp and rest pain, to ulcers or gangrene, and the stage sets the urgency of imaging.
- Kidney strain from iodine contrast and bleeding at the puncture site are the most relevant risks, which is why kidney blood tests and site checks bracket the procedure.
- A normal ankle-brachial index can be falsely reassuring when arteries are stiff and calcified, so ultrasound or toe pressures are sometimes added before deciding on angiography.
- Treated arteries can narrow again, so follow-up ultrasound, exercise therapy, smoking cessation and management of cholesterol, blood pressure and diabetes continue after any procedure.
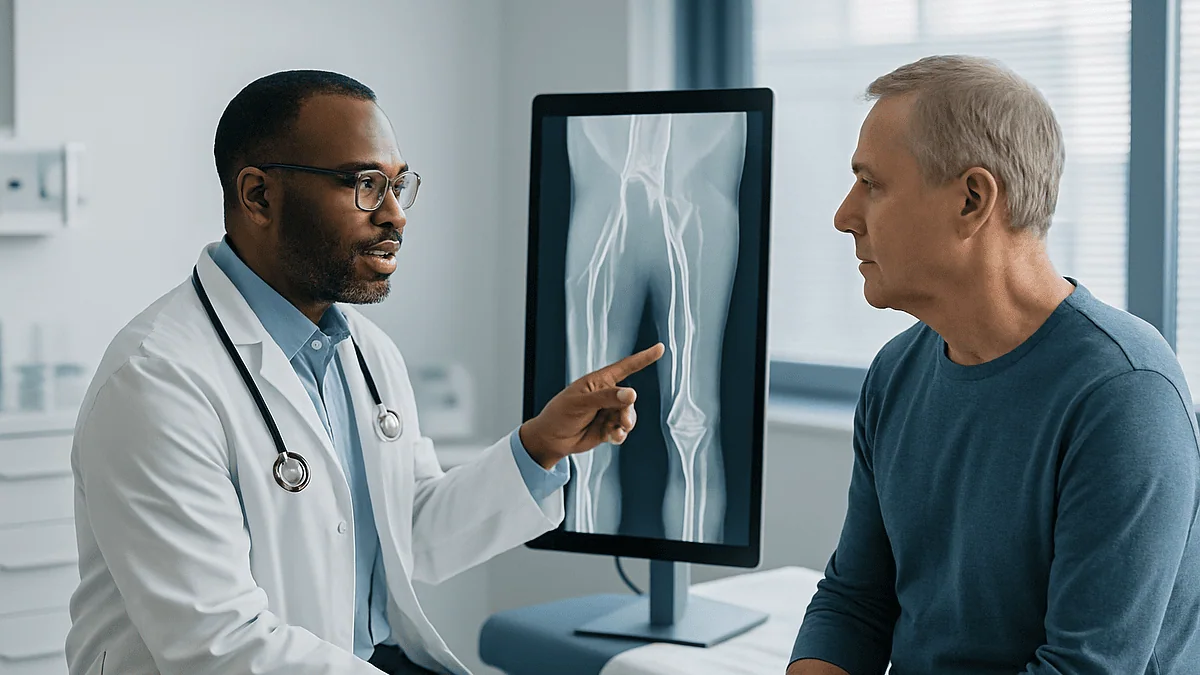
Peripheral angiography is an X-ray study in which a clinician threads a thin tube into an artery, usually at the groin or wrist, injects iodine-based contrast dye, and records real-time images as the dye flows through the leg or arm arteries. Narrowed segments appear as pinched channels and blockages as abrupt stops, giving the care team a road map for deciding whether to treat and how.
The walk from the parking lot to the pharmacy used to be nothing. Now it stops him twice: a cramp in the calf that builds like a fist closing, eases after a minute of pretending to read a sign, then returns. His doctor has already pressed a small probe against his ankle, compared the pressures with his arm, and used the phrase peripheral artery disease. The next step on the referral letter is a peripheral angiogram, and the leaflet raises more questions than it answers.
Most people in that chair want the same three things: to understand how peripheral angiography works, to know what it will feel like, and to learn what the pictures will actually change. This explainer walks through the whole arc, from the first pressure cuff to the days after the puncture site heals, using guideline-level evidence rather than reassurance.
Along the way it corrects a few stubborn myths, sets honest expectations about time and discomfort, and leaves every decision where it belongs, with the team that knows your arteries and your history.
How peripheral angiography works, step by step
Angiography simply means taking pictures of blood vessels. Peripheral angiography applies that idea to the arteries outside the heart and brain, most often those running from the pelvis down to the foot, and sometimes the arteries of the arm.
The physical steps are more mechanical than mysterious. You lie on a narrow table under a C-shaped X-ray arm. The skin over an artery in the groin or wrist is numbed with local anesthetic, a medicine injected under the skin to block pain in that spot. A needle enters the artery, a soft guidewire slides through the needle, and a short plastic sleeve called a sheath replaces the needle so instruments can pass in and out without repeated punctures.
Through the sheath goes a catheter, a flexible tube roughly the width of a strand of spaghetti. Using live X-ray, the operator steers it to the artery of interest. A contrast agent, an iodine-containing liquid that blocks X-rays, is injected. For a second or two the artery lights up as a bright, branching tree on the screen while the surrounding bone and muscle are digitally subtracted, a technique MedlinePlus describes under extremity angiography.
Healthy arteries look smooth and evenly tapered. A plaque of cholesterol, calcium and scar tissue shows as a waist in the channel. A complete occlusion appears as a column of dye that simply ends, often with a faint haze of small bypass vessels the body has grown around it. Because the images are captured as moving sequences rather than single snapshots, the team can also judge how quickly blood reaches the foot, which matters as much as where the narrowing sits.
What the pictures actually show: narrowing, blockage and collaterals
A peripheral angiogram is less a single photograph than a series of chapters. The pelvis chapter shows the aorta splitting into the two iliac arteries. The thigh chapter follows the femoral artery to the knee. The final chapter, often the hardest to read, traces three slender arteries below the knee to the foot.
Three findings drive most decisions. The first is stenosis, a narrowing that still lets some blood through. Radiologists estimate it as a percentage of the normal diameter, and the moving images reveal whether dye pools behind it. The second is occlusion, a complete stop. Its length matters: a short blockage behaves differently from one spanning most of the thigh. The third is the collateral network, small detour vessels that enlarge over months when a main artery closes slowly. Rich collaterals explain why some people with a fully blocked femoral artery walk reasonably well, while a sudden clot in an otherwise healthy artery can threaten the limb within hours.
The team also looks at what lies downstream. A narrowing above the knee can be widened, but if the arteries below it are diseased along their whole length, blood still struggles to reach the toes. Vascular clinicians call this the quality of the run-off, and it shapes whether angioplasty, surgery or medical management is the sensible next step.
Calcium deserves its own mention. Heavily calcified plaque appears even before contrast is injected, as chalky lines along the vessel wall. It tells the operator a balloon may struggle to expand the segment and that a stent, a small metal mesh scaffold, might be considered. None of these judgments happens in isolation; the angiogram is read alongside your symptoms, pressure measurements and ultrasound.
What are the four stages of peripheral vascular disease?
Vascular teams have long grouped leg artery disease into four stages using the Fontaine classification, a system named after the surgeon who described it. It is worth knowing because it frames why an angiogram is offered to one person and deferred for another.
Stage one is silent disease: plaque is present, but the person feels nothing, or notices only that one foot is cooler or hair on the shin has thinned. Many people at this stage are identified through an ankle-brachial index, a comparison of ankle and arm blood pressures. Mayo Clinic notes that a lower ankle pressure relative to the arm suggests narrowed leg arteries.
Stage two is intermittent claudication, the cramping pain in calf, thigh or buttock that comes on with walking and fades within minutes of standing still. The muscle simply demands more oxygen than the narrowed artery can deliver. Stage two is often split into pain after longer distances and pain after shorter ones.
Stage three is rest pain, typically an ache in the foot or toes that wakes people at night and eases when they hang the leg over the side of the bed, because gravity helps blood trickle downhill.
Stage four is tissue loss: an ulcer that will not heal or gangrene, where skin and deeper tissue die from lack of blood. Stages three and four together are described as chronic limb-threatening ischemia, and guidelines from the American Heart Association treat them as a reason for prompt imaging and revascularization planning.
A parallel system, the Rutherford classification, refines the same journey into seven grades. Whichever system your team uses, the point is identical: the stage, not the picture alone, sets the urgency.
Who is usually offered peripheral angiography, and who is asked to wait
Catheter angiography is an invasive test, so it is rarely the first step. Both the NHS and the American Heart Association describe it as the study used when a decision about treatment is already on the table, not as a screening tool.
People most often referred fall into a few groups. Those with rest pain, non-healing wounds or gangrene need a detailed map because the limb is at risk and revascularization is being planned. Those with claudication that still limits daily life after several months of supervised exercise and risk-factor treatment may be offered angiography to judge whether angioplasty is feasible. A third group has had a prior bypass graft or stent that ultrasound suggests is narrowing again. A fourth includes people with a sudden cold, pale, painful limb, where an acute clot is suspected and imaging and treatment may happen in the same sitting.
Others are usually asked to wait, or steered to a different test. Someone with mild claudication who has not yet tried walking therapy and medical management gains little from an invasive picture, because the picture would not change the plan. People with significantly reduced kidney function may be offered ultrasound or MR angiography first, since iodine contrast can strain the kidneys, a risk MedlinePlus lists specifically. A known severe reaction to contrast, an active infection, uncontrolled bleeding tendencies or pregnancy each prompt a conversation about timing and alternatives.
None of these are absolute rules. A frail person with a threatened foot may still be a candidate because the alternative, amputation, carries its own heavy burden. The treating team weighs the odds in your particular case, and the choice remains theirs to explain and yours to accept or question.
Noninvasive tests first: ABI, duplex ultrasound, CT and MR angiography
Most people reach the angiography suite only after a ladder of gentler tests. Understanding that ladder helps explain why the catheter study is reserved for specific questions.
The ankle-brachial index takes a few minutes with a blood pressure cuff and a small Doppler probe. Duplex ultrasound uses sound waves to show both the vessel wall and the speed of blood, and a jet of fast flow through a narrowing is a reliable clue. CT angiography injects contrast into an arm vein rather than an artery and builds a three-dimensional model in seconds. MR angiography does something similar using magnets, often with a different type of contrast.
| Test | What it involves | Strengths | Limits |
|---|---|---|---|
| Ankle-brachial index | Cuff pressures at ankle and arm | Quick, painless, no contrast | Can read falsely normal with stiff calcified arteries |
| Duplex ultrasound | Probe on skin, sound waves | No radiation, shows flow speed | Operator dependent; pelvis and calf can be hard to see |
| CT angiography | Vein injection, rapid scanner | Whole-limb 3D map in minutes | Radiation; heavy calcium can obscure the channel |
| MR angiography | Magnet scanner, sometimes contrast | No X-rays; good soft-vessel detail | Longer scan; not suitable with some implants |
| Catheter angiography | Artery puncture, catheter, contrast | Highest detail; treatment possible immediately | Invasive; bleeding and contrast risks |
The Mayo Clinic and NHS both describe this progression, and the logic is consistent: choose the least invasive study that can answer the question in front of you. The catheter angiogram earns its place when the answer needs to be exact, or when treatment is likely to follow in the same session.
How long does a peripheral angiogram take?
The honest answer has two parts: the time on the table and the time in the building. The NHS estimates that an angiogram generally takes between 30 minutes and 2 hours, and the peripheral version sits comfortably inside that range.
Several factors stretch or shorten it. Mapping both legs takes longer than one. Navigating a catheter from the groin on one side across the pelvis to the opposite leg adds steps. Tortuous, calcified arteries slow the operator, who must advance the wire in small, careful movements. If the team moves straight from diagnosis to angioplasty, the session lengthens accordingly, sometimes to two or three hours of procedure time.
The day, however, is measured differently. You are usually asked to arrive an hour or more ahead for consent, blood tests, an intravenous line and a check of kidney function. Afterward comes the recovery period, which depends heavily on where the artery was entered. When the femoral artery in the groin is used and closed with pressure alone, the NHS describes lying flat for a few hours so the puncture seals. A closure device, a small plug or stitch placed inside the artery wall, can shorten that. Wrist access allows sitting up almost immediately, with a compression band on the forearm instead.
Most diagnostic angiograms are day cases, meaning people go home the same day with an escort, a point the NHS makes plainly. An overnight stay becomes more likely after angioplasty, after a bleed at the puncture site, or if kidney function needs watching. Ask your team which of these scenarios they expect, because a realistic timeline reduces the anxiety of a long day far more than any leaflet can.
Preparing for the procedure: the day before and the morning of
Good preparation is mostly about three things: your kidneys, your blood’s ability to clot, and your comfort.
Kidneys first. Iodine contrast is filtered by the kidneys, and MedlinePlus lists kidney damage among the recognized risks, particularly for people with existing kidney disease or diabetes. Teams usually check a recent blood test, encourage fluids in the days before unless a heart condition limits them, and may adjust the timing of certain medicines around the procedure. Which medicines, and how, is a decision for the prescribing clinician and should never be improvised at home.
Clotting second. Blood thinners, medicines that reduce the blood’s tendency to form clots, are common in people with artery disease. Some are continued through the procedure and some paused briefly; your team will give specific written instructions. Antiplatelet medicines, which make blood cells less sticky, are often kept going because they protect against clots forming on any stent placed. Follow the instructions exactly, and call if anything is unclear.
Comfort third. You will usually be asked not to eat for several hours beforehand, while sips of water are often allowed; the exact window is set by your unit. Wear loose clothing, leave jewelry at home, and arrange for someone to drive you, since the NHS advises against driving for at least a day afterward. Tell the team about any previous reaction to contrast dye, iodine or shellfish confusion aside, any allergy to latex or anesthetic, and whether you might be pregnant.
On the morning itself, expect a gown, a wristband, a groin or wrist shave, and a run through the consent form. A mild sedative through the intravenous line is often offered. You remain awake and able to speak, which matters, because the operator may ask you to hold your breath or keep a leg still at key moments.
Groin or wrist? How the access site is chosen
Where the needle goes in shapes the whole experience, from how you lie during the test to how soon you sit up afterward.
The common femoral artery in the groin has been the classic entry point for decades. It is large, close to the skin and gives a straight run down the same leg. It also allows the operator to cross over the top of the pelvic arteries and treat the opposite leg. Its drawback is the recovery: the artery lies deep beneath tissue where a bleed can spread unnoticed, so pressure, a closure device and a period of lying flat are standard. MedlinePlus describes bruising and bleeding at the site as the most frequent complications.
Radial access through the wrist has grown in peripheral work, borrowing from heart catheterization. The artery is small and superficial, so any bleeding is easy to see and compress, and people can sit up and eat promptly. The trade-off is distance: from the wrist to the foot is a long way, and catheters may not reach the smallest calf arteries in tall individuals. Before choosing the wrist, teams check that the hand has a second artery supplying it, so that temporary narrowing of the radial artery would not compromise circulation.
Less often, the brachial artery at the elbow or the artery on top of the foot is used, particularly when a blockage must be approached from below.
Arm arteries themselves are imaged far less frequently than leg arteries, because plaque disease is uncommon there. When arm angiography is needed, typically to investigate narrowing near the shoulder or after trauma, the same principles apply, with access from the groin or the opposite wrist. Your operator’s choice reflects your anatomy, the target vessel and their own experience, and it is worth asking why a particular route is planned.
When a diagnostic angiogram becomes a treatment: angioplasty and stents
One reason catheter angiography still matters is that the map and the repair can happen in the same session. This is the point where many patients realize the leaflet’s word diagnostic was only half the story.
Angioplasty means passing a thin guidewire across the narrowing, then sliding a deflated balloon over it and inflating the balloon for a short period. The plaque is compressed and the artery wall is stretched. Some balloons carry a coating of medicine on their surface intended to reduce the scar tissue that can re-narrow the vessel; the evidence for coated devices continues to be evaluated in guideline reviews, and your team can explain what is known.
A stent is a mesh tube of metal that stays behind to hold the artery open, used when the vessel springs back or a flap of the inner lining lifts. Long segments of the thigh artery and arteries behind the knee flex with every step, so device choice there is a considered decision rather than a reflex.
Other tools exist: atherectomy devices that shave or drill plaque, and clot-dissolving medicine delivered directly through the catheter when a fresh clot is found. Each has its own risk profile.
The alternative for long or heavily calcified blockages is surgical bypass, in which a vein from the leg or a synthetic tube routes blood around the block. The American Heart Association describes both catheter and surgical approaches as options weighed against symptoms, anatomy and overall health. Whether anything is treated during your angiogram should be discussed and consented to beforehand, including the possibility that the team finds disease that is best left for a planned second procedure. Nothing about this is automatic.
Peripheral angiogram side effects and risks, stated plainly
Every honest explainer owes readers the risk list without softening or dramatizing it. MedlinePlus, the NHS and Mayo Clinic describe a consistent set of possible problems.
The common ones are minor. Bruising around the puncture site is expected and can spread surprisingly far down the thigh over several days before fading. A warm flush spreading through the body as contrast is injected, a metallic taste, or a fleeting sensation of having wet yourself are normal reactions to the dye, not signs of trouble. Mild soreness at the entry point lasting a few days is typical.
The less common ones matter more. A hematoma is a collection of blood under the skin that forms a firm, tender lump; small ones resolve on their own, large ones may need compression or repair. A pseudoaneurysm, a leak from the artery contained by surrounding tissue, can develop a day or two later as a pulsing swelling. Allergic reactions to contrast range from hives to, rarely, a severe whole-body response, which is why staff ask repeatedly about prior reactions and keep treatment at hand. Kidney injury from contrast is usually temporary but is the main reason kidney function is checked before and sometimes after.
Rare but serious complications include damage to the artery wall by the wire, a clot or plaque fragment breaking loose and blocking a smaller artery downstream, and infection at the site. The NHS notes that serious complications are uncommon, and units track their own rates.
Radiation exposure is real but modest for a diagnostic study, and teams use shielding and short bursts of X-ray to limit it. Pregnancy changes that calculation, which is why you are asked. Weigh these risks against the alternative of not knowing, in conversation with the team that will be doing the procedure.
Peripheral angiogram recovery time: what the following days and weeks look like
The first evening is about the puncture site. If the groin was used, you will have been lying flat for a few hours and then walking short distances under observation. At home, the NHS advice is to avoid driving, heavy lifting and strenuous activity for at least a day, and to keep the site clean and dry. Sudden movements such as coughing while bending should be met with a hand pressed over the dressing.
Over the next week, the bruise usually blooms, turns yellow-green and fades. A small, pea-sized firmness under the skin is common and typically softens within a few weeks. Showers are fine within a day or two; soaking in a bath or pool is generally discouraged until the skin has fully sealed. Drinking fluids helps the kidneys clear the remaining contrast, unless you have been told to restrict them.
Recovery from peripheral angioplasty follows a similar arc with two additions. First, you may be started on, or continued on, antiplatelet medicine to reduce the chance of a clot forming on the treated segment; the specific medicine and duration are the prescribing clinician’s decision. Second, the treated leg often feels different quite quickly, warmer or less prone to cramp, though the NHS is careful to describe angioplasty as improving symptoms rather than removing the underlying disease. Many people return to desk work within a few days and to their usual walking within about a week, but individual timelines vary widely.
Follow-up usually includes a clinic visit and a repeat ankle-brachial index or ultrasound within the first months, then at intervals, because treated arteries can narrow again. Supervised exercise, smoking cessation and treatment of cholesterol, blood pressure and diabetes remain the foundation; the angiogram does not replace them.
What people often get wrong about how peripheral angiography works
Myths gather around any procedure involving arteries and X-rays. A few deserve direct correction.
The first is that the angiogram will unblock the arteries by itself. It will not. The diagnostic study only produces images; any opening of a vessel requires a separate, consented step with a balloon or stent. People sometimes leave a purely diagnostic study disappointed that their cramp is unchanged, which reflects a gap in expectation rather than a failed test.
The second is that a stent or angioplasty fixes the disease. Both treat a segment. Plaque remains elsewhere in the same artery and in arteries throughout the body, including the heart, which is why the American Heart Association describes peripheral artery disease as a marker of cardiovascular risk overall. Medical treatment and lifestyle change carry on regardless.
The third is that the dye is radioactive. It is not. Iodine contrast simply blocks X-rays as they pass through; the radiation comes from the X-ray machine, in brief pulses, and stops when the machine does.
The fourth is that a normal ankle-brachial index rules out disease. Stiff, calcified arteries, common in diabetes and kidney disease, can hold their shape under the cuff and give a falsely reassuring reading, one reason ultrasound and toe pressures are sometimes added.
The fifth is that you will be asleep. Most peripheral angiograms use local anesthetic and, at most, light sedation. You remain conscious, can ask for a pause, and may be asked to help by holding still or breathing out.
The last is that leg pain in someone with known plaque must be arterial. Spinal stenosis, hip arthritis and nerve compression can mimic claudication closely. A careful history, and sometimes the angiogram itself, sorts them out, which is why an unexpectedly clear picture is still valuable information.
Questions to ask your care team before and after
A good consultation leaves you knowing not just what will happen but why. These prompts are drawn from what patients most often wish they had asked.
- Which noninvasive tests have already been done, and what specific question is the angiogram meant to settle?
- Is this planned as a purely diagnostic study, or is there a chance treatment will follow in the same session, and have I consented to both?
- Which artery will you enter, and how does that change how long I lie flat and when I can go home?
- What is my kidney function, and what will you do before and after to protect it?
- Which of my medicines should I take, pause or bring with me, in writing?
- What are the realistic options if you find a long or heavily calcified blockage: angioplasty, bypass, or continuing medical treatment?
- If nothing is treated today, what happens next and how soon?
- Who reviews the images with me afterward, and will I receive a written report I can share with my primary care clinician?
- What does follow-up look like over the coming months, including any repeat ultrasound?
- What symptoms at home should make me call the unit tonight rather than wait for the clinic?
Bring a list of every medicine and supplement, a note of any past reaction to contrast, and someone who can listen alongside you. Answers given in the pre-procedure room tend to blur afterward, especially with sedation, so writing them down or asking for them in your discharge letter is reasonable. If an answer is uncertain, a candid response that the team will decide once they see the pictures is more trustworthy than a confident guess. The decision about how to proceed rests with the treating team, informed by what you tell them about how the disease affects your life.
When to call your doctor: red-flag signs after a peripheral angiogram
Most recoveries are uneventful, and knowing the exceptions makes it easier to relax about the ordinary bruise. Seek care promptly, meaning call the number on your discharge sheet or emergency services, if any of the following appear.
Bleeding from the puncture site that does not stop after ten minutes of firm, direct pressure with the leg straight is an emergency; press and call while pressing. A rapidly swelling, tense or throbbing lump at the groin or wrist may signal a hematoma or pseudoaneurysm and needs same-day assessment. A foot or hand that becomes cold, pale, blue, numb or newly painful compared with the other side suggests reduced blood flow and should be treated as urgent, particularly after angioplasty or stenting.
Chest pain, breathlessness, sudden weakness on one side of the body, difficulty speaking or a drooping face are not expected after a leg angiogram and warrant emergency services immediately. So does a spreading rash with swelling of the lips or throat, or wheezing, which can indicate a delayed contrast reaction.
Less dramatic but still important: fever, increasing redness, warmth or discharge at the site after the first two days, which can indicate infection; passing much less urine than usual or noticing marked swelling of the ankles, which can reflect a kidney problem after contrast; or a new pulsing sensation under the skin at the entry point.
Symptoms that were the reason for the test also matter. If rest pain returns or worsens, if a wound on the foot deteriorates, or if walking distance drops sharply in the weeks after a procedure, contact the vascular team rather than waiting for a routine appointment. Trust your sense that something is different; the team would rather see a bruise that turns out to be harmless than miss a problem that was easy to treat early.
Frequently asked questions
How long does a peripheral angiogram take?
The procedure itself usually takes between 30 minutes and 2 hours according to NHS guidance, depending on how many arteries are imaged and how difficult they are to navigate. If angioplasty follows in the same session, expect longer. The full visit adds preparation beforehand and a recovery period afterward, often a few hours of lying flat when the groin artery is used, so plan for most of a day.
What are the possible side effects of a peripheral angiogram in the leg?
The most common effects are bruising and soreness at the puncture site, plus a brief warm flush or metallic taste when contrast is injected. Less often, a lump of blood under the skin, a leak from the artery wall, an allergic reaction to the dye or a temporary dip in kidney function can occur. Serious complications such as artery damage or a clot travelling downstream are uncommon, and units monitor for them.
How long does it take to recover from peripheral angioplasty?
Most people go home the same day or after one night, avoid driving and heavy lifting for at least a day, and return to light routines within several days. Bruising can take a few weeks to fade. Individual recovery varies with the access site, the extent of treatment and overall health, so your team’s specific discharge advice takes precedence over any general timeline.
What are the stages of peripheral artery disease?
The Fontaine system describes four stages: no symptoms, intermittent claudication (cramping pain on walking that eases with rest), pain in the foot at rest, and tissue loss such as ulcers or gangrene. The Rutherford system covers the same journey in seven grades. The later stages are grouped as chronic limb-threatening ischemia and usually prompt more urgent imaging and treatment planning.
Is peripheral angiography painful?
Most people describe it as uncomfortable rather than painful. The skin is numbed with local anesthetic, so the needle and sheath cause pressure more than sharp pain. Contrast injection produces a brief hot flush through the leg. Lying still on a firm table for an hour or more is often the hardest part, and light sedation is commonly offered to help.
Will I be awake during a peripheral angiogram?
Yes, in almost all cases. The procedure is done under local anesthetic with, at most, light sedation, because the team may need you to hold your breath, keep a leg still or report symptoms. You can speak with staff throughout and ask for a pause. General anesthesia is reserved for unusual circumstances, such as combined surgical procedures.
Can peripheral angiography damage my kidneys?
Iodine contrast can temporarily reduce kidney function, particularly in people with existing kidney disease, diabetes or dehydration. MedlinePlus lists kidney damage among the recognized risks. Teams check blood tests beforehand, encourage fluids where safe, limit the contrast volume and may choose ultrasound or MR angiography instead when kidney function is significantly reduced. Any medicine adjustments are made by your prescribing clinician.
What is the difference between a peripheral angiogram and a CT angiogram?
A CT angiogram injects contrast into an arm vein and uses a scanner to build a three-dimensional image without entering an artery, so it is less invasive. A catheter angiogram enters an artery directly, gives the sharpest detail of small vessels and allows treatment in the same session. Teams often use CT or ultrasound first and reserve the catheter study for planning or performing treatment.
Does a peripheral angiogram treat the blockage?
Not on its own. The diagnostic study only produces images. Treating a narrowing requires an additional step, angioplasty with a balloon and sometimes a stent, which uses the same access point but is a separate decision that should be discussed and consented to before the procedure. Some blockages are better suited to surgical bypass or continued medical management.
How soon can I drive after a peripheral angiogram?
The NHS advises not driving for at least 24 hours after an angiogram, partly because of sedation and partly to protect the puncture site from sudden pressure during braking. You will need someone to take you home. After angioplasty or if the groin was used, your team may advise a longer pause; follow the specific instructions on your discharge letter.
References
- MedlinePlus Medical Encyclopedia: Extremity angiography
- NHS: Angiography
- NIH National Heart, Lung, and Blood Institute: Peripheral Artery Disease
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
How Coronary CT Angiography Results Guide the Next Step, From Reassurance to Catheter Tests
After a coronary CT angiogram, the next step depends on what the scan shows. Clear or minimally affected arteries usually mean reassurance and a…

After the Fontan Procedure: Sternum Healing, Hydration and How to Lift Your Child Safely
After the Fontan procedure, most children spend roughly one to two weeks in hospital, then heal the breastbone over about six to eight weeks…

Cardiac Rehabilitation Week by Week: How Exercise Intensity Is Increased Safely
A cardiac rehab 12 week program usually raises exercise intensity in stages: early sessions establish a safe baseline using heart rate, perceived effort and…

Heart Age Calculators: What They Estimate and How Accurate They Are
A heart age calculator converts your estimated 10-year risk of heart attack or stroke into the age of a person with ideal risk factors…

Before a Peripheral Angiogram: Kidney Tests, Contrast Allergy History and Medicine Review
Before a peripheral angiogram, care teams typically check kidney function with a blood test, ask in detail about any previous reaction to iodinated contrast…

Bone Density: The Silent Number Behind Fracture Risk
Bone density measures the mineral packed into your bones, usually reported as a T-score from a DXA scan. A T-score of -1.0 or higher…