

How Soon Can You Walk, Drive and Lift After Gallbladder Surgery for Cholecystitis?

Key Takeaways
- Keyhole gallbladder removal typically allows a return to normal activities in about two weeks, while open surgery usually requires six to eight weeks, according to NHS guidance.
- The driving test is functional, not calendar-based: you must be able to perform an emergency stop without pain, which most keyhole patients manage after about a week, and your insurer may set additional conditions.
- Lifting limits of roughly 10 to 15 pounds in the early weeks exist to prevent incisional hernia, and they outlast the pain because the abdominal wall regains strength more slowly than soreness fades.
- Shoulder-tip pain after keyhole surgery is referred pain from carbon dioxide gas irritating the diaphragm and usually settles within a few days; new shoulder pain after a week needs assessment.
- Walking several times a day from the first day lowers clot risk, restarts the gut and clears trapped gas, so early movement speeds recovery rather than threatening it.
- Looser stools after fatty meals are common once bile flows continuously into the gut and usually improve over weeks to months; a permanent low-fat diet is not standard advice.
After keyhole gallbladder removal for cholecystitis, most people are walking within hours, driving after about a week once they can perform an emergency stop without pain, and back to light exercise within roughly two weeks; heavy lifting is usually held back for a few weeks longer. Open surgery typically means a 6–8 week recovery. The surgical team sets the exact limits, based on how inflamed the gallbladder was.
The discharge nurse hands over a folded sheet of instructions, and the first question out of most people’s mouths is not about the wound. It is about the car in the parking lot, the toddler who wants to be picked up, or the dog that expects a walk tomorrow morning. Recovery after cholecystitis surgery is, for most patients, a logistics problem dressed up as a medical one.
That is understandable. An inflamed gallbladder tends to arrive without warning, often as a night in the emergency department followed by an operation within days. There is no time to plan cover at work or arrange lifts. People go home sore, relieved and slightly dazed, and they want calendar answers.
The honest answer is that the calendar depends on two things: whether the surgery was keyhole or open, and how angry the gallbladder was when it came out. What follows separates what the evidence supports from what gets passed around waiting rooms.
What is a gallbladder, and what does cholecystitis do to it?
The gallbladder is a small, pear-shaped pouch tucked under the right side of the liver. Its job is storage. The liver makes bile, a greenish fluid that helps the gut break down fat, and the gallbladder holds a concentrated reserve of it, squeezing a dose into the small intestine when a fatty meal arrives.
Cholecystitis means inflammation of that pouch. In the great majority of cases the trigger is a gallstone, a hardened lump of cholesterol or bile pigment, lodging in the narrow outlet of the gallbladder. Bile backs up, pressure rises, the wall swells, and bacteria often join in. The result is the classic picture of steady pain under the right ribs, fever and tenderness that makes it hard to take a deep breath. A smaller group develops inflammation without stones, usually after major illness or injury.
Why does this matter for recovery? Because an inflamed gallbladder is a different surgical proposition from a quiet one. A gallbladder removed for occasional pain between attacks is thin-walled and easy to handle. One removed during an acute attack can be thick, swollen and stuck to its neighbors, and the operation can take longer and leave more internal bruising. The NHS notes that surgeons generally aim to operate within about a week of an acute attack when the patient is fit for it, which is why many people find themselves recovering from an operation they had not planned for.
The body manages without a gallbladder. Bile simply drips continuously from the liver into the gut rather than arriving in timed pulses. That change explains some of the digestive wobbles in the early weeks, which we come to later.
How gallbladder surgery for cholecystitis actually works
The operation is called a cholecystectomy, which is simply the medical word for removing the gallbladder. Nearly all are done with keyhole, or laparoscopic, technique, meaning the surgeon works through three or four small incisions using a camera and long instruments rather than one large cut.

Here is the sequence in plain terms. Under general anesthesia the abdomen is gently inflated with carbon dioxide gas so there is room to see. A camera goes in near the navel. Through the other ports the surgeon identifies the cystic duct, the short tube connecting the gallbladder to the main bile duct, and the small artery feeding it. Both are sealed with clips and divided. The gallbladder is then peeled off the underside of the liver and lifted out through one of the incisions, sometimes inside a small retrieval bag. The gas is released and the skin closed with stitches or glue. Mayo Clinic describes the whole procedure as typically taking one to two hours.
Inflammation changes the feel of this. A swollen gallbladder may be hard to grasp, the anatomy around the duct may be obscured, and the surgeon may need to drain fluid from it first. When the view is not safe, the team converts to an open operation through a larger incision under the right ribs. This is a judgment call made for safety, not a failure, and it is more likely when inflammation is severe or long-standing.
A few points shape your recovery before you even wake up. The gas can irritate the diaphragm, the breathing muscle beneath the lungs, producing referred shoulder pain. Longer, harder dissections mean more internal soreness. And a drain tube is sometimes left in for a day or two after a difficult case. Each of these nudges the timelines that follow.
Who is operated on early, and who is asked to wait
Not everyone with cholecystitis goes to theatre that week, and the reasons are worth understanding because they predict how recovery will feel.
Early surgery, within a few days of admission, is the usual approach for people who are otherwise reasonably well. The NHS explains that operating during the first week avoids a second episode and a second hospital stay, and the recovery that follows is essentially a keyhole recovery with some extra internal bruising.
Some people are asked to wait. If someone arrives very unwell, with a serious infection, unstable heart or lung disease, or on blood-thinning medicines that cannot safely be paused, surgeons may treat the inflammation first with intravenous antibiotics and fluids, then plan removal once things have settled. In a few cases a thin drainage tube is placed through the skin into the gallbladder under imaging guidance, a procedure called percutaneous cholecystostomy, to relieve pressure without an operation. Surgery is then reconsidered weeks later, or sometimes not at all if the risks remain high.
Pregnancy, previous upper abdominal operations and suspected stones in the main bile duct also change the plan. Stones in the duct may need a separate endoscopic procedure, performed through the mouth with a flexible camera, before or after the gallbladder comes out.
What this means for your own timeline: if your operation was delayed and done once the inflammation had cooled, your recovery is likely to track the standard keyhole figures closely. If it was done in the thick of an acute attack, or converted to open surgery, expect the slower end of every range in this article. None of this is a reason to worry; it is a reason to ask your team which category you fall into rather than borrowing a neighbor’s experience.
Walking after gallbladder surgery: why the first lap matters most
Of the three activities in the title, walking is the one to start soonest and the one people most often under-do.
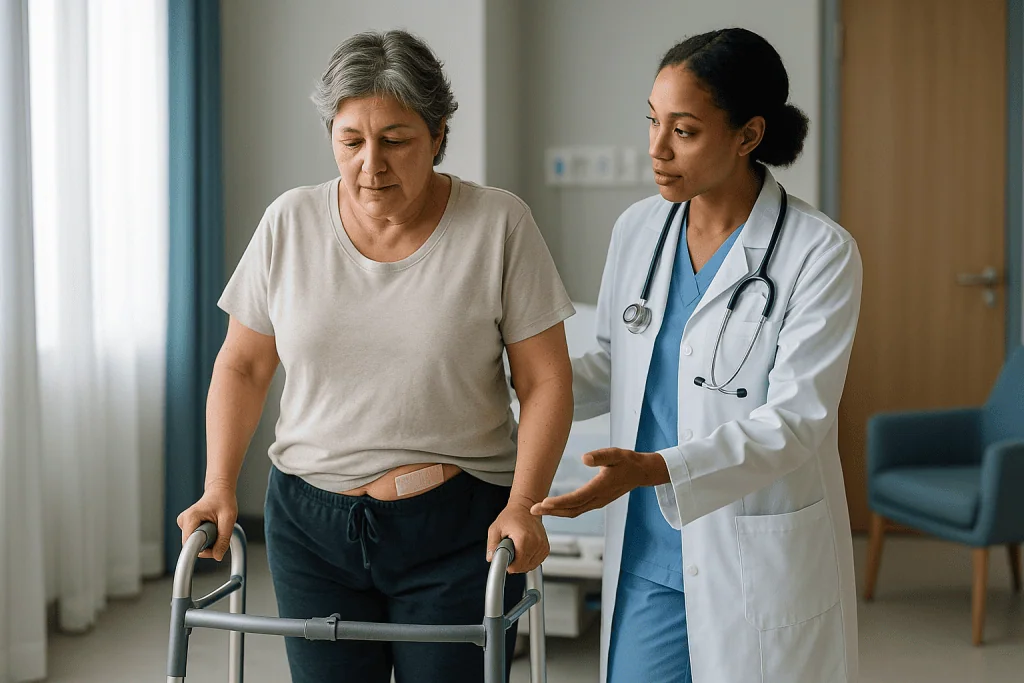
Most people are helped out of bed within a few hours of waking from anesthesia, often the same evening. The first few steps feel oddly cautious, as though the abdomen might object, but the incisions are small and the muscle wall has not been cut in the way it is in open surgery. MedlinePlus discharge guidance for laparoscopic gallbladder removal advises walking several times a day from the first day home and gradually increasing the distance.
Why the emphasis? Three mechanisms. Walking keeps blood moving in the calf veins, which lowers the risk of deep vein thrombosis, a clot in a leg vein that can travel to the lungs. It encourages the gut, which goes quiet after any abdominal operation, to start moving again, easing bloating and constipation. And it helps clear the carbon dioxide gas that causes shoulder and upper abdominal discomfort. Lying still does the opposite on all three counts.
A sensible pattern for the first 48 hours is short and frequent: a lap of the house or hallway every couple of hours while awake, rather than one heroic walk followed by an afternoon on the sofa. By day three or four, many people manage a slow ten or fifteen minute walk outdoors. Stairs are fine from the start; take them one at a time and use the rail.
After open surgery the same principles apply but the pace is slower, and the team will show you how to support the wound with a hand or folded towel when you cough or stand. Expect to feel genuinely tired by the end of a short walk in the first week. Fatigue after anesthesia and infection is normal and lifts gradually; it is not a sign that walking is doing harm.
Driving after gallbladder surgery: what the evidence actually says
There is no law that names a number of days, and that is where confusion starts.
The medical test is functional. You should not drive until you can sit comfortably in the seat, turn to check your blind spot, and perform an emergency stop without hesitation or pain. The NHS puts this at about a week after keyhole surgery for most people, and considerably longer after open surgery, and adds a practical point that is easy to forget: check with your motor insurer, because some policies have their own conditions after an operation.
Two things hold people back from driving safely in the first days. The first is pain. If slamming your foot on the brake makes you flinch, your reaction time is slower than you think, and a flinch at highway speed matters. The second is medication. Opioid pain relievers, the stronger prescription painkillers, can dull alertness, and it is unsafe and in many places illegal to drive while taking them. Many people have moved onto simpler pain relief within a few days, which is one reason the week-ish figure works for most keyhole patients. Your prescribing clinician can tell you when your particular medicines are no longer a concern.
Fatigue counts too. The post-anesthesia tiredness of the first week can be surprisingly heavy, and a drowsy driver is an impaired driver regardless of the wound.
A simple self-check before the first drive: sit in the stationary car, fasten the belt over the incisions, twist fully both ways, and stamp hard on the brake several times. If any of that produces more than mild discomfort, give it a few more days. Start with short, familiar journeys in daylight. After open surgery, the same test applies but the honest answer is usually several weeks, and your surgeon will say when the wound can tolerate a seatbelt and sudden movement.
Lifting after gallbladder surgery: a realistic ladder, not a cliff
Lifting is where advice becomes vague, and vague advice gets ignored. Here is the reasoning behind the limits so the numbers make sense.
Each keyhole port is a small hole through the abdominal wall, and the one at the navel, where the gallbladder came out, is the largest. Those openings close in layers over several weeks. Straining against a heavy load raises pressure inside the abdomen, and in the early weeks that pressure can push tissue through a healing opening, producing an incisional hernia, a bulge of fat or bowel through the muscle gap. It is uncommon, but it usually means another operation, which is why surgeons are firm about it.
MedlinePlus discharge instructions advise against lifting anything heavier than roughly 10 to 15 pounds, about a full grocery bag or a small toddler, until the surgeon clears it, and most keyhole patients are given a window of around two weeks for that lighter limit with a gradual build afterwards. Mayo Clinic frames the same idea as avoiding heavy lifting for a few weeks. After open surgery, the NHS guidance is to avoid strenuous activity and heavy lifting for around six to eight weeks, because a longer incision through muscle needs that long to regain strength.
Think of it as a ladder:
- First week: kettles, plates, a light bag. Nothing that makes you hold your breath.
- Weeks two to three after keyhole surgery: moderate household loads such as a laundry basket, lifted close to the body with bent knees.
- Beyond that, as cleared by your team: a gradual return to gym weights or manual work, adding load over sessions rather than jumping back to previous maximums.
Two red flags while lifting are worth knowing: a new bulge near an incision, or sharp pain that does not settle in minutes. Both warrant a call, not a push through.
What kind of exercise is recommended after gallbladder removal?
Exercise after gallbladder removal is less restricted than most people assume, provided the order is right: walking first, then low-impact cardio, then core and heavy resistance work last.
Walking, as above, starts on day one and can build steadily. Cleveland Clinic’s cholecystectomy guidance encourages light activity early and a return to most normal activity within about two weeks after a keyhole operation. In practice, many people are back to brisk walks, gentle cycling on a stationary bike or an easy swim once the wounds are fully sealed and dry, typically from the second week, with the swimming caveat that any scab or glue should have come away first to reduce infection risk.
Running and higher-impact activity can feel uncomfortable a little longer, not because of the incisions but because of residual internal soreness where the gallbladder sat against the liver. Most people ease back somewhere between two and four weeks after keyhole surgery, guided by comfort.
Core work deserves the most patience. Sit-ups, planks, heavy squats and anything that involves bracing the abdomen hard loads exactly the tissue that is healing. The same hernia logic that governs lifting applies here, which is why trainers who understand surgery hold abdominal work back for several weeks and reintroduce it with light, controlled movements. After open surgery, the six to eight week window for strenuous activity covers structured exercise as well as lifting.
A few practical rules that hold across every stage:
- Pain that increases during an activity and persists afterwards means you went too far too soon.
- Breathlessness out of proportion to effort is not a fitness problem; it is a reason to call.
- Hydration and regular meals matter, since appetite can lag for a week or two and training on empty worsens fatigue.
If you train seriously, ask the surgical team for a specific return-to-sport plan rather than a general all-clear.
Keyhole or open: how the recovery milestones compare
Almost every timeline question has two answers, so it helps to see them side by side. The figures below are the typical ranges described in NHS and MedlinePlus patient guidance; your own team may shorten or lengthen them based on what they found at operation.
| Milestone | Keyhole (laparoscopic) | Open surgery |
|---|---|---|
| Hospital stay | Same day or one night | Around 3–5 days |
| First walk | Within hours | Within a day, with support |
| Driving | About 1 week, once an emergency stop is pain-free | Several weeks, as advised by the surgeon |
| Light household tasks | Within days | 1–2 weeks |
| Return to desk work | Around 2 weeks | Around 6–8 weeks |
| Heavy lifting and strenuous exercise | Gradual build after roughly 2 weeks, cleared by the team | Usually after 6–8 weeks |
Two caveats stop this table from misleading you. First, cholecystitis itself adds time to both columns. Someone whose gallbladder was removed during a severe acute attack, perhaps with a drain left in and a course of antibiotics, often sits at the slow end of the keyhole ranges even though the incisions are small. Second, these are medians of a spread, not deadlines. People with physically demanding jobs, older adults, and those with diabetes or lung disease frequently need longer, and that is expected rather than concerning.
The table is most useful as a conversation tool. Take it to your follow-up appointment and ask which column, and which end of each range, applies to you. A surgeon who saw the inside of your abdomen can calibrate these numbers in a way no article can.
What the first weeks of recovery after cholecystitis surgery usually look like
The pattern of recovery after cholecystitis surgery is front-loaded: the first three days are the worst, and improvement after that is usually visible day to day.
Days one to three. Expect soreness at the incisions, a bruised feeling under the right ribs, and the gas-related shoulder ache covered below. Appetite is modest and sleep is interrupted. Many people describe this phase as feeling as though they have done far too many sit-ups. Simple pain relief as prescribed, short frequent walks, and small bland meals are the whole plan. A drain, if you have one, is typically removed before discharge or at the first wound check.
Days four to seven. The shoulder pain has usually gone, bowels have restarted, and the main complaint becomes tiredness. Showering is generally fine once the dressings are removed or waterproof; soaking in a bath is usually deferred until wounds are sealed. This is the week most keyhole patients pass the driving test described earlier.
Week two. Most people with office-based work are back, often with a lighter week to begin. Mayo Clinic notes that a week or so off is common after laparoscopic surgery, with open surgery requiring more. Wound glue flakes off; dissolvable stitches soften.
Weeks three to six. Energy returns to baseline, exercise expands, and lifting limits lift. For open surgery, this is still the restricted phase.
Digestion deserves a word. Because bile now flows continuously rather than in bursts, some people notice looser stools or urgency after fatty meals. Mayo Clinic describes this post-surgery diarrhea as common and usually improving over weeks to months. Smaller, lower-fat meals in the early weeks help many people, but a permanent restrictive diet is not required, and persistent change should be mentioned to your clinician rather than managed alone.
Is shoulder pain normal after gallbladder removal?
Yes, and it is one of the strangest sensations of the whole experience: an operation on the abdomen that leaves you rubbing your right shoulder or collarbone.
The explanation lies in the carbon dioxide gas used to inflate the abdomen during keyhole surgery. A small amount remains afterwards and collects under the diaphragm, the dome of muscle separating chest from abdomen. The diaphragm shares its nerve supply, the phrenic nerve, with the skin over the shoulder tip. The brain misreads irritation of the diaphragm as pain coming from the shoulder, in the same way heart pain can be felt in the left arm. Doctors call this referred pain.
The NHS lists shoulder pain among the expected after-effects of keyhole gallbladder removal and notes that it typically settles within a few days as the gas is absorbed into the bloodstream and breathed out. It is often worst on the first evening, aches more when lying flat, and can come in waves when you change position.
What helps is movement and breathing rather than rest. Walking shifts the gas and speeds absorption. Slow, deep breaths that push the belly out expand the diaphragm and help clear it. Some people find a warm compress on the shoulder soothing, and the regular pain relief prescribed for the incisions usually covers it. Peppermint tea is sometimes suggested for trapped wind; the evidence for it in this setting is thin, so treat it as harmless comfort rather than treatment.
When is shoulder pain not the gas? If it arrives new after several days of feeling well, is severe and worsening, comes with fever, or is accompanied by breathlessness or chest discomfort, it needs assessment the same day. Pain under the right ribs that intensifies rather than fades, especially with yellowing of the skin or eyes, also points away from gas and toward a bile-related problem. Those are the exceptions; for the great majority, the shoulder ache is gone before the wound dressings come off.
How soon can you fly after gallbladder removal?
Flying after gallbladder removal is a question with no single guideline number, so it pays to understand what surgeons are actually weighing when they answer it.
The first concern is clotting. Any operation raises the risk of deep vein thrombosis for several weeks, and so does sitting immobile in a cramped seat for hours. Combining the two early in recovery stacks the risks. The second is distance from help. A wound infection, a bile leak or a retained stone typically declares itself in the first one to two weeks, and being over an ocean when it does is not ideal. The third is comfort: seatbelts sit across fresh incisions, overhead bins demand lifting, and airports involve long walks with luggage.
For those reasons most surgical teams tie flying to the general recovery window rather than to a fixed rule. After uncomplicated keyhole surgery, that usually means waiting until the first follow-up or wound check has confirmed things are settled, commonly in the second week, and longer for long-haul routes. After open surgery, or after a complicated cholecystitis operation with a drain or prolonged antibiotics, the wait is longer and should be set by the surgeon. Airlines also have their own fitness-to-fly policies and may ask for clearance, so check before booking rather than at the gate.
If you do fly within the first month or so, the clot-prevention basics apply regardless of cabin class:
- Walk the aisle every hour or so and flex your ankles while seated.
- Drink water, go easy on alcohol, and avoid sedating medicines.
- Ask your team whether compression stockings or any clot-preventing measure is appropriate for you; do not start or alter medicines on your own.
- Carry your discharge summary and know how to reach care at your destination.
Travel insurers often require you to declare recent surgery; an undeclared operation can void cover.
What people often get wrong about recovery after cholecystitis surgery
Recovery after cholecystitis surgery attracts myths precisely because the operation is so common; everyone knows someone who had it. These are the corrections worth making.
“Small cuts mean a small operation.” The incisions are small; what happened inside was not. An inflamed gallbladder dissected off the liver leaves raw surfaces and internal bruising that have nothing to do with the skin. Judging recovery by the dressings leads people to overdo week one.
“Rest is the fastest way to heal.” Within reason, the opposite is true. Early walking lowers clot risk, restarts the gut and clears gas. Bed rest beyond the first day or so slows all three.
“You have to eat a low-fat diet for life.” You do not. Many people tolerate fat less well for a few weeks while the gut adjusts to continuous bile flow, and some have longer-lasting looseness after very fatty meals, but a permanent restrictive diet is not standard advice.
“Once the pain is gone, lifting is fine.” Pain fades well before the abdominal wall regains strength. The lifting limit exists to prevent hernia, not discomfort, which is why it outlasts the soreness.
“Shoulder pain means something went wrong.” In the first few days it almost always means trapped gas. New or worsening shoulder pain after a week is a different matter and should be checked.
“Driving is allowed once the painkillers stop.” Stopping sedating medicines is necessary but not sufficient. The emergency-stop test and your insurer’s rules both still apply.
“A drain or an open conversion means the surgery failed.” Both are safety decisions made in the face of inflammation, and both are associated with a slower recovery, not a worse long-term result.
The thread running through all of these: the body heals on a timetable set by tissue, not by how the incisions look or how you feel on a good morning.
Questions to ask your care team before you go home
The five minutes before discharge are the highest-value conversation of the whole episode, and most people spend them nodding. Here is a list to keep in your phone, in rough order of usefulness.
- Was my operation keyhole throughout, or converted to open? Which recovery timeline should I follow?
- How inflamed was the gallbladder, and does that change my restrictions?
- Do I have a drain, stitches that need removing, or glue that will flake off? When is my wound check?
- What is my lifting limit, in plain terms, and for how long? When can I progress, and who decides?
- When may I drive, and which of my medicines rule it out until stopped?
- Is it safe for me to fly, and if so when? Do I need any clot-prevention measures for travel?
- What exercise can I start now, and what should wait? I run / lift / swim; when can I resume each?
- Were there any stones in the bile duct, and is any further procedure or scan planned?
- Am I finishing a course of antibiotics? What should I do if I miss a dose or cannot keep it down?
- Which pain relief am I going home with, how long should I expect to need it, and what should I avoid taking alongside it?
- What digestive changes are normal in the first weeks, and which should prompt a call?
- Who do I contact out of hours, and what number do I use?
Two further suggestions. Ask for the answers in writing, or write them down yourself, because post-anesthesia memory is unreliable for a day or two. And bring the person who will be helping you at home into the conversation; they are the ones who will enforce the lifting limit when the shopping arrives.
If your follow-up is weeks away and something falls between the categories above, it is always acceptable to ring the ward or surgical team and ask. Clinicians would far rather field a call than see a preventable complication.
When to call your doctor
Most recoveries are uneventful, and the aim here is not to make you watch yourself anxiously. It is to make sure that the small number of problems that do occur are caught early, when they are easiest to treat.
Seek urgent medical attention, the same day or through emergency services, for any of the following:
- Fever, shaking chills or feeling generally and increasingly unwell after the first day or two.
- Pain in the abdomen that is getting worse rather than better, or severe pain that is new.
- Yellowing of the skin or whites of the eyes, dark urine, or pale, clay-colored stools, which can signal a problem with bile flow.
- Persistent vomiting, or inability to keep fluids down.
- Redness spreading from an incision, pus or foul-smelling discharge, or a wound that opens.
- A swollen, painful or warm calf, or sudden breathlessness, chest pain or coughing up blood, which can indicate a clot.
- A new bulge at an incision, particularly one that is painful or cannot be gently pushed back.
- Bleeding from a wound that does not stop with firm pressure for ten minutes.
Call during working hours, rather than waiting for a routine appointment, if shoulder pain persists beyond a week or returns after settling, if diarrhea is frequent or lasts beyond a few weeks, if you cannot pass urine or open your bowels for several days, or if fatigue is worsening rather than improving in week two.
The bile duct injury that patients sometimes read about is rare, and when it occurs it usually announces itself with the jaundice, pain and fever listed above within days. Bile leaks and retained stones follow a similar pattern. Each is manageable, and management is simpler the sooner it starts.
Every judgment about restarting, adjusting or extending activity, medication or travel sits with the team that operated on you. This article explains the reasoning; they hold the details of your case.
Frequently asked questions
What is a gallbladder and can you live without it?
The gallbladder is a small pouch under the liver that stores bile, a fluid that helps digest fat, and releases it when you eat. You can live normally without it. After removal, bile flows steadily from the liver into the gut instead of in bursts, which is why some people notice looser stools after fatty meals in the early weeks.
How long is recovery after cholecystitis surgery compared with planned gallbladder removal?
Usually a little longer, even with the same keyhole incisions. An inflamed gallbladder means a harder dissection, more internal bruising and sometimes a drain or antibiotics, so people often sit at the slower end of the typical two-week keyhole range. If the operation was converted to open surgery, expect the six to eight week timeline instead.
When can I drive after gallbladder surgery?
When you can sit comfortably, turn fully to check mirrors and stamp on the brake without pain or hesitation, and once you are no longer taking sedating pain relief. The NHS puts this at about a week after keyhole surgery for most people and longer after open surgery. Check your motor insurance policy as well.
How soon can I fly after gallbladder removal?
There is no fixed guideline number. Most surgical teams prefer you to wait until a wound check has confirmed recovery is on track, commonly in the second week after uncomplicated keyhole surgery, and longer for long-haul flights or after open surgery. Walk the aisle hourly, stay hydrated and ask your team about clot-prevention measures beforehand.
What kind of exercise is recommended after gallbladder removal?
Walking from day one, building to brisk walks, gentle cycling or swimming once wounds are sealed, typically from the second week after keyhole surgery. Running follows as comfort allows. Core work and heavy resistance training should wait several weeks, or six to eight after open surgery, because bracing the abdomen loads healing tissue and raises hernia risk.
Is shoulder pain normal after gallbladder removal?
Yes, in the first few days. The carbon dioxide gas used in keyhole surgery irritates the diaphragm, which shares a nerve with the shoulder tip, so the brain feels the pain there. Walking and deep breathing help it clear, usually within a few days. Shoulder pain that is new or worsening after a week should be checked.
How much can I lift after keyhole gallbladder surgery?
MedlinePlus guidance advises keeping to roughly 10 to 15 pounds, about a full grocery bag, until your surgeon clears heavier loads, which for most keyhole patients means a gradual build after around two weeks. The limit protects the healing port sites from hernia and applies even once pain has gone.
When can I go back to work after gallbladder surgery for cholecystitis?
Desk-based work is usually possible around two weeks after keyhole surgery, sometimes sooner, and around six to eight weeks after open surgery according to NHS guidance. Physically demanding jobs that involve lifting generally need the longer end of each range. Your surgeon can provide a fitness note tailored to your actual duties.
Why do I have diarrhea after gallbladder removal and will it stop?
Without a gallbladder, bile trickles continuously into the gut rather than arriving with meals, and the excess can loosen stools, especially after fatty food. Mayo Clinic describes this as common and usually improving over weeks to months. Smaller, lower-fat meals often help early on; persistent or severe diarrhea should be discussed with your clinician.
When should I worry after gallbladder surgery?
Seek urgent care for fever or chills, worsening abdominal pain, yellow skin or eyes, dark urine or pale stools, persistent vomiting, spreading wound redness or pus, a painful swollen calf, sudden breathlessness or chest pain, or a new bulge at an incision. These can signal infection, a bile problem or a clot, all of which are easier to treat early.
References
- NHS: Gallbladder removal, recovery
- NHS: Acute cholecystitis
- MedlinePlus: Gallbladder removal, laparoscopic, discharge
- Cleveland Clinic: Gallbladder removal (cholecystectomy)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Ulcerative Colitis Flares: When Bleeding, Fever or Severe Pain Means Contacting Your Team Today
Contact your inflammatory bowel disease team the same day if an ulcerative colitis flare brings six or more bloody stools in 24 hours, a…

When Is ERCP Needed? Stuck Gallstones, Duct Narrowing and Bile Leaks Explained
ERCP is needed when a problem in the bile or pancreatic ducts has to be treated, not just seen. The commonest reasons are gallstones…

Dehydration During Gastroenteritis: The Signs That Mean It Is Time for Urgent Care
During gastroenteritis, dehydration becomes urgent when you cannot keep fluids down, pass little or no urine for eight hours or more, feel dizzy or…

What Realistic Long-Term Symptom Control Looks Like With Irritable Bowel Syndrome
For most people, irritable bowel syndrome is a long-term condition that comes and goes rather than one that steadily worsens or damages the bowel.…

Questions to Ask Your Gastroenterologist Before Starting Crohn’s Disease Treatment
Before starting Crohn's disease treatment, ask your gastroenterologist where the inflammation is and how severe it is, which medicine classes fit your situation and…

What Urgent Endoscopy Does for a GI Bleed: Clips, Injections and Heat to Stop the Flow
Urgent endoscopy treats a gastrointestinal bleed by passing a thin camera tube to the bleeding site and sealing it from the inside, using clips…