

Is Ankylosing Spondylitis Only a Young Man’s Disease? Myths That Delay Treatment

Key Takeaways
- The NHS puts ankylosing spondylitis at around twice as common in men as in women, which means roughly one in three people diagnosed is a woman.
- Most cases begin between about 20 and 30 years of age, but onset in adolescence and first diagnosis after 40 are both well documented.
- HLA-B27 sits on chromosome 6, so it is inherited equally from either parent, and each child of a carrier has a 1 in 2 chance of inheriting the gene.
- More than 9 in 10 people with AS carry HLA-B27, yet about 8 in 100 people in the general population carry it and most never develop the disease.
- A normal X-ray does not rule out the condition, because MRI can show active sacroiliac inflammation years before any bone change appears.
- A painful, red, light-sensitive eye in someone with inflammatory back pain may be uveitis and needs same-day assessment to protect vision.
Ankylosing spondylitis is not only a young man's disease. It most often begins between the late teens and early thirties and is diagnosed more frequently in men, but women, older adults and people of every ethnic background develop it too. Because the stereotype shapes who gets tested, many people wait years for a diagnosis. Persistent inflammatory back pain deserves a rheumatology assessment regardless of age or sex.
She was 41, a school administrator, and she had stopped mentioning her back. Every doctor she had seen since her late twenties told her the same thing: desk job, poor posture, probably stress. The stiffness that pinned her to the mattress each morning, easing only after a hot shower and a slow walk to the kitchen, never made it into her notes. When a new clinician finally asked whether the pain woke her at night and felt better once she moved, she started to cry. Nobody had asked that before.
Her story is common enough that rheumatologists have a shorthand for it. Among the most stubborn ankylosing spondylitis myths, who gets it sits at the very top, and the answer people carry in their heads is wrong in a way that costs years. The picture of a lean young man with a rigid, forward-stooped spine comes from textbooks written when only the most advanced cases could be recognized on an X-ray.
This article sets that picture against what the evidence actually shows, and explains why the gap between the two is one of the main reasons treatment starts late.
Who actually gets ankylosing spondylitis? The numbers behind the stereotype
Ankylosing spondylitis, usually shortened to AS, is a long-term inflammatory arthritis that mainly affects the spine and the sacroiliac joints, the two large joints where the base of the spine meets the pelvis. It belongs to a wider family called axial spondyloarthritis, a term that simply means inflammatory arthritis centered on the spine.
Here is what mainstream sources agree on. The condition tends to first appear in teenagers and young adults, and most cases begin in people aged roughly 20 to 30, according to the NHS. The same source puts the condition at around twice as common in men as in women. MedlinePlus Genetics estimates that AS affects somewhere between 0.1 and 1.4 percent of people worldwide, with the figure varying by population.
Read those numbers again, because they do not say what the stereotype says. “Around twice as common” means that for every two men diagnosed, roughly one woman is. That is a lot of women. “Most cases begin in the twenties” leaves a substantial minority who first notice symptoms as teenagers, or in their thirties and forties. And a diagnosis in the twenties often follows years of unexplained pain that started earlier.
The prevalence range also matters. At the higher end, AS is about as common as some conditions every family doctor sees weekly. It is not rare. What is rare is for a patient to walk in already suspecting it, because the public picture excludes so many of the people who have it.
The honest summary is this: a young man is the single most likely person to be diagnosed, but he is far from the only person who develops the disease. When a diagnostic habit is built around the most likely case, everyone else waits.
How ankylosing spondylitis actually works inside the spine
To understand why the condition hides, it helps to know what it is doing. AS is an autoimmune and autoinflammatory process: the immune system directs inflammation at the places where ligaments and tendons attach to bone, called entheses, and at the lining of certain joints. The sacroiliac joints and the small joints between vertebrae are favorite targets.
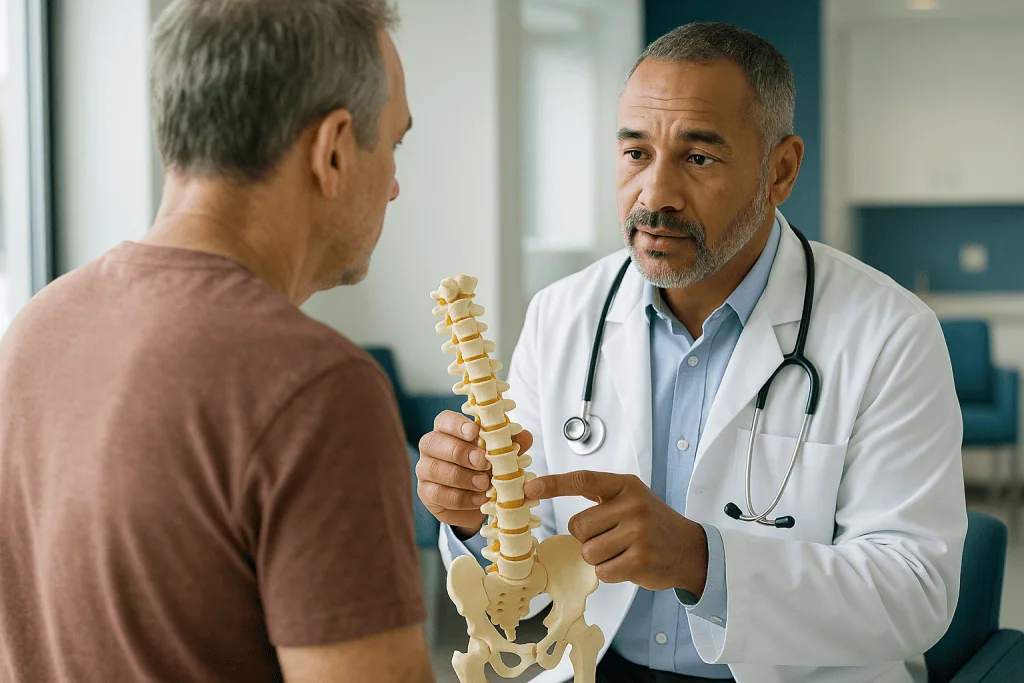
Inflammation at these sites produces the characteristic pain pattern. It builds during rest, which is why nights and early mornings are worst, and it eases with movement, because activity improves blood flow and drains inflammatory fluid. Clinicians call this inflammatory back pain to distinguish it from mechanical pain, the strained-muscle variety that worsens with activity and improves with rest. Stiffness that lingers well beyond half an hour after waking is one of the patterns the NHS lists as typical.
Over time, the body tries to repair repeatedly inflamed bone. The repair can overshoot. New bone forms along ligaments and across joint edges, creating bridges called syndesmophytes between vertebrae. When enough bridges form, segments of the spine fuse. The word ankylosing comes from the Greek for stiffening or fusing, and the fully fused spine, sometimes described as a bamboo spine on X-ray, is the late picture that gave the disease its name.
Two things follow from this mechanism. First, fusion is the end of a long road, not the beginning, so a normal-looking X-ray early on proves nothing. Second, the inflammation, not the fusion, causes most day-to-day symptoms, and inflammation is what modern treatment targets. According to the Mayo Clinic, the process can also involve the hips, shoulders, ribs, heels and the eyes, which is why AS is better understood as a whole-body condition that happens to favor the spine.
Where the "young man's disease" label came from, and why it sticks
The stereotype has a history, and knowing it helps you argue with it. For most of the twentieth century, AS could only be diagnosed with confidence once damage showed on plain X-rays of the sacroiliac joints. X-ray changes take years to appear, and they appear faster and more dramatically in some people than in others. The patients who reached the threshold earliest were disproportionately young men, so the early literature described a disease of young men, and the ratio quoted in older textbooks ran as high as ten to one.
That ratio was never a measurement of who had the disease. It was a measurement of who was being recognized. As imaging improved and MRI began to show active inflammation long before any bone changed, the sex ratio in diagnosed patients narrowed. The NHS now describes AS as around twice as common in men, and the broader category of axial spondyloarthritis, which includes people with inflammation but no X-ray damage, appears more evenly split.
The label persists for understandable reasons. Medical education leans on memorable patterns, and “young man, morning back stiffness” is memorable. Patients absorb the same shorthand from the internet. Back pain is also so common in the general population that clinicians need a reason to look harder, and the stereotype quietly supplies that reason only for people who match it.
Among ankylosing spondylitis myths about who gets it, this one is the most consequential because it operates before any test is ordered. A referral to rheumatology requires someone to suspect inflammation. If suspicion is reserved for one demographic, the test that could end years of uncertainty never happens for the others. The rest of this article walks through the groups most often left out.
Can women get ankylosing spondylitis? Yes, and they often wait longer
Women develop ankylosing spondylitis, and in the wider axial spondyloarthritis group they appear in numbers close to men. What differs is how the disease tends to present and how quickly it gets named.

Research summarized by major clinical sources suggests women more often report pain in the neck, upper back and peripheral joints, more fatigue, and more widespread tenderness, while men more often show the classic lower-back and sacroiliac pattern with earlier X-ray change. None of this is absolute. Plenty of women have textbook lower-back disease, and plenty of men have neck-predominant symptoms. But when a woman’s pain map does not match the diagram in the clinician’s head, the diagnosis drifts toward other explanations.
The alternative labels women receive are telling. Fibromyalgia, a chronic pain condition with widespread tenderness and fatigue, overlaps enough with early AS that one can be mistaken for the other, and the two can also coexist. Postpartum back pain, pelvic instability and hormonal changes are offered as reasons for sacroiliac pain in women of childbearing age. Each explanation may be partly true, which is exactly what makes it hard to challenge.
The consequence is a longer diagnostic journey. Reviews cited by rheumatology bodies consistently find women receive a diagnosis later than men on average, though the exact gap varies by study and country, so this article does not attach a single number to it.
What should a woman with persistent back pain take from this? Not that she has AS, but that the pattern of her pain matters more than her sex. Pain that wakes her in the second half of the night, stiffness that outlasts the first cup of coffee, relief with movement, and a history of eye inflammation, psoriasis or bowel disease are the details worth bringing to an appointment, stated plainly and early.
Ankylosing spondylitis age of onset: can it start after 40, or in childhood?
The typical onset window is real, but it is a window, not a wall. The NHS notes that most cases first start between 20 and 30 and that the condition tends to develop in teenagers and young adults. The Mayo Clinic describes signs usually beginning in late adolescence or early adulthood. Both descriptions leave room at each end.
At the younger end, spondyloarthritis can begin in childhood, where it is grouped under juvenile idiopathic arthritis. Children and adolescents often present differently from adults: a swollen knee or ankle, heel pain from inflammation at the Achilles attachment, or hip pain may appear years before the spine is clearly involved. A teenager whose “growing pains” are always in the same joints, worse in the morning, and accompanied by fatigue is describing something a pediatric rheumatologist would want to hear about. Decisions about assessment and any treatment in children belong entirely to the child’s own care team.
At the older end, two scenarios are common. The first is late recognition: a person in their forties or fifties finally receives a diagnosis for symptoms that began two decades earlier and were attributed to sport, work or posture. The second is genuinely later onset, which is less common but documented. In older adults the picture can be muddied by degenerative spinal changes that are themselves common, so distinguishing inflammatory from mechanical pain requires careful history and often MRI.
A practical point for older readers: age does not exclude AS, and it does not change the core questions. Does the pain improve with activity and worsen with rest? Is there prolonged morning stiffness? Is there a personal or family history of uveitis, psoriasis or inflammatory bowel disease? Those questions are age-neutral, and a clinician who asks them is doing exactly the right thing.
Is HLA-B27 inherited from mother or father? Understanding HLA-B27 gene inheritance
HLA-B27 is a variant of a gene that helps the immune system tell the body’s own cells from invaders. According to the NHS, more than 9 in 10 people with AS carry it. The same source estimates that around 8 in 100 people in the general population carry HLA-B27, and most of them never develop the condition. Both facts matter, and together they explain why the gene is a clue rather than a verdict.
The inheritance question has a clear answer. HLA-B27 sits on chromosome 6, not on a sex chromosome, so it can be passed down by either parent with equal likelihood. A child inherits one copy of the relevant chromosome from each parent, which means a parent who carries HLA-B27 on one copy has a 1 in 2 chance of passing it to each child, a figure the NHS uses when explaining risk to families. There is nothing about the mother’s or father’s side that changes the odds.
Carrying the gene is not the same as inheriting the disease. The NHS estimates that somewhere between 5 and 20 percent of children who inherit HLA-B27 from a parent with AS go on to develop the condition. Turned around, the large majority of children in that situation do not. Other genes, and environmental factors that are still poorly understood, decide the rest.
Two further points reduce confusion. First, some people with AS do not carry HLA-B27 at all, so a negative test cannot rule the condition out, which is one reason the NHS describes the test as not very reliable on its own. Second, the proportion of people with AS who carry the gene differs across ethnic groups, as does the gene’s frequency in the background population. A single global percentage hides real variation, and clinicians interpret the test in that context rather than in isolation.
Is ankylosing spondylitis just back pain? What happens beyond the spine
A second myth, nearly as damaging as the first, holds that AS is a spine problem and nothing more. The disease is systemic, which means it can involve organs that have no obvious connection to the back, and sometimes these are the first symptoms a person notices.
The eyes are the clearest example. Acute anterior uveitis, inflammation of the colored front layer of the eye, produces a painful, red, light-sensitive eye with blurred vision. The Mayo Clinic and NHS both list it as a common complication, and for some people an episode of uveitis precedes any back pain by years. An ophthalmologist who sees a young adult with uveitis will often ask about back stiffness for exactly this reason.
The gut is another. Inflammatory bowel disease, meaning Crohn’s disease or ulcerative colitis, occurs in a meaningful minority of people with AS, and many more have microscopic bowel inflammation without symptoms. Skin is a third: psoriasis sits in the same family of conditions, and the overlap is so common that some people carry a diagnosis of psoriatic arthritis and axial disease together.
Then there are the attachments. Inflammation where tendons meet bone can cause heel pain, pain under the foot, chest-wall pain where ribs join the breastbone, and tenderness at the elbows and knees. Chest-wall involvement can reduce how far the rib cage expands with each breath. Over the long term, the Mayo Clinic notes possible effects on the heart’s main valve and the aorta, as well as a higher risk of fractures in a stiffened spine.
Fatigue deserves its own mention. Many people describe it as the most disabling symptom, and it is not laziness or low mood; it is what chronic inflammation does to energy. When someone’s history includes several of these threads, the spine stops being the whole story and starts being one chapter.
What illness mimics ankylosing spondylitis? Conditions that mimic ankylosing spondylitis
Part of the delay comes from the fact that several conditions genuinely look like AS, and clinicians have to work through them rather than jump to one answer. Knowing the main look-alikes helps you understand why assessment takes the shape it does.
Mechanical low back pain is the most common competitor by far, simply because so many adults have it. The distinguishing features are direction of travel: mechanical pain usually worsens with activity and improves with rest, while inflammatory pain does the opposite. Disc problems can cause night pain too, but typically with nerve symptoms down the leg rather than prolonged morning stiffness.
Diffuse idiopathic skeletal hyperostosis, known as DISH, produces bony growths along the front of the spine that can resemble AS on X-ray. It tends to appear in older adults, spares the sacroiliac joints and is not driven by immune inflammation, so the history and the imaging pattern usually separate the two.
Within the spondyloarthritis family, psoriatic arthritis, reactive arthritis after certain infections, and arthritis linked to inflammatory bowel disease can all involve the spine. These are relatives rather than impostors, and the label a clinician chooses may shift over time.
Fibromyalgia, mentioned earlier, mimics the fatigue and widespread tenderness but does not cause objective inflammation on blood tests or MRI. Osteitis condensans ilii is a benign hardening of bone beside the sacroiliac joints, seen mainly in women who have given birth, and it can be mistaken for sacroiliitis on an X-ray. Infection and, rarely, cancer can cause night-time back pain and are the reasons unexplained symptoms always warrant a proper look.
None of this is a list for self-diagnosis. It is a map of why a rheumatologist asks the questions they ask and orders the tests they order, and why patience with that process, frustrating as it is, serves the final answer.
How ankylosing spondylitis is diagnosed: X-ray, MRI and the non-radiographic form
There is no single test for AS. Diagnosis rests on a combination of history, physical examination, blood tests and imaging, and the Mayo Clinic is explicit that the process can take time. Understanding what each piece contributes keeps expectations realistic.
The history carries the most weight. A clinician listens for inflammatory back pain lasting more than a few months, onset before middle age, prolonged morning stiffness, improvement with exercise, night pain, and the extra-spinal threads described earlier. Examination checks how far the spine bends, how the sacroiliac joints respond to pressure and how much the chest expands.
Blood tests add supporting evidence. Markers of inflammation such as C-reactive protein, a protein the liver releases during inflammation, may be raised, though they are normal in a substantial share of people with active disease. HLA-B27 testing is interpreted alongside everything else for the reasons already covered.
Imaging is where the biggest change of the past two decades sits. Plain X-rays show established damage but miss early inflammation. MRI can reveal bone-marrow edema, a sign of active inflammation, in the sacroiliac joints long before any X-ray change. This is how the category of non-radiographic axial spondyloarthritis came to exist: inflammation on MRI, symptoms consistent with the disease, but X-rays that still look normal.
| Feature | Non-radiographic axial spondyloarthritis | Ankylosing spondylitis (radiographic) |
|---|---|---|
| X-ray of sacroiliac joints | No definite damage | Definite changes present |
| MRI | May show active inflammation | Inflammation and/or structural change |
| Sex ratio in diagnosed patients | Closer to even | More men than women |
| Symptoms and burden | Can be similar | Can be similar |
| Treatment approach | Largely the same principles | Largely the same principles |
The table carries the message of this whole article in miniature. The group once invisible to X-rays, with its more even sex ratio, has the same inflammation and often the same burden. Decisions about which tests to order, and in what sequence, belong with the assessing clinician.
Who is usually treated straight away, and who is asked to wait and watch
Once the question shifts from “what is this” to “what now,” the answer depends on activity, impact and risk, not on age or sex. Guideline-level practice, as summarized by the NHS and Mayo Clinic, follows a few broad principles.
Nearly everyone with a confirmed diagnosis is offered the foundation: education about the condition, a structured exercise and physiotherapy program, advice on stopping smoking because smoking is associated with faster progression, and a medicine from the non-steroidal anti-inflammatory class, which reduces the inflammation driving pain and stiffness. These are starting points rather than consolation prizes, and for some people they remain the whole plan.
Escalation to biologic medicines, which are antibodies that block specific inflammatory signaling proteins such as tumor necrosis factor or interleukin-17, is usually considered when disease remains active despite the foundation. Activity is judged using patient-reported scores, examination findings, inflammatory markers and imaging. Someone with high scores, raised markers and MRI inflammation despite months of anti-inflammatory treatment is a typical candidate for discussion. The decision, including which class and whether now is the right time, sits with the rheumatologist.
Who is usually asked to wait? People whose symptoms are mild and well controlled on the foundation, people whose picture is not yet clear enough to confirm the diagnosis, and people with active infections or other conditions that need to be addressed before immune-modulating treatment is safe. Pregnancy and plans for pregnancy change the conversation rather than ending it, and are discussed individually.
Surgery is reserved for specific situations: a hip so damaged that replacement restores function, or, rarely, correction of severe spinal deformity. The Mayo Clinic describes most people as never needing it.
Nothing in this framework asks how old you are or which box you tick on a form. The right question is whether inflammation is active and what it is costing you.
What the first weeks and months of treatment usually look like
People newly diagnosed often ask what to expect, and the honest answer is that the early period is about building habits and gathering information rather than waiting for a switch to flip.
Exercise comes first and continues throughout. A physiotherapist experienced in inflammatory spinal disease typically designs a program that stretches the spine and hips, strengthens the back and core, keeps the chest wall mobile and works on posture. Many people notice morning stiffness easing within weeks of consistent practice, though individual experience varies and no source promises a particular result. Swimming and other low-impact activities are frequently suggested because they move the spine without loading it.
If an anti-inflammatory medicine is prescribed, its effect on pain and stiffness is usually assessed over a period of weeks, with the prescribing clinician adjusting the plan based on response and tolerance. The Mayo Clinic notes that this class carries risks to the stomach lining, kidneys and cardiovascular system that need monitoring, which is why the medicine, the review schedule and any changes are all decisions for the prescriber.
When a biologic is started, the NHS describes an assessment of response after about 12 weeks to judge whether the medicine is working well enough to continue. Before starting, screening for latent infections such as tuberculosis is standard, because these medicines dampen parts of the immune system. During treatment, people are asked to report fevers and infections promptly.
Follow-up in the first year is usually more frequent than later, with appointments to track symptom scores, inflammatory markers, medicine effects and any eye, gut or skin involvement. Imaging is repeated only when it would change a decision.
Expect a relationship with your care team rather than a one-time fix. The condition is long-term, and the plan evolves with it.
What people often get wrong about ankylosing spondylitis
Myths survive because each contains a sliver of truth stretched too far. Here are the ones clinicians hear most, with what the evidence actually supports.
- “Only young men get it.” Men are diagnosed roughly twice as often, and onset is most common in the twenties, according to the NHS. Women, teenagers and adults past 40 are all part of the picture.
- “If your X-ray is normal, you don’t have it.” X-rays show damage, not inflammation. MRI can show active disease years before bone changes, which is the whole basis of non-radiographic axial spondyloarthritis.
- “A negative HLA-B27 rules it out.” More than 9 in 10 people with AS carry the gene, per the NHS, but some do not, and most carriers never develop the disease.
- “It’s just back pain; everyone has that.” Inflammatory pain has a recognizable signature, and the disease can involve eyes, gut, skin, heels and chest wall.
- “Rest is the answer.” Inflammatory pain worsens with rest. Movement is part of treatment, not a risk to it.
- “Everyone ends up with a fused spine.” Fusion is a late outcome in a subset of people, and it is not the inevitable end of the road for everyone diagnosed today.
- “It’s caused by an injury or bad posture.” The driver is immune inflammation with a strong genetic contribution. Posture problems can follow the disease; they do not cause it.
- “Children can’t have it.” Spondyloarthritis can begin in childhood, often starting in the knees, ankles or heels rather than the spine.
One pattern connects nearly every item on this list: each one gives a clinician or a patient a reason not to look further. That is precisely why correcting them is not a matter of trivia. When the stereotype is the gatekeeper, the people who do not match it pay in years.
Questions to ask your care team about ankylosing spondylitis
A rheumatology appointment is short and the vocabulary is dense. Walking in with questions written down changes the conversation from a lecture into an exchange. These are the ones that tend to produce the most useful answers.
- Which features of my history and tests point toward axial spondyloarthritis, and which point away from it?
- Do I have the radiographic form or the non-radiographic form, and does that distinction change anything about my care?
- Was I tested for HLA-B27, and how are you weighing the result given my family background?
- Which of my symptoms do you attribute to inflammation, and which might have another cause that we should treat separately?
- How will you measure whether my disease is active, and how often will we check?
- What is the goal of the current plan, and what would prompt you to consider a change?
- What are the known risks of the medicines you are suggesting, and what monitoring goes with them?
- Which symptoms in my eyes, gut or skin should I report, and to whom?
- Can you refer me to a physiotherapist who works with inflammatory spinal conditions?
- Is there anything about my work, sport or daily routine that you would like me to adjust?
- If I am planning a pregnancy, now or in the future, how does that affect the plan?
- What should I do if I have a sudden flare between appointments?
Bring a brief timeline too: when the pain started, what it does at night and in the morning, any episodes of eye inflammation, any relatives with similar problems or with psoriasis or bowel disease. Specific details help the team more than a general sense that something is wrong. And if an answer does not make sense, say so. A good team would rather explain twice than have you leave uncertain.
When to call your doctor: red-flag signs with ankylosing spondylitis
Most of the time, AS is managed through planned appointments. A few situations should not wait for the next one, and knowing them in advance removes the hesitation that leads people to tough it out.
Seek same-day care for a painful, red eye, especially with light sensitivity or blurred vision. This can be acute anterior uveitis, which the Mayo Clinic lists as a common complication, and prompt ophthalmology treatment protects sight. Do not assume it will settle by morning.
Seek emergency care for any new weakness or numbness in the legs, numbness in the groin or inner thighs, difficulty controlling the bladder or bowels, or sudden severe back or neck pain after a fall or minor accident. A spine stiffened by long-standing AS fractures more easily than a flexible one, and these symptoms can indicate pressure on the spinal cord or nerves.
Contact your care team promptly for a fever, chills or signs of infection while taking a biologic or other immune-modulating medicine, since these medicines reduce the body’s ability to fight infection. The same applies to a persistent cough, unexplained weight loss or night sweats on treatment.
Chest pain, breathlessness, palpitations or fainting warrant urgent assessment. Chest-wall inflammation is a common and usually benign cause of chest pain in AS, but heart and aortic involvement are documented, and the distinction is not one to make at home.
Also call if you notice persistent diarrhea, blood in the stool or unexplained abdominal pain, which may signal inflammatory bowel disease, or if a flare is severe enough to stop you working, sleeping or caring for yourself.
Finally, if your symptoms are changing in a way that worries you, that alone is reason enough to call. The treating team decides what needs to happen next; your job is to make sure they hear about it.
Frequently asked questions
Who is most likely to get ankylosing spondylitis?
A man in his twenties is the single most likely person to receive a diagnosis, but he is far from the only one. According to the NHS, the condition is around twice as common in men and most often begins between 20 and 30. Women, teenagers and adults past 40 also develop it, and people who carry the HLA-B27 gene or have a close relative with the disease are at higher risk.
Can women get ankylosing spondylitis?
Yes. Women make up a substantial share of people with ankylosing spondylitis, and in the wider axial spondyloarthritis group the split between women and men is closer to even. Women more often report neck and upper-back pain, fatigue and peripheral joint symptoms, which do not match the classic picture, and research consistently finds they wait longer for a diagnosis than men.
What is the typical ankylosing spondylitis age of onset?
The NHS reports that most cases first begin between the ages of 20 and 30, and the Mayo Clinic describes onset in late adolescence or early adulthood. That window is a tendency rather than a limit. Spondyloarthritis can begin in childhood, often in the knees, ankles or heels, and some people develop or finally recognize the condition in their forties or later.
Is HLA-B27 inherited from mother or father?
Either parent can pass it on, with equal likelihood. HLA-B27 is carried on chromosome 6, not on a sex chromosome, so a carrier parent has a 1 in 2 chance of passing the gene to each child regardless of whether they are the mother or father, according to the NHS. Inheriting the gene is not the same as inheriting the disease; most carriers never develop ankylosing spondylitis.
How does HLA-B27 gene inheritance affect my children's risk?
If you have ankylosing spondylitis and carry HLA-B27, each child has a 1 in 2 chance of inheriting the gene, and the NHS estimates that between 5 and 20 percent of children who inherit it from an affected parent go on to develop the condition. Put the other way, most children in that situation do not. Genetic questions about your own family are best discussed with your rheumatologist or a genetic counselor.
What illness mimics ankylosing spondylitis?
Several conditions can look similar. Mechanical low back pain is the most common, though it worsens with activity rather than rest. Diffuse idiopathic skeletal hyperostosis produces spinal bone growth in older adults without immune inflammation. Fibromyalgia shares fatigue and tenderness but not objective inflammation. Psoriatic arthritis, reactive arthritis and bowel-disease-related arthritis are close relatives. Distinguishing them requires a clinician’s history, examination and imaging.
Which conditions that mimic ankylosing spondylitis are most often confused with it in women?
Fibromyalgia and postpartum pelvic or sacroiliac pain are the labels women most often receive before an eventual diagnosis of axial spondyloarthritis. Osteitis condensans ilii, a benign hardening of bone beside the sacroiliac joints seen mainly after pregnancy, can also be mistaken for sacroiliitis on an X-ray. Each can coexist with ankylosing spondylitis, which is why a careful inflammatory-pain history matters.
Can you have ankylosing spondylitis with a negative HLA-B27 test?
Yes. The NHS reports that more than 9 in 10 people with the condition carry HLA-B27, which still leaves a minority who do not, and the proportion varies across ethnic groups. For this reason the NHS describes the test as not very reliable on its own. Clinicians interpret it together with symptoms, examination findings, inflammatory markers and MRI rather than treating a negative result as a verdict.
Are there any celebrities with ankylosing spondylitis?
A number of public figures in sport, music, acting and broadcasting have spoken openly about living with ankylosing spondylitis, and several are women or were diagnosed well past their twenties. Their stories matter less for who they are than for what they show: the condition appears in people who do not fit the stereotype, and visible examples help others recognize their own symptoms and seek assessment sooner.
Does ankylosing spondylitis always lead to a fused spine?
No. Spinal fusion is a late outcome that develops in a subset of people over many years, and it is not inevitable. The Mayo Clinic notes that most people never need surgery. Modern management focuses on controlling the inflammation that drives symptoms and damage, through exercise, anti-inflammatory and, where appropriate, biologic medicines, with the treating team deciding what suits each individual.
References
- NHS: Ankylosing spondylitis
- NHS: Ankylosing spondylitis, causes
- MedlinePlus Genetics: Ankylosing spondylitis
- NIH NIAMS: Ankylosing spondylitis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Physical Therapy for Psoriatic Arthritis: Keeping Strength and Flexibility Between Flares
Physical therapy for psoriatic arthritis uses individually prescribed strengthening, range-of-motion, aerobic and posture work to protect joints, tendons and muscles between flares, while teaching…

Osteoarthritis Treatment Before Joint Replacement: The Non-Surgical Steps Tried First
Before joint replacement, guidelines ask people with osteoarthritis to try a stepwise non-surgical plan: a structured exercise and strengthening program, weight management where relevant,…
Protecting Hands and Feet From Cold With Scleroderma: Practical Care Between Visits
Protecting hands and feet from cold with scleroderma means keeping the whole body warm, not just the fingers: layered clothing, insulated gloves and socks…

Swollen Joints on Both Sides: When a Rheumatologist Suspects Rheumatoid Arthritis
Swelling in the same joints on both sides of the body, especially the knuckles, wrists or toes, together with morning stiffness that lasts longer…
What to Bring to a Sjogren’s Syndrome Consultation: Eye Reports, Dental Records and More
Bring any eye examination reports (including Schirmer or tear-film results), dental records and recent X-rays, a dated timeline of dryness, fatigue and joint symptoms,…

Fibromyalgia Myths, Corrected: Real Pain, Real Diagnosis and a Real Treatment Plan
Fibromyalgia is a recognized chronic pain condition, not an imaginary or purely psychological one. Research points to altered pain processing in the brain and…