

Laser vs Drill in Dentistry: Where Lasers Help and Where Conventional Tools Still Win

Key Takeaways
- A Cochrane review of nine randomized trials found no difference between lasers and drills in how completely they removed decay, with the evidence rated low certainty.
- The same review found lasers were linked to less pain during treatment and less need for local anesthetic for cavities, but treatment often took longer.
- Hard-tissue lasers work by heating the water inside enamel and dentin so tiny bursts flake tooth structure away, which is why nothing spins or touches the tooth.
- Old amalgam fillings cannot be removed with a laser because the metal reflects and overheats, and shaping a tooth for a crown still requires rotary instruments.
- Soft-tissue lasers seal small blood vessels as they cut, so gum reshaping and frenectomy procedures often involve little bleeding and no stitches.
- Sensitivity after any new filling usually settles within a few weeks, and a filling that feels high when you bite should be adjusted rather than tolerated.
Dental lasers and conventional drills are both accepted tools, and neither is better for every job. Lasers work well for soft-tissue procedures such as gum reshaping and may reduce discomfort when removing small cavities, though the evidence is low certainty. Drills remain the standard for removing old fillings, shaping teeth for crowns and larger restorations. Your dentist chooses based on the tooth, the task and your history.
The sound arrives before the sensation: a rising whine, then the faint smell of warm enamel. Most adults can summon it from memory without trying. So when a dentist mentions that a small filling could be done with a laser instead, the question that follows is rarely technical. It is simply: would that be easier?
That question sits at the heart of the laser vs drill dentistry debate, and the honest answer is more interesting than either camp usually admits. Lasers have earned a real place in modern practice, particularly for work on gums and other soft tissue. Drills, unglamorous as they are, still do things a beam of light cannot.
This explainer walks through how each tool actually works, what the published trials show about pain and cavity removal, where each one shines, and which questions are worth asking before you settle back into the chair. The decision, as always, belongs to you and the team treating you.
What does laser vs drill dentistry actually compare?
Start with a small correction to the framing. The comparison is not between two rival philosophies of dentistry but between two instruments that overlap in only part of what they do. A drill is a rotary cutting tool: a tiny abrasive or steel tip, called a bur, spins inside a hand-held unit known as a handpiece. A dental laser is a device that produces a focused beam of light at a single wavelength, and different wavelengths interact with different tissues.
That second point matters more than any marketing sentence you will read. Some lasers are built for hard tissue, meaning enamel (the tooth’s outer shell) and dentin (the softer layer beneath it). Others are built for soft tissue, meaning gums, the lining of the cheeks and the small bands of tissue under the lip and tongue. A practice that owns a soft-tissue laser cannot use it to remove decay, and a practice that owns a hard-tissue laser still keeps a drill in every operatory.
The Mayo Clinic describes cavity treatment in terms of what needs to happen to the tooth rather than which tool achieves it: decayed material is removed, and the space is restored with a filling material chosen to suit the location and the size of the damage. Seen that way, the laser and the drill are alternative routes to the same destination, and the choice depends on the terrain.
Three questions organize the rest of this article. Which tool removes decay reliably? Which one is more comfortable, and how good is the evidence for that? And where does each tool have no real competition? Keep those in mind, and the debate loses most of its heat.
How does a dental drill work, and why does it feel the way it does?
A high-speed handpiece is powered by compressed air or an electric motor and spins a bur fast enough to grind through enamel, which is the hardest substance in the human body. The bur does the cutting; a fine spray of water cools the tooth so friction does not heat the pulp, the living core of nerve and blood vessels at the center of the tooth. A slower handpiece, with more torque and less speed, is often used for finishing and for cleaning out softer, decayed dentin.
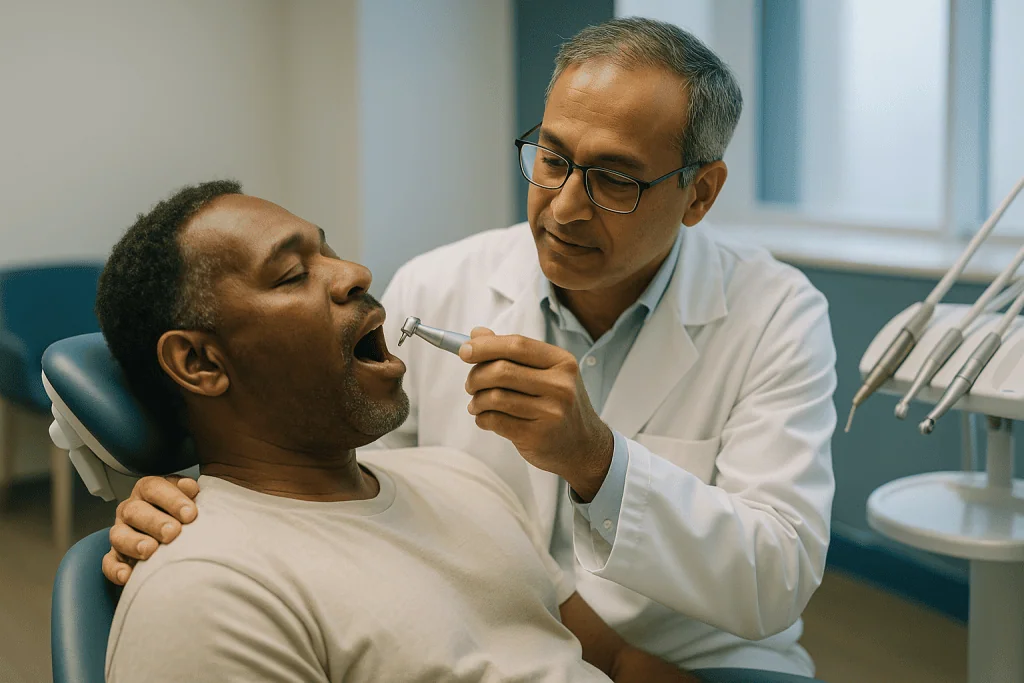
Why the distinctive experience? Three things arrive at once. The whine is the turbine or motor itself. The vibration travels through the tooth into the jawbone and is felt rather than heard. And pressure, however light, registers on a tooth that is already sensitive because decay has brought bacteria closer to the nerve. Local anesthetic addresses the pain signal from the tooth, but it does not switch off the sense of vibration or the sound, which is why some people describe a numb filling as unpleasant rather than painful.
The drill’s great advantage is control. A trained hand can shape a tooth precisely, undercut a cavity so a filling locks in place, smooth a rough margin and remove an old metal filling in one visit. The Cleveland Clinic notes that fillings can be placed in several materials, including composite resin, ceramic and metal alloys, and the drill prepares a tooth for any of them.
None of this is new technology, and that is partly the point. Decades of clinical experience, training curricula and long-term follow-up data are built around the rotary drill. Any newer tool is measured against it.
How does a dental laser cut a tooth without touching it?
The physics is easier than it sounds. Enamel and dentin contain a small amount of water, and decayed tissue contains considerably more. Hard-tissue dental lasers, most often erbium lasers, emit light at a wavelength that water absorbs strongly. When the pulse strikes the tooth, water in the tissue heats and expands almost instantly, and the tiny pressure burst flakes away a microscopic layer of tooth structure. Because decayed dentin holds more water than healthy dentin, the laser removes it somewhat more readily, which is why the approach is sometimes described as selective.
A water spray runs alongside the beam, just as it does with a drill, to keep the tooth cool and wash debris away. There is no rotating part and no direct contact between instrument and tooth, so the vibration that many people associate with the drill is largely absent. The sound is a rapid popping or clicking rather than a whine.
Soft-tissue lasers work on a different principle. Diode lasers, and some others, emit wavelengths that are absorbed by pigment and blood rather than water. They cut gum tissue while sealing small blood vessels as they go, which is why laser gum procedures often involve little bleeding and may not need stitches.
Safety is built around the beam rather than the tooth. Everyone in the room wears protective eyewear matched to the laser’s wavelength, reflective instruments are kept out of the path, and the dentist controls energy and pulse settings carefully because too much heat can irritate or damage the pulp. The Cochrane review on laser caries removal specifically flagged that trials did not adequately report effects on pulp health, so that caution is grounded in a real gap in the evidence, not just good manners.
Laser cavity removal: what the evidence really shows
The most rigorous summary comes from a Cochrane systematic review that pooled nine randomized trials comparing laser cavity removal with the conventional drill in both children’s and adult teeth. Its conclusions deserve to be quoted carefully rather than rounded up into a headline.

On the central question of whether the laser removed decay as completely as the drill, the review found no meaningful difference between the two. That is reassuring for people offered a laser filling, but it is not a victory for the laser either. The review rated the quality of this evidence as low, largely because trials were small, used different lasers and settings, and often did not blind the person assessing the outcome.
On durability, the picture is thinner still. The review found insufficient evidence to say whether fillings placed after laser preparation last as long as those placed after drilling, whether their edges seal as well, or whether the pulp beneath fares any differently over time. In plain terms, no one has yet followed enough laser-prepared fillings for long enough to answer those questions with confidence.
What the laser did appear to offer was a comfort advantage: fewer participants reported pain during treatment and fewer needed local anesthetic. Again, the certainty was low, and the effect varied across trials. Treatment time was sometimes longer with the laser, a practical point that rarely appears in promotional material.
A fair reading, then, is this. Laser cavity removal can be an acceptable alternative for suitable cavities, it may be more comfortable for some people, and the long-term data have not caught up. Anyone who tells you the science is settled in either direction is ahead of the evidence.
Does laser dentistry hurt less than the drill?
This is the question people actually want answered, so it deserves a direct response: often, for small cavities, somewhat less, and with less need for a numbing injection, according to the low-certainty evidence in the Cochrane review. That is a real finding. It is also a modest one, and the reasons behind it help explain who is most likely to benefit.
Pain during drilling comes from several sources. Heat reaching the pulp, pressure on a sensitive tooth, and vibration that the brain interprets as threatening all contribute. A laser reduces vibration and pressure because nothing touches the tooth. Each pulse is brief, so heat has less chance to accumulate when settings are correct. Some people who find injections themselves the worst part of a visit value the chance to avoid one.
Limits apply. Deep cavities close to the nerve tend to be sensitive whatever removes the decay, and dentists frequently still use local anesthetic with a laser in those cases. The laser is also slower for larger lesions, and a longer procedure can offset a gentler one. People with a strong gag reflex or difficulty keeping still may find the extended time harder, not easier.
Sound plays an underrated role. The Mayo Clinic and other patient sources recognize dental anxiety as a common reason people delay care, and for many the drill’s noise is the trigger rather than any actual pain. The laser’s popping sound is different, not silent, and some people find it just as off-putting. Telling your dentist what specifically bothers you, whether noise, needles, vibration or the feeling of losing control, is more useful than asking which tool is gentler in the abstract.
Where lasers genuinely help: gums, lips and soft tissue
If the case for hard-tissue lasers is cautious, the case for soft-tissue lasers is considerably stronger in everyday practice, and it rests on a simple mechanical fact: a beam that cuts and seals at the same time makes bleeding, sutures and swelling less of an issue than a scalpel does.
Common examples include reshaping gum tissue that covers too much of a tooth, a procedure sometimes called a gingivectomy when tissue is removed and gum contouring when it is sculpted. Lasers are also used for a frenectomy, which means releasing a tight band of tissue under the tongue or upper lip that can interfere with feeding, speech or the position of front teeth. Small growths or suspicious patches inside the mouth can be removed for laboratory examination, and lasers are used to treat painful mouth ulcers or cold sores with the aim of easing symptoms.
In gum disease, lasers are used to disinfect and remove inflamed tissue lining the pocket between tooth and gum. Here the evidence is genuinely mixed. Traditional deep cleaning, called scaling and root planing, remains the foundation of treatment for periodontitis, the form of gum disease that damages bone, and the Mayo Clinic describes it as the standard nonsurgical approach. Lasers are generally positioned as an adjunct to that cleaning rather than a replacement, and studies have not consistently shown that adding a laser improves long-term outcomes.
Where soft-tissue lasers earn their keep is in precision, comfort and a tidy field of view. Where they have not earned it is as a substitute for the mechanical removal of hardened plaque, which still requires an instrument that physically scrapes the root surface.
Where conventional tools still win
Some tasks remain drill territory, not because dentistry is slow to change but because of what lasers physically cannot do. Start with old metal fillings. Amalgam, the silver-colored alloy used for generations, reflects and absorbs laser energy unpredictably and can heat dangerously; it is removed with a bur, full stop. Anyone with a mouthful of older restorations will meet the drill again whenever one needs replacing.
Crown preparation is the second frontier. When a tooth needs a crown, a cap that covers the whole visible tooth, the dentist must reduce it evenly on every surface to a precise shape and depth so the crown fits. Rotary instruments do this quickly and controllably. Lasers can remove enamel, but shaping a tooth in three dimensions to close tolerances is far slower and less predictable with a beam.
Cavities between teeth, under existing fillings or wrapping around the side of a tooth are difficult to reach with a laser tip that must be aimed in a straight line. Large cavities take longer with a laser, and the Cochrane review noted that treatment time was sometimes greater. Polishing and finishing a filling so its edges are smooth and its shape fits your bite is done with fine burs and discs, whichever tool started the job.
The Cleveland Clinic lists fillings, crowns, inlays and onlays among the routine restorations for decayed teeth, and every one of them depends on rotary instruments at some stage. A practice that offers lasers has added a tool, not retired one. Understanding that spares you the disappointment of expecting a drill-free visit and then hearing the handpiece start.
Laser vs drill dentistry at a glance
The table below summarizes where each tool sits for common tasks, based on how the instruments work and on the evidence discussed above. It is a guide to the conversation with your dentist, not a substitute for it; the right choice for a specific tooth depends on its size, depth, position and what else is already in your mouth.
| Task | Dental laser | Conventional drill | What the evidence says |
|---|---|---|---|
| Small to moderate cavity in enamel or dentin | Suitable, may need less anesthetic | Standard approach | No difference in decay removal; low-certainty evidence of less pain (Cochrane) |
| Deep cavity near the pulp | Possible, often with anesthetic | Standard approach | Long-term pulp effects of laser not well studied |
| Removing old amalgam filling | Not appropriate | Required | Metal reflects and overheats under laser |
| Shaping a tooth for a crown | Impractical | Required | Rotary tools give speed and 3D control |
| Gum reshaping, frenectomy, small biopsy | Well suited | Scalpel used instead | Less bleeding; often no stitches |
| Gum disease deep cleaning | Adjunct only | Scaling and root planing standard | Adding laser not consistently shown to improve outcomes |
| Finishing and polishing a filling | Not used | Required | Fine burs and discs shape the final surface |
Two patterns stand out. Lasers lead where the target is soft tissue or a contained lesion and where the goal is comfort with minimal bleeding. Drills lead wherever speed, three-dimensional shaping or existing metal is involved. Most people who receive laser treatment will still experience the drill at some point in the same course of care, and that is normal rather than a sign anything went wrong.
Who is laser treatment usually for, and who is usually asked to wait?
Dentists tend to suggest a hard-tissue laser for people with small or moderate cavities on accessible surfaces, especially those who dread injections or find drill vibration intolerable. It can also suit someone having a soft-tissue procedure alongside a filling, since one instrument may handle both. People with a documented allergy or strong aversion to local anesthetic sometimes ask about lasers for exactly this reason, though the decision to skip anesthetic rests with the dentist, who will judge the depth of decay.
Soft-tissue laser work is commonly offered to adults and children with excess gum tissue, tight frenula, small benign growths or recurrent ulcers, and to people whose medical history makes bleeding a concern, because the beam seals vessels as it cuts. Even so, anyone taking blood-thinning medicine should tell the team in advance; the prescribing clinician decides whether any adjustment is needed, and stopping such a medicine without that advice is never appropriate.
Who is usually steered toward conventional tools instead? People whose main problem is an old amalgam filling, a tooth needing a crown, decay tucked between teeth or a very large lesion, for the practical reasons covered earlier. Those with extensive gum disease need mechanical cleaning first, with a laser as an optional extra rather than the plan.
Some situations call for waiting or extra caution regardless of tool. Active infection with swelling, an untreated abscess or uncontrolled medical conditions may need to be addressed before elective work. The NHS advises that how often you need a check-up is set by your dentist based on your risk, and the same individualized judgment applies here. Being asked to wait is not a refusal; it is sequencing.
Laser dentistry for kids: what parents usually ask
Parents raise this question more than any other group, and the interest is understandable. A child’s first experience of the drill can shape a lifetime of attitudes toward dental care, and a tool that avoids vibration and, sometimes, a needle sounds like a gift.
The evidence supports cautious optimism. The Cochrane review included trials in children’s primary teeth as well as permanent teeth and found no difference in how completely decay was removed, with some low-certainty signal of less pain and less need for anesthetic. Primary teeth have thinner enamel and larger pulps relative to their size, which means heat management matters and the dentist’s settings and technique carry real weight.
Preparation is mostly about language and expectation. Children do well when they know in advance that the laser makes a popping sound, that water will spray, that they will wear special glasses and that they may feel cold or a light tapping. Many pediatric practices let a child hold the safety eyewear or hear the sound before starting. Keeping still for longer is the main challenge, because laser cavity removal can take more time than drilling; a child who fidgets may do better with a shorter conventional appointment.
Soft-tissue procedures in children, particularly releasing a tight tongue or lip tie, are frequently done with lasers because of limited bleeding and often no stitches. Aftercare focuses on gentle cleaning of the area, soft foods and any stretching exercises the team demonstrates.
Comfort measures, whether a numbing gel, local anesthetic or, in some settings, sedation, are decided entirely by the treating dentist according to the child’s age, health and the procedure. Parents can ask what will be used and why, and should never adjust any medicine on their own.
What do the following days usually look like after either tool?
Recovery after a filling is broadly similar whichever instrument prepared the tooth, because it is the filling material and the tooth’s own response, not the cutting method, that shape the next week or two.
If local anesthetic was used, numbness in the lip, cheek or tongue typically fades over the following few hours, according to the Cleveland Clinic’s guidance on dental fillings. Eating is best delayed until sensation returns, to avoid biting a numb cheek. If a laser filling was completed without anesthetic, that waiting period simply does not apply.
Sensitivity to cold, sweet foods or pressure is common with any new filling and, the Cleveland Clinic notes, usually settles within a few weeks as the tooth calms down. A filling that feels high when you bite, so that your teeth meet unevenly, should be adjusted at a brief return visit rather than tolerated, because the constant extra load can make a tooth ache.
After soft-tissue laser work, the treated area often looks pale or white for several days as it heals from the inside out. Mild soreness, a little swelling and sensitivity to spicy or acidic food are typical. Keeping the area clean with gentle brushing and any rinse the team recommends helps, and most people return to normal eating within a week or so, though the team will give a timeline for your specific procedure.
Whatever the tool, the rules for protecting the result are the same ones the NIH’s dental institute emphasizes for preventing decay in the first place: brush twice daily with a fluoride toothpaste, clean between teeth, limit sugary snacks and drinks, and keep the review schedule your dentist sets.
What people often get wrong about laser dentistry pros and cons
Myths gather quickly around any technology that promises less pain, so it is worth clearing a few.
The first is that lasers mean no needles, ever. The evidence shows a reduced need for anesthetic for small cavities, not its elimination. Deep decay near the nerve is often numbed regardless, and soft-tissue procedures frequently involve at least a topical numbing gel. If avoiding an injection is your priority, ask directly rather than assuming.
The second is that lasers are more precise, so fillings must last longer. Precision at the moment of cutting has not been shown to translate into longer-lasting restorations; the Cochrane review found insufficient evidence on durability either way. A filling’s lifespan depends mostly on its size, the material, your bite and how well the tooth is cared for afterward.
The third is the reverse: that lasers are experimental or unproven. Hard-tissue lasers have been used clinically for many years and are accepted tools; what remains uncertain is long-term comparative data, not basic safety when used correctly.
A fourth myth holds that laser gum treatment can replace deep cleaning for periodontitis. The mechanical removal of hardened deposits from the root surface remains the core of treatment, and lasers are an adjunct whose added value is not consistently demonstrated.
The fifth is that a practice with a laser will never use a drill on you. As the earlier sections explain, crowns, old metal fillings and final polishing all rely on rotary instruments. Finally, some people believe laser treatment is faster. For soft tissue that is often true; for cavities, it is frequently slower. Weighing these pros and cons honestly leads to a better decision than either enthusiasm or suspicion.
Questions to ask your care team
A short, specific conversation before treatment does more for comfort than any single piece of equipment. These questions are designed to draw out the reasoning behind a recommendation rather than to challenge it.
- Which type of laser do you use, and is it designed for hard tissue, soft tissue or both? This tells you immediately whether cavity removal by laser is even an option here.
- For my particular cavity, would you expect the laser or the drill to give a better result, and why? Listen for the tooth’s location, depth and any existing fillings in the answer.
- Will I still need local anesthetic, and what will you do if I start to feel something partway through?
- Will any part of this visit still involve the drill, for example to finish or polish the filling?
- How long do you expect the appointment to take with each approach?
- What filling material do you recommend, and does the choice of laser or drill affect that?
- If this is a gum procedure, what should the area look like as it heals, and what would be a sign that something is not right?
- I take these medicines and have these conditions; does any of that change your plan or the tool you would choose?
- What is the follow-up, and who do I contact if I have pain, swelling or a filling that feels high?
Write the answers down or ask for them in writing. Anxiety makes details slippery, and having the plan in front of you later is calming. The team may reasonably say that they will decide some things once they see the tooth up close; that flexibility is part of good care, not a dodge, and the final call on technique always sits with the dentist treating you.
When to call your doctor
Most people feel little more than mild sensitivity after a filling or a soft-tissue laser procedure, and that discomfort fades over days to a few weeks. Certain signs, however, should prompt a same-day call to your dental team or, out of hours, to a doctor or urgent care service, whatever tool was used.
- Pain that is severe, worsening rather than easing, or that wakes you at night, particularly a throbbing ache that lingers after hot or cold has been removed.
- Swelling of the gum, face or jaw, or a tender lump on the gum near the treated tooth, which can signal infection or an abscess.
- Fever, a general feeling of being unwell, or difficulty swallowing or opening your mouth; the Mayo Clinic lists these among the reasons to seek prompt care with a dental abscess.
- Any swelling that affects breathing, or that spreads rapidly toward the eye or down the neck; this needs emergency care without delay.
- Bleeding from a gum procedure that does not stop with gentle pressure, or that restarts after several days.
- A filling that falls out, cracks, or leaves a sharp edge that cuts your tongue or cheek.
- Numbness or tingling in the lip, tongue or chin that persists well beyond the time the team said the anesthetic would wear off.
- A gum area that turns dark, smells foul or shows spreading redness rather than the expected pale healing surface.
You do not need to be certain that something is wrong before calling. Dental teams expect these calls and would rather check a filling that turns out to be fine than miss an infection. Describe what you feel, when it started and what makes it better or worse, and let the clinician decide the next step.
Frequently asked questions
Is laser dentistry better than a drill?
Neither tool is better across the board. Lasers excel at soft-tissue work and may make small cavity removal more comfortable, while drills remain necessary for crowns, old metal fillings and larger or hard-to-reach cavities. A Cochrane review found lasers and drills removed decay equally well, with low-certainty evidence that lasers caused less pain. Your dentist picks the tool that suits the specific tooth and task.
Does laser dentistry hurt?
It can be more comfortable than drilling for small cavities, and some people need no numbing injection, but it is not painless in every case. Deep decay near the nerve is often still numbed. Lasers remove vibration and pressure, which many people find are the worst parts of drilling, yet the popping sound and longer treatment time bother some people. Tell your dentist which sensations trouble you most.
Can a laser remove a cavity completely?
Yes, for suitable cavities. The Cochrane review comparing laser cavity removal with drilling found no difference in how thoroughly decay was removed. Lasers are less practical for very large cavities, decay between teeth or lesions under existing fillings, and finishing and polishing the filling still usually involves rotary instruments. Whether a laser fits your cavity depends on its size, depth and location.
Do fillings last longer after laser treatment?
There is no good evidence that they do. The Cochrane review found insufficient data to say whether fillings placed after laser preparation last longer, seal better or protect the pulp differently compared with drilled fillings. A filling’s lifespan depends mainly on its size, the material used, your bite and daily care. Laser precision at the moment of cutting has not been shown to translate into longevity.
Can a laser remove an old silver filling?
No. Amalgam, the silver-colored metal alloy used in older fillings, reflects and absorbs laser energy unpredictably and can overheat, so it is always removed with a drill. If your main need is replacing an old metal filling, expect conventional instruments regardless of whether the practice owns a laser. The new filling placed afterward can be any suitable material your dentist recommends.
Is laser dentistry safe for kids?
It is an accepted option when used by a trained dentist with appropriate settings. Trials in children’s primary teeth found decay removal equal to drilling and some signal of less pain. Children wear protective eyewear and are told to expect a popping sound and water spray. Keeping still for a longer procedure is the main challenge. Any comfort measures, including numbing or sedation, are decided by the treating dentist.
Can lasers treat gum disease instead of deep cleaning?
Not as a replacement. Scaling and root planing, the mechanical removal of hardened deposits from tooth roots, remains the foundation of treating periodontitis. Lasers are sometimes added to disinfect the pocket and remove inflamed tissue, but studies have not consistently shown the addition improves long-term results. If a laser is proposed for gum disease, ask what it adds to the standard cleaning plan.
What are the main laser dentistry pros and cons?
Pros include less vibration and pressure, reduced need for anesthetic with small cavities, and clean, low-bleeding soft-tissue procedures often without stitches. Cons include longer treatment time for cavities, inability to remove metal fillings or shape crowns, limited access to decay between teeth, and a lack of long-term data on filling durability. Both tools are usually used together over a course of care.
How long does sensitivity last after a laser filling?
About the same as after a drilled filling. Sensitivity to cold, sweets or pressure is common with any new filling and, according to the Cleveland Clinic, usually fades within a few weeks as the tooth settles. Persistent or worsening pain, a filling that feels high when you bite, or swelling are reasons to contact your dental team rather than wait it out.
Will I still hear the drill if my dentist uses a laser?
Very possibly, yes. Even when a laser removes the decay, the filling is usually shaped and polished with fine rotary burs, and any crown work or old filling removal needs a drill. Soft-tissue procedures such as gum reshaping may be entirely laser-based. Ask beforehand which steps will involve each instrument so the sound does not catch you off guard.
References
- Cleveland Clinic: Dental fillings
- NHS: Tooth decay
- NIH National Institute of Dental and Craniofacial Research: Tooth decay
- MedlinePlus: Dental cavities
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Caring for Dental Crystals: Brushing Around the Gem and Foods to Avoid on Day One
Tooth gem care comes down to protecting the resin bond and the enamel underneath it. On day one, skip hard, sticky, very hot and…

Why Do Gums Bleed When You Brush? The Message in the Sink
Gums that bleed during brushing are usually inflamed by plaque, the bacterial film that builds along the gumline: an early, reversible stage of gum…

Metal Braces for Adults: Old Fillings, Gum Health and What Changes After Teenage Years
Metal braces work for adults because teeth can move at any age as long as the surrounding bone and gums are healthy. Adults differ…
Dental Hygiene Myths: Does Scaling Damage Enamel or Loosen Teeth?
Professional scaling does not damage healthy enamel or loosen teeth when performed correctly. Enamel is the hardest tissue in the body, far harder than…

Eating After Orthognathic Surgery: From Liquids to Soft Foods and Back to a Normal Diet
Eating after jaw surgery usually moves through three stages: liquids in the first days, blended or pureed meals once swelling eases, then soft foods…
What a Panoramic X-Ray or 3D Scan Shows About an Impacted Tooth: Roots, Nerves and Angle
A panoramic X-ray of an impacted tooth shows, in one flat image, how many roots the tooth has and how they curve, how deeply…