

Liquid Rhinoplasty After a Previous Nose Job: Why Injectors Are Cautious About Scarred Noses

Key Takeaways
- Rhinoplasty lifts the skin off the nasal framework, and the scar that forms underneath makes filler spread unevenly and leaves fewer arteries feeding the skin.
- The nose is one of the two highest-risk facial sites for filler blocking a blood vessel, and a previously operated nose has less vascular backup if that happens.
- Mayo Clinic notes rhinoplasty swelling can continue to change the shape for up to a year, which is why most clinicians wait until then before treating irregularities.
- Filler can only add volume, so it disguises dips and steps but cannot make a nose smaller, narrower, or easier to breathe through.
- The NHS gives hyaluronic acid filler a typical duration of roughly six to eighteen months, and it advises against permanent fillers because they cannot be dissolved.
- Skin turning white, gray, or mottled, worsening pain, or any change in vision after nose filler is an emergency that needs same-day care.
Nose filler after rhinoplasty is possible for some people, but injectors treat a previously operated nose with extra caution. Surgery leaves scar tissue and rewires the small blood vessels that keep the skin alive, which raises the risk that filler blocks a vessel. Most clinicians wait until swelling has fully settled, use small volumes of dissolvable hyaluronic acid, and reserve filler for minor contour irregularities rather than structural problems.
She had waited a year for the swelling to go down, exactly as she was told. The bump was gone. The profile she had wanted since her twenties was finally there in photographs. And yet, in a certain light, a small dip sat just above the tip, a shadow that had not been in any of the surgeon’s sketches.
The idea of another operation felt enormous. A friend suggested a quick fix instead: a few minutes in a chair, a syringe, no anesthesia, back to work by lunch. So she booked a consultation for nose filler after rhinoplasty and was surprised when the injector, rather than reaching for a syringe, spent twenty minutes asking about the surgery, pressing gently on the skin, and explaining why an operated nose is a different proposition from one that has never been touched.
That caution is not fussiness. It reflects what surgery does to the tissue under the skin, and what can go wrong when filler meets a nose whose plumbing has already been rearranged.
Can I have nose filler after rhinoplasty?
The honest answer is: sometimes, for the right problem, in the right nose, after enough time has passed. Nose filler after rhinoplasty is not forbidden, and many experienced injectors will treat a previously operated nose. But almost all of them approach it differently from a first-time nose, and a meaningful number will decline if the anatomy or the history gives them pause.
Liquid rhinoplasty is the everyday name for injecting a soft gel, usually hyaluronic acid, into the nose to change its shape without surgery. Hyaluronic acid is a sugar molecule the body already makes; in filler form it is cross-linked into a gel that holds its shape for months and can be dissolved with an enzyme if needed. On a nose that has never been operated on, the tissue layers are predictable and the blood vessels run where the textbooks say they run. After surgery, neither of those things is guaranteed.
Three things change the calculation. First, scar tissue replaces some of the soft, gliding tissue between skin and cartilage, so filler spreads less evenly and the skin is less forgiving. Second, the arteries that feed the nasal tip and dorsum may have been cut, moved, or thinned, so the skin depends on fewer vessels and an accidental blockage has less backup. Third, the reason a person wants filler after surgery is often a real structural irregularity, and filler can only camouflage, never rebuild.
None of this means the door is closed. It means the consultation matters more than the procedure. A careful injector will want to know what was done, how long ago, whether grafts were placed, and whether the skin has thinned. The rest of this article explains why each of those questions matters, what the procedure actually involves, who tends to be a good candidate, and where the genuine risks sit.
What a scarred nose really means once the surgeon has closed
People hear the word scar and picture a line on the skin. In a nose, the scar that matters is the one you cannot see. Rhinoplasty, whether done through incisions inside the nostrils or with a small external cut across the columella (the strip of skin between the nostrils), involves lifting the skin off the underlying bone and cartilage, reshaping that framework, and laying the skin back down. Everything between skin and framework heals as scar.

Healthy nasal skin sits on a thin cushion of loose tissue that lets it slide and lets injected gel spread smoothly. Scar tissue is denser, less elastic, and unpredictable. It can form in bands, so a small volume of filler that would sit as a gentle dome on an untouched nose may instead pool in one pocket and leave the neighboring area unchanged. It can also tether the skin to the cartilage below, so lifting the skin to place filler underneath becomes harder and less precise.
The Mayo Clinic notes that swelling after rhinoplasty can take up to a year to fully settle, and that the final shape continues to refine during that time as tissue softens and contracts. Scar does not finish maturing the day the splint comes off. Filler placed while that process is still under way is being placed into a moving target.
Skin thickness changes too. Some people develop thicker, more fibrous skin over the tip; others, especially after multiple procedures or aggressive thinning, end up with skin so fine that the edges of grafts show through. Thin skin over scar shows every lump and every shadow, and it tolerates the stretch of added volume poorly.
An injector pressing on your nose during consultation is reading all of this: how the skin moves, where it is stuck, where it feels firm and where it feels hollow. That map decides whether filler is sensible at all.
How liquid rhinoplasty works, and what actually happens in the chair
The mechanics are simple to describe. A gel is placed in tiny amounts beneath the skin, along the midline of the nose, to fill a dip, smooth a step, or lift a drooping tip by adding support at its base. The gel does not remove anything. A bump is disguised by filling the hollow above and below it so the profile reads as one straight line, which means the nose gets very slightly larger to look smaller.
A typical appointment, described in neutral terms, runs like this. The skin is cleaned and photographed. A numbing cream may be applied, though many hyaluronic acid fillers already contain a local anesthetic. The injector then works either with a fine needle or a cannula, a blunt-tipped flexible tube introduced through a single entry point and glided under the skin. On an operated nose, many injectors prefer the cannula because a blunt tip is less likely to pierce a vessel, although it is not a guarantee, and scar can make a cannula harder to advance.
The gel goes in slowly, in small increments, with the injector pausing to watch the skin color after each pass. Blanching, a sudden whitening of the skin, is the signal that a vessel may be compressed or blocked, and it is the reason a careful injector never hurries the nose. The whole thing usually takes well under an hour, and the change is visible immediately.
Hyaluronic acid is the standard choice because it can be reversed. Hyaluronidase is an enzyme that breaks down hyaluronic acid within hours; it is kept on hand precisely so that a lump or, more urgently, a blocked vessel can be treated. Permanent fillers exist, and the NHS advises against them in general because they cannot be dissolved and complications are far harder to manage. On a previously operated nose, where the odds of needing to undo something are higher, that reversibility is not a nicety. It is the safety net that makes the procedure defensible.
Why blood supply is the whole story: vascular occlusion explained
If one concept explains the caution around nose filler after rhinoplasty, it is this. The nose is fed by a network of small arteries that arrive from the sides and meet at the tip and along the midline. Those same arteries connect, through branches around the eye, to the vessels that supply the retina. Filler injected into an artery, or pressed against one hard enough to squeeze it shut, can cut off blood to a patch of skin. Filler that travels backward along the wrong branch can, rarely, reach the eye.
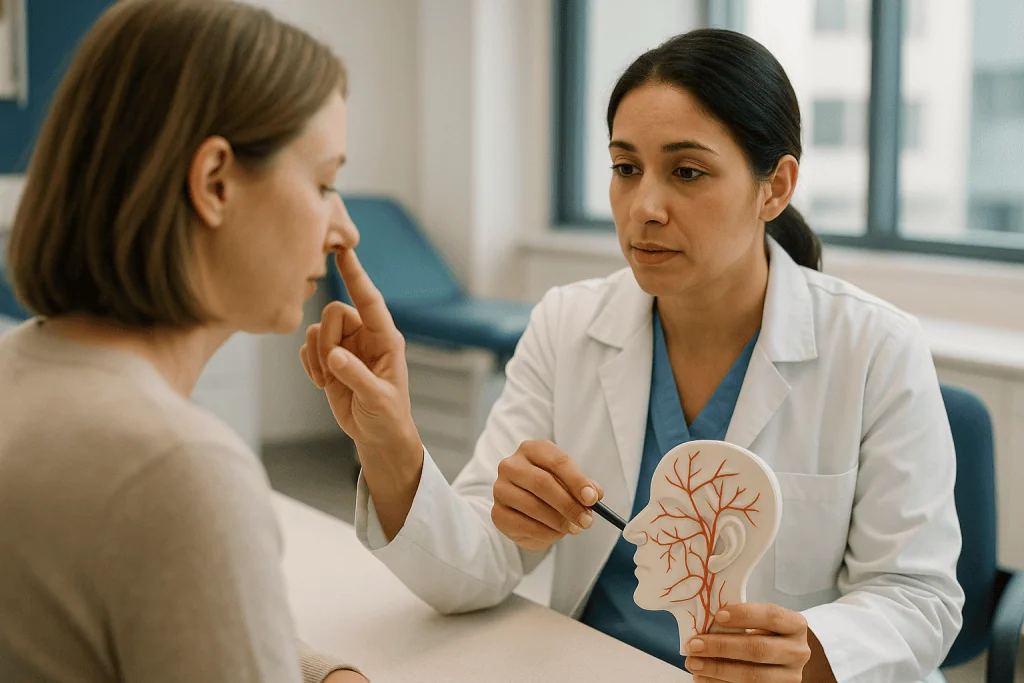
This event is called vascular occlusion: a blockage of a blood vessel by filler, either from the inside or from pressure outside. Harvard Health lists tissue death and vision loss among the serious, though uncommon, complications of dermal fillers, and the nose and the area between the brows are widely recognized as the highest-risk zones for exactly this reason.
Now consider what surgery does to that network. Reshaping the dorsum and tip means lifting skin off the framework, and the arteries that ran in that layer are inevitably disturbed. Some are divided. Others are stretched, thinned, or pushed into unfamiliar positions by grafts and sutures. The skin recovers because remaining vessels expand and new ones grow in, but the safety margin shrinks. A nose with two good arteries feeding the tip can lose one and survive. A nose that has already lost one cannot afford to lose the other.
Scar makes the geometry worse. Vessels that once floated in soft tissue may now be pinned in place by fibrous bands, right where an injector would expect open space. Landmarks that normally guide a safe injection plane may have moved.
None of this means occlusion is likely. It remains an uncommon complication. But the consequences are severe, the anatomy after surgery is less predictable, and the injector has fewer margins to work with. That combination is why experienced clinicians slow down, use blunt cannulas, inject tiny volumes, and sometimes simply say no.
Who nose filler after rhinoplasty is usually for, and who is asked to wait
The people who tend to do well share a pattern. They had a single, uncomplicated rhinoplasty. Enough time has passed for swelling to resolve and scar to soften. Their concern is small and specific: a shallow dip on the bridge, a slight step where bone meets cartilage, a mild asymmetry that catches the light. Their skin is reasonably thick and moves freely over the framework. And their expectation is camouflage, not correction.
The people who are usually asked to wait, or to consider a different route, fall into several groups.
- Anyone still within the first months of healing, when swelling can mask the true result. Mayo Clinic describes changes continuing for up to a year, and an irregularity that seems permanent at six months sometimes settles on its own.
- Anyone with very thin, shiny, or tethered skin over the tip or bridge, where filler is likely to show as lumps and where the skin has the least reserve if blood flow is compromised.
- Anyone who has had two or more operations. Each procedure adds scar and removes vascular margin.
- Anyone whose problem is structural: a collapsed bridge (saddle nose), a tip that has lost support, a nostril that has retracted, or a breathing problem. Filler cannot restore support or open an airway.
- Anyone with an active skin infection, a history of serious filler complications, or a condition that impairs healing or clotting.
- Anyone with permanent filler already in the nose, because layering products of unknown behavior invites reaction and makes any future problem harder to unpick.
There is also a softer category: people whose real wish is the result they hoped for from surgery. Filler can shave the edge off a disappointment, but it cannot deliver a second rhinoplasty in a syringe. A good injector will name that gently, because the wrong expectation causes more unhappiness than any lump.
The final call belongs to the clinician who examines you, and ideally to a conversation that includes the surgeon who did the original operation, since they know exactly what lies under the skin.
How long should you wait after rhinoplasty before considering filler?
There is no single number that every guideline endorses, so it is worth saying what the evidence supports and where clinical habit fills the gap.
The best-anchored fact is the healing timeline. Mayo Clinic states that while most swelling settles within weeks, subtle changes can continue for up to a year, and the NHS gives a similar picture, noting that it can take months for the final shape to become clear and that swelling of the tip is often the last to go. The skin over the tip is thick and holds fluid stubbornly; a fullness there at four months is very often swelling, not scar or excess cartilage.
Because of this, most surgeons would not consider revision surgery before roughly a year, and many injectors apply the same logic to filler. Treating a dip that is really a temporary hollow beside a swollen area means chasing a moving shape, and the filler may look wrong once the swelling resolves. Waiting also allows scar to mature from firm and reactive to softer and more stable, which improves how the gel spreads.
Some clinicians do inject earlier for very small irregularities once the splint is off and bruising has resolved, particularly if the surgeon requests it. That is a decision for the operating team, who understand the exact state of the tissue, not a general recommendation.
Waiting has a psychological side too. The months after rhinoplasty are famously hard on self-image; the nose looks different every week, and the eye fixates on flaws that others do not see. Many people who were certain at four months that something needed fixing feel differently at twelve. Time is the one intervention with no complication rate.
Ask your surgeon when they consider the result final, and use that as your earliest starting point for a filler conversation rather than the date of the operation.
Non surgical nose job after rhinoplasty vs revision surgery: how they compare
The choice is rarely filler or nothing. It is filler, revision surgery, or leaving things as they are. Each carries a different profile, and the table below sets them side by side in neutral terms. Revision rhinoplasty means a second operation to correct or refine the result of the first.
| Factor | Filler (liquid rhinoplasty) | Revision rhinoplasty | No further treatment |
|---|---|---|---|
| What it can address | Small dips, steps, mild asymmetry; camouflage only | Structural problems, support, airway, size reduction | Nothing changes; some irregularities soften with time |
| Anesthesia | Topical or none | Usually general | None |
| Duration of effect | Temporary; NHS cites roughly 6 to 18 months for hyaluronic acid | Intended to be long-lasting | Not applicable |
| Reversibility | Hyaluronic acid can be dissolved | Not reversible | Not applicable |
| Downtime | Hours to days of swelling or bruising | Weeks, with a year for full settling | None |
| Key risks | Vascular occlusion, lumps, infection, added volume | Surgical and anesthetic risk, further scarring, further vascular compromise | Ongoing dissatisfaction if the concern is real |
| Effect on future surgery | Usually needs dissolving first; can complicate planning | Each operation makes the next harder | Preserves options |
The table shows the trade-off honestly. Filler is fast, adjustable, and reversible, but it is temporary and can only add. Revision surgery can genuinely rebuild, but it reopens a nose that has already been operated on, with all the scarring and vascular cost that implies, and surgeons often describe it as more demanding than a first operation.
What the table cannot show is which is right for you. That depends on what the irregularity actually is under the skin, something only an examination, and sometimes the original operative notes, can reveal.
What filler can fix after surgery, and what it simply cannot
The clearest way to think about filler is as a tool for filling shadows. Anything that reads as a hollow, a dip, or a missing sliver of contour is fair game. Anything that reads as excess, collapse, or a breathing problem is not.
Filler tends to work reasonably well for a shallow dip along the bridge left where bone and cartilage meet, a slight step at the edge of a graft, or a subtle unevenness where one side of the bridge sits marginally lower than the other. It can also soften a pollybeak, a fullness just above the tip that makes the profile look like a parrot’s beak, but only by filling the bridge above it so the whole line reads straight, which adds volume to the nose overall.
Filler cannot remove a residual bump; it can only build around it. It cannot shrink a tip, narrow a bridge, or reduce a nose that came out larger than hoped. It cannot lift nostrils that have retracted, straighten a septum, or open a collapsed valve inside the nose. Cleveland Clinic describes fillers as adding volume and smoothing contours; none of that translates into removing tissue or restoring structural support.
The saddle nose deserves its own line. This is a bridge that has sunk because the supporting cartilage or bone was over-resected or has weakened, leaving a scooped profile. Filler can disguise a very mild version, but the skin over a saddle is often thin and the blood supply already strained, and the tissue underneath offers little to hold the gel. Most clinicians consider a true saddle a surgical problem.
The honest test is to ask: would I be happy if this shadow were filled in and nothing else changed? If yes, filler is worth discussing. If the answer involves the words smaller, narrower, or breathe, the conversation belongs with a surgeon.
How long does nose filler last, and can it really last 4 years?
The NHS puts the duration of hyaluronic acid fillers at roughly six to eighteen months, depending on the product and the area treated. The nose sits toward the longer end of that range in many people’s experience, because it moves less than the lips or cheeks and the gel is not constantly worked by muscle. But that is a typical range, not a promise.
The question of four years comes up constantly online, and it deserves a careful answer. There is evidence that hyaluronic acid filler does not always vanish on the schedule the packaging implies. Imaging studies and clinical reports describe gel persisting well beyond the expected window, sometimes for years, particularly in low-movement areas. So it is not impossible for a nose to still show some effect after a long time.
Two caveats matter. First, persistence is not the same as a maintained result. Gel that lingers may have shifted, softened, or attracted fluid, so what remains at three years may not look like what was placed at three weeks. Second, a nose that still looks good years later has usually been topped up, and the person may not be counting those visits. A single session lasting four years unchanged would be unusual.
Permanent fillers are sometimes marketed as the answer to this. The NHS advises against them, and the reasoning is stronger on an operated nose than anywhere else. A material that cannot be dissolved leaves no way to treat a lump, a shift, or a late inflammatory nodule except by cutting it out, and cutting into an already-scarred nose to remove a foreign material is exactly the operation nobody wants. Any filler described as permanent should be treated as a reason to ask more questions, not fewer.
For most people the practical answer is: expect a temporary result, plan on maintenance if you want it kept, and treat longevity as a variable, not a guarantee.
Filler after rhinoplasty risks: the downsides people underestimate
Vascular occlusion is the risk that keeps injectors awake, but it is not the only one, and the everyday complications are the ones most people actually encounter.
Bruising and swelling are common and generally short-lived; the NHS lists them as the expected side effects of any dermal filler. On a nose with scar tissue, swelling can be more pronounced and last longer, because the tissue drains less efficiently.
Lumps and irregularities are more likely in scarred skin. Gel that would spread smoothly in soft tissue can catch in fibrous bands and sit as a visible bead, especially over the tip. Thin skin shows this mercilessly. Most lumps can be massaged or dissolved, but the dissolving enzyme does not discriminate between the lump and the filler you wanted to keep.
Infection is uncommon but real, and any foreign material carries a small risk of biofilm, a stubborn low-grade infection that can flare weeks or months later. Delayed nodules, firm swellings that appear long after treatment, sometimes triggered by an unrelated illness or vaccine, are described in the filler literature and can be harder to sort out when scar is also present.
Skin changes deserve mention. Repeated stretching of thin, scarred skin can leave it thinner still, and some people notice a slight shine or visible vessels over treated areas. Filler can also migrate, drifting from the bridge toward the sides or upward toward the brow.
There is a longer-term cost too. Filler in the nose complicates any future revision surgery. Surgeons generally want it dissolved beforehand, and residual gel or the inflammation it leaves can make dissection harder and the result less predictable. Choosing filler now is not neutral for the surgery you might want later.
And finally, the aesthetic downside: filler adds. Several rounds over several years can leave a nose that is smoother but larger than the one that left the operating room. That creep is gradual, and mirrors are poor at spotting it.
What the following days and weeks usually look like
Most people walk out with the shape visible straight away, some redness at the entry points, and perhaps a faint tightness along the bridge. What follows is generally undramatic, but knowing the normal course makes the abnormal easier to spot.
In the first hours, mild swelling is usual, and the nose may look slightly fuller than intended. Injectors typically ask you to avoid pressing on it, sleeping face-down, wearing glasses that rest on the treated area, heavy exercise, alcohol, and heat such as saunas for a short period, because all of these can worsen swelling or shift gel before it has settled. Skin color is worth watching in a good light during this window; the skin should look pink and even, not white, dusky, or mottled.
Over the next few days, bruising, if it appears, follows its ordinary arc from purple to yellow. Tenderness eases. Any small bumps at needle points usually soften. Cleveland Clinic describes filler swelling as generally settling within days, and this matches most people’s experience in the nose, though scarred tissue can hold fluid a little longer.
Around the two-week mark, the gel has integrated with the tissue and the result you see is close to the result you will keep. Many injectors book a review at this point, and it is the right moment to discuss a small adjustment, or to dissolve a spot that has not settled, rather than doing so in the first few days when swelling still distorts the picture.
From there, months pass quietly. The effect softens gradually rather than switching off, and most people notice the return of the original shadow before anyone else does. When and whether to repeat is a conversation to have with your injector, ideally with photographs from before and after the first session so that added volume is tracked rather than guessed.
What happens 10 years after rhinoplasty, and why it matters for filler
Rhinoplasty is often described as a permanent result, and the framework is indeed permanent. But the nose is living tissue that keeps changing, and the person searching for what happens a decade on has usually noticed something.
Cartilage remembers. Grafts and reshaped cartilage can warp slowly over years, so a bridge that was ruler-straight at one year develops a gentle curve, or a tip that was symmetrical drifts a few millimeters. Skin thins with age, and thinning skin reveals edges and contours that were invisible when it was thicker: the outline of a graft, a slight irregularity in the bone, the join between different segments. Scar tissue also contracts over time, which can pull the tip downward or pinch the nostrils inward.
Ordinary aging adds its own layer. The nasal tip tends to droop as supporting ligaments loosen, the bridge can appear more prominent as the cheeks lose volume around it, and the skin becomes less elastic. Some of what people notice at ten years is not the surgery changing but the face around it changing.
All of this bears directly on filler. A nose ten years out from surgery has fully mature scar, which is good, but it may also have thinner skin, visible graft edges, and a tip with less structural support, none of which filler handles well. Filler placed over a warped graft may highlight the warp rather than hide it. Filler used to lift a tip that has lost support will be pressing on tissue with nothing beneath it to hold the gel in place.
The useful takeaway is that late changes are common, are often subtle, and are not a sign that the operation failed. Whether they warrant treatment at all, and whether filler or revision is the right tool, is a question for a surgeon who can examine what has actually shifted and why.
What people often get wrong about nose filler after surgery
The first misconception is that filler is the low-risk option. Compared with surgery, it is less invasive. But the nose is one of the two highest-risk sites for filler anywhere on the face, and a previously operated nose sits at the riskier end of that. Low downtime is not the same as low stakes.
The second is that filler can make a nose smaller. It cannot. Every liquid rhinoplasty adds volume; the illusion of a smaller or straighter nose comes from filling hollows so the eye reads a cleaner line. On a nose that came out of surgery slightly larger than hoped, filler moves in the wrong direction.
Third, people assume the result will be permanent, or nearly so. The NHS range of roughly six to eighteen months for hyaluronic acid is the realistic planning horizon. Longer persistence happens, but it is not something to count on, and it is not always flattering when it does.
Fourth, there is a belief that a dissolvable filler is fully reversible in every sense. The gel can be broken down, yes. But an injection that caused a vascular problem is not undone by dissolving the gel afterward; tissue damage can already have occurred. Reversibility is a safety feature for lumps and unwanted shape, and an emergency tool for occlusion, not a guarantee that nothing can go wrong.
Fifth, many people think the surgeon and the injector are interchangeable, or that the surgeon’s opinion is not needed. In fact, the operating surgeon holds information no one else has: what was removed, what was grafted, how thin the skin was made. A ten-minute call or a copy of the operative notes can change an injector’s plan entirely.
And last, the idea that a good injector will always find a way. The most experienced injectors decline more often than the least experienced, precisely because they have seen what a scarred nose can do.
Questions to ask your care team before nose filler after rhinoplasty
A consultation is an interview in both directions. These questions tend to surface the information that matters most, and the quality of the answers is itself a useful signal.
- Have you reviewed my operative notes, or spoken with my surgeon, about what was done and where grafts were placed?
- In your assessment, is the irregularity I am concerned about a hollow that filler can fill, or a structural problem that filler will only disguise, or make worse?
- How does the skin over my bridge and tip feel to you: thick enough to hide filler, or thin and tethered?
- Which product do you plan to use, is it hyaluronic acid, and can it be dissolved?
- Do you use a needle or a cannula in the nose, and why?
- Do you keep hyaluronidase available during the appointment, and have you managed a vascular occlusion before?
- What signs should I watch for in the first hours and days, and how do I reach you if something looks wrong outside working hours?
- How much filler are you planning, and how will we track total volume over repeat sessions?
- If I later want revision surgery, how would the filler affect that, and would it need dissolving first?
- Would you recommend waiting longer, or not doing this at all, and if so, why?
Write down what you hear, or ask if you can. It is common to leave a consultation with a clear feeling but a hazy memory of the reasoning. A clinician who welcomes the last question in that list, the one that invites them to say no, is usually the one worth trusting with a yes.
Consider also asking your original surgeon the same set of questions independently. When two clinicians who have not spoken to each other reach the same conclusion about your nose, that agreement is worth more than any single opinion.
When to call your doctor
Most problems after nose filler are minor and settle on their own. A small number are emergencies, and with vascular occlusion the difference between a good outcome and a bad one is measured in hours. Every reputable injector will tell you how to reach them urgently; make sure you have that number before you leave.
Seek urgent care, contacting your injector immediately and going to an emergency department if you cannot reach them, for any of the following:
- Skin on or around the nose turning white, gray, dusky purple, or developing a lace-like or mottled pattern, especially if it spreads.
- Pain that is severe, out of proportion to the procedure, or worsening rather than easing, particularly if the skin looks abnormal.
- Any change in vision, including blurring, a shadow, loss of part of the visual field, double vision, or pain in or behind the eye.
- A drooping eyelid, weakness on one side of the face, sudden severe headache, confusion, or difficulty speaking.
- Skin that blisters, breaks down, or develops a dark crust in the days after treatment.
Contact your injector or doctor promptly, though less urgently, for spreading redness, increasing warmth, or pus at an injection point; a fever; a firm lump that appears weeks or months later; swelling that keeps worsening after the first few days rather than improving; or numbness that persists.
The everyday course, described in the earlier section, is mild swelling, possible bruising, and a little tenderness that fades over days. Anything that departs from that pattern deserves a phone call. Clinicians would far rather hear about a false alarm than miss a real one, and no one who has treated a scarred nose will consider the question a nuisance.
Decisions about dissolving filler, further treatment, or referral to a surgeon rest with the clinician who sees you. Your job is only to notice, and to call.
Frequently asked questions
Can I have nose fillers after rhinoplasty?
Often yes, but with more caution than a first-time nose. Surgery leaves scar tissue and disturbs the arteries that supply the skin, so injectors tend to wait until the result is fully settled, use small volumes of dissolvable hyaluronic acid, and reserve filler for shallow dips or mild asymmetry. Thin skin, multiple previous operations, or a structural problem often lead a clinician to advise against it. The final decision rests with the clinician who examines you.
Is a non surgical nose job after rhinoplasty safer than revision surgery?
It is less invasive, not automatically safer. Filler avoids anesthesia and long recovery, and hyaluronic acid can be dissolved. But the nose is a high-risk site for filler blocking a blood vessel, and scarring from surgery increases that concern. Revision surgery carries its own risks, including further scarring. Which is appropriate depends on what is actually wrong under the skin, which only an examination can determine.
What happens 10 years after rhinoplasty?
The bone and cartilage framework stays, but the nose continues to change. Cartilage and grafts can warp slowly, skin thins with age and may reveal edges that were once hidden, scar tissue contracts, and the tip tends to droop as the face ages. These late changes are common and are not a sign the surgery failed. Whether they need treatment, and whether filler or revision is suitable, is a question for a surgeon.
How long does nose filler last after a previous nose job?
The NHS gives hyaluronic acid filler a typical range of about six to eighteen months, and the nose often sits toward the longer end because it moves little. Scar tissue does not reliably shorten or lengthen that. The effect fades gradually rather than disappearing, and most people notice the original shadow returning before anyone else does. Repeat treatment is a decision for you and your injector.
Can nose fillers last 4 years?
Occasionally some filler persists for years, and imaging studies have found hyaluronic acid lingering well beyond its expected window. But persistence is not the same as a maintained result; lingering gel may have shifted or softened. A single session that looks unchanged after four years would be unusual, and most long-lasting results have been quietly topped up. Plan on a temporary effect rather than counting on longevity.
What are the downsides of getting nose filler?
The most serious is vascular occlusion, where filler blocks a blood vessel and can cause skin damage or, rarely, vision loss. More common downsides include bruising, swelling, lumps that show through thin or scarred skin, infection, delayed nodules, migration, and gradual enlargement of the nose over repeated sessions. Filler in the nose can also complicate any future revision surgery, which usually requires it to be dissolved first.
What are the filler after rhinoplasty risks that are specific to an operated nose?
Scar tissue makes filler spread unpredictably and increases the chance of visible lumps, especially over the tip. Surgery also divides or repositions arteries, so the skin depends on fewer vessels and has less reserve if one is blocked. Thin skin after aggressive reshaping shows every irregularity. And filler placed over a warped graft or unsupported tip may highlight the problem rather than hide it.
Should I ask my original surgeon before getting filler?
Yes, wherever possible. The operating surgeon knows what was removed, what was grafted, how thin the skin was made, and where the blood supply was disturbed. That information can change an injector’s plan or lead them to advise waiting. Many surgeons are also willing to say whether an irregularity is likely to settle on its own or whether it is genuinely permanent.
Revision rhinoplasty vs filler: how do I know which I need?
Ask what the irregularity actually is. If it is a shallow hollow, dip, or step, filler can often disguise it. If it involves a residual bump, a nose that is too large, a collapsed bridge, retracted nostrils, or breathing problems, filler cannot help and revision surgery is the relevant conversation. A surgeon examining the nose, sometimes with the original operative notes, is the only reliable way to tell.
Are permanent fillers a good idea after rhinoplasty?
Mainstream guidance advises against them. The NHS notes that permanent fillers cannot be dissolved, so lumps, migration, or late inflammatory reactions can only be treated by surgical removal. On a previously operated nose, cutting into scarred tissue to remove a foreign material is a difficult operation with its own risks. Reversible hyaluronic acid is the standard choice precisely because problems can be undone.
References
- NHS: Dermal fillers
- NHS: Nose reshaping (rhinoplasty)
- Cleveland Clinic: Dermal Fillers
- MedlinePlus: Rhinoplasty
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is Genioplasty Painful? General Anesthesia, Chin Tightness and What Helps in the First Days
Genioplasty is usually described as uncomfortable rather than severely painful. Because it is performed under general anesthesia, nothing is felt during the operation itself.…

Forehead Lift for Men: Hairline, Brow Shape and Why the Plan Differs for Male Faces
A forehead lift for men lifts sagging brows and softens deep forehead lines by repositioning the tissue beneath the skin, but the plan usually…

Lip Lift vs Corner Lip Lift vs Italian Lip Lift: How the Incision Patterns Differ
The main types of lip lift differ by where the surgeon places the cut. A standard subnasal lip lift removes a strip of skin…

How Sliding Genioplasty Is Performed: The Osteotomy, Repositioning and Plate Fixation
A sliding genioplasty procedure reshapes the chin by cutting the lower front part of the jawbone through an incision inside the mouth, sliding the…

When Can You Wear Contacts and Makeup After Blepharoplasty? Eye Care in the First Weeks
Most surgeons ask patients to keep makeup off the eyelids until incisions have sealed and any stitches are out, which Mayo Clinic places at…

What to Ask a Rhinoplasty Surgeon at Your First Consultation: Twelve Questions That Matter
The most useful questions to ask a rhinoplasty surgeon cover four areas: their training and how often they perform nose surgery, what change is…