

Local or General Anesthesia for Vitrectomy: What You Feel and How the Choice Is Made

Key Takeaways
- Most adult vitrectomies use a numbing block around the eye plus light intravenous sedation, not full general anesthesia.
- A working block stops the operating eye from seeing or moving, so people perceive light, color or darkness rather than watching the surgery.
- General anesthesia is reserved for children, long or complex repairs, and adults who cannot lie flat and still, because it adds airway and whole-body risks.
- The NHS estimates death linked to general anaesthesia at roughly one in every hundred thousand anaesthetics, concentrated in very unwell patients having major surgery.
- The 24-hour ban on driving after sedation or general anesthesia exists because judgment and reaction time stay impaired after you feel awake, and a fresh eye patch or gas bubble alters vision further.
- If a gas bubble is placed, flying, high altitude and nitrous oxide must be avoided until the surgeon confirms it has absorbed, which can take several weeks.
Most vitrectomies in adults are performed under local anesthesia: numbing injections around the eye, usually combined with light intravenous sedation, so you are relaxed, pain-free and unable to see or move the operating eye. General anesthesia, where you are fully asleep, is chosen for children, very long or complex operations, severe anxiety, or when lying still is difficult. The retinal surgeon and anesthesia team make the choice together with you.
The pre-op nurse has just asked whether you would prefer to be “awake or asleep,” and the question lands oddly. Awake for eye surgery? You picture yourself watching a needle come toward your own eye. In reality, that picture is wrong in almost every detail, which is part of why the conversation about vitrectomy anesthesia deserves more than a checkbox.
A vitrectomy is an operation that removes the vitreous, the clear gel filling the back of the eye, so a retinal surgeon can repair the retina or clear blood and scar tissue. It is delicate work done through openings smaller than a millimeter, and it can last anywhere from under an hour to several hours. How you are kept comfortable during that time is not an afterthought. It shapes what you remember, how quickly you go home, and which risks you carry.
This explainer walks through what each option actually feels like, how surgeons and anesthesia teams weigh the decision, and the questions that people quietly worry about but rarely ask out loud.
Do they put you to sleep for a vitrectomy?
Usually not fully. For most adults, a vitrectomy is done under local anesthesia with sedation, which means the eye and its surroundings are made numb and still while medicine given through a small intravenous line keeps you calm and drowsy. You are not “knocked out.” You can breathe on your own, respond if spoken to, and many people drift in and out of a light sleep without any memory of the middle of the operation.
General anesthesia, the kind where a machine and an anesthesia clinician take over your breathing and you are completely unconscious, is the alternative. It remains the standard for children, for people who cannot lie flat and still for the required time, and for certain long or unpredictable operations such as repairs after severe eye injury.
The shift toward local techniques happened for practical reasons. Modern vitrectomy uses very small instruments, so the operation is shorter and less traumatic to the eye than it was a generation ago. Local anesthesia avoids the airway management, the recovery-room time and the nausea that can follow a general. It also lets the surgeon check in with you if something changes.
What the evidence says: the NHS describes local anesthesia as the usual choice for many eye operations because it carries fewer whole-body effects and allows a faster return home, while general anesthesia is reserved for when it is clinically needed. Neither approach is “better” in a universal sense. The right one is the one that lets a particular surgeon complete a particular repair safely in a particular patient, and that judgment sits with your treating team.
What actually happens during vitrectomy anesthesia, step by step
The choreography is more predictable than people expect. A vitrectomy is done through the pars plana, a narrow band of the eye wall just behind the colored iris where instruments can enter without damaging the retina or lens. Three tiny ports are placed there: one to keep the eye inflated with fluid, one for a light, and one for the cutting instrument that removes the vitreous gel in small bites.
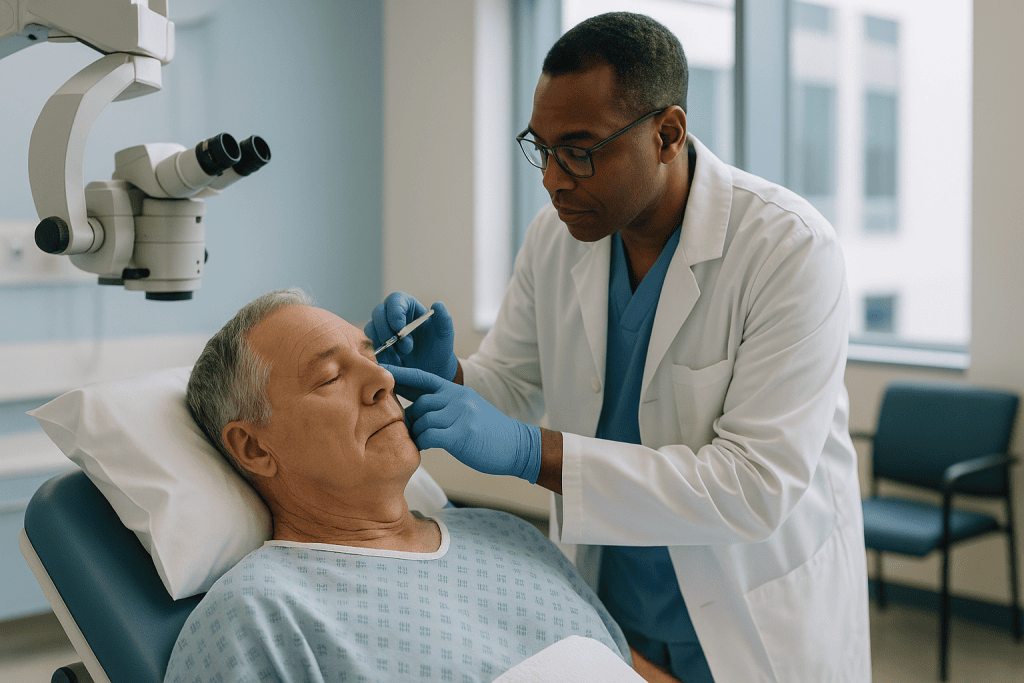
Before any of that, the anesthesia plan is carried out. With a local approach, drops first numb the surface. Then a numbing medicine is injected around, not into, the eyeball. The two common methods are a peribulbar block, placed in the soft tissue beside the eye, and a sub-Tenon’s block, delivered through a small opening in the thin membrane covering the white of the eye. Both aim for two things: no pain sensation and akinesia, which is the medical word for the eye being temporarily unable to move.
Once the block has set, the eye is cleaned, a sterile drape is placed over your face with an opening for the operating eye, and fresh air or oxygen flows under the drape. The surgeon works through an operating microscope suspended above you. Speaking is discouraged because the jaw moves the head, but you can squeeze a nurse’s hand to signal discomfort.
Under general anesthesia the sequence differs at the start: medicine through the intravenous line puts you to sleep within seconds, a breathing device is placed, and you wake in a recovery area after the eye has been patched. Many surgeons still add a local block at the end so that you wake with a comfortable eye rather than a sore one.
Vitrectomy under local anesthesia: what you actually feel while awake during eye surgery
The single most common misconception is that you will watch the operation. You will not. Once a block has taken effect, the optic nerve and the muscles are quiet, so vision in the operating eye drops to vague light and shadow or nothing at all. People often describe swirling colors, a sense of brightness from the microscope light, or simply darkness. Some report seeing nothing and hearing everything.
The injection itself is the moment most people brace for, and it is over quickly. There is a pressure sensation and a brief sting, similar in intensity to a dental injection, followed within minutes by a heavy, numb feeling around the eye. The eye may feel “full.” After that, sensations during surgery are mostly pressure and pulling rather than pain. If a sharp sensation does break through, tell the team; a top-up of local anesthetic is straightforward.
Sedation changes the texture of the experience. Given intravenously, it works within a minute or two and is adjusted continuously. The aim is a drowsy calm where time passes strangely. Many patients are surprised to be told the operation is finished when they believed only a few minutes had gone by.
Sounds are the other thing people remember: the soft rhythm of the vitrectomy cutter, the surgeon’s quiet instructions, the beep of the monitor tracking your heart rate. Knowing this in advance helps. None of it means anything is wrong.
The MedlinePlus vitrectomy entry notes that patients who receive local anesthesia with sedation are usually able to go home the same day, once the sedation has worn off enough for them to be safely accompanied.
What general anesthesia for vitrectomy feels like
General anesthesia is, from the inside, a gap. You are given medicine through an intravenous line, sometimes after breathing oxygen through a mask, and the next thing you experience is a recovery nurse saying your name. There is no dreaming that people reliably recall, no sense of duration, and no awareness of the surgery.

Behind the scenes, a good deal is happening. Once you are asleep, the anesthesia clinician places a breathing device, either a mask that sits above the voice box or a tube that passes through it, and a ventilator supports your breathing. Your blood pressure, oxygen level, heart rhythm and depth of anesthesia are monitored continuously. For eye surgery in particular, the team watches for the oculocardiac reflex, a slowing of the heart that can be triggered when eye muscles are pulled; it is well recognized and treatable in the moment.
Waking up is gradual rather than sudden. The first hour commonly brings grogginess, a dry or slightly sore throat from the breathing device, feeling cold, and sometimes nausea. Mayo Clinic lists these among the expected short-term effects of general anesthesia, and notes that confusion or memory gaps in the first hours are more common in older adults.
The eye itself may be surprisingly comfortable on waking if a local block was placed at the end of the operation, which is common practice. Later that day, as the block fades, a gritty, aching or scratchy feeling is usual. Your team will discuss ordinary pain relief; that is their decision to tailor, not something to arrange yourself.
Going home after a general typically takes longer than after local with sedation, because the recovery team needs to see you drinking, walking steadily and free of significant nausea first.
Who usually gets local, who gets general, and who is asked to wait
The anesthesia decision for vitrectomy weighs three things: the operation, the patient and the setting.
The operation comes first. A straightforward repair of a macular hole or the removal of a persistent vitreous hemorrhage may take under an hour and suits local anesthesia well. Repair of a complex retinal detachment with scar tissue, or surgery after a penetrating injury where the eye wall is open, is longer and less predictable, and many surgeons prefer a general so they can work without a clock.
The patient comes second. Children almost always need general anesthesia because staying motionless under a drape is not realistic. Adults with severe claustrophobia, uncontrolled tremor, dementia, a persistent cough, or an inability to lie flat because of heart or lung disease are also often steered toward general. Conversely, people with significant heart or lung problems in whom a general carries higher risk may do better with a well-managed local block, provided they can lie still.
Anticoagulant medicines are a specific consideration. Injections around the eye carry a small bleeding risk, so people taking blood thinners are assessed in advance; a sub-Tenon’s technique is often favored because it avoids a sharp needle deep behind the eye. Never adjust these medicines yourself; the surgical and prescribing teams coordinate this.
Who is asked to wait? Elective vitrectomy is commonly postponed for an active chest infection, uncontrolled blood pressure or blood sugar, a recent heart attack or stroke, or pregnancy in the first trimester, because anesthesia risk rises in those windows. The NHS notes that pre-assessment clinics exist precisely to identify these issues early. A retinal detachment threatening the center of vision is a different matter: urgency can override the usual waiting rules, and the team will explain that trade-off.
Retinal surgery anesthesia options compared: a side-by-side table
Seeing the choices next to each other makes the logic visible. The table describes typical patterns, not guarantees; your own experience depends on the operation and your health.
| Feature | Local block with sedation | General anesthesia |
|---|---|---|
| State during surgery | Drowsy, calm, may doze; eye numb and still | Fully unconscious, breathing supported |
| What you see | Light, shadow or nothing in operating eye | Nothing |
| What you hear | Voices, instruments, monitors | Nothing |
| Airway | Breathing on your own, oxygen under drape | Breathing device placed after you are asleep |
| Typical recovery-room stay | Shorter; home once sedation wears off | Longer; nausea and grogginess more common |
| Common side effects | Bruising around eye, temporary double vision, droopy lid for hours | Sore throat, nausea, shivering, temporary confusion |
| Usually preferred for | Adults, shorter or predictable operations | Children, long or complex repairs, inability to lie still |
| Can the surgeon communicate with you? | Yes, through hand signals | No |
Two clarifications matter. First, the sedation row does not mean you are guaranteed to be asleep; some people stay pleasantly aware throughout. Second, “longer recovery” for general anesthesia refers to the hours in the surgical unit, not to how the eye heals. The retina does not know which anesthesia was used, and visual recovery depends on the underlying disease and the repair, not the drug.
Where the evidence sits: the NHS and Mayo Clinic both describe local anesthesia as generally carrying fewer systemic risks than general, while acknowledging that some operations and some patients need a general for safety. That is the balance your team is striking.
Sedation: the middle ground most people have never heard explained
Between “awake” and “asleep” lies a wide territory, and it is where most adult vitrectomies live. Sedation means medicine given through a vein to reduce anxiety and awareness without switching off breathing or protective reflexes. Clinicians grade it from minimal, where you are relaxed but fully conversational, through moderate, where you respond to voice and touch but may not remember much, to deep, which begins to resemble general anesthesia and requires closer airway attention.
For eye surgery the target is usually minimal to moderate. There is a specific reason not to go deeper: a person who is very deeply sedated may snore, jerk, or wake suddenly and turn their head, all of which are hazardous when an instrument is inside the eye. A cooperative, lightly drowsy patient is safer than a heavily sedated one. This is why the anesthesia clinician sits at your side throughout, adjusting the infusion to keep you in that window.
The medicines used in this role are short-acting and are chosen for how quickly they wear off; some also blunt memory formation, which explains the common experience of “losing” an hour. The choice of agent and how it is adjusted is entirely the anesthesia team’s call, and it varies with your age, weight, other medicines and medical history.
Sedation is not the same as being pain-free. The block does the pain work; sedation manages the mind. If a block is incomplete, more sedation is not the answer, and a good team will top up the local instead.
Ask in advance how much you are likely to remember, and say plainly if you would rather remember less or more. Preferences differ, and clinicians can usually accommodate them within safe limits.
“I’m scared of not waking up from anesthesia.” What should I know?
This fear is common, rarely spoken aloud, and worth answering with numbers rather than reassurance. Serious harm from anesthesia in an otherwise reasonably healthy adult is genuinely rare. The NHS puts the risk of death linked to general anaesthesia at roughly one in every hundred thousand anaesthetics, and notes that most of those cases involve people who were already very unwell or undergoing major emergency surgery. Vitrectomy is not major body surgery: there is no large incision, little blood loss and no manipulation of the heart, lungs or gut.
Why, then, does the fear feel so large? Partly because unconsciousness is unfamiliar and total; partly because anesthesia is often blamed for outcomes that were really about the illness that required surgery. Understanding what actually protects you can shrink the fear to its true size.
The protection is continuous monitoring by a trained clinician whose only job is you. Oxygen levels, breathing, heart rhythm and blood pressure are tracked second by second, and the medicines used today are short-acting and reversible in their effects. If something drifts, it is corrected in real time, long before it becomes dangerous.
For local anesthesia with sedation, the whole-body exposure is smaller still. You keep breathing for yourself, and the sedation is titrated by the person watching you.
Two practical steps help. Attend the pre-assessment appointment and answer honestly about smoking, alcohol, sleep apnea, allergies and previous reactions to anesthesia, including in relatives. Then tell the anesthesia clinician directly that you are frightened. It is a routine conversation for them, and many people find that a five-minute explanation of the monitoring does more for their nerves than any medicine could.
Why can’t you drive for 24 hours after anesthesia?
The rule feels arbitrary when you are sitting up, chatting and eating toast an hour after surgery. It is not arbitrary. After a general anesthetic or intravenous sedation, the NHS advises that you should not drive, operate machinery, sign legal documents or drink alcohol for 24 hours, and that an adult should take you home and ideally stay with you overnight.
Three reasons sit behind that guidance. First, the medicines used for sedation and general anesthesia are cleared from the body over hours, not minutes, and their tail effects on judgment, reaction time and coordination outlast the feeling of being awake. People routinely overestimate their own sharpness in this window, which is exactly the problem: the impaired brain is the one being asked to judge itself.
Second, after vitrectomy you have a patched or freshly operated eye. Depth perception and field of vision are altered even without any medicine on board. If a gas bubble has been placed in the eye, vision on that side may be a blur of moving fluid for days or weeks.
Third, the numbing block itself may leave the eye muscles weak for hours, producing double vision when the patch comes off. Driving with double vision is unsafe at any time.
Beyond driving, the same logic applies to caring for small children alone, cooking on an open flame, or climbing stairs in the dark. The MedlinePlus general anesthesia entry frames the first day as a time to rest at home with someone nearby.
Your surgeon will separately tell you when vision in the operated eye is adequate for driving again. That may be well beyond 24 hours, depending on the repair and whether gas was used, and it is a clinical judgment rather than a fixed number.
What happens if you don’t sleep before surgery?
Almost everyone sleeps badly the night before an eye operation, and a poor night does not cancel surgery. Anesthesia is not affected by how tired you are; the medicines do their work regardless. The people most affected by your sleeplessness are you, in the sense that anxiety feels louder on no rest, and nobody else.
Where a bad night does matter is in the things that tend to accompany it. Skipping breakfast because you are nauseous with nerves is fine if you are already fasting, but drinking coffee at 5 a.m. may breach your fasting instructions. Forgetting to take a permitted morning medicine because you are foggy is more consequential than the fatigue itself. So the practical advice is to prepare everything the night before: lay out clothes, write down the fasting times, and put the medicines you have been told to take in a visible place.
Fasting deserves a clear word. Fasting exists because a general anesthetic or deep sedation relaxes the reflexes that keep stomach contents out of the lungs. The NHS notes that instructions vary by hospital but commonly involve stopping food for around six hours and clear fluids for around two hours beforehand. Follow your own unit’s times exactly, even for a local anesthetic, because plans can change on the day and a local may need to be converted to a general.
If you have obstructive sleep apnea, tell the team and bring your device if asked. If you take a sedative or sleep aid regularly, do not stop or double it on your own; ask at pre-assessment.
Finally, if you are genuinely unwell rather than just tired, with fever, a new cough or vomiting, phone the unit early in the morning. That is information they need before you arrive.
The first days and weeks after vitrectomy anesthesia: a realistic timeline
Two clocks run after a vitrectomy: the anesthesia clock, measured in hours, and the eye clock, measured in weeks.
The anesthesia clock is short. Numbness around the eye from a block typically fades over several hours, sometimes with a droopy eyelid, mild double vision or bruising that resolves over a few days. Sedation grogginess clears through the first evening. After a general, sore throat and nausea usually settle within a day. The 24-hour restrictions on driving, alcohol and decision-making discussed above cover this period.
The eye clock is longer and depends on what was done. The eye is commonly patched overnight and examined the next morning. Redness, grittiness and light sensitivity are usual for the first week. Prescription drops are typically continued for several weeks; how many and for how long is set by your surgeon.
If a gas bubble was placed to hold the retina in position, it absorbs on its own over roughly two to eight weeks depending on the gas used, and vision on that side stays blurry until it is gone. The NHS retinal detachment guidance is explicit that you must not fly or travel to high altitude while gas remains, because pressure changes can expand the bubble dangerously, and that the same applies to nitrous oxide if you need another anesthetic for any reason during that time. Some people are also asked to keep their head in a specific position for several days so the bubble presses where it is needed.
If silicone oil was used instead, it stays until a later operation removes it. Vision through oil is usable but altered.
MedlinePlus notes that visual recovery after vitrectomy can take weeks to months and is governed by the health of the retina, not by which anesthesia was chosen. A cataract may also develop or progress in the operated eye over the following months and is treated separately if it does.
Risks and side effects of each vitrectomy anesthesia approach, in plain language
Every anesthesia choice trades one set of small risks for another. Honest information about both is what makes the decision yours as well as your team’s.
Local blocks around the eye carry risks specific to needles placed near a delicate organ. Bruising and swelling of the eyelids are common and harmless. Less common are bleeding behind the eye, which can raise pressure and occasionally requires the surgery to be delayed; accidental puncture of the eyeball, a rare but serious event more likely in very long-sighted eyes with a stretched wall; and spread of anesthetic toward the optic nerve or brainstem, which can cause temporary confusion, breathing changes or a slowed heart and is why monitoring continues even under “just a local.” Sub-Tenon’s techniques use a blunt cannula and reduce several of these risks, which is one reason many surgeons prefer them.
Sedation adds the possibility of breathing becoming shallow, disinhibition or restlessness, and, rarely, an allergic reaction. These are managed in the moment by the clinician at your side.
General anesthesia’s common side effects are nausea, sore throat, shivering, dental damage during airway placement and short-term confusion, particularly in older adults. Serious events, such as a severe allergic reaction, aspiration of stomach contents, or a heart or breathing complication, are rare and more likely in people with significant existing illness. Mayo Clinic notes that overall risk relates more to the patient’s health and the surgery than to the anesthetic itself.
Post-operative delirium in older people deserves a mention: a temporary state of confusion that can last days. It is more common after general anesthesia and after long operations, and families should be aware it can happen so it is recognized early.
None of these figures should be read as predictions for you. Your pre-assessment is where the general becomes specific.
What people often get wrong about anesthesia for eye surgery
Correcting a few myths does more to reduce pre-surgery dread than any amount of soothing language.
“I will see the surgery happening.” You will not. The block dampens the optic nerve and stops eye movement; most people perceive light, color or nothing.
“Being awake means feeling pain.” The block, not the sedation, handles pain. Pressure and pulling are normal; sharp pain is a signal to speak up and is fixable with more local anesthetic.
“General anesthesia is always safer because I won’t move.” Movement is prevented equally well by a good block. A general adds airway management and whole-body drug exposure, which is why it is reserved for cases that need it rather than used by default.
“If I sneeze or cough I will ruin the repair.” Surgeons pause for coughs constantly. Warn them if you feel one coming by raising a hand. Suppressing it silently and then jerking is worse.
“I have to fast for a local.” Usually yes, because a local can be converted to a general if needed. Follow the instructions you were given.
“Anesthesia causes long-term memory loss.” Short-term fogginess is common; sustained cognitive decline attributable purely to a single anesthetic is not established in the evidence, though older adults and those with existing memory problems are monitored more carefully.
“I can’t have surgery if I take blood thinners.” Many people do, with a plan agreed in advance. The technique may be adjusted rather than the medicine.
“The anesthetic decides how well I see afterward.” It does not. Visual outcome depends on the retina and the repair. The anesthetic decides how the day feels, and how the first 24 hours go.
Questions to ask your care team before vitrectomy
Pre-assessment appointments move quickly, and it is easy to leave with a leaflet but no answers to the things you actually wondered. Write these down and take them with you.
- Which type of anesthesia are you recommending for me, and what about my eye or my health points you that way?
- If we start with a local block and it is not enough, what happens next?
- Roughly how long do you expect the operation to take?
- How much am I likely to remember, and can the sedation be adjusted if I prefer more or less awareness?
- Will a block be placed even if I have a general, so the eye is comfortable when I wake?
- Which of my regular medicines should I take on the morning of surgery, and which should I pause? Who will confirm that plan for my blood thinner or diabetes medicine?
- What are my exact fasting times for food and for clear fluids?
- Do you expect to use a gas bubble or silicone oil, and if so, will I need to hold a head position or avoid flying?
- Who will be monitoring me during the operation, and will they be in the room throughout?
- What should I expect to feel in the first evening, and what is normal versus a reason to call?
- When can I realistically drive, work at a screen, or return to physical work?
- Is there anything about my sleep apnea, anxiety, previous anesthesia reactions or family history that changes the plan?
Bring someone with you if you can. Two sets of ears retain more, and that person is likely to be the one collecting you afterward and hearing the discharge instructions on your behalf.
None of these questions is a challenge to the team’s judgment. Good clinicians welcome them, because a patient who understands the plan lies stiller, worries less and recognizes problems earlier.
When to call your doctor after vitrectomy
Most of what you feel in the first days is expected: grittiness, redness, watering, a dull ache, blurred vision, and a heavy or bruised feeling around the eye from the block. The following are different and warrant a same-day call to the surgical unit or eye emergency service, using the number on your discharge sheet.
- Severe or steadily worsening eye pain that is not eased by the pain relief you were advised to use, especially with nausea or vomiting, which can signal high pressure inside the eye.
- A sudden drop in vision compared with the day before, a new curtain or shadow across your sight, or a shower of new floaters or flashes.
- Increasing redness, swelling or discharge from the eye, or the lids becoming hot and tight, which may indicate infection.
- Persistent double vision or an eyelid that is still drooping beyond the first day or two.
- Fever, chest pain, breathlessness, a new persistent cough or confusion in the days after a general anesthetic.
- Any head injury or fall onto the operated eye.
Sight-threatening infection inside the eye after surgery is uncommon, but it moves fast, which is why the combination of worsening pain, worsening redness and falling vision should never wait until morning. MedlinePlus lists infection, bleeding and retinal re-detachment among the recognized complications of vitrectomy that need prompt assessment.
If you have a gas bubble and you must have any other procedure or anesthetic before your surgeon has confirmed it is gone, tell that team clearly. Nitrous oxide can expand the bubble and cause a rapid, painful rise in eye pressure.
When in doubt, call. Eye units would far rather see a worried patient with a normal eye than miss the one that needed treatment.
Frequently asked questions
Do they put you to sleep for vitrectomy?
Not usually. Most adults have a local anesthetic block around the eye combined with intravenous sedation that makes you drowsy and calm while you keep breathing on your own. Full general anesthesia is used for children, long or complex operations, or people who cannot lie still. Your surgeon and anesthesia clinician decide together with you based on the repair needed and your health.
Is vitrectomy under local anesthesia painful?
The injection around the eye stings briefly, similar to a dental injection, and then the area goes numb and heavy. During the operation most people feel pressure or pulling but not sharp pain. If pain does break through, tell the team by raising a hand; more local anesthetic can be added. The sedation manages anxiety, while the block handles pain.
Will I be awake during eye surgery and see what is happening?
You may be lightly aware, but you will not watch the surgery. A working block quiets the optic nerve and the eye muscles, so the operating eye perceives only light, shadows or darkness. Many people doze under sedation and remember little. You will hear voices and the instruments, which is normal and not a sign of any problem.
I am scared of not waking up from anesthesia. How likely is that?
It is very rare. The NHS puts the risk of death linked to general anaesthesia at about one in every hundred thousand anaesthetics, mostly in people who are already seriously ill having major surgery. Vitrectomy is not major body surgery, and you are monitored continuously by a clinician whose sole job is your safety. Tell your anesthesia team about the fear; explaining the monitoring often helps.
Why can’t you drive for 24 hours after anesthesia?
Sedative and anesthetic medicines impair judgment, coordination and reaction time for hours after you feel alert, and the impaired brain is poor at assessing itself. After vitrectomy your operated eye is also patched or blurred, and a block can cause temporary double vision. The NHS advises no driving, machinery, alcohol or legal documents for 24 hours, with an adult accompanying you home.
What happens if you don’t sleep before surgery?
A poor night does not cancel or affect the anesthesia. The medicines work regardless of fatigue. What matters is following your fasting times, taking only the medicines you were told to take, and arriving on time. Prepare everything the night before so a foggy morning does not lead to mistakes. If you are actually unwell with fever or cough, phone the unit early.
What are the retinal surgery anesthesia options if I take blood thinners?
Many people on anticoagulants have vitrectomy safely. Injections around the eye carry a small bleeding risk, so teams often choose a sub-Tenon’s block, which uses a blunt cannula, or a general anesthetic. Whether to pause a blood thinner is decided jointly by your surgeon and prescribing clinician in advance. Never stop or change it on your own.
Do I have to fast if I am only having a local anesthetic?
Usually yes. Fasting protects your lungs if a local has to be converted to a general anesthetic during the operation, which can happen if the surgery becomes longer or more complex. The NHS notes that instructions vary by hospital but often involve no food for around six hours and no clear fluids for around two hours beforehand. Follow your own unit’s times exactly.
How long does the numbness around the eye last after a vitrectomy block?
Numbness and heaviness typically fade over several hours, sometimes with a droopy eyelid, mild double vision or bruising that settles over a few days. As the block wears off, the eye commonly feels gritty or achy. Your surgeon will advise on appropriate pain relief. Persistent double vision or a drooping lid beyond a day or two should be reported.
Does the type of anesthesia affect how well I see after vitrectomy?
No. Visual recovery depends on the health of the retina and the repair performed, not on whether you had a local block or a general anesthetic. MedlinePlus notes that recovery of vision can take weeks to months. The anesthesia choice shapes how the day itself feels and how the first 24 hours go, not the final result.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Glaucoma Surgery Can and Cannot Do: Protecting the Vision You Still Have
Glaucoma surgery lowers pressure inside the eye to slow or stop further damage to the optic nerve. It cannot restore vision already lost, because…

Intraocular Lens Recovery: Eye Drops, Lifting Limits and When Vision Settles
Most people recover from intraocular lens (IOL) surgery over about 4 to 8 weeks, according to the NHS and Mayo Clinic, though everyday vision…

Helping a Child Stick With Eye Patching: Practical Support for Amblyopia Treatment
Helping a child with an eye patch for amblyopia works best when patching becomes a predictable, short, engaging routine: same time daily, paired with…

Preparing for a Contact Lens Fitting: Prescriptions to Bring and What to Tell Your Doctor
Preparing for a contact lens fitting means bringing your current glasses, any previous contact lens prescription or boxes, a list of medicines and eye…

PRK for Athletes, Pilots and Contact-Sport Players: Why No Flap Can Matter
PRK is a laser vision correction method that reshapes the cornea after removing its surface layer, rather than cutting a hinged flap as LASIK…
What the Femtosecond Laser Changes in Femto LASIK Compared With a Blade
In Femto LASIK, a femtosecond laser replaces the mechanical blade (microkeratome) used to create the thin corneal flap that begins LASIK. The laser fires…