

Mealtime Support for Someone With Dysphagia: Positioning, Pacing and Swallowing Safety

Key Takeaways
- Swallowing has four stages, oral preparatory, oral, pharyngeal and esophageal, and the texture, posture and pacing advice a person receives depends on which stage is failing.
- The IDDSI framework used by most clinicians runs from level 0 (thin liquids) to level 7 (regular food), and a dysphagia 5 diet means minced and moist food that mashes easily with a fork.
- Mixed textures such as cereal in milk or soup with lumps are among the riskiest foods because the liquid part reaches the airway before the solid part is controlled.
- Silent aspiration, where food enters the airway without a cough, is common after stroke and in neurological disease, so recurring chest infections and unexplained fevers can be the only clue.
- Thickened drinks slow the flow of liquid to protect the airway but are reliably drunk in smaller amounts, which makes dehydration a recognized complication that needs active monitoring.
- Tilting the head back to help food go down opens the airway and is usually the opposite of what a swallowing plan recommends; neutral or chin-forward is the default unless told otherwise.
Mealtime support for dysphagia means helping someone eat and drink in the way their swallowing assessment recommends: sitting fully upright with the head slightly forward, offering small mouthfuls at a slow, unhurried pace, serving the prescribed food texture and drink thickness, keeping distractions low, checking the mouth is clear before the next bite and staying upright afterwards. Coughing, wet breathing, fever or chest symptoms after meals need prompt medical review.
The soup is the right temperature, the spoon is the right size, and still the man at the table hesitates. His wife waits, hand hovering. Three weeks after his stroke, every mouthful is a small negotiation between hunger and the memory of the last coughing fit. Nobody warned either of them that eating would become the hardest part of the day.
Scenes like this play out in kitchens, care homes and hospital bays more often than most people realize. Swallowing is a reflex we take for granted roughly a thousand times a day, and when it falters, the people who love the person with dysphagia suddenly become the front line of safety. Good mealtime support for dysphagia is not instinctive; it is learned, and the evidence on what helps is clearer than the folklore suggests.
This explainer covers what actually happens when a swallow goes wrong, how positioning and pacing change the odds, what the texture levels mean, and the warning signs that should send you to the phone.
What mealtime support for dysphagia actually involves
Dysphagia is the medical word for difficulty swallowing, whether that is trouble moving food around the mouth, trouble triggering the swallow or trouble getting food down the esophagus, the muscular tube from throat to stomach. Mealtime support is the practical, moment-to-moment help that makes eating safer for someone with that difficulty.
The central danger is aspiration: food, drink or saliva slipping past the vocal cords into the airway instead of the esophagus. Aspiration can cause choking in the moment and, less obviously, a chest infection called aspiration pneumonia days later. According to the Mayo Clinic, dysphagia can also lead to malnutrition, dehydration and weight loss when eating becomes slow, tiring or frightening.
Support therefore works on two fronts at once. The physical front is about mechanics: how the person sits, how much goes on the spoon, how fast it arrives, what texture it has. The human front is about attention: watching for subtle signs of trouble, protecting the person’s dignity, keeping the meal calm enough that the swallow is not rushed by anxiety.
In most health systems, a speech-language pathologist (sometimes called a speech and language therapist) assesses the swallow and writes a plan. That plan might name a food texture, a drink thickness, a sitting position, a specific swallowing technique and a pace. The job of the family member or care worker is to carry that plan out consistently and to report back when something changes. Mealtime support is not a substitute for assessment; it is what makes an assessment useful between appointments.
The four stages of swallowing, and where the stages of dysphagia come from
People often search for the four stages of dysphagia. Strictly, clinicians describe four stages of a normal swallow, and dysphagia is named by the stage where things go wrong. Understanding them explains why positioning and pacing matter so much.
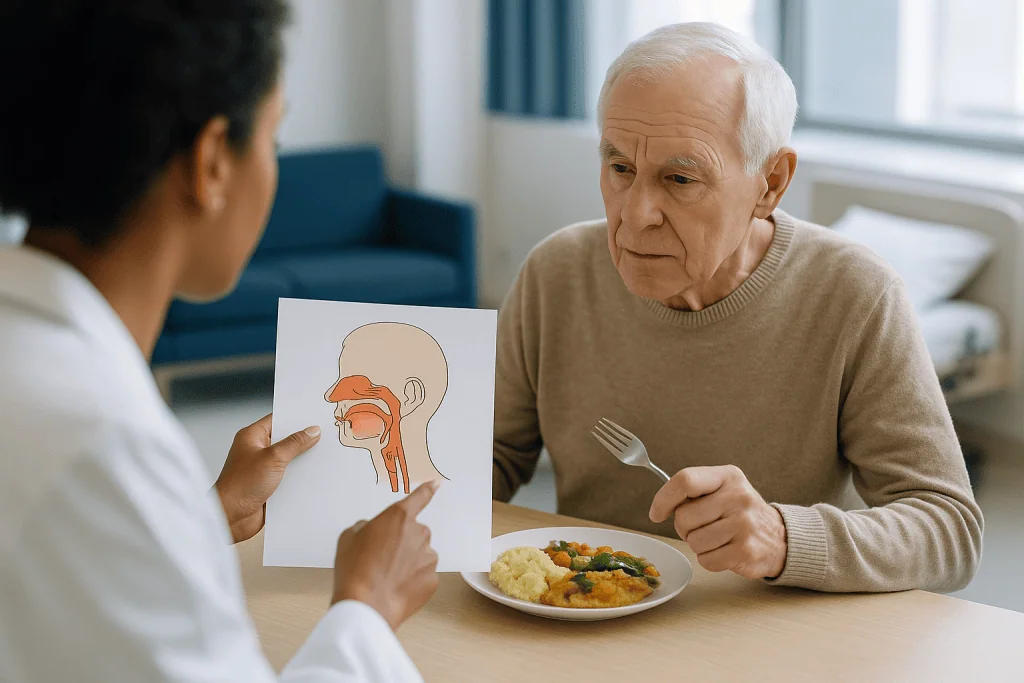
The oral preparatory stage is chewing: food is broken down and mixed with saliva into a soft ball called a bolus. The oral stage is the tongue pressing that bolus backwards towards the throat. The pharyngeal stage is the reflex part: in well under a second the soft palate lifts, the voice box rises, the epiglottis folds over the airway and the bolus is squeezed through the pharynx, the throat space behind the mouth. The esophageal stage is the muscular wave that carries food down to the stomach.
Johns Hopkins Medicine divides difficulties into oropharyngeal dysphagia, affecting the mouth and throat stages, and esophageal dysphagia, affecting the tube below. Strokes, Parkinson’s disease, dementia and head and neck cancer treatment tend to disturb the first group; narrowing, reflux damage or motility disorders tend to cause the second.
Why does this matter at the table? Because the fixes differ. Weak chewing calls for softer textures. A slow or delayed pharyngeal reflex means thin liquids may reach the airway before it closes, which is why some people are prescribed thicker drinks. Esophageal problems rarely improve with posture alone and may need medical or endoscopic treatment that only the treating team can decide on. When you know which stage is failing, the plan stops looking arbitrary.
Who needs mealtime support for dysphagia, and who should wait for an assessment
Anyone with a confirmed swallowing problem benefits from someone who knows how to help at meals. In practice, that means people recovering from stroke, people living with progressive neurological conditions such as Parkinson’s disease, multiple sclerosis or motor neuron disease, people with advanced dementia, people after surgery or radiotherapy to the head and neck, and frail older adults whose swallow has simply weakened. The NHS notes that dysphagia can affect people of any age but is more common in older adults.
Who should wait? Nobody should be started on texture-modified food, thickened drinks or a particular posture on a hunch. A family member who notices coughing at meals, a wet-sounding voice after drinks or food sticking should ask for a swallowing assessment rather than improvise a soft diet. Unassessed modification can backfire: thickened fluids reduce how much people drink, pureed food can be less nutritious and less appetizing, and the wrong head position can make some swallows less safe, not more.
Assessment usually begins with a bedside or clinic examination by a speech-language pathologist. If more detail is needed, the Mayo Clinic describes two common instrumental tests: a videofluoroscopic swallow study, which is a moving X-ray taken while the person swallows barium-coated foods and drinks, and a fiberoptic endoscopic evaluation of swallowing, where a thin flexible camera is passed through the nose to watch the throat directly.
Those tests show which textures reach the airway and which are swallowed cleanly. The plan that follows is individual. Two people with the same diagnosis can need different textures and opposite head positions, which is exactly why copying what worked for a neighbor is unwise.
How should someone with dysphagia sit to eat?
Posture is the cheapest, fastest safety intervention at any table, and it is the one most often skipped. The aim is simple: use gravity to send food towards the esophagus and give the airway the best chance to close.

Fully upright means hips bent at roughly a right angle, back supported, feet flat on the floor or a footrest, and shoulders level. Slumping to one side or sliding down a chair lets the chin rise, which opens the airway and straightens the throat into a chute towards the lungs. In bed, this means sitting up as high as the bed and pillows allow, with support behind the back rather than just behind the head.
The head should be in a neutral position or tipped slightly forward. Many swallowing plans prescribe a chin tuck: lowering the chin towards the chest during the swallow, which narrows the airway entrance and widens the space where food collects before the swallow triggers. It helps some people and not others, so it belongs in the plan only when a clinician has recommended it.
Some people after a stroke are taught a head turn towards the weaker side of the throat, which closes off that side and routes food down the stronger channel. Again, direction matters, and the wrong direction can worsen matters.
Practical details make the difference. Bring the food to the mouth rather than asking the person to lean down to the plate. Avoid feeding anyone who is drowsy, agitated or lying flat. After the meal, keep the person upright for the period the therapist advises, because residue left in the throat or reflux from the stomach can be aspirated after the last bite.
Pacing a meal: why slower is safer
If posture is the skeleton of a safe meal, pacing is its heartbeat. A weakened or delayed swallow needs time, and the most common error a well-meaning helper makes is loading the next spoonful while the last one is still in the throat.
Start with small amounts: a teaspoon rather than a tablespoon, half a cup rather than a full glass. Smaller boluses are easier to control and, if they go the wrong way, less dangerous. Offer one mouthful, then wait. Watch for the throat to rise and fall, which shows the swallow has happened. Some people need two or three swallows to clear a single mouthful; the plan may ask for a deliberate dry swallow after each bite.
Check that the mouth is empty before the next spoon. Food pocketed in the cheek, common after a stroke or in dementia, can be inhaled later when the person lies down or talks. A quick look, or a gentle prompt to run the tongue around the mouth, prevents that.
Talking while chewing or swallowing is a hazard, not a social nicety. Keep conversation for the gaps between mouthfuls. Turn the television off, clear the table of clutter and sit at eye level rather than standing over the person; attention is easier to hold without competing noise.
Fatigue changes the swallow. Many people are strongest at the start of a meal and at the start of the day, so the most nourishing part of the meal should come early, and a long meal is often better split into two shorter ones. If coughing, throat clearing or a gurgly voice appears, stop, let the person recover fully and reassess before offering more.
What do people with dysphagia eat? Dysphagia diet foods explained
The honest answer is: it depends entirely on their assessment. There is no single dysphagia diet. There is a ladder of food textures and drink thicknesses, and each person is placed on the rung their swallow can manage safely.
Most clinicians now use the International Dysphagia Diet Standardisation Initiative framework, usually shortened to IDDSI. Cleveland Clinic describes it as a scale of eight levels numbered 0 to 7, running from thin liquids at the bottom through increasingly thick drinks to pureed, minced, soft and finally regular foods at the top. Drinks occupy levels 0 to 4 and foods levels 3 to 7, with overlap in the middle where a thick drink and a thin puree behave similarly.
What the levels have in common is predictability. A dangerous food is one that behaves unpredictably in the mouth: it splits into a liquid and a solid (soup with lumps), it needs a lot of chewing (steak, crusty bread), it crumbles into dry particles (crackers, dry cake), it is sticky (peanut butter, soft white bread balls up) or it is stringy and fibrous (celery, pineapple). Mixed textures are the classic trap, which is why cereal in milk is often off the menu even for people who can manage both separately.
Safer foods at the softer levels are moist, uniform and hold together on the spoon: smooth yogurt, well-mashed potato with gravy, scrambled eggs, soft flaked fish in sauce, blended casseroles, thick smooth soups. At the higher levels, soft cooked vegetables, tender meat cut small and ripe bananas may be allowed. The therapist’s plan names the level; a dietitian can help make that level nourishing, since pureed diets are easy to under-eat on.
What is a dysphagia 5 diet? The texture levels side by side
A dysphagia 5 diet is IDDSI Level 5, called minced and moist. It is one of the most frequently prescribed levels and sits between pureed food and soft, bite-sized food. The table summarizes the food levels as described in the IDDSI framework and summarized by Cleveland Clinic.
| Level | Name | What it looks like | Typical examples |
|---|---|---|---|
| 3 | Liquidised | Pourable, smooth, no lumps; can be drunk from a cup or eaten with a spoon | Thin smooth soup, runny custard |
| 4 | Pureed | Smooth, holds its shape on a spoon, no chewing needed | Thick puree of meat or vegetables, smooth mousse |
| 5 | Minced and moist | Small, soft, moist lumps that mash easily with a fork; minimal chewing | Finely minced meat in thick gravy, mashed soft fish |
| 6 | Soft and bite-sized | Soft, tender pieces that can be cut with the side of a fork; chewing needed | Tender casserole meat, soft cooked vegetables |
| 7 | Easy to chew / Regular | Normal foods, with hard or stringy items avoided at the easy-to-chew sub-level | Most everyday meals |
Level 5 food is minced finely enough that lumps are small and uniform, and moist enough that no liquid separates out on the plate. The fork test used in IDDSI is practical: press a fork onto the food and it should mash easily, with no hard pieces left behind. Dry mince, mince with visible gristle, or mince sitting in thin watery juice all fail the standard.
If you are preparing Level 5 food at home, moisture is the ingredient that matters most. Thick sauces, gravies and dressings bind the lumps and make the bolus hold together in the mouth. A food processor with pulse control gives more consistent results than a knife. Ask the therapist to check a sample if you are unsure; getting the level right is a safety issue, not a culinary one.
Thickened drinks, dehydration and the hydration trade-off
Thin liquids are, for many people with dysphagia, the most dangerous thing on the table. Water moves fast and spreads out, so if the pharyngeal reflex is slow the liquid can reach the open airway before it closes. Thickening slows the flow and gives the throat time to catch up, which is why speech-language pathologists prescribe drinks at IDDSI levels 1 through 4, from slightly thick to extremely thick.
Thickening is usually done with a commercial powder or gel added to drinks, or with pre-thickened products. The prescribed level, the amount of thickener and the mixing method should come from the swallowing plan and the product’s own instructions; too thin and the drink is unsafe, too thick and it leaves residue in the throat that can itself be aspirated.
The trade-off is real. Thickened drinks are less pleasant and less thirst-quenching, and people reliably drink less of them. The Mayo Clinic lists dehydration among the recognized complications of dysphagia, and it tends to creep up quietly: darker urine, dry mouth, constipation, confusion in older adults. Offering drinks little and often across the day, rather than relying on large volumes at meals, helps. So does counting the fluid hidden in foods such as thick soups, yogurt and pureed fruit.
Ice cream, jelly and ice cubes deserve a special warning. They are solid on the plate and thin liquid in the mouth, which makes them behave like water once they melt. They are often restricted for anyone on thickened fluids unless the therapist says otherwise.
Some services use carefully supervised protocols that allow sips of plain water between meals for selected people with a clean mouth. Whether that is appropriate is a clinical decision for the treating team, not a household one.
Mouth care, dentures and medicines at mealtimes
A clean mouth is one of the least glamorous and most effective parts of mealtime support for dysphagia. If small amounts of saliva or food do reach the lungs, what they carry matters: a mouth full of dental plaque and bacteria is far more likely to seed a chest infection than a clean one. Brushing teeth, gums and tongue twice a day, and rinsing or wiping the mouth after meals, lowers that bacterial load.
Dentures change the equation in both directions. Well-fitting dentures restore chewing and help form a bolus; loose ones slip, cause pain and encourage people to swallow food half-chewed. Weight loss, which is common with dysphagia, often makes dentures that once fitted become loose. A dental review is worth asking for whenever eating has become slower or more cautious.
Medicines are a frequent sticking point, literally. Large tablets and capsules can lodge in the throat or esophagus, and some people are tempted to crush them or open capsules into food. That is not always safe: modified-release and coated formulations are designed to dissolve slowly or in a particular place, and crushing can change how the drug behaves. Only a pharmacist or the prescribing clinician should decide whether a specific medicine can be altered or swapped for a liquid or a different form. The right question to take to the pharmacy is simply: this person has dysphagia, which of these can be safely given in a different form?
Dry mouth, a side effect of many medicines and a symptom of some conditions, makes swallowing harder because saliva is the natural lubricant. Sips of prescribed-consistency fluid before and during meals, and raising the issue with the care team, are reasonable first steps.
What the first weeks on a modified texture usually look like
The timeline depends on the cause. After a stroke, swallowing often improves in the early weeks as the brain recovers, and the NHS notes that many people regain a safer swallow with time and therapy. In progressive conditions such as Parkinson’s disease or motor neuron disease, the direction of travel is the opposite, and the plan is reviewed as abilities change. In either case, a texture level is a snapshot, not a sentence.
The first days usually feel like a loss. Pureed food looks institutional, thickened tea tastes wrong, and meals take longer. Appetite often dips. This is the period when weight should be watched most closely, because a person who eats less of a less energy-dense diet can lose weight quickly. Weekly weighing on the same scales, at the same time of day, gives the team useful numbers.
Swallowing therapy may begin in parallel. The Mayo Clinic describes exercises designed to strengthen or coordinate the swallowing muscles, along with techniques such as altered head positions or specific swallowing maneuvers. Exercises are prescribed individually and need practice between sessions, which often falls to the family.
Reassessment is the hinge of the whole process. If the person is coughing less, finishing meals and gaining or holding weight, the therapist may trial a less restrictive level. If coughing, chest infections or weight loss appear, the plan may be tightened or further tests arranged. Neither change is a failure; both are the system working.
For some people whose swallow remains unsafe or who cannot take enough by mouth, the team may raise the option of tube feeding into the stomach. That is a significant, individual decision with benefits and burdens on both sides, and it belongs in a conversation with the treating team, the person and those close to them.
Tips for coping with dysphagia: appetite, dignity and eating with others
The clinical plan keeps someone safe; the social plan keeps them eating. Both matter, because malnutrition is as real a complication as pneumonia.
Presentation changes appetite more than most people expect. Pureed meals served as separate colors, shaped with molds or simply piped rather than spooned in a heap, look like food rather than paste. Season generously; chewing releases flavor, and food that is barely chewed can taste flat. Serve hot food hot and cold food cold, because lukewarm puree is nobody’s favorite.
Little and often beats three large meals for most people who tire quickly. Five or six small eating occasions across the day spread the effort and give more chances to take in energy and fluid. A dietitian can suggest ways to make small portions count: adding cream, butter, cheese, milk powder or oil to purees raises the energy without adding volume.
Eating is social, and isolation makes dysphagia worse. Where it is safe, keep the person at the family table at normal mealtimes, even if their food looks different. In restaurants, soups, risottos, well-cooked fish and mashed sides are often workable at the softer-but-not-pureed levels; a quiet word with staff about avoiding garnish, nuts and crusty bread solves most problems. Carry a small container of thickener if drinks are prescribed thick.
Finally, protect choice. Being fed is one of the hardest losses of independence an adult experiences. Let the person set the pace with a hand signal, choose between two options, hold the cup where possible, and finish when they say they are finished. Autonomy is not a luxury added after safety; it is part of what keeps people willing to eat at all.
What people often get wrong about mealtime support for dysphagia
“If they are not coughing, they are not aspirating.” Silent aspiration, where food or liquid enters the airway without triggering a cough, is well recognized, particularly after stroke and in neurological disease. The Mayo Clinic lists aspiration pneumonia among dysphagia’s complications precisely because the body’s alarm system is often faulty. A quiet meal is reassuring but not proof of safety; recurrent chest infections and unexplained fevers are the clues.
“Soft food is automatically safe food.” Soft is not the same as uniform. Minestrone is soft and dangerous because it mixes thin liquid with lumps. A ripe banana is soft but can be sticky. The level matters, not the adjective.
“Thicker is always safer.” Overly thick drinks leave residue in the throat and are drunk less, which trades one risk for dehydration and more residue to aspirate later. The prescribed level is a target, not a minimum.
“Tipping the head back helps it go down.” For most people with oropharyngeal dysphagia, extending the neck opens the airway and is one of the riskiest things a helper can do. Neutral or slightly forward is the default unless the plan says otherwise.
“Dysphagia is just part of getting old.” Swallowing weakens with age, but new or worsening difficulty always has a cause worth finding. The NHS is clear that swallowing problems should be assessed rather than accepted.
“Crushing tablets into yogurt is harmless.” Some formulations are safe to alter and some are not; only the pharmacist or prescriber can say which.
“Once on puree, always on puree.” Levels move in both directions with reassessment. Many people after stroke progress back towards normal textures over weeks.
Questions to ask your care team
Appointments are short and the questions arrive on the drive home. Taking a list makes the plan clearer and your role more confident. The following are the ones that most often matter.
- Which stage of swallowing is affected, and what does that mean for the kinds of foods and drinks that are risky?
- Exactly which IDDSI level is prescribed for food, and which for drinks? Can I have it in writing?
- Is there a specific head position or swallowing technique for this person, and can you show me rather than describe it?
- How large should each mouthful be, and how long should I wait between them?
- What signs during a meal should make me stop, and what signs should make me call someone?
- Is it safe for this person to drink plain water between meals, and under what conditions?
- Which of their regular medicines can be given in a different form, and who do I ask about that?
- Are there swallowing exercises to practice at home, how often, and how will we know if they are working?
- How often will the swallow be reassessed, and what would trigger an earlier review?
- Who do I contact if things change on a weekend or in the evening?
- Can a dietitian help us keep weight and energy intake up on this texture?
- If swallowing does not improve, what are the options, and when would that conversation start?
Write down the answers, including the name of the person who gave them. If several carers are involved, a single sheet on the fridge with the texture level, drink thickness, posture, pace and stop signs prevents the dangerous drift that happens when each helper does things slightly differently.
When to call your doctor
Mealtime support is designed to prevent emergencies, and knowing the line between “watch closely” and “act now” is part of the job.
Call emergency services immediately if the person cannot breathe, cannot cough or speak, is clutching the throat, or turns blue or grey around the lips: these are signs of choking with a blocked airway and need first aid and an ambulance at once. Also treat sudden severe breathlessness, chest pain or collapse during or after a meal as an emergency.
Contact the doctor or care team the same day for a new fever, a wet or crackly cough, breathlessness, confusion or unusual drowsiness in the hours or days after meals, since these can be early signs of aspiration pneumonia. The same applies to a wet, gurgly voice that persists after eating, repeated coughing or throat clearing at most meals when it was not there before, or a meal where food appeared to lodge and would not clear.
Arrange a routine but prompt review for food sticking in the chest, pain on swallowing, unexplained weight loss, signs of dehydration such as dark urine or dizziness on standing, a noticeable increase in the time meals take, refusal of food or drink, or a general sense that the swallow is getting worse. Any of these may mean the texture level needs revisiting or further tests are warranted.
Do not change the prescribed texture, thickness or technique on your own, even in the direction that seems safer; thickening everything can create its own problems. Report what you have seen, as specifically as you can, and let the treating team decide the next step. A short note of dates, foods involved and what happened is worth more than any amount of worried description.
Frequently asked questions
What do people with dysphagia eat day to day?
People with dysphagia eat the texture level their swallowing assessment prescribes, which ranges from smooth purees to soft bite-sized food. The common thread is predictability: moist, uniform foods that hold together, such as smooth yogurt, mashed potato with gravy, scrambled eggs or blended casseroles. Dry, crumbly, sticky, stringy or mixed-texture foods are usually avoided. A dietitian can help keep the chosen level nourishing.
What are the four stages of dysphagia?
The phrase usually refers to the four stages of a normal swallow: oral preparatory (chewing), oral (the tongue moving food back), pharyngeal (the reflex that closes the airway and pushes food through the throat) and esophageal (the muscular wave to the stomach). Dysphagia is described by the stage affected, most often as oropharyngeal or esophageal, and the treatment plan follows from that.
What is a dysphagia 5 diet?
A dysphagia 5 diet is IDDSI Level 5, called minced and moist. Food is finely minced into small, soft lumps, bound with enough sauce or gravy that no liquid separates out, and should mash easily under a fork with no hard pieces. It needs minimal chewing and sits between pureed food (Level 4) and soft, bite-sized food (Level 6).
What are the best tips for coping with dysphagia at home?
Follow the prescribed texture and drink thickness exactly, sit fully upright with the chin slightly forward, take small mouthfuls slowly and check the mouth is clear between them. Keep the mouth clean, serve small meals more often, present pureed food attractively and season it well. Protect the person’s choice and pace, and report any coughing, chest infections or weight loss to the care team promptly.
How should a person with dysphagia be positioned to eat?
Sit them fully upright with the back supported, hips at about a right angle and feet flat, whether in a chair or propped high in bed. Keep the head neutral or slightly forward; never tipped back. Some plans add a chin tuck or a head turn towards the weaker side, but those are individual instructions from the therapist. Stay upright after the meal for the time advised.
Why are thin liquids like water dangerous in dysphagia?
Thin liquids move quickly and spread out in the mouth and throat, so if the swallowing reflex is slow or weak the liquid can reach the airway before it closes. Thickening slows the flow and gives the throat time to protect itself. Whether someone needs thickened drinks, and at what level, is decided by a swallowing assessment rather than guessed at home.
Can someone with dysphagia aspirate without coughing?
Yes. Silent aspiration, where food, drink or saliva enters the airway without triggering a cough, is well recognized, especially after stroke and in neurological conditions. That is why a quiet meal is not proof of safety, and why recurring chest infections, unexplained fevers or a persistently wet voice after eating should be reported to the care team even if nobody saw a choking episode.
How long does dysphagia last after a stroke?
It varies widely. The NHS notes that swallowing often improves in the weeks after a stroke as the brain recovers and with therapy, while in other people difficulty persists longer. Texture levels are reviewed and can be relaxed as the swallow strengthens. The treating speech-language pathologist is the right person to ask about an individual outlook, since recovery depends on the size and site of the stroke.
Is it safe to crush tablets for someone with swallowing problems?
Not without checking first. Some tablets can be crushed or capsules opened safely, but modified-release and coated medicines are designed to dissolve slowly or in a particular part of the gut, and altering them can change how they work. A pharmacist or the prescribing clinician can advise which medicines can be given in a liquid or alternative form for someone with dysphagia.
When should a carer stop a meal and call for help?
Stop the meal if coughing, choking, throat clearing, a wet or gurgly voice, breathlessness or distress appears, and let the person recover fully. Call emergency services if they cannot breathe, cough or speak, or their lips turn blue or grey. Contact the doctor the same day for fever, a chesty cough, confusion or drowsiness after meals, which can signal aspiration pneumonia.
References
- NHS: Swallowing problems (dysphagia)
- Cleveland Clinic: Dysphagia (difficulty swallowing)
- MedlinePlus: Swallowing disorders
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Families Can Do Between Therapy Sessions to Support a Child With Cerebral Palsy
Between therapy sessions, families support a child with cerebral palsy mainly by folding the therapist's goals into daily routines: planned positioning, regular stretching, supported…

Can Cognitive Stimulation and Nutrition Help in Alzheimer’s Disease? What Care Plans Include
Cognitive stimulation, usually delivered as structured group sessions, produces small but measurable gains in thinking and quality of life for people with mild to…

Who Is a Candidate for Deep Brain Stimulation in Parkinson’s Disease? How Teams Decide
A person is usually considered a candidate for deep brain stimulation in Parkinson's disease when the diagnosis is confirmed, symptoms still respond well to…

How Can Family Help During and After a Seizure? A Caregiver’s Guide to Epilepsy Care
Helping someone during a seizure means keeping them safe, not stopping the seizure. Ease them to the floor, cushion the head, move hard objects…

When Symptoms Do Not Match the Scans: How an FND Diagnosis Is Confirmed and Treatment Begins
FND is diagnosed by a neurologist on the basis of positive clinical signs, not by normal scans alone. The examiner looks for features that…

Preparing an Infant for Congenital Hydrocephalus Surgery: Imaging, Feeding and Anesthesia
Preparing a baby for hydrocephalus surgery usually involves three strands: imaging (head ultrasound, MRI or CT) to confirm where fluid is building up; fasting…