

Nausea, Constipation and Sulfur Burps on GLP-1s: Why They Happen and What Genuinely Helps

Key Takeaways
- Nausea, constipation and sulfur burps on semaglutide share one mechanism: the medicine slows stomach emptying, which dries stool, stretches the stomach and gives bacteria longer to ferment sulfur-rich protein.
- In the pivotal weight-management trial, 24 percent of people on semaglutide reported constipation and 44 percent reported nausea, against 11 and 17 percent on placebo, with most episodes mild and clustered around strength increases.
- Post hoc analyses found people with no nausea or vomiting lost about as much weight as those who had them, so side effects are not a gauge of whether the medicine is working.
- Eggs are not banned on Ozempic; they are simply high in cysteine and methionine, the amino acids gut bacteria turn into rotten-egg-smelling hydrogen sulfide when food lingers.
- A head-to-head trial in 2025 found gastrointestinal side effects broadly similar between tirzepatide and semaglutide, so Mounjaro constipation follows the same logic and responds to the same measures.
- Ileus was added to Ozempic's labeling in 2023 based on postmarketing reports; the pattern that needs same-day care is several days without a bowel movement plus a swollen, firm, painful abdomen and vomiting.
Ozempic constipation, nausea and sulfur burps share one root cause: the medicine slows how fast food leaves the stomach and moves through the gut. Slower transit dries out stool, stretches a full stomach and lets bacteria ferment sulfur-rich protein into rotten-egg gas. Most symptoms are mild and ease within weeks; persistent vomiting, severe pain or no bowel movement for several days needs medical review.
The comment sections filled up first. Within days of the FDA clearing a tablet form of semaglutide for weight management in late 2025, the videos arrived: people filming themselves mid-belch, then apologizing to whoever was in the car. “Nobody warned me about the eggs,” one caption read. As of early 2026, searches for ozempic constipation, rotten-egg burps and “how long does the nausea last” sit near the top of every health query list, and the questions are more practical than panicked.
That practicality is deserved. GLP-1 medicines are now taken by millions of adults for type 2 diabetes and for weight management, and the digestive side effects are, by a wide margin, the most common reason people call their clinic in the first three months. Some of what circulates online is right. A fair amount is folklore dressed up as insider knowledge.
This piece sorts one from the other, using trial numbers rather than testimonials, and explains what a slowed-down gut actually does to a Tuesday afternoon.
Why does Ozempic cause constipation? The gut simply slows down
Semaglutide, the active ingredient in Ozempic and Wegovy, is a GLP-1 receptor agonist: a lab-made copy of glucagon-like peptide-1, a hormone your small intestine releases after a meal to tell the body food has arrived. The natural hormone lasts minutes. The medicine lasts about a week, which is exactly why it works and exactly why the gut notices.
One of GLP-1’s jobs is to slow gastric emptying, the rate at which the stomach hands food to the small intestine. Slower emptying is a feature for blood sugar, because glucose trickles in rather than floods. Further down, though, the same braking effect stretches the time stool spends in the colon. The colon’s main task is to reclaim water, and it is good at it. Give it an extra day with the same material and you get stool that is drier, harder and more reluctant to move. That is ozempic constipation in one sentence.
Two quieter contributors stack on top. People on these medicines eat considerably less, and a smaller volume of food means less bulk to trigger the stretch reflexes that push the bowel along. Fiber intake tends to fall in step with total intake, and so does fluid, because a stomach that already feels full is not asking for a glass of water. Add the fatigue many people report in the early weeks, and the daily walk that used to keep things regular quietly disappears.
Physiology studies using stomach-emptying tests suggest the delay is strongest in the first weeks and partially fades over months, especially for solid food. That matches what most people describe: the constipation is real, it is usually worst early and after a strength increase, and for many it settles into something manageable rather than something permanent.
Ozempic nausea: what is actually happening in the stomach and brain
Nausea on semaglutide comes from two directions at once, which is why it can feel different from ordinary queasiness.
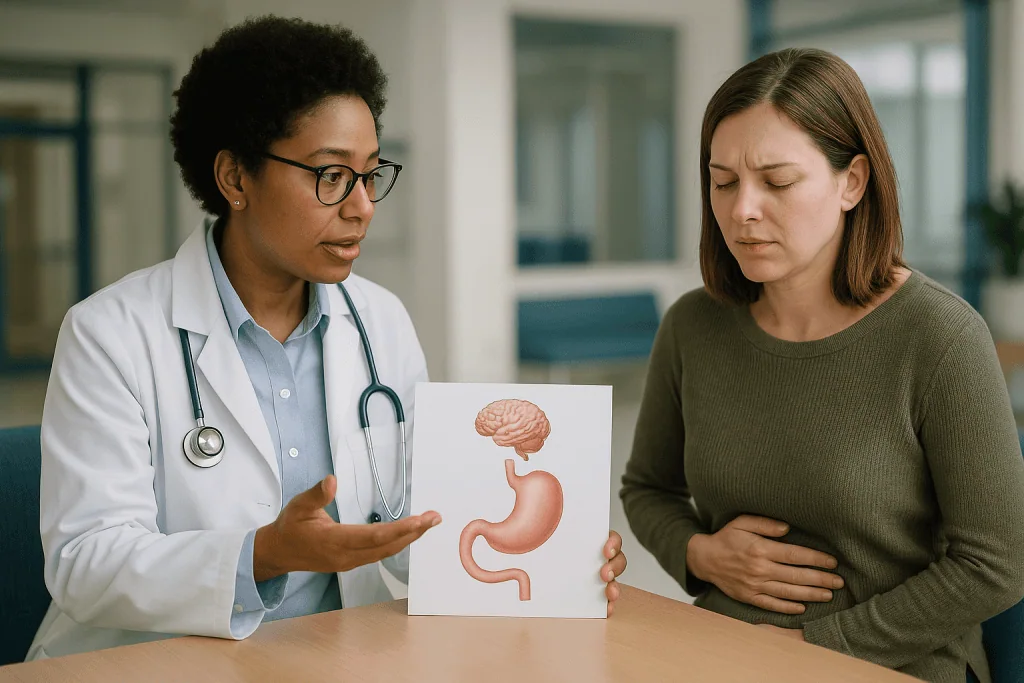
The first route is mechanical. A stomach that empties slowly is a stomach that stays stretched. Stretch receptors in its wall send fullness signals to the brainstem, and when a normal-sized dinner arrives on top of a lunch that has not fully left, those signals tip from “satisfied” into “too much.” This is the nausea people describe after eating the way they used to eat.
The second route is direct. The area postrema, a small region at the base of the brain that sits outside the blood-brain barrier and acts as the body’s nausea detector, carries GLP-1 receptors. The medicine stimulates them. This is the same region that responds to certain chemotherapy drugs and to motion, and it explains why some people feel queasy on an empty stomach, or before they have eaten anything at all.
Trial data give the shape of the problem. In the large weight-management trials of semaglutide, roughly four in ten participants reported nausea at some point, compared with fewer than two in ten on placebo. The overwhelming majority of episodes were rated mild or moderate, and most clustered in the first weeks and around each move to a higher strength, then faded. Vomiting was less common, affecting about a quarter of participants over more than a year versus about one in fourteen on placebo.
What makes ozempic nausea worse is predictable: large meals, high-fat meals, lying down within an hour of eating, alcohol, and anxiety about the nausea itself, which primes the very brain region already on alert. What makes it better is the mirror image of that list, covered later in the article.
Sulfur burps on Ozempic: the rotten-egg chemistry explained
Sulfur burps are belches that smell like rotten eggs or a struck match. The odor is hydrogen sulfide, a gas your gut bacteria produce when they break down sulfur-containing compounds, mainly the amino acids cysteine and methionine found in protein, along with sulfate from some vegetables and processed foods.
Under normal conditions, most protein digestion happens in the small intestine before bacteria get much of a chance at it. Slow the stomach down and the arithmetic changes. Food sits longer, more of it reaches bacteria in a partly digested state, more gas is produced, and the outlet at the bottom of the stomach is in no hurry to let anything through. Gas takes the route of least resistance, which is upward.
The clinical trials did not record “sulfur burps” as a category, because trials use standardized medical terms. They did record eructation, the formal word for belching. In the pivotal weight-management study of semaglutide, about 7 percent of participants reported it, compared with roughly 1 percent on placebo. That understates lived experience, since many people mention the smell only when a doctor asks, but it confirms the pattern is a medicine effect, not a coincidence.
Foods rich in sulfur compounds turn the volume up: eggs, red meat, poultry, fish, dairy, garlic, onions, broccoli, cauliflower, cabbage, Brussels sprouts, and some whey protein supplements. Beer and certain dried fruits treated with sulfites can contribute too. This is where the viral “you can’t eat eggs on Ozempic” claim was born, and the section on eating explains why the truth is narrower.
Sulfur burps are unpleasant and socially awkward. They are not, on their own, a sign of harm. When they arrive with watery diarrhea, fever or greasy stools, the culprit may be an unrelated infection rather than the medicine, and that combination belongs in the when-to-see-a-doctor list.
What changed recently and why these side effects are trending
Three developments, spaced over roughly two years, have pushed GLP-1 digestive side effects back into everyday conversation.

In September 2023, the FDA-approved labeling for Ozempic was updated to add ileus, a condition in which the bowel stops moving without a physical blockage, to the list of effects reported after the medicine reached the market. The MedlinePlus drug entry for semaglutide injection now reflects this, and it prompted a wave of headlines about “stomach paralysis” that still echoes in search results today.
In November 2023, tirzepatide, the medicine in Mounjaro, received FDA approval for weight management under the brand name Zepbound. That put a second injectable in wide use, and with it a second round of questions: is Mounjaro constipation better or worse than Ozempic constipation? A dedicated section below takes that on.
In late 2025, the FDA approved an oral tablet form of semaglutide for chronic weight management, the first pill in this class for that purpose. The trials supporting it reported a digestive side-effect profile that looked much like the injections: nausea, constipation, diarrhea and vomiting led the list. Because a pill lowers the psychological barrier to starting, a fresh cohort of first-time users is now meeting these side effects for the first time, and many are documenting them online.
Layered over all of this is the social-media effect. Short videos about sulfur burps, “Ozempic breath” and bathroom emergencies travel fast because they are relatable and slightly embarrassing. The Mayo Clinic and Cleveland Clinic patient pages on GLP-1 agonists have both expanded their side-effect guidance in this period, which is a reasonable signal that clinicians are fielding the same questions the internet is.
None of this represents new danger. It represents more people, more forms of the medicine, and more honesty about what the first months feel like.
What the evidence actually says, and how strong it is
Not every claim about GLP-1 side effects rests on the same foundation. Here is a frank grading.
How common the side effects are: strong evidence. The frequencies come from large randomized, placebo-controlled trials involving thousands of participants followed for one to two years. Randomization means the placebo group tells us how much nausea or constipation would have happened anyway. This is the highest tier of evidence, and the numbers in this article’s table are drawn from it.
Why they happen: moderate evidence. The gastric-emptying mechanism is supported by small physiological studies using breath tests and imaging, plus animal work on brainstem GLP-1 receptors. These studies are consistent with one another but involve dozens of people, not thousands. The claim that emptying delay fades over months for solid food rests on a handful of such studies.
Whether side effects predict weight loss: moderate evidence. Secondary analyses of the semaglutide weight trials found that participants who never had nausea or vomiting lost roughly as much weight as those who did. This undercuts the popular idea that feeling sick means the medicine is “working.” It is a post hoc analysis, so it is suggestive rather than definitive.
What helps constipation: indirect evidence. No large trial has tested fiber, fluids or specific laxative types specifically in people on GLP-1 medicines. The recommendations borrow from decades of general constipation research, where osmotic laxatives and soluble fiber have randomized-trial support. Borrowing is reasonable, but it is borrowing.
Bowel obstruction risk: observational evidence. The signal comes from post-marketing reports and database studies comparing users of GLP-1 medicines with users of other weight-loss drugs. These cannot prove cause, and absolute numbers are small.
Sulfur burp remedies: expert opinion and anecdote. Food swaps make mechanistic sense. Nobody has run a trial.
How common are nausea, constipation and burping? The trial numbers side by side
Rates differ depending on which medicine, which strength range and which population was studied. People with type 2 diabetes in the Ozempic trials generally used lower strengths than people in the weight-management trials, and their side-effect rates were correspondingly lower. The table pulls the headline figures together; all are approximate ranges across pivotal trials, rounded to the nearest whole number.
| Side effect | Semaglutide, type 2 diabetes trials | Semaglutide, weight-management trial | Tirzepatide, weight-management trial | Placebo (weight trials) |
|---|---|---|---|---|
| Nausea | 16–20% | 44% | 25–31% | 9–17% |
| Constipation | 3–5% | 24% | 11–17% | 6–11% |
| Diarrhea | 8–9% | 30% | 19–23% | 7–16% |
| Vomiting | 5–9% | 24% | 8–12% | 2–7% |
| Belching (eructation) | Not commonly reported | 7% | Not separately reported | 1% |
| Fatigue | Not commonly reported | 11% | Not separately reported | 5% |
Two things stand out. First, constipation and diarrhea can both happen on the same medicine, sometimes in the same person at different points, because slowed transit and altered gut signaling can push the bowel either way. Second, the placebo columns are not zero. A quarter of people on placebo in a weight-management trial reported some digestive complaint, a reminder that changing how you eat, all by itself, changes how your gut behaves.
The other consistent finding across every trial is timing. Most first episodes occur in the opening weeks and around each step to a higher strength. Discontinuation because of digestive effects ran in the low single digits to roughly 4 percent, meaning the large majority of people who experienced these symptoms found them tolerable enough to continue.
How often should I poop on Ozempic?
There is no single correct number, on the medicine or off it. The range clinicians treat as normal runs from three bowel movements a day to three a week. Someone who went daily before starting and now goes every other day has changed but may not be constipated. Someone who went twice daily and now goes twice a week almost certainly is.
Doctors define constipation less by frequency than by a cluster of features: fewer than three movements a week, stools that are hard or lumpy, straining, a sense of incomplete emptying, or needing to press on the abdomen to finish. If two or more of those describe most of your bathroom visits over several weeks, the label fits regardless of your count.
The more useful question is how far you have drifted from your own baseline. Keeping a simple note for the first two months, a tally mark and a word about consistency, sounds tedious and pays off in a clinic visit. “I used to go every morning and now it’s every third day and it hurts” is information a prescriber can act on. “I think I’m constipated” is not.
People eating far less will also produce less stool, and less stool can mean less frequent, entirely comfortable movements. That is not constipation. Discomfort, hardness and effort are what matter. The Bristol stool chart, a seven-type visual scale used by gastroenterologists, puts types 1 and 2 (separate hard lumps, or a lumpy sausage shape) in constipated territory and types 3 and 4 in the comfortable zone. Many people find it easier to report a Bristol number than to describe the details out loud.
A sustained pattern of several days without a movement, especially with bloating, cramping or nausea that is getting worse rather than better, moves this from a lifestyle question to a medical one. The red-flag list near the end of the article spells out the thresholds.
What genuinely helps ozempic constipation, ranked by evidence
Start with what has randomized-trial support in general constipation, then adapt it to the reality of a smaller appetite.
Fiber, raised gradually. Soluble fiber, the kind in oats, beans, lentils, chia, ground flaxseed, apples and pears, absorbs water and forms a gel that keeps stool soft. It has the best trial record for chronic constipation. Insoluble fiber, found in wheat bran, vegetable skins and nuts, adds bulk. Most adults fall well short of the roughly 25 to 30 grams a day dietary guidelines recommend, and on a GLP-1 medicine intake often halves again. The catch: jumping fiber intake overnight produces gas and bloating in a stomach that is already slow. Increase over two or three weeks.
Fluids, deliberately. Fiber without water can make stool worse, not better. A full stomach mutes thirst, so fluid needs scheduling rather than instinct: a glass on waking, one with each small meal, one mid-afternoon. Warm liquids in the morning stimulate the colon’s natural wake-up contraction in some people.
Movement. Walking after meals improves colonic motility in studies of older adults and people with sedentary jobs. Twenty minutes is enough to count. It also counters the fatigue that keeps people on the couch.
Toilet timing and posture. The colon is most active in the half hour after breakfast. Sitting then, unhurried, with feet raised on a low stool so knees sit above hips, straightens the angle of the rectum and reduces straining. This costs nothing and is underused.
Meal structure. Skipping meals entirely, which is tempting when appetite vanishes, removes the gastrocolic reflex that food triggers. Several small meals keep that reflex firing.
What has weak or no evidence: detox teas, “gut cleanse” supplements, large probiotic doses aimed at constipation, and any product marketed specifically as an Ozempic fix. If two or three weeks of the measures above have not helped, the next step is a conversation with your prescriber, not a bigger fiber tub.
What is the best laxative to use when taking Ozempic?
There is no laxative tested specifically in people on GLP-1 medicines, so the honest answer draws on general constipation research and on the way these medicines behave. The choice, and the go-ahead to use one at all, belongs to your prescriber or pharmacist, who know your other medicines and your history. What follows is a map of the categories, not a recommendation.
Bulk-forming agents such as psyllium work like dietary fiber: they hold water and soften stool. They are gentle and suitable for longer use in general populations, but they require generous fluid intake to work, and in a stomach that empties slowly they can add to bloating. People who already struggle to drink enough may find them counterproductive.
Osmotic laxatives, including polyethylene glycol and certain magnesium-based products, pull water into the bowel and hold it there. This category has the strongest randomized-trial evidence for chronic constipation and tends to be the first thing gastroenterologists reach for. Because osmotics do not depend on stimulating the bowel wall, they suit a gut that is sluggish rather than spasming. Magnesium-based products can be a concern for people with kidney problems, another reason the decision needs a clinician.
Stool softeners such as docusate have surprisingly thin evidence; several reviews found them no better than placebo for chronic constipation.
Stimulant laxatives, including senna and bisacodyl, trigger bowel-wall contractions. They work quickly and are appropriate for short-term use, but the cramping they cause can be pronounced in someone whose bowel is already tender from slowed transit.
Three cautions apply across all categories. Do not use any laxative to push through severe abdominal pain, vomiting or a swollen, firm belly; those need evaluation first, because laxatives are the wrong tool for a possible blockage. Do not use one daily for weeks without telling the prescriber. And never adjust or pause the GLP-1 medicine on your own because of constipation; that conversation belongs with the clinician who prescribed it.
Why can't you eat eggs on Ozempic? Eating to calm nausea and sulfur burps
You can eat eggs on Ozempic. No prescribing information, guideline or trial restricts them. The claim grew from a real observation, sulfur burps are worse for some people after sulfur-rich foods, and eggs are among the richest common sources of cysteine and methionine. If your burps smell like eggs and you ate eggs, the connection is not imaginary. It is also not universal, and it is not a ban.
A more useful frame is an experiment. Pull the highest-sulfur foods (eggs, red meat, whey protein, garlic, onion, cruciferous vegetables) for five days and see whether the belching changes. If it does, reintroduce them one at a time, in smaller portions, spread across the day rather than in a single large meal. Many people find the culprit is the quantity eaten at once rather than the food itself, which fits the mechanism: a big protein load sitting in a slow stomach ferments more than a modest one.
For nausea, the evidence-informed pattern is consistent across GLP-1 patient guidance from major medical centers:
- Smaller meals more often, stopping at the first hint of fullness rather than at a clean plate.
- Lower-fat choices; fat is the macronutrient that most slows stomach emptying on its own, and the medicine adds to it.
- Cold or room-temperature foods, which give off less aroma than hot ones.
- Bland, dry carbohydrates in the morning: toast, crackers, plain rice.
- Staying upright for an hour after eating.
- Ginger in tea or as candied pieces; randomized trials in pregnancy and chemotherapy nausea show modest benefit, though no trial has tested it for GLP-1 nausea.
- Going easy on alcohol, which irritates the stomach lining and slows emptying further.
Protein still matters. People losing weight quickly lose muscle along with fat, and adequate protein blunts that loss. The goal is not to abandon eggs or meat but to portion them so a slow stomach can keep pace.
Mounjaro constipation: is tirzepatide any easier on the gut?
Tirzepatide, sold as Mounjaro for type 2 diabetes and Zepbound for weight management, works on two hormone receptors rather than one. Alongside GLP-1, it mimics GIP, glucose-dependent insulinotropic polypeptide, another gut hormone released after meals that influences insulin and fat metabolism. Whether that second action changes the digestive experience is a fair question, and the data allow a partial answer.
In the pivotal weight-management trial of tirzepatide, constipation was reported by roughly 11 to 17 percent of participants across strengths, versus about 6 percent on placebo. Nausea ran 25 to 31 percent versus 9 percent, diarrhea 19 to 23 percent versus 7 percent, and vomiting 8 to 12 percent versus 2 percent. Set beside the semaglutide weight trial figures in the table above, those rates look a little lower. The comparison is imperfect: different trials, different participants, different years.
A head-to-head randomized trial published in 2025 directly compared tirzepatide with semaglutide for weight management. Gastrointestinal side effects were the most common complaints in both groups and were broadly similar in frequency and severity, with most rated mild or moderate. That is the best evidence available, and it suggests the two medicines are more alike than different where the gut is concerned. Mounjaro constipation is real, follows the same slowed-transit logic, and responds to the same measures.
Individual variation swamps the average difference. Some people tolerate one medicine noticeably better than the other for reasons nobody can predict in advance. Switching between them is a legitimate clinical option in some circumstances, but it is a prescriber’s call based on diabetes control, weight goals, insurance realities and the full side-effect picture, not a self-directed swap because a forum post said one was gentler.
One more distinction matters for expectations. Because tirzepatide’s approval for weight management came later, real-world experience with it is shorter. The trial numbers are solid; the long tail of everyday reports is still being written.
Ozempic fatigue and Ozempic breath: are they connected to the gut effects?
Both show up constantly in search data, and both are more indirect than they seem.
Ozempic fatigue. Fatigue was reported by about 11 percent of participants in the semaglutide weight-management trial versus 5 percent on placebo, so the medicine does appear to contribute. The likeliest routes run through eating rather than through any direct sedative effect. A sharp drop in calories, particularly in the first weeks, leaves less fuel for the day. Mild dehydration from drinking less amplifies tiredness. People with type 2 diabetes whose blood sugar falls quickly from a high baseline sometimes feel drained while their body recalibrates. And constipation itself, with its bloating and low-grade discomfort, disturbs sleep. In most reports the fatigue eases over the first couple of months as intake stabilizes. Persistent, worsening exhaustion, or fatigue with dizziness, shakiness or confusion, is a reason to call the prescriber, because low blood sugar is possible in people who also take insulin or certain other diabetes medicines.
Ozempic breath. Bad breath is not listed as a side effect in the prescribing information, but the mechanism behind the complaints is plausible. Dry mouth from lower fluid intake reduces the saliva that normally rinses odor-causing bacteria from the tongue and gums. Eating far fewer carbohydrates pushes the body to burn fat for fuel, producing ketones, one of which, acetone, is exhaled and smells faintly of nail-polish remover; this is the same “keto breath” people notice on very low-carbohydrate diets. Reflux and sulfur burps add their own contribution from below.
What helps is unglamorous: scheduled fluids, brushing the tongue as well as the teeth, sugar-free gum to stimulate saliva, and not skipping meals entirely. Sudden fruity breath together with nausea, vomiting and extreme thirst in a person with diabetes is a different matter entirely and needs urgent care; it can signal diabetic ketoacidosis, a dangerous buildup of ketones.
Can Ozempic cause bowel blockage? Ileus, obstruction and the real numbers
This is the question behind the most frightening headlines, so precision matters.
Ileus is a condition in which the intestine stops contracting and moving contents along, even though nothing is physically blocking it. The bowel effectively goes quiet. Symptoms include a swollen, tight abdomen, cramping, nausea, vomiting and an inability to pass stool or gas. In 2023, ileus was added to the postmarketing section of the Ozempic labeling, meaning enough reports had accumulated after approval to warrant listing, though the frequency could not be calculated because the total number of users is unknown.
Mechanical bowel obstruction, a physical blockage from hardened stool, scar tissue or a twist, is a separate entity. Severe, prolonged constipation can occasionally progress to a stool impaction that behaves like an obstruction.
How common is any of this? A 2023 observational study using insurance-claims data compared people prescribed GLP-1 medicines for weight loss with people prescribed a different weight-loss drug combination. It found a higher rate of bowel obstruction in the GLP-1 group, along with higher rates of pancreatitis and gastroparesis. The absolute numbers were small, a handful of cases per thousand people per year, and the study design cannot prove the medicine caused them. The randomized trials, which involved thousands of participants, did not identify obstruction as a common event. Taken together, the evidence supports “rare but real” rather than either “never” or “likely.”
Some people carry more baseline risk: those with previous abdominal surgery, a history of bowel obstruction, chronic opioid use (opioids independently slow the bowel), significant prior constipation, or conditions such as gastroparesis or inflammatory bowel disease. These are worth raising with the prescriber before starting, not after.
The practical takeaway is not to fear the medicine but to respect a specific pattern: several days without a bowel movement plus a belly that is visibly swollen, firm or increasingly painful, plus vomiting. That combination is not something to treat with a laxative at home. It is a same-day medical evaluation.
Common myths about GLP-1 side effects, corrected
The viral claims deserve individual answers rather than a general shrug.
“If you feel sick, the medicine is working.” Secondary analyses of the semaglutide weight trials found that people who reported no nausea or vomiting lost roughly the same amount of weight as those who did. Side effects are a sign the medicine is in your system, not a measure of its effectiveness. Feeling fine is not a failure.
“You can’t eat eggs on Ozempic.” There is no such rule. Eggs are high in sulfur-containing amino acids and can worsen sulfur burps in some people. Portion and timing usually matter more than elimination.
“Constipation means your bowel is paralyzed.” Ordinary constipation from slowed transit affects roughly a quarter of people in the weight-management trials. Ileus, the true loss of bowel movement, is rare and comes with a distinctive picture of swelling, vomiting and inability to pass gas. The two are not on a continuum where one inevitably becomes the other.
“Sulfur burps mean your gut is toxic and needs a cleanse.” Hydrogen sulfide is a normal bacterial byproduct that becomes more noticeable when food sits longer. Cleanses and detox products have no trial evidence and some carry their own laxative ingredients that can make matters worse.
“Just eat more fiber and it’ll fix itself.” Fiber helps, and it helps most when raised gradually and matched with fluid. Dumping a large amount into a slow stomach produces gas and bloating and sends people running from the one strategy that would have worked with patience.
“Skip a week if you’re constipated; it resets you.” Pausing or adjusting the medicine changes blood sugar control in people with diabetes and undoes the gradual adaptation that lets the gut tolerate it. Any change in timing or strength belongs to the prescribing clinician.
“The pill version has no stomach side effects.” The trials of oral semaglutide reported the same leading complaints as the injections. Route changes convenience, not physiology.
When to see a doctor about nausea, constipation or burping on a GLP-1
Most digestive effects of these medicines are a nuisance, not an emergency, and they improve with time and the measures above. A minority are signals that something else is going on. Knowing the line between the two is the single most useful thing a person on a GLP-1 can carry around.
Seek same-day or emergency care for:
- Severe abdominal pain, especially pain that is constant, worsening, or radiates to the back, which can indicate pancreatitis, inflammation of the pancreas.
- A visibly swollen, firm belly with cramping, vomiting and no passage of stool or gas, the picture of ileus or obstruction.
- Repeated vomiting over more than a day, inability to keep fluids down, or signs of dehydration such as dizziness on standing, very dark urine or confusion.
- Pain in the upper right abdomen with fever, yellowing of the skin or eyes, or pale stools, which can point to gallbladder disease, a known association with rapid weight loss.
- Fruity-smelling breath with nausea, vomiting and extreme thirst in someone with diabetes, a possible sign of ketoacidosis.
- Black, tarry stools or blood in vomit.
Book a routine appointment for:
- No bowel movement for four or more days despite fiber, fluids and movement.
- Constipation that has lasted more than three weeks, or that needs a laxative more than occasionally.
- Nausea that has not eased eight weeks after starting or after the last strength increase, or that is causing you to skip meals repeatedly.
- Unintended weight loss faster than your clinician expected, or ongoing fatigue that interferes with daily life.
- Sulfur burps together with diarrhea, fever or greasy stools lasting more than a few days, which may indicate an unrelated gut infection.
- Any new medicine, including over-the-counter laxatives or supplements, you are considering adding.
Bring your bowel-habit notes, a list of everything you take, and a clear description of when the symptoms started relative to your last strength change. Every decision about continuing, adjusting or pausing the medicine belongs with the clinician who prescribed it. Side effects are information for that conversation, not a reason to make changes alone.
Frequently asked questions
What is the best laxative to use when taking Ozempic?
No laxative has been tested specifically in people on GLP-1 medicines, so the choice should be made with your prescriber or pharmacist. In general constipation research, osmotic laxatives such as polyethylene glycol have the strongest randomized-trial evidence and suit a sluggish rather than spasming bowel. Bulk-forming fiber products need plenty of fluid, stool softeners have weak evidence, and stimulant laxatives are for short-term use. Never use a laxative to push through severe pain or a swollen abdomen.
Why can't you eat eggs on Ozempic?
You can. There is no medical restriction on eggs with semaglutide. The idea spread because eggs are rich in sulfur-containing amino acids, and when a slowed stomach lets protein sit longer, gut bacteria convert those compounds into hydrogen sulfide, the gas behind sulfur burps. Some people notice worse belching after eggs; many do not. Smaller portions spread across the day usually matter more than cutting the food out entirely.
How often should I poop on Ozempic?
Anywhere from three times a day to three times a week is considered normal, and eating less will naturally produce less stool. What matters is the change from your own baseline and whether stools are hard, painful or feel incomplete. Fewer than three comfortable movements a week, or a stretch of four or more days without one despite fiber, fluids and movement, is a reason to contact your prescriber.
Can Ozempic cause bowel blockage?
Rarely. Ileus, where the bowel stops moving without a physical block, was added to Ozempic’s labeling in 2023 from postmarketing reports. A 2023 observational study found a higher rate of bowel obstruction in GLP-1 users than in users of another weight-loss drug, but absolute numbers were small and the design cannot prove cause. Severe constipation with a swollen, firm belly, vomiting and no passage of gas needs same-day medical evaluation.
How long do sulfur burps on Ozempic last?
For most people they are worst in the first weeks after starting or after a strength increase and fade as the gut adapts, typically over several weeks. Trials recorded belching in about 7 percent of participants over more than a year. Reducing large servings of high-sulfur foods such as eggs, red meat, whey protein, garlic and cruciferous vegetables, and eating smaller meals, usually shortens the run. Burps with fever or watery diarrhea should be checked for an unrelated infection.
When does Ozempic nausea go away?
In the large trials, nausea usually appeared within the first few weeks and around each step to a higher strength, then eased over the following weeks as the stomach adapted. About four in ten people on the weight-management strength reported it at some point, most as mild or moderate. Nausea that persists more than about eight weeks after the last change, or that causes repeated skipped meals or vomiting, should be reviewed by the prescriber.
Is Mounjaro constipation better or worse than Ozempic constipation?
Broadly similar. Tirzepatide’s weight-management trial reported constipation in roughly 11 to 17 percent of participants, and a 2025 head-to-head randomized trial comparing tirzepatide with semaglutide found gastrointestinal side effects comparable in frequency and severity. Individual responses vary more than the averages do. Switching between the two is a clinical decision for the prescriber, not something to do on the strength of an online comparison.
Why does Ozempic make me so tired?
Fatigue was reported by about 11 percent of people on semaglutide in the weight-management trial versus 5 percent on placebo. The likely drivers are indirect: a steep drop in calories, mild dehydration from drinking less, rapidly falling blood sugar in people who started high, and disturbed sleep from bloating. It usually improves within a couple of months. Fatigue with shakiness, dizziness or confusion needs prompt attention, particularly if you also take insulin or other diabetes medicines.
What causes Ozempic breath and what helps?
Bad breath is not a listed side effect, but three mechanisms explain the complaints: dry mouth from lower fluid intake, acetone from burning fat for fuel on a much lower carbohydrate intake, and reflux or sulfur burps rising from a slow stomach. Scheduled fluids, brushing the tongue, sugar-free gum and not skipping meals help most people. Fruity breath with vomiting and extreme thirst in someone with diabetes is a warning sign of ketoacidosis and needs urgent care.
Should I stop Ozempic if I get constipated?
Not on your own. Constipation affected about a quarter of people in the weight-management trial, and the large majority managed it with gradual fiber increases, scheduled fluids, walking and toilet timing, sometimes with a clinician-approved laxative. Pausing or adjusting the medicine changes blood sugar control and undoes the gradual adaptation that helps the gut tolerate it. Bring your symptoms to the prescriber; the decision about continuing, adjusting or stopping belongs with them.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Muscle Loss on GLP-1 Medicines: How Much Is Lean Mass and How to Protect It
On GLP-1 medicines such as semaglutide and tirzepatide, roughly 25 to 40 percent of the weight lost in trial body-composition substudies was lean mass,…

Hair Loss on Ozempic or Mounjaro: Telogen Effluvium, Timing and Recovery
Hair loss on Ozempic or Mounjaro is usually telogen effluvium, a temporary shedding that begins two to four months after rapid weight loss or…

Ozempic and Alcohol: What Is Known About Drinking on GLP-1 Medicines
Drinking alcohol while taking Ozempic (semaglutide) is not prohibited by its prescribing information, but the combination can raise the risk of low blood sugar,…
Ozempic and Thyroid Cancer: What the Boxed Warning Says and What Human Data Show
Ozempic (semaglutide) carries a US boxed warning because it caused thyroid C-cell tumors in rats and mice; whether that applies to people is unknown.…

Loose Skin After GLP-1 Weight Loss: “Ozempic Butt”, Arms and Abdomen: When Surgery Is Considered
"Ozempic butt" is the informal name for a flatter, softer or looser-looking backside after substantial weight loss on GLP-1 medicines such as semaglutide or…

How Does Ozempic Work? The Science of GLP-1 Explained Without the Hype
Ozempic (semaglutide) works by mimicking GLP-1, a gut hormone released after meals. It prompts the pancreas to release insulin only when blood sugar is…