

Preparing for Vaginoplasty: The Pelvic Exam, Blood Work and Habits to Pause Beforehand

Key Takeaways
- Hair removal in the donor skin must be done before surgery because follicles inside the new canal cannot easily be treated afterward, and because hair growth cycles mean the process takes months, not weeks.
- Nicotine from any source, including vaping and pouches, narrows the small blood vessels that keep skin flaps alive, which is why surgeons require abstinence and often verify it with a metabolite test.
- Preoperative blood work typically includes a blood count, kidney and liver measures, glucose or hemoglobin A1c, and clotting studies when indicated, each chosen to predict anesthesia safety and wound healing.
- Aspirin inhibits platelets for their roughly seven-to-ten-day lifespan, while several supplements such as fish oil, ginkgo and vitamin E also affect clotting, so all of them belong on the list your anesthesiologist reviews.
- Whether estrogen is paused before vaginoplasty varies between programs; observational evidence on continuing it with clot prevention is reassuring but not conclusive, so the protocol is a surgeon-level decision.
- Dilation begins within days of surgery and is performed several times daily in the early months because the skin lining the canal contracts if it is not stretched regularly.
Preparing for vaginoplasty usually involves a pelvic and genital examination, routine blood tests such as a blood count, kidney and liver measures, blood sugar and clotting checks, and a review of every medicine and supplement you take. Most programs ask patients to stop smoking and nicotine well beforehand, limit alcohol, complete genital hair removal and arrange recovery help. Your surgical team sets the exact requirements.
The folder on the kitchen table is already thick: a consultation summary, a lab requisition, a leaflet about hair removal, and a page of instructions that begins with the words “six weeks before.” For many people, the surgery date itself feels less daunting than the long runway leading up to it. Preparing well is where the quiet work happens, and it is also where small decisions can shape how smoothly the weeks after surgery unfold.
This article explains how to prepare for vaginoplasty in plain language: what the pelvic exam looks for, what the blood work measures and why, and which habits surgeons routinely ask patients to pause. The emphasis is on mechanisms, so that each instruction makes sense rather than feeling arbitrary.
None of this replaces your own team’s checklist. Programs differ, and your surgeon and anesthesiologist will tailor the plan to your health history. Think of what follows as the explanation behind the list, not a substitute for it.
How to prepare for vaginoplasty starts with knowing what the surgery does
Vaginoplasty is an operation that constructs or reconstructs a vagina and, in most gender-affirming cases, a vulva (the external genitals: labia and clitoris). The most common technique uses penile and scrotal skin to line a new canal placed between the bladder and the rectum, with sensitive tissue from the glans preserved to form a clitoris. The urethra (the tube that carries urine) is shortened and repositioned, according to descriptions from the Mayo Clinic and Cleveland Clinic.
Other techniques exist. When there is not enough genital skin, surgeons may use a section of bowel or a skin graft from elsewhere on the body. Some people choose a shallow-depth, or “zero-depth,” version that creates the external anatomy without a canal, which removes the need for lifelong dilation.
Why does this matter for preparation? Because each element of the plan maps onto a surgical reason. Hair removal is needed because skin that lines the new canal would otherwise grow hair internally. Bowel preparation is requested because the rectum sits a few millimeters behind the dissection plane. Smoking cessation matters because the skin flaps depend on small blood vessels that nicotine narrows.
Surgery itself usually takes several hours under general anesthesia, and the Mayo Clinic notes that patients typically remain in the hospital for a few days afterward. A urinary catheter (a soft tube draining the bladder) and packing inside the new canal stay in place for the first stretch of recovery.
Understanding the anatomy also helps you ask sharper questions. If you know the canal is lined with skin, you will understand why the surgeon asks about scars, prior circumcision, or skin conditions in the genital area during the exam described below.
Who vaginoplasty is usually for, and who is usually asked to wait
Most people seeking vaginoplasty are transgender women or nonbinary people with persistent gender dysphoria, the distress that can arise when gender identity and body do not align. A smaller group includes people born with differences of sex development, people with vaginal agenesis (a vagina that did not form before birth), and those needing reconstruction after cancer treatment or injury.

For gender-affirming surgery, programs generally follow guideline-based pathways. The NHS describes assessment by specialist gender services before surgical referral, and the Mayo Clinic lists common criteria: a documented, persistent diagnosis, the capacity to make an informed decision, being of legal age, and reasonable control of any significant medical or mental health conditions. Many surgeons also ask for a period of hormone therapy beforehand unless there is a medical reason not to, though this is a program decision rather than a universal rule.
Being asked to wait is not a refusal. Teams commonly postpone surgery when:
- Blood sugar is poorly controlled, because high glucose slows wound healing and raises infection risk.
- Nicotine use continues, for the blood-flow reasons explained later.
- An active infection, untreated bleeding disorder, or recent blood clot is present.
- Hair removal in the donor skin is incomplete.
- A support plan for the recovery weeks, including help at home, is not yet in place.
Body weight is sometimes discussed. Some surgeons set thresholds because deeper pelvic anatomy can make the dissection technically harder and because anesthesia risk rises with certain conditions linked to higher weight. The evidence on fixed cutoffs is mixed, and approaches differ between teams. A respectful conversation about what is realistic for your body, and whether the threshold is flexible, is a fair thing to ask for.
What does the pelvic exam before vaginoplasty involve?
The pelvic exam before vaginoplasty is a planning exam rather than a screening exam. The surgeon is mapping the tissue they will work with, and the whole process usually takes only a few minutes.
For gender-affirming surgery on someone with penile and scrotal anatomy, the surgeon looks at several things. The amount and elasticity of penile skin, because it lines most of the canal. The size of the scrotum, because scrotal skin is often used for the labia majora and sometimes as a graft to extend canal depth. Whether circumcision was performed, since that reduces available skin. The pattern of hair growth and how much electrolysis or laser treatment has already been completed. Scars from hernia repair or other procedures, which can change the blood supply.
A digital rectal exam (a gloved, lubricated finger in the rectum) is sometimes included to assess the prostate and the tissue plane where the canal will sit. It can feel awkward, and you are entitled to ask the surgeon to explain each step before it happens, to have a chaperone present, or to pause.
For people with vaginal agenesis or reconstruction needs, the exam assesses the existing vestibule, any dimple or short canal, the pelvic floor muscles, and the perineum (the area between the vaginal opening and the anus). Imaging is sometimes added to understand internal anatomy.
The exam also screens for anything that should be treated first: fungal infection in skin folds, dermatitis, or warts, each of which can complicate healing. You may be asked about urinary symptoms, bowel habits, and sexual function, because baseline information helps the team interpret recovery later.
If exams of this kind carry trauma for you, say so in advance. Many programs can adapt pace, positioning and who is in the room.
Which blood tests are done before vaginoplasty, and why
Preoperative blood work is about safety under anesthesia and healing afterward. Johns Hopkins Medicine describes the general purpose: finding problems that could cause complications before, during or after surgery so they can be treated or planned around. The exact panel differs between programs, but several tests appear almost everywhere.
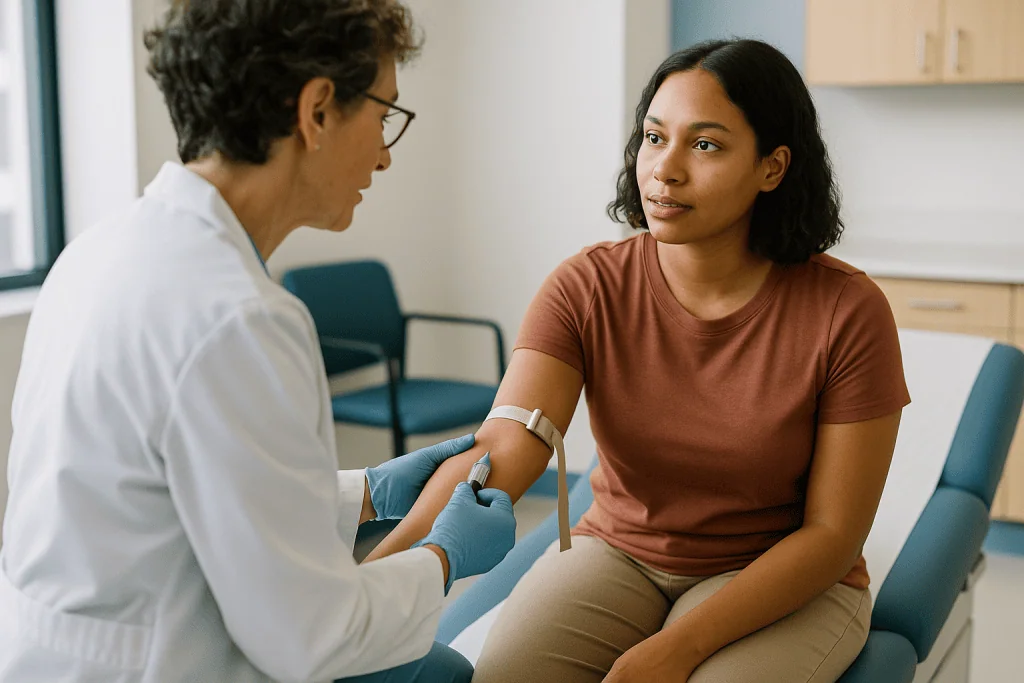
A complete blood count measures red cells, white cells and platelets. Low hemoglobin (anemia) means less oxygen reaches healing tissue and leaves less reserve if bleeding occurs. An unexpectedly high white count can point to an infection worth treating first.
A metabolic panel checks kidney function, electrolytes and liver enzymes. Kidneys clear many anesthetic and pain medicines, and the anesthesiologist adjusts choices accordingly. Liver results matter for the same reason and because estrogen is processed by the liver.
Glucose and hemoglobin A1c (a measure of average blood sugar over roughly three months) help identify undiagnosed or poorly controlled diabetes. High glucose impairs the white cells that fight bacteria and slows collagen formation, so wounds close more slowly.
Clotting studies are ordered when there is a personal or family history of bleeding or clots, or when medicines affecting clotting are in use. Some teams screen for inherited clotting tendencies in anyone on estrogen.
Programs commonly add screening for HIV, hepatitis B and C, and sometimes syphilis, because results change infection-control planning and, for hepatitis, liver assessment. A urine test and, in some centers, a nicotine metabolite test are also used.
Hormone levels are often checked, particularly estradiol and testosterone, to confirm a stable baseline. Expect an electrocardiogram (a tracing of heart rhythm) if you are over a certain age or have cardiac risk factors; that threshold is set by the anesthesia team, not by a fixed rule in this article.
Vaginoplasty pre op requirements: the consultations beyond the surgeon
The surgeon is one voice in a larger team. Most programs require or strongly recommend several other appointments, and the sequence usually spans months rather than weeks.
An anesthesiology assessment reviews airway, heart and lung health, sleep apnea, prior reactions to anesthesia and every medicine you take. A primary care or internal medicine review may be requested to optimize blood pressure, blood sugar or thyroid function. Mental health letters, where the pathway requires them, are typically prepared earlier in the process. Pelvic floor physical therapy before surgery is increasingly common; a therapist teaches relaxation and coordination of the muscles that will surround the new canal, which can make early dilation less uncomfortable.
Fertility counseling belongs here too. Vaginoplasty involves removal of the testes in most gender-affirming techniques, which permanently ends sperm production. The Mayo Clinic notes that sperm banking is an option to discuss beforehand if future biological children are a possibility.
| Typical window | What usually happens | Why it matters |
|---|---|---|
| Months ahead | Hair removal sessions; mental health documentation; fertility decisions | Hair removal needs repeated cycles; sperm banking cannot be done after surgery |
| Several weeks ahead | Stop smoking and nicotine; blood tests; anesthesia visit; arrange help at home | Blood flow and oxygen delivery recover over weeks; results allow time to correct problems |
| Final days | Medication adjustments as directed; bowel preparation if requested; fasting instructions | Reduces bleeding, contamination and anesthesia risks |
Windows in this table describe common practice reported by the Mayo Clinic, Cleveland Clinic and MedlinePlus, not promises. Your program’s calendar may be longer or shorter, and it takes precedence.
Why hair removal before vaginoplasty starts months ahead
Of all the preparation steps, hair removal before vaginoplasty is the one that most often delays a surgery date, because it cannot be rushed.
The reason is anatomical. Skin that will line the inside of the canal, usually from the penile shaft and sometimes the scrotum or perineum, keeps its hair follicles after surgery. Hair growing inside a canal that is not easily cleaned can trap discharge, form small balls of matted hair and contribute to odor or irritation. Once the skin is inside, removing follicles becomes far harder. The Cleveland Clinic lists permanent hair removal of the genital skin among standard pre-surgical steps.
Two methods are used. Electrolysis destroys follicles one at a time with a fine probe and an electric current; it works on all hair colors but is slow. Laser hair removal targets pigment in the hair shaft, so it works best on dark hair against lighter skin and is less effective on light, gray or red hair. Hair grows in cycles, and a follicle can only be destroyed during its active phase, which is why multiple sessions spaced weeks apart are needed and why providers commonly describe the process as taking months.
Your surgeon will mark or describe the exact area to clear, and it varies with technique. Clearing the wrong region wastes sessions, so get the map first.
Shaving or waxing in the days before surgery is not a substitute, and some surgeons ask you not to shave the area at all in the final week to avoid tiny skin nicks that can harbor bacteria. If complete removal is not achievable in time, surgeons can scrape follicles from the inner surface of the skin during the operation, though this is less thorough. Discuss the trade-off openly rather than hoping it will not come up.
Should I stop smoking before vaginoplasty? What nicotine does to healing
Yes, and nearly every surgical program makes it a condition. The question people really want answered is why the rule is so firm.
Nicotine constricts small arteries. The skin flaps used in vaginoplasty survive on a fragile network of tiny vessels at their edges, and when those vessels narrow, the flap tip may not receive enough oxygen. The result can be partial skin loss, delayed healing or breakdown of the suture lines. Carbon monoxide from smoke adds a second insult by binding to hemoglobin and reducing how much oxygen the blood can carry at all. MedlinePlus summarizes the surgical consequences: smokers have more wound infections, slower healing, more breathing complications under anesthesia and a higher chance of blood clots.
Timing matters. MedlinePlus advises stopping as early as possible before any operation, noting that quitting even a short time beforehand helps the heart and lungs, while the full benefit to wound healing accumulates over several weeks. Many surgeons set their own minimum and verify it with a urine or blood nicotine metabolite test; a positive result can lead to postponement.
Vaping, nicotine pouches, gum and patches all deliver nicotine, so they produce the same vessel-narrowing effect even without smoke. Whether nicotine replacement is acceptable close to surgery varies between surgeons and is a question for your team, not a decision to make alone.
Quitting is hard, and shame does not help. Behavioral support, quit lines and prescribed cessation medicines all have evidence behind them; the CDC and NHS both offer free support programs. If you are struggling, tell your surgical coordinator early. A delayed date is far better than a flap that fails, and most teams would rather help you succeed than discover the problem on the operating table.
Alcohol, cannabis and other habits worth pausing before surgery
Smoking gets the headlines, but several other habits affect anesthesia and healing in ways worth understanding.
Alcohol interacts with surgery on several fronts. Regular heavy drinking can impair the liver’s handling of anesthetic drugs, reduce platelet function and increase bleeding, and weaken immune response. Abrupt withdrawal in someone who drinks heavily every day can cause dangerous agitation, high blood pressure or seizures in the hospital, which is why anesthesiologists ask about intake honestly and without judgment. The Cleveland Clinic and NHS both advise limiting or avoiding alcohol in the period before surgery. If you drink daily, tell the team; a supervised plan is safer than stopping suddenly on your own.
Cannabis is often overlooked. Smoked cannabis irritates the airway in a similar way to tobacco and may increase coughing or airway reactivity during anesthesia. Regular use can also change how much sedative and pain medicine is needed. Edibles avoid the airway effect but still interact with anesthesia. Your anesthesiologist needs to know frequency and form.
Recreational stimulants raise heart rate and blood pressure and can interact unpredictably with anesthetic agents; most teams ask for abstinence for a defined window before surgery and will say what that window is.
Two quieter habits deserve mention. Poor sleep in the final weeks raises stress hormones that modestly impair immune function, so protecting rest is not indulgent. And tanning or intense sun exposure to the surgical area can inflame skin that is about to be operated on.
Caffeine is generally fine, though the team may ask you to taper if you drink a great deal, because withdrawal headaches can complicate the first postoperative days. Hydration, balanced meals and gentle regular movement in the weeks beforehand all support the body’s reserve for healing.
Supplements, painkillers and blood thinners: what to review with your team
The single most common preoperative mistake is assuming that something bought without a prescription cannot matter. It can.
Several supplements affect clotting. Fish oil, vitamin E, garlic extract, ginkgo, ginseng and high-dose turmeric are all reported to reduce platelet aggregation or interact with blood-thinning medicines, according to the NIH Office of Dietary Supplements. St. John’s wort changes how the liver processes many drugs, including some anesthetics. Because supplement labels are not held to the same standards as prescription medicines, actual content can vary, which makes effects less predictable. Most anesthesia teams ask patients to stop supplements in the weeks before surgery; the exact timing comes from them.
Over-the-counter painkillers deserve the same scrutiny. Aspirin permanently inhibits platelets for the life of the platelet, roughly a week to ten days, which is why it is usually paused well before elective surgery unless a cardiologist says otherwise. Nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen and naproxen block platelets reversibly for a shorter time. Acetaminophen does not affect platelets and is often the painkiller teams allow in the final days, but confirm this rather than assume.
Prescribed anticoagulants and antiplatelet medicines, used after clots, stents or for heart rhythm problems, require a coordinated plan between the surgeon and the prescribing physician. Stopping them unsupervised can cause a stroke or clot; continuing them unplanned can cause serious bleeding. The decision about whether to pause, bridge with a different agent or continue belongs to those clinicians together.
Bring an actual list, or the bottles themselves, to the anesthesia visit. Include vitamins, protein powders, herbal teas taken daily and any hormones obtained outside your regular prescriber. Nothing on that list will be judged; everything on it helps the team keep you safe.
Hormone therapy before vaginoplasty: what the evidence actually shows
Few topics generate more anxiety in online forums than whether estrogen must be stopped before vaginoplasty. The honest answer is that practice is changing and the evidence is mixed.
The concern is venous thromboembolism, a blood clot that forms in a deep vein (usually the leg) and can travel to the lungs. Estrogen increases the liver’s production of clotting factors, and major pelvic surgery independently raises clot risk through immobility, tissue injury and inflammation. Combining the two was historically assumed to multiply risk, and the Mayo Clinic notes that some surgeons ask patients to stop hormone therapy for a period before surgery.
What has shifted is the recognition that stopping estrogen carries its own costs: mood changes, hot flashes, fatigue and distress at a time when emotional reserve matters. Observational studies of gender-affirming surgery patients who continued estrogen have reported low clot rates when standard prevention measures are used, though these studies are small and not randomized, so they cannot prove equivalence. Route may matter too; transdermal estrogen (patches or gels, absorbed through skin) appears to have less effect on clotting factors than oral forms in studies of menopausal hormone therapy, a finding often extrapolated to this setting.
Given that uncertainty, programs land in different places. Some continue hormones throughout. Some pause for a defined window. Some switch route beforehand. All of them typically use mechanical and medicine-based clot prevention in hospital: compression stockings, calf pumps, early walking and often a short course of an injectable anticoagulant.
Do not change your hormone regimen on your own in either direction. Ask your surgeon what their protocol is, what reasoning sits behind it, and how they will support you if a pause is requested. Testosterone blockers such as spironolactone also need review, because that medicine affects potassium and blood pressure under anesthesia.
Weight, blood sugar and nutrition: how metabolic health shapes wound healing
Wounds heal with materials the body has on hand, so the weeks before surgery are a chance to stock the shelves.
Protein is the raw material for collagen, the scaffolding of new tissue, and for the immune cells that defend a fresh wound. Someone eating very little protein, whether from dieting, nausea or restricted appetite, heals more slowly. MedlinePlus patient guidance on recovering from surgery emphasizes adequate protein, fluids and overall calories. Vitamin C and zinc are both needed for collagen cross-linking, and a varied diet usually provides them; your team can advise if a deficiency is suspected on blood work rather than guessing with supplements, which, as noted earlier, carry their own interactions.
Blood sugar is the second pillar. Even in people without diabetes, stress hormones released by surgery push glucose upward. In people with diabetes, sustained high glucose stiffens the walls of small blood vessels, dulls white cell function and feeds bacteria. The hemoglobin A1c result from your preoperative labs tells the team how your average sugar has run over the preceding three months; if it is high, optimizing control with your usual prescriber before surgery is a recognized way to lower infection risk. Changes to diabetes medicines around surgery, especially insulin and the newer injectable GLP-1 class, which slows stomach emptying and affects fasting safety, are decisions for the anesthesia and prescribing teams.
Weight is a sensitive topic and deserves a careful framing. Higher body weight is associated with somewhat higher rates of wound complications and anesthesia challenges in surgery generally, which is why some surgeons set thresholds. Crash dieting in the final weeks, however, depletes protein and can leave you less prepared, not more. If weight comes up, the most useful conversation is about realistic, sustainable changes and whether the surgeon’s threshold has flexibility, rather than about rapid loss.
The final two weeks: bowel preparation, fasting and what to pack
The last stretch is where instructions become specific, and where following them precisely matters most.
Bowel preparation is requested by many vaginoplasty surgeons because the rectum lies directly behind the plane where the canal is created. An empty rectum reduces the consequences of an accidental injury and keeps the surgical field cleaner. Preparations range from a clear-liquid diet the day before to a laxative regimen or enema; your team specifies which, and this article deliberately gives no amounts or products. Expect to spend much of the day before surgery near a bathroom, and plan work and travel accordingly.
Fasting instructions come from anesthesiology. The reason is aspiration: under general anesthesia, the reflexes that keep stomach contents out of the lungs are suppressed, and a full stomach becomes dangerous. Typical instructions stop solid food the night before and allow clear fluids until a few hours before arrival, but the exact cutoffs are set by your team and may differ if you take medicines that slow stomach emptying. When in doubt, ask rather than estimate.
Skin preparation often includes antiseptic washes in the days before, with instructions not to shave the operative area yourself. Remove nail polish and jewelry as directed; some monitoring equipment reads through the fingertip.
Packing is practical rather than glamorous. Loose, soft clothing that will not press on the groin. Slip-on shoes, because bending will be awkward. A long phone charger. Lip balm and unscented moisturizer for dry hospital air. A list of your medicines and allergies. Your dilators if the program has already given them to you. Something absorbing to read or watch, because the first days involve a lot of lying still.
Arrange the person who will drive you home and stay for the first days now, not the night before.
How to prepare for vaginoplasty recovery: what to expect after vaginoplasty
Knowing what to expect after vaginoplasty makes the early days less alarming, and some of it should shape how you set up your home before you leave for the hospital.
In hospital, you will have a urinary catheter, packing or a soft mold inside the new canal, and a dressing over the vulva. The Mayo Clinic describes a hospital stay of a few days, during which the team manages pain, watches for bleeding and gets you walking to prevent clots. Swelling and bruising of the vulva are expected and can look dramatic; the final appearance is not visible for months.
Packing and catheter are usually removed before or shortly after discharge, and dilation begins. Dilation means inserting a smooth, graduated cylinder into the canal for a set period to keep the skin from contracting and the space from narrowing. The Cleveland Clinic describes dilating several times a day in the first months, then less often over time, with a lifelong maintenance schedule. Your team provides the exact routine.
At home, expect spotting, some yellowish discharge as internal sutures dissolve, and discomfort when sitting. A donut cushion, a squeeze bottle for rinsing after urination, and a supply of absorbent pads help. Stairs are manageable but tiring. Bowel movements may be uncomfortable at first, which is one reason teams emphasize fluids and fiber.
Activity returns in stages. Walking is encouraged from the start. Lifting, cycling and strenuous exercise are typically restricted for several weeks, and sexual activity involving the canal is deferred until the surgeon confirms healing. The Cleveland Clinic notes that full recovery is often described in months rather than weeks, with follow-up visits to check healing and dilation progress.
Set up a recovery station before you go: cushions, water, pads, medicines in reach, and a schedule template for dilation taped where you will see it.
What people often get wrong about preparing for vaginoplasty
Misunderstandings travel fast in online spaces, and several of them can affect outcomes.
“Vaping is fine because it is not smoking.” Nicotine, not smoke, is the main threat to skin flaps. Any nicotine product narrows the small vessels on which healing depends. Teams that test for nicotine will pick up vaping and pouches.
“I can finish hair removal in the last month.” Follicles are only destroyed during their active growth phase, and only a portion of hair is active at any time. That is why providers schedule sessions weeks apart over many months. Starting late often means postponing surgery.
“Supplements are natural, so they do not count as medicines.” Several common supplements change clotting or drug metabolism, as the NIH Office of Dietary Supplements documents. They belong on the list you give the anesthesiologist.
“Everyone has to stop hormones.” Practice varies and the evidence is unsettled. Some programs continue estrogen with clot prevention; others pause. Neither approach should be adopted without your surgeon’s guidance.
“Losing weight quickly before surgery is always helpful.” Rapid restriction depletes protein stores needed for collagen and immune function. Stability and adequate nutrition in the final weeks generally serve healing better than a crash diet.
“If the first days look bad, something went wrong.” Significant swelling, bruising and asymmetry are expected early. The Mayo Clinic notes that final results take months to emerge. What matters is the trajectory and the absence of red flags, not the appearance on day three.
“Dilation is optional once things feel healed.” The canal is lined with skin that contracts if not stretched. Lapses, particularly in the first year, can narrow or shorten it. The schedule tapers over time but, for canal-depth techniques, does not end.
Questions to ask your care team before vaginoplasty
Consultations go faster than expected, and the questions you meant to ask evaporate once you are in the room. Writing them down beforehand helps, and the following cover gaps people most often report afterward.
- Which surgical technique do you plan for me, and why does my anatomy suit it? What would change the plan during surgery?
- Exactly which area needs hair removal, and can you mark it or give me a diagram for my electrolysis or laser provider?
- What is your protocol for hormone therapy around surgery, and what is the reasoning behind it?
- Which of my current medicines and supplements should I pause, when, and who will coordinate that with my other prescribers?
- How do you confirm nicotine abstinence, and how far in advance do you require it?
- What is your approach to clot prevention in hospital and after discharge?
- How long do you expect me to stay in hospital, and what are the criteria for going home?
- What does the dilation schedule look like in the first weeks, and who do I call if I cannot complete it?
- What complications do you see most often, and how are they managed?
- What are the signs that should make me call you urgently rather than wait for the next visit?
- Who answers the phone after hours, and what is the plan if I live far from the hospital?
- Can I speak with a pelvic floor therapist before surgery?
- What follow-up schedule do you expect over the first year?
Bring someone with you if you can. A second set of ears catches details, and some programs will let you record the conversation if you ask. It is reasonable to request a written summary of the preoperative plan, with dates for each milestone, so that the folder on your kitchen table becomes a sequence you can follow rather than a pile.
When to call your doctor
Most of the preparation period passes without drama, but a few situations before and after surgery warrant a prompt call rather than waiting for the next appointment.
Before surgery, contact the team if you develop a fever, a cough or chest infection, a new skin infection or rash in the genital area, vomiting or diarrhea in the final days, or any new medicine prescribed by another clinician. Call too if you have slipped with nicotine; the team would rather know and plan than find out from a test. Any symptoms of a blood clot, such as a swollen, painful calf or sudden breathlessness, need same-day assessment regardless of how close surgery is.
After surgery, the Cleveland Clinic and Mayo Clinic describe red flags that should prompt an urgent call or emergency evaluation:
- Heavy bleeding that soaks through pads quickly or does not slow with rest and gentle pressure.
- Fever, chills, or spreading redness, warmth and increasing pain around the wound.
- Foul-smelling or pus-like discharge, which can indicate infection.
- Inability to pass urine after the catheter is removed, or urine leaking from the canal, which may suggest a fistula (an abnormal connection between two organs).
- Stool or gas passing from the canal, which can indicate a connection to the rectum and needs same-day assessment.
- Calf pain and swelling, chest pain, or sudden shortness of breath, which can signal a blood clot in the leg or lung.
- Dark or blackened tissue at wound edges, suggesting compromised blood supply.
- Severe pain that is escalating despite prescribed medicines, or pain that suddenly changes character.
- Dilation that has become impossible because of pain or narrowing.
Emotional distress is a medical matter too. Low mood, overwhelming anxiety or regret in the early weeks is common and worth raising; many programs have mental health support built in. If you ever feel unsafe, use your local emergency number or crisis line immediately.
Every decision about timing, medicines and recovery sits with your treating team, who know your history. When in doubt, call.
Frequently asked questions
What are the standard vaginoplasty pre op requirements?
Most programs require a documented diagnosis where the surgery is gender-affirming, a surgical consultation with genital exam, anesthesia assessment, routine blood tests, completed genital hair removal, nicotine abstinence, a medication and supplement review, and a plan for help at home during recovery. Many also ask for a period of hormone therapy beforehand and offer fertility counseling. The specific list differs between surgeons, and the treating team’s version is the one that applies to you.
How long does hair removal before vaginoplasty take?
Providers generally describe the process in months because follicles can only be destroyed during their active growth phase, and only part of the hair is active at any time. Sessions of electrolysis or laser are spaced weeks apart to catch successive cycles. Laser works best on dark hair; electrolysis works on any color but is slower. Ask your surgeon for a precise map of the area to clear before booking sessions.
Do I have to stop smoking before vaginoplasty?
Yes. Nicotine constricts the tiny blood vessels that supply the skin flaps, raising the risk of flap breakdown, infection and slow healing, and MedlinePlus notes smokers have more wound and breathing complications after surgery. Most surgeons require abstinence from all nicotine, including vaping and pouches, for a period they set and may test. If quitting is hard, tell your team early so they can connect you with support.
What does the pelvic exam before vaginoplasty check?
The surgeon assesses the skin available for the operation, including penile and scrotal skin elasticity and whether circumcision was performed, hair growth and how much removal remains, scars from prior surgery, and any skin conditions that should be treated first. A rectal exam is sometimes included to evaluate the prostate and the tissue plane behind the planned canal. You can ask for a chaperone and for each step to be explained.
Which blood tests are done before vaginoplasty?
A complete blood count, a metabolic panel covering kidney function, electrolytes and liver enzymes, and blood sugar measures such as glucose or hemoglobin A1c are nearly universal. Clotting studies are added when history or medicines warrant them. Many programs also screen for HIV and hepatitis, check hormone levels, test urine, and sometimes test for nicotine metabolites. Results are used to plan anesthesia safely and to correct problems before surgery.
Will I need to stop estrogen before vaginoplasty?
It depends on your surgeon’s protocol. Estrogen raises clotting factor production, and pelvic surgery independently increases clot risk, so some teams pause it for a period. Others continue it with standard clot prevention, citing observational studies reporting low clot rates, though those studies are small. Transdermal estrogen appears to affect clotting less than oral forms. Do not change your regimen without discussing it with your surgical team.
What should I expect after vaginoplasty in the first weeks?
Expect a hospital stay of a few days with a catheter and internal packing, significant swelling and bruising, and spotting or yellowish discharge as sutures dissolve once home. Dilation typically begins after packing removal and is performed several times a day at first. Walking is encouraged early, while lifting, strenuous exercise and sexual activity are deferred for weeks until the surgeon confirms healing. Final appearance emerges over months.
Why is bowel preparation needed before vaginoplasty?
The new canal is created in the space between the bladder and the rectum, so the rectal wall lies directly behind the surgical plane. An empty rectum keeps the field cleaner and reduces the consequences if the rectum is accidentally injured. Preparations vary from a clear-liquid diet to a laxative regimen or enema, and your surgical team specifies exactly what to use and when.
Can I take supplements or ibuprofen before vaginoplasty?
Usually not in the final weeks without checking first. Ibuprofen and other NSAIDs reduce platelet function, aspirin does so for the life of the platelet, and supplements such as fish oil, vitamin E, garlic, ginkgo and ginseng can also increase bleeding, according to the NIH Office of Dietary Supplements. Acetaminophen is often permitted but confirm this. Bring every product you take to the anesthesia visit for review.
What signs after vaginoplasty mean I should call my doctor urgently?
Heavy bleeding that soaks pads quickly, fever or spreading redness around the wound, foul or pus-like discharge, inability to urinate after catheter removal, stool or gas passing from the canal, blackened wound edges, and calf pain, chest pain or sudden breathlessness all need prompt contact with your team or emergency care. Escalating pain or an inability to dilate also warrants a call rather than waiting.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is Tumescent Liposuction Right for You? Small Areas, Stable Weight and Honest Limits
Tumescent liposuction is usually considered for adults at or near a stable, healthy weight who have a few well-defined fat pockets that have not…

Is Classic Liposuction Right for You? Skin Elasticity, Stable Weight and Realistic Areas
A typical classic liposuction candidate is an adult at or near a stable weight for several months, with localized fat pockets that resist diet…
What the Tumescent Solution Does in Tumescent Liposuction: Bleeding, Bruising and Comfort
Tumescent solution is a large volume of very dilute salt water carrying a local anesthetic and epinephrine, infused into the fat before liposuction. It…
How Monsplasty Is Performed: Liposuction, Skin Removal and Where the Incision Sits
Monsplasty reshapes the mons pubis, the soft fatty mound over the pubic bone, using one of two approaches or both together. Liposuction removes excess…

Who Is a Candidate for Vaginoplasty? Childbirth Changes, Symptoms and Surgical Timing
A candidate for vaginoplasty is usually someone who has finished childbearing, has persistent looseness or bulging of the vaginal wall (often after vaginal birth),…

What Are the Risks of Monsplasty? Swelling, Numbness and the Signs Worth Reporting Early
Monsplasty risks are mostly the ordinary risks of any skin-and-fat contouring operation: swelling that can last for months, temporary or occasionally lasting numbness, bruising,…