

Questions to Ask Your Bariatric Surgeon Before Signing the Consent Form

Key Takeaways
- Guidelines from the NHS and NIDDK generally consider surgery at a BMI of 40 or more, or 35 or more with a weight-related condition, after non-surgical approaches have been tried.
- A sleeve gastrectomy removes roughly 80 percent of the stomach and cannot be reversed, while gastric bypass reroutes food past most of the stomach and changes how alcohol and some medicines are absorbed.
- The Mayo Clinic describes a staged return to regular food textures over roughly eight weeks, moving from liquids to pureed to soft foods only as each stage is tolerated.
- The 30/30 rule is patient shorthand for separating drinks from meals by about half an hour, a principle that appears in Mayo Clinic eating guidance to protect fullness and avoid discomfort.
- Supplements and blood tests are lifelong after most procedures because deficiencies in iron, vitamin B12, vitamin D, and calcium can develop years later, according to the NHS and NIDDK.
- Chest pain, sudden breathlessness, severe abdominal pain with fever or a racing heart, or vomiting blood after surgery are emergency signs that need immediate care.
Before signing a bariatric surgery consent form, ask your surgeon how many of your specific operation they perform each year, why they recommend that procedure for you, what the realistic complication risks are in numbers, what the first weeks of recovery and eating involve, how lifelong follow-up and supplements are arranged, and what alternatives exist. A good consent conversation leaves every decision with you and your treating team.
The consent form is usually three or four pages. It arrives after months of appointments, a dietitian’s food diary, a psychology screen, blood tests, and at least one evening spent reading forum posts at two in the morning. And still, sitting in the pre-op room with a pen, many people realize they have a dozen questions they never quite asked out loud.
That moment is worth slowing down for. Bariatric surgery permanently changes how your stomach and intestines work, and the questions to ask your bariatric surgeon are not about second-guessing a decision you have already made. They are about making sure the decision is genuinely yours, informed by what the evidence says rather than by what a glossy brochure or a stranger’s video promised.
This explainer walks through what the consent actually covers, what the operations do, who is asked to wait, what recovery looks like week by week, and the specific questions that experienced patients wish they had raised before the ink dried.
What does informed consent for bariatric surgery actually cover?
Informed consent is the legal and ethical process by which you agree to a procedure after understanding what it involves, what could go wrong, and what else you could do instead. The signature is the smallest part. The conversation is the point.
For weight-loss surgery, guideline bodies such as the NHS describe consent as covering four things: what the operation does to your body, the known risks and how likely they are, the realistic benefits and their limits, and the alternatives, including no surgery at all. If any of those four feels fuzzy when the form is in front of you, that is a signal to pause, not a sign that you are being difficult.
A useful test: could you explain to a friend, in your own words, which part of your digestive tract will be altered and why that particular change was chosen for you? Could you name the two or three complications the surgeon is most concerned about in your case? If not, the consent is technically valid but practically thin.
Consent is also not a one-way transaction. You are allowed to ask the surgeon to draw the operation on paper. You are allowed to bring a family member who takes notes. You are allowed to ask the same question twice if the first answer used words you did not recognize. Surgeons who perform these operations regularly expect this; the Mayo Clinic notes that thorough preparation, including understanding lifelong dietary changes, is part of the standard pathway rather than an optional extra.
Finally, consent can be withdrawn. Right up to the anesthetic, you can say you need more time. That is uncomfortable to imagine, but knowing it is possible tends to make the signature feel less like a cliff edge and more like a step you chose.
How bariatric surgery works: what actually happens inside
All bariatric operations change the anatomy of the upper digestive tract so that you feel full sooner, absorb fewer calories, or both. They also alter the gut hormones that regulate hunger and blood sugar, which is why appetite often changes in ways that go beyond a simple smaller stomach.
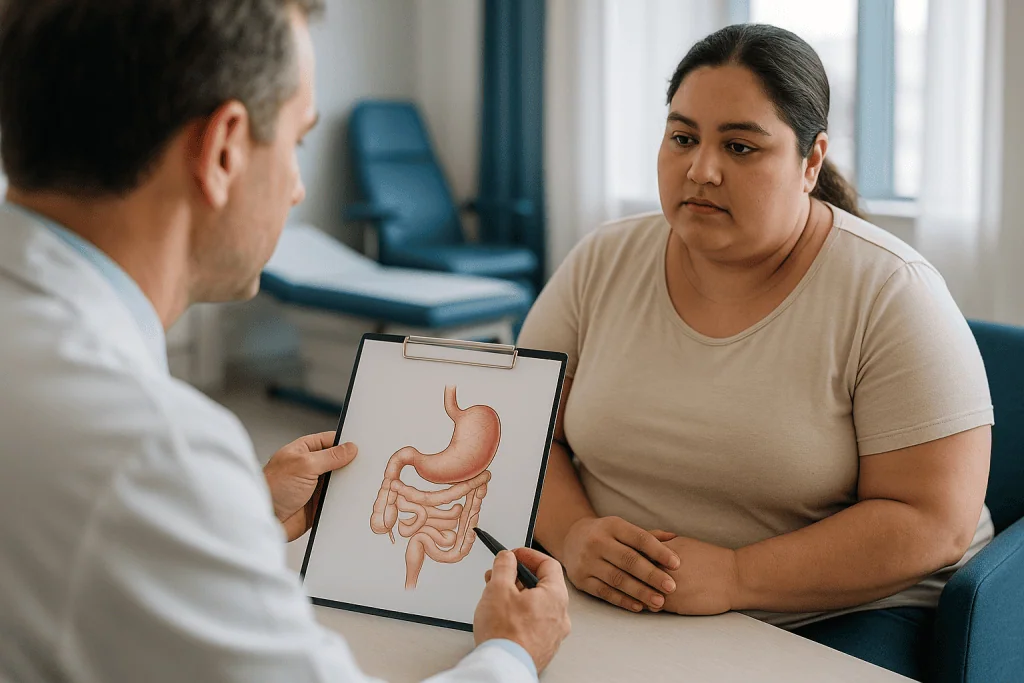
The sleeve gastrectomy removes a large portion of the stomach, roughly 80 percent according to the NIH’s National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), leaving a narrow tube shaped like a banana. Nothing is rerouted. The part removed also produces much of the hormone ghrelin, which drives hunger.
Roux-en-Y gastric bypass creates a small pouch at the top of the stomach and connects it directly to a lower part of the small intestine. Food bypasses most of the stomach and the first section of the intestine. Both restriction and reduced absorption are at work, and blood sugar regulation often shifts quickly because of hormone changes in the bypassed segment.
An adjustable gastric band is an inflatable ring placed around the upper stomach to create a small pouch. It is adjustable and removable, but the NHS notes it is now used less often than sleeve and bypass in many programs.
Biliopancreatic diversion with duodenal switch combines a sleeve with a longer intestinal bypass. It produces the greatest change in absorption and carries the highest risk of nutritional deficiency, so it is usually reserved for specific situations.
Nearly all of these are done laparoscopically, meaning through several small incisions with a camera, which is why hospital stays are measured in days rather than weeks. Understanding which of these mechanisms applies to your operation, restriction, malabsorption, or both, is the foundation for every later question about eating, supplements, and risk.
What would disqualify me from bariatric surgery, and who is asked to wait?
Eligibility is set by guidelines rather than by any single surgeon’s preference. The NHS and NIDDK describe surgery as generally considered for adults with a body mass index (BMI) of 40 or more, or of 35 or more alongside a weight-related condition such as type 2 diabetes, sleep apnea, or high blood pressure. Some guidance now allows consideration at lower BMI thresholds when type 2 diabetes is poorly controlled. BMI is a ratio of weight to height used as a population screening tool, not a verdict on any individual.
Most programs also expect that non-surgical approaches have been tried, and that you are prepared to commit to lifelong changes in eating and follow-up. That expectation is not a moral test; it reflects evidence that outcomes depend on what happens after the operation as much as during it.
People are usually asked to wait, rather than permanently declined, in a few common situations:
- Active alcohol or substance use disorder that is not yet in treatment.
- An eating disorder that is not stabilized, because surgery changes eating mechanics without addressing the underlying pattern.
- Uncontrolled psychiatric illness that would make follow-up unsafe or unrealistic.
- Pregnancy or plans to conceive in the near term; the NHS advises avoiding pregnancy for the first 12 to 18 months after surgery while weight and nutrition are changing rapidly.
- Medical conditions that make general anesthesia unusually dangerous, such as severe uncontrolled heart or lung disease.
- Recent or active cancer treatment, where the priority is elsewhere.
Permanent disqualification is rare. More often the answer is “not yet,” with a plan attached. If you have been told to wait, a fair question is: what specifically needs to change, how will it be measured, and who will reassess me? A vague “come back when you’re ready” is not a plan.
Questions to ask your bariatric surgeon about experience and the program
Volume matters in surgery, and it is a legitimate thing to ask about. The question is not “Are you good?” but “How many of this specific operation do you perform each year, and how many has the whole team done?” Sleeve and bypass are different procedures with different learning curves, so a surgeon’s total bariatric count tells you less than their count for your operation.

Ask what happens if something goes wrong at three in the morning. Who is on call? Does the same team that did the surgery manage complications, or are you transferred elsewhere? The NHS and Mayo Clinic both describe bariatric care as a team activity involving dietitians, psychologists, specialist nurses, and physicians, not a surgeon working alone.
Ask how the program tracks its own outcomes. A team that can tell you its leak rate, its readmission rate, and its reoperation rate for your procedure, and can compare those to published benchmarks, is a team that is paying attention. You are not looking for perfect numbers. You are looking for a team that knows its numbers.
Ask what the follow-up schedule looks like at one month, six months, one year, and beyond, and who runs it. Lifelong follow-up is a guideline expectation, according to the NHS, because nutritional deficiencies and weight regain can appear years later. A program that becomes hard to reach after the first year is a program with a gap.
And ask, plainly, what the surgeon would want to know if a family member were in your seat. That question tends to move the conversation from a script to an honest exchange, which is exactly where consent should live.
Which operation is right for me? Comparing the main procedures
Surgeons recommend a procedure based on your BMI, your medical conditions, your history of reflux, prior abdominal surgery, and what you are prepared to manage afterwards. The right question is not “Which is best?” but “Why this one for me, and what would make you choose differently?”
| Procedure | Main mechanism | Reversible? | Points to raise with your surgeon |
|---|---|---|---|
| Sleeve gastrectomy | Restriction plus hormone change | No; stomach tissue is removed | Reflux history, since sleeve can worsen heartburn (Mayo Clinic) |
| Roux-en-Y gastric bypass | Restriction plus reduced absorption | Technically possible but rarely done | Dumping syndrome, lifelong supplements, alcohol absorption |
| Adjustable gastric band | Restriction only | Yes; band can be removed | Adjustment visits, band slippage, lower use in current practice (NHS) |
| Duodenal switch | Restriction plus significant malabsorption | No | Highest deficiency risk; usually reserved for specific cases (NIDDK) |
A few specific things are worth asking about. If you have significant acid reflux, ask how the choice between sleeve and bypass accounts for it, because the Mayo Clinic notes reflux can be aggravated after a sleeve. If you have type 2 diabetes, ask how the hormonal effects of bypass factor into the recommendation. If you have had previous abdominal operations, ask whether scar tissue changes the plan or the risk.
Ask what the surgeon would do if the anatomy inside looks different from the scans. Would they switch procedures during the operation, and did you consent to that possibility? Ask about revision: if this operation later needs converting to another, what does that pathway look like?
You are entitled to hear the case against the recommended procedure as clearly as the case for it. A surgeon who can articulate both is showing you their reasoning, and reasoning is what you are consenting to.
Bariatric surgery risks and complications: the questions that get honest numbers
Every operation carries risk, and bariatric surgery is a major abdominal procedure under general anesthesia. Asking about risk is not pessimism; it is the core of consent. The trick is to ask in a way that produces numbers rather than reassurance.
Short-term complications described by the NHS, Mayo Clinic, and MedlinePlus include bleeding, infection, blood clots in the legs or lungs, leaks from the staple line or new connections, breathing problems, and adverse reactions to anesthesia. Ask your surgeon: for my operation, in this program, roughly how often does each of these happen, and what is the plan if it does?
Longer-term issues include nutritional deficiencies (iron, vitamin B12, vitamin D, calcium, and others), gallstones as weight falls quickly, hernias at incision sites, bowel obstruction from scar tissue, ulcers at the new connection after bypass, and dumping syndrome, which is rapid emptying of stomach contents into the intestine causing nausea, sweating, and diarrhea after eating. The NHS also lists excess loose skin as a common consequence that many people underestimate.
Ask which of these apply to your specific procedure. Dumping syndrome is mostly a bypass issue; worsening reflux is mostly a sleeve issue. A generic risk list does not tell you your risk.
Ask about your personal risk modifiers. Smoking impairs healing and raises ulcer risk. Sleep apnea affects anesthesia planning. Certain medicines increase bleeding. Ask how each of yours changes the picture and what is being done about it before the operation.
And ask the uncomfortable question directly: what is the risk of death for this operation in this program? A surgeon who answers calmly with a figure and its context is a surgeon who has thought about it. Silence or deflection is information too.
What do the first days and weeks after bariatric surgery usually look like?
Recovery has a rhythm, and knowing it in advance takes some of the fear out of the first week. Timelines vary by procedure and program, so treat these as typical ranges rather than promises.
The hospital stay. Most laparoscopic procedures involve a stay of one to a few days, according to MedlinePlus. You will be asked to walk within hours, because movement lowers the risk of blood clots and helps the bowel wake up. You will be sipping clear fluids in tiny amounts, with staff watching how you tolerate them.
The first two weeks. Expect fatigue, some abdominal soreness, and a liquid-only eating plan. Pain is usually managed with medicines your team prescribes; how and when to take them is their call, not something to adjust on your own. Many people report that the hardest part is not hunger but the strangeness of not eating normally.
Weeks two to eight. The Mayo Clinic describes a staged progression from liquids to pureed foods, then soft foods, then regular textures over roughly eight weeks, with each step introduced only when the previous one is tolerated. Protein comes first at every stage. Portions are measured in tablespoons before they are measured in cups.
Returning to normal life. The NHS describes a recovery of several weeks before most people return to usual activities, longer for physically demanding work or for open rather than keyhole surgery. Lifting restrictions are typical early on to protect incisions.
Questions to raise before consenting: What is your program’s exact stage-by-stage eating plan? When is my first follow-up, and who do I call in between? When can I drive, shower, lift, and return to work? What symptoms in the first fortnight are expected, and which mean I should call immediately?
What is the 30/30 rule for bariatric surgery, and what does the evidence say?
The “30/30 rule” is a patient-community shorthand, not a term from any clinical guideline. It usually means: do not drink anything for 30 minutes before a meal and 30 minutes after it. Some people also use it to mean spending around 30 minutes on each meal, eating slowly.
The idea behind it is sound and appears, in less catchy form, in mainstream dietary guidance. The Mayo Clinic’s post-bypass eating advice recommends not drinking liquids with meals and waiting about 30 minutes after eating before drinking again. The reasoning is mechanical: a small pouch or sleeve fills quickly, and liquid taken with food either overfills it, causing discomfort, or washes food through faster, reducing the sense of fullness that the operation is designed to create.
Eating slowly serves a similar purpose. Fullness signals lag behind swallowing, and a pouch that is overfilled tends to announce itself with pain, nausea, or vomiting. Chewing thoroughly matters more after surgery because the narrowed outlet can be blocked by poorly chewed food.
What the evidence does not support is treating the number 30 as sacred. Programs vary; some advise 15 minutes, others longer. The principle is separating liquids from solids and eating without hurry. Your dietitian’s version is the one to follow.
The 30/30 rule also sits inside a bigger picture of lifelong eating that the NIDDK and NHS describe: small portions, protein prioritized, sugary drinks and high-fat foods limited, and consistent hydration between meals to avoid dehydration, which is a common reason for early readmission. Ask your team to show you their written eating plan before you sign, and ask what happens at the six-month and one-year points when many people find old habits creeping back.
Questions about supplements, medicines and lifelong follow-up
Bariatric surgery changes how your body absorbs nutrients and, in some cases, how it absorbs medicines. This is one of the least glamorous parts of consent and one of the most consequential.
Nutritional supplements are lifelong after most procedures. The NHS and NIDDK describe regular vitamin and mineral supplementation, commonly including a multivitamin, iron, vitamin B12, calcium, and vitamin D, along with blood tests to check levels. The exact products, amounts, and forms are decided by your team based on your operation and your bloodwork, and they can change over time. Ask: which supplements will I need, how often will my levels be checked, and who will act on the results?
Existing medicines deserve a specific conversation. Some tablets are absorbed differently after bypass. Extended-release formulations may not behave as intended when the stomach is smaller or the intestine is shortened. Certain anti-inflammatory painkillers are usually avoided after bypass because they raise the risk of ulcers at the new connection. Medicines for diabetes and blood pressure often need adjusting as weight and metabolism change, sometimes quickly. None of these changes should be made on your own; the prescribing clinician decides, and the question to ask is how that coordination will happen between your surgical team and your regular doctor.
Follow-up is where long-term outcomes are made or lost. The NHS describes lifelong monitoring as part of the pathway. Ask how often you will be seen in years two, three, and five. Ask who monitors bone health, since calcium and vitamin D absorption fall after some procedures. Ask what support exists if weight regain occurs, because it is common enough that a good program has a plan rather than a shrug.
If the answer to any of these is “we’ll sort that out later,” ask for it to be sorted out now.
Questions about mental health, alcohol and support after surgery
Surgery changes your body in a matter of hours. It does not change the reasons food became a comfort, a reward, or a way to cope, and it does not change the relationships around you. Asking about the psychological side of the pathway is not a sign of weakness; it is the mature question.
Most programs include a psychological assessment before surgery. Ask what it is for and what happens with the findings. Ask whether ongoing counseling or support groups are part of the package or something you would need to arrange yourself.
Alcohol deserves particular attention. After gastric bypass, alcohol enters the bloodstream faster and reaches higher peak levels because it is no longer slowed by a full stomach, according to the Mayo Clinic. Some people also find that the urge to eat is replaced by an urge to drink, a pattern sometimes called addiction transfer. Ask your team how they screen for this and what support exists if it appears.
Mood can shift in the months after surgery for reasons that are partly hormonal, partly nutritional, and partly about identity. Rapid weight loss changes how strangers treat you, how clothes fit, and sometimes how partners react. Ask what to watch for and whom to call.
Relationships with food do not vanish. The eating plan is precise in the early months, but by year two the structure loosens and old patterns can return. Ask whether your program offers dietitian access beyond the first year.
Practical support matters too. Who will drive you home? Who will be around in the first week? Ask the team what they expect from your support network and what they can offer if it is thin. A surgeon who takes these questions seriously is treating you as a whole person rather than an anatomy diagram.
What people often get wrong about bariatric surgery
The myths around weight-loss surgery run in both directions: some make it sound like a shortcut, others like a catastrophe. Neither helps consent.
“It’s the easy way out.” The operation itself is the shortest part. Lifelong eating changes, supplements, follow-up, and psychological adjustment are the long part, and the NHS describes the commitment as permanent. People who have done it rarely describe it as easy.
“The surgery does all the work.” Anatomy creates conditions for change; behavior determines whether the change lasts. Weight regain over years is a recognized pattern, which is why programs build in long-term monitoring.
“Once you lose the weight, you’re done.” Nutritional deficiencies can develop years later, according to the NIDDK, sometimes without obvious symptoms until they are advanced. Blood tests continue for life.
“Everyone ends up with sagging skin.” Loose skin is common after large weight loss, as the NHS notes, but its extent varies with age, genetics, how much weight is lost, and how fast. Ask your team what to expect and whether body-contouring surgery is ever part of the pathway.
“Bypass is reversible, so it’s lower risk.” Reversal is technically possible in some cases but is itself a major operation and rarely performed. Consent for bypass should assume permanence.
“You can never eat normally again.” Most people return to regular food textures within a couple of months, per the Mayo Clinic’s staged plan. Portions are smaller and certain foods may not agree with you, but eating is not a lifetime of liquids.
“Diabetes disappears.” Many people see marked improvement in blood sugar after bypass in particular, but outcomes vary, some conditions return, and no guideline describes surgery as a guaranteed fix. Ask what your team’s own data show for people like you.
What to ask before gastric sleeve surgery: what people wish they had known
Sleeve gastrectomy is now the most commonly performed bariatric procedure in many countries, and it has its own set of surprises. These are themes that patients repeatedly raise in follow-up clinics and that are worth turning into questions before consent.
Reflux. The Mayo Clinic notes that a sleeve can worsen or trigger heartburn because the narrow tube increases pressure in the stomach. Ask: do I have any reflux now, was it assessed, and what is the plan if it appears or worsens?
Hunger returns. The early months often bring an almost eerie absence of appetite, partly because the removed portion of stomach produced much of the hunger hormone ghrelin. That effect tends to soften over time. Ask your dietitian how eating structure changes when appetite comes back.
Irreversibility. Stomach tissue is removed and cannot be put back. Ask what revision options exist if the sleeve later causes intractable reflux or if weight regain is significant; conversion to bypass is one pathway some programs offer.
Hydration is hard. Sipping enough fluid through a narrow sleeve without drinking around meals takes planning. Dehydration is a common early problem. Ask what daily fluid target your team uses and how to spread it across the day.
Food textures behave differently. Dry meats and bread are frequently poorly tolerated early on. Ask for the program’s list of foods to introduce cautiously.
Emotional whiplash. Rapid change in body size can arrive faster than the mind adjusts. Ask what psychological support is available in the first year.
None of these are reasons not to proceed. They are reasons to walk in with specific questions and walk out with specific answers, which is what consent is supposed to produce.
What can you never do again after bariatric surgery?
“Never” is a strong word, and mainstream guidance uses it sparingly. The honest answer is that a short list of things becomes permanently different, a longer list becomes cautious, and most of life carries on.
Permanently different. Supplements and blood monitoring are lifelong after most procedures, according to the NHS and NIDDK. Large portions eaten quickly will cause discomfort for the rest of your life; the anatomy simply does not allow it. Certain anti-inflammatory painkillers are usually avoided long term after bypass because of ulcer risk, a decision that sits with your prescribing clinician.
Approached with caution. Alcohol is absorbed faster and hits harder after bypass, per the Mayo Clinic, and carries a higher risk of misuse patterns. Carbonated drinks stretch the pouch and cause pain for many people. Sugary foods can provoke dumping syndrome after bypass. Pregnancy is generally advised against in the first 12 to 18 months, according to the NHS, and requires closer nutritional monitoring afterwards.
Usually fine, with adjustment. Exercise is encouraged and expected. Travel is possible once recovery is complete. Eating out is possible with smaller orders and slower pace. Most medicines can continue, though some formulations may need changing under medical supervision.
The question to ask your surgeon is not “What can I never do?” but “What specifically changes for my operation, and which of those changes is a hard rule versus a strong suggestion?” A hard rule is something like lifelong supplements. A strong suggestion is something like avoiding carbonated drinks. Knowing which is which helps you plan a life rather than a list of prohibitions.
Ask also about the things nobody mentions: dental health can suffer if vomiting is frequent; hair shedding is common in the months of fastest weight loss and usually settles as nutrition stabilizes. Small surprises are easier to bear when they are not surprises.
Bariatric surgery consultation questions: a checklist for your care team
Bring this list to your final pre-op appointment. Cross out what has already been answered, and do not sign until the rest has been.
About the surgeon and program
- How many of my specific operation do you perform each year?
- What are your program’s leak, readmission, and reoperation rates for this procedure?
- Who manages complications, and how do I reach the team after hours?
- Which specialists are on the team, and will I see them after the first year?
About the choice of operation
- Why this procedure for me rather than the alternatives?
- How does my reflux, diabetes, or previous surgery affect the recommendation?
- Could the plan change during the operation, and have I consented to that?
- What revision options exist if this operation does not work as hoped?
About risk
- What are the most likely complications for me, in numbers?
- Which of my medical conditions or medicines raise my risk, and what is being done about them?
- What is the risk of death for this operation in this program?
About recovery and life afterwards
- What is the stage-by-stage eating plan, in writing?
- When can I drive, work, lift, and exercise?
- Which supplements will I need, and how often will my levels be checked?
- How will my regular medicines be reviewed, and by whom?
- What support exists for mood, alcohol, and eating patterns after surgery?
- What is the plan if I regain weight?
Consent is complete when you can answer the question “What am I agreeing to?” without looking at the form. Ask your team to help you get there, and treat their willingness to do so as part of what you are choosing.
When to call your doctor after bariatric surgery: red-flag signs
Most recovery is uneventful, but some complications need urgent attention, and knowing the signs before the operation is part of good consent. Ask your team for their specific list; the following reflects mainstream guidance from MedlinePlus, the Mayo Clinic, and the NHS.
Call emergency services or go to an emergency department immediately if you have:
- Chest pain, sudden shortness of breath, or coughing up blood, which can signal a blood clot in the lungs.
- Severe or worsening abdominal pain, especially with a fast heartbeat, fever, or a feeling of being very unwell, which can indicate a leak or internal bleeding.
- Vomiting blood or passing black, tarry, or bloody stools.
- Fainting, confusion, or a racing heart at rest.
Contact your surgical team the same day if you notice:
- A temperature that stays raised, or chills.
- Redness, warmth, swelling, or discharge at an incision.
- Pain, swelling, or warmth in one calf, which can be a clot in the leg.
- Inability to keep down fluids for more than a few hours, or signs of dehydration such as dark urine, dizziness, or very dry mouth.
- Persistent vomiting after every attempt to eat or drink.
- Yellowing of the skin or eyes, or pain under the right ribs, which may relate to gallstones.
Raise at your next appointment, or sooner if worsening: heartburn that does not settle, new or unusual tiredness, numbness or tingling in hands or feet, hair shedding that seems excessive, low mood, or any change in drinking habits. These can point to nutritional or psychological issues that are easier to manage early.
Every one of these decisions sits with your treating team. Ask them, before you sign, exactly which number to call for each of these situations, and write it down somewhere your family can find it.
Frequently asked questions
What is the 30/30 rule for bariatric surgery?
The 30/30 rule is patient shorthand for not drinking for about 30 minutes before and after meals, and sometimes for eating each meal slowly over about 30 minutes. It is not a formal guideline, but the principle appears in Mayo Clinic eating guidance: separating liquids from solids protects the sense of fullness a small pouch or sleeve creates and reduces discomfort. Follow your own dietitian’s version of the timing.
What would disqualify me from bariatric surgery?
Permanent disqualification is uncommon; most barriers are temporary. People are usually asked to wait for active alcohol or substance use disorder not yet in treatment, an unstabilized eating disorder, uncontrolled psychiatric illness, current pregnancy or near-term plans to conceive, or conditions that make general anesthesia unusually risky. Programs also expect that non-surgical approaches have been tried. If you are told to wait, ask what specifically needs to change and who will reassess you.
What do people wish they knew before gastric sleeve surgery?
Common themes from follow-up clinics include how much hydration planning is needed, how reflux can appear or worsen after a sleeve, how appetite returns after the first months, how poorly some textures like dry meat are tolerated early, and how quickly body changes outpace emotional adjustment. Because stomach tissue is removed, the sleeve is not reversible, so asking about revision options before consent is sensible.
What can you never do again after bariatric surgery?
Few things are absolute, but supplements and blood monitoring are lifelong after most procedures, and large portions eaten quickly will always cause discomfort. Some anti-inflammatory painkillers are usually avoided after bypass because of ulcer risk. Alcohol, carbonated drinks, and sugary foods are approached cautiously rather than forbidden. Pregnancy is generally advised against for the first 12 to 18 months, according to the NHS.
How many bariatric surgeries should my surgeon have done?
No guideline sets a single magic number, but volume in your specific operation matters more than total experience, because sleeve and bypass have different learning curves. Ask how many of your procedure the surgeon performs each year, and how the whole team’s outcomes, such as leak and readmission rates, compare with published benchmarks. A team that knows and shares its numbers is demonstrating the kind of attention you want.
What are the main bariatric surgery risks and complications to ask about?
Short-term risks described by the NHS and Mayo Clinic include bleeding, infection, blood clots, staple-line or connection leaks, and anesthesia reactions. Longer-term issues include nutritional deficiencies, gallstones, hernias, bowel obstruction, ulcers after bypass, dumping syndrome, and loose skin. Ask which apply to your specific procedure, how often each occurs in your program, and how your own conditions such as smoking or sleep apnea change your risk.
How long is recovery after bariatric surgery?
Hospital stays after laparoscopic procedures are usually measured in days, according to MedlinePlus. The NHS describes several weeks before most people return to usual activities, longer for physically demanding jobs. The Mayo Clinic outlines roughly eight weeks of staged eating from liquids to regular textures. These are typical ranges, not promises; your team will set your timeline based on your operation and how you recover.
Can I change my mind after signing the consent form?
Yes. Consent can be withdrawn at any point before the anesthetic is given, and asking for more time is a legitimate choice rather than a failure. A good team would rather you delay than proceed uncertain. If you have unanswered questions on the day, say so. The form records your agreement; it does not remove your right to pause.
Will my regular medicines still work after gastric bypass?
Some may behave differently. Bypass changes how certain tablets are absorbed, extended-release formulations may not work as intended, and some anti-inflammatory painkillers are usually avoided because of ulcer risk. Medicines for diabetes and blood pressure often need review as weight changes. All adjustments belong to your prescribing clinician; ask before surgery how your surgical team and regular doctor will coordinate that review.
Does bariatric surgery treat type 2 diabetes?
Many people see marked improvement in blood sugar after surgery, especially after gastric bypass, because of hormonal changes in the bypassed intestine as well as weight loss. Outcomes vary, and for some people diabetes returns over time. No guideline describes surgery as a guaranteed fix. Ask your team what their own data show for people with your profile, and how your diabetes medicines will be monitored afterwards.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
How Does the Surgeon See Inside? Camera Ports and Gas in Gastric Laparoscopic Surgery
In laparoscopic gastric surgery, the surgeon works through several small cuts in the abdomen rather than one long incision. Carbon dioxide gas is pumped…

Bile Reflux After Mini Gastric Bypass: An Honest Look at the Risk and How It Is Managed
Bile reflux after a mini gastric bypass (also called one anastomosis gastric bypass) happens when bile from the bypassed bowel loop flows back into…

What Happens When the Gastric Balloon Comes Out? Removal and Keeping Habits Afterward
Gastric balloon removal is a short endoscopic procedure, usually done under sedation about six months after placement: the balloon is punctured, drained, and drawn…

Gastric Bypass Recovery Stages: From the Hospital Bed to Your First Solid Meal
Gastric bypass recovery usually moves through stages: a hospital stay of roughly one to four days, a liquid-only diet for the first days, pureed…

When Is the Right Time for Bariatric Contouring? Weight Stability and Nutrition Checks
Body contouring after bariatric surgery is usually considered once weight has been stable for several months, most often 12 to 18 months or more…

Eating After Gastric Sleeve Surgery: Portion Sizes, Protein First and Foods That Cause Trouble
Long-term eating after gastric sleeve surgery settles into a pattern of small, protein-first meals, roughly a cup of food at a time for most…