

Questions to Ask Your Reconstructive Surgeon Before Agreeing to a Staged Plan

Key Takeaways
- Staging exists because transferred tissue needs time to grow a blood supply, and because waiting for pathology results protects the final reconstruction from being undone.
- Each stage of a staged plan should have its own purpose, its own consent discussion, and its own named risks; ask which stage carries the most.
- The intervals between stages are often the hardest part, so ask explicitly what you will look like and be able to do during each one.
- Nicotine constricts the small vessels that flaps and grafts depend on, which is why most teams require you to be nicotine-free around tissue-transfer stages.
- Surgical site infections most commonly appear within 30 days of an operation, making the early review visits after every stage the ones not to miss.
- Scars and swelling continue to mature for a year or more, so refinement stages are deliberately scheduled late and early results should not be judged as final.
Before agreeing to a staged reconstructive plan, ask your surgeon why staging is needed, how many stages are expected, what each one aims to fix, how long the gaps are, what you will look like and be able to do between stages, which risks apply to each step, what the alternatives are, and what would change the plan. Write the answers down and ask for time to decide.
The consultation is nearly over when the surgeon says it: “We’d do this in stages.” Three, possibly four operations, spread across the better part of a year, each one depending on how the last one heals. You nod, because nodding is what people do in that chair. On the drive home you realize you have no idea what you just agreed to.
That gap between nodding and understanding is where most regret in reconstructive care begins. Staged plans are common in facial reconstruction, whether the starting point is a skin cancer excision on the nose, a facial fracture, a burn, or a condition present from birth. They are often the right call. They are also harder to grasp than a single operation, because the plan has moving parts and a timeline that stretches further than most people expect.
So this is a list of the questions to ask reconstructive surgeon teams before you sign anything, along with the reasoning behind each one, so the answers mean something when you hear them.
What does a staged reconstructive plan actually mean?
A staged plan is a series of planned operations that build toward one result, rather than a single procedure that tries to do everything at once. Each stage has its own purpose: clearing disease or dead tissue, bringing in new tissue, shaping it, then refining the details once swelling settles.
The reason surgeons stage facial work comes down to biology. Transferred tissue needs a blood supply, and blood vessels grow on a schedule the surgeon cannot hurry. A flap, which is a block of skin and underlying tissue moved from one place to another while still attached to its own blood vessels, often needs to stay connected to the donor area for a period before that connection is divided. Skin grafts, which are thin sheets of skin fully detached and laid onto a prepared wound bed, need the bed to be clean and well supplied before they will survive. MedlinePlus describes how grafts depend on new vessels growing into them from below, a process measured in days to weeks rather than hours.
Staging also gives the team information. A first operation might remove a tumor with a margin of normal tissue, and the pathology report from that specimen tells the surgeon whether the area is clear before anything is rebuilt over it. Rebuilding first and discovering residual disease later would mean undoing work. Waiting a short interval protects the final result.
Finally, staging spreads the physical load. A long, complex operation under general anesthesia carries more risk than two shorter ones for some patients, particularly those with heart or lung conditions. Your team weighs that against the downside of living with an unfinished reconstruction between visits. Both are real costs, and a good plan names them.
How staged facial reconstruction works, step by step
Plans vary enormously, but most staged facial reconstructions follow a recognizable arc. The first stage deals with the problem that created the defect: excising a cancer, cleaning a wound of damaged tissue (a process called debridement), or stabilizing a fracture. Sometimes a temporary covering is placed over the open area to keep it protected while pathology results come back.
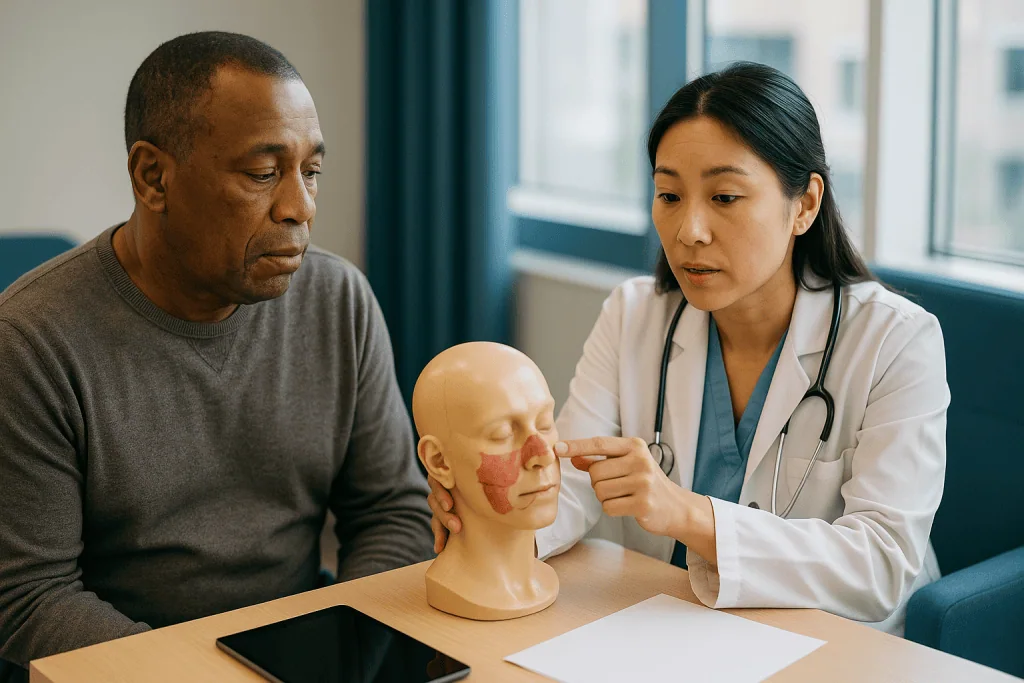
The second stage usually brings in the main building material. That might be a local flap turned from the cheek or forehead, a graft of cartilage from the ear or rib to give a nose its shape, or a tissue expander. An expander is a soft silicone balloon placed under healthy skin and filled gradually over weeks so the skin stretches and produces extra surface area; Mayo Clinic describes this gradual filling at follow-up visits before the expander is later swapped for permanent tissue or an implant. Expanded skin matches color and texture far better than skin borrowed from elsewhere, which matters on the face.
A third stage, where one is planned, often divides a flap from its original blood supply once the new site can sustain it on its own, then thins and contours it. The forehead flap used for larger nasal defects is the classic example: the tissue remains attached between stages, then the bridge is divided and shaped.
Later stages are refinements. Scar revision, which means re-cutting and re-closing a scar so it sits in a more natural line, or adjustments to contour, usually wait until swelling has fully settled, which can take many months. Surgeons generally prefer to judge a result at maturity rather than chase a moving target.
Knowing which of these roles each proposed stage plays is the first thing to establish. If you cannot say in one sentence what stage two is for, ask again.
Who is usually offered a staged plan, and who is asked to wait?
Staging tends to be offered when the defect is large relative to the available local tissue, when it crosses more than one facial unit (the nose, the lip, and the cheek are separate units with different skin), when disease margins are uncertain, or when the wound is contaminated or still evolving, as burns and crush injuries often are. Children with congenital differences are frequently staged so that reconstruction keeps pace with growth, with later procedures timed to development rather than to a calendar.
Some people are asked to wait before any elective stage begins. Active infection at the site is the clearest reason; operating through infected tissue invites failure of grafts and flaps. Uncontrolled diabetes impairs healing and raises infection risk, so teams commonly ask for better control first. Smoking is the other big one. Nicotine narrows small blood vessels, and the NHS advises stopping smoking before plastic surgery because of the raised risk of complications; many reconstructive surgeons will not perform flap surgery on someone who is still smoking, since the flap’s survival depends on exactly the vessels nicotine constricts.
Nutritional state, recent radiotherapy to the area, and medicines that affect clotting or immune function can all shift timing. None of these are judgments about you as a person. They are variables that change the odds of a stage succeeding, and a surgeon who postpones for them is protecting your result.
If you are asked to wait, the useful questions are specific: what exactly needs to change, how will it be measured, who is helping you get there, and what happens to the plan if it cannot change. A delay with a reason and a path is very different from a vague “not yet.”
Questions to ask your reconstructive surgeon about the overall plan
Start wide before going narrow. The questions to ask reconstructive surgeon teams at this level are about the architecture of the plan, not the stitches.

Ask why staging is recommended for you specifically. There is usually a concrete reason: pending pathology, a flap that needs time on its pedicle, skin that needs expanding. Then ask how many stages are planned and how firm that number is. Many surgeons will say “three, possibly four,” and the honest answer includes what would trigger the fourth.
Ask what the end point looks like and how the team will know they have reached it. Reconstruction aims to restore form and function, which includes things like breathing through the nose, closing the eyelid fully, or eating without leakage. Appearance matters too, and it is fair to ask for a realistic description of the likely result, including which scars will remain visible. Be wary of any promise about how it will look; mainstream guidance from the NHS on plastic surgery stresses realistic expectations rather than guarantees.
Ask what the total time commitment is from first stage to final review, counting recovery after each step and the waiting periods between them. People consistently underestimate this. Ask, too, what the plan looks like if a stage does not go as hoped: is there a fallback, and does it add stages or replace them?
Finally, ask who else is involved. Facial reconstruction often brings in dermatology, oncology, ophthalmology, dental or prosthetic specialists, and speech or physical therapy. Knowing who sits on the team, and who coordinates them, tells you how joined-up your care will be across a long plan.
What to ask a plastic surgeon about each individual stage
Once the big picture is clear, walk through each stage as if it were its own operation, because it is. For every stage, ask what will be done, what tissue will be used and where it comes from, what kind of anesthesia is planned, and whether it is a day procedure or an overnight stay.
Ask about the donor site. Grafts and flaps borrow from somewhere, and that somewhere also heals and scars. MedlinePlus notes that split-thickness graft donor areas heal on their own over roughly one to two weeks, while full-thickness donor sites are stitched closed and leave a line scar. On the face, donor choice drives how well color and texture match, so it is worth asking why a particular donor area was chosen over another.
Ask what you will be left with at the end of that stage. After a forehead flap, for example, a visible bridge of tissue connects the forehead to the nose for a period before division. People who were not told this in advance find the interval genuinely distressing. A surgeon who shows you photographs of a typical intermediate stage, with the patient’s consent, is doing you a favor.
Ask how the team will judge whether the stage has succeeded before moving on, and what signs would mean it has not. Ask what you are responsible for during recovery: wound care, dressings, head elevation, activity limits, avoiding sun on new scars.
Then ask the question that gets forgotten: which stage carries the most risk, and why? Stages are not equal. The one that moves tissue with its blood supply is usually the one the team watches most closely, and you should know which one that is.
What will I look like and be able to do between stages?
The intervals between stages are where real life happens, and they are the part of a staged plan least often discussed in detail. Ask directly.
Appearance first. Will there be an open or dressed wound, a temporary covering, a visible flap pedicle, or an expander creating a noticeable bulge under the skin? For how long? Can anything be done to make it easier to go about your day, such as dressing choices, hair styling, or a temporary prosthesis? Expander sequences in particular change your appearance progressively over weeks as the balloon fills, and people describe the middle of that process as the hardest stretch.
Function next. Depending on the site, ask about eating, speaking, breathing, vision, wearing glasses, shaving, sleeping position, and exercise. A nasal reconstruction may mean breathing through the mouth for a while. Work around the eye may restrict driving. Ask when you can return to work and what kind of work the team has in mind, since a desk job and a job involving lifting or dust carry different answers.
Travel and distance deserve a question of their own. Flap division dates and expander fills are scheduled around healing, not convenience, and missing one can set the whole plan back. If you live far from the surgical team, ask how follow-up will be managed and what should happen if something looks wrong between visits.
Emotional load is legitimate to raise. Living with an unfinished face, even temporarily, affects confidence, relationships, and mood. Ask whether the service has access to psychological support or patient peer contact; many reconstructive teams do, and knowing it exists before you need it is better than searching for it afterward.
Which risks belong to which stage?
Every operation carries general risks: bleeding, infection, reactions to anesthesia, blood clots, and scarring. Reconstruction adds specific ones, and they cluster at particular stages.
Tissue transfer stages carry the risk that the moved tissue does not survive. A graft can fail to take if fluid or blood collects beneath it, if it shifts before vessels grow in, or if the wound bed is poorly supplied. A flap can lose part of its edge if the blood supply at the far end is marginal. Partial loss is more common than total loss, and it often heals with dressings and time, though it may add a revision stage. Ask what percentage of flaps or grafts in this location typically have problems; a careful surgeon will tell you what the published evidence shows for that technique rather than quoting a single reassuring number.
Infection risk peaks in the days to weeks after each stage. The CDC notes that surgical site infections most commonly show up within 30 days of an operation, which is why the early review visits matter. Expanders carry a specific concern: because they are foreign material under tension, infection or exposure through thinned skin can mean removing the expander and starting that stage again later.
Refinement stages carry lower physical risk but a different one: the risk of chasing perfection. Each revision adds scar and healing time, and results plateau. Ask the surgeon where they think the point of diminishing returns lies.
Across all stages, ask what the team does to reduce each risk, what you can do, and what the early warning signs are. The answers should be concrete. Vague reassurance is itself a warning sign.
What are the alternatives to a staged reconstruction?
Agreeing to a plan is only meaningful if you know what you are not choosing. Ask the surgeon to lay out the alternatives, even the ones they do not favor, and to explain why they land where they do.
A single-stage reconstruction is sometimes possible, using a local flap or graft that can be completed in one sitting. It trades a faster finish for a possibly less refined match, a limit on defect size, or higher risk if margins are uncertain. Ask whether you are a candidate and what would be gained or given up.
Healing by secondary intention, which means leaving a wound to close on its own from the base and edges, works surprisingly well in some facial locations such as concave areas near the inner corner of the eye. It avoids an operation but takes weeks of wound care and may leave a different kind of scar.
A facial prosthesis, a custom-made silicone replacement for a nose, ear, or eye region, is a well-established option, particularly for larger defects or for people who prefer not to undergo multiple operations. Prostheses can be retained with adhesives or with small implants placed in bone. They need periodic replacement and daily care, and some people find them freeing while others find them a constant reminder.
Delaying reconstruction altogether, or stopping after a functional repair without cosmetic refinement, is also a legitimate choice. The NHS guidance on consent is clear that a decision to decline treatment must be respected when the person has the information and capacity to make it.
No alternative is automatically better. The useful question is which one fits your priorities, your health, and your tolerance for time and uncertainty.
Staged versus single-stage reconstruction: a side-by-side view
Numbers and durations in any individual plan come from your surgeon, but the trade-offs are fairly consistent across facial reconstruction. The table below summarizes what each approach tends to ask of you and what it tends to offer, drawing on the general descriptions in MedlinePlus and NHS plastic surgery guidance.
| Consideration | Staged plan | Single-stage plan |
|---|---|---|
| Typical use | Larger or multi-unit defects, uncertain margins, contaminated wounds, growth in children | Smaller defects with clear margins and good local tissue |
| Number of operations | Two or more, each with its own recovery | One, sometimes with a later minor revision |
| Time to final result | Months, often approaching a year once refinements are counted | Weeks to a few months as swelling settles |
| Intermediate appearance | Visible unfinished phases, possible pedicle or expander | Immediate closure, early swelling and bruising |
| Tissue match potential | Often higher, because expanded or carefully staged tissue can be chosen for color and texture | Limited by what is available next to the defect |
| Flexibility | Plan can adapt after each stage based on healing and pathology | Little room to adjust once closed |
| Cumulative anesthesia exposure | Spread across several shorter procedures | Concentrated in one longer procedure |
| Main emotional challenge | Living with an unfinished result between stages | Accepting a result that may be harder to refine later |
Reading the table, notice that the staged column trades time and visibility for control and match. Whether that trade is worth it depends on where the defect is, how much it affects function, and how you personally weigh a longer road against a more adaptable one. Those are questions only you can answer, but you can only answer them well once the surgeon has filled in the specifics for your case.
What the days and weeks after each stage usually look like
Recovery repeats with every stage, which is one reason the total commitment is easy to underestimate. The shape of it is fairly predictable.
The first few days bring swelling, bruising, and discomfort that is usually managed with the medicines your team prescribes; follow their instructions and raise any concerns with them rather than adjusting on your own. Keeping the head elevated, including when sleeping, reduces swelling in facial work. Dressings may need to stay dry and undisturbed until the first review. Grafts in particular are often secured under a bolster dressing, a padded dressing tied over the graft to hold it still, for several days while vessels grow in.
The first review, often within the first week, is when the team checks that tissue is alive and the wound is clean. Sutures on the face are typically removed within about a week, since facial skin heals quickly and early removal limits track marks. MedlinePlus describes graft donor sites healing over roughly one to two weeks for split-thickness grafts, with the grafted area itself needing protection for longer.
Weeks two through six are about settling. Swelling eases, color evens, and scars begin their long maturation. Scars are typically at their reddest and firmest in the early months before softening, a process that continues for a year or more, which is why refinement stages wait. Sun protection on new scars matters throughout this period because ultraviolet exposure can darken them permanently.
Between stages, your task is to heal, attend reviews, and report anything unexpected. Ask your team for written instructions specific to each stage, including activity limits and what wound appearance is normal, so you are comparing what you see against a real reference rather than against worry.
Questions to ask reconstructive surgeon teams about smoking, diabetes, and healing
Your general health shapes a staged plan more than any single surgical decision does, so it belongs in the conversation early. These are the questions to ask reconstructive surgeon teams about the factors you can influence.
If you smoke or vape nicotine, ask how long the team wants you to be nicotine-free before and after each stage, and whether that applies to all stages or mainly to flap work. Nicotine constricts the small vessels that new tissue depends on, and the NHS advises stopping before plastic surgery to reduce complications. Ask what help is available to stop; many hospitals have dedicated services, and your primary care team can refer you.
If you have diabetes, ask what level of control the team is looking for and how it will be checked. High glucose impairs the immune response and slows wound healing, and the CDC lists diabetes among the factors that raise surgical site infection risk. Coordination with whoever manages your diabetes is worth asking about, since changes to that management are theirs to make, not the surgeon’s.
Ask about any medicine you take that affects bleeding or immunity, including supplements. Do not stop anything on your own; ask the surgical team and the prescriber to agree on a plan and tell you what it is.
Ask whether prior radiotherapy, steroid use, or a connective tissue condition changes the approach. Radiation-treated skin heals less reliably and may push the surgeon toward tissue brought in from outside the field.
Nutrition is a quieter factor. Protein and overall intake support healing, and if you have lost weight recently or eat poorly, say so. A dietitian referral before a long staged plan is a reasonable thing to request.
Consent, second opinions, and the right to pause a reconstructive surgery consultation
Consent for a staged plan is not a single signature. Each stage should have its own discussion and its own consent, because circumstances change and so might your view. The NHS guidance on consent describes it as a process in which the person is given enough information about benefits, risks, and alternatives to make a voluntary decision, and in which that decision can be withdrawn. Ask your team how consent will be handled at each stage and whether you will see the same surgeon each time.
Ask for the plan in writing. A one-page summary listing each stage, its purpose, the approximate interval, and the person responsible is more valuable than any amount of verbal reassurance. If the surgeon cannot produce one, that is information too.
Second opinions are normal in reconstructive care, and a confident surgeon will not resent the request. Facial reconstruction involves judgment calls about donor sites, timing, and technique, and two experienced surgeons may reasonably propose different sequences. A second opinion is most useful when you bring the first plan with you and ask the second surgeon to comment on it specifically, rather than starting from scratch.
You can also pause. Nothing about an elective reconstruction requires you to commit to all stages at the first visit, and NHS guidance on cosmetic and reconstructive procedures explicitly encourages taking time rather than deciding under pressure. Between stages, if your priorities shift or your health changes, say so; the plan may be adjustable, shortened, or stopped at a functional end point.
Bring someone with you to consultations. A second set of ears catches what you miss, and the person who drives you home will remember the conversation differently from the person who was in the chair.
What people often get wrong about staged reconstruction surgery
A few misunderstandings come up so often that they are worth naming before they shape your expectations.
The first is that more stages means something went wrong. Usually the opposite is true: staging is designed in from the start because the biology demands it. A surgeon who proposes three stages has not failed to do it in one; they have judged that one would be less safe or give a poorer result. That said, an unplanned extra stage after a complication is different, and you are entitled to ask which kind of stage any addition is.
The second is that the final appearance is visible after the main stage. It is not. Swelling, scar redness, and flap bulk all improve over months, and judging a result in the first weeks leads to needless distress and, sometimes, to pushing for revisions the surgeon would advise against. Ask when a fair assessment is possible and hold your judgment until then.
The third is that reconstruction can restore the face exactly as it was. Reconstructive surgery restores form and function; it cannot return tissue that was lost, and every repair leaves some scar. Teams aim for a result that looks natural at conversational distance, not one that is invisible under close inspection. Unrealistic expectations are the most common source of dissatisfaction, which is why the NHS guidance on plastic surgery leads with the importance of understanding what is achievable.
The fourth is that the plan is fixed. It is a plan, not a contract with biology. Healing, pathology, and your own circumstances can all change it. The right response is not alarm but a conversation about what changed and why.
Last: treating the gaps between stages as dead time. They are when healing happens, and how you use them affects the next stage.
Questions to ask your care team before agreeing
Here is a consolidated list to take into the consultation. You will not need all of them, and your surgeon will likely answer some before you ask, but having them written down means the ones that matter to you do not get lost in the moment.
- Why is a staged plan recommended for me rather than a single operation?
- How many stages are planned, what is each one for, and what would add or remove a stage?
- What is the realistic end result, in terms of both function and appearance, and which scars will remain visible?
- What is the total time from the first stage to the final review, including recovery and waiting intervals?
- What will I look like and what will I be able to do between stages?
- Which stage carries the most risk, and what are the specific risks of each?
- What are the alternatives, including a prosthesis or stopping after a functional repair, and why do you favor this plan?
- What do you need from me regarding smoking, blood sugar, medicines, and nutrition, and who will help with those?
- How will consent be handled at each stage, and will I see the same surgeon throughout?
- Who coordinates the other specialists involved, and who do I contact between visits?
- Can I have the plan in writing, and can I see examples of intermediate stages for a similar case?
- What signs should make me call the team urgently?
Two habits make this list work. First, write the answers down during the appointment or ask whether you may record the discussion. Second, before leaving, repeat the plan back in your own words: “So stage one removes the tumor and waits for pathology, stage two brings tissue from the forehead, stage three divides it in about three weeks, and refinements come later.” If the surgeon corrects you, you have learned something important. If they nod, you have understood.
When to call your doctor
Across a staged plan, there are several recovery periods and several chances for something to go wrong early, when it is most fixable. Your team will give stage-specific instructions; these general red flags apply at any point.
Contact your surgical team the same day if you notice a flap or graft changing color, particularly turning dusky purple, pale white, or black at the edges, or if a flap feels cold or unusually firm. Those changes can mean the blood supply is compromised, and timing matters.
Call promptly for spreading redness around the wound, increasing rather than decreasing pain after the first few days, pus or foul-smelling drainage, a wound edge that opens, or a fever. The CDC describes redness, pain, drainage, and fever as the typical signs of a surgical site infection, and early treatment limits damage to the reconstruction.
Seek urgent care, by emergency services if needed, for bleeding that soaks through dressings and does not stop with firm pressure, rapidly increasing swelling that affects breathing or swallowing, sudden vision change after surgery near the eye, chest pain, breathlessness, or a swollen, painful calf, which can signal a blood clot after any operation.
Expander patients should also call for sudden pain, redness, or thinning skin over the device, or if it appears to be deflating.
Do not wait for the next scheduled review if something worries you. Teams would far rather see a wound that turns out to be fine than hear about a lost flap afterward. Keep the contact number for the on-call service somewhere you can find it, and know who covers when your surgeon is unavailable. Every decision about what to do next belongs to the treating team, and the sooner they know, the more options they have.
Frequently asked questions
What are the most important questions to ask a reconstructive surgeon about a staged plan?
Ask why staging is needed for you, how many stages are planned and what each is for, what the realistic end result is, how long the whole plan takes, what you will look like between stages, which stage carries the most risk, and what the alternatives are. Ask for the plan in writing and for time to decide before committing.
What should I ask a plastic surgeon about scars after facial reconstruction?
Ask where every scar will sit, including at donor sites, which ones are likely to remain visible at conversational distance, and how long scars typically take to fade. Facial scars are usually reddest in the early months and continue to soften for a year or more, which is why scar revision, if offered at all, is scheduled after that maturation period.
How long does staged reconstruction surgery take from start to finish?
It depends on the number of stages and the healing intervals between them, which your surgeon should estimate for your case. Plans involving flaps that need division or tissue expanders filled over weeks commonly span many months, and once late refinements are counted the full timeline can approach a year. Treat any figure as a typical range rather than a promise.
Is it normal to want a second opinion before a reconstructive surgery consultation plan is finalized?
Yes. Facial reconstruction involves judgment calls about donor sites, timing, and sequence, and experienced surgeons can reasonably differ. A second opinion is most useful when you bring the first plan and ask the second surgeon to comment on it directly. A confident surgeon will not object to the request, and you are not obliged to explain it.
Why can't my surgeon just do everything in one operation?
Sometimes they can, and it is worth asking whether you are a candidate. Staging is chosen when a flap must stay attached to its blood supply before division, when skin needs expanding to match the face, when pathology margins are pending, or when a wound is still evolving. Doing it all at once in those situations raises the risk of tissue loss or of rebuilding over residual disease.
What happens if a stage does not heal properly?
Partial loss of a graft or flap edge is more common than total loss and often heals with dressings and time, though it may add a revision. Infection is treated early to protect the reconstruction. Expanders that become infected or exposed are usually removed and the stage repeated later. Ask your team in advance what the fallback is for each stage so a setback is not a surprise.
Do I have to stop smoking for every stage, or just the main one?
Ask your team, because requirements vary with the type of surgery. Stages that move tissue with its blood supply are the most nicotine-sensitive, since nicotine narrows the vessels the tissue depends on, and many surgeons will not perform flap surgery on active smokers. Most teams prefer you to remain nicotine-free throughout the plan, and hospitals and primary care can help with stopping.
What will I look like between stages of a nasal reconstruction?
It depends on the technique, so ask for specifics and, if possible, photographs of a typical intermediate stage. With a forehead flap, a visible bridge of tissue connects the forehead to the nose until it is divided at a later stage. With an expander, a bulge grows under the skin over weeks. Knowing this beforehand makes the interval far easier to manage.
Can I change my mind partway through a staged plan?
Yes. Consent is given for each stage, not for the whole plan at once, and it can be withdrawn. If your priorities or health change, tell your surgeon; the plan may be shortened, paused, or stopped at a functional end point. The treating team can explain what each option means for your result, but the decision remains yours.
What signs after a stage mean I should call the surgeon right away?
Call the same day for a flap or graft that turns dusky, pale, or black, or feels cold; for spreading redness, worsening pain, pus, fever, or a wound that opens; and for an expander that becomes painful, red, or exposed. Seek emergency care for heavy bleeding, swelling that affects breathing, sudden vision change, chest pain, breathlessness, or a swollen painful calf.
References
- NHS: Plastic surgery
- NHS: Consent to treatment
- MedlinePlus: Skin graft
- MedlinePlus: Plastic and Cosmetic Surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Cryotherapy Results: How Treated Skin Looks Once Healed and Why Repeat Sessions Happen
Cryotherapy results depend on what was frozen. For warts, sun-damaged patches and other skin growths, the treated area blisters, crusts and sheds within roughly…
Cryotherapy vs Surgical Removal for Skin Lesions: Why Pathology Sometimes Wins
Cryotherapy freezes a skin lesion with liquid nitrogen and leaves nothing for a laboratory to examine, while surgical excision removes the tissue intact so…

Dermabrasion Recovery: The Raw Days, Ointments and When Redness Finally Fades
Dermabrasion recovery time typically runs in stages: the treated skin is raw, red and weeping for the first days, new skin usually covers the…

Sun Protection After Dermabrasion: Why Strict Cover Matters for Months, Not Days
Sun protection after dermabrasion needs to continue for months, not days, because the newly grown skin is thin and its pigment cells are easily…

What Happens During an IPL Photorejuvenation Session: Cooling Gel, Flashes and Timing
During an IPL photorejuvenation session, a clinician cleanses the skin, applies a cool clear gel, gives you protective eyewear, and passes a handpiece across…

Why Your Cold Sore History Matters Before Laser Resurfacing and How Doctors Prepare for It
Your cold sore history matters before laser resurfacing because the herpes simplex virus that causes cold sores stays dormant in facial nerves and can…