

Recovering From Jaw Cyst Removal: Swelling, Cold Compresses and Monitoring the Bone
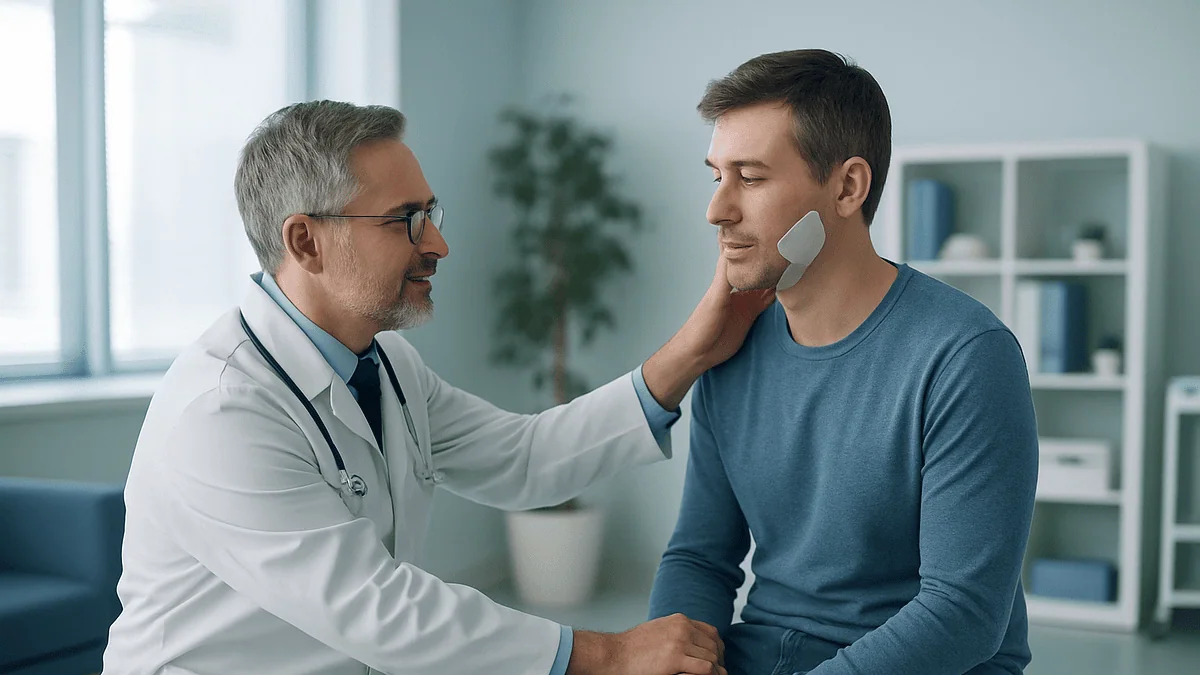
Key Takeaways
- Facial swelling after jaw cyst surgery typically peaks on day two or three, not on the day of the operation, so a worse-looking morning on day two is the expected pattern rather than a warning sign.
- Cold compresses do most of their work in the first day or two by narrowing blood vessels before fluid collects; used later, they add little and risk injuring numbed skin.
- The gum usually seals within about two weeks, but the bone cavity fills in over many months to a couple of years, which is why follow-up X-rays continue long after you feel normal.
- Odontogenic keratocysts have a recognized tendency to recur, sometimes years later and without symptoms, so laboratory confirmation of the cyst type shapes how long you are monitored.
- Suction and heat dislodge the protective blood clot: no straws, spitting, smoking or hot drinks in the first day is the single most effective piece of early aftercare.
- Numbness of the lip or chin after lower-jaw cyst removal most often reflects nerve bruising and commonly improves over weeks to months, but it should always be reported and tracked.
Jaw cyst surgery recovery usually happens in two stages. Soft tissue swelling and soreness are typically worst in the first two to three days, ease with cold compresses, rest and prescribed pain relief, and settle over one to two weeks. The bone cavity left behind fills in far more slowly, over many months, so surgeons monitor it with periodic X-rays. Any decisions about medicines or follow-up rest with your treating team.
The X-ray had been up on the screen for perhaps ten seconds before she noticed it herself: a smooth, dark oval sitting under a molar, like a bubble trapped in the bone. No pain. No lump she could feel. She had come in for a routine check and was leaving with a word she had to look up in the car park.
That is how most jaw cysts announce themselves, quietly and by accident, which is one reason the weeks after surgery feel so disorienting. The operation is often shorter than people expect. The swelling is often bigger than they expect. And then comes the strange part of jaw cyst surgery recovery: the wound in the gum heals in a fortnight, while the hollow in the bone takes months to fill, tracked by X-rays you cannot feel or see.
This guide walks through those two clocks, the fast one and the slow one, with the evidence behind each stage and honest answers to the questions people type into search engines late at night.
How serious is a jaw cyst, and what happens if it is left untreated?
A jaw cyst is a closed sac in the jawbone, lined with tissue and filled with fluid or semi-solid material. Most begin from remnants of the cells that once formed teeth, which is why dentists call them odontogenic cysts. The commonest examples, according to Mayo Clinic, are dentigerous cysts that form around the crown of an unerupted tooth, radicular cysts that grow at the tip of a tooth whose nerve has died, and odontogenic keratocysts, which behave more aggressively and have a known tendency to come back after removal.
Seriousness depends less on the word cyst and more on three things: what type it is, how large it has grown, and what sits next to it. The overwhelming majority are benign, meaning they are not cancer and do not spread to other parts of the body. That said, benign does not mean harmless. A cyst grows by slowly pushing bone aside and, as Mayo Clinic explains, an untreated one can hollow out enough bone to weaken the jaw, push neighboring teeth out of position, damage their roots, or press on the nerve that runs through the lower jaw. Cysts that connect to a dead tooth can also become infected, turning a silent finding into a painful, swollen abscess.
The practical answer to what if it is left untreated is therefore: it usually keeps growing, and the operation needed later tends to be larger than the one needed now. A small cyst can often be lifted out through the gum. A large one may involve teeth, nerves or the thin floor of the sinus above the upper molars. Your surgeon will have examined the X-ray or CT scan and, in most cases, sent a sample for laboratory analysis, since only a pathologist looking at the lining under a microscope can confirm exactly which type of cyst it was.
How jaw cyst removal works: enucleation, marsupialization and decompression
Three techniques cover almost every jaw cyst operation, and the one your team chooses shapes how your recovery unfolds.

Enucleation means removing the entire cyst, lining and all, in one piece. The surgeon opens the gum, removes a small window of bone if the cyst has not already thinned it, peels the sac away from the cavity walls, and closes the gum with stitches. Small and medium cysts are often treated this way in a single visit, frequently under local anesthetic, sometimes with sedation or general anesthesia for larger or awkward ones, as Mayo Clinic describes in its overview of jaw cyst treatment.
Marsupialization takes the opposite approach for very large cysts. Rather than removing the sac, the surgeon creates an opening into it and stitches the lining to the gum, so the cavity stays open to the mouth. Pressure inside the cyst drops, the cavity slowly shrinks from the walls inward, and bone regrows behind it. Months later, a smaller second operation may remove what remains.
Decompression is a close cousin: a small tube or stent is placed into the cyst so fluid can drain and the cavity can shrink, again followed by definitive removal once the cyst is smaller and safer to take out.
Which approach you had matters for the weeks ahead. After enucleation, your job is mainly to protect a closed wound and let the bone fill in. After marsupialization or decompression, you will also be irrigating an opening or tube daily and attending more frequent reviews. Sometimes a tooth whose root sits inside the cyst is removed at the same time, or its root tip is trimmed and sealed, a procedure called an apicoectomy. Ask your surgeon which of these applied to you; the aftercare sheet you were given will make far more sense once you know.
Who is usually offered surgery now, and who is asked to wait?
Not every jaw cyst goes straight to the operating room, and being told to wait is not the same as being told nothing is wrong.
Surgery is usually recommended promptly when the cyst is growing on serial X-rays, has become infected, is displacing or eroding the roots of teeth, is large enough to thin the jaw, or when the imaging appearance raises the possibility of a keratocyst or a benign tumor such as ameloblastoma. Mayo Clinic notes that biopsy or removal is often needed simply because different cysts and tumors can look alike on a scan, and the right long-term plan depends on the laboratory result.
A period of observation may be suggested for small, symptom-free findings around a tooth that is still expected to erupt, or where a tiny radicular cyst is likely to resolve after root canal treatment removes its source. The interval between check X-rays is set by the treating team.
Some people are asked to wait for their own safety rather than because of the cyst. Common reasons include an active infection that needs settling first, blood-thinning medicines that the prescribing clinician wants to review, uncontrolled diabetes that slows healing, recent heart events, or pregnancy, where non-urgent surgery is often deferred. People taking certain medicines for osteoporosis or cancer that affect bone turnover are assessed carefully because of a rare but serious healing complication in the jaw; that conversation belongs with your doctor and surgeon together, and no one should stop a prescribed medicine on their own.
Children and teenagers deserve a mention. Dentigerous cysts around developing teeth are common in this group, and surgeons sometimes favor marsupialization so that the trapped tooth can still erupt rather than being sacrificed. Recovery for a child follows the same principles as for an adult: comfort, soft food, gentle hygiene and follow-up imaging.
What actually happens on the day and the first night at home
Most people are surprised by how ordinary the day feels. You arrive, confirm which side is being operated on, and the anesthetic is given. Under local anesthetic alone you will feel pressure and vibration but not pain; with sedation you may remember very little. A straightforward enucleation often takes well under an hour, though large or deep cysts take longer.

You leave with stitches in the gum, which are frequently the dissolving kind, and a gauze pad to bite on for the first short while. Your face may already look asymmetrical from the local anesthetic and the early fluid shift into the tissues.
The first night is about three things. First, protecting the blood clot that seals the socket or cavity: no vigorous rinsing, spitting, straws or smoking, because suction and heat can dislodge it. MedlinePlus advises this same caution after any tooth-socket surgery. Second, controlling swelling before it builds, which is where cold compresses earn their place, discussed in detail below. Third, keeping your head elevated on an extra pillow or two, since lying flat lets more fluid pool in the operated side.
A little blood-tinged saliva is normal. Pain typically becomes noticeable as the local anesthetic wears off over a few hours, which is why surgeons often suggest taking the first dose of prescribed pain relief before that happens rather than chasing the pain later. The specifics of which medicine, how much and how often belong entirely to your prescribing clinician and the written instructions you were given.
If you had sedation or a general anesthetic, plan for someone to take you home and stay with you overnight. Coordination, judgment and memory are dulled for the rest of the day even when you feel alert.
What is the worst day after jaw cyst surgery, and why is swelling delayed?
Search data show this is one of the most common questions people ask, and the honest answer surprises them: the worst day is usually not the day of surgery.
Swelling is the body’s inflammatory response to injury. When tissue is cut, small blood vessels leak plasma, immune cells arrive, and chemical messengers widen local vessels further. This process ramps up over hours rather than minutes. Both NHS and Mayo Clinic guidance on oral surgery recovery describe facial swelling as worst during the first two to three days before it gradually improves, so the morning of day two or three is when most people look in the mirror and feel alarmed. The cheek can be visibly rounded, the skin tight and shiny, and opening the mouth stiff.
Bruising follows a similar but slower curve. Blood that has tracked down through the tissues may appear as a yellow-green patch along the jawline or neck several days later, sometimes lower than the operation site because gravity moves it. This looks dramatic and is almost always harmless.
Pain generally peaks alongside the swelling and then eases. Jaw stiffness, medically called trismus, tends to be most noticeable around the same time because the chewing muscles were stretched and are now bathed in inflammatory fluid.
Knowing the shape of this curve is genuinely useful. If day two is worse than day one, that is the expected pattern, not a sign that something has gone wrong. The pattern to watch for is the reverse: swelling that was settling and then begins to grow again after day four or five, or pain that is worsening at a point when it should be fading. Those changes can signal infection or a lost blood clot and belong in the red-flag section at the end of this article.
Swelling after jaw cyst removal: how cold compresses help and how to use them safely
Cold works on swelling through simple physics and physiology. Chilling the skin narrows the small blood vessels underneath, which reduces the amount of fluid leaking into the tissues while inflammation is at its most active. It also numbs superficial nerve endings, taking the edge off soreness without any medicine at all.
Timing matters more than most people realize. Cold is most useful in the first day or two, while the swelling is still building; once fluid has already collected, chilling the skin does much less. MedlinePlus and NHS aftercare advice for oral surgery both describe applying a cold cloth or wrapped ice pack to the outside of the face during this early window.
A few practical points keep it safe:
- Always put a thin towel between ice and skin. Numbed, freshly operated skin cannot warn you it is getting too cold.
- Use cycles rather than continuous cold. Many surgical teams suggest roughly 15 to 20 minutes on, then a similar break; follow the interval your own team gave you.
- Keep the compress on the cheek over the surgical site, not in the mouth.
- Stop if the skin becomes blotchy white or you feel burning.
After the first couple of days, some surgeons switch their advice to gentle warmth, since warm compresses improve blood flow and can help the collected fluid drain and the stiff muscles loosen. Others do not. This is one of the questions worth asking before you leave the clinic, because advice varies with the size and site of the cyst.
One more point: cold compresses reduce swelling, but they do not prevent it. Some degree of facial fullness after jaw surgery is normal healing, not a failure of your aftercare.
Jaw cyst surgery recovery timeline: what the first two weeks usually look like
Every recovery is individual, and the ranges below are typical patterns drawn from NHS and Mayo Clinic guidance on oral surgery healing, not promises. Large cysts, marsupialization, simultaneous tooth removal or a second surgery all stretch the timeline.
| Stage | What usually happens | What you are usually doing |
|---|---|---|
| Day 0 | Numbness fades over hours; oozing settles; swelling begins | Biting on gauze, cold compresses, head elevated, soft cold food |
| Days 1 to 3 | Swelling and soreness peak; bruising may appear; mouth opening stiff | Cold compresses in cycles, prescribed pain relief, gentle salt-water rinses from day 1 or 2 if advised |
| Days 4 to 7 | Swelling visibly easing; eating becomes easier; bruise changes color | Gradually firmer soft foods, careful brushing near the site, return to desk work for many |
| Weeks 2 to 3 | Gum largely closed; dissolving stitches gone or removed; stiffness resolving | Near-normal diet, first surgical review, resumption of most activity |
| Months 3 to 24 | Bone gradually fills the cavity, visible on X-rays | Periodic imaging appointments set by the surgeon |
NHS advice for wisdom tooth removal, a comparable operation on the jawbone, describes recovery from the soft-tissue part taking up to two weeks, with swelling, stiffness and tenderness improving steadily across that period. Most people are back to routine work within a few days to a week, depending on how physical their job is and how much sedation they had. Strenuous exercise is commonly held back for about a week because raising blood pressure and heart rate can restart bleeding and worsen swelling.
Two features of this timeline deserve emphasis. Progress is not perfectly linear; a tiring day can leave the jaw more swollen the next morning. And the last row is where jaw cyst surgery differs from a simple extraction: the visible recovery ends in weeks, but the structural recovery continues quietly for a very long time.
How long does it take to heal from jaw cyst surgery? Soft tissue versus bone
Ask three people who have had this operation and you may get three different answers, because they are measuring different things.
The gum heals first. Epithelium, the surface layer of the mouth’s lining, grows across a clean wound edge quickly, and the mucosa is generally sealed within about two weeks, in line with the NHS recovery timeframe for comparable oral surgery. From that point food no longer packs into an open wound, and the risk of a lost clot has passed.
The muscles and nerves come next. Chewing muscles that were stretched during surgery regain their range over a few weeks. If the nerve supplying the lower lip and chin was bruised, tingling or numbness may take weeks or months to settle, which is covered in its own section below.
The bone is the slow clock. After enucleation, the empty cavity first fills with a blood clot, which is gradually replaced by soft fibrous tissue, then by immature woven bone, and finally by dense mature bone remodeled along the lines of chewing stress. On an X-ray, the cavity starts as a dark hollow and becomes progressively grayer and then indistinguishable from the surrounding jaw. Mayo Clinic notes that regular follow-up is part of standard care after jaw cyst removal precisely because this process, and any sign of recurrence, can only be judged on imaging over time. Small cavities fill faster than large ones, younger bone faster than older, and the lower jaw generally more slowly than the upper.
So when someone asks how long healing takes, the layered answer is: comfortable in days, sealed in weeks, structurally restored over many months to a couple of years, and considered settled only when your surgeon is satisfied with the follow-up images. That last judgment belongs to the treating team, not to a calendar.
Bone healing after cyst removal: how surgeons monitor the cavity and why it matters
The monitoring that follows a jaw cyst operation confuses many patients because nothing hurts, nothing looks wrong, and yet the appointments keep coming. There are three separate reasons for them.
The first is confirming the diagnosis. The cyst lining is sent for histopathology, the microscopic examination of tissue, and the result usually arrives a week or two after surgery. It settles whether this was a simple dentigerous or radicular cyst, a keratocyst, or, occasionally, something the surgeon did not expect. That result decides how long and how closely you will be followed.
The second is watching the bone fill in. Periodic plain X-rays, and sometimes a cone-beam CT scan, let the surgeon compare the size and density of the cavity against the last image. Steady shrinkage is the expected pattern. A cavity that stops shrinking or begins to enlarge is a signal to look more closely.
The third is checking for recurrence. Mayo Clinic highlights that some types, keratocysts in particular, have a meaningful tendency to return, sometimes years after an apparently complete removal, and that follow-up examinations are a standard part of care rather than an optional extra. Recurrences are usually painless at first and are picked up on imaging long before they cause symptoms, which is exactly why attending a review when you feel perfectly well is worthwhile.
For very large defects, some surgeons place a bone graft or a bone substitute at the time of surgery to support healing, while others rely on the jaw’s own capacity to regenerate. Both approaches are used in mainstream practice, and neither is inherently superior for every case; the choice depends on the size and position of the cavity, the risk of fracture and the surgeon’s assessment. If a graft was used, your follow-up imaging will also be checking that it is integrating.
Eating, brushing and keeping the wound clean without disturbing it
The mouth is a difficult place to heal. It is warm, wet, full of bacteria and used many times a day. The aftercare advice you were given is designed around that reality rather than around comfort alone.
For the first two or three days, cool, soft foods do double duty: they need little chewing and they soothe. Yogurt, smoothies eaten with a spoon, lukewarm soups, mashed vegetables and scrambled eggs are typical suggestions. Very hot food and drink are avoided early on because heat dilates blood vessels and can restart oozing, a point MedlinePlus makes in its guidance on tooth-socket care. Crunchy, seedy or sharp foods are kept back until the gum has closed, since fragments can lodge in the wound.
Chewing on the opposite side is sensible, but most people naturally do this anyway. What people forget is hydration: the reluctance to drink because the mouth is sore is common, and dehydration slows healing and worsens headaches.
Oral hygiene is a balancing act. Brushing the rest of the mouth from the first evening is encouraged, because plaque left to build increases infection risk everywhere. The operated area itself is treated gently, usually with a soft brush around rather than on the stitches for the first several days. Gentle warm salt-water rinses, typically started the day after surgery and repeated after meals, help clear debris without the chemical harshness of many commercial mouthwashes; the NHS describes this approach in its wisdom-tooth recovery advice. Some surgeons prescribe an antiseptic mouth rinse instead; use whichever your team advised.
Smoking deserves a blunt sentence. It reduces blood flow to the healing gum and bone, raises infection risk and is a leading cause of the painful lost-clot complication. If there is ever a fortnight to stop, this is it, and your care team can point you to support.
Pain, numbness and the other things people are not warned about
Discomfort after jaw cyst removal is real but usually manageable, and understanding what is happening reduces the anxiety that amplifies it.
Pain relief. Most surgical teams use ordinary over-the-counter analgesics, sometimes in combination and sometimes with a short course of a stronger prescription medicine for the first day or two. Anti-inflammatory painkillers work by damping the chemical cascade that drives both pain and swelling; simple analgesics act mainly on pain signaling. Which medicines are appropriate for you, in what amounts and for how long, depends on your other health conditions and prescriptions and is decided by your prescribing clinician. Do not add or combine medicines without checking with them.
Numbness. The lower jaw carries a nerve that supplies feeling to the lower lip, chin and teeth on that side. Cysts in the lower jaw often sit right against it. Bruising or stretching of this nerve during surgery can leave the lip or chin numb or tingling. Mayo Clinic lists nerve injury among the recognized risks of jaw cyst and tumor surgery. In most cases the sensation returns gradually over weeks to months as the nerve recovers, though in a small number of cases some change is permanent. Persistent numbness should always be reported at follow-up so it can be tracked.
Teeth. Teeth next to the cyst may feel loose, tender to bite on or oddly sensitive for a while. Some may have lost their nerve supply because of the cyst itself and later need root canal treatment. If a tooth was removed, the gap may eventually be addressed with a bridge, denture or implant once the bone has matured, a decision for many months down the line.
Sinus symptoms. After upper-jaw cysts, a stuffy nose or a little blood from the nostril on that side can occur if the thin sinus floor was involved. Avoid blowing your nose forcefully and mention it at review.
What people often get wrong about jaw cyst surgery recovery
Several beliefs circulate widely enough to deserve direct correction.
Myth: if the swelling is getting worse on day two, something has gone wrong. As described above, peak swelling at 48 to 72 hours is the expected course in NHS and Mayo Clinic guidance. The concerning pattern is swelling that had improved and then returns.
Myth: ice should be used until the swelling is gone. Cold is most effective during the first day or two while swelling is building. Prolonged icing beyond that adds little and risks skin injury over numbed tissue.
Myth: once the stitches are out, you are healed. The gum is healed. The bone cavity underneath is at the very start of a process that continues for many months and is checked with imaging. Skipping the follow-up X-rays because you feel fine is the single most common way a recurrence is missed.
Myth: a benign cyst does not need removing. Benign refers to whether it can spread to other organs, not to whether it can damage the jaw. Untreated cysts enlarge, weaken bone and threaten neighboring teeth and nerves, as Mayo Clinic’s overview of jaw cysts makes clear.
Myth: rinsing hard keeps the wound clean. Forceful rinsing, spitting and drinking through straws in the first day can dislodge the protective clot. Gentle is the operative word, and only from the time your team advised.
Myth: the more antibiotics, the safer. Antibiotics are used when there is infection or a specific reason to prevent it, not routinely for every jaw operation. Whether you need them is your surgeon’s decision; taking leftover courses from home is unsafe.
Myth: numbness means the nerve was cut. Most post-operative numbness reflects bruising or stretching, and sensation commonly returns over weeks to months. Report it, track it, but do not assume the worst.
Questions to ask your care team before you leave the clinic
The ten minutes after surgery, when you are sore and possibly sedated, are a poor time to absorb instructions. Bring this list to your pre-operative visit or hand it to whoever is accompanying you.
- Which operation did I have: full removal, marsupialization or decompression? Was a tooth removed or root-treated at the same time?
- Was anything placed in the cavity, such as a graft, a dressing or a drainage tube, and does it need care at home?
- When will the laboratory result on the cyst lining be available, and how will I be told?
- What is the follow-up imaging plan: how often, for how long, and what would prompt an earlier scan?
- How should I use cold compresses, for how many days, and should I switch to warmth afterwards?
- Which pain relief do you want me to use, and which of my regular medicines should I continue exactly as prescribed?
- When can I start salt-water rinses, brush near the site and return to a normal diet?
- What activity restrictions apply, and for how long, for work, exercise and driving?
- Is there any risk to the nerve or sinus on my side, and what sensations should I report?
- Are my stitches dissolving, or do I need an appointment to have them removed?
- Which teeth near the cyst might need treatment later, and who will monitor them?
- Who do I contact after hours if something worries me, and what symptoms mean I should not wait until morning?
Write the answers down. Recovery advice varies between surgeons for good reasons, and the instructions from the person who saw the inside of your jaw outrank anything written for a general audience, including this article.
When to call your doctor: red flags after jaw cyst removal
Most recoveries are uneventful, and the pattern is reassuring: a rough first three days, then steady improvement. Contact your surgical team, dentist or doctor the same day if the pattern breaks in any of the following ways.
- Bleeding that does not stop after firm pressure with gauze for a sustained period, or that starts again heavily after settling.
- Swelling or pain that worsens after day three or four, having previously improved, or swelling that spreads toward the eye, down the neck or under the tongue.
- Fever, chills or feeling generally unwell, or a foul taste and pus from the wound; MedlinePlus and Mayo Clinic list these as signs of infection after oral surgery.
- Severe, throbbing pain radiating to the ear several days after surgery, with an empty-looking socket, which can indicate a lost blood clot.
- Difficulty opening the mouth that is getting worse rather than better, or difficulty swallowing or breathing. Any breathing difficulty is an emergency: call emergency services.
- Numbness that is spreading, or altered sensation that has not begun to change within the period your surgeon told you to expect.
- A hard lump, movement of teeth or a change in how your teeth meet in the weeks or months afterward.
- Fluid from the nose when drinking after upper-jaw surgery.
- Signs of a reaction to a medicine, such as a rash, facial or tongue swelling, or wheezing.
Trust the instinct that something is off even if it is not on this list. Surgical teams would far rather hear about a false alarm on day five than about a spreading infection on day nine. And in the longer term, attend every imaging review you are offered, even years later, because the quietest recurrences are the ones caught early.
Frequently asked questions
What is the jaw cyst removal recovery time for most people?
Most people feel comfortable within a few days and have a healed gum within about two weeks, based on NHS guidance for comparable oral surgery. Bone healing is far slower and is judged on X-rays over many months. Large cysts, marsupialization or simultaneous tooth removal lengthen the timeline, and your surgeon’s assessment of your imaging decides when recovery is complete.
What is the worst day after jaw cyst surgery?
Day two or three is usually the hardest, because inflammatory swelling builds over 48 to 72 hours before it starts to fall, as NHS and Mayo Clinic aftercare guidance describes. Pain and jaw stiffness tend to peak at the same time. Improvement from then on is expected; swelling that returns after day four should be reported.
How serious is a jaw cyst?
Most jaw cysts are benign, meaning they cannot spread to other organs, but they are not harmless. Left in place they enlarge, thin the jawbone, displace or damage teeth and can press on nerves or become infected. Seriousness depends on the type confirmed by laboratory analysis, the size, and what structures sit nearby, all of which your surgeon will explain.
What happens if a jaw cyst is left untreated?
An untreated cyst usually continues to grow slowly. Mayo Clinic notes that this can weaken the jaw, move or damage neighboring teeth and, in some types, return or transform after long neglect. Cysts linked to a dead tooth may also become infected. Delay generally means a larger operation later, though small stable findings are sometimes monitored on your surgeon’s advice.
How long does swelling after jaw cyst removal last?
Swelling typically peaks at two to three days and then eases steadily over the following week, with most facial fullness gone within about two weeks according to NHS oral surgery recovery guidance. Bruising can appear later and drift down the neck before fading. Cold compresses in the first day or two and sleeping with the head raised help limit how much builds.
How long should I use cold compresses after jaw surgery?
Cold is most useful during the first day or two, while swelling is still forming. Aftercare guidance from MedlinePlus and the NHS describes applying a wrapped ice pack or cold cloth to the face in short cycles with breaks in between. After that, some surgeons suggest gentle warmth to help drainage and stiffness. Follow the specific timing your own team gave you.
How do surgeons check bone healing after cyst removal?
They compare periodic X-rays, and sometimes cone-beam CT scans, against earlier images. A healing cavity gradually shrinks and turns from a dark hollow to the same gray density as the surrounding bone. The same images check for recurrence, which is usually silent. Mayo Clinic describes regular follow-up examinations as a standard part of jaw cyst care.
Will the hole in my jaw fill in on its own?
In most cases, yes. The cavity first fills with a blood clot, then fibrous tissue, then new bone that matures over many months. Very large cavities take longer and may be supported with a graft or bone substitute at the surgeon’s discretion. Only follow-up imaging can confirm the process is complete, so the appointments continue even when you feel well.
Why is my lip or chin numb after jaw cyst surgery?
Cysts in the lower jaw often lie against the nerve that supplies feeling to the lip and chin, and it can be bruised or stretched during removal. Mayo Clinic lists nerve injury as a recognized risk of this surgery. Sensation usually returns gradually over weeks to months, though occasionally some change persists. Report any numbness so your team can track it.
Can a jaw cyst come back after it is removed?
Some types can. Odontogenic keratocysts in particular have a known tendency to recur, sometimes years after complete removal, which is why Mayo Clinic emphasizes long-term follow-up. Simple dentigerous and radicular cysts recur far less often once fully removed and any related tooth is treated. The laboratory report on the cyst lining determines how long you are monitored.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Bleeding Gums Myths: Stopping Brushing, Harder Brushing and Other Habits to Unlearn
Bleeding gums are usually a sign of gingivitis, early gum inflammation caused by plaque, not a reason to stop brushing or to scrub harder.…

How Dental Lasers Work: What Focused Light Changes for Gum Treatment and Small Cavities
Dental lasers work by emitting a single wavelength of light that particular tissues absorb: water inside enamel and dentin for hard-tissue lasers, and pigment…

Who May Not Suit Teeth Whitening? Crowns, Gum Disease, Pregnancy and Grey Discoloration
People usually asked to wait or skip teeth whitening include anyone with untreated gum disease, cavities or cracked teeth, those who are pregnant or…

What Happens at a Composite Bonding Appointment: Shade Matching, Layering and Polishing
A composite bonding procedure usually takes 30 to 60 minutes per tooth and rarely needs an injection. The dentist selects a resin shade against…

Bleeding Gums and Blood Thinners: What Your Dentist Checks Before Gum Treatment
Blood thinners do not cause gum disease, but they can make inflamed gums bleed longer and more visibly. Before gum treatment, a dentist reviews…

Clear Aligner Problems to Watch: Tracking Issues, Sore Spots and Gum Irritation
Most clear aligner problems are minor and fixable: trays that stop fitting usually reflect too few hours of wear, sore spots come from pressure…