

Robotic vs Laparoscopic Bariatric Surgery: How Surgeons Decide Which Approach Fits You
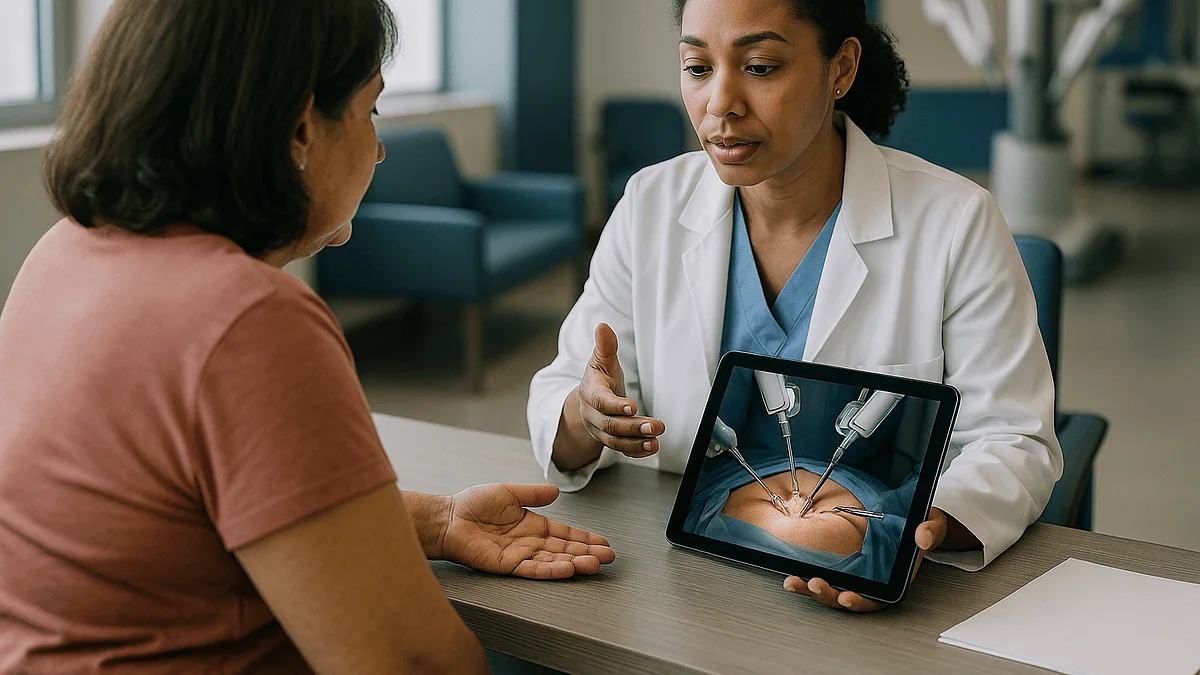
Key Takeaways
- Robotic and laparoscopic bariatric surgery perform the same operation through similar small incisions; the difference is whether the surgeon controls instruments by hand or from a console.
- In robot-assisted surgery the machine has no autonomy: every movement is made by the surgeon, with tremor filtered and a magnified three-dimensional view.
- Large registry comparisons show broadly similar rates of serious complications between the two approaches, with robotic cases consistently taking longer in the operating room.
- The robot is used most often for gastric bypass, revision surgery and very high BMI, where wristed instruments help with suturing and difficult anatomy; routine sleeves are usually laparoscopic.
- The NHS describes a hospital stay of a few days and a recovery of roughly four to six weeks after weight-loss surgery, ranges that apply to both approaches.
- Weight loss and diabetes improvement depend on the operation chosen and on long-term follow-up, not on the platform used to perform it.
Robotic and laparoscopic bariatric surgery are both minimally invasive; the difference is how the surgeon controls the instruments, not what is done to the stomach. Large comparisons show similar safety and weight outcomes overall, with robotic cases often taking longer in the operating room. Surgeons usually decide based on body build, prior operations, procedure complexity, their own training, and hospital equipment, not on which approach is newer.
The pamphlet on the kitchen table has two columns. One says “laparoscopic.” The other says “robotic,” with a photograph of a sleek machine that looks like it belongs in an aerospace lab. Marcus, who has spent eighteen months preparing for weight-loss surgery, keeps flipping between them, trying to work out whether picking the wrong column would be a mistake he lives with forever.
It is one of the most common worries a bariatric coordinator hears. The question of robotic vs laparoscopic bariatric surgery has a way of feeling like a choice between old and new, cautious and cutting-edge. In practice, it is closer to choosing between two well-made tools for the same job.
This explainer walks through what each approach involves, what the evidence honestly shows about safety and recovery, and the factors that move a surgeon toward one method or the other. The decision, as with every part of a bariatric pathway, rests with the treating team, but understanding their reasoning tends to make the conversation far less frightening.
What does "robotic vs laparoscopic bariatric surgery" actually mean?
Start with what the two approaches share. Both are forms of minimally invasive surgery, which means the operation happens through several small incisions rather than one long cut across the abdomen. Both use a thin camera and long, slender instruments passed through narrow tubes called ports. Both are used to perform the same underlying procedures, most often a sleeve gastrectomy or a gastric bypass.
The word laparoscopic describes the surgeon holding those long instruments directly, guiding them by hand while watching a video monitor. Laparoscopy has been the standard for bariatric surgery for decades, and the Mayo Clinic describes it as the usual method for most weight-loss operations because it typically means less pain and a shorter hospital stay than open surgery.
Robotic surgery, sometimes called robot-assisted laparoscopy, adds a layer between hand and instrument. The same small ports are placed, but the instruments are attached to mechanical arms. The surgeon sits at a console a few feet away, looking into a magnified, three-dimensional view and moving hand controls that the machine translates into movements at the instrument tips. The Cleveland Clinic is careful on one point that reassures many patients: the robot does not operate on its own or make any decisions. It is a very precise extension of the surgeon’s hands.
So the comparison is not between two different operations. A robotic sleeve gastrectomy removes the same portion of stomach as a laparoscopic one. A robotic gastric bypass creates the same small pouch and the same rerouted intestine. What differs is the control system, the ergonomics for the surgeon, the time the case takes, and, in some situations, how well the tools cope with a difficult anatomy. Keeping that distinction clear is the single most useful thing a patient can carry into the consultation.
How does laparoscopic weight-loss surgery work, step by step?
Picture the abdomen as a tent that needs to be pitched before anyone can work inside it. After general anesthesia, the surgeon introduces carbon dioxide gas to lift the abdominal wall away from the organs, creating a working space. Usually four to six small incisions follow, each roughly the width of a fingertip, according to MedlinePlus descriptions of laparoscopic gastric bypass.

Through one port goes the laparoscope, a slim telescope with a light and camera at its tip. Through the others go graspers, staplers and energy devices that seal tissue. The surgeon stands at the bedside, watching a high-definition screen while an assistant holds the camera steady and adjusts the view on request.
For a sleeve gastrectomy, the surgeon frees the stomach from its attachments, then uses a stapler to divide it along its length, removing roughly the outer three-quarters and leaving a narrow tube. The staple line is checked for bleeding and, in many centers, tested for leaks before the removed stomach is drawn out through one of the ports. For a gastric bypass, the stomach is divided to create a small pouch, and a loop of small intestine is brought up and joined to it. That join is called an anastomosis, a surgical connection between two hollow structures, and creating it is the most technically demanding part of the case.
Laparoscopic instruments are straight and rigid. They pivot at the abdominal wall, so the surgeon’s hands move in the opposite direction to the instrument tips, a bit like steering a wheelbarrow backward. Experienced bariatric surgeons become remarkably fluent with this, which is why the Mayo Clinic notes that outcomes depend heavily on surgeon and center experience rather than on the equipment alone. The procedure typically ends with the gas released, ports removed, and small incisions closed with absorbable stitches or skin glue.
What actually happens during robotic bariatric surgery?
The room looks different before anything else does. Alongside the operating table stands a patient-side cart with three or four articulated arms, and across the room sits the console where the surgeon will spend most of the case. Anesthesia, gas insufflation and port placement proceed much as in a laparoscopic operation, though port positions are often adjusted to give the robotic arms room to move without colliding.
Once the ports are placed, the arms are “docked,” meaning attached to the ports, and the instruments are inserted. The surgeon then moves to the console, scrubs out of the sterile field, and looks into a viewer that provides a magnified, three-dimensional image. The Mayo Clinic describes this enhanced view as one of the main features of robot-assisted surgery, alongside instruments that bend and rotate at their tips in ways a human wrist can, only in a smaller space.
Every movement of the surgeon’s fingers is scaled and translated to the instrument tips in real time. Small hand tremors are filtered out. The camera is controlled by the surgeon directly rather than by an assistant. Inside the abdomen, the steps are the same: freeing the stomach, firing the stapler, suturing where needed. Many surgeons find that hand-sewn joins, particularly during gastric bypass or revision surgery, are easier with wristed instruments, which is one reason robotic use tends to be higher for those cases than for a straightforward sleeve.
A bedside assistant remains scrubbed throughout, exchanging instruments, applying suction, and ready to convert to a standard laparoscopic or open approach if the team judges that safer. Docking and undocking add minutes that a laparoscopic case does not require, which is the main reason robotic operations run longer on average in published comparisons. At the end, the arms are withdrawn, the incisions are closed, and the patient wakes in the recovery area exactly as they would after any laparoscopic operation.
Is robotic surgery safer than laparoscopic for bariatric procedures?
This is the question patients most want answered, and the honest reply is: not clearly, in either direction. Robotic bariatric surgery has been studied in national registries involving many thousands of cases, and the overall picture is one of broad equivalence in serious complications, readmissions and deaths, with some differences that vary by procedure and by how experienced the center is with the robotic platform.

The Mayo Clinic states plainly that robotic surgery carries risks similar to those of conventional laparoscopic surgery, including infection and bleeding, and that it is not an option for everyone. The Cleveland Clinic makes a related point: the benefits described for robotic surgery, such as less blood loss or a shorter stay, are mainly benefits of minimally invasive surgery in general, and laparoscopy already delivers most of them. Moving from open to keyhole surgery was a large leap in safety. Moving from keyhole to robot-assisted keyhole is a much smaller step.
Where do the two approaches differ in the evidence? Robotic cases consistently take longer, largely because of docking time and instrument exchanges. Longer anesthesia is not automatically harmful, but it is a real difference. Some registry analyses have reported slightly higher rates of certain complications after robotic sleeve gastrectomy, while others have suggested fewer leaks or bleeding events after robotic gastric bypass. These findings are not consistent across all studies, and many are observational, meaning they compare patients who were not randomly assigned and may differ in ways the data cannot fully capture.
The most defensible summary is this: at an experienced center, both approaches are safe methods for delivering the same operation, and the surgeon’s familiarity with the chosen tool matters more than the tool itself. That is not a marketing sentence in either direction, and it is why guideline bodies have not declared one method superior.
Robotic gastric sleeve vs laparoscopic: what the evidence shows
Sleeve gastrectomy is now the most commonly performed bariatric operation, and it is also the one where robotic assistance has the least obvious mechanical advantage. The procedure is largely a stapling operation along a fairly straight line, without the intestinal joins that make wristed instruments so appealing in a bypass.
That shapes the evidence. Several large database comparisons have found that a robotic sleeve gastrectomy takes longer than a laparoscopic one and, in some analyses, has been associated with modestly higher rates of certain early complications, such as bleeding or leak from the staple line. A staple line leak means that stomach contents escape through a gap in the row of staples, one of the more serious problems after any sleeve. Other studies, particularly from high-volume robotic programs, have reported no difference at all. When results conflict this way, the likeliest explanation is that outcomes track experience and case selection rather than the platform.
There are situations in which a surgeon may still favor the robot for a sleeve. Patients with a very high body mass index, meaning a weight-to-height ratio well above the usual surgical threshold, can have a thick abdominal wall that makes rigid laparoscopic instruments hard to maneuver. Robotic arms hold their position without fatigue, which some surgeons find useful in these cases. A very large or fatty liver, which sits directly over the stomach, can also make visualization difficult, and the magnified three-dimensional view may help.
For the average patient having a first-time sleeve, however, the choice of approach is unlikely to change how the operation goes or how recovery feels. The Mayo Clinic’s description of sleeve gastrectomy focuses on the procedure and its dietary aftermath rather than the platform, which reflects how clinicians think about it. If your surgeon proposes a laparoscopic sleeve, that is the standard of care, not a lesser option.
Robotic gastric bypass benefits: where the robot may matter more
Gastric bypass is a more intricate operation than a sleeve, and this is where the case for robotic assistance is strongest, though still not settled. A Roux-en-Y bypass, the most common form, requires the surgeon to create a small stomach pouch and then make two intestinal connections. Each anastomosis must be precise and watertight, and each is a potential site of leak, narrowing or bleeding.
Wristed robotic instruments can rotate through angles a straight laparoscopic instrument cannot, which makes intracorporeal suturing, meaning stitching performed entirely inside the abdomen, more natural for many surgeons. Several observational studies have reported lower rates of anastomotic leak and fewer conversions to open surgery with robotic bypass, particularly for hand-sewn connections. Others have found no advantage once operative time and surgeon experience are accounted for. Randomized trials remain small, so any claimed benefit should be described as possible rather than proven.
Revision surgery is the other setting where surgeons frequently reach for the robot. Revisions, meaning operations to modify or convert a previous bariatric procedure, involve working through scar tissue, distorted anatomy and adhesions, bands of internal scarring that glue tissues together. The stable camera, magnified view and fine instrument control can be genuinely helpful when the landscape is unfamiliar. Complex cases such as a sleeve being converted to a bypass, or repair of a hiatal hernia alongside bariatric surgery, are among the most common robotic indications in practice.
None of this means a laparoscopic bypass is inferior. Surgeons who have performed hundreds of laparoscopic bypasses achieve excellent results with stapled connections and hand-held instruments, and the NIDDK notes that outcomes of bariatric procedures are closely tied to the experience of the surgical team. The reasonable expectation for a patient is that the surgeon will choose the platform on which they personally perform the bypass most reliably.
Robotic vs laparoscopic bariatric surgery at a glance
Patients often ask for the comparison in one place. The table below summarizes how the two approaches differ, drawing on descriptions of minimally invasive and robotic surgery from the Mayo Clinic and Cleveland Clinic and on the general pattern of published bariatric comparisons. Where the evidence is mixed, the table says so rather than tipping the balance.
| Feature | Laparoscopic | Robot-assisted |
|---|---|---|
| Incisions | Several small ports | Several small ports, sometimes positioned differently |
| Who controls the instruments | Surgeon, by hand at the bedside | Surgeon, from a console; the machine reproduces movements |
| View | 2D high-definition monitor, camera held by assistant | Magnified 3D view, camera controlled by surgeon |
| Instrument movement | Straight, rigid instruments pivoting at the abdominal wall | Wristed tips that rotate; tremor filtered |
| Operating time | Typically shorter | Typically longer, mainly due to docking |
| Serious complications | Low at experienced centers | Broadly similar overall; mixed data by procedure |
| Hospital stay and recovery | Usually a few days; weeks to normal activity | No consistent difference shown |
| Common uses | Most first-time sleeves and bypasses | Complex bypass, revisions, very high BMI, hernia repair combined with surgery |
| Availability | Widely available | Depends on equipment and trained team |
Two things stand out. First, the rows that matter most to patients, meaning safety, hospital stay and long-term weight outcomes, are the ones where the two approaches look most alike. Second, the rows where they clearly differ, such as operating time and availability, are practical rather than clinical. Reading the table this way tends to lower the stakes of the decision considerably. It also explains why many surgeons are comfortable saying, without hedging, that they would be happy for a family member to have either.
Who is usually offered each approach, and who is asked to wait?
Eligibility for bariatric surgery itself comes first, and it does not depend on the platform. The NHS describes weight-loss surgery as an option generally considered for adults with a body mass index of 40 or more, or between 35 and 40 with a weight-related condition such as type 2 diabetes or high blood pressure, when other approaches have not achieved lasting results. The NIDDK notes that current professional guidance also considers surgery for some people with a BMI of 35 or higher regardless of other conditions, and for people with a BMI of 30 or higher who have type 2 diabetes. Those thresholds are a starting point for discussion, not an entitlement or a verdict.
Within that eligible group, most first-time patients having a sleeve or a standard bypass are offered laparoscopic surgery simply because it is well established and widely available. Robotic surgery tends to be proposed when the anatomy is expected to be difficult: prior abdominal operations, a previous bariatric procedure that needs revision, a very high BMI with a thick abdominal wall, or a large hiatal hernia that will be repaired at the same time. In some programs, the surgeon performs all bariatric cases robotically as a matter of routine, which is also reasonable if that is where their experience lies.
Who is asked to wait? The reasons are almost always about readiness rather than the robot. The NHS emphasizes that candidates must be fit enough for general anesthesia and willing to commit to long-term follow-up and lifestyle change. Uncontrolled medical conditions, active substance use, untreated eating disorders or unstable mental health are common reasons a team postpones surgery while support is arranged. Some patients are asked to stop smoking for a period beforehand because smoking raises the risk of wound problems and ulcers at the surgical joins.
Very rarely, a specific factor rules out the robot in particular, such as an inability to tolerate the steep positioning some robotic setups require, or equipment limits for very large body sizes. Your team will tell you if that applies.
How surgeons actually decide: the factors that carry the most weight
Ask a bariatric surgeon how they choose, and the answer is rarely a single reason. It is a weighing of several practical considerations, most of which the patient never sees.
Surgeon training and volume come first. A surgeon who has completed hundreds of laparoscopic bypasses and a few dozen robotic ones will, quite properly, prefer laparoscopy for a routine case. The reverse is equally true. Every published comparison that has looked at it finds outcomes improve as a team moves along its learning curve with a new platform, so choosing the tool the surgeon knows best is a safety decision, not a preference.
The procedure itself matters next. Sleeves lean laparoscopic; complex bypasses, duodenal switch variants and revisions lean robotic in many programs, for the reasons described earlier. Patient factors follow: a history of prior surgery, expected adhesions, a very high BMI, or an enlarged liver may tip toward the robot. Institutional factors sit alongside these, including whether the equipment is available on the operating day, whether a trained bedside team is scheduled, and how long the case can be allotted.
Two things influence the decision far less than patients expect. One is the size or number of scars, which are nearly identical between approaches. The other is any expectation of greater weight loss; no major guideline suggests the platform affects how much weight a person loses, because that depends on the operation performed and on the years of eating, activity and follow-up that come after it.
Surgeons also know when to change course. Conversion from robotic to laparoscopic, or from either to open surgery, is planned for in every case and is a sign of good judgment rather than failure. If your surgeon explains their reasoning in terms of their own experience and your specific anatomy, you are hearing exactly the kind of reasoning the evidence supports.
Does robotic bariatric surgery mean a faster recovery time?
Marketing sometimes implies that a robot means being home sooner and back to work faster. The evidence does not support a meaningful difference. Because both approaches use the same small incisions and perform the same internal operation, the drivers of recovery, meaning pain from the ports, the body’s adjustment to a new stomach, and the healing of internal staple lines, are the same.
The NHS advises that most people stay in hospital for a few days after weight-loss surgery and that it can take four to six weeks to recover fully and return to normal activities, including work. Those ranges apply to laparoscopic and robotic operations alike, and individual timelines vary with the procedure, age, other health conditions and the physical demands of a person’s job. A desk-based role may be feasible sooner than heavy manual work.
Some studies of robotic bariatric surgery have reported slightly shorter hospital stays, others slightly longer, and most no difference once other factors are considered. Where a difference appears, it is often explained by hospital protocols rather than the platform: programs that have invested in a robotic service frequently also run modern enhanced-recovery pathways, with early walking, careful fluid management and minimal opioid use, and those pathways shorten stays regardless of how the surgery was done.
Pain after either approach is usually managed with a combination of non-opioid and, when needed, short-term opioid medicines, plus early mobilization. Your team will set the plan and adjust it; the specifics are theirs to decide. Gas used to inflate the abdomen can cause shoulder-tip discomfort for a day or two after both approaches, a curious sensation that surprises many patients and settles on its own.
The practical takeaway is to plan recovery around the operation you are having, not the machine performing it. Ask your team what their typical patients experience and build your leave, childcare and support around that.
What the first days and weeks usually look like after either approach
The pattern of early recovery is remarkably consistent whether a robot was involved or not. Understanding it in advance takes some of the fear out of the first week.
Day of surgery and the first night: you wake in a recovery area, often with a sore throat from the breathing tube and tightness around the port sites. Nurses encourage you to sit up and take short walks within hours, because moving reduces the risk of blood clots in the legs and helps clear the gas that causes shoulder discomfort. Fluids are introduced cautiously, usually starting with small sips.
Days one to three: most people go home within this window, in line with the NHS description of a hospital stay of a few days. Before discharge, the team confirms you can drink enough to stay hydrated, that pain is controlled with oral medicines, and that you understand the diet plan. Many programs prescribe a short course of blood-thinning injections or tablets after discharge; the type and duration are decisions for your surgical team.
The first two weeks: the diet is liquid, then puréed, progressing through stages over several weeks as the Mayo Clinic describes for both sleeve and bypass. Fatigue is normal; the body is healing internally while taking in very few calories. Small incisions are checked for redness or discharge. Gentle walking is encouraged daily, while lifting and strenuous exercise are typically restricted for a period your surgeon will specify.
Weeks three to six: soft foods return, energy climbs, and most people are back at work, allowing for the NHS’s four-to-six-week recovery range. Follow-up visits check weight, hydration, wound healing and early nutritional status. Lifelong vitamin and mineral supplementation begins early after bypass in particular, because the rerouted intestine absorbs less; the exact regimen is set by your team, not by an article.
Emotional adjustment runs alongside physical recovery. Relationships with food shift abruptly, and low mood in the early weeks is common and worth mentioning at follow-up.
Which bariatric surgery is most successful, and why that is the wrong question
Two questions dominate online searches: which operation is most successful, and whether people lose weight faster with a bypass or a sleeve. Both deserve straight answers, and both need reframing.
On average, gastric bypass produces somewhat more weight loss than sleeve gastrectomy and tends to have a stronger effect on type 2 diabetes and acid reflux, a pattern described by the Mayo Clinic in its comparison of the two procedures. Sleeve gastrectomy is technically simpler, avoids intestinal rerouting, and carries a lower risk of certain long-term nutritional deficiencies and internal hernias. Early weight loss is rapid after both, with most of the change occurring in the first year or two, and the difference between them at the individual level is much smaller than the difference between a patient who engages with follow-up and one who does not.
“Most successful” therefore depends on what you are trying to achieve. Someone with severe reflux may be steered away from a sleeve, which can worsen it. Someone on medicines that need reliable absorption, or who cannot commit to lifelong supplementation, may be steered away from a bypass. The NIDDK frames all bariatric procedures as tools that work alongside long-term changes in eating and activity, and that framing is the one the evidence supports.
The platform, robotic or laparoscopic, does not appear in this calculation at all. No mainstream guideline suggests that the robot changes how much weight is lost, how much diabetes improves, or how likely weight regain becomes. Those outcomes belong to the operation and to the years that follow it.
If a consultation spends most of its time on the machine and little on which procedure suits your health history, that is a cue to redirect the conversation. The choice of operation is the decision with real consequences; the choice of instrument control is a matter of surgical logistics.
What people often get wrong about robotic and laparoscopic bariatric surgery
Myth: the robot does the surgery. It does not. The Cleveland Clinic is explicit that the surgeon controls every movement; the system has no autonomy and cannot act independently. “Robot-assisted” is the more accurate term.
Myth: robotic means smaller scars. Both approaches use small ports of similar size and number. Any difference is a matter of millimeters and placement, not visibility.
Myth: newer is safer. The Mayo Clinic states that robotic surgery carries risks similar to conventional laparoscopy. Some registry data even suggest slightly higher early complication rates for robotic sleeve gastrectomy at less experienced centers, which is a caution against assuming novelty equals safety.
Myth: laparoscopic is outdated. Laparoscopy remains the standard method for most bariatric operations worldwide and continues to deliver excellent results. A surgeon who recommends it is recommending the mainstream, not the past.
Myth: you lose more weight with the robot. Weight loss depends on the operation and on long-term behavior, not on the instrument platform. No guideline body links the robot to better weight outcomes.
Myth: surgery ends the relationship with obesity. Bariatric surgery treats obesity as a chronic condition; it does not end it. Weight regain over years is possible, which is why the NHS insists on commitment to lifelong follow-up as a condition of surgery.
Myth: divorce is inevitable afterward. Research from a large Swedish cohort found that people who had bariatric surgery were more likely than comparison groups to both end relationships and begin new ones in the years afterward. The likeliest interpretation is that dramatic changes in health, confidence and daily life can shift the dynamics of an already strained relationship, and can also make leaving one feel possible. Stable partnerships often become stronger. Many programs offer counseling for partners for exactly this reason, and asking about it is sensible rather than pessimistic.
Questions to ask your care team
A good consultation is a conversation, and the most useful questions are the ones that reveal reasoning rather than sales points. Bring this list, and expect clear answers.
- Which procedure are you recommending for me, and why that one rather than the alternatives?
- For that procedure, do you usually operate laparoscopically or robotically, and what tips you one way or the other in my case?
- Roughly how many of this exact operation have you performed on each platform?
- If you plan a robotic approach, how does that change my operating time, positioning, or port placement?
- What would make you convert to a different approach during surgery, and how often does that happen in your practice?
- What complications do you watch for most closely with this procedure, and what are the early signs I should know?
- How long do your patients typically stay in hospital, and what does your follow-up schedule look like over the first two years?
- What supplements will I need long term, and who monitors my blood tests?
- Does your program offer dietitian, psychology and support-group access after surgery, including support for partners and family?
- What is your plan if I regain weight or develop reflux years from now?
Notice what is missing from the list: any question about which approach is “best.” A surgeon who answers the questions above thoroughly has told you everything that matters about their choice of platform without needing to rank the tools. The NHS and NIDDK both stress that bariatric surgery is a long-term partnership between patient and team; the quality of that partnership is the thing most worth assessing during your consultation.
Write down the answers, or bring someone who will. Consultations move quickly, and the details about follow-up and nutrition are the ones people most often wish they had recorded.
When to call your doctor
Recovery from either approach usually proceeds quietly, but complications do occur, and they are far easier to manage when caught early. Your surgical team will give you a direct contact number for the first weeks; use it without hesitation. The signs below warrant a same-day call, and several warrant emergency care.
Call urgently or seek emergency care if you develop a fever, a fast heart rate that persists at rest, worsening abdominal pain that is not controlled by your prescribed medicines, or shortness of breath. These can be early signs of a leak from a staple line or surgical join, or of a blood clot in the lung, both of which are uncommon but serious and described among the main risks of bariatric surgery by the Mayo Clinic and NIDDK.
Contact your team the same day for persistent vomiting or an inability to keep fluids down, since dehydration develops quickly when intake is already tiny. Report black or tarry stools, vomiting blood, or bleeding from an incision. Redness, warmth, swelling or pus around a port site can indicate wound infection. New pain, swelling or warmth in one calf may signal a clot in the leg.
Later in recovery, mention difficulty swallowing, food feeling stuck, severe heartburn, or dizziness and sweating after meals, which can point to a narrowing at a join or to dumping syndrome, a rapid emptying of stomach contents into the intestine that can follow bypass. Persistent low mood, anxiety or thoughts of self-harm deserve prompt attention too; the emotional side of recovery is part of medical care, not separate from it.
None of these signs is a reason for shame or a suggestion you did something wrong. Bariatric teams expect calls and would far rather hear from you about a symptom that turns out to be nothing than miss one that mattered.
Frequently asked questions
Which surgery is better, robotic or laparoscopic, for weight loss?
Neither is better for weight loss, because both perform the same operation. The amount of weight lost depends on whether you have a sleeve, a bypass or another procedure, and on your follow-up, eating and activity in the years afterward. Large comparisons show similar safety overall, with robotic cases taking longer. Your surgeon will choose the platform they perform most reliably for your specific anatomy.
Is robotic surgery safer than laparoscopic surgery?
Not in any consistent way. The Mayo Clinic describes the risks of robotic surgery as similar to conventional laparoscopy. Some studies suggest fewer leaks with robotic gastric bypass, while others have found slightly higher early complication rates with robotic sleeve gastrectomy, particularly at less experienced centers. The strongest predictor of safety in the evidence is the experience of the surgeon and team with whichever tool they use.
What is robotic bariatric surgery recovery time compared with laparoscopic?
Recovery is essentially the same. The NHS indicates a hospital stay of a few days and around four to six weeks to return to normal activities after weight-loss surgery, and no consistent difference has been shown between robotic and laparoscopic approaches. Where robotic programs report shorter stays, it is usually attributable to enhanced-recovery protocols rather than the machine. Plan your leave around the procedure, not the platform.
How does robotic gastric sleeve vs laparoscopic compare in outcomes?
Outcomes are broadly similar, but a robotic sleeve takes longer and has not shown a clear advantage. A sleeve is mainly a stapling operation without intestinal joins, so the wristed instruments that help in bypass surgery add less. Some database analyses have linked robotic sleeves to slightly more early complications; others have found none. Most first-time sleeves are done laparoscopically, and that remains the standard approach.
What are the robotic gastric bypass benefits surgeons talk about?
The main advantage is control during suturing. Wristed instruments rotate in ways straight laparoscopic tools cannot, which many surgeons find helpful when hand-sewing the two intestinal connections a bypass requires, and in revision surgery through scar tissue. Some observational studies report fewer leaks or conversions to open surgery, but findings are mixed and randomized trials are small, so these benefits are described as possible rather than established.
What is the most successful type of bariatric surgery?
It depends on your health goals. On average, gastric bypass produces somewhat more weight loss and stronger effects on type 2 diabetes and reflux than sleeve gastrectomy, according to the Mayo Clinic, while the sleeve is simpler and carries fewer long-term nutritional risks. Success is shaped far more by lifelong follow-up and lifestyle than by the procedure, and the treating team matches the operation to the individual.
Do you lose weight faster with bypass or sleeve?
Early weight loss is rapid after both, with most change in the first year or two, and the pace is similar. Bypass tends to produce a slightly greater total loss on average, but individual results overlap widely. Neither the robotic nor the laparoscopic platform changes this. Your team will focus on which operation suits your medical history rather than on which produces a faster number on the scale.
Why is the divorce rate so high after bariatric surgery?
Research from a large Swedish cohort found that people who had bariatric surgery were more likely than comparison groups both to separate and to enter new relationships afterward. Rapid changes in health, confidence, social life and daily routines can strain an already fragile partnership, and can also make leaving one feel possible. Strong relationships often grow stronger. Many programs offer counseling that includes partners; asking about it is sensible.
Does the robot ever operate on its own during bariatric surgery?
No. The Cleveland Clinic and Mayo Clinic both describe robot-assisted surgery as fully surgeon-controlled: the surgeon sits at a console and every instrument movement reproduces their hand motions, with small tremors filtered out. The system has no programming to act independently. A scrubbed assistant remains at the bedside throughout, and the team can switch to standard laparoscopic or open surgery at any point if that is judged safer.
Can I choose robotic or laparoscopic bariatric surgery myself?
You can express a preference, but the final decision sits with your surgeon and depends on their training, your anatomy, the procedure planned and equipment availability. Choosing the platform the surgeon uses most is itself a safety decision, since outcomes track experience in every published comparison. The more valuable choices to discuss are which operation you have and how your long-term follow-up will be organized.
References
- NHS – Weight loss surgery
- NIH NIDDK – Bariatric Surgery
- MedlinePlus – Gastric bypass surgery
- Cleveland Clinic – Robotic Surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Gastric Band vs Gastric Sleeve: Reversible Device or Lasting Reshaping, Compared Honestly
An adjustable gastric band is a removable silicone ring fitted around the upper stomach and tightened through a port under the skin; a gastric…

Robotic Bariatric Surgery: What the Robotic Arms Change Inside the Operating Room
Robotic bariatric surgery uses a surgeon-controlled console and wristed instruments to perform standard weight-loss operations, such as sleeve gastrectomy or gastric bypass, through small…

Gastric Balloon vs Gastric Sleeve: Temporary Device or Surgery, and How Doctors Compare Them
A gastric balloon is a temporary, saline-filled device placed in the stomach through the mouth and usually removed after about six months, while a…

Preparing for an Obesity Clinic Appointment: Weight History, Medicines and Questions to Bring
To prepare for an obesity clinic appointment, bring a written weight history (your weight at key life stages, past attempts, what helped and what…

Gastric Sleeve Results Over the Years: What Realistic Long-Term Expectations Look Like
Gastric sleeve results long term typically show the largest weight loss in the first one to two years, with a partial regain for many…

Does Metabolic Syndrome Change After Menopause? What Doctors Watch in Midlife Women
Yes. After menopause, the pattern of metabolic syndrome shifts even when weight stays steady: fat moves toward the waist, LDL cholesterol and triglycerides tend…