

Toddler Constipation: Causes, Foods and When to See a Doctor

Key Takeaways
- Toddler constipation is defined by hard, painful or withheld stools, not by a calendar; a comfortable child who goes every other day is not constipated.
- About 95 percent of childhood constipation is functional, meaning the bowel is normal and a pain-withholding cycle is driving the problem.
- Prunes, pears, peaches and plums help because they contain sorbitol, which pulls water into the stool, and they only work when the child also drinks enough fluid.
- Cow's milk beyond roughly 16 to 24 ounces a day is the most common dietary cause pediatricians find in toddlers, because it displaces fiber, fruit and water.
- Polyethylene glycol 3350 and lactulose have randomized-trial support in children, while castor oil, probiotics and fiber supplements do not, and all medicine decisions belong to the pediatrician.
- Vomiting, a swollen belly, blood through the stool, fever, poor weight gain or constipation lasting more than two weeks are reasons to see a doctor rather than try another home remedy.
Toddler constipation usually means hard, painful or infrequent stools, often with straining, leg-crossing or stool withholding, and it is most often functional rather than caused by disease. Fluids, fruit such as prunes and pears, regular toilet sitting and a calm routine help many children, while a pediatrician should assess vomiting, blood in stool, a swollen belly, fever, poor weight gain or constipation lasting more than two weeks.
The video has a familiar rhythm: a parent in a kitchen, a dark bottle held up to the camera, a promise that a few drops rubbed on a toddler’s belly, or stirred into juice, will “clear everything out by morning.” As of June 2025, castor oil clips like this have pushed searches for toddler constipation, and for castor oil doses in children, to one of their highest points in years. The oil is old, the trend is new, and the gap between the two is where many families get stuck.
Pediatricians see the real version of this story every week. A two-year-old who used to go daily now disappears behind the sofa, stiffens, turns red, and refuses the potty. Three days later there is a stool the size of a fist, a tearful bathroom, and a child who has learned that pooping hurts. Nothing in that sequence is rare: around 3 in 10 children will have constipation at some point, and the toddler years are the peak.
This guide explains what is actually going on inside that small body, which foods genuinely help, what the research supports, and the specific signs that mean a doctor, not a social feed, should be your next stop.
What counts as toddler constipation? It is not only about frequency
Parents often count days. Doctors look at the stool, the behavior and the pattern together, because a healthy toddler’s bowel habit varies enormously. One child goes twice a day; another goes every other day and is perfectly comfortable. Neither is constipated.
The widely used Rome IV criteria, a set of expert definitions for bowel disorders updated in 2016, describe functional constipation in children under four as at least two of the following for about a month: two or fewer bowel movements a week, a history of painful or hard stools, large stools that can clog the toilet, a large mass of stool felt in the rectum, visible stool-holding behavior, or soiling of underwear in a child who is already toilet trained. “Functional” is the key word. It means the bowel is structurally normal and the problem lies in how it is being used, which describes roughly 95 percent of childhood cases.
In practice, three clues matter most for a toddler:
- The stool is hard, dry, pellet-like or unusually large, whatever the frequency.
- Passing it hurts, or the child acts as if it will hurt.
- The child is actively trying not to go.
A stool chart can help you describe things precisely. Pediatric teams often use the Bristol stool scale, a seven-type picture guide: types 1 and 2 (separate hard lumps, or a lumpy sausage) point to constipation, while types 3 and 4 are the soft, formed goal.
One more distinction. Constipation that began in the first weeks of life, especially if the newborn did not pass meconium, the first dark stool, within 48 hours, is a different clinical question from constipation that starts at 18 months after a switch to whole milk. The first needs medical evaluation; the second is usually the everyday kind this article focuses on.
Why do toddlers get constipated? The withholding cycle explained
Picture the rectum as a stretchy muscular pouch with a built-in alarm. When stool arrives, the wall stretches, nerves fire, and the child feels the urge. If the child answers that urge, the pouch empties and resets. If the child clenches instead, the stool sits, the colon keeps absorbing water from it, and it gets harder and larger. The next urge is now attached to a bigger, drier stool, which is more likely to hurt. Pain teaches withholding. Withholding makes the next stool worse. Pediatricians call this the withholding cycle, and it explains most toddler constipation better than any single food does.
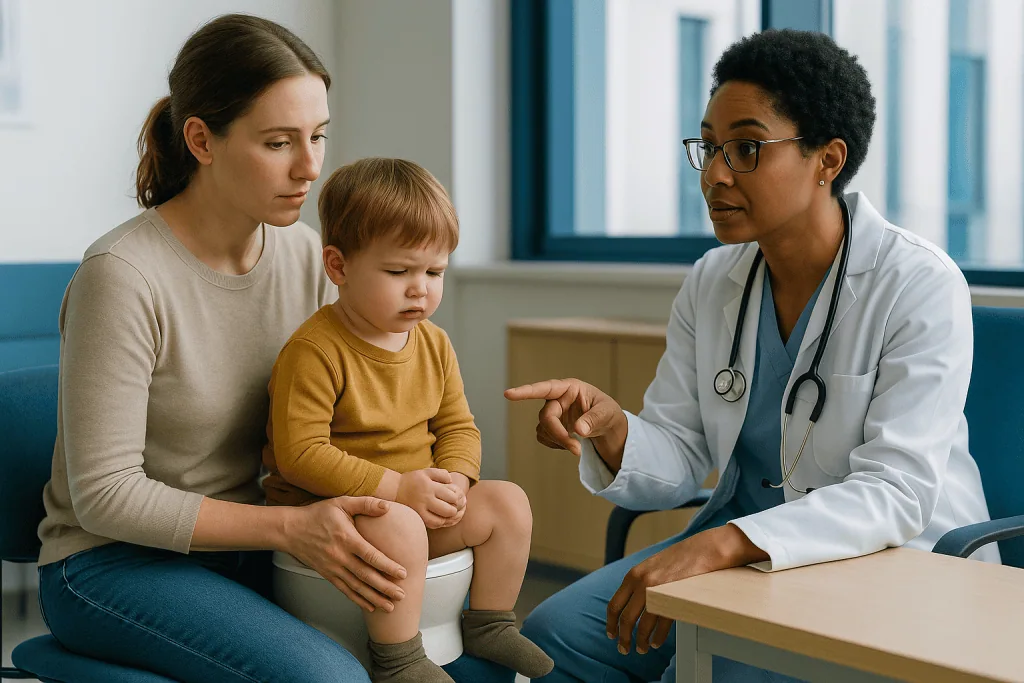
What starts the cycle? Common triggers cluster around change:
- Diet shifts, such as moving from breast milk or formula to cow’s milk and table food, or a toddler who suddenly eats little but dairy and crackers.
- Toilet training that begins before the child is ready, or that comes with pressure.
- A single painful stool, often from a small tear at the anus called an anal fissure.
- Illness with fever, reduced drinking and days on the couch.
- Travel, starting daycare, a new sibling, or any disruption to routine and privacy.
- Being too busy playing to stop, a surprisingly common reason at age two and three.
Over weeks, a chronically full rectum stretches and loses sensitivity, so the alarm grows quieter. That is why some children truly do not feel the need to go, and why soft liquid stool can leak around the hard mass and stain underwear. Parents sometimes mistake this for diarrhea; it is usually the opposite.
Medical causes are uncommon but real: an underactive thyroid, celiac disease, cow’s milk protein allergy, certain medicines, spinal cord problems, and Hirschsprung disease, a condition in which nerve cells are missing from part of the bowel. The red flags in the doctor section are there to catch these.
What changed recently in toddler constipation advice and research
The science of childhood constipation moves slowly, but a few shifts are worth dating. The clearest came in 2016, when the Rome IV criteria shortened the required symptom duration for infants and toddlers to one month, so that treatment can begin before the withholding cycle entrenches itself. Mayo Clinic and Johns Hopkins patient guidance now reflect that earlier-is-better stance, emphasizing that a few weeks of constipation deserve a pediatric conversation rather than a wait-and-see of several months.
The second shift is about polyethylene glycol 3350, the osmotic laxative sold as MiraLAX and under generic names. An osmotic laxative works by holding water in the stool so it stays soft. Through the 2010s, parents worried about online reports linking it to behavioral changes in children, and the US Food and Drug Administration funded research at a children’s hospital to investigate. Published analyses have not found evidence that the product causes the neuropsychiatric effects described in those reports, and the drug remains the most-studied first-line option in pediatric guidelines, used under a clinician’s direction since it is not labeled for children under 17 in the United States. The evidence section grades this more carefully.
The third change is cultural rather than scientific. Beginning in 2023 and accelerating through 2024 and 2025, short-form videos promoting castor oil for a long list of ailments, including “belly-button castor oil” for digestion and oral castor oil for constipation in children, went viral. Castor oil is a genuine stimulant laxative approved for adults, but mainstream guidance from the NHS and MedlinePlus cautions against routine use in young children, and there are no published randomized trials of castor oil in toddlers. The surge in searches for how much castor oil to give a child is the reason this topic is trending, and the reason the home remedy section below is blunt about it.
None of these developments alters the fundamentals: soften the stool, remove the fear, build the routine.
What the evidence actually says, graded by strength
Evidence in pediatric constipation ranges from solid randomized trials to tradition dressed up as fact. Here is an honest ranking.

Strong evidence (multiple randomized controlled trials). Osmotic laxatives, chiefly polyethylene glycol 3350 and lactulose, reliably soften stool and increase bowel movements in children. Head-to-head trials and systematic reviews, summarized by Mayo Clinic and Johns Hopkins, generally find polyethylene glycol at least as effective as lactulose and better tolerated. Treatment typically needs to continue for months, not days, because a stretched rectum takes time to regain tone; stopping early is the most common reason children relapse.
Of course, these medicines are not for parents to start or adjust on their own. A pediatrician decides whether, which, and for how long.
Moderate evidence (trials with limitations, consistent expert consensus). Behavioral measures, such as scheduled toilet sitting after meals, a footstool for proper posture, and reward charts for sitting rather than for producing a stool, improve outcomes when added to laxatives. The effect is hard to blind in a trial, but the physiological logic (the gastrocolic reflex, a wave of colon activity after eating) and consistent results across studies make this a guideline-level recommendation.
Weak or mixed evidence (observational data, small trials). Dietary fiber helps some children, and population data link higher fruit, vegetable and whole-grain intake with fewer constipation complaints. Yet randomized trials of fiber supplements in constipated children are small and inconsistent, so fiber is best viewed as part of a healthy diet rather than a treatment on its own. Probiotics fall here too: reviews cited by the NIH find no reliable benefit for pediatric constipation, with wide variation between strains and studies.
Finally, there is expert opinion and tradition: warm baths, abdominal massage, apple juice, and the like. Harmless in moderation, occasionally comforting, unproven.
Signs of constipation in toddlers that parents often miss
The obvious sign is a hard stool. The subtle signs are behavioral, and toddlers are inventive about hiding them. A child who stands on tiptoe, crosses her legs, squeezes her buttocks together, rocks on the sofa arm, or goes rigid and red-faced is not trying to go. She is trying not to go. Parents frequently describe this as “straining,” which sends the conversation in the wrong direction.
Other clues that point to constipation rather than something else:
- Stomachaches that come and go, often around mealtimes, and ease after a bowel movement.
- A smaller appetite, or a child who fills up fast and then wants snacks an hour later.
- A firm, slightly bloated lower belly that a pediatrician can feel on exam.
- Small streaks of soft stool or smears in the diaper or underwear, sometimes several times a day. This leakage, called encopresis when it occurs in a child older than four, happens when liquid stool slips past a hard mass. It is involuntary, and scolding makes it worse.
- Bright red blood on the toilet paper or stool surface, usually from an anal fissure.
- Sudden refusal to use the potty after weeks of progress.
- Bedwetting or repeated urinary tract infections, because a full rectum presses on the bladder.
Then there are the behaviors that look like something else entirely: irritability, clinginess, waking at night, or a toddler who seems “off” for no reason. Constipation is one of the first things pediatricians check in an uncomfortable, cranky young child, precisely because it is so common and so easy to overlook.
A simple two-week log noting stool size, texture on the Bristol scale, pain, soiling and the child’s behavior is more useful to a doctor than any single description, and takes a parent less than a minute a day.
Foods for toddler constipation: what actually helps relieve it
Food cannot fix an established withholding cycle on its own, but it can soften what arrives in the rectum, which is half the battle. Two mechanisms do most of the work. Sorbitol, a natural sugar alcohol in certain fruits, draws water into the bowel, which is why prunes have earned their reputation. Fiber, the indigestible part of plants, adds bulk and holds moisture. Both need enough fluid to work; fiber without water can make stool firmer.
| Food | Why it helps | Toddler-friendly form |
|---|---|---|
| Prunes and prune purée | High in sorbitol and fiber; best-supported fruit in small pediatric studies | Stewed, puréed, or chopped into oatmeal |
| Pears, peaches, plums, apricots | The “P fruits”: sorbitol plus soluble fiber | Soft ripe slices, skin on when tolerated |
| Kiwi | Fiber and an enzyme, actinidin; adult trials show benefit | Halved and scooped, or diced |
| Oats and whole-grain bread | Soluble fiber that holds water | Porridge, whole-wheat toast fingers |
| Beans, lentils, peas | Very high fiber; also feed gut bacteria | Mashed into pasta sauce or soup |
| Broccoli, carrots, sweet potato | Fiber plus fluid | Steamed soft; roasted for sweetness |
| Water | Needed for any fiber to soften stool | A cup offered with every meal and snack |
A practical target: offer a fruit or vegetable at every meal and most snacks, and favor whole grains over white bread and plain crackers. Toddlers eat in waves; what matters is the pattern over a week, not any single plate.
A note on juice. A small daily portion of pear or prune juice can loosen stool because of its sorbitol, and pediatricians sometimes suggest it for toddlers over one year. More is not better; large volumes of juice crowd out food and fluids and can cause diarrhea and tooth decay. Ask your pediatrician what amount, if any, fits your child.
Which foods and habits make toddler constipation worse?
The single most common dietary culprit in a pediatric clinic is not a food that is “bad.” It is cow’s milk in large amounts. Milk is filling and low in fiber, and a toddler drinking from a bottle or cup all day may take in more than the roughly 16 to 24 ounces (about 2 to 3 cups) that pediatric guidance considers an upper daily range for this age. The result is a child too full for fruit, vegetables and water, with stools that turn pale, firm and infrequent. Shifting milk to mealtimes and offering water in between is often the first change a pediatrician recommends.
Other patterns that tend to tighten things up:
- A beige diet: white bread, crackers, cheese, plain pasta and rice cereal, with little fruit or vegetable.
- Not enough fluid, especially during hot weather, illness or when a child is busy and forgets to drink.
- Large portions of unripe (green-tinged) banana. Ripe bananas are fine; the starch in unripe fruit is the issue.
- Iron drops or certain other medicines. Do not stop any prescribed treatment, but do mention it to the prescriber, who can adjust the plan.
- Skipping breakfast and rushing out the door, so the body’s natural post-meal urge arrives at daycare where the child will not go.
Then there are habits that have nothing to do with food. A potty in a cold, echoing bathroom; a toilet seat that leaves the child’s feet dangling; a caregiver who sighs when the stool does not come; a sticker only for “success.” Each of these raises the stakes, and a child who senses stakes will clench.
What about cow’s milk protein allergy? A small subgroup of constipated toddlers improves when cow’s milk is removed, and some pediatricians will trial this. It is a medical decision, not a home experiment, because removing dairy without a replacement risks calcium and calorie shortfalls in a growing child.
Toddler constipation remedies at home: castor oil, warm baths and massage
Start with the one that trends. Castor oil is a stimulant laxative: it irritates the bowel lining and triggers contractions, and it has been used for generations. Three things about it are not in dispute. It is approved as an over-the-counter laxative for adults. It causes cramping and, at excess, dehydrating diarrhea. And there are no randomized trials of castor oil in toddlers, which is why the NHS, MedlinePlus and Mayo Clinic do not list it among recommended treatments for young children. Rubbing it on the navel, the other viral version, has no plausible route to the colon; skin absorption of the oil is negligible. The honest answer to “how much castor oil for a toddler” is that mainstream pediatric guidance does not give an amount, because it does not recommend the oil for this age without a clinician’s explicit direction.
A warm bath is kinder and gentler. Warmth and gentle splashing can relax a tense child, and many parents notice a stool arrives during or shortly after the bath. The evidence is anecdotal, the mechanism is relaxation rather than any effect on the stool itself, and that is fine; a bath will not hurt, and a calm toddler withholds less.
Abdominal massage, slow clockwise circles following the path of the colon, has small positive studies in adults and infants but nothing robust in toddlers. Treat it as a bonding ritual with a possible bonus.
Bicycle legs, tummy time and running around the yard all help in the same modest way: movement stimulates the gut. Fluids and the fruits in the table above do more.
Things to avoid without medical advice: adult laxative tablets, enemas, mineral oil in a child who might choke on it, herbal “detox” teas, and inserting anything into the rectum, including thermometers, to “stimulate” a stool. Each can cause harm, and none addresses the withholding that keeps the cycle going.
What can I do to help my child with constipation quickly?
Quickly is relative. A stool that has been building for four days will not soften in an hour, and the safest fast options are the ones a pediatrician chooses for your child, not the ones a stranger demonstrates online. Within that limit, a few things can genuinely speed relief the same day or the next.
First, sit after meals. Ten to twenty minutes after breakfast and dinner, when the gastrocolic reflex is strongest, have the child sit on the potty or toilet for about five minutes, with feet planted flat on a step or box so the knees are higher than the hips. This posture straightens the angle of the rectum and makes passing stool mechanically easier. Make it boring and pleasant: a book, a song, no pressure to produce.
Second, hydrate deliberately. Offer water with every meal and snack, and for a child over one year, a small portion of pear or prune juice as the pediatrician advises.
Third, front-load the P fruits. Prune purée at breakfast, pear at lunch, peach at dinner. Sorbitol works within a day in many children.
Fourth, lower the fear. If the child is crying in the bathroom, stop, hug, and try again later. A tearful standoff teaches the wrong lesson.
Fifth, protect the skin. If there is a small fissure, a plain barrier ointment on the area can ease the sting; a pediatrician can advise if something more is needed.
Sixth, call the pediatrician if the child is in real distress, has not passed stool in several days, has a swollen belly, or is vomiting. Clinicians have safe, well-studied options, including glycerin suppositories and osmotic laxatives, and will choose based on the child’s age, weight and history. The six-year-old in the search question above is old enough for a slightly different toolkit than a two-year-old, which is exactly why the decision belongs to the clinician who knows the child.
Potty training, pressure and the stool-holding toddler
If there is one moment when toddler constipation is born, it is often the week potty training begins. The timing is not a coincidence. Toilet training asks a child to control a reflex she has never had to think about, in a place that is often loud, cold and unfamiliar, with an adult watching. Some children find this fascinating. Others find it alarming, and the quickest way to avoid an alarming thing is to hold it in.
Pediatric guidance consistently makes two recommendations. The first is readiness over calendar: a child who stays dry for a couple of hours, notices when she is about to go, can pull pants down and up, and shows interest is ready; a child who is simply two is not necessarily ready. The second is to separate bowel training from the pressure of “success.” Reward sitting, not producing. Keep sits short. If the child asks for a diaper to poop in, allow it, in the bathroom, so the stool is passed without fear; the location can move later.
Signs the training itself is driving constipation include stool withholding that started within a week or two of training, a child who will urinate in the potty but demands a diaper for stool, and crying or hiding when the potty is mentioned. The standard advice in that situation is to pause training for several weeks, soften the stool with diet or whatever the pediatrician recommends, and restart only once stools are comfortable.
This is the part of the plan families most often skip, because pausing feels like going backwards. It is not. A toddler who pauses, softens and restarts usually trains faster than one who grinds through a cycle of painful stools. The goal is a child who does not associate the toilet with hurting, and that goal is worth a few extra weeks of diapers.
Medicines a pediatrician may use for constipation in children
Parents are sometimes startled when a doctor recommends a laxative for a toddler. It helps to understand the logic. If a stool hurts, no amount of encouragement will make a child want to pass it. Softening the stool removes the pain, and removing the pain removes the reason to withhold. In that sense, a laxative is a behavioral treatment delivered through the bowel.
The medicines most often discussed, named only so parents can recognize them on a prescription or in conversation:
- Polyethylene glycol 3350 (MiraLAX and generics), an osmotic laxative that holds water in the stool. It is the most studied option in children, generally well tolerated, and in the United States it is used in young children off its adult label, which is why a clinician must direct it.
- Lactulose, a prescription sugar solution that also works osmotically; a common first choice in the United Kingdom and for infants.
- Glycerin suppositories, which draw water into the rectum for faster relief of a hard stool near the exit.
- Senna and other stimulant laxatives, sometimes added short-term when softening alone does not produce a stool.
- Docusate and mineral oil appear in older guidance; evidence for docusate is weak, and mineral oil carries a risk of aspiration in children who may choke, so both are less used in toddlers.
Pediatricians typically describe treatment in two phases. Disimpaction, if needed, clears a large retained mass over a few days. Maintenance then keeps stools soft, often for several months, while the rectum regains tone and the child relearns that going does not hurt. Stopping early is the most common cause of relapse, and tapering is done gradually under the clinician’s guidance.
Everything about amounts, timing, choice of product and duration belongs to the prescribing clinician, who weighs age, weight, symptoms and any other conditions. Never change or stop a child’s prescribed treatment without that conversation.
Common myths about toddler constipation, corrected
Myth: A toddler must poop every day. Healthy patterns range from several times a day to once every two or three days. Comfort, texture and the absence of withholding matter more than the count.
Myth: Castor oil is natural, so it is safe for small children. Natural is not a safety rating. Castor oil is a potent stimulant laxative with no toddler trials and real risks of cramping and dehydration. The belly-button version does nothing; the oil does not reach the colon through the skin.
Myth: Bananas always cause constipation. Ripe bananas contain soluble fiber and are fine. Large amounts of unripe banana, heavy in resistant starch, can firm stool. Most of the reputation belongs to the green ones.
Myth: Laxatives are habit-forming and will make the bowel lazy. This fear, borrowed from adult stimulant overuse, does not match pediatric evidence for osmotic laxatives, which do not stimulate the bowel and have been used for months at a time in trials without dependency. The lazy bowel in this story is the one stretched by retained stool, which a laxative helps reverse.
Myth: Soiled underwear means the child is being lazy or defiant. Leakage around a hard mass is involuntary, and the child often cannot feel it. Punishment deepens shame and withholding.
Myth: Fiber supplements fix it. Trials of fiber supplements in constipated children are small and inconsistent. A fruit-and-vegetable-rich diet is worthwhile for many reasons; a powder is not a treatment plan.
Myth: Once the big stool is out, the problem is over. Clearing a backlog is the start. Without weeks of soft stools and a routine, the cycle usually restarts.
Myth: Probiotics are proven for kids’ constipation. Reviews summarized by the NIH find no consistent benefit; results vary widely by strain and study. Harmless for most children, unproven for this purpose.
When to see a doctor about toddler constipation: red flags and routine checks
Most toddler constipation can be managed with food, fluids, routine and, when a pediatrician advises, a laxative. Some situations need prompt medical attention, and a few need it the same day.
Seek urgent care or call your pediatrician immediately if your child has:
- Vomiting, especially if it is green or yellow-green, which can signal a blockage.
- A swollen, tense or very painful belly.
- Blood mixed through the stool (rather than a streak on the surface), or black stool.
- Fever along with constipation and abdominal pain.
- Severe pain that stops the child from walking or settling.
- Weakness in the legs, a change in walking, or new bladder problems, which can point to a nerve or spinal issue.
Book a routine appointment if:
- Constipation has lasted more than two weeks despite diet and routine changes.
- The child is soiling underwear, or has repeated anal fissures.
- There is poor weight gain, a falling-off growth curve, or persistent poor appetite.
- Constipation began in the first weeks of life, or the newborn passed meconium late.
- The child has a bloated belly between stools, very foul-smelling stools, or is unusually tired or pale.
- Constipation keeps returning after stopping a treatment.
- You have been giving any over-the-counter or home remedy regularly.
At the visit, expect questions about diet, fluids, toilet habits, family history and the stool log, plus a physical exam that includes feeling the abdomen and checking the lower back and anus. Blood tests, X-rays or referral to a pediatric gastroenterologist are reserved for red flags or constipation that does not respond.
Every decision about medicines, amounts and how long to treat belongs to the clinician who examines the child. The internet can help you describe the problem well; it cannot examine a belly.
Chronic constipation in children: the long game and preventing relapse
Here is the pattern pediatric gastroenterologists describe, and that parents rarely expect. A child is treated, stools soften, the family breathes out, treatment stops after three weeks, and two months later the hiding and the leg-crossing are back. Relapse is so common that guidelines now frame childhood constipation as a condition to manage over months, with maintenance treatment continued for a period after symptoms resolve and tapered slowly under the clinician’s direction. Around half of children with chronic constipation are still symptomatic a year later, and a smaller share carry it into adolescence, which is a strong argument for treating early and thoroughly.
What keeps a child well once things are moving:
- A daily toilet sit after a main meal, feet supported, kept short and low-pressure, even on good days.
- Fruit or vegetables at most meals, water freely available, milk limited to mealtimes in the amounts your pediatrician recommends.
- A one-line daily note of stool texture for the first few months, so an early change is caught before a mass builds.
- Planning for the known triggers: travel, illness, starting preschool, or a new sibling. Many families loosen the diet and tighten the routine in those weeks.
- No shame. Accidents are discussed matter-of-factly; the child is never “dirty” or “naughty.”
Encopresis in an older child, the involuntary soiling that follows long-standing retention, often needs the same approach plus patience, and sometimes support from a pediatric psychologist. It resolves in most children with consistent treatment, but it is one of the clearest reasons to take toddler constipation seriously before it becomes school-age constipation.
The best outcome looks ordinary: a child who eats a reasonably varied diet, goes when she needs to, and never thinks about it. That ordinariness is built, stool by soft stool, over a season or two. It is worth the patience.
Frequently asked questions
What can I do to help my 6-year-old with constipation quickly?
Same-day steps are a five-minute toilet sit after breakfast and dinner with feet on a step, extra water, and prune or pear at each meal; anything faster, such as a suppository or an osmotic laxative, should be chosen by the child’s pediatrician. A six-year-old who is soiling, in pain or has gone several days without stool needs a clinician’s plan, not an adult laxative from the cabinet.
What foods help relieve constipation in toddlers?
Prunes, pears, peaches, plums, apricots and kiwi help most because of sorbitol and fiber, backed by oats, whole-grain bread, beans, lentils and soft-cooked vegetables. Pair every fiber-rich food with water, since fiber without fluid can firm stool. Offer fruit or vegetables at most meals and keep milk to mealtimes so it does not crowd out everything else.
Can a hot bath help with constipation in a toddler?
A warm bath can relax a tense child and many parents notice a stool follows, but there is no trial evidence that it treats constipation. The benefit is calmness, which reduces withholding. Keep the water comfortably warm rather than hot, never leave a toddler unattended, and treat the bath as a soothing extra rather than the main plan.
How much castor oil for constipation in a toddler?
Mainstream pediatric guidance does not give an amount because it does not recommend castor oil for toddlers without a clinician’s explicit direction. Castor oil is a strong stimulant laxative approved for adults, can cause cramping and dehydrating diarrhea, and has no published trials in young children. Rubbing it on the navel has no effect on the bowel.
What are the signs of constipation in toddlers?
Look for hard, dry or very large stools, pain or crying when passing them, and withholding behaviors such as tiptoeing, leg-crossing, hiding or stiffening. Other clues are recurring tummy aches, small appetite, streaks of soft stool in underwear, blood on the toilet paper, bedwetting and sudden refusal of the potty. A two-week stool log makes these patterns clear.
Is constipation in children a sign of something serious?
Rarely. Around 95 percent of cases are functional, with a normal bowel caught in a pain-withholding cycle. Medical causes such as thyroid problems, celiac disease, cow’s milk protein allergy or Hirschsprung disease are uncommon and usually come with red flags: vomiting, a swollen belly, blood through the stool, poor growth, or constipation from the first weeks of life.
Does too much milk cause toddler constipation?
It can. Milk is filling and contains no fiber, so a toddler drinking well above roughly 16 to 24 ounces a day often eats less fruit, vegetable and whole grain and drinks less water, which firms stool. Shifting milk to mealtimes and offering water between meals is one of the first changes pediatricians suggest. A true cow’s milk protein allergy is separate and needs medical assessment.
How long does treatment for toddler constipation usually take?
Longer than most families expect. Guidelines describe months rather than days, because a stretched rectum needs time to regain tone and the child needs repeated painless stools to unlearn withholding. Pediatricians typically continue a softening plan for a period after symptoms settle, then taper gradually. Stopping early is the most common reason constipation returns.
Are toddler constipation remedies like probiotics or fiber gummies worth trying?
Evidence is weak for both. Reviews find no consistent benefit from probiotics in pediatric constipation, and trials of fiber supplements in children are small and mixed. Neither replaces fluids, whole fruit, a toilet routine and, when a pediatrician advises, an osmotic laxative. Ask the clinician before adding any supplement, especially for a child under three.
Should I pause potty training if my toddler is constipated?
Usually yes, for several weeks. Pediatric guidance recommends stopping training while stools are hard or painful, softening them through diet or whatever the pediatrician recommends, and restarting once going is comfortable. Letting the child poop in a diaper in the bathroom in the meantime keeps the stool moving without fear. Children who pause and restart often train faster than those who push through.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Preparing Your Child for Congenital Correction Surgery: Consultations, Imaging and Feeding
Preparing a child for congenital heart surgery usually means a series of pre-operative consultations, imaging such as echocardiography and sometimes cardiac MRI or catheterization,…

After Newborn Jaundice Treatment: Frequent Feeds, Rechecks and What Parents Watch For
After phototherapy for newborn jaundice, most babies go home once bilirubin has fallen to a level considered safe for their age, with a repeat…

Toddler Tantrums, Talking and Potty Training: The Normal Ranges
Most toddler tantrums are a normal stage of brain development, most common between 18 months and 3 years and usually fading by age 4.…

Anesthesia for Pediatric Surgery: What Parents Can Expect Before, During and After
Pediatric anesthesia follows a predictable pathway: a pre-operative assessment, fasting guided by the 2-4-6 rule, a brief mask or IV induction, continuous monitoring by…

Why Do Videos of Movement Episodes Help? Preparing for a Pediatric Movement Assessment
Videos help because movement episodes in children are brief, unpredictable and hard to describe, and a clinician rarely witnesses one in clinic. A steady,…

Grommets (Ear Tubes): What They Are, What They Do and Whether They Fall Out
Grommets, also called ear tubes or tympanostomy tubes, are tiny hollow cylinders placed through the eardrum during a short operation. They let air into…