

Ureteral Stent or Nephrostomy Tube: Which Drainage Route Suits Your Hydronephrosis?

Key Takeaways
- A ureteral stent runs internally from kidney to bladder and leaves nothing visible, while a nephrostomy exits through the flank into an external bag.
- Randomized comparisons in infected, obstructed kidneys have found both routes relieve obstruction comparably, so no major guideline names an overall winner.
- Nephrostomy is usually placed under local anesthetic with sedation, which is why it is often chosen for people too unstable for a general anesthetic.
- A nephrostomy drains one kidney, so the other kidney keeps filling the bladder and most people continue to urinate normally.
- External compression of the ureter by a pelvic tumor can squeeze an internal stent shut, which is a common reason teams favor external drainage.
- Both devices need a written removal or exchange date, because a forgotten stent encrusts and a long-term nephrostomy must be changed every few months.
A ureteral stent and a nephrostomy tube both relieve hydronephrosis by letting trapped urine escape, but by different routes. A stent is an internal tube from kidney to bladder placed through the urethra; a nephrostomy is a tube passed through the flank into the kidney and drained into an external bag. Neither is proven superior overall; the choice depends on infection, stability, anatomy, and the planned next treatment.
It is close to midnight in an emergency department. A woman in her fifties has spent six hours doubled over with pain that started in her side and crept toward her groin. The ultrasound image on the screen shows her left kidney swollen like a water balloon, its inner drainage system stretched by urine that has nowhere to go. The doctor says two words she has never heard before, stent and nephrostomy, and asks which she would prefer.
Most people have no idea how to answer that. The ureteral stent vs nephrostomy question sounds like a choice between two gadgets, but it is really a choice between two routes out of the kidney: an inside route that runs down to the bladder, and an outside route that exits through the skin of the back. Each has a logic, each has trade-offs, and each is chosen for reasons that have more to do with the patient in front of the team than with the device itself.
This explainer walks through what each drain does, who tends to be offered which, what the following weeks usually feel like, and which warning signs should never be ignored. The decision stays with your treating team; the aim here is to make their explanation land.
Why hydronephrosis sometimes needs a drain, and sometimes does not
Hydronephrosis is the medical word for a kidney swollen with urine because the urine cannot drain normally. The kidney itself is still making urine, roughly a liter and a half a day across both kidneys in a typical adult, but the exit is blocked or narrowed, so the collecting system inside the kidney balloons under pressure.
The blockage can sit anywhere along the route. A kidney stone lodged in the ureter, the thin muscular tube that carries urine from kidney to bladder, is the most familiar cause. Others include scar tissue narrowing the ureter, a tumor pressing on it from outside, an enlarged prostate backing urine up from the bladder, pregnancy, or a congenital kink at the junction between kidney and ureter. The NHS and MedlinePlus list these as the main culprits in adults.
Pressure is the problem. A kidney under sustained back-pressure gradually loses filtering capacity, and if bacteria are trapped behind the block, urine becomes a sealed, warm culture medium. An obstructed, infected kidney is one of the few true urological emergencies, because infection can spill into the bloodstream quickly. That is why clinicians move fast when fever and obstruction appear together.
Yet not every swollen kidney needs a tube. Mild hydronephrosis with controlled pain, normal kidney function, no infection and a small stone that is likely to pass on its own is often simply watched, with repeat imaging. The same is true for the physiological hydronephrosis of pregnancy, and for many babies whose dilated kidneys are spotted on prenatal scans. Drainage is a decision, not a reflex, and the ureteral stent vs nephrostomy question only arises once the team has decided that draining is necessary.
Ureteral stent vs nephrostomy: how each drainage route actually works
Think of the kidney as a house with one door, the ureter, that has jammed. A ureteral stent props that door open from the inside. A nephrostomy tube knocks a small new opening in the back wall and runs a pipe out to the garden.
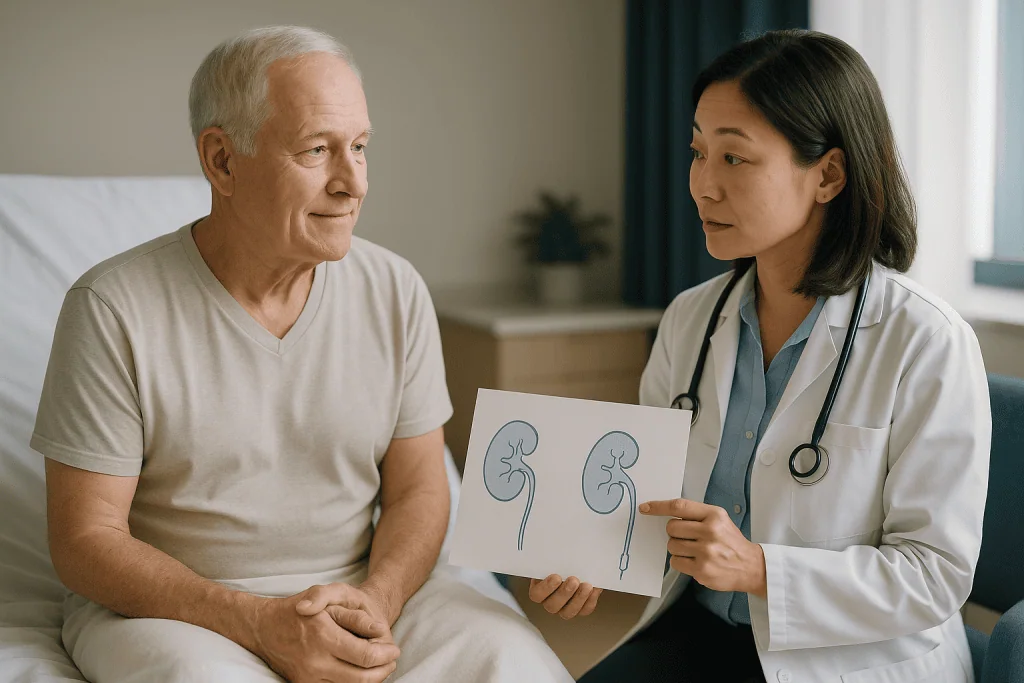
A ureteral stent is a soft, hollow plastic tube about the width of a cooked spaghetti strand, with a curl at each end. One curl sits in the renal pelvis, the funnel-shaped chamber where urine collects inside the kidney; the other curl rests in the bladder. The curls are why it is often called a double J stent. Urine flows both through the tube’s central channel and along the outside of it, because the stent gently holds the ureter open. Nothing shows on the outside of the body. The person urinates normally, and the drained urine simply joins the bladder’s usual contents.
A percutaneous nephrostomy, usually shortened to nephrostomy or PCN, takes the opposite approach. Percutaneous means through the skin. A thin catheter is passed through the skin of the flank, just below the ribs, directly into the dilated renal pelvis. Its tip forms a small pigtail loop so it cannot slip out easily. The other end connects to a drainage bag worn on the leg or clipped to the waistband. Urine from that kidney bypasses the ureter and bladder entirely.
Both routes achieve the same first goal: dropping the pressure inside the kidney within minutes. Where they differ is in what the person lives with afterward, how the procedure is done, what happens if the device fails, and what each makes possible for the next step of treatment.
How a ureteral stent is placed, step by step
Stent placement is a retrograde procedure, meaning it works backward up the urinary tract, entering where urine normally exits. It is performed by a urologist, most often in an operating room.
You lie on your back with your legs supported. Anesthesia varies: many centers use a general anesthetic so you are asleep, some use a spinal block so you are numb from the waist down, and occasionally a stent is placed under local anesthetic with sedation. Your anesthesia team decides this with you.
The urologist passes a cystoscope, a slim telescope with a light and camera, through the urethra into the bladder. Inside the bladder they identify the ureteral orifice, the small opening where the affected ureter empties. A soft-tipped guidewire is threaded through that opening and advanced up the ureter toward the kidney, past the obstruction. Live X-ray, called fluoroscopy, confirms the wire has reached the renal pelvis; a small amount of contrast dye may be injected to outline the anatomy.
The stent slides over the guidewire like a bead on a string. Once its upper curl is in the kidney, the wire is withdrawn and the lower curl springs open in the bladder. Some surgeons attach a fine thread to the bladder end that exits the urethra, so the stent can later be removed by gently pulling, without another cystoscopy. The scope comes out and the procedure is over.
Because nothing is cut, most people go home the same day unless they were admitted for infection or pain. Cleveland Clinic describes stent placement as a short, minimally invasive outpatient procedure, and that framing matches guideline practice worldwide.
How a nephrostomy tube is placed, step by step
Nephrostomy insertion is an antegrade procedure, approaching the kidney from above and outside. It is usually done by an interventional radiologist, a doctor who performs procedures using imaging for guidance, in a radiology suite rather than an operating room.

You lie on your front or slightly tilted onto your side. Most nephrostomies are placed under local anesthetic, which numbs the skin and deeper tissues of the flank, combined with intravenous sedation to keep you drowsy and comfortable. General anesthesia is not usually required, which matters enormously for someone who is septic or too unwell to be safely put to sleep.
Using ultrasound, the radiologist locates the swollen renal pelvis. The dilation that makes hydronephrosis dangerous also makes it a larger target, which is why nephrostomy is technically easier in a very distended kidney. A fine needle is guided into the collecting system, and a trickle of urine confirms correct placement. A sample is usually sent to the laboratory to check for infection.
A guidewire goes through the needle, the needle is removed, and the tract is gently widened with a series of tapered dilators. The pigtail catheter is then advanced over the wire, its loop formed and locked in the renal pelvis, and the position checked with fluoroscopy. The tube is secured to the skin with a stitch or an adhesive fixation device, a dressing is applied, and the drainage bag is connected.
Expect the flank to feel bruised for a day or two. Light blood-staining of the urine in the bag is common at first and typically clears. Because a tract now runs through muscle and kidney tissue, bleeding and dislodgement are the two complications teams watch for most closely in the first hours.
Is kidney stent placement considered surgery?
People search this question for a practical reason: they want to know whether to expect an incision, a hospital stay, and a long recovery. The honest answer is that stent placement sits in a gray zone that medicine labels a minimally invasive procedure rather than open surgery.
Nothing is cut and no stitches are placed. The stent is introduced through a natural opening, the urethra, using a telescope. In that sense it is closer to an endoscopy than to an operation. Yet it is usually performed in an operating room, under anesthesia, with a consent form, fasting instructions and a recovery bay. Hospitals code it as a surgical procedure, and your urologist is a surgeon. If someone tells you that you are having kidney stent surgery, they are not wrong; they simply mean this endoscopic kind.
What this means for you is modest. You will likely be asked not to eat for several hours beforehand because of the anesthetic, and you will need someone to take you home if you have been sedated. There is no wound to care for and no lifting restriction specific to the stent itself. Many people return to desk work within a day or two, though stent-related bladder symptoms can make the first days uncomfortable.
A nephrostomy, by contrast, is classed as an interventional radiology procedure. It leaves a puncture rather than an incision, but it does leave an external device and a dressing that need care. Neither route is the sort of surgery that involves a hospital ward for a week; both are designed to be quick ways to decompress a kidney so that the real cause can be addressed later, on a planned basis, once infection has settled and the picture is clear.
Who is usually offered a stent, who is steered toward a nephrostomy, and who is asked to wait
Guidelines from major urology bodies agree on a frustrating but honest point: for the most urgent scenario, an obstructed kidney with infection, both routes work, and neither has been shown to be clearly better at relieving the obstruction or resolving sepsis. Randomized comparisons have been small and have found similar outcomes. So the choice rests on patient and situation factors rather than on a universal winner.
Teams often lean toward a ureteral stent when the person is stable enough for anesthesia, the ureter is likely passable with a guidewire, a stone is the cause and the same anesthetic might allow later stone treatment, or the person strongly prefers nothing external. Stents are also chosen when a bleeding tendency makes puncturing the kidney riskier.
A nephrostomy tends to be favored when someone is septic or hemodynamically unstable and needs the fastest decompression under local anesthetic; when a stent attempt has failed or the ureter is blocked by a large, impacted stone; when a tumor in the pelvis or abdomen is compressing the ureter from outside, because stents can be squeezed shut by external pressure; when there is a urinary diversion or an abnormal bladder; or when the kidney will need percutaneous access anyway for a planned stone operation through the back.
Who is asked to wait? Someone with mild, uninfected hydronephrosis, stable kidney function and a small stone likely to pass may be observed with pain control and repeat imaging. Pregnant women with the common, mild hydronephrosis of pregnancy are usually monitored unless pain or infection develops. Infants with prenatally detected dilation are often followed with scans rather than drained. Watchful waiting is a legitimate option, not an omission.
Ureteral stent vs nephrostomy at a glance: a side-by-side comparison
The table below sets the two routes next to each other. It describes typical practice, not a rule for any individual; your team may have good reasons to depart from any row.
| Feature | Ureteral (double J) stent | Percutaneous nephrostomy |
|---|---|---|
| Route | Through urethra and bladder, up the ureter | Through flank skin directly into kidney |
| Who places it | Urologist, usually in an operating room | Interventional radiologist, in an imaging suite |
| Anesthesia | Often general or spinal | Usually local anesthetic plus sedation |
| Visible on the outside | No (sometimes a fine removal thread) | Yes: tube, dressing and drainage bag |
| Urination | Normal, via bladder | Drained kidney bypasses bladder; other kidney still fills it |
| Common discomforts | Urgency, frequency, flank ache when voiding, blood-tinged urine | Site soreness, bag management, dressing changes |
| Works against external compression | Less reliably | More reliably |
| Main early risks | Infection, migration, failure to pass obstruction | Bleeding, dislodgement, site infection |
| Can be monitored directly | No; output mixes with bladder urine | Yes; output from that kidney measured in bag |
| Removal or exchange | Cystoscopy or thread pull; exchange if long-term | Exchange over a wire every few months if long-term |
Two rows deserve emphasis. First, a nephrostomy lets the team measure exactly how much urine the blocked kidney is producing, which is genuinely useful when there is doubt about how well that kidney still works. Second, when a cancer in the pelvis is squeezing the ureter shut, an internal stent can itself be compressed, and clinical experience and guideline reviews consistently favor external drainage in that setting. Everything else is a balance of comfort, logistics and what comes next.
Can someone with a nephrostomy tube still urinate?
Yes, in almost every case. This is one of the most common worries people bring to the ward, and it comes from a reasonable misunderstanding about where urine actually comes from.
Each kidney produces its own urine and sends it down its own ureter to the bladder. A nephrostomy tube diverts the output of one kidney into a bag. The other kidney carries on exactly as before, filling the bladder, and you will continue to pass urine through the urethra in the normal way. The volume may be a little lower than you are used to, because half the supply is now going into the bag, but the sensation and the mechanics are unchanged.
Even the drained kidney may contribute. If the obstruction is partial, some urine can still trickle past the blockage down the ureter to the bladder. People are sometimes surprised to find urine in both the bag and the toilet from what seems like the same side; this is normal and not a sign that the tube has failed.
There are exceptions worth naming. If both kidneys are obstructed and both have nephrostomy tubes, very little urine reaches the bladder and you may pass almost none. If you have only one functioning kidney and it is the one being drained, the same applies. In these situations the bladder is simply quiet rather than broken, and normal urination returns once internal drainage is restored.
With a ureteral stent, the question does not arise: all urine still reaches the bladder. What changes is how urination feels, which the next sections cover. If you have a nephrostomy and notice that bladder urine has stopped completely when it previously had not, mention it to the team, because it may mean the other side has become blocked too.
What the first days and weeks usually look like with each drain
Relief of pressure pain is often quick, sometimes within hours of either procedure. What follows differs sharply between the two routes.
With a stent, the bladder end of the tube is the troublemaker. It tickles the bladder lining, producing urgency, frequency, a feeling of incomplete emptying, and sometimes a dull flank ache at the moment of urinating, because the stent lets a little urine flow backward up to the kidney when the bladder contracts. Pink or rust-tinged urine is common, especially after activity. Cleveland Clinic notes that most people have some stent-related symptoms, which usually ease as the body adapts but may persist for as long as the stent is in. Medicines that relax bladder muscle or the ureter are sometimes prescribed to soften these symptoms; whether they suit you is your clinician’s call.
Stents placed for a stone are typically removed or replaced at the time of stone treatment, often within a few weeks. Stents left long-term, for example for a narrowing or a tumor, are exchanged on a schedule because minerals slowly coat them; Cleveland Clinic cites roughly three months as a common upper limit before a stent is changed, though your team sets your interval.
With a nephrostomy, the first two or three days bring flank soreness and light blood in the bag. A nurse will teach you or a family member to empty the bag, keep the tubing free of kinks, change the dressing, and sometimes flush the tube with sterile saline if instructed. Showering is usually possible once the site has sealed, with the dressing protected. Long-term tubes are exchanged in the radiology department every few months. Many people return to most daily activities within a week, adjusting clothing to accommodate the bag.
Risks and complications of each route: what the evidence actually shows
Both drains are safe in the hands of experienced teams, and both carry risks that deserve plain description rather than reassurance.
Ureteral stents can introduce or worsen infection, since a foreign body sits in the urinary tract. They can migrate up or down, usually detected on a follow-up X-ray. A guidewire may fail to pass a tightly impacted stone or a long stricture, in which case the team pivots to a nephrostomy. Over months, stents encrust with mineral deposits, and a stent that is forgotten becomes a serious problem, occasionally requiring major surgery to remove. The most consistent downside, though, is not dangerous at all: the daily bladder irritation described above, which trials comparing the two routes repeatedly identify as the main quality-of-life penalty of stenting.
Nephrostomy risks cluster around the puncture. Significant bleeding is uncommon but is the complication radiologists watch hardest, especially in people on blood thinners. The tube can fall out, particularly in the first days before the tract matures, and a tract that has closed cannot simply be re-threaded. The skin site can become infected. Very rarely, the needle path can injure a neighboring structure such as the bowel or the lining of the lung, which is why upper-pole punctures are planned carefully. The external bag brings practical burdens: leaks, kinks, interrupted sleep and the visible reminder of illness.
What about which is safer? Randomized trials in people with infected, obstructed kidneys have found both routes relieve the obstruction and clear infection with comparable success, differing mainly in procedure time, radiation exposure and patient-reported discomfort. No major guideline declares either route superior overall. That is why the decision is individual, and why an honest team will tell you the evidence does not pick a winner.
Stent, catheter, urostomy, nephrostomy: untangling the terms
Four words get mixed up at bedsides every day, and the confusion matters because each describes a different plumbing arrangement.
A urinary catheter, in everyday usage, means a Foley catheter: a flexible tube passed through the urethra into the bladder, held in place by a small inflated balloon, draining bladder urine into a bag. It solves a bladder-emptying problem, not a kidney problem. If the blockage is below the bladder, as with a very enlarged prostate causing hydronephrosis on both sides, a catheter alone may relieve the kidneys.
A ureteral stent is internal and lives between kidney and bladder. It solves a ureter problem. Strictly speaking it is also a type of catheter, which is why some clinicians say stent and catheter interchangeably, but to a patient the distinction is enormous: a stent has no external bag and does not pass through the urethra once placed.
A nephrostomy drains a kidney directly through the skin of the back to an external bag. It is temporary or long-term, but it is not a surgically constructed permanent opening; the tract closes within days once the tube is removed.
A urostomy is different in kind. It is a permanent opening created during surgery, most often after the bladder has been removed for cancer. The surgeon uses a short segment of small intestine as a conduit, connects both ureters to it, and brings its end to the abdominal wall as a stoma, where a bag collects urine continuously. Urine never enters a bladder again. Cleveland Clinic and MedlinePlus describe urostomy as a form of urinary diversion, a category that also includes internal pouches.
A hybrid also exists: the nephroureteral stent, which enters through the flank like a nephrostomy but extends down the ureter into the bladder, allowing drainage both externally and internally.
What people often get wrong about ureteral stents and nephrostomy tubes
Fear fills the gaps that explanation leaves. These are the misunderstandings clinicians hear most often, and what the evidence says instead.
Having a nephrostomy means the kidney is failing. Not necessarily. A nephrostomy is chosen for logistical and safety reasons, such as sepsis, a blocked ureter that could not be passed, or external compression. It says nothing about how much function the kidney has left. In fact, measuring the bag output is one of the best ways to find out.
A stent means the stone has been dealt with. Usually the opposite. A stent placed in an emergency bypasses the stone to protect the kidney; the stone itself is typically treated at a later planned procedure. People sometimes stop attending follow-up because the pain has gone, and a stone then sits quietly for months.
Stents are permanent. Most are temporary, measured in weeks. Even long-term stents are exchanged on a schedule, because left indefinitely they encrust and can obstruct. Cleveland Clinic and NHS patient guidance both stress that a stent must have a planned removal or exchange date.
You cannot shower or move normally with a nephrostomy. Once the site has sealed, showering with the dressing protected is generally allowed, and walking, desk work and gentle activity are encouraged. The restrictions are about protecting the tube from being pulled, not about immobility.
A nephrostomy is only for cancer. Stones and strictures account for a large share of nephrostomies, particularly emergency ones.
Blood in the urine means the device has failed. Light blood-staining is expected with both drains, especially early and after exertion. What matters is heavy bleeding, clots, or urine that is suddenly thick and dark, which belong in the red-flag list below.
Questions to ask your care team before choosing a drainage route
A good conversation about ureteral stent vs nephrostomy takes ten minutes and saves weeks of confusion. These questions tend to unlock the most useful answers; take them in, or hand the list to someone accompanying you.
- What is blocking my kidney, and is this drain a bridge to a later treatment or a longer-term solution?
- Why are you recommending this route for me specifically, and what would make you switch to the other?
- How much function does the affected kidney appear to have, and will draining it tell us more?
- What anesthesia will I have, and does my heart, lung or bleeding history affect which route is safer?
- If the stent cannot be passed, what is the plan on the day?
- Which everyday symptoms should I expect, and which should prompt a call?
- Who do I contact out of hours if the tube falls out, stops draining, or I develop a fever?
- When will the device be removed or exchanged, and who is responsible for booking that?
- Will I need imaging or blood tests while the drain is in place?
- How will this affect work, driving, exercise, sex and travel in the coming weeks?
- Are there medicines you are considering to ease symptoms, and how do they work?
- What is the definitive treatment plan once the kidney has settled, and roughly when?
Write down the removal or exchange date before you leave. A device without a date attached to it is the single most preventable source of harm in this whole area. If the plan changes, ask for the new date in writing. Your team makes the clinical decisions; your job is to make sure the timeline never goes quiet.
When to call your doctor: red-flag signs with a stent or nephrostomy
Most problems with either drain announce themselves early and clearly. Seek urgent care, by calling your urology or radiology team, your out-of-hours service, or emergency services if you are very unwell, for any of the following.
- Fever, shaking chills, or feeling suddenly and profoundly unwell. In someone with an obstructed kidney this can signal infection spreading to the blood and needs same-day assessment.
- Severe or rapidly worsening flank or abdominal pain that is not controlled by what you have been prescribed.
- A nephrostomy tube that has fallen out, pulled back, or stopped draining for several hours while you feel pain or pressure building. Keep the tube and dressing, do not try to reinsert anything, and go in; tracts can close within a day.
- Heavy bleeding: urine that is thick red, contains clots, or a nephrostomy bag that fills with blood rather than pink-tinged urine.
- Leakage of urine around the nephrostomy site that soaks the dressing repeatedly, or redness, warmth and pus at the skin.
- Being unable to pass urine from the bladder at all, or passing only drops with a painful, full feeling.
- With a stent, a sudden return of the original colicky pain, which can mean the stent has blocked or moved.
- Vomiting that stops you keeping fluids down, dizziness on standing, or confusion.
- A stent that has visibly protruded from the urethra, or a removal thread that has been accidentally pulled.
Call during working hours, rather than waiting for the next appointment, if symptoms are milder but persistent: ongoing low-grade temperatures, bladder spasms that stop you sleeping, a steady increase in blood-staining, or any doubt about the removal date. Your treating team would far rather hear about a false alarm than see a sealed, infected kidney arrive late. Every decision about adjusting, exchanging or removing a drain rests with them; your part is to report early and specifically.
Frequently asked questions
Is kidney stent placement considered surgery?
It is classed as a minimally invasive endoscopic procedure rather than open surgery. No incision is made; the stent passes through the urethra using a telescope, usually under general or spinal anesthesia in an operating room. Hospitals code it as surgical and a urologist performs it, but there is no wound and most people go home the same day.
Can someone with a nephrostomy tube still urinate?
Yes, in nearly all cases. The tube drains only the obstructed kidney; the other kidney continues to send urine to the bladder, so normal urination carries on, often with slightly less volume. Only people with tubes in both kidneys, or a single functioning kidney that is drained, pass very little bladder urine until internal drainage is restored.
What is the difference between a urinary stent and a catheter?
A urinary catheter, usually a Foley, is passed through the urethra into the bladder and drains bladder urine to an external bag, solving a bladder-emptying problem. A ureteral stent sits entirely inside the body between kidney and bladder, holding the ureter open with no external part. Technically a stent is a kind of catheter, but patients experience them very differently.
What is the difference between a urostomy and a nephrostomy?
A nephrostomy is a temporary or exchangeable tube passed through the flank into the kidney; remove it and the tract closes within days. A urostomy is a permanent surgical opening, usually created after bladder removal, in which a segment of bowel carries urine from both ureters to a stoma on the abdomen. One is a drain; the other is a reconstructed urinary system.
Nephrostomy tube vs stent: which one hurts more?
They hurt differently rather than more or less. Stents cause bladder irritation: urgency, frequency and a flank twinge when urinating, which can last as long as the stent stays in. Nephrostomy causes flank soreness for a few days plus the daily inconvenience of a bag. Trials comparing the routes report similar pain overall but more bladder-type symptoms with stents.
Double J stent vs nephrostomy: which is better for an infected, blocked kidney?
The evidence does not favor either. Small randomized trials in people with obstruction and infection found both routes decompressed the kidney and resolved infection with comparable success. Teams usually choose based on how unwell the person is, whether a general anesthetic is safe, whether the ureter can be passed, and what the next planned treatment will be.
How long can a ureteral stent stay in?
Stents placed for a stone are typically removed within weeks, at the time of definitive stone treatment. Stents used long-term for a stricture or tumor are exchanged on a schedule because minerals coat them; Cleveland Clinic cites roughly three months as a common limit before exchange. Your team sets your exact interval, and the date should be written down.
Percutaneous nephrostomy vs ureteral stent: why would a stent fail?
A stent can fail to pass a tightly impacted stone or a long narrowing during placement, in which case the team usually converts to a nephrostomy. Once in place, a stent can be compressed by a tumor pressing on the ureter from outside, can migrate, or can block with mineral deposits over time. External drainage is less affected by compression.
Can a nephrostomy be converted to an internal stent later?
Often, yes. Once infection has settled or swelling has reduced, a wire can be passed down the ureter through the nephrostomy tract and an internal stent placed antegrade, after which the external tube is removed. Whether this is possible depends on what caused the blockage and whether the ureter can be opened; your team will assess this with imaging.
Does hydronephrosis cause permanent kidney damage?
It can if pressure persists, which is why timely drainage matters, but function often recovers once the obstruction is relieved, especially when the blockage has been brief. How much returns depends on how long and how severely the kidney was obstructed and whether infection occurred. Follow-up imaging and blood tests after drainage show your team how the kidney is recovering.
References
- Cleveland Clinic: Hydronephrosis
- NHS: Hydronephrosis, Treatment
- MedlinePlus: Hydronephrosis of one kidney
- NIH NIDDK: Treatment for Kidney Stones
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Renal Pharmacotherapy Explained: How Medicines Are Adjusted When Kidneys Filter Less
Medication management in kidney disease means adjusting medicines because the kidneys clear many drugs from the blood, and when filtration falls those drugs can…

After an Enlarged Prostate Procedure: Catheter Care, Fluids and the First Weeks of Recovery
After an enlarged prostate procedure such as TURP, a urinary catheter is usually left in for about one to three days to drain the…

Easing Epididymitis Pain Safely: Scrotal Support, Cold Packs and Rest Your Urologist Recommends
Epididymitis pain relief rests on three measures that urology guidelines consistently list: supporting and elevating the scrotum with snug underwear or a jockstrap, applying…

How Kidney Function Tests Guide Renal Pharmacotherapy and Why They Are Repeated
Kidney function tests before medication measure how well the kidneys filter blood, usually through serum creatinine, an estimated glomerular filtration rate (eGFR), and a…

After Peyronie’s Injection Treatment: Bruising, Discomfort and the Follow-Up Schedule
After a Peyronie's injection, bruising, swelling and tenderness of the penis are expected and usually fade over about one to two weeks, while the…
What Does the Surgeon Actually See in Robotic Urology? The View the Patient Never Notices
In robotic urology, the surgeon sits at a console a few feet from the patient and looks into a magnified, high-definition, three-dimensional view sent…