

What Coronary Angiography Results Lead To: Medication, Angioplasty, Stenting or Surgery

Key Takeaways
- A narrowing on an angiogram does not automatically mean a stent; for stable angina, guideline-level advice starts with medication that acts on every artery at once rather than on one spot.
- Pressure-wire measurements of blood flow across a narrowing often carry more weight in the decision than the visual percentage written on the report.
- Bypass surgery is typically favoured for left main disease, three-vessel disease and diabetes with multi-vessel disease, where grafts tend to give more durable results than multiple stents.
- After a drug-eluting stent, the artery lining takes months to grow over the mesh, which is why the NHS describes dual antiplatelet therapy commonly lasting up to a year, set by the cardiologist.
- The puncture site in the wrist or groin seals within hours but can bruise for up to a couple of weeks, and a pulsing swelling there needs assessment rather than waiting.
- An angiogram shows the arteries, not heart failure itself; it identifies whether blocked vessels are the cause of a weak pump, while an echocardiogram measures the pumping.
Coronary angiogram results usually lead to one of three paths: medication and risk-factor control when narrowings are mild or stable; angioplasty with a stent when a significant blockage is suitable for a catheter-based repair; or bypass surgery when disease is extensive, involves the main left artery, or affects several vessels. A cardiology team weighs the images, symptoms and other tests before recommending the next step.
The pictures come up on the screen before you have even sat up. Grey branches of contrast dye, a pause from the cardiologist, a quiet word to a colleague, and then a sentence you will replay for days: there is a narrowing, and we need to talk about what to do. Most people lying on a catheter lab table have rehearsed the test itself. Almost nobody has rehearsed what comes after.
That gap is where worry grows. Patients and families often assume the result is binary, either all clear or straight to surgery, when in practice coronary angiogram results next steps fall across a wide spectrum, and the most common of them involves no further procedure at all.
This explainer walks through what the images show, how a heart team reads them, why medication is so often the first answer, who is offered a stent or bypass, and what the days and weeks afterwards tend to look like. The decision belongs to your treating team. Understanding the logic behind it belongs to you.
Coronary angiogram results explained: what the images actually show
Coronary angiography is an X-ray test in which a thin, flexible tube called a catheter is guided from an artery in the wrist or groin up to the heart, and a contrast dye is injected so the coronary arteries show up as dark channels on a moving X-ray image. Mayo Clinic describes it as the most accurate way to see whether, where and how much the arteries that feed the heart muscle have narrowed.
What the cardiologist is looking at is plumbing in motion. Three main vessels matter: the left anterior descending artery down the front of the heart, the circumflex around the side, and the right coronary artery. A short trunk called the left main stem feeds the first two, which is why disease there carries so much weight in decision-making.
A narrowing is called a stenosis. Reports describe each one by its location, its length, and roughly how much of the vessel diameter it takes up, often as a percentage. They also note the flow beyond the narrowing, whether the vessel wall looks calcified, and whether the artery is completely blocked. In some labs a pressure wire is passed through the narrowing to measure fractional flow reserve, a ratio comparing blood pressure before and after the blockage; it answers a question the picture alone cannot, which is whether the narrowing is actually starving the muscle of blood.
Many angiograms also include a ventriculogram, a brief dye injection into the main pumping chamber that shows how vigorously the heart squeezes. Put together, these pieces give the team a map: not just where the problem is, but how much it matters and how fixable it looks.
What is the next step after an angiogram?
The next step depends almost entirely on three things: what the images show, why the test was done, and how you have been feeling. The NHS groups the possible outcomes plainly. Some people are told their arteries are clear or only mildly narrowed and are managed with medication and lifestyle changes. Some have a narrowing suitable for angioplasty and a stent, which can sometimes be done during the same procedure. Some have disease that is better treated with coronary artery bypass surgery.
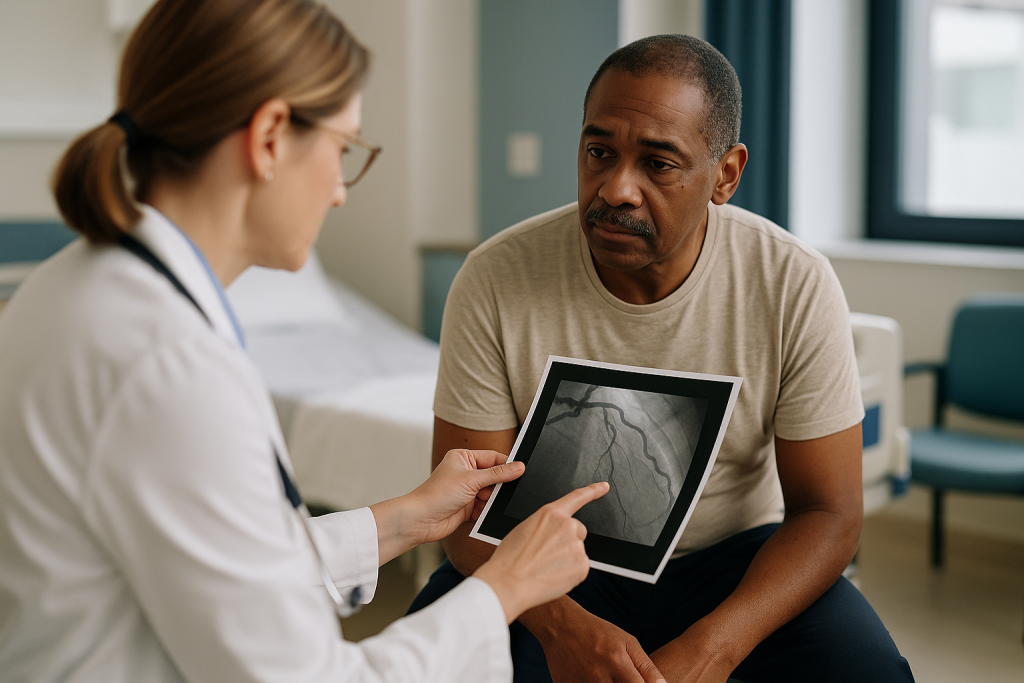
Timing matters as much as the destination. If the angiogram was done urgently because of a heart attack, the team is often already prepared to open the blocked artery there and then. If it was a planned test for chest discomfort on exertion, the images are usually reviewed more deliberately, sometimes in a multidisciplinary meeting, and the plan is discussed with you afterwards rather than on the table.
For most planned procedures, the NHS notes that the test itself takes between 30 minutes and 2 hours and that people typically go home the same day. You should leave with at least a provisional understanding of what was found, who will contact you, and when. If a decision is pending, ask what the options under consideration are and who is weighing them.
Whatever the outcome, two things almost always follow. The first is a review of your medicines, because the test gives the prescribing clinician firmer ground for what to continue, adjust or add. The second is attention to risk factors: blood pressure, cholesterol, blood sugar, smoking, activity and weight. A clear angiogram is good news, but it is not a verdict on the next twenty years; the processes that cause plaque do not stop because the pictures looked reassuring.
What happens if they find something during an angiogram?
Finding something is common; angiograms are done precisely because there is reason to look. The important distinction is between finding plaque and finding a problem that needs a procedure. Coronary plaque, a build-up of fat, cholesterol and calcium inside the artery wall, is present in many adults past middle age, and a scattering of mild irregularities does not by itself call for a stent.
If the cardiologist sees a narrowing that looks significant, several things can happen. In an emergency setting, for example a heart attack with an artery fully blocked, the team may proceed straight to angioplasty. In a planned setting, some cardiologists will discuss a stent with you on the table if you consented to that possibility beforehand; this is sometimes called an ad hoc procedure. Others will stop, document the findings and arrange a follow-up conversation, especially when the picture is complex.
You may also hear that the team wants more information before deciding. A pressure wire study can be done during the same session. Imaging from inside the artery, using a tiny ultrasound or light-based probe on the catheter, can clarify how severe a borderline narrowing really is. A separate test of heart muscle viability or stress imaging may be ordered afterwards if it is unclear whether a chronically blocked vessel is still feeding living tissue.
What should not happen is a decision made in silence. Cleveland Clinic and the NHS both describe the cardiologist explaining the findings and options with the patient, and a stent placed during the procedure should be something you agreed to in principle before the test began. If you wake up with a stent you were not expecting, the team should be able to explain exactly why.
Why medication alone is often the first answer
Here is the part that surprises people most: a narrowing on an angiogram does not automatically mean a stent. For stable coronary artery disease, meaning chest discomfort that comes predictably with exertion rather than at rest, guideline-level advice from the NHS, the American Heart Association and major cardiology societies starts with what clinicians call optimal medical therapy.

That phrase bundles several classes of medicine, each with a different job. Antiplatelet drugs make blood cells less sticky so a clot is less likely to form on a cracked plaque. Statins lower LDL cholesterol and are thought to stabilise the fatty core of plaques so they are less likely to rupture. Beta blockers slow the heart and reduce how much oxygen it demands. Nitrates widen vessels and ease angina when it happens. Medicines for blood pressure and, where relevant, diabetes work on the conditions that drive plaque in the first place.
The reasoning is mechanistic. A stent treats one spot in one artery. Plaque is a disease of the whole arterial tree, and the plaques most likely to cause a heart attack are not always the ones that look worst on the picture. Medication acts on every segment at once. For many people with stable symptoms, guidelines treat a stent as something to add if symptoms persist despite medication, not as the opening move.
This is not a lesser option or a way of putting you off. It is the approach with the broadest evidence base for reducing future events. If your team recommends medication alone, it is reasonable to ask what would prompt them to reconsider, how symptoms will be monitored, and when you will be reviewed. Decisions about starting, stopping or adjusting any medicine rest with the prescribing clinician who knows your full history.
Who is usually offered angioplasty and stenting, and who is asked to wait
Percutaneous coronary intervention, usually shortened to PCI, is the umbrella term for angioplasty, in which a small balloon is inflated inside a narrowing to widen it, and stenting, in which a tiny wire-mesh tube is left behind to hold the artery open. Two groups are most often offered it.
The first is people having a heart attack or an unstable pattern of chest pain, where a plaque has cracked and a clot is blocking flow. Here speed matters and the evidence strongly favours opening the artery promptly; the American Heart Association describes catheterisation as the standard route to doing so. The second group is people with stable angina whose symptoms limit daily life despite medication and whose angiogram shows a discrete narrowing that a catheter can reach.
Anatomy decides a great deal. A short, uncomplicated narrowing in a single vessel is the classic stent candidate. Long, heavily calcified segments, narrowings at branch points, chronically blocked vessels and small, tortuous arteries are technically harder and sometimes better served another way.
Who is asked to wait, or steered elsewhere? People whose narrowings look moderate but whose pressure-wire readings suggest flow is adequate are often managed with medication first. People with diabetes and disease in several vessels frequently do better with bypass surgery according to guideline summaries, and will be referred to a surgeon rather than stented. People with other serious illness may be asked to pause while that is addressed, and anyone taking anticoagulants, or with kidney problems that make the contrast dye risky, may need their plan adjusted first.
Waiting is rarely neglect. It is usually the team choosing the option whose benefit, for your specific anatomy and health, most clearly outweighs its risk.
What happens during angioplasty and stent placement
The mechanics are a close cousin of the angiogram itself, which is why the two can be combined. A catheter goes in through the wrist or groin under local anaesthetic, and you are awake, usually with a mild sedative. The NHS notes the procedure typically takes between 30 minutes and 2 hours, longer for complex cases.
A very fine guidewire is threaded across the narrowing. Over it travels a deflated balloon, positioned using X-ray and contrast. The balloon is inflated for a few seconds, compressing the plaque against the artery wall; you may feel a brief tightness in the chest while flow is interrupted, which the team will warn you about. The balloon is deflated and withdrawn, and a stent mounted on a second balloon is placed across the same spot and expanded until it presses into the vessel wall.
Nearly all stents used today are drug-eluting, meaning they are coated with a medicine that slowly releases over weeks to months and discourages the artery lining from overgrowing inside the mesh, a process called restenosis. Bare-metal stents are now used only in specific circumstances.
Afterwards, the artery wall needs time to grow a smooth lining over the metal. Until it does, the stent is a foreign surface where a clot can form. That is why the NHS describes a period of dual antiplatelet therapy, two blood-thinning medicines taken together, commonly for up to a year after a stent, with the exact duration set by the cardiologist based on your bleeding risk and the reason the stent was placed. Stopping those medicines early without medical advice is one of the few things that can turn a routine stent into an emergency, so any change should go through the prescribing team.
When bypass surgery is recommended instead of a stent
Coronary artery bypass grafting, abbreviated CABG, is open-chest surgery in which a surgeon takes a blood vessel from elsewhere in the body, usually an artery from inside the chest wall or a vein from the leg, and attaches it so blood detours around a blocked section of coronary artery. The NHS describes it as a treatment for people whose arteries are too narrowed or blocked for angioplasty to be appropriate.
Several patterns on an angiogram push the recommendation towards surgery. A significant narrowing in the left main stem, because so much heart muscle depends on that one trunk. Disease in all three major vessels, particularly when the pumping function is already weakened. Diabetes combined with multi-vessel disease, where guideline summaries report more durable results from grafts than from multiple stents. Long, calcified or branching lesions that a stent would struggle to cover. And some chronically blocked vessels that a wire simply cannot cross.
The appeal of surgery is durability and completeness: a graft bypasses not only the worst narrowing but the plaque-prone segment around it. The cost is a bigger operation. The NHS notes that most people stay in hospital for about a week and need around 12 weeks to recover, and that risks include wound infection, bleeding, irregular heart rhythms, stroke and, rarely, heart attack during or after the operation. Some operations are done with the heart still beating; others use a heart-lung machine.
Choosing surgery is not a sign that your disease is hopeless. It is the team concluding that the shape of your arteries favours a solution that lasts, and accepting a longer recovery to get it. Age alone is not a bar; overall fitness, frailty and other conditions carry more weight in the assessment.
Medication, stent or surgery: how the options compare
Seeing the three paths side by side makes the logic easier to follow. The table summarises typical patterns described in NHS and American Heart Association patient resources; your own situation may differ, and the matching of findings to treatment is always an individual judgement by the treating team.
| Question | Medication and risk-factor control | Angioplasty with stent | Bypass surgery (CABG) |
|---|---|---|---|
| Typical angiogram picture | Mild or moderate narrowings; stable symptoms; adequate flow on pressure wire | Discrete, reachable narrowing in one or two vessels; heart attack with blocked artery | Left main disease; three-vessel disease; diabetes with multi-vessel disease; complex lesions |
| How it works | Reduces clot risk, stabilises plaque, lowers oxygen demand across all arteries | Mechanically widens one narrowing and props it open with mesh | Reroutes blood around blocked segments using grafted vessels |
| Anaesthetic | None | Local, with sedation | General |
| Typical hospital stay (NHS) | Outpatient | Same day or overnight | About 7 days |
| Typical return to usual activity (NHS) | Immediate | Around a week for most activities | Around 12 weeks |
| Main risks | Medicine side effects; symptoms may persist | Bleeding at access site, artery damage, stent clot, restenosis, rare heart attack or stroke | Wound infection, bleeding, rhythm problems, stroke, rare heart attack |
| Often chosen when | Symptoms are controlled and disease is stable | Symptoms persist despite medication, or during a heart attack | Disease is extensive or anatomy unsuitable for stents |
Two caveats. First, these are not rival camps; nearly everyone who has a stent or an operation also takes long-term medication, because the underlying disease continues. Second, the categories blur at the edges. Hybrid approaches exist, and a person who starts on medication may move to a procedure later if symptoms change. The table shows tendencies, not rules.
The stent or bypass decision: who actually decides
When an angiogram shows disease that could be handled either way, the choice is not meant to rest on one person’s preference. European and American guidelines encourage a heart team approach: an interventional cardiologist who places stents, a cardiac surgeon, and often the general cardiologist who knows you, reviewing the images together. The point is to cancel out the natural pull each specialist feels towards their own tool.
They weigh anatomy first. How many vessels are involved, where the narrowings sit, how long and calcified they are, and whether the left main is affected. Scoring systems that assign points to each feature help standardise this. Then they weigh you: age and frailty, diabetes, kidney function, lung disease, previous surgery, how well the heart pumps, and how much risk a general anaesthetic would carry. Finally they weigh preference, because a person who cannot take a year of dual antiplatelet therapy, or who dreads open surgery, is a legitimate part of the equation.
Patients are sometimes frustrated that this takes days rather than minutes. The delay is usually a sign that the case is genuinely balanced. A clear-cut single narrowing would have been stented. A blocked left main would have gone to surgery. The in-between cases earn the meeting.
You are entitled to hear the reasoning. Ask what the team discussed, whether the recommendation was unanimous, and what the realistic alternative would involve. If you want a second opinion, that is a normal request in cardiology and should not strain the relationship with your team. Shared decision-making is written into the guidelines precisely because the right answer depends on values as well as pictures, and only you hold the values.
What happens after an angiogram: the following days and weeks
The immediate aftermath is about the puncture site. If the wrist was used, a tight band is applied and loosened over a few hours. If the groin was used, you lie flat for a period while the artery seals, sometimes with a small closure plug. The NHS advises that most people go home the same day and should have someone with them overnight, and that you should not drive or do anything strenuous until the day after.
Over the first week, expect a bruise and some tenderness where the catheter went in; the NHS notes bruising can take a couple of weeks to fade and that a small lump under the skin is common. Drink fluids to help the kidneys clear the contrast dye. Light activity is encouraged; lifting, pushing and heavy exercise are not until the site has settled. Mayo Clinic suggests avoiding strenuous activity for a few days. Return to desk work is often possible within a few days, physical work later, and your team will give specific advice.
If a stent was placed, the pattern is similar with one addition: the medicine regimen becomes central. You will usually be discharged with a clear written plan and a follow-up appointment, and cardiac rehabilitation, a supervised programme of exercise and education, is typically offered. The NHS advises that most people can return to normal activities within about a week of angioplasty, with driving rules depending on whether the stent was planned or placed during a heart attack.
If bypass surgery is the plan, the weeks after the angiogram are about preparation: pre-operative assessment, anaesthetic review, possibly dental checks, and a date. If medication is the plan, the weeks are about settling into it and noticing how your symptoms respond, with a review booked to reassess.
How long does it take for an artery to heal after an angiogram?
This question usually means two different arteries, and they heal on very different clocks.
The first is the access artery in the wrist or groin, which was punctured by the catheter. The hole itself seals within hours, which is why a pressure band or a short period lying flat is enough for most people. The surrounding tissue takes longer. The NHS describes bruising lasting up to a couple of weeks and advises avoiding heavy lifting for about a week so the seal is not disturbed. A firm lump at the site is usually a small collection of blood called a haematoma that the body reabsorbs. Rarely, the artery wall fails to seal properly and a pulsing swelling called a pseudoaneurysm forms, which needs assessment; that is one reason the site should be checked if it swells or becomes painful rather than steadily better.
The second artery is the coronary artery itself, and it only needs healing if a stent was placed. Here the timeline is months, not days. The mesh sits bare against flowing blood until a thin layer of cells grows over it. With drug-eluting stents, which deliberately slow that cell growth to prevent the artery re-narrowing, the lining takes longer to form than with older bare-metal designs. This is the biological reason behind the extended period of dual antiplatelet therapy that the NHS describes as commonly lasting up to a year, and why the duration is set by the cardiologist rather than by how well you feel.
If your angiogram showed no need for a stent, there is nothing inside the heart to heal. The coronary arteries were only photographed. The recovery is all about the wrist or groin.
Can you see heart failure on an angiogram?
Not directly, and the distinction matters. Heart failure is a condition in which the heart muscle cannot pump strongly enough, or relax well enough, to meet the body’s needs. It is a diagnosis made from symptoms, examination, blood tests and, above all, an echocardiogram, the ultrasound scan that measures how much blood the main chamber ejects with each beat.
What a coronary angiogram does show is one of the commonest causes of heart failure: coronary artery disease that has damaged muscle through previous heart attacks or chronic under-supply. If a ventriculogram is included, the dye injection into the left ventricle gives a rough visual impression of how the chamber contracts, and a cardiologist can see areas that move poorly or not at all. Pressure measurements taken inside the heart during the catheterisation can also reveal elevated filling pressures consistent with a struggling pump.
So the angiogram contributes evidence rather than a verdict. People with known heart failure are often sent for angiography precisely to answer the question of cause: is this muscle weak because the arteries are blocked, in which case restoring blood flow by stent or bypass might help, or is it weak for another reason, in which case the arteries will look clear and attention turns elsewhere? MedlinePlus lists heart failure and valve problems among the reasons cardiac catheterisation may be ordered.
If you have been told your heart function is reduced, the angiogram result will be read alongside your echocardiogram, not instead of it. A clear angiogram in someone with heart failure is informative because it rules out the ischaemic cause. A blocked angiogram in the same person reshapes the whole treatment conversation, because fixing the supply may be part of treating the pump.
What people often get wrong about coronary angiogram results next steps
The first myth is that a stent fixes the disease. It treats a narrowing. Plaque continues to form elsewhere, and the plaques most likely to rupture are not always the biggest. Medication and risk-factor control remain the backbone of treatment whether or not metal goes in, and a stent is not a licence to abandon them.
The second is that a percentage on the report tells you how dangerous a narrowing is. Angiographic percentages are visual estimates of diameter, and two cardiologists can read the same image differently. Pressure-wire measurements and the pattern of symptoms often matter more than the number. A narrowing that looks dramatic but leaves flow adequate may be left alone; a modest-looking one that limits flow may be treated.
The third is that medication alone means the team has given up or is rationing care. For stable disease, medical therapy is the guideline-recommended first step because it acts on the whole arterial system. The absence of a procedure is a clinical judgement, not a cost-saving measure.
The fourth is that bypass surgery is only for the sickest. In reality it is often chosen for people fit enough to recover well, because durable grafts across several vessels can be the better long-term solution for complex anatomy. Frailty, not age, is the limiting factor.
The fifth concerns the blood thinners after a stent. People stop them because of bruising, or because a dentist asks, or because they feel fine. The medicines protect against a clot forming inside the stent while the lining grows, and interrupting them is a decision for the cardiologist, not for the patient or another clinician acting alone.
The sixth is that a clear angiogram means the chest pain was imaginary. Microvascular disease, coronary spasm and non-cardiac causes are all real and have their own treatment paths.
Questions to ask your care team after an angiogram
Most people leave the catheter lab with a head full of images and no vocabulary to interrogate them. Writing questions down beforehand, or asking a relative to take notes, changes the quality of the conversation. These are the ones cardiologists say they wish more patients asked.
- Which arteries are narrowed, how severely, and how confident are you in that estimate? Was a pressure wire or intravascular imaging used?
- How does what you found explain my symptoms? If it does not fully explain them, what else might?
- Is my disease stable or unstable, and does that change how quickly a decision needs to be made?
- What are all the options you considered, including doing nothing more than medication, and why did you settle on this one?
- Was this discussed by a heart team including a surgeon? If not, would it be reasonable to ask for that?
- If a stent is recommended, how long will I be on two antiplatelet medicines, and what should I do if another clinician wants me to stop them?
- If surgery is recommended, what grafts would be used, how long is the expected hospital stay, and what does recovery look like week by week?
- How well is my heart pumping, and does that affect the choice?
- What symptoms should prompt me to call you, and which should prompt an emergency call?
- Will I be offered cardiac rehabilitation, and when does it start?
- When will my medicines be reviewed, and by whom?
- What is the plan for the risk factors that caused this: cholesterol, blood pressure, blood sugar, smoking?
None of these questions is adversarial. A good team expects them and will often be relieved to answer, because a patient who understands the plan is far more likely to follow it. If an answer is not clear, ask for it in writing or ask who else can explain.
When to call your doctor after a coronary angiogram or stent
Most recoveries are uneventful, and the warning signs are specific enough to be recognisable. The NHS and Mayo Clinic describe the following as reasons to seek help promptly.
Call emergency services, do not drive yourself, if you develop chest pain, pressure or tightness similar to or worse than the symptoms that led to the test, especially if it spreads to the arm, jaw or back, or comes with breathlessness, sweating, nausea or light-headedness. After a stent, new chest pain is treated as a possible stent clot until proven otherwise. Call emergency services too for sudden weakness or numbness on one side, slurred speech or facial drooping, which can signal a stroke, or for bleeding from the puncture site that does not stop with ten minutes of firm pressure.
Contact your cardiology team or doctor the same day for swelling, a growing or pulsing lump, increasing pain, redness, warmth or discharge at the wrist or groin site; a hand or leg on the catheter side that becomes cold, pale, numb or painful; a fever; a rash, itching or breathing changes that might indicate a delayed reaction to the contrast dye; or a marked drop in how much urine you pass, since contrast can affect the kidneys.
Also get in touch, without waiting for the next appointment, if you have bruising or bleeding that seems out of proportion while on antiplatelet medicines, if you have been advised by anyone to stop those medicines, if you have missed doses, or if your angina returns or changes pattern on medication alone. Breathlessness lying flat, swollen ankles or sudden weight gain over a few days can indicate fluid build-up and deserve a prompt review.
You are not wasting anyone’s time. Teams would far rather hear about a false alarm than miss a real one, and every one of these calls sits squarely within the care you are already receiving.
Frequently asked questions
What is the next step after an angiogram?
It depends on what the images show. Mild or moderate narrowings with stable symptoms are usually managed with medication and risk-factor control. A significant, reachable narrowing may be treated with angioplasty and a stent, sometimes during the same procedure. Extensive or complex disease is often referred for bypass surgery. The cardiology team reviews the pictures alongside your symptoms and other tests and discusses the recommendation with you, typically before you go home or at a follow-up appointment.
My angiogram showed a blockage, what next?
A blockage is not a single answer. The team will consider where it sits, how much of the vessel it narrows, whether it limits blood flow and whether it explains your symptoms. Options range from medication alone to a stent or bypass surgery. In an emergency the artery is usually opened straight away; in planned cases the images are often reviewed by a heart team first. Ask which options were considered and why one was chosen.
What happens if they find something during an angiogram?
Finding plaque is common and does not always mean a procedure. If a significant narrowing is seen, the cardiologist may place a stent during the same session if you agreed to that beforehand, measure flow with a pressure wire, or stop and arrange a follow-up discussion, especially for complex disease. Any stent placed should be one you consented to in principle, and the reasoning should be explained to you afterwards.
How long does it take for an artery to heal after an angiogram?
The puncture site in the wrist or groin seals within hours, but the NHS notes bruising can last up to a couple of weeks and advises avoiding heavy lifting for about a week. If a stent was placed, the coronary artery takes months for a smooth lining to grow over the mesh, which is the reason for the extended course of two antiplatelet medicines, with its length set by your cardiologist.
Can you see heart failure on an angiogram?
Not directly. Heart failure is diagnosed mainly by echocardiogram, symptoms and blood tests. An angiogram shows whether coronary artery disease, one of the commonest causes of a weak heart, is present, and a dye injection into the main chamber can give a visual impression of how it contracts. In someone with known heart failure, the angiogram helps answer whether blocked arteries are the cause and whether restoring blood flow might help.
Why would a doctor choose medication instead of a stent?
For stable angina, medication is the guideline-recommended first step because plaque affects the whole arterial tree and medicines act on every segment, lowering clot risk and stabilising plaques. A stent treats one narrowing only. If symptoms persist despite well-adjusted medication, a procedure can be added later. Choosing medication is a clinical judgement, not a sign the team has given up, and the plan should include a review date.
How is the stent or bypass decision made?
Guidelines encourage a heart team, usually an interventional cardiologist and a cardiac surgeon, to review the images together. They weigh the number and location of narrowings, whether the left main stem is involved, how calcified or complex the lesions are, your other conditions such as diabetes and kidney function, how well the heart pumps, and your own preferences. You are entitled to hear the reasoning and to request a second opinion.
How long will I be in hospital after a stent or bypass?
The NHS describes most people going home the same day or the next day after angioplasty and stenting, with a return to normal activities within about a week. Bypass surgery involves a stay of around seven days and a recovery period of roughly twelve weeks. These are typical ranges; your own timeline depends on your health, whether the procedure was planned or urgent, and how your recovery progresses.
What does a clear angiogram mean if I still have chest pain?
It means the large coronary arteries are not significantly narrowed, which is reassuring, but it does not mean the pain was imaginary. Disease of the tiny vessels that the angiogram cannot show, spasm of a coronary artery, and non-cardiac causes involving the gut, lungs, muscles or anxiety are all real and treatable. Your team may suggest further tests or a different treatment path.
What should I ask before agreeing to a stent during the angiogram?
Ask whether a stent might be placed during the same procedure, what findings would prompt it, and whether the team would stop and discuss first for complex disease. Ask how long you would need two antiplatelet medicines afterwards, how that fits with any planned surgery or dental work, and what the alternatives would be. Agreeing in principle beforehand lets the team act efficiently while keeping the decision yours.
References
- NHS: Coronary angiography
- NHS: Coronary angioplasty and stent insertion
- NHS: Coronary artery bypass graft (CABG)
- MedlinePlus: Coronary angiography
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Is an Aortic Problem Watched, Medicated or Repaired? How Doctors Decide the Path
Doctors decide by asking three questions: is the problem a bulge (aneurysm) or a tear (dissection), where on the aorta does it sit, and…

Comparing Heart Rhythm Disorder Treatments: Medication, Ablation or a Device?
The main types of arrhythmia treatment are medicines that slow or steady the heartbeat or lower stroke risk, catheter ablation that scars the small…

Pacemakers and Defibrillators in Cardiac Sarcoidosis: When a Device Becomes Part of Care
An ICD, an implantable cardioverter-defibrillator, is usually considered in cardiac sarcoidosis when someone has survived a dangerous ventricular rhythm, has a weakened heart pump…

Supporting a Child Through Congenital Heart Surgery: Feeding, Comfort and the Unit Stay
Preparing a child for congenital heart surgery means learning the pathway in advance: the pre-admission tests, the fasting times the team gives in writing,…

Pericardial Disease Recovery: Why Strenuous Activity Waits Until Your Cardiologist Clears It
Most people recovering from acute pericarditis are asked to avoid strenuous exercise until chest pain has gone and inflammation markers, ECG and echocardiogram have…

Who Is a Candidate for Ablation Therapy When Heart Rhythm Medicines Are Not Enough?
Cardiac ablation is usually considered for people whose abnormal heart rhythm keeps causing symptoms despite a fair trial of at least one rhythm-control medicine,…