

What Does a Doppler Ultrasound Show in Deep Vein Thrombosis and What Happens Next?

Key Takeaways
- A deep vein that will not flatten under gentle probe pressure is the single most reliable ultrasound sign of a clot, more decisive than color flow alone.
- Duplex ultrasound is highly accurate for thigh and knee veins but has blind spots in the calf and pelvis, which is why a repeat scan about a week later is standard when the first is clear but suspicion remains.
- A raised D-dimer does not diagnose DVT; it is a trigger for imaging, while a normal D-dimer in a low-risk person can safely end the search.
- MedlinePlus states a Doppler ultrasound usually takes about 30 to 60 minutes, needs no fasting, sedation or radiation, and has no recovery period.
- The NHS states anticoagulant treatment for DVT usually lasts at least 3 months, with the decision to extend reviewed by the prescribing clinician.
- According to the CDC, roughly one third to one half of people with DVT develop long-term leg symptoms, and about one in three have another clot within 10 years.
A Doppler ultrasound for DVT uses sound waves to show whether blood is moving through the deep veins of the leg and whether each vein flattens under gentle probe pressure. A vein that will not compress usually contains a clot. If a clot is found, anticoagulant treatment typically begins promptly; if the scan is clear but symptoms continue, clinicians often repeat the scan within about a week.
It is close to midnight in an urgent care bay, and a man in his fifties is looking at his own calf as if it belongs to someone else. It is tighter than the other one, warmer, faintly purple around the ankle. He drove nine hours yesterday. The nurse has already asked about his family history and whether he has ever had a clot before. Now she says the words that bring most people to this article: we would like to get a Doppler ultrasound for DVT.
Deep vein thrombosis, or DVT, is a blood clot in one of the large veins that run deep inside the leg. The scan that finds it is quick, painless and, for something so ordinary-looking, surprisingly decisive. A trolley, a probe, some cold gel, and within an hour the plan for the next three months can be set.
This article explains what the sonographer is actually seeing on that gray screen, how confident the result is, and what usually happens in the hours, days and weeks that follow.
Can a Doppler ultrasound tell if you have a blood clot?
Yes, and in most cases it does so more reliably than any symptom or blood test. The scan clinicians order is usually called a venous duplex ultrasound: “duplex” because it combines two views at once. The first is an ordinary grayscale picture of the vein wall and whatever sits inside it. The second is the Doppler component, which measures movement. Sound waves bounce back at a slightly different pitch when they hit moving red blood cells, the same physics that makes an ambulance siren drop in tone as it passes. The machine turns that shift into color and sound, so the sonographer can literally see and hear blood flowing.
A fresh clot looks different from flowing blood in two ways. First, it fills the vein with a soft gray material where there should be a dark, empty channel. Second, and more importantly, a healthy vein collapses completely when the probe presses down on the skin above it, the way a garden hose flattens under a foot. A vein containing a clot will not squash flat, because the clot props it open. That single observation, called non-compressibility, is the backbone of the whole test. The National Library of Medicine’s MedlinePlus describes Doppler ultrasound as the standard imaging test for suspected deep vein clots in the legs and arms, and the NHS lists it as the confirmatory test once a clot is thought likely.
What the scan cannot do is rule out every clot everywhere. It is excellent for the large veins between the groin and the knee. It is less certain for the small veins deep in the calf and for veins hidden behind the pelvic bones. That limitation shapes several of the decisions described later, including why some people are asked to return for a second scan.
What actually happens during a doppler ultrasound for DVT
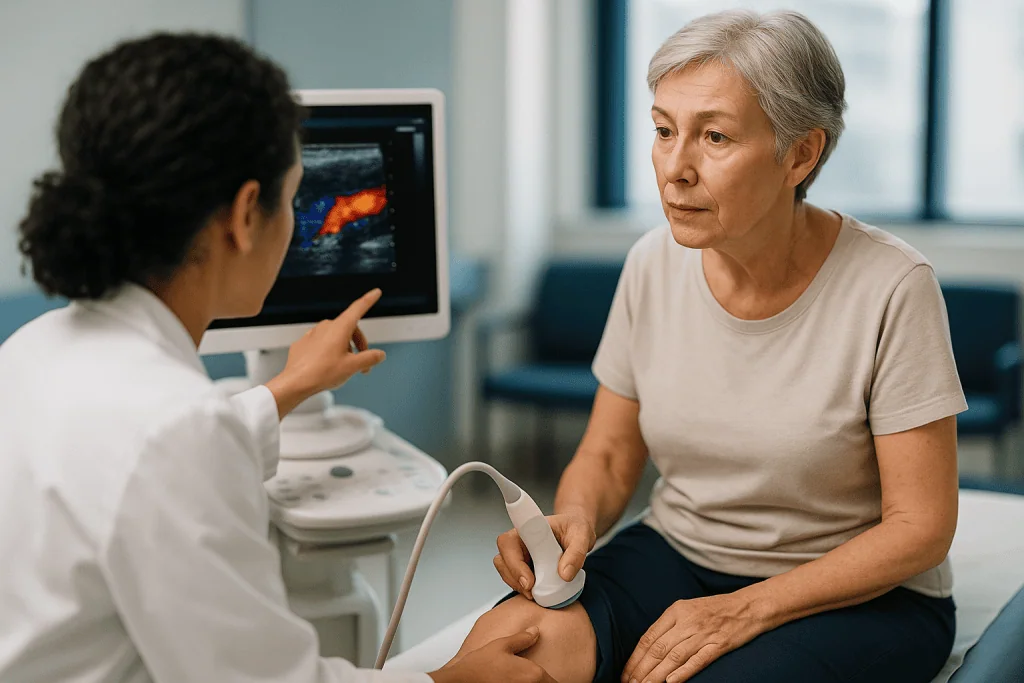
The appointment tends to be quieter than people expect. You lie on an examination couch, usually on your back with the head of the bed raised so gravity fills the leg veins and makes them easier to see. The sonographer, a technologist trained in vascular imaging, applies a water-based gel to the skin. The gel feels cold and slightly sticky; its only job is to remove the layer of air between the probe and the skin, since sound waves travel poorly through air.

The probe starts at the crease of the groin, where the common femoral vein lies next to the artery of the same name. From there it moves down the inner thigh, following the femoral vein to the knee, then behind the knee to the popliteal vein, and finally into the calf if the protocol includes the calf veins. At each station, three things happen. The sonographer takes a still image, presses down to test compression, and then switches on color Doppler to watch flow. You may be asked to point your toes or squeeze your calf so a rush of blood can be seen moving through the vein.
The pressing is firm but should not be painful. Over an inflamed clot it can be tender, and it is entirely reasonable to say so; the technologist will adjust. There is no radiation, no injection and no contrast dye in a standard venous duplex ultrasound. Some departments scan only the side with symptoms; others scan both legs, either because the symptoms are vague or because comparing the two sides helps interpret borderline findings.
Afterwards you wipe off the gel and can walk out. In many hospitals the images are reviewed by a radiologist or vascular specialist before the result reaches the clinician who ordered the test, which is why there can be a wait of an hour or more even when the scan itself was short.
What the sonographer is looking for: compression, color and flow
Three signs, read together, make the diagnosis. Understanding them takes some of the mystery out of the report you may later be handed.
Compressibility comes first. A normal deep vein, pressed from above, disappears completely on the screen; its two walls meet. If the walls stop short of each other, something is holding them apart. An acute clot is soft and slightly spongy, so the vein may partially indent but never fully closes. An older, organized clot is firmer and often thinner, hugging the wall with a channel of flow reopened through the middle. Radiologists use these textures to estimate whether a clot is new, weeks old or a remnant from a previous episode, though the estimate is approximate.
Color flow comes second. With Doppler switched on, moving blood paints the vein red or blue depending on direction. A vein blocked by clot shows a gap in color, or color that hugs only one edge. Absent color alone is not enough, because a slow-flowing vein in a very still patient can also look empty; that is why the compression test remains the deciding sign.
Flow behavior comes third. In a healthy leg, venous flow rises and falls gently with breathing, a pattern called phasicity, and surges when the calf is squeezed, a response called augmentation. If a clot sits higher up, in the pelvis where the probe cannot reach, the flow below it becomes flat and continuous and fails to surge on squeezing. That indirect clue can prompt a different imaging test of the pelvic veins even when the visible leg veins appear clear.
The report will usually name each vein segment and state whether it was compressible, whether clot was seen, and whether the clot appears to fill the vein completely (occlusive) or only partly. Those details matter for what comes next.
Positive, negative or indeterminate: what the DVT ultrasound result means
A positive result means a non-compressible deep vein was identified, and in nearly all cases it means a clot is present. The report will say where: iliac or femoral veins at the top, popliteal behind the knee, or the smaller peroneal, tibial and muscular veins of the calf. Clots at or above the knee are called proximal; those confined to the calf are distal. Proximal clots carry the higher risk of breaking off and travelling to the lungs, which is why they are treated with more urgency.
A negative result means every deep vein that was examined compressed normally. For the thigh and knee veins this is strong reassurance. For the calf it is weaker, partly because calf veins are small and paired, and partly because a very fresh clot can be nearly invisible on grayscale until it has had time to organize. Mayo Clinic notes that clinicians sometimes arrange a series of ultrasounds over several days to see whether a clot is growing or whether a new one has appeared, and the NHS pathway allows a repeat scan when the first is negative but suspicion remains.
Indeterminate results are less common but real. Marked swelling, a large body habitus, a plaster cast, a fresh surgical wound or severe tenderness can all block the probe’s view. The report may then say a segment was “not visualized” or “limited.” In that situation the clinician weighs how strongly the story points to a clot and may choose a repeat scan, a blood test, or a different imaging method of the pelvis.
One phrase that causes confusion is “chronic changes” or “chronic thrombus.” This describes scarring in a vein from a past clot, not necessarily an active new event. Whether it needs treatment depends on your history, and it is a fair question to ask the clinician directly.
Is a Doppler ultrasound the most accurate test for DVT?
For clots in the leg, duplex ultrasound is the first-line imaging test in every major guideline, chosen because it is accurate for the veins that matter most, carries no radiation and can be repeated freely. No test is perfect, though, and each option in the table below answers a slightly different question.
| Test | What it shows | Main strength | Main limitation |
|---|---|---|---|
| D-dimer blood test | A breakdown product released when the body dissolves clot | A normal result in a low-risk person makes DVT unlikely | Raised by many other things: surgery, infection, pregnancy, age, cancer |
| Venous duplex ultrasound | Vein compressibility and blood flow from groin to calf | No radiation; accurate for thigh and knee veins; repeatable | Less sensitive in the calf and pelvis; blocked by casts or heavy swelling |
| CT venography | Contrast dye filling (or failing to fill) pelvic and leg veins | Sees pelvic veins; often combined with a lung scan for PE | Radiation and iodine contrast; not suitable for everyone |
| MR venography | Detailed images of pelvic and abdominal veins | No radiation; useful in pregnancy when pelvic clot is suspected | Less available, longer scan, not used for routine leg DVT |
The D-dimer test deserves a plain-language definition because it is so often misunderstood. D-dimer is a fragment left over when the body breaks down fibrin, the protein mesh of a clot. A low level tells clinicians that there is probably no significant clot being formed and dissolved anywhere. A high level does not confirm DVT; it simply says the question is still open. That is why the NHS and Mayo Clinic describe D-dimer as a test used to decide who needs an ultrasound, rather than a substitute for one.
Contrast venography, the older X-ray method in which dye is injected into a foot vein, was once the gold standard. It is now rarely used because ultrasound answers the same question without a needle in the foot.
Who is usually offered the scan, and who is asked to wait
Not everyone with a sore leg goes straight to the ultrasound room, and the order of tests is decided by likelihood rather than by how worried someone feels. Clinicians use a structured risk assessment, most commonly a version of the Wells score, which adds up factors such as recent surgery or immobility, active cancer, a swollen calf compared with the other side, tenderness along the deep veins and a personal history of DVT. This is a tool for trained staff working with an examination, not a checklist for self-diagnosis; a low score does not mean a clot is impossible, and a high score does not confirm one.
People judged likely to have a clot usually go directly to ultrasound, ideally within hours. The NHS pathway aims to scan within 4 hours of a request, and, if that cannot happen, to start an interim anticoagulant and scan within 24 hours. People judged unlikely usually have a D-dimer blood test first. If it comes back normal, the search generally stops; if it is raised, an ultrasound follows.
Being asked to wait for a scan can feel alarming, but it usually reflects a specific safeguard: an anticoagulant given in the meantime. The NHS describes this interim dose approach for people whose scan cannot be arranged promptly. The decision about whether you need interim treatment while waiting belongs to the clinician who has examined you.
Some groups are handled differently. In pregnancy, D-dimer is unreliable because levels rise naturally, so ultrasound is usually ordered directly. People with a plaster cast may need the cast removed or windowed. Those with symptoms in the arm have the same duplex principle applied to the veins of the shoulder and neck. And when the main concern is breathlessness or chest pain rather than the leg, the workup may start with a lung scan instead, because a clot that has already travelled changes the priorities.
Which leg usually gets DVT, and does location change the plan?
People often ask whether one leg is more prone than the other. The honest answer is that DVT is slightly more common in the left leg, and the reason is anatomical rather than mysterious. The left common iliac vein, the large vein carrying blood from the left leg toward the heart, passes underneath the right common iliac artery. In some people the artery presses the vein against the spine, narrowing it and slowing flow. This arrangement, sometimes called iliac vein compression or May-Thurner anatomy, is one reason left-sided clots occur a little more often, especially in younger women. The difference is modest, and a clot can form in either leg or both.
Location within the leg matters more than side. Ultrasound reports describe clot by segment, and clinicians think about it in two tiers. Proximal DVT, meaning clot in the popliteal vein at the knee or anywhere above it, is the form most closely linked to pulmonary embolism, a clot that breaks free and lodges in the lungs. Guidelines from the NHS and the American Heart Association treat proximal DVT as an unambiguous indication for anticoagulation.
Distal DVT, confined to the calf veins, is a gray zone. Some calf clots dissolve on their own; a minority extend upward into the popliteal vein over the following days. For an isolated calf clot with no high-risk features, one accepted approach is careful monitoring with repeat ultrasound over about 2 weeks rather than immediate treatment; another is to treat from the outset. Which path fits you depends on symptoms, bleeding risk and personal history, and the decision rests with the treating team.
Clots that reach the iliac veins or extend up into the pelvis are the most extensive and may prompt additional imaging or a discussion with a vascular specialist. Recognizing a pelvic clot from indirect flow signs, as described earlier, is one of the more subtle skills of the sonographer.
How long does a DVT ultrasound take, and how should you prepare?
Most people ask this while sitting on the couch waiting for the gel. MedlinePlus states that a Doppler ultrasound usually takes about 30 to 60 minutes. A focused scan of one leg from groin to knee can be quicker; a two-leg study including the calf veins, or a scan in someone with heavy swelling, sits at the longer end. If a radiologist needs to look at the images before the result is released, add time for that step.
Preparation is minimal. There is no fasting, no sedation and no need to stop eating or drinking. Wear or bring loose clothing, because the probe needs bare skin from the groin crease to the ankle, and shorts or a gown will be offered if trousers are in the way. Remove tight compression garments before the appointment unless told otherwise, since they can alter how the veins fill.
Tell the sonographer about anything that might affect the scan: a previous DVT in the same leg, recent surgery, a pacemaker (which does not affect ultrasound but is worth noting for any later imaging), a plaster cast, or an area too tender to press. Bring a list of your medicines. If you already take an anticoagulant, or if you were given an interim dose while waiting for the scan, the interpreting clinician will want to know.
You do not need someone to drive you home. There are no after-effects, no restrictions on activity and no bruising, although skin that was tender before the scan may remain so for a while. Walking in and out of the department is fine; standard guidance does not require bed rest for suspected DVT, and immobility is one of the risk factors clinicians are trying to avoid.
A practical tip: write down the questions you want answered before you arrive. The window between the scan and the conversation about results can be short, and having them ready helps you use it well.
Positive scan: what usually happens in the first 24 hours
If the ultrasound confirms a deep vein clot, the next conversation tends to happen quickly, often the same day. Its purpose is to stop the clot from growing, to lower the chance of a piece breaking free and reaching the lungs, and to give the body time to reabsorb what is already there. The medicine that does this is an anticoagulant, a drug that slows the chain of chemical reactions by which blood turns from liquid to gel. Anticoagulants do not dissolve an existing clot; the body’s own systems do that gradually over weeks and months. What the medicine does is tip the balance so that the clot stops advancing.
Two broad approaches are used. Direct oral anticoagulants, taken by mouth, block a single clotting factor and act within hours. Older approaches involve an injectable heparin-type medicine, sometimes followed by a vitamin K antagonist that requires regular blood tests to adjust. The NHS describes both routes as standard, and the choice depends on kidney function, body weight, other medicines, pregnancy, cancer and personal preference. That choice, along with every question about how much and how often, belongs to the prescribing clinician; this article deliberately gives no dosing information.
Most people with an uncomplicated leg DVT are now treated at home rather than admitted. Admission is more likely if the clot is very extensive, if there are signs of pulmonary embolism, if bleeding risk is high, or if the person cannot manage medicines safely at home.
You will usually be encouraged to keep walking. Gentle mobility is thought to help venous return and does not increase the risk of the clot moving once anticoagulation has started. Raising the leg when sitting eases swelling. Compression stockings are no longer routinely recommended to prevent long-term complications, according to the NHS, though some clinicians suggest them for symptom relief; ask before buying any.
Negative ultrasound but leg pain: why a repeat scan is often arranged
A clear scan combined with a leg that still hurts is one of the most unsettling outcomes, and it is worth understanding why clinicians sometimes respond by booking another scan rather than closing the case. The limitation lies almost entirely in the calf. Small, paired, deeply buried veins are difficult to compress reliably, and a clot that formed in the past day or two may not yet have the texture that shows up on grayscale imaging. If a calf clot is present but missed, the concern is not so much the calf clot itself as the possibility that it extends upward into the popliteal vein over the following week.
The standard safeguard is a second ultrasound roughly 6 to 8 days after the first, which is the interval the NHS pathway uses when the initial scan is negative but the D-dimer was raised or clinical suspicion was high. Mayo Clinic similarly describes repeat scanning over several days when the first study is inconclusive. Most people who return for that second scan are again negative, and at that point DVT can be set aside with confidence.
In the meantime, the clinician will consider other causes for the symptoms. A ruptured Baker’s cyst, a fluid-filled sac behind the knee that leaks into the calf, mimics DVT closely and is sometimes spotted on the same ultrasound. Muscle tears, cellulitis (a skin infection), superficial vein inflammation and simple fluid retention are all on the list. Some of these show up on the scan; others need an examination or a different test.
Between scans, the practical advice is to stay mobile, avoid long periods of sitting still, and watch for the red-flag signs described near the end of this article. Whether interim anticoagulation is appropriate during the wait is a case-by-case decision for the treating clinician, not something to assume either way.
What the following days and weeks usually look like
The first week after a confirmed DVT is often the most uncomfortable. Swelling and aching tend to ease over 1 to 2 weeks as anticoagulation stops the clot growing and the leg’s smaller veins take on more of the work. Warmth and redness fade in a similar timeframe. Many people are back at work within days, depending on how much standing or sitting the job involves; long periods of sitting still are the thing to break up, with short walks every hour or so.
Treatment length is measured in months, not days. The NHS states that anticoagulant treatment for DVT usually lasts at least 3 months. Clots triggered by a clear, temporary cause such as surgery, a long flight or a cast often fall at that shorter end. Clots with no obvious trigger, or in someone with ongoing risk factors, may lead to a longer or indefinite course, because the CDC notes that about one in three people who have had a clot experience another within 10 years. The decision to stop, continue or extend is reviewed with the prescribing clinician, usually around the 3-month mark.
A follow-up ultrasound is not always needed. Some clinicians repeat the scan at the end of treatment to record what the vein looks like as a baseline, so that any future episode can be compared against it rather than mistaken for an old scar. Others rely on symptoms alone. Ask which approach your team uses.
The CDC also reports that roughly one third to one half of people with DVT develop long-term symptoms in the affected leg, known as post-thrombotic syndrome: aching, heaviness, swelling and skin changes caused by damaged vein valves. It usually shows up within the first 2 years. Early mobility and completing the prescribed course of treatment are the measures most consistently associated with lower risk, though no single step guarantees prevention.
What people often get wrong about doppler ultrasound for DVT
The first misunderstanding is that a clear scan proves there is no clot anywhere. It does not. It proves there is no clot in the veins that were examined, at that moment, to the limits of the technique. Pelvic veins and small calf veins remain partially blind spots, which is exactly why repeat scanning and clinical judgment exist alongside the images.
The second is that a Doppler ultrasound checks for pulmonary embolism. It cannot see the lungs. If a leg clot is found in someone with chest symptoms, the clinician may infer that a piece has travelled, but confirming a lung clot requires a different test, usually a CT scan of the chest with contrast dye. Conversely, a leg scan can be entirely normal in someone whose clot has already left the leg and lodged in a lung.
The third is that a bigger clot on ultrasound means a more dangerous person. Size and extent matter, but so do location, symptoms and what triggered the clot. A small clot in the popliteal vein in someone with an unprovoked episode may warrant longer treatment than a longer clot after knee surgery with a clear, resolved cause.
The fourth is that the medicine “dissolves” the clot and the scan will show it gone in a week. Anticoagulants stop new clot forming; the body’s own enzymes slowly remodel the old one over weeks to months, and some veins never look fully normal again on ultrasound even when the person feels well. A residual scar on a later scan is not automatically a treatment failure.
The fifth is that a D-dimer alone can diagnose or exclude DVT. A normal D-dimer in a low-risk person is genuinely reassuring. A raised one is a prompt for imaging, nothing more; surgery, infection, pregnancy, cancer and simply being older all push it up.
A final quiet error: assuming a normal ultrasound means the leg pain does not need explaining. It usually does, just not by a clot.
Questions to ask your care team after a DVT ultrasound
The conversation after the scan can be brief, and the person explaining the result may not be the one who ordered it. A short list of questions helps you leave with a plan you understand rather than a leaflet you do not.
- Exactly which veins contained clot, and is it proximal (at or above the knee) or distal (calf only)? This single distinction shapes almost everything that follows.
- Does the report suggest the clot is new or old, and how confident is that estimate?
- Was the whole leg seen clearly, or were any segments “limited” or “not visualized”? If so, is further imaging planned?
- Do you think this clot had a clear trigger, or is it unprovoked? The answer influences how long treatment is likely to last and whether any further tests are suggested.
- Which anticoagulant is being recommended for me and why this one rather than the alternatives, given my kidneys, weight, other medicines and bleeding history?
- How long do you expect treatment to continue, and when will that be reviewed?
- What bleeding signs should make me stop and call, and what should I do if I miss a dose? Ask for this in writing.
- Is there anything I should avoid: certain over-the-counter painkillers, alcohol, contact sports, long-haul travel in the next few weeks?
- Will I need a repeat ultrasound, and if so, when and for what purpose?
- Should I wear compression stockings, and if you suggest them, is it for symptom relief or for a specific medical reason?
- Who do I contact with questions during treatment, and how quickly can I expect a reply?
If a calf-only clot has been found and you are offered monitoring rather than immediate treatment, ask what would change that decision and how the follow-up scans will be arranged. If you are pregnant or planning a pregnancy, ask specifically how that affects both medicine choice and imaging. And if anything in the report uses a word you do not recognize, ask for it to be translated on the spot. Good teams expect these questions and would rather answer them now than at 2 a.m. later in the week.
When to call your doctor: red-flag signs after a DVT scan
Some symptoms mean the situation may have changed and need urgent assessment rather than a wait for the next scheduled appointment. They apply whether your scan was positive or negative, because a clot can travel or grow regardless of what an earlier image showed.
Call emergency services, or go to the nearest emergency department without driving yourself, if you develop sudden shortness of breath, sharp chest pain that worsens when you breathe in, a racing or irregular heartbeat, coughing up blood, lightheadedness or fainting. These are the classic warning signs of pulmonary embolism, a clot that has reached the lungs, and the CDC and NHS both list them as reasons for immediate care.
Seek same-day assessment if the leg becomes markedly more swollen, painful or discolored than it was at the scan; if the skin turns pale, blue or cold, or if you lose sensation or the ability to move the foot. Rapidly worsening swelling up to the groin can indicate a clot extending into the pelvic veins.
If you have started an anticoagulant, bleeding becomes the second thing to watch. Contact your care team urgently for black or bloody stools, blood in the urine, vomiting blood, a nosebleed that will not stop after 10 minutes of pressure, coughing up blood, unusually heavy menstrual bleeding, or any head injury or fall, even without obvious symptoms. A sudden severe headache, confusion, weakness on one side or slurred speech require emergency care because of the possibility of bleeding inside the skull.
Less dramatic but still worth a prompt call: a new fever with a hot, spreading red area on the leg, which may indicate infection rather than clot; new pain in the other leg; or symptoms that have not begun to settle after 1 to 2 weeks of treatment.
None of this replaces the individual instructions given by the clinician who examined you. If your team has told you to call about something not listed here, follow their guidance. When in doubt, a phone call that turns out to be unnecessary is always the better error.
Frequently asked questions
Can a Doppler tell if you have a blood clot?
Yes. A venous duplex ultrasound, which includes Doppler, shows whether the deep leg veins compress normally and whether blood is flowing through them. A vein that will not flatten under probe pressure almost always contains clot. The test is very reliable for veins from the groin to the knee, less so for small calf veins and pelvic veins, which is why clinicians sometimes repeat it or add other imaging.
Which leg usually gets DVT?
DVT is slightly more common in the left leg. The left common iliac vein passes beneath the right common iliac artery, and in some people the artery compresses it, slowing flow. The difference is modest, and clots occur in either leg or both. Where the clot sits within the leg, above or below the knee, matters more for treatment decisions than which side it is on.
What is the most accurate test for DVT?
For clots in the leg, duplex ultrasound is the first-line imaging test in major guidelines because it is accurate for the large veins, uses no radiation and can be repeated. CT or MR venography see pelvic veins better and are used when ultrasound is inconclusive or a pelvic clot is suspected. D-dimer is a screening blood test, not a diagnostic one.
How long does a DVT ultrasound typically take?
MedlinePlus states a Doppler ultrasound usually takes about 30 to 60 minutes. A focused scan of one leg above the knee can be shorter; scanning both legs including the calf veins, or a leg with heavy swelling, takes longer. Waiting for a radiologist to review images before the result is released may add time, but the scan itself has no preparation or recovery.
What does a venous duplex ultrasound of the leg feel like?
It feels like cold gel and firm pressing along the inner thigh, behind the knee and down the calf. The pressure should not hurt, although skin over an inflamed clot can be tender, and you can ask the sonographer to ease off. There is no needle, no radiation and no dye. You may be asked to squeeze your calf or point your toes so flow can be seen.
I have a negative ultrasound but leg pain. What happens now?
A normal scan makes a clot in the thigh and knee veins very unlikely, but small calf clots can be missed early. If your D-dimer was raised or suspicion remains high, the NHS pathway arranges a repeat scan about 6 to 8 days later. Meanwhile your clinician will consider other causes such as a Baker’s cyst, muscle injury or skin infection, and will advise whether interim treatment is needed.
Does the D-dimer test for blood clot confirm DVT?
No. D-dimer is a fragment released when the body breaks down fibrin, the protein mesh of a clot. A normal result in someone judged low risk makes DVT unlikely and can end the workup. A raised result only means imaging is needed, because surgery, infection, pregnancy, cancer and older age all raise D-dimer without any clot being present.
Do I need a follow-up ultrasound after DVT treatment?
Not always. Some clinicians repeat the scan at the end of treatment to record how the vein looks as a baseline, so a future episode can be distinguished from old scarring. Others rely on symptoms alone. For an isolated calf clot managed by monitoring rather than immediate treatment, repeat scans over about 2 weeks are used to check the clot is not extending upward.
Can a leg ultrasound show a pulmonary embolism?
No. A leg ultrasound images only the veins of the leg. It cannot see the lungs. If a leg clot is found in someone with chest pain or breathlessness, clinicians may suspect a piece has travelled, but confirming a lung clot requires a chest CT with contrast or a lung perfusion scan. A normal leg scan does not exclude pulmonary embolism.
How long does DVT treatment usually last after a positive scan?
The NHS states anticoagulant treatment usually lasts at least 3 months. Clots with a clear temporary trigger such as surgery often fall at that shorter end, while unprovoked clots or ongoing risk factors may lead to longer treatment because the CDC reports about one in three people have another clot within 10 years. The prescribing clinician reviews the decision, usually around the 3-month mark.
References
- NHS: Deep vein thrombosis (DVT)
- MedlinePlus: Doppler Ultrasound
- CDC: About Venous Thromboembolism (Blood Clots)
- Cleveland Clinic: Deep Vein Thrombosis (DVT)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Life After Heart Bypass Surgery: Cardiac Rehab, Medicines and the Habits That Protect Grafts
Life after heart bypass surgery usually means a hospital stay of about a week, 6–12 weeks of healing while the breastbone knits, and a…

How Do Pacemakers, CRT and Defibrillators Support a Failing Heart? Device Therapy Explained
Heart failure device therapy uses small implanted electrical devices to support a weakened heart. Pacemakers keep the heart from beating too slowly, cardiac resynchronization…

Does a Coronary Angiogram Hurt? Local Anesthesia, the Warm Contrast Feeling and Afterward
A coronary angiogram is usually uncomfortable rather than painful. The skin at the wrist or groin is numbed with local anesthetic, which stings briefly;…

Which Questions to Ask When Cardiac Sarcoidosis Treatment Is First Proposed
When cardiac sarcoidosis treatment is first proposed, the most useful questions cover five areas: how certain the diagnosis is and which scans support it,…

What Happens During a Cardiac Ablation Procedure, From Mapping to the Final Rhythm Check
During cardiac ablation, a heart rhythm specialist threads thin, flexible catheters through a vein, usually in the groin, up into the heart, records its…

After Aortic Aneurysm Repair: The Wound, Leg and Kidney Changes to Report Promptly
After aortic aneurysm repair, report promptly any wound that becomes increasingly red, hot, swollen, leaking or opens; a leg that turns pale, cold, numb,…