

After Aortic Aneurysm Repair: The Wound, Leg and Kidney Changes to Report Promptly

Key Takeaways
- Repair of an abdominal aortic aneurysm is typically considered at about 5.5 cm, with growth of more than 1 cm a year, or when the aneurysm causes symptoms, according to NHS guidance.
- Open repair usually means a hospital stay of around 7–10 days and months of recovery, while EVAR usually means a stay of a few days and recovery over weeks.
- A fall in urine output is the single most useful early sign of kidney trouble after either operation, because kidney injury rarely causes pain.
- A painful blue or purple toe with normal ankle pulses suggests small debris from the aorta has lodged in toe arteries and should be reported the same day.
- Most endoleaks after EVAR cause no symptoms and are detected only on scans, which is why imaging surveillance continues for life.
- An aneurysm signals vascular disease throughout the body, so stopping smoking and controlling blood pressure matter more after repair, not less.
After aortic aneurysm repair, report promptly any wound that becomes increasingly red, hot, swollen, leaking or opens; a leg that turns pale, cold, numb, blue-toed or newly painful; a sharp fall in urine output, dark urine or new swelling of ankles and face; and fever, breathlessness, black stools, or sudden back, abdominal or chest pain. These can signal infection, blocked blood flow, kidney injury or graft problems that need same-day assessment.
The first shower at home is where many people notice it. Not pain exactly, but a dressing that looks a little pinker than yesterday, a calf that feels heavier than the other one, or the odd realization that the bathroom visits have thinned out since the hospital. Is that normal after having a segment of the body’s largest artery rebuilt? Or is it the thing the discharge nurse said to call about?
That uncertainty is the real work of the first weeks. The operation itself, whether through a long abdominal incision or through two small groin punctures, is over. What remains is a watching brief, and most people were handed it with a stapled leaflet and a drowsy memory of the instructions.
This explainer sets out the aortic aneurysm repair warning signs after surgery that deserve a same-day phone call, grouped the way clinicians think about them: the wound, the legs and the kidneys. It also covers what ordinary recovery looks like, so the many small aches that mean nothing do not crowd out the few that mean a lot.
What actually happens during aortic aneurysm repair
An aneurysm is a weakened stretch of artery wall that has ballooned to roughly one and a half times its normal width. The aorta runs from the heart down through the chest and abdomen, and in adults the abdominal section is normally about 2 cm across, so a repair conversation usually begins when it has swollen well beyond that, according to the NHS.
There are two ways to fix it. In open repair, a surgeon makes a long incision in the abdomen (or chest for thoracic aneurysms), clamps the aorta above and below the bulge, and sews in a fabric tube called a graft. The old aneurysm wall is wrapped around the graft like a sleeve. Blood then flows through the new tube and never presses on the thin wall again.
In endovascular aneurysm repair, usually shortened to EVAR, no large incision is made. Through a small cut or puncture in each groin artery, the team threads a collapsed stent graft, a fabric tube held open by a metal mesh, up inside the aorta and expands it in place. It seals against healthy artery above and below, so blood runs through the stent and the aneurysm sac is left outside the circulation, as described by MedlinePlus.
Both approaches share one goal: take pressure off the weak wall so it cannot burst. They differ in how much the body has to heal, and that difference explains why the warning signs to watch for are not identical. Open repair brings a large wound and a longer recovery. EVAR brings groin punctures, exposure to X-ray contrast dye that passes through the kidneys, and a lifelong need for imaging to confirm the seal is holding.
At what point should an aortic aneurysm be repaired, and who is asked to wait?
Size, speed and symptoms drive the decision. The NHS describes repair being considered when an abdominal aneurysm reaches about 5.5 cm, when it grows by more than 1 cm in a year, or when it causes symptoms such as persistent back or abdominal pain regardless of size. Below those thresholds the risk of rupture is generally judged lower than the risk of an operation, so most smaller aneurysms are monitored with scans every few months to every few years depending on size.

Waiting is not neglect. It is an active plan, and the same guidance stresses what fills the gap: stopping smoking, controlling blood pressure and cholesterol, and attending every surveillance appointment. Smoking in particular is the strongest modifiable driver of growth, and the NIH’s National Heart, Lung, and Blood Institute lists it alongside age, male sex, high blood pressure and family history as the leading risk factors.
Some people with large aneurysms are also asked to wait, or offered a different route than they expected. Severe heart or lung disease can make the general anesthetic and aortic clamping of open repair too risky, which is one reason EVAR exists. Conversely, EVAR needs a straight enough stretch of healthy aorta below the kidney arteries for the stent to seal, and when anatomy will not allow that, open repair or more complex stent designs come into play.
Thresholds for thoracic aneurysms, and for people with inherited aortic conditions, are set differently and often lower. The point for a reader recovering from surgery is simpler: the decision has been made by a team weighing a specific aorta against a specific body, and the follow-up schedule they set is part of the same calculation.
Open repair vs EVAR: what to watch for after each
The two operations leave different footprints, and a reader who knows which one they had can filter the list of things to notice. The table below summarizes the typical patterns described by the NHS and MedlinePlus; individual plans vary and the treating team’s instructions always come first.
| Feature | Open repair | Endovascular repair (EVAR) |
|---|---|---|
| Incision | Long abdominal or chest wound | Small cut or puncture in each groin |
| Typical hospital stay (NHS) | Around 7–10 days, often with time in intensive care | A few days |
| Typical return to usual activities | Several months | A few weeks |
| Main wound concerns | Infection, separation, later hernia along the scar | Groin bruising, lump (hematoma or false aneurysm), infection |
| Main leg concerns | Clots or debris blocking flow, deep vein thrombosis | Graft limb kinking or blockage, embolized debris |
| Main kidney concerns | Clamp time above or near kidney arteries, low blood pressure during surgery | Contrast dye load, stent covering a kidney artery |
| Long-term imaging | Occasional | Lifelong, to check for endoleak |
Two things stand out. First, the groin is to EVAR what the abdominal scar is to open repair: the place where most early trouble declares itself. Second, kidney risk is real after both, but it arrives by different routes. Open surgery stresses the kidneys through clamping and blood pressure swings; EVAR stresses them through the iodine-based dye needed to see the arteries. Knowing which route applies makes the questions at follow-up sharper.
Aortic aneurysm repair warning signs after surgery: the wound
A healing incision follows a fairly predictable script. Mild redness along the edges, some firmness beneath the skin, bruising that migrates and yellows, and a small amount of clear or pale pink fluid in the first days are all part of it. What matters is direction of travel. A wound that looks a little better each day is behaving; one that looks worse than yesterday is not.
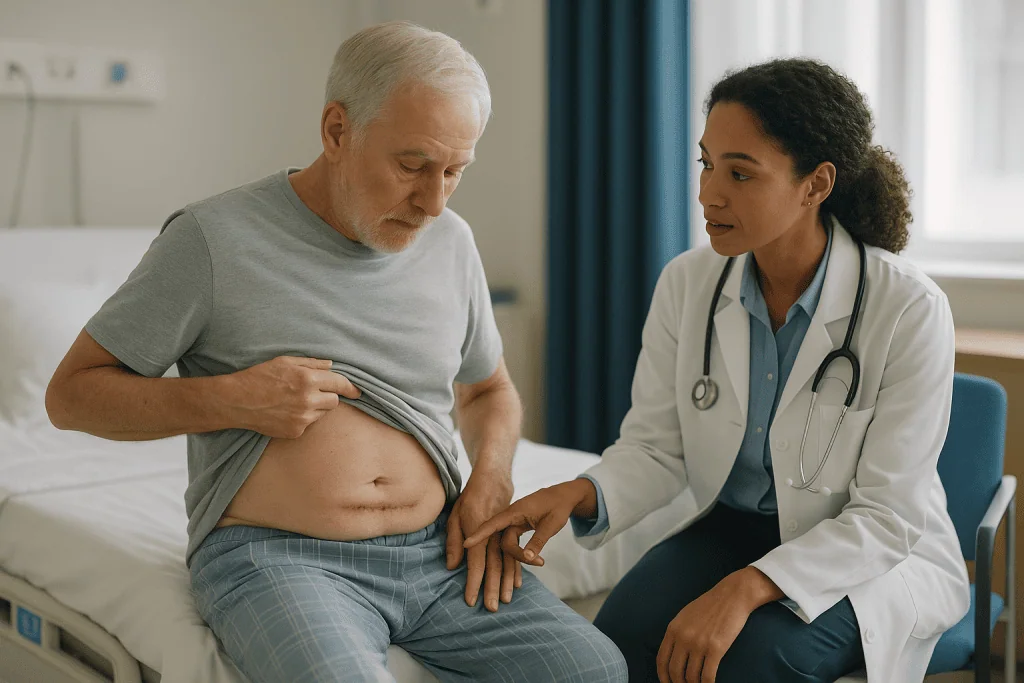
The MedlinePlus discharge guidance for open repair describes the changes to report: redness that spreads outward or feels hot, swelling that increases rather than settles, drainage that turns thick, cloudy, yellow-green or foul-smelling, edges that pull apart, and bleeding that does not stop with gentle pressure. A fever accompanying any of these raises the level of concern.
After EVAR the wound is small, but the groin is a busy place. A soft bruise is expected. A firm, growing lump, a lump that pulses under the fingers, or sudden swelling with pain can indicate a hematoma (a collection of blood under the skin) or a pseudoaneurysm (a leak from the puncture site contained by surrounding tissue). Both need prompt assessment because the artery beneath was deliberately entered and sealed.
Deep infection is uncommon but serious after either operation, because fabric grafts cannot clear bacteria on their own. Persistent fever, unexplained night sweats, or a wound that keeps weeping weeks after surgery are reasons to ask specifically whether the graft itself might be involved, rather than treating it as a skin problem.
One later wound issue is worth flagging now. After open repair, a bulge along the scar that appears when coughing or standing is often an incisional hernia, where abdominal contents push through a gap in the healed muscle. It is rarely an emergency unless it becomes painful, hard or cannot be pushed back, but it should be reported so the team can decide whether and when to address it.
Leg changes after aortic aneurysm repair: pulses, color, temperature and pain
Both legs are downstream of the repair. Everything that was done to the aorta, whether clamping, sewing, or sliding a stent through the iliac arteries that branch toward each thigh, can affect how blood reaches the feet. That is why nurses in hospital kept checking pulses at the ankle and feeling whether the toes were warm. At home, the same checks continue informally, and the Mayo Clinic lists blocked blood flow to the legs among the recognized complications of repair.
Compare one leg with the other. A foot that is noticeably paler, mottled, cooler, or that feels numb or weak compared with its partner suggests reduced arterial flow. Pain in the calf or thigh that comes on with walking a short distance and eases with rest, when it was not there before surgery, points the same way. After EVAR, the stent has two limbs that run into each iliac artery, and if one kinks or clots the corresponding leg loses flow. After open repair, small fragments of plaque loosened during the operation can lodge in the small arteries of the toes, producing one or more painful blue or purple toes while the main pulses stay normal. Either pattern deserves a same-day call.
The other leg problem is venous, not arterial. A deep vein thrombosis (a clot in the deep veins of the leg) presents as a calf or thigh that is swollen, tight, warm and tender, usually on one side, and is a risk after any major surgery that involves lying still, as the MedlinePlus guidance notes. Breathlessness or chest pain alongside a swollen leg is an emergency because the clot may have traveled to the lungs.
Not every ache is sinister. Groin soreness after EVAR, stiffness from days in bed, and a bruise tracking down the thigh are common. The combination to act on is change in color, temperature or sensation, or swelling that is one-sided and growing.
Kidney changes to report: urine, swelling and the numbers on your blood test
The arteries that feed each kidney leave the aorta just above where most abdominal aneurysms sit. During open repair the clamp may need to go on near or above them, briefly interrupting their supply. During EVAR the stent’s top edge is positioned just below them, and the X-ray contrast used to place it is filtered by the kidneys on its way out. Add the blood pressure dips that can happen under anesthesia, and it is no surprise that the MedlinePlus endovascular repair overview lists kidney injury among the risks to discuss beforehand.
Kidney trouble rarely announces itself with pain. The clues are quieter. The most useful one is urine volume: passing far less than usual over a day, or going many hours without needing to, is the single sign to take most seriously. Urine that is persistently dark or tea-colored, new puffiness around the ankles, shins or eyes, unexpected weight gain over a couple of days from retained fluid, and a sense of breathlessness when lying flat can all follow when kidneys fall behind.
Nausea, loss of appetite, a metallic taste, and a foggy or unusually tired feeling are less specific but join the picture when they persist. People who already had reduced kidney function, diabetes or heart failure before surgery are at higher risk and are often asked to have repeat blood tests in the first weeks precisely because the warning signs can be subtle.
What the blood test measures is creatinine, a waste product the kidneys clear; a rise means they are clearing less. Ask what the number was before surgery and what it is now. A small, settling bump is common. A number still climbing at the first follow-up is a conversation the team will want to have, and it may change which medicines are continued and when the next contrast scan is scheduled.
How long does it take to recover from aortic aneurysm repair surgery?
The honest answer is that there are two timelines, and they are quite different. The NHS describes a hospital stay of around 7–10 days after open repair, often including a spell in intensive care, with a few months before people feel back to their usual selves. After EVAR, the same source describes a stay of a few days and a recovery measured in weeks. These are typical ranges, not promises, and age, heart and lung health, and complications shift them in both directions.
The first week at home after open repair is dominated by the incision. Walking around the house, then around the block, is encouraged from the start because it keeps the lungs expanded and the leg veins moving. Coughing and laughing hurt; a folded towel pressed against the abdomen helps. Appetite is often poor and bowels sluggish because the intestines were handled during surgery; both usually recover over one to two weeks. Lifting anything heavier than a small bag is generally discouraged for about six weeks while the abdominal wall knits, according to MedlinePlus.
After EVAR, the groin wounds are sore for a few days and bruising can spread impressively down the thigh before fading. Most people are walking normally within the first week, and the main restriction is on heavy lifting and straining while the puncture sites seal.
Fatigue is the complaint that surprises people most after either operation. Major surgery triggers an inflammatory response and a period of muscle loss, and energy returns in steps rather than a straight line. A bad day after two good ones is normal. A steady slide backward, or new symptoms appearing after an initial improvement, is not, and is worth reporting rather than waiting for the scheduled appointment.
Beyond the wound, legs and kidneys: fever, breathing and bowel changes
Three other systems earn a place on the watch list because the operation touches them indirectly.
Fever is the broad signal. A low temperature in the first day or two after surgery is common and often reflects the body’s inflammatory response or shallow breathing. A fever appearing or returning after discharge, especially with chills, sweats or a general sense of being unwell, has fewer innocent explanations. The possibilities range from a chest or urine infection, which are common after any anesthetic, to wound infection, to the rarer and more serious scenario of infection around the graft. Rather than wait it out, report it; the team will decide whether blood tests or imaging are needed, in line with the MedlinePlus discharge advice to call for fever or chills.
Breathing deserves attention after open repair in particular. A long abdominal incision makes deep breaths painful, so small areas of lung can collapse and become infected. New or worsening breathlessness, a cough producing colored sputum, or chest pain that is sharp and worse on breathing in all need prompt assessment. Sudden breathlessness with a swollen leg raises the possibility of a clot in the lung and is an emergency.
The bowel is the quiet casualty. The intestine is lifted aside during open surgery and some of its small blood vessels run close to the aneurysm, so a portion of the large bowel can be left short of blood supply. The Mayo Clinic lists bowel complications among the recognized risks. The signs are diarrhea that is bloody or dark, abdominal pain that is severe or out of proportion to the wound, a swollen tense abdomen, and vomiting that will not settle. Constipation and bloating in the first week, by contrast, are expected and usually ease with walking, fluids and the measures the team suggested.
Endoleak symptoms after EVAR: why follow-up scans are not optional
An endoleak is blood continuing to flow into the aneurysm sac outside the stent graft, which means the sac can still be under pressure even though the repair is technically in place. It is the reason the NHS describes regular scans continuing for life after EVAR, usually with ultrasound or CT at intervals set by the team.
The frustrating truth is that most endoleaks cause no symptoms at all. They are found on scans, not felt. Some come from small side branches that keep feeding the sac from behind; these are often monitored because many close on their own or stay stable. Others come from an imperfect seal at the top or bottom of the stent, or from a tear in the fabric, and these matter more because they transmit the full force of the heartbeat into the weak wall. The scan can tell the difference; the person cannot.
That said, there are symptoms that should never be ignored after EVAR precisely because an endoleak could be behind them. New or returning deep back pain, abdominal pain that feels like the pre-surgery ache, a pulsing sensation in the abdomen that was not there before, and any sudden, severe pain with faintness or collapse are the pattern of a sac that is growing or has started to leak. These warrant emergency care, not a routine appointment.
The practical lesson is twofold. Keep every imaging appointment even when feeling perfectly well, because the scan is doing a job no symptom can. And if a scan is missed, rebook it rather than assume silence means safety. People who return to full, active lives after EVAR do so alongside this surveillance, not instead of it. The Johns Hopkins Medicine overview frames it the same way: the stent is a device, and devices are checked.
What are the potential side effects of repairing an aortic aneurysm?
People tend to ask this question in two forms: what might go wrong, and what will simply feel different. Both deserve plain answers.
The recognized complications, as listed by the Mayo Clinic and MedlinePlus, include bleeding, infection of the wound or graft, heart attack or irregular rhythm during the stress of surgery, kidney injury, blocked blood flow to the legs or bowel, blood clots, and, after EVAR, endoleak, stent movement or later blockage of a stent limb. Spinal cord injury causing leg weakness is a specific risk of repairs that involve the chest portion of the aorta, where arteries feeding the spinal cord branch off. The treating team will have weighed these against the specific aneurysm, and the frequency of each depends heavily on age, anatomy and other illnesses, which is why this article does not quote blanket percentages.
The everyday changes are less dramatic but more universal. A numb patch of skin beside a long incision is common because small nerves are cut and may or may not regrow. The scar itself can stay sensitive for months. Appetite and bowel habit often take weeks to normalize. Men can experience changes in sexual function after open abdominal repair because nerves controlling ejaculation run across the front of the aorta; this is a legitimate thing to raise, and teams expect the question.
Fatigue and low mood in the weeks after major vascular surgery are well recognized and frequently underreported. Neither is a sign of failure. Mentioning them at follow-up allows the team to check for treatable contributors such as anemia or disturbed sleep and to point toward supervised exercise programs where they exist.
Can you live a normal life after aortic aneurysm repair?
For most people the answer is yes, with two qualifications: the first weeks are not normal, and some habits change for good.
Activity returns in stages. Walking is encouraged immediately and increases daily. Driving is generally discouraged until an emergency stop would not cause pain or hesitation and the team has agreed, which MedlinePlus places at a few weeks for most after open repair. Heavy lifting, vigorous abdominal exercise and contact sports wait until the abdominal wall or groin punctures have fully healed, typically around six weeks after open surgery and less after EVAR, again as a range rather than a rule. Sexual activity can resume when it is comfortable. Air travel is usually possible once mobility is good and the team is satisfied, with the standard clot-prevention basics of walking the aisle and staying hydrated.
The permanent changes concern the arteries elsewhere. An aneurysm is a marker of vascular disease throughout the body, so the American Heart Association and the NHS emphasize the same long-term measures: not smoking, controlling blood pressure, managing cholesterol, staying active and keeping a healthy weight. Many people leave hospital on a cholesterol-lowering medicine (a statin, which stabilizes plaque inside artery walls), an antiplatelet (which makes platelets less sticky so clots are less likely to form on the graft), and blood pressure treatment. Each of these is chosen and adjusted by the prescribing clinician, and the right response to a side effect is a conversation with them, not a quiet decision to stop.
The last ingredient of a normal life is the one easiest to skip: the surveillance scan. After EVAR it is lifelong. After open repair it is occasional but still matters, because the rest of the aorta can enlarge over the years. Normal life includes the calendar reminder.
What people often get wrong about recovery after aneurysm repair
Several beliefs circulate in waiting rooms and online forums, and some of them lead people to ignore signs that matter or worry about ones that do not.
“The aneurysm has been removed.” In open repair the sac is opened and wrapped around the graft; in EVAR it is left in place around the stent. The weak wall still exists. It is simply no longer under pressure, provided the seal holds. This is why imaging continues.
“Keyhole surgery means there is nothing to recover from.” EVAR is gentler on the body, but the arteries were still entered, contrast still passed through the kidneys, and a device was still implanted. The NHS describes a recovery of weeks, not days, and the groin and kidney signs above apply fully.
“Pain means something has gone wrong.” Incisional pain, groin soreness and muscular aches from bed rest are expected and should ease steadily. The pattern to act on is pain that is new, severe, deep in the back or abdomen, or accompanied by faintness, not the familiar wound ache.
“No pain means everything is fine.” Endoleaks are usually silent. Kidney injury is usually silent. A missed scan or a skipped blood test can hide a problem a person feels nothing from.
“Once repaired, blood pressure and smoking no longer matter.” They matter more. The repair fixed one segment of a vascular system that showed it was vulnerable. The American Heart Association places these risk factors at the center of long-term care.
“Older people should not bother reporting small changes.” Age is a reason to report sooner, not later, because kidney reserve and heart reserve are smaller and problems compound faster.
Questions to ask your care team before and after you leave hospital
A short, specific list beats a vague “anything I should know?” Here are the questions that produce the most useful answers, drawn from what people most often wish they had asked.
- Which operation did I have, open or endovascular, and where exactly does the graft sit in relation to my kidney arteries?
- What was my kidney blood test before surgery and what is it now? When will it be rechecked?
- Were there any problems with blood flow to my legs during the operation, and should I check anything specific at home?
- What should my wound look like at one week and at three weeks? Is any part of the incision at particular risk?
- Was there an endoleak on the completion scan, and if so, what type and what is the plan for it?
- When is my first follow-up scan, who arranges it, and what should I do if I do not receive an appointment?
- Which medicines are new, what is each one for, and which of them might affect my kidneys or bleeding risk?
- What activity can I do this week, and what is the sign that I am doing too much?
- When can I drive, lift, return to work, and travel?
- Who do I call during office hours, and what is the out-of-hours number? What warrants emergency services instead?
Write the answers down or ask for them in the discharge letter. The Johns Hopkins Medicine overview of aneurysm repair notes that a clear plan for follow-up and for recognizing problems is part of the procedure, not an afterthought. A family member or friend at the discharge conversation is worth more than any leaflet, because anesthesia and painkillers blur memory for days.
Finally, ask what the team would want to know about between appointments. Most are explicit: they would rather hear about a false alarm than find out at the next scan that something was ignored.
When to call your doctor after aortic aneurysm repair
Some signs need emergency services, not a phone call to the clinic. Sudden, severe pain in the back, abdomen or chest, especially with dizziness, faintness, collapse, a racing pulse or cold clammy skin, may indicate bleeding from the repair or the aorta and is a 911 situation. The same applies to sudden breathlessness or chest pain with a swollen leg, a leg that suddenly turns white, cold and numb, or heavy bleeding from a wound that pressure does not control. The MedlinePlus discharge guidance for open repair and the NHS both describe these as emergencies.
Call the surgical team or a doctor the same day for the following:
- Wound redness spreading or becoming hot, swelling that is increasing, thick or foul-smelling drainage, edges opening, or a firm growing lump in the groin.
- Fever or chills, or feeling generally and increasingly unwell.
- A leg or foot that is paler, cooler, numb, weak or more painful than the other, new pain on walking, or one or more toes turning blue or purple.
- One calf or thigh that is swollen, tight, warm and tender.
- Passing much less urine than usual, going many hours without urinating, dark urine, or new swelling of the ankles, legs or face.
- Persistent nausea or vomiting, a swollen tense abdomen, or black, tarry or bloody stools.
- A new cough producing colored sputum, or breathlessness that is worsening.
- Any return of the back or abdominal ache that was present before surgery, or a new pulsing sensation in the abdomen.
Between those extremes sits a large gray zone of minor aches, small bruises and tired days. The rule of thumb is direction and combination: anything getting worse rather than better, and any single sign that arrives with a second one, is worth a call. The team decides what to do with the information; the person’s job is simply to supply it promptly.
Frequently asked questions
How long does it take to recover from aortic aneurysm repair surgery?
Recovery depends on the operation. The NHS describes a hospital stay of around 7–10 days after open repair, often with time in intensive care, and several months before people feel fully recovered. After endovascular repair (EVAR) the stay is usually a few days and recovery takes a few weeks. Age, heart and lung health, and any complications shift these ranges, so the treating team’s estimate for an individual is the one to rely on.
What is the typical EVAR recovery time before returning to normal activities?
Most people walk normally within the first week after EVAR and return to light daily activities over a few weeks, according to the NHS. Groin soreness and bruising spreading down the thigh are expected and fade. Heavy lifting and straining are usually restricted until the puncture sites have sealed. Driving, work and travel are agreed with the team, and lifelong follow-up scans continue regardless of how well recovery goes.
At what point should an aortic aneurysm be repaired?
For abdominal aneurysms, NHS guidance describes repair being considered at about 5.5 cm across, when growth exceeds 1 cm in a year, or when the aneurysm causes symptoms such as persistent back or abdominal pain. Below these thresholds the rupture risk is usually judged lower than the operative risk, so monitoring with regular scans is preferred. Thoracic aneurysms and inherited aortic conditions use different thresholds set by the specialist team.
What are the signs of infection after aneurysm repair?
Wound infection shows as redness spreading or becoming hot, increasing swelling, thick cloudy or foul-smelling drainage, edges pulling apart, and fever or chills. After EVAR, a firm, growing or pulsing lump in the groin needs assessment too. Deep infection around the graft is uncommon but serious and may present only as persistent fever, night sweats or a wound that keeps weeping for weeks, so report these promptly rather than treating them as a skin problem.
What are the endoleak symptoms after EVAR I should watch for?
Most endoleaks cause no symptoms and are found only on surveillance scans, which is why imaging continues for life after EVAR. Signs that an aneurysm sac may be growing or leaking include new or returning deep back pain, abdominal pain resembling the pre-surgery ache, a new pulsing sensation in the abdomen, and sudden severe pain with faintness. The last pattern is an emergency and warrants calling emergency services rather than waiting for a clinic appointment.
What leg changes after aortic aneurysm repair mean reduced blood flow?
Compare the two legs. A foot that is paler, cooler, numb or weaker than the other, new pain in the calf or thigh on walking, or one or more toes turning blue or purple suggest reduced arterial flow or debris lodged in small arteries. A leg that suddenly becomes white, cold and numb is an emergency. One-sided swelling that is warm and tender points instead to a deep vein clot and also needs same-day assessment.
How do I know if my kidneys are affected after aneurysm surgery?
Kidney injury rarely causes pain, so the clues are quiet: passing far less urine than usual, going many hours without urinating, dark urine, new puffiness of the ankles or face, rapid weight gain from fluid, nausea or unusual fatigue. Blood tests measuring creatinine, a waste product the kidneys clear, confirm it. Ask the team what your level was before surgery and what it is now, and report any of these changes rather than waiting for the next appointment.
What are the potential side effects of repairing an aortic aneurysm?
Recognized complications include bleeding, wound or graft infection, heart problems during surgery, kidney injury, reduced blood flow to the legs or bowel, blood clots and, after EVAR, endoleak or stent movement. Everyday effects are more universal: numbness beside the scar, a sensitive incision for months, slow return of appetite and bowel habit, fatigue, low mood and, after open abdominal repair in men, possible changes in sexual function. The frequency of each depends on individual health and anatomy.
What does abdominal aortic aneurysm surgery recovery look like week by week?
After open repair the first weeks center on the incision: walking from day one, painful coughing eased by pressing a folded towel to the abdomen, poor appetite and sluggish bowels that recover over one to two weeks, and no heavy lifting for about six weeks according to MedlinePlus. Energy returns in steps rather than a straight line. After EVAR the same stages are compressed into days and weeks, with groin soreness and bruising the main early features.
Can you live a normal life after aortic aneurysm repair?
For most people, yes, once the recovery period has passed. Activity returns in stages and most restrictions lift within weeks to months depending on the operation. Two things change permanently: long-term attention to smoking, blood pressure and cholesterol, since an aneurysm reflects vascular disease elsewhere, and follow-up imaging, which is lifelong after EVAR and occasional after open repair. Medicines prescribed after surgery are adjusted only in discussion with the prescribing clinician.
References
- NHS: Abdominal aortic aneurysm – Treatment
- MedlinePlus: Abdominal aortic aneurysm repair – open
- MedlinePlus: Aortic aneurysm repair – endovascular
- NIH National Heart, Lung, and Blood Institute: Aortic Aneurysm
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Which Questions to Ask When Cardiac Sarcoidosis Treatment Is First Proposed
When cardiac sarcoidosis treatment is first proposed, the most useful questions cover five areas: how certain the diagnosis is and which scans support it,…

What Happens During a Cardiac Ablation Procedure, From Mapping to the Final Rhythm Check
During cardiac ablation, a heart rhythm specialist threads thin, flexible catheters through a vein, usually in the groin, up into the heart, records its…

Pericarditis, Effusion and Constriction: How Pericardial Diseases Are Treated Differently
Pericarditis is usually treated with anti-inflammatory medicines, a temporary break from strenuous exercise and scheduled follow-up, and most viral or idiopathic cases settle within…

During Deep Vein Thrombosis Treatment: What Is Expected and When to Call Your Doctor
During deep vein thrombosis treatment, leg aching, swelling and warmth usually ease gradually over days to weeks while anticoagulant medicines stop the clot from…

Hypertension and Your Other Medicines: What the Doctor Reviews Before Adjusting Treatment
Before adjusting blood pressure treatment, doctors review every medicine and supplement a person takes, because several common ones can raise blood pressure or blunt…

Palpitations After Eating: Why It Happens, Common Triggers and How to Stop Them
Palpitations after eating are usually harmless and often settle within minutes. To calm them, sit upright, breathe slowly with a longer exhale than inhale,…