

What Does a Voiding Cystourethrogram Show? The VCUG Test for Children Explained

Key Takeaways
- A voiding cystourethrogram films the bladder and urethra while filling and emptying, and its main purpose is to detect urine flowing backward toward the kidneys (vesicoureteral reflux).
- Reflux is graded from I to V; the NIDDK notes that many children with lower grades outgrow it without surgery as the ureter lengthens and the valve mechanism matures.
- The test is done awake in most children because the voiding phase, which cannot happen under general anesthesia, is what distinguishes a VCUG from a plain cystogram.
- Contrast in a VCUG goes into the bladder rather than the bloodstream, so the kidney concerns associated with intravenous contrast do not apply.
- A nuclear cystogram detects reflux with less radiation but shows the urethra poorly, so it is often used for follow-up rather than as a first study in boys.
- Fever within two to three days of the test can signal a catheter-related infection and should prompt a same-day call to your child's doctor.
A voiding cystourethrogram (VCUG) is an X-ray test that shows a child's bladder and urethra while filling and emptying. A thin catheter delivers contrast dye into the bladder, and images reveal whether urine flows backward toward the kidneys (vesicoureteral reflux), whether the urethra is narrowed or blocked, and how the bladder is shaped. It is most often ordered after a urinary tract infection or when prenatal scans showed swollen kidneys.
The appointment letter arrives with a word nobody in the house can pronounce. Cystourethrogram. Your daughter is three, she had a fever last month that turned out to be a kidney infection, and now the pediatric team wants a picture of what her bladder does when she pees. You read the leaflet twice. The sentence about a catheter stops you both times.
Parents facing a voiding cystourethrogram for a child tend to arrive with two questions tangled together: what is this test actually looking for, and what will my child experience in that room? Those questions deserve separate, honest answers, because the first is about plumbing and the second is about a small person who did not ask to be there.
This explainer walks through both. It covers what the images can and cannot reveal, how the test compares with its cousins, what the day usually looks like, and where the evidence is firmer than the internet makes it sound.
What does a voiding cystourethrogram show in a child?
The test answers one question better than any other: does urine travel the wrong way? In a healthy urinary tract, urine flows from the kidneys down two tubes called ureters into the bladder, and from there out through the urethra. A valve-like junction where each ureter enters the bladder is supposed to let urine in and keep it from washing back up. When that junction is loose or short, urine can reflux toward the kidney, especially during the squeeze of voiding. This is vesicoureteral reflux, and the voiding cystourethrogram was designed to catch it.
A VCUG also shows the shape and capacity of the bladder, whether it empties completely, and whether the urethra is open all the way along its length. In boys, that last point matters a great deal, because a congenital web of tissue known as posterior urethral valves can partially block the urethra and cause pressure to build backward toward the kidneys. MedlinePlus lists reflux, urethral narrowing, and bladder abnormalities among the main findings the test can reveal.
What the voiding cystourethrogram does not do is equally worth knowing. It does not measure kidney function, and it does not show kidney scarring directly. Those questions need blood tests, ultrasound, or a nuclear medicine scan of the kidneys. Think of the VCUG as a motion picture of the lower urinary tract under working conditions, filmed while the bladder does its ordinary job.
For a voiding cystourethrogram in a child, the phrase that matters most in the report is usually the reflux grade, a number from I to V that describes how far up and how forcefully urine travels backward. That grade shapes what happens next, so a later section explains it in detail.
What is the VCUG procedure, step by step?
Picture a dim room with a flat table and a camera arm overhead. A fluoroscope, which is an X-ray machine that produces moving images in real time, hangs above the table. Your child lies down, usually on their back, and a radiology technologist or nurse cleans the genital area with an antiseptic.
A soft, thin catheter is then passed through the urethra into the bladder. Lubricating gel, sometimes containing a numbing agent, helps it slide. This part takes a minute or two and is the step most children remember, so teams tend to move efficiently and talk the child through it. Once the catheter is in, any urine already in the bladder may drain out. A liquid contrast agent, a fluid that shows up white on X-ray, then flows in slowly by gravity from a bag hung above the table. The bladder fills until the child feels the urge to go, or until the expected volume for their age is reached.
Several still or moving images are captured during filling. The radiologist watches for contrast appearing in the ureters or kidneys, which would mean reflux. Then comes the voiding part. The child is asked to pee on the table, into a pan, a bedpan, or absorbent padding, with the catheter either sliding out as they start or already removed. Images taken during the stream show the urethra outlined by contrast, and a final picture after emptying shows whether anything stays behind.
According to MedlinePlus, the whole study, from positioning to the last image, is commonly finished within about an hour, and the actual X-ray exposure is a small fraction of that time. Children can usually get dressed and leave straight afterward. There is no anesthesia to recover from unless sedation was planned in advance.
Which children are usually referred for a voiding cystourethrogram, and who is asked to wait?
Referral patterns have shifted over the years, and understanding why helps parents make sense of their own child’s pathway. Two situations account for most pediatric VCUGs.
The first is a febrile urinary tract infection, meaning an infection with fever that suggests the kidney itself was involved rather than only the bladder. Mayo Clinic and the NIDDK both describe this as the most common trigger for reflux testing, because a child whose infection reached the kidney may have a pathway letting bacteria travel upward. The second is an abnormal prenatal or newborn ultrasound showing hydronephrosis, the medical term for a kidney that is swollen with urine. Significant swelling raises the question of reflux or a downstream blockage, and the VCUG can tell those apart.
Other reasons include a sibling or parent with known reflux in some centers, recurrent infections even without fever, suspected posterior urethral valves in a boy, persistent daytime wetting that has not responded to behavioral approaches, or a known spinal condition affecting bladder nerves.
Who waits? Here the picture is more nuanced than it once was. Not every child with a first febrile UTI is sent straight for a VCUG anymore. Many guideline groups recommend a kidney and bladder ultrasound first, reserving the catheter study for children whose ultrasound is abnormal, who have a second febrile infection, or who have features suggesting a higher risk of complications. Infants under a few months, children with unusual bacteria, and those who did not respond quickly to antibiotics are more likely to be imaged earlier. A child with an active urinary infection is typically asked to wait until it has been treated, because filling an infected bladder is uncomfortable and may push bacteria upward.
Whether your child needs the test now, later, or not at all is a judgment for the treating team, weighing the chance of finding reflux against the distress and small radiation exposure involved.
Vesicoureteral reflux grading: what the numbers on the report mean
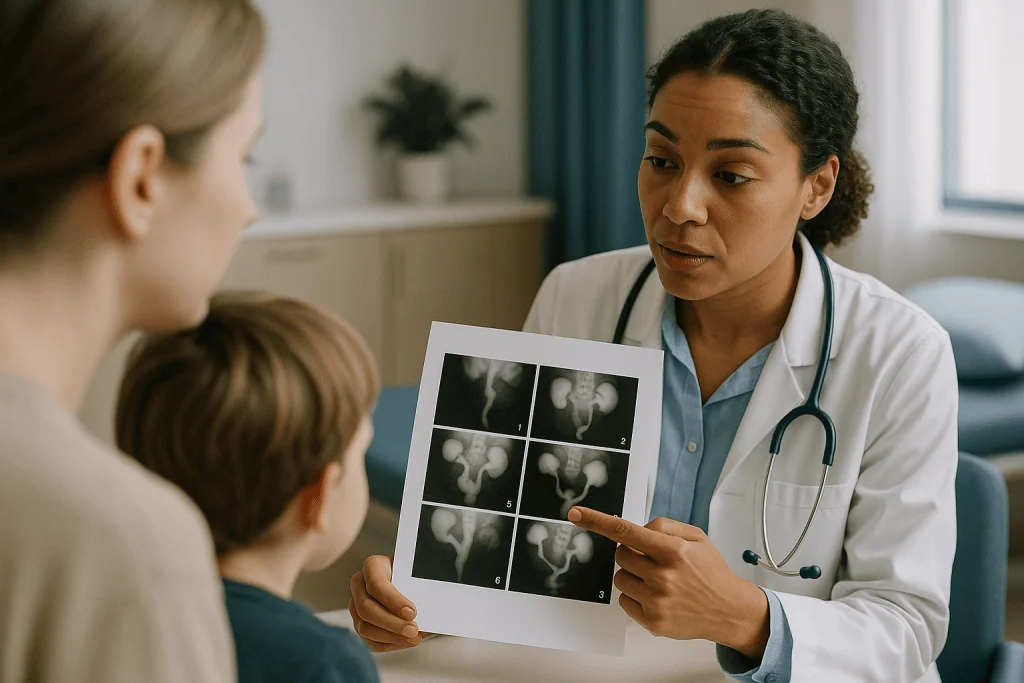
Reflux is not one condition. A trace of contrast tickling the lower ureter is a very different finding from a kidney ballooned with backward flow, and the international grading system exists to capture that spread. The scale runs from I to V, and the NIDDK and Mayo Clinic describe it in similar terms.
| Grade | What the VCUG shows | What it generally means |
|---|---|---|
| I | Contrast enters the ureter only, not the kidney | Mild; often improves as the child grows |
| II | Contrast reaches the kidney’s collecting system without stretching it | Mild; frequently monitored rather than treated surgically |
| III | Mild to moderate widening of the ureter and collecting system | Moderate; follow-up imaging usually planned |
| IV | Marked widening with some blunting of the kidney’s inner shapes | Moderate to severe; closer monitoring and discussion of options |
| V | Severe widening, tortuous ureter, loss of normal kidney contours | Severe; more likely to need intervention |
Why does the grade matter so much? Because lower grades have a strong tendency to resolve on their own. The ureter lengthens as the child grows, the valve mechanism matures, and the backward flow stops. The NIDDK notes that many children, particularly those with grades I to III, outgrow reflux without surgery. Higher grades resolve less reliably and carry a greater chance of kidney scarring if infections recur, which is why they attract more intensive follow-up.
Two further details sometimes appear on a report. Reflux may be unilateral (one side) or bilateral (both). It may occur during filling, during voiding, or both; reflux that appears only at high pressure during voiding is a somewhat different physiological picture from reflux that begins early in filling. Your child’s urologist or nephrologist will read these nuances alongside the ultrasound, the infection history, and the child’s age.
VCUG vs retrograde cystogram vs nuclear cystogram: how the tests differ
Three tests share a family resemblance, and the names get muddled even in clinic corridors. All three involve filling the bladder through a catheter. The differences lie in what is being looked for and how the pictures are made.
A retrograde cystogram fills the bladder with contrast and takes X-ray images, but it does not necessarily include the voiding phase and its main purpose is different. It is most often used to check the bladder wall for a leak or tear after injury or surgery, or to outline a bladder abnormality. If the question is “is the bladder intact?”, a cystogram answers it. If the question is “does urine reflux and is the urethra normal while emptying?”, the voiding part is essential, and that is what makes a VCUG a VCUG.
A nuclear cystogram, also called a radionuclide cystogram, replaces X-ray contrast with a tiny amount of a radioactive tracer and records the images with a gamma camera. It is very sensitive for detecting reflux and delivers a lower radiation dose to the gonads than a conventional fluoroscopic study. Its weakness is anatomy: the images are blurry outlines, so it cannot grade reflux with the same precision and it shows the urethra poorly. That makes it unsuitable as a first test for a boy in whom posterior urethral valves are a concern, but it is often favored for follow-up studies in a child already known to have reflux, or for screening siblings.
Some centers also offer contrast-enhanced voiding urosonography, which uses ultrasound microbubbles instead of X-rays. It avoids ionizing radiation entirely but is less widely available and depends heavily on the operator’s experience.
None of these is universally better. The right choice depends on whether the team needs urethral detail, how many repeat studies are expected, and what the local department does well. Asking “why this one for my child?” is a fair question.
How do you prepare a child for a VCUG test?
Preparation is mostly emotional, and the evidence on child life approaches, which are structured techniques for helping children understand and cope with medical procedures, points consistently in one direction: honesty pitched to the child’s age reduces distress more than vague reassurance.
For a toddler, that might mean one or two sentences on the morning of the test: “A nurse will put a tiny straw in the place where your pee comes out so the camera can see inside. It might feel funny for a minute. You get to pee on the table, which is allowed today.” For a school-age child, a day or two of notice and a chance to ask questions works better than a surprise. Many pediatric radiology departments send picture books or short videos in advance, and some offer a pre-visit with a child life specialist. Ask whether yours does.
Practical steps are few. Your child can usually eat and drink normally unless sedation is planned, in which case the department will give fasting instructions. A current urinary infection should be fully treated first; tell the team if there have been new symptoms since the referral. Bring a change of clothes, a favorite comfort object, and something to watch on a tablet, since distraction during catheter placement is one of the better-studied comfort measures. Dress your child in clothes that come off and on easily.
Some departments ask parents to practice having the child lie still and pee lying down at home, which sounds odd but genuinely helps a child who has been toilet trained to do the one thing they have been taught not to do.
Parents are nearly always welcome in the room. One calm adult at the head of the table, holding a hand and narrating gently, is worth more than two anxious ones. If you know the catheter step will be hard for you to watch, it is reasonable to swap with the other parent or a grandparent for that part.
Is a VCUG painful? Catheters, sedation, and comfort
The honest answer is that catheter placement is uncomfortable rather than painful for most children, and that the discomfort is brief. The urethra is sensitive, and a child who is tense tightens the muscles around it, which makes the catheter harder to pass. This is why so much effort goes into relaxation. Most children describe the sensation afterward as pressure, stinging, or “weird” rather than sharp pain.
Topical numbing gel applied a few minutes before catheterization is used in many departments and is supported by trial evidence as a modest help, though it does not remove the sensation entirely. The filling phase feels like an increasingly full bladder, which is familiar. Voiding on a table in front of adults is often the part older children find most awkward, and the teams who do this daily are practiced at making it matter-of-fact.
Sedation is not routine for a VCUG. A sedated child cannot void on command, and the voiding phase is the point of the test, so most studies are done fully awake. Some centers offer a short-acting sedative that relaxes without stopping voiding for children who are very anxious or who have had a previous traumatic experience; others use it rarely. Any medicine decision, including whether sedation is appropriate at all, sits with the radiology and pediatric team, who weigh the child’s age, temperament, and history.
Comfort measures with reasonable evidence behind them include a parent present, a child life specialist, distraction with video or music, a small reward promised in advance, and giving the child controllable choices, such as which arm to hold the comfort toy in or whether to count out loud. Children who have had one calm experience tend to tolerate repeat studies better, which is a practical argument for getting the first one right.
How much radiation does a child receive from a voiding cystourethrogram?
Parents ask this more than any other safety question, and it deserves a clear answer rather than a reflexive “it’s very low.” A VCUG uses fluoroscopy, which means X-rays are switched on in short pulses while the radiologist watches. Modern pediatric departments use pulsed rather than continuous fluoroscopy, tight collimation to the bladder area, and a last-image-hold feature that saves the final frame without extra exposure. Together these have reduced doses substantially compared with studies done a generation ago.
The effective dose from a well-performed pediatric VCUG is typically in the range of a few months of natural background radiation, the radiation everyone receives from soil, air, and cosmic rays. The NIH and Mayo Clinic both describe the exposure as low. It is higher than a chest X-ray and lower than a CT scan of the abdomen. Because the field includes the pelvis, there is particular attention to the ovaries and testes, and departments shield or angle to minimize exposure where it does not compromise the images.
Does this matter? The theoretical risk from a single low-dose study is extremely small, and no study has shown measurable harm from one VCUG. The reasonable caution is about repetition. A child followed for reflux might have several studies over years, and this is one reason nuclear cystograms or ultrasound-based alternatives are often chosen for follow-up once the anatomy has been documented.
What parents can do is ask whether the department follows pediatric dose-reduction protocols, whether the equipment is set for children, and whether a lower-radiation alternative is appropriate for repeat imaging. These are standard questions that a good department expects. The benefit side of the equation, finding reflux or an obstruction before it damages a kidney, is what justifies the exposure in the first place.
What happens in the hours and days after a VCUG?
Most children walk out of the department and carry on with their day. The first few urinations may sting slightly, a leftover effect of the catheter irritating the urethral lining, and this usually settles within a day. MedlinePlus notes that a small amount of blood-tinged urine or mild burning can occur and typically resolves quickly. Encouraging fluids helps dilute the urine and flushes out any remaining contrast, which is colorless and passes unnoticed.
A minority of children, particularly toddlers, become temporarily reluctant to pee after the test because the first attempt stung. Patience, warm baths, and letting them void in the bath if needed usually breaks the cycle within a day or two. Persistent refusal to urinate for many hours is a reason to call, as covered in the final section.
The other thing that happens after a VCUG is waiting for results. In many departments the radiologist reviews the images the same day and sends a report to the referring doctor within a few days. Some teams give a preliminary impression before you leave; others prefer the ordering clinician to deliver the result in context. Ask before you go home which to expect, so you are not refreshing a patient portal for a week.
If the study is normal, the pathway often ends there, or continues with simple infection prevention advice. If reflux is found, the next conversation is about grade, about whether a preventive low-dose antibiotic is appropriate, and about the timing of follow-up imaging. If a blockage such as posterior urethral valves is seen, referral to a pediatric urologist tends to happen promptly. In none of these cases does the radiology report itself decide treatment; it is one piece of information the treating team puts alongside everything else they know about your child.
Reading the report: common findings and what they can mean
VCUG reports follow a fairly predictable structure, and knowing the vocabulary takes some of the fear out of the envelope.
The bladder is described first: its outline, whether the wall looks smooth or trabeculated (a word meaning thickened and irregular, which suggests the bladder has been working against high pressure), and whether any small pouches called diverticula are present. A thick-walled bladder in a boy raises the question of obstruction; in any child it may point toward a bladder that does not relax normally.
Next come the ureters and kidneys. If no contrast appears in them, the report states that no reflux was seen. If it does, the side and grade are given, along with whether it occurred during filling or voiding. A ureter that enters the bladder in an unusual position, or a kidney with a duplicated collecting system, may be noted here too.
The urethra section matters most in boys. A normal male urethra is outlined smoothly from bladder to tip. Posterior urethral valves show as a dilated upper urethra with an abrupt narrowing below. A urethral stricture, meaning a scarred narrow segment, appears as a pinched area. In girls the urethra is short and these findings are rare, though a spinning-top shape is sometimes described in children with dysfunctional voiding.
Finally, the post-void image reports residual volume. A healthy bladder empties nearly completely; a significant residual suggests the bladder is not contracting well or that something downstream is in the way.
A normal VCUG is genuinely reassuring about reflux and obstruction, but it is not a guarantee that a child will never have another urinary infection, since most infections in children occur without any anatomical abnormality. The treating team interprets the report in that light.
What is voiding dysfunction, and how does the VCUG fit in?
Voiding dysfunction is an umbrella term for toilet-trained children whose bladder and the muscles that control urination do not coordinate well, in the absence of a nerve or structural disease. In plain terms, the bladder squeezes while the outlet stays clenched, or the child holds urine for so long that the bladder stretches and empties poorly. The pattern often shows up as daytime wetting, urgency, frequent small voids or very infrequent large ones, straining, and recurrent infections. Constipation is a frequent travelling companion, because a full rectum presses on the bladder and shares its nerve supply.
Most children with voiding dysfunction never need a VCUG. The diagnosis is clinical, built on a bladder diary, a physical examination, an ultrasound with a post-void residual measurement, and sometimes a uroflow study, which measures the speed and pattern of the urine stream into a special toilet. First-line management is behavioral: timed voiding on a schedule, double voiding, relaxed posture on the toilet with feet supported, treating constipation, and adequate fluid intake spread through the day.
Where the VCUG enters the picture is when voiding dysfunction is accompanied by febrile infections or by hydronephrosis on ultrasound, or when a structural cause has to be excluded. In those children the study can reveal reflux, which is more common in children with dysfunctional voiding because the high bladder pressures overwhelm the ureteral valve, and it can show the characteristic urethral shape of a child who voids against a tight pelvic floor.
The relationship runs both ways. Reflux found on a VCUG in a toilet-trained child should prompt questions about bladder habits and constipation, because treating the dysfunction often improves the reflux and reduces infections. Some clinicians consider this the single most overlooked connection in pediatric urology.
What people often get wrong about the VCUG test for children
“If the VCUG is normal, my child will not get another UTI.” A normal study rules out reflux and obstruction at the time of testing. It does not change the fact that most childhood urinary infections, as the NHS notes, happen in children with completely normal anatomy. Hygiene, constipation, and voiding habits still matter.
“Reflux means my child will need surgery.” Most children with lower-grade reflux never have an operation. The NIDDK describes spontaneous resolution as common in mild to moderate grades, and the usual strategy is monitoring, prompt treatment of infections, and in some children a low-dose preventive antibiotic. Surgery is discussed mainly for higher grades, breakthrough infections, or kidney damage.
“The test needs general anesthesia.” It does not, and anesthesia would defeat the voiding phase. Most children have it awake with comfort support.
“Contrast dye will harm the kidneys.” The contrast in a VCUG goes into the bladder, not the bloodstream, so the kidney effects associated with intravenous contrast do not apply. The main risk is a small chance of introducing infection via the catheter, which sterile technique keeps low.
“My child is too young for the test to work.” Infants cannot void on command, but they void spontaneously once the bladder is full, and radiologists are practiced at capturing that moment. Many VCUGs are done in babies under a year.
“Older VCUG radiation doses apply today.” Pulsed fluoroscopy and pediatric protocols have cut doses markedly. The exposure from a well-performed modern study is low.
“If my child wets the bed, they need a VCUG.” Isolated nighttime wetting without daytime symptoms or infections is not usually an indication for the test.
“A retrograde cystogram is the same thing.” It is not; the voiding phase is the whole point of a VCUG, and a cystogram without it answers a different question.
Questions to ask your care team before and after a voiding cystourethrogram
Parents often leave the referral appointment with the practical details and none of the reasoning. These questions tend to surface the reasoning.
Before the test
- What specifically are you hoping this study will show or rule out in my child?
- Was an ultrasound done first, and what did it show?
- Would a nuclear cystogram or a contrast ultrasound study be an acceptable alternative for my child, and why or why not?
- Does the department use pediatric dose-reduction settings, and is a child life specialist available?
- Is numbing gel or any form of sedation planned, and what does that involve?
- Should my child finish their current antibiotic course before the test?
- Can I stay in the room, and what is the best way for me to help?
- How will I receive the results, and roughly when?
After the test
- Was reflux seen, on which side, and what grade?
- Was the urethra normal, and did the bladder empty completely?
- Does this result change anything about how we handle fevers or suspected infections at home?
- Is preventive antibiotic being considered, and what is the thinking behind that for my child specifically?
- When would repeat imaging be considered, and what type?
- Should we be looking at bladder habits or constipation as part of the plan?
- At what point would a pediatric urologist or nephrologist become involved?
Writing down the answers, or asking permission to record the conversation, is reasonable; grade numbers and side are easy to muddle a week later. Every one of these questions has an answer that depends on your child, and the team is the right place to get it.
When to call your doctor after a VCUG
Serious problems after a voiding cystourethrogram are uncommon, but the catheter does create a small opening for infection, and children who have just had an infection may already be vulnerable. The practical rule is that mild stinging for a day is expected; anything escalating or new is not.
Contact your child’s doctor the same day, or seek urgent care, if you notice any of the following:
- A fever, especially above 38°C (100.4°F), in the two to three days after the study, since this can signal a urinary infection introduced during catheterization.
- Pain in the back or side, which can indicate kidney involvement rather than bladder irritation.
- Urine that is clearly bloody, rather than faintly pink, or that contains clots.
- Burning or pain with urination that is worsening after the first day rather than improving.
- Your child has not passed urine for eight hours or more despite drinking, or is straining without producing a stream.
- Vomiting, unusual drowsiness, or a child who looks generally unwell.
- In an infant, poor feeding, irritability, or fewer wet diapers than usual.
- Swelling, redness, or discharge around the urethral opening.
For babies under three months, any fever is treated as urgent regardless of the recent test, in line with MedlinePlus guidance on urinary infections in young children.
Separately from the test itself, if your child has known reflux awaiting follow-up and develops a fever without an obvious cause such as a cold, a urine sample should be checked promptly. Early treatment of kidney infections is the main way reflux-related scarring is prevented, and this is the one piece of advice that applies to nearly every child in this pathway. Your child’s team will tell you exactly how they want you to reach them and what threshold they prefer; when in doubt, make the call.
Frequently asked questions
What is the VCUG procedure for a child, in simple terms?
A thin catheter is passed into the bladder, contrast fluid fills it, and X-ray images are taken while the bladder fills and while the child urinates. The images show whether urine flows backward toward the kidneys and whether the urethra is open along its length. The child is awake, a parent can usually stay, and MedlinePlus notes the study is commonly completed within about an hour.
What are the indications for micturating cystourethrography in children?
Micturating cystourethrography is simply another name for the VCUG. The main indications are a febrile urinary tract infection, particularly in infants or when ultrasound is abnormal, and hydronephrosis (swollen kidneys) seen on prenatal or newborn scans. Others include recurrent infections, suspected posterior urethral valves in boys, and daytime wetting with infections. The treating team decides whether and when the test is appropriate.
What is the difference between a retrograde cystogram and a VCUG?
Both fill the bladder through a catheter with contrast, but a retrograde cystogram is mainly used to check the bladder wall for leaks or tears and may not include urination. A VCUG always includes the voiding phase, which is what reveals reflux during the bladder’s squeeze and outlines the urethra. In children, the VCUG is the standard study for reflux and obstruction.
What is voiding dysfunction in a child?
Voiding dysfunction describes toilet-trained children whose bladder and outlet muscles do not coordinate normally, without a nerve or structural disease. Symptoms often include daytime wetting, urgency, holding, straining and recurrent infections, frequently alongside constipation. Most children are managed with bladder habits and constipation treatment; a VCUG is reserved for those with febrile infections or abnormal ultrasound findings.
What does vesicoureteral reflux grading mean?
Grading describes how far urine travels backward and how much it stretches the ureter and kidney, on a scale from I (ureter only) to V (severe widening with distorted kidney contours). Lower grades often resolve as the child grows, according to the NIDDK and Mayo Clinic, while higher grades are monitored more closely and are more likely to lead to discussion of intervention.
Is a VCUG painful for a child?
Catheter placement is the uncomfortable step, usually described as stinging or pressure lasting a minute or two rather than sharp pain. Numbing gel, a parent’s presence, distraction and child life support reduce distress. The filling phase feels like a full bladder. Mild stinging with the first urinations afterward is common and usually settles within a day.
Does a VCUG test for children expose them to a lot of radiation?
A modern pediatric VCUG uses pulsed fluoroscopy and tight collimation, and the dose is described as low by the NIH and Mayo Clinic, roughly comparable to a few months of natural background radiation. It is more than a chest X-ray and much less than an abdominal CT. For repeat studies, lower-radiation options such as nuclear cystography are often considered.
Can a baby have a voiding cystourethrogram?
Yes. Infants cannot urinate on request, but they void spontaneously once the bladder is full, and pediatric radiologists are experienced at capturing that moment. Many VCUGs are performed in babies under one year, typically after a febrile urinary infection or when prenatal scans showed hydronephrosis. Feeding and comfort holding are usually part of the routine.
How long after a UTI should a child have a VCUG?
The infection is usually treated fully first, because filling an infected bladder is uncomfortable and may push bacteria upward. Many teams schedule the study a few weeks after the infection has cleared, though timing varies with the child’s age and findings on ultrasound. Your child’s doctor will set the interval based on their situation.
What happens if the VCUG shows reflux?
The next steps depend on grade, age and infection history. Lower grades are often monitored with prompt treatment of any infections and sometimes a preventive antibiotic, with repeat imaging planned later. Higher grades, breakthrough infections or kidney damage prompt referral to a pediatric urologist to discuss options. All of these decisions rest with your child’s treating team.
References
- MedlinePlus: Voiding cystourethrogram
- MedlinePlus: Vesicoureteral reflux
- MedlinePlus: Urinary tract infection – children
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

From Urine Test to Cystoscopy: How Urologists Sequence Diagnostic Tests and Why Order Matters
Urologists usually sequence diagnostic tests from least to most invasive: a symptom history and physical exam, then urinalysis and often a urine culture, then…

Which Blood Tests Drive Renal Osteodystrophy Care and How Results Adjust the Plan
Renal osteodystrophy care is guided mainly by blood tests for parathyroid hormone, phosphate, calcium, alkaline phosphatase and vitamin D, read alongside kidney function markers…

Diabetes Medicines and Blood Thinners Before Urological Surgery: What Your Team Reviews
Before urological surgery, the anesthesia and surgical team review every diabetes medicine and blood thinner you take, because fasting, surgical stress and bleeding risk…

When Antibiotics Are Not Enough for a Complicated UTI: Drainage, Stones and Urology Care
Antibiotics alone may not clear a complicated urinary tract infection when a kidney stone, a narrowing or an enlarged prostate blocks urine flow, or…

What Slowing Kidney Disease Actually Looks Like: Realistic Goals for Function and Symptoms
Yes, for most people chronic kidney disease progression can be slowed, though not usually reversed. Slowing means the yearly fall in eGFR shrinks toward…

Living With an Enlarged Prostate: Follow-Up Visits, Medication Reviews and Daily Habits
Living with an enlarged prostate usually means a long-term partnership with a clinician rather than a single fix: periodic follow-up visits that track symptoms,…