

What Happens During a Root Canal? Cleaning, Shaping and Sealing the Canals Step by Step
Key Takeaways
- A root canal removes infected or dead pulp from inside the tooth and seals the canals; the tooth survives because the surrounding bone and gum still support it from outside.
- The procedure has four stages, numbing and access, cleaning, shaping and sealing, and the disinfecting rinse between files does much of the work that people imagine the instruments do.
- Cleveland Clinic gives typical appointment times of 30 to 60 minutes, with complex molars taking up to about 90 minutes and sometimes a second visit.
- Under local anesthesia the NHS describes root canal treatment as no more unpleasant than a filling; the pain people fear is usually the toothache that came before.
- Antibiotics cannot clear infection sealed inside a tooth because a dead pulp has no blood supply; they only help control spread into surrounding tissues.
- The NHS reports that a root-treated tooth can survive up to 10 years in about 9 out of 10 cases, and a crown placed promptly is a key part of reaching that outcome.
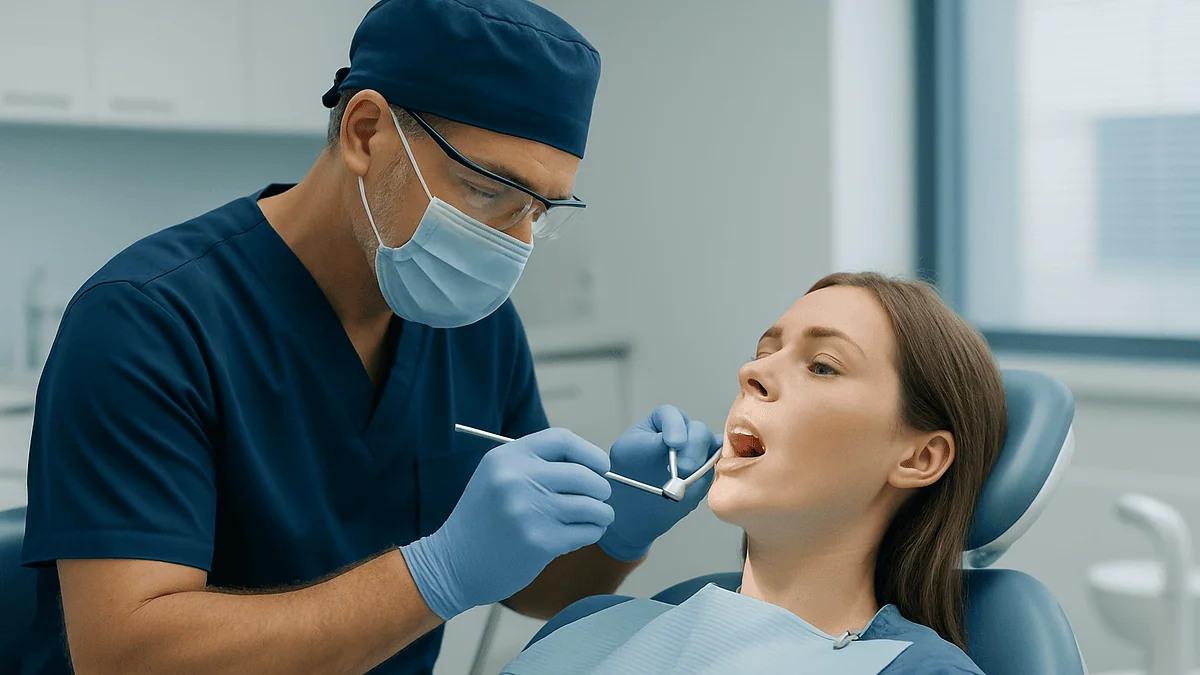
A root canal procedure treats infection or inflammation inside a tooth by removing the soft tissue in its center, cleaning and shaping the narrow root canals, and sealing them. The dentist numbs the tooth, isolates it, opens the top, cleans and disinfects the canals with fine instruments and rinses, fills them with a rubber-like material, and closes the tooth, usually with a filling and later a crown. It typically takes one or two visits.
The X-ray goes up on the screen, the dentist points at a dark shadow under a root, and says the word that makes most people’s shoulders tighten: root canal. What usually follows is a rush of half-remembered stories from relatives and a vague sense that something dramatic is about to happen inside the jaw.
The reality is quieter and more mechanical than the reputation. A root canal procedure step by step is closer to careful plumbing than surgery: a small opening, a cleaning of very narrow channels, a shaping of those channels so they can be filled properly, and a seal. Most of the drama people fear is actually the toothache that led them to the chair in the first place.
This explainer walks through what the dentist is doing at each stage, what the evidence says about pain and recovery, and where the common myths fall apart. The decisions about your tooth belong to you and your treating team; the aim here is to make that conversation easier.
What is a root canal procedure step by step, in plain language?
Every tooth has a hollow center. Inside it sits the pulp, the soft tissue of nerves and blood vessels that helped the tooth form and still registers hot and cold. From that central chamber, thin channels called root canals run down through each root toward the jawbone. When bacteria reach the pulp, through a deep cavity, a crack, or repeated dental work, the tissue becomes inflamed and eventually dies. The tooth itself can survive without its pulp, because the surrounding bone and gum keep nourishing it from outside. What cannot be left in place is infected tissue sealed inside a space the immune system struggles to reach.
Root canal treatment, which dentists also call endodontic treatment (endodontics is the branch of dentistry dealing with the inside of the tooth), removes that tissue and seals the space so bacteria cannot recolonize it. The NHS describes the sequence in four broad movements: opening the tooth, removing the pulp and any pus, cleaning and enlarging the canals, then filling and sealing them.
Think of a canal as a tiny, curved drinking straw embedded in the root, often narrower than a millimeter at the tip. The dentist cannot see down it. The work relies on X-rays, measuring devices, tactile feel and a series of flexible files that gradually clear and widen the channel. Once the canals are clean and shaped, a rubber-like material is packed in to fill them completely, and the top of the tooth is closed.
That is the whole idea. The following sections take each stage in turn, because the details, and the reasons behind them, are what answer most of the questions people bring to the chair.
Why does a tooth end up needing root canal treatment?
Bacteria get into the pulp through one of a handful of routes. The most common is decay that has burrowed through enamel and dentin (the softer layer beneath enamel) and reached the pulp chamber. A crack from grinding, a hard bite or an old injury can do the same, sometimes with no visible hole at all. Repeated fillings on one tooth, or a knock to the mouth years earlier, can also leave the pulp struggling.
Once bacteria are inside, the pulp becomes inflamed. In a finger or a knee, inflammation has room to swell. Inside a tooth it does not; the rigid walls trap the pressure, which is one reason a dying pulp can hurt so intensely. Eventually the tissue dies and the infection spreads through the tip of the root into the bone, where it can form a pocket of pus called an abscess. Mayo Clinic notes that an untreated abscess does not resolve on its own and can spread to the jaw and beyond.
A dead pulp is not always painful. Some teeth go quiet after the initial ache, and the first sign of trouble is a shadow on a routine X-ray or a small pimple-like swelling on the gum. That silence is misleading; the infection is still active in the bone.
Dentists decide whether the pulp can recover or must be removed using the history of the pain, tests of how the tooth responds to cold, gentle tapping, and X-rays. A pulp that is reversibly inflamed may settle after the cavity is fixed. A pulp that is irreversibly inflamed or dead needs either root canal treatment or extraction. That distinction, not the size of the cavity, is what puts root canal treatment on the table.
Who is a root canal usually for, and who is usually asked to wait?
Root canal treatment is offered when the pulp is irreversibly damaged or infected but the tooth itself is worth keeping: enough sound structure remains above the gum to hold a filling or crown, the roots are intact, and the surrounding bone can support the tooth after healing. Age is not a barrier in itself. Children with fully formed adult teeth, adults of any age and older people with otherwise healthy mouths are all treated routinely.
Some situations push the treating team toward a different plan or a pause. A tooth split vertically down the root usually cannot be saved, because no seal can close a crack that runs into the bone. A tooth with so much decay that little natural structure remains may not hold a crown afterward, and extraction with a replacement may be the more predictable route. Roots that are severely curved, blocked by earlier treatment or fused in unusual ways may need referral to an endodontist, a dentist with additional training in root canal treatment.
Waiting is sometimes deliberate rather than a delay. If a person arrives with a large facial swelling and fever, the first visit may focus on draining the abscess and, when the dentist judges it necessary, prescribing an antibiotic to control spreading infection; the full cleaning follows once the acute phase settles. People taking blood thinners, those with certain heart conditions or those whose medical history calls for coordination with a physician may also have the timing adjusted. In each case the sequence is set by the treating team, and the reasoning should be explained to you.
Pregnancy deserves a specific mention. Dental infection is not something to leave untreated during pregnancy, and dentists routinely provide treatment with appropriate precautions; the timing and imaging are individual decisions made with the patient.
Step 1: numbing, isolating the tooth and opening the top
The first minutes look like any filling appointment. A local anesthetic, a medicine that temporarily blocks nerve signals in one area, is injected near the tooth. Because an inflamed pulp can be harder to numb, the dentist may use more than one injection site or technique and will check that the tooth is fully numb before starting. The NHS is explicit that the procedure is carried out under local anesthetic and should not be painful.
Next comes the rubber dam, a thin sheet of latex or latex-free material stretched over a small frame with a hole for the tooth being treated. It has three jobs. It keeps saliva, which is full of bacteria, out of the tooth while the inside is being disinfected. It stops rinsing solutions and small instruments from going down the throat. And it gives the dentist a dry, clear view of one tooth at a time. Many people find it oddly restful, because there is nothing to hold open or swallow around.
Then the dentist uses a drill to make a small opening through the top of the tooth into the pulp chamber. For a back tooth this goes through the chewing surface; for a front tooth, through the back surface so the front stays untouched. The opening is deliberately shaped so that each canal entrance can be reached in a straight line, which reduces the chance of a file bending or breaking later. This is the moment the pressure inside a badly inflamed tooth is released, and some people notice relief almost immediately.
With the chamber open, the dentist locates the canal openings. A molar typically has three or four; a front tooth usually one. Finding every canal is a central part of the job, because a missed one is a common reason for treatment to fail later.
Step 2: cleaning the canals, and what is actually being removed
Cleaning is the heart of the procedure and the part people picture least accurately. There is no scraping of the tooth from outside. The dentist works entirely within the canals using files: slender, flexible instruments, some twisted by hand and some driven by a slow motor, that remove pulp tissue and the thin inner layer of dentin lining the canal.
Before that can happen safely, the dentist needs to know how long each canal is. A file placed in the canal is measured with an X-ray, an electronic apex locator (a device that senses when the tip of the file reaches the end of the root, called the apex) or both. Working too short leaves infected tissue behind; working too long pushes debris into the bone and irritates it. The measurement is recorded and every subsequent file is set to that length.
Between files, the canal is flushed repeatedly with an irrigant, a disinfecting rinse that dissolves remaining tissue and kills bacteria in the microscopic side branches no instrument can reach. This alternating rhythm of file, rinse, file, rinse, is where most of the appointment time goes. The rinsing is doing at least as much of the disinfection as the metal.
People often ask what is being taken out. In a freshly inflamed tooth it is living but damaged pulp, which is why the tooth is numbed first. In a long-dead tooth it may be necrotic tissue and pus, and the dentist may notice the canal drain for a moment when it is first opened. Either way the goal is the same: an empty, disinfected channel from the chamber to just short of the root tip.
If the infection is extensive, the dentist may place an antibacterial paste inside the canals and close the tooth with a temporary filling, letting the disinfectant work between visits. The NHS notes that the dentist may leave the tooth for around a week in this situation before finishing.
Step 3: shaping the canals, and why the shape matters as much as the cleaning
A natural canal is narrow, irregular and often curved. Even a spotless canal of that shape cannot be filled reliably, because the filling material needs a smooth, tapering passage to flow into and pack against. Shaping is the process of enlarging the canal into a gentle cone, widest at the chamber and narrowest near the root tip, while following the canal’s original curve.
Dentists do this with a sequence of files of increasing size, each removing a fraction of a millimeter of dentin. Modern files are usually made from a nickel-titanium alloy that bends around curves instead of straightening them, which lowers the risk of carving a false path through the root wall. The dentist stays within the measured working length throughout, so the taper ends where the canal naturally ends rather than beyond it.
Shaping serves cleaning as well as filling. Widening the canal lets the irrigant reach deeper and circulate more effectively, and the dentin removed during shaping is the layer most likely to harbor bacteria that have penetrated its microscopic tubules. Cleaning and shaping are therefore taught as a single combined phase rather than two separate ones.
There is a balance to strike. Remove too little and the seal may be incomplete; remove too much and the root is thinned, which raises the risk of a fracture years later. This judgment, made canal by canal, is one of the reasons experience and referral matter in complex cases, and why a tooth with unusually curved or calcified canals (canals partly closed by mineral deposits over time) may be sent to an endodontist.
Once the dentist is satisfied that each canal is clean, dry and shaped to a consistent taper, the tooth is ready for the stage that most people think of as the root canal itself: the filling of the canals.
Step 4: sealing the canals and closing the tooth
The canals are dried with fine paper points, absorbent tapers that soak up the last of the rinsing solution. A canal that is still wet or still weeping fluid from the bone is not ready to be sealed, and the dentist may choose to place medication and finish at a later visit rather than fill a damp canal.
The filling material is gutta-percha, a rubber-like substance derived from the sap of certain trees that has been used in dentistry for well over a century. It is chosen because it is inert, adapts to canal walls under gentle pressure, and can be removed if the tooth ever needs re-treatment. Pre-shaped cones of gutta-percha matched to the final file size are coated with a sealer, a paste that fills the microscopic gaps between the cone and the dentin, and placed to the measured working length. Depending on technique, the dentist may pack additional cones alongside the first or soften the material with heat so it flows into irregularities.
A final X-ray checks that the fill reaches the right length and looks dense along the whole canal without voids. This image also becomes the baseline for future comparison; healing of the bone around the root tip is judged against it over the following months.
The last task is closing the access opening. Some dentists place the permanent filling at the same visit; others place a temporary one and schedule the definitive restoration separately. Either way, the tooth is now sealed from above and below. What it still lacks is protection from the forces of chewing, which is the subject of the crown discussion later in this article.
Cleveland Clinic gives a typical total appointment time of 30 to 60 minutes, with complex teeth taking closer to 90 minutes, and notes that a molar with several canals can require more than one visit.
How long does a root canal take, and why does it sometimes need two visits?
The honest answer depends on which tooth it is, how many canals it has, and how infected it is when the dentist opens it. A front tooth with a single straight canal is a different job from a lower molar with four curved ones. The table below summarizes the typical pattern, using the appointment ranges published by Cleveland Clinic and the visit structure described by the NHS.
| Situation | Typical chair time per visit | Usual number of visits | Why |
|---|---|---|---|
| Front tooth, one canal, no active abscess | About 30 to 60 minutes | Often one | Single straight canal, easy to dry and fill |
| Molar, three or four canals | Up to about 90 minutes | One or two | Multiple curved canals; more cleaning and shaping |
| Any tooth with pus draining or persistent wetness | Varies | Two or more | Medication placed inside; sealed once the canal is dry |
| Re-treatment of a previously filled tooth | Often longer | Two or more | Old filling material must be removed first |
The split into two visits is not a sign that something went wrong. When a canal keeps producing fluid, sealing it would trap bacteria and moisture beneath the fill. Placing an antibacterial paste and a temporary filling, then returning once the tooth is quiet, is a standard approach the NHS describes for teeth with active infection.
Single-visit treatment has become more common as instruments and disinfection methods have improved, and for a tooth with no drainage many dentists will complete everything in one sitting. Neither pattern has been shown to be clearly superior for every case; the choice rests on the state of the tooth on the day. Ask which pattern is planned for you and what would change it.
Does a root canal hurt? What the evidence says about pain during and after
The pain most people associate with root canals belongs to the toothache before treatment, not to the procedure. With effective local anesthesia, the NHS states that root canal treatment should not be painful and is no more unpleasant than having a filling. During the appointment you may feel pressure, vibration and the sensation of the dentist working, but the nerve fibers that would register sharp pain are blocked.
There are two exceptions worth knowing about. A severely inflamed pulp can be resistant to anesthesia, and a dentist may need to add anesthetic directly into the pulp once the chamber is open; this can produce a brief sharp moment before the tooth goes fully numb. And a tooth with a large abscess may be tender to touch even after numbing, because the inflamed tissue in the bone around the root is sensitive to pressure. Tell the dentist if anything hurts. Stopping to add anesthetic is routine, not an inconvenience.
After the appointment, some tenderness is expected. The ligament that holds the root in its socket has been irritated by the instruments and by the inflammation that brought you in, so the tooth may feel bruised when you bite for a few days. Cleveland Clinic describes this as mild discomfort that typically settles within a few days and that over-the-counter pain relief usually manages; the choice and use of any medicine is a conversation with your dentist or pharmacist, particularly if you take other medications.
Pain that escalates rather than fades, throbbing that keeps you awake, or swelling that grows in the days after treatment is not the normal pattern and should prompt a call, as set out in the final section.
Root canal recovery time: what the following days and weeks usually look like
The first hours are about the anesthetic wearing off. Until sensation returns fully, chewing on that side risks biting the cheek or tongue without noticing, so soft food and care with hot drinks are sensible. Once feeling returns, the tooth typically feels tender to pressure rather than achy on its own.
Over the next two or three days, that tenderness usually eases. Cleveland Clinic notes that most people return to normal activities the following day and that sensitivity generally resolves within a few days. Gentle brushing and flossing around the tooth should continue as normal; the seal inside is not affected by cleaning outside.
If a temporary filling was placed, it is designed to last weeks, not years. It wears and can chip, so avoid chewing sticky or very hard foods on that side and keep the appointment for the permanent filling or crown. The NHS advises against biting on hard foods with a root-treated tooth until it has been fully restored, because a tooth that has lost its pulp and had an opening drilled through its top is more prone to cracking under load.
Healing inside the bone takes longer than healing of the gum. The dark area seen on the original X-ray around the root tip shrinks gradually as bone regrows, a process the dentist assesses at follow-up visits, usually months later. Feeling normal does not mean the bone has finished healing, and finishing the restoration promptly is the single most practical thing a patient controls during this period.
Occasional mild awareness of the tooth when biting can persist for a few weeks while the ligament recovers. Persistent pain, a bad taste, a bump on the gum that returns, or the tooth feeling high when you close are reasons to be seen again rather than to wait.
Why the crown matters as much as the root canal itself
Cleaning and sealing the canals removes the infection. It does not restore the strength of the tooth. A back tooth that has lost its pulp, had decay removed and had an access opening drilled through its center has lost a substantial share of the structure that resisted chewing forces. Without protection, these teeth are vulnerable to splitting, and a split that runs below the gum usually means extraction, undoing everything the root canal achieved.
A crown is a cap, made of ceramic, metal or a combination, that covers the whole visible tooth and binds the remaining walls together so that biting force is spread across the cap rather than wedging the walls apart. The NHS advises that a crown is usually recommended after root canal treatment, particularly for teeth that do heavy chewing, and that the tooth may darken slightly over time, which a crown also addresses cosmetically.
Front teeth with a small access opening and otherwise intact structure may sometimes be restored with a filling alone, because they bear less force. Molars and premolars almost always benefit from full coverage. The decision depends on how much tooth remains, where it sits in the bite, and whether the person grinds their teeth; it is a judgment the dentist should walk through with you.
Timing matters. A root-treated tooth left with only a temporary filling for many months is exposed to two risks: fracture under load, and leakage of bacteria past the worn temporary back into the sealed canals. Both are avoidable. When the NHS reports that a root-treated tooth can survive for up to 10 years in about 9 out of 10 cases, that figure assumes the tooth was properly restored afterward. The crown is not an optional extra; it is the second half of the treatment.
Risks, alternatives and the reasons a root canal can fail
Root canal treatment is a routine procedure, and serious complications are uncommon, but it is not risk-free and patients deserve the plain list. During treatment, a file can occasionally break inside a curved canal; the fragment is often left in place if the canal beyond it is clean, and it does not usually affect the outcome. A canal can be perforated, meaning a small hole is made through the root wall, which may require repair. Rinsing solution can, rarely, be pushed beyond the root tip and cause swelling and bruising that resolves over time.
Failure over the longer term usually traces back to bacteria that survived or re-entered: a missed canal, a canal not cleaned to its full length, a leaking filling or crown, or a crack that lets saliva in. The NHS notes that if infection returns, treatment can often be repeated (re-treatment), or a small surgical procedure at the root tip can be considered. Extraction remains the fallback if neither is possible.
The main alternative is removing the tooth. Extraction ends the infection just as definitively, but the gap then needs a decision of its own: leave it, replace it with a bridge, a denture or an implant, each with its own timeline, risks and maintenance. Neighboring teeth can drift into an unfilled gap and the opposing tooth can over-erupt, which is why dentists usually favor keeping a natural tooth when it is reasonably restorable.
There is no medication that clears an infection sealed inside a tooth. Antibiotics can reduce spreading infection in the soft tissue and bone, which is why they are sometimes used alongside treatment when there is swelling or fever, but they cannot reach dead tissue in a canal that has no blood supply. Whether an antibiotic is appropriate, and for how long, is a decision for the prescribing dentist based on the clinical picture.
What people often get wrong about root canals
“A root canal is agonizing.” The pain belongs to the infected tooth, not to the treatment. Under local anesthesia the procedure is comparable to a filling, as the NHS states directly. Most people leave surprised by how ordinary it felt.
“If the tooth stopped hurting, the problem went away.” A pulp that dies stops sending pain signals, but the bacteria remain and the infection at the root tip continues. Mayo Clinic is clear that an abscess will not resolve without treatment. Silence is not healing.
“Antibiotics can fix it instead.” Antibiotics travel through the bloodstream, and a dead pulp has no bloodstream. They can help control spreading infection in the surrounding tissues, but the source inside the tooth still has to be physically removed and sealed.
“Root canals cause illness elsewhere in the body.” This idea dates from early twentieth-century theories that were never supported by controlled evidence and have not held up. Mainstream dental and medical bodies do not regard a properly treated tooth as a source of systemic disease. Leaving an untreated abscess in the jaw, by contrast, is a recognized route for infection to spread.
“Pulling the tooth is simpler.” Extraction is quicker on the day, but it starts a second decision about replacing the tooth, and each option carries its own appointments, risks and upkeep. Keeping a restorable natural tooth is usually the less complex path over years, which is why dentists generally favor it when the tooth is sound enough.
“Once the canals are filled, the tooth is finished.” The seal stops infection; it does not restore strength. A root-treated molar without a crown is more likely to fracture, and a worn temporary filling can let bacteria back in. The permanent restoration is part of the treatment, not an afterthought.
“The tooth is dead, so it can’t hurt again.” The tooth has no nerve, but the ligament and bone around it do. Renewed pain months or years later usually points to reinfection or a crack and needs assessment.
Questions to ask your care team before a root canal
A good consultation leaves you knowing not just that a root canal is planned, but why this tooth, why now, and what happens afterward. These questions tend to draw out the parts that matter most.
- What did the tests and X-ray show, and how confident are you that the pulp cannot recover on its own?
- How many canals does this tooth have, and do you anticipate anything that makes it complex, such as curved or narrowed canals?
- Do you plan to complete treatment in one visit or two, and what would change that plan on the day?
- Would this tooth be better treated by an endodontist, and if so, how does referral work?
- What kind of permanent restoration do you recommend afterward, and how soon should it be placed?
- How much of the tooth remains, and is it strong enough to hold a crown for the long term?
- What are the realistic alternatives for this particular tooth, including extraction and replacement, and how do they compare in your view?
- What should I expect to feel in the first few days, and what would be a reason to contact you?
- I take these medications and have these health conditions; does anything need to be adjusted or coordinated with my physician?
- When will you review the tooth with an X-ray to confirm the bone is healing?
Write the answers down or ask for them in writing. A root canal is usually a straightforward procedure, but the decisions around it, particularly about restoration and timing, shape how long the tooth lasts. The treating team makes the clinical calls; your job is to understand them well enough to keep your side of the plan, which mostly means turning up for the crown.
When to call your doctor
Some tenderness for a few days after root canal treatment is expected. The signs below are not, and they warrant a prompt call to your dentist, or to a doctor or emergency service if the dental practice is closed and symptoms are severe.
- Swelling of the face, cheek or under the jaw that appears or grows after treatment, especially if it spreads toward the eye or the neck.
- Fever, chills or feeling generally unwell in the days following the appointment.
- Pain that is increasing rather than easing after two or three days, or throbbing severe enough to disturb sleep.
- Difficulty swallowing, difficulty breathing, or inability to open the mouth normally. These can indicate infection spreading into the deep spaces of the neck and are treated as emergencies.
- A return of the original toothache, a bad taste or pus near the tooth, or a pimple-like bump on the gum that reappears.
- The temporary filling falling out or breaking, or the tooth cracking.
- An allergic-type reaction such as rash, itching or facial swelling after any medicine prescribed around the procedure.
- Numbness of the lip, chin or tongue that persists beyond several hours after the anesthetic should have worn off.
MedlinePlus advises that a tooth abscess with spreading swelling or fever needs urgent attention because infection can extend into the jaw and surrounding tissues. Do not wait for a scheduled follow-up if any of these develop. Your treating team would rather see you for a false alarm than miss a complication, and every decision about further treatment, including any medication, rests with them.
Frequently asked questions
What are the root canal steps in order?
The dentist numbs the tooth, isolates it with a rubber dam, and drills a small opening into the pulp chamber. Each canal is measured, then cleaned of pulp tissue with fine files and disinfected with rinsing solution. The canals are shaped into a smooth taper, dried, filled with gutta-percha and sealer, and checked on an X-ray. The opening is closed with a filling, and a crown usually follows to protect the tooth.
How long does a root canal take from start to finish?
Cleveland Clinic gives a typical range of 30 to 60 minutes for a single appointment, with complex teeth such as molars taking up to about 90 minutes. Some teeth are completed in one visit; others, particularly those with active infection or drainage, need a second visit after medication has been placed inside. Including the permanent crown, the full course may span a few weeks.
Does a root canal hurt while it is being done?
With effective local anesthesia it should not. The NHS describes the procedure as no more unpleasant than having a filling. You may feel pressure and vibration. A badly inflamed tooth can be harder to numb, so tell the dentist immediately if anything is sharp; adding more anesthetic is routine. Most of the pain associated with root canals is the toothache before treatment, which the procedure relieves.
What is the typical root canal recovery time?
Most people feel tenderness when biting for a few days, which Cleveland Clinic describes as mild and usually settling within a few days. Normal activities generally resume the next day. Healing of the bone around the root tip takes months and is checked on follow-up X-rays. Pain that increases after two or three days, or swelling, is not part of normal recovery and should be reported.
Why does a root canal sometimes need two visits?
If the canals are still draining fluid or pus, sealing them would trap bacteria and moisture inside. The dentist instead places an antibacterial paste, closes the tooth with a temporary filling, and completes the fill once the canal is dry and quiet. The NHS describes leaving the tooth around a week in this situation. Teeth with many canals or that are being re-treated may also need more time.
Can antibiotics treat a tooth infection instead of a root canal?
No. Antibiotics reach tissues through the bloodstream, and a dead or dying pulp has lost its blood supply, so the bacteria inside the tooth are beyond their reach. They may be used alongside treatment to control infection spreading into the face or jaw, at the prescribing dentist’s judgment. The source inside the tooth still has to be removed and sealed, or the tooth extracted.
Do I really need a crown after a root canal?
Usually, especially for back teeth. Removing the pulp, the decay and the tooth structure needed for access leaves the tooth weaker and more likely to split under chewing forces. The NHS advises that a crown is generally recommended after root canal treatment. Some front teeth with minimal loss of structure may be restored with a filling alone; your dentist will assess how much sound tooth remains.
What is the success rate of root canal treatment?
The NHS states that root canal treatment is usually successful and that in about 9 out of 10 cases the tooth can survive for up to 10 years afterward. That figure assumes the tooth is properly restored with a filling or crown. Outcomes vary with the tooth’s condition, the number and shape of the canals, and how well the final restoration seals the tooth from bacteria.
What are the alternatives to a root canal?
The main alternative is extraction, which removes the infection along with the tooth. The resulting gap can be left, or replaced with a bridge, denture or implant, each with its own timeline and maintenance. Leaving an infected tooth untreated is not a safe alternative, because Mayo Clinic notes an abscess will not resolve on its own and can spread. The treating team can compare the options for your specific tooth.
Why does my tooth still feel sensitive weeks after a root canal?
The tooth itself no longer has a nerve, but the ligament and bone around the root do, and they can remain mildly tender for a few weeks while they recover from the original inflammation and the treatment. A tooth that feels high when you bite may need a small adjustment. Sensitivity that worsens, persistent pain, a bad taste or a gum bump warrant a return visit for assessment.
References
- NHS: Root canal treatment
- Cleveland Clinic: Root Canal
- MedlinePlus: Tooth abscess
- MedlinePlus: Dental Health
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Tooth Decay Treatment Visit: Numbing, Removing Damaged Tissue and Restoring the Tooth
A cavity treatment procedure usually has three steps: the dentist numbs the area with a local anesthetic, removes the softened, decayed part of the…

How a Smile Makeover Is Planned: Photographs, Digital Impressions and Smile Design
A smile makeover is planned in stages: a dental health examination first, then a set of standardized photographs, a digital scan of the teeth,…

Gum Recession Treatment Results: How Grafted Gum Matures and What It Can and Cannot Restore
Gum graft results develop in stages: the graft attaches over the first one to two weeks, swelling and a pale or reddish look settle…
How to Read a Smile Makeover Plan: Questions About Each Step and Temporary Teeth
A smile makeover treatment plan is a written, sequenced document that lists each proposed procedure, the order it will happen in, what temporary teeth…

How Aesthetic Dentistry Is Planned: Smile Assessment, Imaging and Treating Decay First
Aesthetic dentistry treatment planning follows a fixed order: first a full smile assessment of the teeth, gums, bite and facial proportions; then imaging such…

When Aesthetic Dentistry Makes Sense and When Gum Health Has to Come First
Cosmetic dentistry usually makes sense once your gums are healthy and stable, any decay or infection has been treated, and a specific feature of…