

What Happens During a Tooth Extraction? Numbing, Loosening the Tooth and Closing the Socket
Key Takeaways
- An extraction loosens the tooth by stretching the periodontal ligament and flexing the socket, so you feel pressure and vibration rather than a sudden pull.
- Lower-jaw anesthetic is placed at the main nerve trunk, which is why a lower extraction numbs half the tongue and lip as well as the tooth.
- The blood clot in the socket is the scaffold for healing; the NHS advises no rinsing, spitting, straws, smoking or alcohol for the first 24 hours to protect it.
- Dry socket typically announces itself with pain building one to three days after the extraction, often radiating toward the ear, and is managed with cleaning and a medicated dressing.
- Dissolvable stitches used after wisdom tooth removal typically break down within about a week to ten days, according to the NHS.
- A pale white or yellowish film in the socket during the first week is usually granulation tissue from healing, not infection.
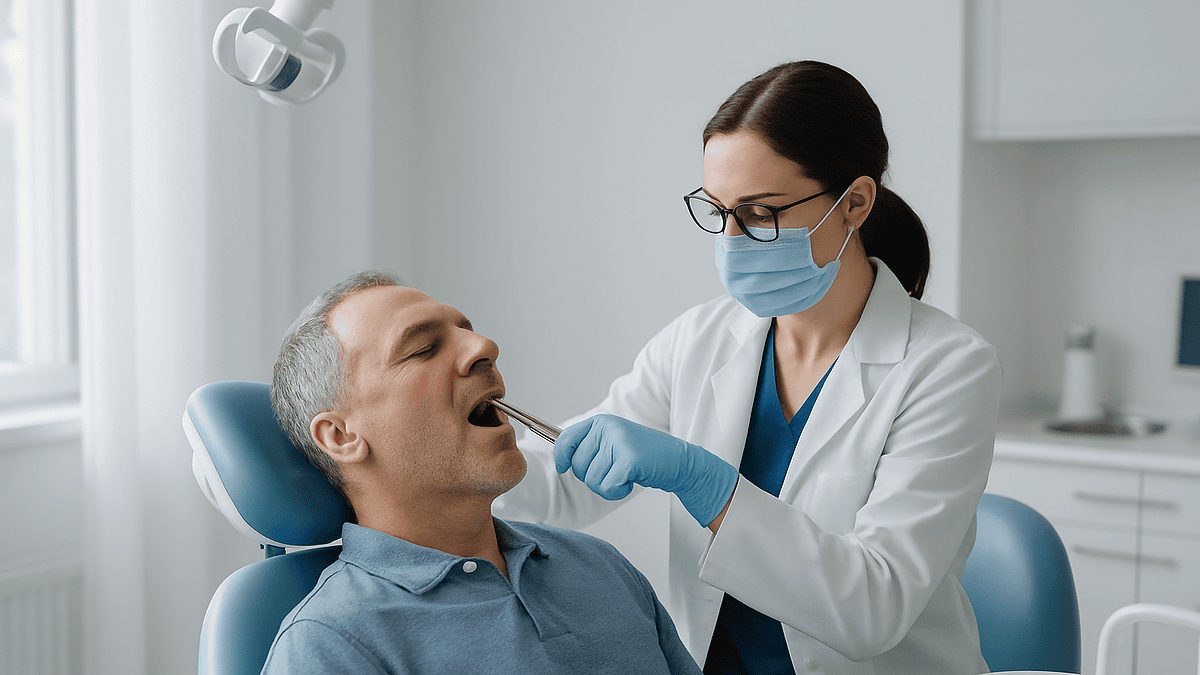
A tooth extraction procedure has three stages. First, the dentist numbs the tooth and surrounding gum with a local anesthetic injection, so you feel pressure but not sharp pain. Next, they loosen the tooth by gently widening its socket with instruments and lift it out, removing a little gum or bone if the tooth is impacted. Finally, they control bleeding with gauze, sometimes place stitches, and a blood clot seals the socket while it heals.
The waiting room has a fish tank, a stack of magazines nobody reads, and a man in his forties pressing his tongue against a lower molar that has finally cracked past the point of repair. He has been told it needs to come out. What he has not been told, at least not in a way that stuck, is what the next forty minutes will actually involve.
That gap between “you need an extraction” and “here is exactly what happens” is where most dental anxiety lives. People picture pulling, force, and a sudden pop. The reality of a modern tooth extraction procedure is slower, quieter and far more deliberate: a careful numbing step, patient loosening of the tooth within its socket, and a closing stage that is mostly about protecting a blood clot.
This explainer walks through each of those stages in order, using what mainstream dental and medical sources say rather than what a nervous relative remembers from decades ago.
What is a tooth extraction procedure, in plain language?
A tooth extraction is the removal of a tooth from its socket, the pocket of jawbone that holds the root in place. Dentists and oral surgeons (dentists with additional surgical training) perform millions of these each year, and the technique has changed less than people imagine. What has changed is the comfort.
Every tooth sits in a cushion of fibers called the periodontal ligament, which attaches the root to the bone on all sides. Think of a fence post set in slightly springy soil rather than concrete. The whole art of extraction is persuading those fibers to let go and the bone to flex a fraction of a millimeter, so the tooth can slide out along its own long axis. According to MedlinePlus, the dentist does this by rocking the tooth gently back and forth with instruments until it loosens, rather than yanking it straight up.
Where the tooth is visible and intact, this is called a simple extraction. Where it is broken at the gum line, still partly under bone, or has curved roots, the dentist may need to open the gum and remove a small amount of bone first; that is a surgical extraction. Both follow the same three-part logic described in the title: numb, loosen, close. The difference is how much work the middle step takes.
Why this matters: knowing that the procedure is about controlled movement rather than brute force tends to change how people breathe in the chair. The sensations you feel are mostly pressure and vibration, and the dentist is reading those same sensations through the instrument to judge when the tooth is ready to come out.
Why dentists recommend removing a tooth, and who is usually asked to wait
Dentists generally try to keep natural teeth, so an extraction is suggested when the alternatives are weaker. The Cleveland Clinic lists the common reasons: decay that has destroyed too much tooth to restore, a crack that runs below the gum line, advanced gum disease that has loosened the tooth, an infection that has not responded to root canal treatment, and crowding when teeth are being straightened. Wisdom teeth, the third molars at the very back, are often removed because they are impacted, meaning they cannot fully emerge and sit at an angle against the neighboring tooth; the NHS notes that impacted wisdom teeth that cause repeated infection, decay or damage to adjacent teeth are the usual candidates.

Children sometimes need a baby tooth removed if it is badly decayed or refuses to fall out and blocks the adult tooth beneath it. The steps are the same, with more attention to explanation and comfort.
Who is asked to wait? Not usually forever, but often until something else is sorted out. A person with an acute, swollen infection may be asked to let the swelling settle first, because local anesthetic works less reliably in inflamed tissue. Someone taking medicines that affect clotting, including anticoagulants and antiplatelet drugs, should expect the dentist to coordinate with the prescribing clinician; the usual advice is to never stop these medicines on your own. People who have had radiation to the jaw, or who take certain bone-strengthening drugs, need extra planning because their jawbone heals differently. Pregnancy does not rule out an extraction, but timing and imaging are discussed case by case. The decision always rests with the treating team, who weigh the tooth against the whole person.
Before the tooth extraction procedure: the exam, the X-ray and the honest conversation
Nothing is removed until the dentist has looked both at and under the tooth. A clinical exam checks how loose or firm it is, how much crown remains above the gum, and whether the gum is inflamed. Then comes the X-ray, which answers the questions the eye cannot: how many roots, how curved, how close to the sinus floor in the upper jaw, and how close to the inferior alveolar nerve, the nerve that runs through the lower jaw and supplies feeling to the lip and chin. For lower wisdom teeth in particular, the Mayo Clinic notes that imaging helps the surgeon judge nerve proximity and plan the approach.
Expect a medical history review that feels thorough for a dental visit. The dentist wants to know about heart conditions, diabetes, bleeding disorders, allergies, previous reactions to anesthetics, and every medicine and supplement you take. Some of these change the plan; others simply mean the team watches for specific things afterward.
This is also when the choice of anesthesia is settled. Most extractions are done under local anesthetic alone, with the person fully awake. For longer surgical cases or for people with significant anxiety, sedation may be offered, either as a tablet beforehand, as a gas breathed through a nose mask, or through an intravenous line; the Mayo Clinic describes all three as options for wisdom tooth removal, with general anesthesia reserved for selected cases. Each has different rules about eating beforehand and about having someone drive you home. Ask what applies to you rather than assuming.
Step one: numbing. What local anesthesia actually does inside the gum
Local anesthetics work by blocking sodium channels in nerve fibers, the tiny gates that let an electrical signal travel along the nerve. With the gates closed, the nerve cannot send its pain message to the brain. The tooth is still there, still being touched, but the wiring is temporarily cut.

In practice the dentist often starts with a topical gel on the gum so the needle itself is less noticeable. Then the injection is placed near the tooth. In the upper jaw the bone is thin and porous, so the anesthetic soaks through to the root tips directly. In the lower jaw the bone is dense, so the dentist usually aims for the main nerve trunk further back, which is why a lower extraction numbs half your tongue and lip as well as the tooth. That spreading numbness is expected, not an error.
Onset typically takes a few minutes. Before beginning, the dentist will test the gum with an instrument and ask what you feel. If anything registers as sharp rather than dull pressure, more anesthetic is added. The MedlinePlus patient guidance is explicit that you should tell the dentist if you feel pain at any point, and that extra numbing can be given.
The numbness generally lasts well beyond the procedure itself. The NHS advises that feeling returns over the following hours, and it warns against eating hot food or chewing on that side until sensation is back, because a numb cheek or tongue is easy to bite without noticing. Decisions about which anesthetic agent to use, and whether to combine it with sedation, belong to the dentist.
Does tooth extraction hurt? Separating pressure from pain
The most searched question deserves a straight answer: with adequate local anesthesia, the extraction itself should not be painful. It will, however, be strange. People reliably describe three sensations. The first is pressure, sometimes considerable, as the dentist pushes against the tooth and bone. The second is vibration or a creaking feeling conducted through the jaw, especially during the loosening phase. The third is sound: the squeak of ligament fibers letting go, a click as the tooth lifts, the whir of a handpiece if bone is being smoothed. None of these is pain, but the brain can mislabel them when it is already braced for the worst.
Pain during the procedure usually means the anesthetic has not fully reached one part of the tooth, which happens more often with lower molars and with teeth that are acutely infected, because inflamed tissue is more acidic and anesthetics work less efficiently there. The fix is more anesthetic, a different injection site, or occasionally a pause to let an infection settle before trying again. Raise a hand; dentists expect it.
After the numbness wears off, soreness is normal and peaks in the first day or two. How much depends on the size of the tooth, how long it took, and whether bone was removed. The NHS notes that pain and swelling after wisdom tooth removal usually improve over a few days and that over-the-counter pain relief is commonly sufficient; what to take, and how, is a question for the dentist or pharmacist, especially if you have other health conditions or medicines.
Step two: loosening the tooth, and why it is wiggled rather than pulled
Once the area is numb, the dentist begins with an instrument called an elevator, a slim lever that slips between the tooth and the bone. By rotating and gently pressing it, they stretch the periodontal ligament fibers and start to expand the socket. The bone of the jaw is not rigid; it is slightly elastic, particularly on the cheek side, and it can be flexed outward a little before springing back once the tooth is gone.
Forceps follow. These grip the tooth low on the root rather than on the crown, and the dentist moves the tooth in slow, deliberate directions: outward toward the cheek, inward toward the tongue, sometimes with a slight rotation for a single-rooted tooth like a canine. The MedlinePlus description is accurate to what you will feel: rocking back and forth until the tooth loosens. Each movement widens the socket by a fraction and tears a few more ligament fibers. The patience is the point. Pulling straight up risks snapping a root, which turns a simple job into a fiddlier one.
Multi-rooted molars are sometimes sectioned, meaning the dentist cuts the crown so each root can be removed separately along its own curve. This is routine, not a sign of trouble. If a root tip breaks, the dentist decides whether to retrieve it or, rarely, leave a tiny fragment that is safer to leave than to chase.
When the tooth finally releases there is often a distinct sensation of relief in the jaw, followed by nothing much. The dentist checks the tooth to confirm all roots are complete, inspects the socket, and removes any infected tissue or sharp bone edges before moving to the closing stage.
Simple vs surgical extraction: what changes and what stays the same
People often arrive believing “surgical” means hospital, general anesthesia and days off work. Usually it means the dentist needs to see more of the tooth. If the crown has crumbled below the gum, if the tooth is impacted under bone, or if the roots are curved or fused, the dentist makes a small incision in the gum, lifts it back, and removes a thin shell of bone with a handpiece cooled by water. From that point the loosening and lifting proceed as before, and the gum is stitched back afterward. The Cleveland Clinic describes both categories, and the Mayo Clinic notes that impacted wisdom teeth may need to be divided into pieces to come out through a smaller opening.
| Feature | Simple extraction | Surgical extraction |
|---|---|---|
| Tooth position | Visible above the gum, intact enough to grip | Broken at gum line, impacted, or with difficult roots |
| Anesthesia | Local anesthetic | Local anesthetic, with or without sedation |
| Gum incision | Not usually | Yes, a small flap lifted and replaced |
| Bone removal | No | Sometimes, a thin layer around the tooth |
| Tooth sectioned | Occasionally for molars | Common for impacted teeth |
| Stitches | Sometimes | Usually, often dissolvable |
| Typical swelling | Mild | More noticeable, peaks around days 2 to 3 |
What stays the same matters more than what differs. Both rely on complete numbing, both depend on the dentist reading resistance through the instruments, and both end with the same priority: a stable blood clot in the socket. Recovery after a surgical extraction tends to be longer and more swollen, which the NHS attributes to the greater disturbance of gum and bone, but the healing biology is identical.
Step three: closing the socket. Clots, gauze and stitches explained
The socket left behind is a hole in bone roughly the shape of the root, lined with torn ligament fibers and small bleeding vessels. Closing it is not about sealing it shut; it is about letting the body build a plug. Within minutes, blood pools in the socket and begins to clot. That clot is the scaffold for everything that follows: new blood vessels grow into it, soft tissue migrates across it, and over months bone fills in beneath. The Mayo Clinic is blunt about its importance: the clot protects the exposed bone and nerve endings, and losing it is what leads to dry socket.
So the dentist’s first move is to place a folded gauze pad over the socket and ask you to bite down firmly. Pressure slows the bleeding and holds the forming clot in place. MedlinePlus advises biting on the gauze for roughly half an hour to an hour, changing it if it becomes soaked, and avoiding the temptation to peek or poke with your tongue.
Stitches, formally sutures, are placed when the gum has been lifted or when the edges gape. Many are dissolvable; the NHS notes these typically break down on their own within about a week to ten days after wisdom tooth removal, though some types take longer and non-dissolving stitches need a short follow-up visit. Dissolvable stitches can feel like loose threads for several days, which is normal.
Before you leave, the dentist checks that bleeding has slowed to a trickle, confirms you can see the written aftercare instructions, and may place a fresh gauze pad. A little oozing that tints your saliva pink for several hours is expected; a socket that fills steadily with bright blood is not, and the “when to call” section below covers that distinction.
Tooth extraction recovery time: what the first two weeks usually look like
Healing has a recognizable shape, and knowing it reduces the number of worried evenings. The figures here are typical ranges from the NHS and Cleveland Clinic, not promises; large surgical extractions sit at the longer end and a wobbly baby tooth at the shorter.
In the first 24 hours, the job is protecting the clot. The NHS advises against rinsing, spitting forcefully, drinking through a straw, smoking or drinking alcohol during this window, because suction and chemical irritation can dislodge the clot. Rest, keep your head slightly raised, and eat soft, cool or lukewarm food on the opposite side. Numbness fades over hours; soreness arrives as it does.
Days two and three are usually the peak for swelling and stiffness, particularly after lower wisdom teeth. A cool compress on the cheek in short intervals during the first day can limit swelling; after that, the body is already doing the work. From the second day onward the NHS recommends gentle rinsing with warm salt water after meals to keep the socket clean, letting the water fall out of the mouth rather than spitting.
Through the first week, the socket surface changes from dark red to a yellowish-white film. That film is healing tissue, not infection, and it alarms people every day. Normal brushing continues for the rest of the mouth, with care near the site. By the end of week two the gum has typically grown over the socket; the Cleveland Clinic notes that the underlying bone keeps remodeling for several months, which is why implant or denture planning is paced accordingly. If you are still needing regular pain relief after a week, or pain is getting worse rather than better, that is a reason to be seen.
Dry socket after tooth extraction: what it is and how dentists manage it
Dry socket, known clinically as alveolar osteitis, is what happens when the blood clot either fails to form or is lost before the socket has grown a protective lining. The bone and nerve endings are left exposed to air, food and saliva. The Mayo Clinic describes the hallmark: pain that begins to build one to three days after the extraction, often radiating to the ear or temple on the same side, sometimes with a bad taste or odor and a socket that looks empty or shows whitish bone instead of a dark clot.
It is the most common complication of extraction and is seen more often after lower wisdom teeth, in people who smoke, in those taking oral contraceptives, and when the socket has been subjected to suction or vigorous rinsing early on. The Mayo Clinic lists these as recognized risk factors; none guarantees a dry socket and avoiding them does not guarantee you will not get one.
Management is straightforward and belongs with the dentist. The socket is gently irrigated to remove debris, then a medicated dressing is placed to cover the bone and ease pain; this is usually changed every day or two until the socket starts to heal on its own. Pain relief is discussed individually. Antibiotics are not routinely needed because dry socket is a healing problem rather than a bacterial infection, although the dentist will assess for infection separately.
The practical lesson is simple. Pain that improves each day is healing. Pain that was improving and then sharply worsens around day two or three, especially with a bad taste, is a dry socket until proven otherwise, and it is treatable; it is not a sign that something went wrong during the extraction itself.
Other risks of a tooth extraction, and the alternatives worth discussing
Beyond dry socket, the recognized complications are infrequent but worth naming plainly. Infection of the socket can occur, usually showing as increasing swelling, pus, fever or a persistent bad taste beyond the first few days. Bleeding that restarts hours later is usually controlled with firm gauze pressure, though people on anticoagulants are watched more closely. Nerve injury is specific to lower teeth, especially wisdom teeth sitting on the inferior alveolar or lingual nerve: the NHS notes that temporary tingling or numbness of the lip, chin or tongue can follow, and that permanent change is rare. Upper molar roots occasionally sit so close to the maxillary sinus that removing them opens a small communication between mouth and sinus, which the dentist manages at the time. Jaw stiffness, bruising and a sore corner of the mouth from retraction are common and self-limiting.
Alternatives depend on why the tooth is being removed. For a tooth with a dead or infected nerve but sound structure, root canal treatment, which removes the infected pulp and seals the canals, can keep the tooth. For a broken tooth with enough root remaining, a crown after a post and core may be possible. For teeth loosened by gum disease, periodontal treatment sometimes stabilizes them, though not always. For a symptom-free impacted wisdom tooth, watchful monitoring is a legitimate option; the NHS states that impacted wisdom teeth causing no problems do not normally need removal.
None of these is universally better. Each trades different risks, timelines and future repair needs. Your dentist should be able to explain why extraction was recommended over the alternatives for this specific tooth, and what the replacement options would be afterward, whether that is an implant, a bridge, a denture, or simply leaving the gap when the tooth is a third molar.
What people often get wrong about having a tooth removed
The myths cluster in predictable places, and most of them make recovery harder rather than easier.
“Rinse hard to keep it clean.” The opposite is true for the first day. Vigorous rinsing or spitting is one of the surest ways to lose the clot, and the NHS specifically advises against it in the first 24 hours. Gentle salt-water rinses start the following day.
“The white stuff in the socket means it is infected.” In most cases that pale film is granulation tissue, the early scaffolding of healing. Infection usually announces itself with worsening pain, swelling and sometimes fever, not with a quiet whitish socket.
“Extraction is pulling.” As described above, it is controlled loosening. People who understand this report the pressure sensations as less frightening.
“Antibiotics are always needed.” They are not. Routine antibiotics after a straightforward extraction are not supported by mainstream guidance and contribute to resistance; they are prescribed when there is a specific infection or a medical reason, and that call belongs to the dentist.
“Wisdom teeth always have to come out.” The NHS is clear that symptom-free, well-positioned third molars can be left and monitored.
“Lost teeth cause other teeth to fall out.” Neighboring teeth can drift or tilt into a gap over time, and the opposing tooth can over-erupt, which is a reason to discuss replacement. They do not loosen or fall out because a neighbor was removed.
And a final one: “If it hurt last time, it will hurt this time.” Anesthetic techniques, imaging and the willingness of dentists to pause and re-numb have all improved. A difficult past experience is worth mentioning so the team can plan around it, not a forecast.
Questions to ask your care team before a tooth extraction procedure
A good consultation leaves you knowing the plan and the fallbacks. These are questions that patients who have been through it wish they had asked.
- Why is extraction recommended over root canal treatment, a crown, or monitoring for this particular tooth?
- Will this be a simple or a surgical extraction, and what does that change for me on the day and afterward?
- What anesthesia or sedation do you suggest, and will I need someone to take me home?
- How close are the roots to the nerve or the sinus on my X-ray, and what does that mean for risk?
- Which of my current medicines or supplements should I mention to the prescribing clinician before the appointment, and should any be changed? (Never stop a prescribed medicine on your own.)
- Will I have stitches, are they dissolvable, and do I need a follow-up visit?
- What is your advice on pain relief after the numbness wears off, given my other health conditions?
- How will I recognize a dry socket or an infection, and how do I reach you out of hours?
- When can I return to work, exercise and normal eating?
- What are my options for replacing the tooth, and when is the earliest sensible time to plan that?
Write the answers down or have someone with you; sedation in particular blurs memory of the briefing. If anything in the explanation does not make sense, say so. Dentists would far rather spend five extra minutes on the plan than field a frightened call at midnight about a sensation that was entirely expected.
When to call your doctor or dentist after a tooth extraction
Most recoveries are uneventful, and a sore, swollen jaw for a few days is not a reason for alarm. Certain signs, however, should prompt a same-day call to the dentist, or to an emergency service if the practice is closed and the symptom is severe.
Bleeding that does not slow after you have bitten firmly on fresh gauze for a sustained period, or that fills the socket with bright red blood repeatedly, needs assessment, especially if you take anticoagulants. Severe pain that begins or sharply worsens one to three days after the extraction, particularly with a bad taste or smell, suggests a dry socket, which the Mayo Clinic notes is treatable in the chair but rarely settles well on its own. Swelling that keeps increasing after day three, pus from the socket, a fever, or difficulty opening the mouth wider than before point toward infection.
Call urgently, or go to an emergency department, if swelling spreads toward the eye or down into the neck, if you have difficulty swallowing your own saliva or any difficulty breathing, or if you feel faint or unwell with a high temperature. These are uncommon but need immediate care.
Numbness of the lip, chin or tongue that persists beyond a day after a lower extraction should be reported, not because emergency treatment is needed but because the dentist will want to document and monitor it. The same applies to a sudden sense of air or fluid passing between your mouth and nose after an upper molar is removed.
When in doubt, call. The team that performed the extraction knows exactly what they found in the socket and is best placed to decide whether you need to be seen, and how soon.
Frequently asked questions
Does tooth extraction hurt while it is being done?
With adequate local anesthesia the extraction itself should not be painful, though you will feel firm pressure, vibration and hear clicks or squeaks as the tooth loosens. If anything feels sharp, raise a hand; the dentist can add more anesthetic or change the injection site. Soreness after the numbness fades is expected and usually peaks within the first day or two.
What is the difference between teeth and tooth?
Tooth is the singular and teeth is the irregular plural, the same pattern as foot and feet. A dentist removing one molar performs a tooth extraction; someone having all four wisdom teeth removed has multiple extractions in one visit. The grammar matters slightly in searching: guidance pages on ‘tooth extraction’ and ‘teeth removal’ describe the same procedure.
What are the 32 adult teeth called?
A full adult set has 32 teeth: 8 incisors at the front for cutting, 4 canines (the pointed corner teeth) for tearing, 8 premolars behind them, and 12 molars at the back for grinding, including the 4 third molars known as wisdom teeth. Children have 20 primary teeth with no premolars. Many adults have fewer than 32 because wisdom teeth never develop or are removed.
Which teeth usually decay first?
The back molars tend to decay first, because their chewing surfaces have deep grooves that trap food and are hardest to brush, and because wisdom teeth sit where a toothbrush barely reaches. In young children, the upper front teeth are often affected first when sugary drinks pool around them. Decay location, not just presence, often influences whether a tooth can be restored or needs extraction.
What food kills mouth bacteria?
No food reliably kills mouth bacteria, and claims about specific ‘antibacterial’ foods are not supported by strong evidence. What the evidence does show is that limiting the frequency of sugar, brushing twice daily with a fluoride toothpaste, and cleaning between teeth reduce the acid-producing activity of plaque bacteria. Water and unsweetened dairy are kinder to teeth than sugary or acidic drinks, but they do not sterilize the mouth.
How long does a tooth extraction take?
The NHS notes that removing a wisdom tooth can take anything from a few minutes to around 20 minutes or longer, depending on how impacted it is. A simple extraction of a loose or straightforward tooth is often quicker; a surgical extraction with bone removal takes longer. Numbing time and aftercare instructions are added on top, so the whole appointment is usually longer than the extraction itself.
How long is tooth extraction recovery time?
Soreness and swelling typically improve over the first few days, and the NHS suggests full recovery after wisdom tooth removal can take up to two weeks. The gum generally closes over the socket within about two weeks, while the Cleveland Clinic notes the bone underneath keeps remodeling for several months. Simple extractions tend to sit at the shorter end; surgical ones at the longer end.
What does dry socket after tooth extraction feel like?
Dry socket feels like pain that begins or sharply worsens one to three days after the extraction, often throbbing and radiating toward the ear, eye or temple on the same side, sometimes with a bad taste or smell. The socket may look empty or show whitish bone rather than a dark clot. It is treatable by the dentist with cleaning and a medicated dressing, so it is worth calling promptly.
What is the difference between a simple vs surgical extraction?
A simple extraction removes a tooth that is visible above the gum and intact enough to grip, using elevators and forceps alone. A surgical extraction involves a small incision in the gum and sometimes removal of a thin layer of bone, used when the tooth is broken at the gum line, impacted or has difficult roots. Both use local anesthetic; surgical cases more often include sedation and stitches.
Can I drive home after a tooth extraction?
If you had local anesthetic alone, driving is usually fine once you feel steady, though a numb lip and some soreness can be distracting. If you had any form of sedation, including tablets, inhaled gas or an intravenous line, you will be told not to drive for a set period and to have an adult take you home. Confirm the specific rule for your anesthesia with the team beforehand.
References
- MedlinePlus: Tooth extraction
- Cleveland Clinic: Tooth Extraction
- NHS: Wisdom tooth removal
- NHS: Wisdom tooth removal, recovery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Wisdom Teeth Removal Cost: Simple vs Surgical Extraction Pricing
Surgical wisdom tooth extraction sits at EUR 130-250 per tooth in our guide range for international patients, compared with roughly GBP 250-600 in the…

How Halitosis Is Diagnosed: Breath Assessment, Gum Checks and Finding the Source
Halitosis diagnosis starts with a clinician smelling the breath from the mouth and nose separately and rating it on a standard scale, then examining…
Can a Sinus Infection Cause Tooth Pain? Why It Happens and How to Tell It from a Dental Problem
Yes. A sinus infection can cause tooth pain, usually a dull ache across several upper back teeth. Those roots sit just beneath the floor…
Mouth Care After Wisdom Teeth Removal: Gentle Rinsing, Brushing and Keeping the Socket Clean
Mouth care after wisdom teeth removal means protecting the blood clot in each socket for the first 24 hours, then gently brushing the other…
What an Orofacial Pain Treatment Plan Combines: Dental, Physiotherapy and Pain-Management Care
An orofacial pain treatment plan usually combines three strands: dental care to rule out tooth, gum and bite causes and sometimes provide a custom…

How Long Does a Root Canal Take? Visit by Visit, Tooth by Tooth
Most root canals take 30 to 90 minutes of chair time per visit, and many are finished in a single appointment. Front teeth, with…