

What Injection Treatment for Diabetic Retinopathy Usually Achieves and Why It Continues

Key Takeaways
- Anti-VEGF injections work by blocking the growth signal that makes damaged retinal vessels leak and sprout, so swelling drains and new vessels regress while the medicine is active.
- The medicine clears from the eye over weeks but the diabetic retina keeps producing the signal, which is why NHS and NEI guidance describe monthly treatment at first and then intervals set by scans rather than by calendar.
- Recovery from each injection takes a day or two for the eye surface, while the retina's response is judged on imaging roughly a month later.
- A dry scan and improved vision mean the treatment is working, not that it is finished; most people need ongoing treatment, usually heaviest in the first year.
- Laser treats proliferative disease with fewer visits but sacrifices some side vision, while injections preserve more of the visual field at the cost of a long clinic relationship.
- Worsening pain, falling vision, spreading redness or light sensitivity in the week after an injection are the signs of rare but urgent complications and warrant a same-day call.
Injection treatment for diabetic retinopathy usually aims to dry swelling in the central retina and shrink abnormal new blood vessels, which can stabilize sight and sometimes improve it, but it does not remove the underlying diabetes. Treatment is often given monthly at first, then spaced out as the retina settles. Many people continue intermittently for years because each injection wears off within weeks while the disease process persists.
The appointment letter said forty minutes. The man in the waiting room had budgeted the whole afternoon, because the words he kept turning over were not about this visit at all. They were about the next one, and the one after that. He had typed “diabetic retinopathy injections how long” into his phone the night before and found a dozen forums and no straight answer.
His question is the right one. An injection into the eye is quick, oddly undramatic, and far less uncomfortable than most people fear. What unsettles patients is the open-endedness: the sense of signing up for a treatment with no obvious finish line.
This explainer takes that worry seriously. It covers what the injections do inside the retina, what a visit and the days after actually feel like, why the schedule stretches and shrinks, and why continuing is usually a sign the plan is working rather than failing.
What is happening inside the eye in diabetic retinopathy?
The retina is the light-sensing layer at the back of the eye, thinner than a credit card and fed by some of the smallest blood vessels in the body. Years of raised blood glucose damage those vessel walls. They leak, they close off, and parts of the retina start to run short of oxygen.
Two things follow, and both can steal sight in different ways. The first is diabetic macular edema, which means fluid pooling in the macula, the central patch of retina responsible for reading, faces and fine detail. Swelling there blurs and distorts central vision even when the rest of the eye looks healthy. The second is proliferative diabetic retinopathy, in which the oxygen-starved retina releases a growth signal called VEGF (vascular endothelial growth factor) that prompts fragile new vessels to sprout. These new vessels bleed into the gel of the eye and can pull on the retina as scar tissue forms. Patient guidance from the National Eye Institute describes diabetic retinopathy as the most common cause of vision loss among people with diabetes, and notes that risk rises the longer someone has lived with the condition.
Early retinopathy often causes no symptoms at all. That is why screening exists, and why many people first hear the word from a photograph rather than from a change they noticed. By the time vision blurs, the process has usually been underway for a long time. Understanding that timeline matters, because it explains the central puzzle of treatment: injections target the swelling and the vessel growth, but they cannot reach back and remove the years of glucose exposure that caused them.
How do eye injections for diabetic retinopathy actually work?
Most injections given for diabetic retinopathy belong to a class called anti-VEGF medicines. They are proteins designed to bind VEGF, the growth signal described above, and switch it off locally. Less VEGF means less leakage from damaged vessels, so fluid in the macula drains and the swelling subsides. It also means the abnormal new vessels of proliferative disease lose their chemical encouragement and tend to regress.
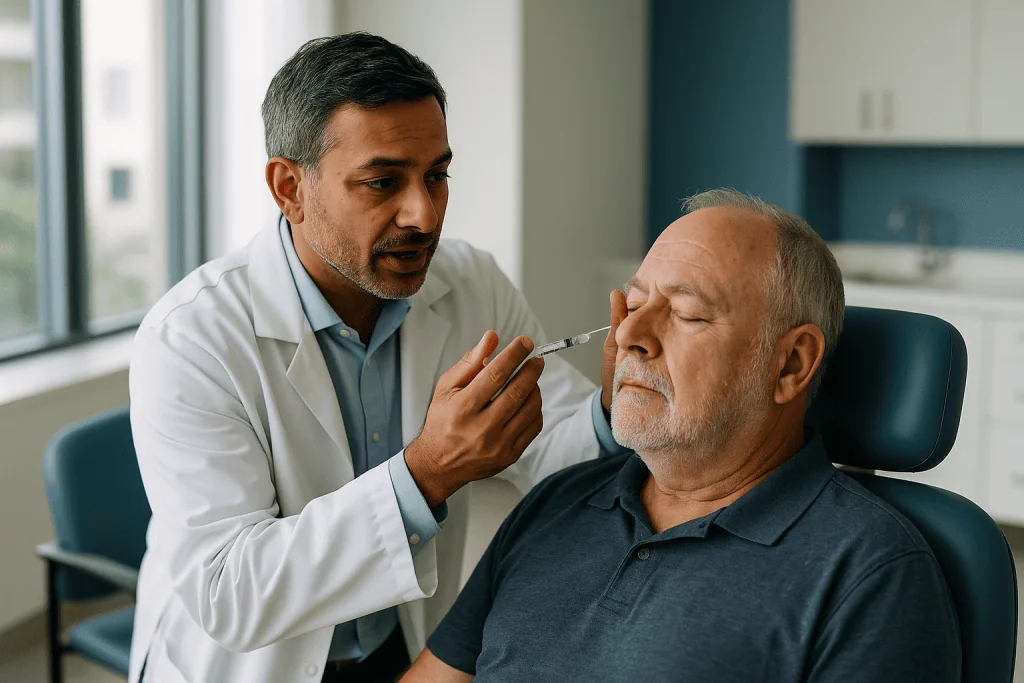
The medicine is placed in the vitreous, the clear gel filling the eye, so that it sits beside the retina rather than circulating through the whole body. Over several weeks the eye clears it. That clearance is the hinge on which the entire treatment schedule turns. The drug fades; the diabetic retina, still exposed to glucose, begins producing VEGF again; and swelling or vessel growth can return. Mayo Clinic’s patient guidance puts it plainly: treatment slows or stops progression, but because diabetes is lifelong, further retinal damage remains possible.
A second class, corticosteroid implants, works differently. Steroids damp down several inflammatory pathways at once rather than one signal, and some are released slowly over months. They carry their own trade-offs, chiefly cataract formation and raised eye pressure, which is why clinicians weigh them case by case rather than reaching for them first. The NHS and Cleveland Clinic both describe anti-VEGF injections as the usual first choice for macular edema, with steroids and laser as alternatives or additions.
What none of these medicines do is repair tissue that has already died. A retina that has lost cells to years of poor circulation will not regrow them. The realistic goal is to protect what remains and to recover vision that was lost to swelling rather than to scarring.
What happens at an injection visit, step by step
People picture a needle approaching an open eye and assume the worst. The reality is more clinical and far shorter than the anxiety that precedes it.
A nurse or technician checks vision on the chart first, then usually measures eye pressure and photographs or scans the retina with optical coherence tomography, a painless imaging method that maps retinal thickness in cross-section. Those scans are how the team decides whether today’s injection goes ahead and how soon the next one should follow.
Anesthetic drops numb the surface of the eye. An antiseptic solution, typically iodine-based, is applied to the eyelids and the eye itself to reduce infection risk; this stings briefly and is the part many patients find most noticeable. A small speculum holds the lids apart so you cannot blink at the wrong moment. The clinician asks you to look in a particular direction, and the injection is given through the white of the eye a few millimeters from the colored iris, well away from the lens and the retina itself.
The NHS describes the whole procedure as taking only a few minutes. Most people report pressure rather than pain, and a dark swirl or a few floating specks may appear immediately as the medicine mixes into the vitreous. The eye is then checked once more, sometimes with a quick confirmation that you can see hand movements, and the speculum comes out.
You will not be allowed to drive yourself home, partly because of the dilating drops and partly because that eye will be blurry for hours. Many clinics ask you to bring someone, or to arrange transport. The visit that felt like a mountain in advance is, for most, remembered afterward mainly for the sting of the antiseptic and the length of the wait.
Do eye injections hurt? What patients honestly report
The honest answer is: usually not much, but it is rarely nothing. Anesthetic drops numb the surface effectively, so the needle itself tends to register as a brief pressure or a dull push rather than a sharp pain. The NHS patient guidance notes that the eye is numbed beforehand and that discomfort is generally mild.

Three sensations account for most complaints, and knowing them in advance takes the edge off each.
- The antiseptic. Iodine solution on the eye surface stings and can leave a gritty, sandpaper feeling for the rest of the day as it dries the tear film. Preservative-free lubricating drops, if your clinic recommends them, often help.
- The speculum. Having the lids held open feels strange, and some people find the instinct to blink more distressing than the injection.
- The afterward. A mild ache, a red patch on the white of the eye where a tiny surface vessel bled, and floaters that drift for a day or two are all common and expected.
Pain that builds over hours rather than fading is not expected, and it belongs in the red-flag section below. A sharp, deep ache with worsening vision and light sensitivity in the day or two after an injection needs same-day assessment.
Anxiety amplifies every one of these sensations, which is why experienced teams talk patients through each step. Some people ask for a hand to hold; some prefer counting; some simply ask the clinician to narrate. None of these are unusual requests. Many patients who dreaded their first injection describe the second as almost routine, not because it hurt less in any measurable way, but because the unknown had become known.
Diabetic retinopathy injections: how long does recovery take after each visit?
Recovery from a single injection is measured in hours and days, not weeks. That distinction surprises people who equate “eye procedure” with the longer convalescence of cataract or retinal surgery.
In the first few hours, vision in the treated eye is blurred by the dilating drops, the antiseptic and the medicine itself. Floaters are common, and a small red blotch on the white of the eye may appear where the needle passed. Mayo Clinic’s guidance describes temporary blurring and irritation as the usual aftermath. Reading with that eye is difficult the same evening; most people manage with the other eye or simply rest.
By the next morning the surface irritation has usually eased, though a gritty feeling can linger for a day or two as the tear film recovers from the iodine. The red blotch, if present, fades over one to two weeks in the same way a bruise does. Floaters settle as the medicine disperses. Most people return to desk work, cooking and ordinary activity within a day, with the common-sense exceptions covered in the next section.
The medicine’s effect on the retina follows a slower clock. Swelling in the macula typically begins to shrink within days, and the team will usually look for the fullest effect at the next scan, often a month later. Vision can lag behind the anatomy: a retina that has dried on the scan may take weeks longer to deliver a clearer chart reading, and in some eyes the improvement is modest because long-standing swelling has already damaged cells.
So when people ask how long recovery takes, there are really two answers. The eye itself recovers in a day or two. The retina’s response unfolds over weeks, and it is that response, not the surface healing, that decides what happens next.
After an eye injection, what should you avoid?
The precautions are fewer than most people expect, and nearly all of them exist for one reason: the needle creates a tiny, self-sealing opening in the eye wall, and for the first day or so the aim is to keep bacteria away from it.
The following points reflect common guidance from the NHS and major eye centers; your own clinic’s instructions take priority if they differ.
- Avoid rubbing or pressing on the eye, especially while the surface is numb and you cannot judge how hard you are touching it.
- Keep water out of the eye for the first day or two: no swimming, no hot tubs, and care when washing your face or hair.
- Skip eye makeup on the treated side until the surface feels normal again, usually a few days.
- Do not drive on the day of the injection. Dilating drops and blur make it unsafe, and in many places illegal.
- Dusty, gritty environments such as gardening or building work are best left for a couple of days.
Ordinary life otherwise carries on. Walking, light exercise, screens and reading with the other eye are fine. There is no need to keep the eye closed, to wear a patch unless the clinic provides one, or to sleep upright.
Two things are often forgotten. First, if you use glaucoma drops or other prescribed eye drops, ask the team when to resume them rather than assuming; most are restarted the same day, but the instruction should come from them. Second, keep the follow-up date. The precautions after an injection protect against a rare complication; the follow-up protects against the common one, which is simply that the disease creeps back while nobody is watching.
Diabetic retinopathy injections: how long does treatment usually continue?
Here is the question behind every other question, and it deserves an honest shape rather than a number. Patient guidance from the NHS and the National Eye Institute describes the same general pattern: injections are usually given monthly at the start, continued until the retina and vision stabilize, and then either spaced out, paused, or stopped, with treatment resumed if swelling or new vessels return.
That pattern has a logic. The early monthly phase is sometimes called loading, and its purpose is to drive VEGF down hard enough to dry the macula and let the retina show what it can recover. Once scans are stable, clinicians use one of two broad strategies. In a treat-and-extend approach, the gap between visits is lengthened step by step as long as the retina stays dry, and shortened again if fluid reappears. In an as-needed approach, the person is monitored at regular intervals and treated only when the scan shows activity. Both approaches lean on the imaging rather than on a fixed calendar.
How long does that add up to? For many people, the heaviest treatment falls in the first year, and the frequency tends to drop in subsequent years as the retina quietens. Some eyes settle into long gaps or stop needing injections for extended stretches. Others, particularly where blood glucose or blood pressure remain high, need treatment that continues for years. Cleveland Clinic’s guidance makes the point that anti-VEGF treatment is ongoing for most patients rather than a one-off course.
No clinician can tell you at the first visit how many months you will need, because the answer is written in your scans as they accumulate. What they can tell you is that the schedule is a response to your retina, not a sentence handed down in advance.
Why injections continue even when vision has improved
The most common moment of frustration arrives around the time things go well. Vision has cleared, the scan is flat, and the clinician says: see you next month. Why keep going?
Because the improvement is evidence that the medicine is working, not evidence that the disease has gone. Anti-VEGF drugs are cleared from the eye over weeks. The retina beneath has not changed its nature; it is still a diabetic retina, still prone to leak and to signal for new vessels. Stop too early and, in many eyes, the fluid returns, and each return risks a little more permanent damage. Mayo Clinic’s guidance is direct on this point: treatment slows or halts progression, but because diabetes is lifelong, future damage and vision loss remain possible.
Think of it less like a course of antibiotics and more like managing blood pressure. The reading looks normal because the treatment is active. The team’s task is to find the longest interval that keeps it that way, which is exactly what the extending schedule is designed to discover. Each time a gap is stretched and the scan stays dry, you have learned something about your own eye. Each time fluid reappears, you have found your current limit, and the gap narrows a little.
Two things shift the trajectory in your favor over time. Improved glucose, blood pressure and lipid control reduces the underlying drive, and the retina itself can quieten after a sustained dry period. Some people reach long maintenance intervals; some pause altogether for months or years under monitoring. Continuing when things look good is not the system failing to notice your progress. It is the system protecting it.
Who are the injections usually for, and who is usually asked to wait?
Injections are not offered to everyone with retinopathy, and being asked to wait is often the better news. The decision rests on which stage of disease the scans and examination show.
Anti-VEGF injections are generally considered when there is diabetic macular edema affecting the center of the macula, particularly when vision has already dropped. They are also used for proliferative retinopathy, either alone or alongside laser, and before some vitrectomy operations to shrink vessels that would otherwise bleed during surgery. The NHS treatment guidance frames injections, laser and surgery as options matched to stage rather than as a ladder every patient climbs.
People with background or non-proliferative retinopathy, where vessels leak slightly but the macula is not swollen and no new vessels have formed, are usually monitored rather than treated. The same applies to mild macular thickening that spares the center and leaves vision unaffected. For them the active treatment is upstream: glucose, blood pressure, cholesterol, and keeping screening appointments. The CDC notes that regular dilated eye examinations are the main way early retinopathy is caught before it threatens sight.
Some situations call for caution or a different route. An active infection in or around the eye delays an injection. Very high eye pressure, certain recent strokes or heart events, and pregnancy all prompt a conversation about timing and alternatives, since anti-VEGF agents can enter the bloodstream in small amounts. People who cannot attend frequent visits may be steered toward laser, which requires fewer appointments, or toward a longer-acting steroid implant.
Being told to wait is uncomfortable when the diagnosis is new and the instinct is to act. Waiting under surveillance, with a scan date in the diary, is itself a plan. The team is choosing the moment when treatment will help rather than merely reassure.
Injections, laser or surgery: how the options compare
Most people with sight-threatening retinopathy are offered one of three approaches, and many will receive more than one over the years. The table summarizes what each does, drawing on guidance from the NHS, Mayo Clinic and Cleveland Clinic. It is a map, not a menu; the choice belongs to the treating team.
| Approach | What it does | Typical use | Main trade-offs |
|---|---|---|---|
| Anti-VEGF injections | Block the growth signal driving leakage and new vessels | Center-involving macular edema; proliferative disease | Repeated visits; small infection risk per injection; effect wears off |
| Steroid implants | Suppress several inflammatory pathways; release slowly | Macular edema not responding to anti-VEGF, or where frequent visits are hard | Cataract progression; raised eye pressure needing drops or monitoring |
| Laser (panretinal) | Treats oxygen-starved peripheral retina so it stops signaling for new vessels | Proliferative retinopathy | Usually fewer sessions; can reduce peripheral and night vision |
| Laser (focal) | Seals specific leaking spots away from the center | Macular edema sparing the center | Does not improve vision much; aims to stabilize |
| Vitrectomy surgery | Removes blood-filled gel and scar tissue; relieves traction | Persistent bleeding; retinal detachment from scarring | Operation with recovery period; cataract and other surgical risks |
Two patterns are worth noticing. Laser trades a small, permanent sacrifice of side vision for a durable effect with fewer visits; injections preserve more of the visual field but ask for a long relationship with the clinic. Neither is simply better. Someone who travels for work, lives far from the hospital or struggles to arrange transport may reasonably be offered laser earlier; someone whose central vision is the priority may lean toward injections. Surgery sits at the end of the row not because it is a failure but because it addresses complications the other two cannot.
Anti-VEGF injection side effects and real risks
Side effects divide neatly into the common and harmless, the uncommon and serious, and the theoretical. Clear thinking about each makes the treatment easier to live with.
Common and harmless covers the sting of antiseptic, a gritty surface for a day, a red patch on the white of the eye, floaters, and a mild ache. These are listed in NHS and Mayo Clinic guidance as expected and self-limiting. A brief rise in eye pressure right after the injection is also common; the team checks for it and it usually settles within hours.
Uncommon and serious is dominated by one event: infection inside the eye, called endophthalmitis. It is rare, which is why antiseptic preparation is so meticulous, but it is sight-threatening and time-critical. The warning signs are worsening pain, increasing redness, falling vision and sensitivity to light, usually within the first week. Other rare complications include retinal tear or detachment, bleeding inside the eye, and damage to the lens if the needle path is wrong. Cleveland Clinic’s guidance lists these as unusual but recognized risks.
Theoretical concerns relate to the small amount of medicine that reaches the bloodstream. Because VEGF also plays a role in blood vessels elsewhere, researchers have looked at whether anti-VEGF injections raise the risk of stroke or heart attack. The evidence has not shown a clear increase in people with retinopathy, but clinicians remain cautious in those with a very recent cardiovascular event, and the question is worth raising if that applies to you.
Steroid implants add two predictable effects: cataract progression in most eyes that still have their natural lens, and raised eye pressure in a meaningful minority, sometimes requiring pressure-lowering drops. These are reasons they are chosen selectively rather than reasons to fear them.
Can diabetic retinopathy be reversed, and what role does blood sugar play?
The word people want is “reversed,” and the honest answer has two halves. Swelling can reverse. Scarring cannot.
Fluid in the macula is a reversible state. When injections drain it, the retinal layers can settle back into position and the vision lost to distortion can return, sometimes substantially. New vessels can also regress, and bleeding can clear. In that sense, treatment does more than hold the line. What it cannot do is replace photoreceptors or nerve cells that died during long periods of poor blood supply, or undo scar tissue that has already contracted. This is why outcomes differ so widely between two people on the same treatment: the eye with recent swelling and intact cells has more to recover than the eye that waited years.
Blood glucose, blood pressure and cholesterol are not background advice here. They are the upstream half of the treatment. The CDC’s guidance on diabetes and vision loss emphasizes that managing these three, along with not smoking, lowers the risk of retinopathy developing and slows it once present. Lower glucose exposure means less vessel damage and less VEGF production, which in practice can mean longer gaps between injections and a quieter retina over time.
One counterintuitive point deserves mention. Rapid, large improvements in glucose control, for example after starting a new regimen or after bariatric surgery, can temporarily worsen retinopathy before it improves. This is well recognized and is a reason eye teams like to know when your diabetes management changes significantly, so they can increase monitoring for a while. It is not a reason to avoid improving control; the long-term benefit is clear. It is a reason for the eye team and the diabetes team to talk to each other, with you in the middle.
What people often get wrong about eye injections
Myths cluster around this treatment because it sounds alarming and because so much of what happens is invisible to the patient. Five misunderstandings come up again and again.
“The needle goes into the pupil.” It does not. The injection passes through the white of the eye, several millimeters from the iris, into the gel behind the lens. You are asked to look away from the needle, and most people see nothing but a shadow.
“If it worked, I would be finished.” The opposite is closer to the truth. A dry scan and better vision mean the medicine is doing its job. The medicine wears off; the diabetes does not. Continuing is how the gain is kept.
“Injections are a sign of failure.” Being offered them means the team has found something treatable at a stage where treatment can help. Many people with diabetes never reach this stage; those who do and are treated promptly generally keep more sight than those who are not. Mayo Clinic and NHS guidance both frame early treatment as the point of screening.
“I can stop once my sugar is controlled.” Better control reduces the drive, sometimes dramatically, but the eye that has already developed retinopathy needs monitoring and often continued treatment while it quietens. Decisions to pause belong to the retina team, informed by scans.
“The treatment fixes my eyesight.” It aims to protect and, where possible, restore vision lost to swelling. Cells already lost do not return, and glasses, lighting and low-vision support may still be part of the picture. Expecting the retina of twenty years ago sets up disappointment; expecting a stable, usable retina for the years ahead is realistic and, for most, achievable.
Questions to ask your care team
Appointments are short and dilated eyes make note-taking hard. Bringing a few written questions, and someone to hear the answers, changes the quality of the conversation. These are the ones that tend to matter most, grouped by what you are really trying to find out.
About your own eye:
- Which stage of retinopathy do I have, and is the macula involved?
- What does my scan show today compared with last time?
- How much of my vision loss is from swelling that might recover, and how much from permanent change?
About the plan:
- Are you using a treat-and-extend or an as-needed approach, and what would make you lengthen or shorten the gap?
- What would prompt you to consider laser, a steroid implant or surgery instead of, or alongside, injections?
- If I miss or delay an appointment, how much does it matter, and whom do I call to rebook?
About living with it:
- What exactly should I do in the first two days after each injection?
- Which symptoms mean I should contact you the same day?
- Should my diabetes team know about any change in my eye treatment, and how will you share results?
About the bigger picture:
- What targets for glucose, blood pressure and cholesterol would most help my eyes?
- Is there anything about my heart or stroke history that affects which medicine you choose?
- Would a referral for low-vision support or driving assessment be useful at this stage?
A good team welcomes these. The answers will be specific to you in ways no article can be, and hearing them aloud often does more for the open-ended dread than any statistic.
When to call your doctor
Most injections are followed by nothing more than a scratchy evening and a few floaters. A small number are followed by something that needs attention within hours, and the difference is usually clear if you know what to look for.
Contact your eye clinic or emergency eye service the same day, or go to an emergency department out of hours, if you notice any of the following in the days after an injection:
- Pain in the eye that is increasing rather than easing, especially a deep ache.
- Vision that is getting worse rather than slowly clearing.
- Redness that is spreading, or new sensitivity to light.
- A sudden shower of new floaters, flashes of light, or a shadow or curtain across part of your vision.
- Yellow or sticky discharge, or swelling of the lids.
These can indicate infection inside the eye, a retinal tear or detachment, or a sharp rise in eye pressure. All are uncommon and all are treatable, but the window matters, and no clinic would rather you waited to see.
Outside the injection period, the same rules apply to the underlying disease. A sudden drop in vision, new floaters or a dark patch in one eye can mean bleeding from new vessels and should be assessed promptly rather than left for the next scheduled scan. MedlinePlus and NHS guidance both advise urgent review for sudden vision change in anyone with diabetes.
Do not treat this list as a checklist for diagnosing yourself. Treat it as permission to call. Clinics expect these phone calls, and a conversation that ends with “that sounds like the antiseptic sting, see you at your next visit” is a good outcome, not a wasted one. Every decision about what happens next, from whether to treat today to whether to change approach, rests with the team that can see your retina.
Frequently asked questions
How long does it take to recover from a diabetic retinopathy injection?
Most people feel close to normal within a day or two. The treated eye is blurred for several hours by drops and the medicine, and a gritty or scratchy feeling from the antiseptic can linger for a day. A red patch on the white of the eye, if it appears, fades over one to two weeks. The retina’s response takes longer and is usually assessed on a scan about a month later.
What shouldn't you do after an eye injection?
Avoid rubbing the eye, getting water in it from swimming or showering directly, wearing eye makeup, and driving on the day of treatment. Dusty activities such as gardening are best delayed for a couple of days. These precautions protect the tiny needle opening while it seals. Ordinary walking, reading with the other eye and screen use are fine. Follow your own clinic’s instructions where they differ.
How many months do I have to get shots for diabetic retinopathy?
There is no fixed number, because the schedule follows your scans. NHS and National Eye Institute guidance describe monthly injections at the start until the retina stabilizes, then spacing out, pausing, or stopping, with treatment resumed if swelling or new vessels return. For many people treatment is heaviest in the first year and lighter afterward, but some need intermittent injections for years.
How painful are eye injections for diabetic retinopathy?
Usually far less than feared. Anesthetic drops numb the surface, so the injection itself tends to feel like brief pressure rather than sharp pain. The most noticeable discomfort is the sting of the iodine antiseptic and a gritty feeling afterward. A mild ache for a few hours is common. Pain that increases over the following day is not expected and should be reported the same day.
How many eye injections for diabetic retinopathy are typical over time?
Frequency depends on the stage of disease and how the retina responds. Guidance from Cleveland Clinic and Mayo Clinic describes anti-VEGF treatment as ongoing rather than a single course, with frequent visits initially and longer gaps once scans are stable. The team uses imaging to find the longest interval that keeps the macula dry, so the total varies widely from person to person.
What are the main anti-VEGF injection side effects?
Common effects are temporary: surface irritation, a red spot on the white of the eye, floaters and mild ache. A brief rise in eye pressure is usual and checked before you leave. Rare but serious risks include infection inside the eye, retinal tear or detachment, and bleeding, which is why worsening pain, redness or vision loss in the following week needs urgent review.
Why do the injections continue if my vision has improved?
Because improvement shows the medicine is working, not that the disease has gone. Anti-VEGF drugs clear from the eye within weeks, while the diabetic retina continues to produce the growth signal. Stopping early often allows fluid to return and risks further permanent damage. The team extends the gap step by step as long as the scan stays dry, which is how your longest safe interval is found.
Can diabetic retinopathy be reversed with injections?
Partly. Swelling in the macula and abnormal new vessels can regress with treatment, and vision lost to swelling can recover. Retinal cells that have already died and scar tissue that has formed do not return. This is why outcomes differ between people and why early treatment matters. Good glucose, blood pressure and cholesterol control supports the retina’s recovery and can lengthen the gaps between injections.
Is laser or injection better for diabetic retinopathy?
Neither is better in general; they suit different stages and circumstances. Injections are usually first choice for center-involving macular edema and preserve more side vision. Laser is a long-standing treatment for proliferative disease, needs fewer visits, but can reduce peripheral and night vision. Many people receive both over time. The treating team matches the approach to the scan findings and to what is practical for you.
Do eye injections hurt more the second time?
Most people report the opposite. The physical sensation is similar each time, but anxiety is a large part of the first experience, and knowing what each step feels like makes later visits easier. The antiseptic sting and a few hours of blur remain predictable. If any injection is markedly more painful than previous ones, or the pain builds afterward, tell the clinic rather than assuming it is normal.
References
- NHS: Diabetic retinopathy, Treatment
- NIH National Eye Institute: Diabetic Retinopathy
- Cleveland Clinic: Diabetic Retinopathy
- MedlinePlus: Diabetic Eye Problems
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is PRK or SMILE Better for You? No Flap in Either, Very Different Recoveries
Neither PRK nor SMILE is better for everyone. Both reshape the cornea without a LASIK-style flap, but PRK removes the eye's surface layer and…

How Trabeculectomy Lowers Eye Pressure: The Tiny Flap, the Bleb and the Operating Room Steps
Trabeculectomy lowers eye pressure by creating a new, controlled exit for the fluid inside the eye. The surgeon lifts a tiny trapdoor in the…

When a Chalazion Keeps Coming Back: Repeat Treatment and Why a Biopsy May Be Advised
A recurring chalazion is an eyelid oil-gland blockage that returns after it has settled or been drained. Repeat episodes are usually linked to ongoing…

When Does a Damaged Cornea Need Surgical Repair? Injuries, Infections and Thinning Explained
A damaged cornea needs surgical repair when the injury, infection or thinning threatens the eye's structure or cannot heal with medicines alone: a full-thickness…
Pain, Light Sensitivity or Blurred Vision With Pink Eye: Why These Need Same-Day Review
Most pink eye is mild conjunctivitis that settles on its own, but eye pain, sensitivity to light, or blurred vision that does not clear…

Oculoplastic Surgery Recovery: Cold Compresses, Sleeping Propped Up and Bruise Timelines
Oculoplastic surgery recovery, including eyelid procedures such as blepharoplasty, usually brings the most swelling and bruising in the first two to three days, with…