

What Periodontal Measurements Reveal About Gum Recession: Pocket Depths and Bone Support

Key Takeaways
- Clinical attachment loss, the sum of recession plus pocket depth measured from the enamel edge, tracks lost support more reliably than pocket depth alone.
- Mayo Clinic describes healthy probing depths as 1 to 3 millimeters, with pockets deeper than 4 millimeters raising the possibility of periodontitis and those over 5 millimeters hard to clean at home.
- A shallow pocket beside visible recession can hide substantial attachment loss, because the pocket reads as shallow only after the gum has already gone.
- X-rays reveal bone loss between teeth but are poor at showing missing bone on the cheek and tongue surfaces, which is exactly where brushing-related recession tends to occur.
- Recession over healthy, non-bleeding pockets usually has a mechanical or anatomical cause such as hard brushing or thin tissue, not infection, and is managed differently.
- Receded gum tissue does not regrow on its own; stabilizing the cause stops further loss, and only surgical grafting can move the margin back in suitable defects.
Periodontal measurements translate gum recession into numbers a dental team can track. A probe measures pocket depth, the gap between gum and tooth, and recession, the exposed root above the gum line. Added together they give clinical attachment loss, the clearest indicator of lost support. X-rays confirm how much bone remains. Shallow pockets with recession suggest mechanical causes; deep pockets with bleeding suggest periodontitis.
The hygienist is calling out numbers in a steady rhythm: “three, two, three… four, five, four.” You are flat on your back with a mirror in your mouth, and somewhere around the lower front teeth the voice pauses. Someone writes something down. Nobody explains what just happened, and you leave with a vague sense that your gums are being graded.
That little ritual is the heart of how periodontal measurements and gum recession are assessed. Each number is a millimeter, and each millimeter tells a story about where your gum sits, how firmly it still attaches to the tooth, and how much bone remains underneath to hold everything in place.
This explainer walks through what those numbers measure, why the single most useful figure is one most patients never hear, how X-rays fill in the part a probe cannot reach, and what the whole chart means for the choices your dental team may lay out for you.
Why do periodontal measurements matter for gum recession?
Gum recession is something you can see: a tooth that looks longer than its neighbor, a notch of yellowish root where pink tissue used to be. What you cannot see is whether that recession is a cosmetic shift in soft tissue or the visible edge of a deeper loss of support. Periodontal measurements are how a dental team tells those two stories apart.
Periodontal simply means “around the tooth.” The structures involved are the gum, a ligament that tethers the root to bone, and the jawbone itself. Periodontitis, the inflammatory disease that destroys these structures, is common: the National Institute of Dental and Craniofacial Research reports that it affects nearly half of adults aged 30 and older in the United States, and the proportion rises with age. Recession can accompany periodontitis, but it can also appear in a mouth with no infection at all.
Measurements settle the question because they capture three different things at once. Pocket depth describes the space between gum and tooth. Recession describes how far the gum margin has slipped from its original position. Bone levels, read from X-rays, describe what still anchors the tooth. A patient with 2 millimeters of recession and shallow, healthy pockets is in a very different situation from a patient with the same recession plus 6-millimeter pockets that bleed. The gum looks similar; the prognosis does not.
There is one more reason the numbers matter. Recession rarely announces itself with pain. Sensitivity to cold may be the only symptom, and periodontitis is often painless until late. Measurements taken at regular intervals catch change before you would ever notice it in the mirror, which is why the same tedious chart is repeated at visits years apart.
How is gingival recession measured?
Gingival recession is measured from a landmark that does not move: the cementoenamel junction, usually shortened to CEJ. This is the line where the enamel of the crown meets the cementum, the thin covering of the root. In health, the gum margin sits a short distance above the CEJ, hiding it. When recession occurs, the CEJ becomes visible and the clinician measures the distance from that line down to where the gum edge now rests.
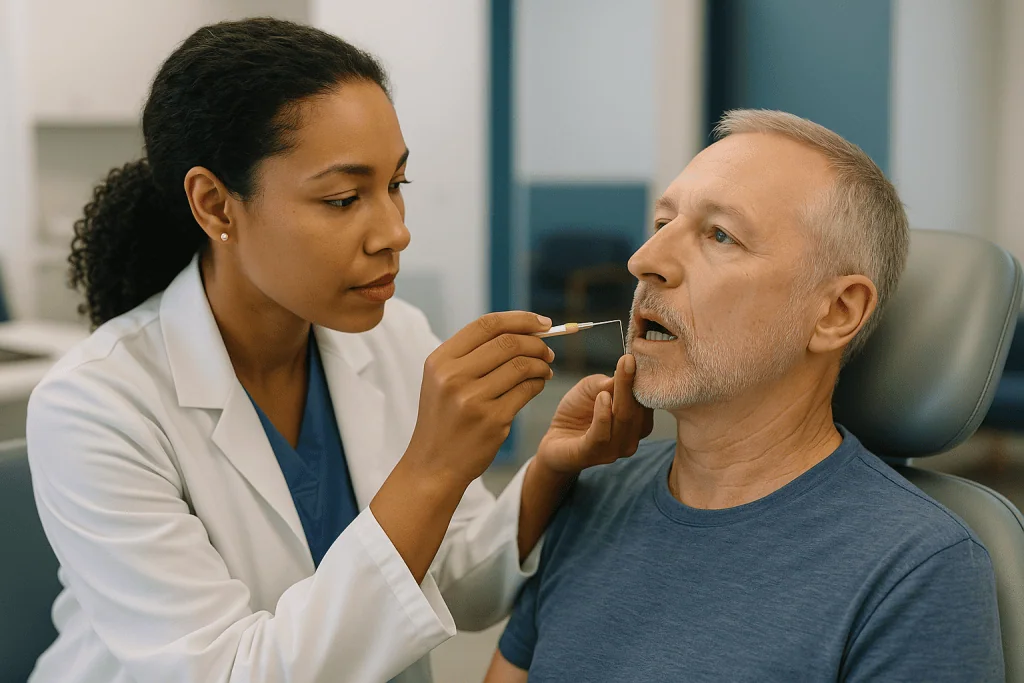
The tool is a periodontal probe, a slim, blunt-tipped instrument marked in millimeters like a tiny ruler. The clinician rests the tip at the CEJ, reads the mark level with the gum margin, and records the number. One or two millimeters is mild; recession reaching several millimeters toward the root tip is more significant because more root surface is exposed to decay, wear and temperature.
Recession is not measured at a single spot. The width matters as well as the depth, since a narrow V-shaped notch behaves differently from a broad band of exposed root. The team also looks at the tissue beside the recession: whether there is a band of firm, pale “attached” gum below the defect or whether the margin runs straight into the loose, darker lining of the lip and cheek. Thin tissue with little attached gum is more vulnerable to further loss.
Where the CEJ has been worn away or covered by a filling, the clinician estimates its position from the neighboring teeth, which is one reason recession measurements carry a small margin of error. Photographs and study models are sometimes added so that a change of a millimeter can be checked against an earlier image rather than against memory. MedlinePlus notes that receding gums are themselves a common sign that periodontal disease should be checked for, so the measurement is usually paired with probing of the pocket beneath.
What do gum probe numbers mean?
The numbers called out during charting are probing depths. The probe slides gently into the sulcus, the natural crevice between tooth and gum, until it meets resistance from the attached tissue. The distance from the gum margin to that stopping point is the pocket depth, taken at six points around every tooth: three on the cheek side and three on the tongue side.
Mayo Clinic describes healthy pocket depth as usually between 1 and 3 millimeters. Pockets deeper than 4 millimeters may indicate periodontitis, and pockets deeper than 5 millimeters are difficult to clean well at home, which is why they tend to progress without professional help.
| Probing depth | What it usually suggests | Typical next step |
|---|---|---|
| 1–3 mm, no bleeding | Healthy attachment | Routine care and recall |
| 1–3 mm with bleeding | Gingivitis: inflammation without bone loss | Improved home care, professional cleaning |
| 4–5 mm | Early to moderate periodontitis is possible | Full charting, X-rays, deeper cleaning as advised |
| 6 mm or more | Advanced loss of attachment likely | Specialist assessment of options |
Bleeding on probing is recorded alongside depth, because a 4-millimeter pocket that bleeds is inflamed and active, while a 4-millimeter pocket that stays dry may be stable. The chart may also note suppuration (pus), furcation involvement, where the probe slips between the roots of a multi-rooted tooth, and mobility, graded by how far the tooth can be rocked.
One caveat matters for anyone with recession. Pocket depth alone can be misleading: when the gum has receded, the pocket may read as shallow precisely because tissue has already been lost. That is why the next number is the one to ask about.
What is clinical attachment loss, and why is it the number that matters most?
Clinical attachment loss, or CAL, is the distance from the CEJ to the bottom of the pocket. It combines the two measurements already taken: recession, from CEJ to gum margin, plus probing depth, from gum margin to pocket base. If the gum has receded 2 millimeters and the pocket is 3 millimeters deep, attachment loss is 5 millimeters. The gum itself may look only mildly short, yet the tooth has lost 5 millimeters of the ligament that once held it.

This is the figure that most faithfully tracks disease over time, because it is anchored to a fixed landmark rather than to a gum edge that can swell or shrink. A pocket can appear to “improve” from 5 to 3 millimeters after treatment simply because the gum shrank back as inflammation settled. Attachment loss will not change in that scenario, and that honesty is exactly what a clinician wants when deciding whether a tooth is stable.
Attachment loss also explains why two common patterns feel so different. In the first, recession is present but pockets are shallow and there is no bleeding: attachment loss equals the recession and nothing more, and the cause is usually mechanical, such as scrubbing with a hard brush or thin tissue over a prominent root. In the second, recession is modest but pockets are deep and bleed: attachment loss is large, and the explanation is inflammatory periodontitis working beneath a gum line that has barely moved.
Where the gum has swollen above the CEJ, a “pseudopocket” can produce a deep probing number with no real attachment loss at all. Measuring from the CEJ prevents that overcall. If you want one question answered after charting, make it this: how much attachment have I lost, and is it changing?
How do dental X-rays show the bone that holds teeth in place?
A probe measures soft tissue and the top of the attachment. It cannot measure bone. For that, the team turns to radiographs, most often small bitewing films that show the crowns and the crest of bone between neighboring teeth, and periapical films that capture the whole root.
In a healthy mouth the bony crest sits just a millimeter or two below the CEJ, running almost level between adjacent teeth. Periodontitis dissolves that crest. On the film the bone edge drops away from the enamel, and the clinician measures the gap from CEJ to crest, then compares it with the full root length to estimate what percentage of support remains. The current international classification of periodontitis uses this radiographic bone loss, expressed as a share of root length, as one of the main criteria for staging severity.
Patterns tell their own story. Horizontal bone loss, where the crest drops evenly across several teeth, usually reflects generalized, slowly progressing disease. Vertical or angular defects, where bone is lost in a trench beside one root, often point to a local factor such as a food trap, an overhanging filling or heavy biting forces. Bone loss between the roots of a molar, visible as a dark triangle under the crown, matches the furcation involvement felt with the probe.
X-rays also have blind spots worth knowing. They show bone between teeth clearly but are poor at revealing loss on the cheek or tongue side, because the dense root overlaps the thin plate of bone there. Recession on the front surface of a lower incisor can therefore sit over a sliver of missing bone that no two-dimensional film will reveal. The probe and the film answer different questions, and a trustworthy diagnosis uses both. Mayo Clinic lists checking X-rays for bone loss as a routine part of diagnosing periodontitis.
Periodontal charting explained: what actually happens at the appointment
A full periodontal chart is the visit where every tooth is measured, recorded and compared. Expect it to take longer than a routine check, and expect the sound of numbers rather than conversation while it is in progress.
It begins with a look. The clinician notes gum color, swelling, recession and plaque before the probe touches anything, because probing itself can cause slight bleeding. Then the probe is “walked” around each tooth in small steps, dipping into the sulcus at the six standard points. The pressure used is light, roughly the force that would blanch a fingernail, so the reading reflects where tissue attaches rather than how hard the clinician pushes. Healthy gums usually feel this as pressure; inflamed gums can sting briefly.
Each reading is spoken aloud and entered into a chart, often by a second team member, and bleeding points are marked as they appear. Recession is recorded tooth by tooth. Any tooth that moves is graded for mobility, and multi-rooted teeth are checked for furcation involvement with a curved probe. Plaque and calculus (hardened plaque below the gum) are noted, since they are the reason pockets stay inflamed.
X-rays are taken or reviewed, and the clinician reads bone levels against the probing findings. If depths, bleeding and bone loss line up, the picture is periodontitis. If recession is present with shallow, dry pockets and level bone, the cause is likely mechanical or anatomical.
The end product is a dated map that the NHS describes as the basis for deciding how often you need reviews and whether a referral to a specialist is appropriate. Ask to see it. Most charts are color-coded, and seeing where the deep pockets cluster makes the home-care advice that follows far more concrete.
What are the different stages of receding gums?
People searching for “stages of receding gums” often expect a tidy scale from one to four. In practice two different systems are at work, and knowing which one your clinician means avoids confusion.
The first classifies the recession itself. The current international scheme sorts recession into three types based on the tissue between the teeth. Type 1 recession has no loss of attachment between the teeth: the gum has slipped on the cheek side only, and the papilla, the small triangle of gum between adjacent teeth, is intact. Type 2 has interdental attachment loss that is less than or equal to the loss on the cheek side. Type 3 has greater loss between the teeth than on the cheek side. The type matters because the tissue between teeth is what a graft can be anchored to; Type 1 defects are generally the most favorable to cover, and Type 3 the least, though individual anatomy always shapes what a surgeon expects.
The second system stages periodontitis, the disease that may underlie recession. Stage I describes initial attachment loss with bone loss confined to the top portion of the root. Stage II is moderate. Stage III is severe, with deeper bone loss, possible furcation involvement and the potential for tooth loss. Stage IV adds complications such as drifting teeth or loss of several teeth. Alongside the stage sits a grade, A to C, that estimates how fast the disease is progressing, with smoking and diabetes raising the grade.
Recession without periodontitis has no “stage” in the disease sense, because there is no infection to advance. Its severity is simply the measured depth, width and type. Cleveland Clinic notes that recession cannot regrow on its own, so the useful question is less “what stage am I?” and more “is this moving, and why?”
Who is usually asked to have a full periodontal assessment, and who can wait?
Not every mouth needs a full six-point chart at every visit. Many dental teams begin with a screening examination that samples pockets around the mouth and flags only the areas that warrant the longer measurement. The decision to move to full charting rests on what the screening shows and on individual risk.
Full assessment is commonly suggested when screening finds pockets of 4 millimeters or more, bleeding on probing across several areas, visible recession that has changed since the last record, teeth that move, or X-rays that show bone loss. It is also usual for anyone with a history of treated periodontitis, because disease that was once active tends to be monitored closely even when it is quiet.
Risk factors push toward charting sooner. Mayo Clinic lists smoking, diabetes, a family history of gum disease, hormonal changes such as pregnancy, certain medicines that cause dry mouth or gum overgrowth, and conditions that lower immunity. In these groups, the threshold for measuring everything is lower because disease can progress faster and with fewer warning signs.
Who is usually asked to wait? Someone with healthy screening scores, no bleeding, no recession and no risk factors will typically be rechecked at the recall interval their dentist sets rather than charted in full. A patient with acute pain, a swollen abscess or an active ulcer is also often asked to wait: inflamed tissue probes deeper than its true attachment, so measurements taken during a flare can overstate the problem. The team will usually settle the acute issue first and chart once the tissue has calmed. Pregnancy does not prevent charting, though X-rays are kept to what is clinically necessary.
These are typical patterns, not rules. The interval and the depth of assessment are your clinician’s call, made against your own history.
Why do gums recede when the pockets are shallow and healthy?
A surprising number of people with recession have no gum disease at all. Their pockets measure 1 to 3 millimeters, nothing bleeds, and the bone between the teeth is level. Yet one or more roots are plainly exposed. Measurements identify this pattern quickly, and it points to a different set of causes.
Brushing technique is the one most often implicated. A hard-bristled brush used with a horizontal scrubbing motion wears away thin gum tissue over time, especially on the cheek side of canines and premolars where the brush naturally bears down. Cleveland Clinic lists aggressive brushing among the leading causes of recession, alongside gum disease, genetics, tobacco use and misaligned teeth.
Anatomy does the rest. Some people inherit a thin “phenotype,” a narrow band of gum over a thin plate of bone. When a root is prominent, or when orthodontic treatment moves a tooth outward through that thin bone, the covering tissue has little to spare. Recession here is often described as a soft-tissue problem sitting over a bony dehiscence, a slot-shaped gap in the bone that X-rays cannot show.
Other mechanical contributors include a high frenum, the band of tissue connecting lip to gum, that tugs at the margin; piercings in the lip or tongue that rub the same spot repeatedly; and grinding or clenching, which some clinicians believe concentrates force at the neck of the tooth, though evidence for grinding as a direct cause remains mixed and is best described as uncertain.
The practical consequence is that treatment aims at the cause rather than at infection. A softer brush and a gentler stroke, a frenum release, or protection of exposed root from decay may matter more than deep cleaning. Measurements that stay flat year after year are the proof that the cause has been controlled.
How do the measurements shape treatment options for gum recession?
Treatment follows the numbers. The same recession can lead to very different recommendations depending on what the pockets, bleeding points and X-rays show, and the decision always sits with the clinician who holds the full chart.
When charting shows inflamed pockets of 4 millimeters or more with bone loss, the first step is almost always non-surgical. Scaling and root planing is a deep cleaning that removes plaque and calculus from the root surface below the gum, often under local anesthetic and over more than one visit. Mayo Clinic describes it as the usual starting point for periodontitis. Its purpose is to let inflamed tissue heal against a clean root; pockets often shrink as swelling resolves.
Where pockets remain deep after that healing period, surgical options enter the conversation. Flap surgery lifts the gum to allow cleaning and reshaping of bone, then stitches it back at a level that is easier to maintain. Bone grafts or guided tissue regeneration aim to rebuild lost support in certain defect shapes, particularly the vertical trenches described earlier. Clinicians speak of these as attempts to regain support, not as guarantees.
When the pattern is recession with healthy, shallow pockets, the question becomes whether to cover the root. Gum grafts, in which tissue is taken from the palate or a donor material is used and positioned over the exposed root, can increase the band of attached gum and may cover part or all of the defect. How much coverage is realistic depends heavily on the recession type: intact tissue between the teeth makes full coverage more achievable, while interdental loss limits it. Alternatives include simply monitoring stable recession, treating sensitivity, placing a filling to protect exposed root, or correcting the brushing habit that caused it.
Every option carries trade-offs of discomfort, cost in time, and uncertainty. A good consultation lays them out against your own numbers.
What do the following weeks usually look like after periodontal treatment?
Periodontal care is unusual among dental treatments in that the “result” is read with the same probe that found the problem. The weeks after treatment are therefore a waiting period before the chart is repeated.
After scaling and root planing, gums commonly feel tender for a few days and may bleed slightly when brushed. Exposed roots can become more sensitive to cold as swollen tissue shrinks back and uncovers more root surface; this is expected and usually settles, though it can be unwelcome for someone who sought care because of recession. Clinicians generally advise continuing to brush and clean between teeth gently rather than avoiding the treated area, since plaque left on a freshly cleaned root undermines the whole exercise.
Re-evaluation follows once the tissue has had time to heal. At that visit the pockets are probed again and compared with the baseline chart. Three outcomes are possible. Pockets that have shallowed and stopped bleeding are placed on a maintenance schedule. Pockets that have improved but remain over 5 millimeters may be treated again or referred for surgical assessment. Pockets that have not changed prompt a search for why: missed calculus, a cracked root, uncontrolled diabetes or continued smoking are common explanations.
After grafting surgery, the timeline is different. The grafted site is protected, often with a dressing, and the palate donor site can be sore for longer than the recipient site. Patients are usually asked not to brush the area and to avoid pulling the lip to look at it, because early movement can disturb the graft before it gains a blood supply. Final tissue position is judged months rather than weeks later, as the graft matures and settles.
Long term, Mayo Clinic notes that people with treated periodontitis typically need professional cleanings more often than the standard recall. The NHS similarly describes ongoing hygienist visits as part of keeping gum disease under control. Think of maintenance as the treatment continuing at a lower intensity, with the numbers as the scorecard.
What people often get wrong about periodontal measurements and gum recession
Myth one: a shallow pocket means a healthy tooth. Not when recession is present. A 2-millimeter pocket beside 4 millimeters of recession adds up to 6 millimeters of attachment loss. The pocket is shallow only because the gum has already gone. Ask about attachment loss, not pocket depth alone.
Myth two: receded gums grow back if you brush better. They do not. Cleveland Clinic is explicit that gum tissue lost to recession will not regenerate on its own. Better brushing stops further loss; only surgery can move the margin back up, and only in suitable defects.
Myth three: bleeding gums are normal, or caused by brushing too hard. Healthy gums do not bleed under normal brushing or gentle probing. Bleeding is a sign of inflammation, and the usual response is to clean more thoroughly, not less. MedlinePlus lists bleeding gums among the earliest signs of gum disease.
Myth four: X-rays show everything. They show bone between teeth well and bone on the cheek and tongue surfaces poorly. A tooth with alarming recession on its front face can look fine on a film. The probe is not a backup to the X-ray; it measures what the X-ray misses.
Myth five: the numbers are precise to the millimeter. Probing is influenced by inflammation, probe angle, pressure and the exact landmark used. A change of 1 millimeter between visits may be measurement noise; a consistent change of 2 millimeters or more at the same site is the kind of shift clinicians act on.
Myth six: once pockets are treated, the disease is finished. Periodontitis is managed, not eliminated. It stays quiet as long as plaque is controlled and risk factors are addressed, and it can reactivate when they are not. That is why the chart is repeated for life rather than filed away.
Myth seven: gum disease is just a mouth problem. The associations with diabetes control and cardiovascular disease are real in observational research, even though cause and effect are not settled. Your dental chart is worth mentioning to the clinician who manages your general health.
Questions to ask your care team about your gum measurements
The most useful conversations after charting are specific. These questions help you leave with a picture of your mouth rather than a reassurance or a warning.
- What is my attachment loss at the worst sites, and how does it compare with my last chart?
- How many sites bled on probing, and is that number rising or falling?
- Is my recession the kind that comes with gum disease, or does it sit over healthy, shallow pockets? What do you think is causing it?
- What recession type do the affected teeth have, and does that make root coverage realistic if I wanted it?
- What do my X-rays show about bone levels, and are there any angular defects or furcation involvements?
- Which teeth are you most concerned about, and what would change your view of their prognosis?
- If deep cleaning is recommended, when will the pockets be re-measured, and what result would lead you to suggest something further?
- What recall interval do you suggest, and what would move me to a longer or shorter one?
- Is there anything in my general health or medicines that is likely to affect how my gums respond?
- Can I have a copy of the chart to compare at my next visit?
Two further points are worth raising. First, ask how the clinician distinguishes a real change from measurement variation at a single site; the answer tells you how your progress will be judged. Second, if a graft is on the table, ask what happens if it covers less root than hoped. Partial coverage is a possible outcome of any grafting procedure, and knowing what “partial” would look like makes the decision clearer. The answers belong to your treating team; the questions belong to you, and bringing a written list is entirely reasonable.
When to call your doctor or dentist
Most gum recession and most early periodontitis are slow, quiet processes that belong in a scheduled appointment, not an emergency slot. Some signs, though, warrant a call sooner rather than waiting for the next recall.
Contact your dental team promptly if you notice a gum that has become swollen, shiny and tender over a short period, especially if there is a pimple-like bump that drains or a bad taste that does not clear with brushing. These can signal a periodontal abscess, a pocket of infection in the gum that may need draining and cleaning. A tooth that has started to feel loose, has shifted position, or no longer meets its partner when you bite is another reason to be seen soon, because mobility suggests support is being lost quickly.
Seek same-day advice from a dentist or, where none is available, a doctor or urgent care service if facial swelling spreads toward the eye or under the jaw, if you develop fever with a swollen gum, if swallowing or opening your mouth becomes difficult, or if bleeding from the gum will not stop with firm pressure. Spreading dental infection is uncommon but can become serious, and the NHS advises urgent care for swelling that affects the face, neck or breathing.
Less urgent, but still worth mentioning at your next visit: new or worsening cold sensitivity on an exposed root, a gum margin that looks visibly lower than it did a few months ago, bleeding when you brush or clean between teeth, persistent bad breath, or a change in general health such as a new diabetes diagnosis or a medicine that has made your mouth dry.
If you have periodontitis and also have diabetes or heart disease, let both your dental and medical clinicians know about each other’s findings. The decision about what, if anything, needs doing rests with the team that examines you, but your description of what changed, and when, is the information they cannot get from the probe.
Frequently asked questions
What are the different stages of receding gums?
Recession is classified by how much tissue remains between the teeth, in three types: Type 1 with intact interdental gum, Type 2 with interdental loss no greater than the cheek-side loss, and Type 3 with greater interdental loss. Separately, periodontitis itself is staged I to IV by severity of attachment and bone loss. Recession without gum disease has no disease stage; its severity is simply its measured depth, width and type.
What is the life expectancy of someone with periodontal disease?
Periodontitis is not a fatal illness and does not carry a life expectancy figure. Research has found associations between gum disease and conditions such as heart disease and poorly controlled diabetes, but these are observational links and a direct cause-and-effect relationship has not been established. The sensible response is to treat the gums, control shared risk factors such as smoking and blood sugar, and keep both dental and medical teams informed.
How is gingival recession measured?
A periodontal probe marked in millimeters is placed at the cementoenamel junction, the fixed line where enamel meets root, and the clinician reads the distance down to the current gum margin. Width and the amount of firm attached gum beside the defect are also recorded. Photographs or models may be kept for comparison, since changes of a millimeter are hard to judge from memory.
What do different gum probe numbers mean?
Probe numbers are pocket depths in millimeters at six points around each tooth. Mayo Clinic describes 1 to 3 millimeters as typical of health, 4 millimeters or more as possibly indicating periodontitis, and over 5 millimeters as difficult to clean at home. Bleeding at a site adds meaning: a bleeding pocket is inflamed and active, while a dry one of the same depth may be stable.
Can gum recession happen without gum disease?
Yes. Many people with exposed roots have shallow, non-bleeding pockets and level bone on X-rays. In that pattern the usual causes are hard brushing, a thin gum and bone type, prominent roots, orthodontic tooth movement, a frenum pulling at the margin, or a piercing rubbing the same spot. Management focuses on removing the cause and protecting the exposed root rather than on deep cleaning.
What is clinical attachment loss in a periodontal chart?
Clinical attachment loss is the distance from the cementoenamel junction to the bottom of the pocket, calculated by adding recession to probing depth. It is anchored to a fixed landmark, so it is less affected by gum swelling or shrinkage than pocket depth alone. Clinicians rely on it to judge whether support is stable or still being lost between visits.
Why does my gum look fine but the X-ray shows bone loss?
Periodontitis often destroys bone beneath a gum line that barely moves, because the inflamed gum stays at its original height while the attachment below it is lost. The result is a deep pocket rather than visible recession. X-rays reveal the bone level between teeth that the eye cannot see, which is why they are read alongside probing rather than instead of it.
Will receded gums grow back on their own?
No. Cleveland Clinic notes that gum tissue lost to recession does not regenerate by itself. Gentler brushing, treating inflammation and removing the cause can stop further loss and keep the measurements stable. Moving the gum margin back over the root requires surgical grafting, and how much coverage is realistic depends on the recession type and the tissue remaining between the teeth.
How often should periodontal charting be repeated?
There is no single interval. Dental teams decide based on screening results, history of treated periodontitis and risk factors such as smoking or diabetes. Healthy mouths may be screened briefly at routine visits, while treated periodontitis is usually charted in full at regular maintenance appointments so that changes at individual sites can be compared against the earlier record.
Does probing hurt or damage the gums?
Probing uses light pressure and does not damage healthy tissue. Healthy gums usually register only pressure; inflamed gums can sting briefly and may bleed, which is itself a recorded finding rather than harm from the instrument. If probing is consistently painful, tell the clinician, because that usually reflects inflammation at those sites and can be managed with local measures during charting.
References
- Cleveland Clinic: Gum Recession
- NHS: Gum Disease
- MedlinePlus: Gum Disease
- NIH National Institute of Dental and Craniofacial Research: Periodontal (Gum) Disease
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Do Children Get Removable Appliances? How Jaw Growth Shapes the Timing
Removable appliances for children are usually fitted during the mixed dentition years, when baby and adult teeth share the mouth and the jaws are…
Why a Cleaning Comes Before Teeth Whitening: Checking Enamel, Gums and Old Fillings
A professional cleaning usually comes before teeth whitening because whitening gel works on clean enamel, not on plaque and tartar, and because the dentist…

How Fiber Application Works in One Visit: Bonding the Fiber Into Composite Resin
A fiber reinforced composite procedure adds a ribbon of glass or polyethylene fiber inside tooth-colored composite resin so the restoration resists bending and cracking.…
How Digital Planning Maps Tooth Movement Before Clear Aligners Are Made
Clear aligner digital planning starts with a 3D scan of the teeth, often alongside X-rays, from which software separates each tooth and lets the…

How Long Does Sensitivity Last After Restorative Dental Treatment? Numbness and Temporaries
Mild sensitivity after restorative dental work, such as a filling or crown, is common and usually eases over a few days to a few…

Flying After a Tooth Extraction: How Long to Wait and How to Protect the Clot
Most dental teams prefer that you avoid flying for at least 24 hours after a simple tooth extraction, and many suggest 48 to 72…