

When a PEG Tube Needs Replacing: Blockages, Wear and How the Exchange Is Done

Key Takeaways
- Bumper-retained PEG tubes are replaced when they wear out or fail, not on a fixed schedule, while balloon-retained tubes are exchanged at manufacturer-recommended intervals because the balloon slowly weakens.
- The ESGE guideline describes the gastrostomy tract as generally mature at around four weeks; before that, any exchange is usually done with endoscopic or X-ray guidance rather than blindly at the bedside.
- Most blockages clear with warm water in a large syringe used with a gentle push-pull motion; acidic drinks such as cola are poorly supported and can firm up a protein plug.
- Buried bumper syndrome, reported in roughly 1% to 2% of PEG users, is largely prevented by keeping the external disc slightly loose and advancing and rotating the tube daily.
- Leaking around a tube is usually a tract or stomach-emptying problem, and upsizing the tube tends to stretch the tract and bring the leak back within weeks.
- A tube that falls out is a same-day problem because the tract begins to narrow within hours; covering the stoma or gently keeping it open while calling the team preserves the option of a simple bedside reinsertion.
A PEG tube usually needs replacing when it blocks and cannot be cleared by flushing, when the material cracks, kinks or discolors, when a balloon-type tube fails, or when the internal bumper causes problems. The exchange is a short procedure done through the existing opening, either at the bedside or with an endoscope, and your treating team decides the timing and method based on the tube type and how mature the tract is.
It is a little after six in the morning, the kitchen light is on, and the syringe will not budge. She has pushed water through her husband’s feeding tube every morning for eleven months without thinking about it. Today it stops halfway, like a straw pressed against the bottom of a glass. She tries again, gentler, then firmer, and then she puts the syringe down and wonders whether this is the day the tube has to come out.
That moment arrives for most families eventually. A PEG tube is a working part, not a permanent fixture, and it wears in ways that are fairly predictable once you know what to look for. Understanding when a peg tube replacement is genuinely needed, and when a blockage or a leak can be sorted without one, takes much of the fear out of that early morning.
This explainer walks through the reasons tubes fail, how the exchange is actually carried out, what the weeks afterward tend to look like, and the signs that mean you should not wait until office hours.
Why does a PEG tube need replacing at all?
A PEG tube, short for percutaneous endoscopic gastrostomy, is a soft feeding tube placed through the skin of the abdomen into the stomach with the help of an endoscope, a thin camera passed down the throat. Once the channel between skin and stomach has healed into a firm little tunnel, called the tract, the tube becomes a piece of household equipment that is used several times a day, every day.
Equipment wears. The silicone or polyurethane softens and stretches with months of formula, medicines and stomach acid moving through it. The outer plastic can yellow, become sticky or develop small cracks near the connector where it is clamped and unclamped most often. The feeding port may no longer grip the syringe, so feeds dribble at the join. A tube that once lay flat against the skin may start to slide in and out more than it used to, or feel stiff and hard to rotate.
Wear on its own rarely forces a same-day change. The three things that usually push a peg tube replacement from “soon” to “now” are a blockage that will not clear, a balloon-retained tube whose balloon has deflated or burst, and a tube that has come out entirely. A fourth, less visible reason is a problem with the internal bumper, the mushroom-shaped disc that holds a traditional PEG in place inside the stomach. That is covered later, because it changes how the exchange is done.
MedlinePlus describes gastrostomy tubes as designed for long-term feeding, and many function for many months before showing wear; there is no fixed expiry date that applies to every person, so the treating team judges each tube on how it is behaving rather than on the calendar alone.
How often should a PEG tube be changed?
The honest answer is that it depends on which kind of tube is in place, and families are often surprised that there are two very different designs.

The first is the classic bumper-retained PEG placed at the original procedure. Its internal disc holds it without any moving parts. The European Society of Gastrointestinal Endoscopy (ESGE) guideline on enteral tubes notes that these tubes are not replaced on a routine schedule; they are exchanged when they wear out, block, or develop a complication. Some remain in use for well over a year.
The second is the balloon-retained gastrostomy tube, which is held in the stomach by a small water-filled balloon rather than a solid disc. Balloons slowly lose water and eventually weaken, so manufacturers advise periodic exchange, typically every few months, and the ESGE guideline supports following manufacturer guidance for these devices. Low-profile “button” devices that sit flush with the skin are usually balloon-type and follow the same pattern.
Timing also hinges on tract maturity. The ESGE guideline describes the tract as generally mature at around four weeks after the first placement. Before that, the stomach wall and the abdominal wall have not fully knitted together, so pulling a tube out or pushing a new one in risks the stomach dropping away and the new tube ending up in the abdominal cavity rather than the stomach. Any early exchange therefore usually happens with endoscopic or X-ray guidance rather than at the bedside.
In practice, a nutrition nurse or gastroenterology team reviews the tube at follow-up and records the type, the placement date and, for balloon tubes, the recommended exchange interval. Keep that information on the fridge or in your phone. The person on call at three in the morning will ask for it.
PEG tube blocked: what to do first, and what not to do
Most blockages are not the tube’s fault. They come from formula left to dry in the lumen, medicines crushed and mixed together, or a flush that was skipped because the day got away from you. MedlinePlus advises flushing with water before and after every feed and every medicine, precisely because a tube that is rinsed regularly rarely clogs.
When it does, the first step is patience rather than force. Warm water drawn into a large syringe and pushed and pulled gently in a rocking motion is the standard first attempt described by MedlinePlus and mirrored in the ESGE guideline. The rocking action matters more than the pressure; it works the plug loose from both directions. Clamping the tube and letting warm water sit for a while, then trying again, often finishes the job.
Several habits make things worse:
- Using a small syringe. Smaller barrels generate much higher pressure and can split the tube.
- Pushing anything solid or sharp down the lumen. A wire or knitting needle can perforate the tube wall or the stomach.
- Carbonated drinks or fruit juices. These are folk remedies; acidic liquids can curdle formula protein and tighten the plug, and the evidence for them is poor.
If warm water fails, the next step belongs to the clinical team. Some services use a solution of pancreatic enzymes to digest protein-based clogs, and specialized declogging brushes exist for use by trained staff. The ESGE guideline lists these as options where simple flushing has not worked, while acknowledging the evidence base is limited. Only when those measures fail, or when the blockage keeps returning because the tube itself has narrowed with age, does a peg tube replacement become the sensible route.
How a PEG tube replacement is actually done
Picture the tract as a healed tunnel with a door at each end. The exchange is essentially removing one tube from that tunnel and threading another through it before the tunnel starts to narrow. How the old tube comes out depends entirely on what is holding it in.
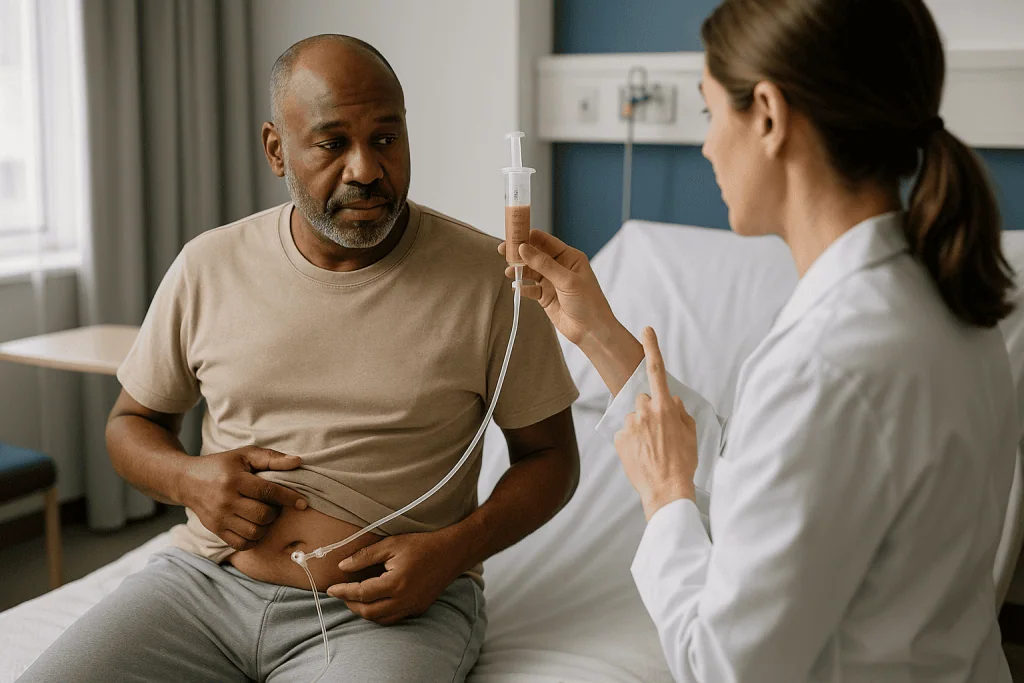
For a balloon-retained tube, the clinician attaches a syringe to the small side port, draws the water out of the balloon, and slides the tube out with steady pressure. The stoma, the opening in the skin, is checked and cleaned. A new tube of the same size is lubricated, passed through the tract into the stomach, and its balloon is filled with the amount of sterile water specified by the manufacturer. The external disc is set so the tube sits snugly but not tightly against the skin. Placement is confirmed by drawing back stomach contents, and in many services by checking that the fluid is acidic. Done at the bedside or in a clinic room, this often takes only a few minutes, and MedlinePlus notes that trained caregivers are sometimes taught to do it at home for established balloon tubes.
For a bumper-retained PEG, the internal disc cannot simply be pulled without judgment. Some bumpers are designed to collapse and be drawn out through the skin with firm traction; the ESGE guideline supports external traction removal for suitable tubes in mature tracts. Others are rigid and must be cut at the skin, the internal piece grasped with the endoscope and brought out through the mouth. The new tube may then be a balloon device pushed through the tract, or a fresh bumper PEG placed endoscopically with the pull technique used the first time.
Sedation, if any, follows the method: bedside balloon changes usually need none, while endoscopic exchanges use the same light sedation as the original placement.
Who is usually offered a PEG tube replacement, and who is asked to wait
The clearest candidates are people whose tube has failed mechanically: a burst balloon, a crack that leaks with every feed, a lumen so narrowed that flushes take twice as long as they did, or a tube that has come out. In those situations the question is not whether to replace but how quickly and by which route.
A second group are people on scheduled balloon exchanges. Here the tube is working fine; the change is preventive, timed to the manufacturer’s interval and the person’s convenience. Skipping these because “it’s not broken” tends to convert a planned clinic visit into an unplanned one when the balloon eventually gives out.
Some people are asked to wait, and the reasons are worth understanding rather than resenting:
- The tract is younger than about four weeks. As the ESGE guideline explains, the stomach and abdominal wall are not yet fused, so an exchange carries a real risk of misplacement and is deferred or done under imaging.
- The stoma is infected. Swapping tubes through inflamed, weeping skin can push infection deeper; the skin is usually treated first.
- There is bleeding, a suspected buried bumper, or unexplained abdominal pain. These need assessment, and sometimes imaging, before anyone pulls on the tube.
- The person is unwell for another reason, such as a chest infection, and sedation would add risk. A bedside change may still be possible, but an endoscopic one may be postponed.
A different conversation happens when the tube may no longer be needed at all. Someone recovering swallowing after a stroke, for example, may be heading toward removal rather than replacement. That decision sits with the speech and language team, the dietitian and the treating physician together, and it is reasonable to ask whether an exchange is the right next step or whether a swallow reassessment should come first.
Which type of tube goes in? A comparison
Once a tube is due for exchange, the team chooses what replaces it. There is no single best design; each trades convenience against durability, and the right choice depends on the person’s activity, who will be caring for the tube, and how easily they can reach clinical support.
| Feature | Bumper-retained PEG | Balloon gastrostomy tube | Low-profile button |
|---|---|---|---|
| How it is held in | Solid internal disc | Water-filled balloon | Usually a balloon, flush with skin |
| Typical lifespan | Many months to over a year; replaced when worn | Months; scheduled exchange per manufacturer | Months; scheduled exchange per manufacturer |
| Where exchange happens | Endoscopy unit for rigid bumpers; bedside traction for collapsible types in mature tracts | Bedside, clinic, or trained caregiver at home | Bedside or clinic; extension set needed to feed |
| Accidental dislodgement | Uncommon; disc resists pulling | More common; balloon can deflate | Less external length to catch, but balloon can still fail |
| Main drawback | Buried bumper if too tight; endoscopy needed to remove some types | Balloon rupture; needs regular checks of balloon water | Fiddly connectors; not all sizes suit every tract |
The ESGE guideline and MedlinePlus both describe the balloon tube as the usual replacement once a tract is mature, because exchanges can be done without sedation and without an endoscopy slot. A person who is very active, or who pulls at the tube, may do better with a low-profile button or a bumper tube. Someone living far from support may be steered toward the design their caregiver can manage independently. Ask the team to explain which trade-off they are making on your behalf.
Buried bumper syndrome: the complication that changes the plan
Buried bumper syndrome is what happens when the internal disc of a bumper-retained PEG gradually migrates from the inside of the stomach into the stomach wall, and sometimes all the way into the abdominal wall, so the tissue closes over it. It is the complication most likely to turn a simple exchange into something more involved.
The mechanism is pressure. If the external disc is fixed too tightly against the skin, the internal bumper presses constantly against the stomach lining. The lining ulcerates under it, heals around it, and slowly swallows the disc. Weight gain after the tube was placed can do the same thing, because the abdominal wall thickens while the tube length stays fixed.
The ESGE guideline reports buried bumper syndrome in roughly 1% to 2% of people with a PEG, usually months to years after placement. Clues include a tube that can no longer be pushed inward or rotated, feeds that leak around the tube or cause pain when infused, and an external portion that looks shorter than it used to. It is one reason the daily care routine for a bumper PEG includes gently advancing the tube a short way into the stomach and turning it, so the disc never sits in one spot.
When a buried bumper is suspected, nobody should pull. The team confirms it with endoscopy or imaging, then chooses a removal method based on how deeply the disc is buried: endoscopic techniques that cut the overgrown tissue and retrieve the bumper, or occasionally a surgical approach for deeply embedded devices. A new tube can often be placed through the same tract afterward, or a fresh site is used if the old one is too damaged. The ESGE guideline recommends removing a buried bumper even when it is causing few symptoms, because the risks of leaving it grow with time.
Leaking, granulation tissue and a loosening tube: when a new tube isn't the fix
A wet dressing every morning is one of the commonest reasons families ask for a new tube, and it is also one of the situations where a replacement can make things worse.
Leakage around a PEG usually means the tract has stretched wider than the tube, or that stomach emptying is slow so feed is backing up under pressure. The instinct is to put in a bigger tube to fill the gap. Both the ESGE guideline and Johns Hopkins patient guidance caution against this: a wider tube stretches the tract further, the leak returns in a few weeks, and the cycle repeats. The better approaches are to look for the cause, such as constipation, coughing, a tube that has been anchored too loosely, or medicines that slow the stomach, and in some cases to remove the tube for a short period so the tract can shrink before a same-size tube goes back in.
Granulation tissue, the pink, moist, easily bleeding overgrowth that forms at the edge of a stoma, is another frequent worry. It is the body’s healing response to friction, and it is not a sign that the tube is failing. It tends to form when the tube rubs because the external fixation is too loose or too tight. Management is topical and mechanical, adjusting the fit and, when needed, having the team treat the tissue; swapping the tube itself does little unless the fit is corrected at the same time.
Skin that is red, hot, painful and producing thick discharge is different again. That is infection of the stoma, and MedlinePlus lists it among the reasons to contact the care team promptly. Infection is treated first; exchange, if still needed, follows.
The pattern across all three is the same: the tube is often blamed for a problem that lives in the tract or the skin, and a peg tube replacement fixes the tube while leaving the real cause untouched.
My PEG tube fell out: why the clock matters
A tube that comes out entirely is alarming, but it is also common, and the response is straightforward as long as it is quick.
The tract begins to narrow within hours once nothing is holding it open. MedlinePlus and Johns Hopkins patient instructions both advise contacting the care team immediately and, if you have been shown how, covering the stoma with a clean dressing or gently placing the old or a spare tube a short way into the opening to keep it from closing, without feeding through it until placement is confirmed. Families of long-term tube users are often given a spare tube and taught this for exactly this reason.
What happens next depends on two things: how old the tract is and how long the tube has been out. In a mature tract with a tube out for only a few hours, a same-size balloon tube can usually be passed at the bedside or in an emergency department, and position confirmed by drawing back stomach contents. If the tract is younger than about four weeks, or the tube has been out long enough that the opening has tightened, the ESGE guideline advises against blind reinsertion because of the risk of pushing the new tube into the wrong place. In those cases the team uses X-ray with contrast, or endoscopy, to guide a new tube in or, if the tract has closed, to place a new PEG.
The mistake to avoid is waiting overnight to see. A tract that could be reopened at breakfast may need a repeat endoscopy by evening. If the person cannot take anything by mouth, missed feeds and missed medicines add their own urgency, so this counts as a same-day problem even when the person feels well.
What the following days and weeks usually look like
After a bedside balloon exchange, most people go home the same hour. Feeds and medicines usually restart as soon as the team is satisfied the tube is in the stomach, which may be immediately or after a short pause; the treating team sets that timing based on how the confirmation went.
A mild ache around the stoma for a day or two is expected. The tract has been stretched slightly, and the new tube’s fixation plate may sit a little differently. A small amount of clear or pinkish fluid on the dressing is also typical early on. MedlinePlus patient guidance describes cleaning the site daily with mild soap and water, drying it well, and checking that the external disc has a small gap from the skin rather than pressing hard into it.
For balloon tubes, the first week is when the balloon volume is checked, because a balloon that was slightly underfilled can let the tube slip. Caregivers are often taught to check the water in the balloon at an interval the team specifies, replacing whatever has been lost.
After an endoscopic exchange under sedation, the day is fuller. Expect drowsiness for the rest of the day, a sore throat from the scope, and a ban on driving until the next day. Feeding through the new tube commonly begins within hours once the team has confirmed position, but some units wait longer if the removal of a rigid bumper caused any bleeding.
Over the following weeks the focus shifts back to routine: flushing with water before and after every use, rotating and advancing a bumper tube daily, and watching for the early signs of the same wear that prompted the change. A follow-up call or visit with the nutrition team is usual, and it is the moment to report any leaking, pain on feeding or difficulty flushing while they are small.
Risks of the exchange, and the alternatives your team may weigh
Replacing a tube through a mature tract is a low-risk procedure, but not a no-risk one, and the risks are specific enough to be worth naming.
The most serious is misplacement: a new tube ending up between the stomach and the abdominal wall rather than inside the stomach. Feeding into that space can cause peritonitis, an inflammation of the abdominal lining that is a medical emergency. This is why teams confirm position before the first feed, why early tracts are handled with imaging, and why sudden severe pain after an exchange should never be attributed to “just soreness”. Minor bleeding from the tract or the stomach lining is common and usually settles; heavier bleeding is rare but more likely after removal of a rigid bumper. Infection of the stoma can follow any manipulation. A review of PEG complications in the World Journal of Gastroenterology describes these as the main procedural risks and notes that most are minor and manageable, while serious complications are uncommon.
Alternatives depend on why the exchange is being considered. If the tube is blocked, the alternative is a more determined attempt to clear it. If the problem is leaking, the alternative may be a temporary removal to let the tract shrink. If the person is recovering swallowing, the alternative may be planned removal with close dietetic follow-up. When the stomach itself is the problem, with severe reflux or slow emptying, the team may discuss a tube that extends beyond the stomach into the small intestine, either through the existing gastrostomy or as a separate jejunostomy, a feeding tube placed directly into the small bowel. Each of these has its own maintenance demands, and the ESGE guideline describes them as options for specific indications rather than upgrades.
Every one of these choices is a judgment about a particular person. The team should be able to say which risk they are trying to lower with the option they recommend.
What people often get wrong about PEG tube replacement
Some beliefs about feeding tubes are so widespread that they feel like knowledge. Several of them cause real harm.
“A blocked tube means it needs replacing.” Most blockages clear with warm water and patience. The tube is replaced for a blockage only when clearing has genuinely failed or the clogs keep coming back because the lumen has narrowed with age.
“Cola dissolves the clog.” The evidence for carbonated or acidic drinks is weak, and acid can curdle formula protein and make the plug firmer. Warm water is the first-line method in MedlinePlus guidance and the ESGE guideline.
“Tighter is safer.” Fixing the external disc hard against the skin is the single most preventable cause of buried bumper syndrome. The tube should sit snugly with a small gap, and a bumper PEG should be advanced and rotated daily.
“If it leaks, go up a size.” A larger tube stretches the tract, and the leak returns. Finding the cause, or resting the tract briefly, is the guideline-supported approach.
“Any tube can be pulled out at home.” Balloon tubes, yes, once a caregiver has been trained. Bumper tubes, only if the type is known to be collapsible and the tract is mature. Pulling a rigid bumper can tear the tract.
“Once it falls out, there’s no hurry.” The tract starts closing within hours. Same-day contact with the team preserves options that are lost by morning.
“Replacement means another big procedure.” For most people with a mature tract and a balloon tube, an exchange is a few minutes in a clinic chair with no sedation. It is the original placement, and buried-bumper retrievals, that require endoscopy.
Replacing these beliefs with the actual mechanics is, in the end, the best protection a family has against both unnecessary exchanges and dangerous delays.
Questions to ask your care team
A five-minute conversation before an exchange saves a great deal of uncertainty afterward. These are the questions that experienced tube users tend to ask, and none of them should be awkward.
- What type of tube do I have now, and what type will replace it? Ask them to write down the design, the size and the date of placement.
- Is my tract considered mature, and does that affect where and how the exchange will be done?
- Will this be a bedside change or an endoscopic one, and will I need sedation? If sedation is planned, what are the arrangements for getting home?
- How soon after the exchange can feeds and medicines restart, and who confirms that the tube is in the right place?
- If the new tube is balloon-retained, how often should the balloon water be checked, and who will teach us to do it?
- What is the planned interval for the next exchange, and what should prompt us to bring it forward?
- Can a caregiver be trained to replace a dislodged balloon tube at home, and will we be given a spare?
- What is the fastest way to reach the team out of hours if the tube blocks or comes out?
- Has anyone reviewed whether I still need a tube at all, or whether a swallow reassessment is due?
- Which of the risks you have described is the one you are most trying to avoid with the plan you are recommending?
Write the answers on the same sheet that records the tube type. Bring it to every appointment, and keep a photograph of it on your phone. When something goes wrong on a weekend, that sheet does more to speed things along than anything else you own.
When to call your doctor
Most tube problems are inconvenient rather than dangerous, and most can wait for a daytime call. A small number cannot, and the distinction is worth learning by heart.
Seek urgent care, by emergency services if necessary, for any of the following:
- Severe or worsening abdominal pain after an exchange or after a feed, especially with a rigid or swollen abdomen, fever, or vomiting. This can signal that the tube is not in the stomach or that the stomach lining has been injured.
- Bleeding from the stoma or through the tube that does not stop with gentle pressure, or vomiting blood or passing black stool.
- A tube that has come out completely, particularly if the original placement was fewer than about four weeks ago.
- Difficulty breathing, chest pain, or a new cough during or after feeding, which may point to aspiration.
- Formula or stomach fluid appearing in the dressing in large amounts, or visible in the wound rather than around the tube.
Call the care team the same day, without waiting for a routine appointment, for a blockage that has not cleared after two careful attempts with warm water, a tube that has stopped rotating or advancing, an external portion that looks shorter than usual, redness and warmth spreading beyond the immediate stoma, thick or foul-smelling discharge, pain on feeding that was not there before, or a balloon that will not hold water.
MedlinePlus and Johns Hopkins patient guidance both list these signs as reasons to contact the team promptly. When in doubt, call. The person on the other end would far rather hear about a problem that turns out to be minor than about one that was watched overnight. Every decision about clearing, replacing or removing a tube rests with the treating team, and they can only make it if they know.
Frequently asked questions
How often should a PEG tube be changed?
It depends on the tube type. A bumper-retained PEG is changed when it wears, blocks or develops a complication, not on a set schedule, and many last well over a year. Balloon-retained tubes and low-profile buttons are exchanged at intervals set by the manufacturer, usually every few months, because the balloon gradually weakens. Your team records the type and interval at follow-up.
What should I do if my PEG tube is blocked?
Start with warm water in a large syringe, using a gentle push-and-pull rocking motion rather than force, then clamp the tube and let the water sit before trying again. Avoid small syringes, sharp objects and acidic drinks. If two careful attempts fail, contact your care team the same day; they may use enzyme solutions or a declogging device before considering replacement.
Can a PEG tube be replaced at home?
Sometimes. Balloon-retained tubes in a mature tract can be exchanged by a trained caregiver at home, and many services teach this and supply a spare tube. Bumper-retained PEG tubes usually require a clinic or endoscopy unit, because the internal disc may need endoscopic removal. Never attempt a home change unless your team has trained you for that specific tube.
What is buried bumper syndrome?
Buried bumper syndrome occurs when the internal disc of a bumper PEG migrates into the stomach wall and tissue grows over it, usually because the tube was fixed too tightly or the abdominal wall thickened. Signs include a tube that will not rotate or advance and leaking or pain on feeding. It is confirmed by endoscopy or imaging and removed by the team, never pulled at home.
My PEG tube fell out. How long do I have?
Treat it as a same-day problem. The tract starts to narrow within hours, so contact your care team immediately and, if you have been shown how, cover the stoma or gently keep it open with a spare or the old tube without feeding through it. Reinsertion is simplest in a mature tract within a few hours; an early or closing tract needs imaging or endoscopy.
Does a PEG tube replacement hurt?
A bedside balloon exchange typically causes brief discomfort as the old tube slides out and the new one goes in, followed by mild soreness for a day or two. Endoscopic exchanges use light sedation, so the procedure itself is not usually felt, though a sore throat and drowsiness are common afterward. Persistent or severe pain is not expected and should be reported promptly.
Why does my PEG tube leak and would a bigger tube help?
Leaking usually means the tract has stretched or the stomach is emptying slowly, not that the tube is too small. Guidelines advise against upsizing, because a wider tube stretches the tract further and the leak returns. The team looks for causes such as constipation, coughing, poor fixation or slow gastric emptying, and may rest the tract briefly before replacing a same-size tube.
How soon can I feed after a PEG tube replacement?
Feeding usually restarts once the team has confirmed the new tube is in the stomach, often within hours of a bedside balloon change and later the same day after an endoscopic exchange. Some units wait longer if a rigid bumper removal caused bleeding. Follow the specific timing your treating team gives you rather than a general rule.
What are the signs a PEG tube is wearing out?
Look for yellowing, stickiness or cracks in the tubing, a connector that no longer grips the syringe, feeds that dribble at the join, flushes that take noticeably longer, a tube that has become stiff or hard to rotate, and repeated blockages despite good flushing. None of these is an emergency on its own, but together they suggest an exchange should be planned.
Can a PEG tube be removed instead of replaced?
Yes, if the person no longer needs tube feeding, for example after swallowing recovers following a stroke. That decision involves the speech and language team, the dietitian and the treating physician, usually after a formal swallow assessment. In a mature tract the tube is removed and the opening typically closes on its own over days, with the team monitoring the site.
References
- MedlinePlus – Feeding tube insertion – gastrostomy
- MedlinePlus – Gastrostomy feeding tube – bolus (care and flushing instructions)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Which Tests Come Before a GERD Treatment Plan? Endoscopy, pH Monitoring and Manometry
GERD testing before treatment usually starts with a history and physical exam; many people begin acid-suppressing therapy without any test. Doctors typically order an…

Lactose Intolerance Over the Years: What Improves, What Persists and How Care Adjusts
Lactose intolerance is usually long term when it comes from the normal, genetically programmed decline in the lactase enzyme after early childhood; that form…

Digestive Enzymes: Who Actually Needs Them and Who Is Wasting Money
Digestive enzyme supplements help a specific group of people: those with exocrine pancreatic insufficiency (from chronic pancreatitis, cystic fibrosis or pancreatic surgery), who need…

Silent Reflux: The Throat-Clearing, Hoarse-Voice Reflux Many People Never Suspect
Silent reflux, known clinically as laryngopharyngeal reflux (LPR), happens when stomach contents travel up past the esophagus and irritate the throat and voice box,…

What Hepatitis B Blood Tests Show: Markers, Viral Load and How They Shape Your Plan
A hepatitis B viral load test measures how much hepatitis B virus DNA is circulating in a set volume of blood, usually reported in…

Recovering After a Gastrointestinal Bleed: Anemia Checks, Diet Steps and Regaining Energy
Recovery after a GI bleed usually unfolds over weeks rather than days. The lining heals first, then the blood count and iron stores follow,…