

When Can You Walk After Robotic Hip Replacement? From Walker to Crutches to Unaided

Key Takeaways
- Most people stand and take supported steps within 24 hours of hip replacement, often on the day of surgery, according to NHS and Mayo Clinic guidance.
- Robotic assistance improves the precision of implant placement; mainstream guidance gives the same walking and recovery ranges whether or not a robot was used.
- A walking stick belongs in the hand opposite the operated hip, where it stops the pelvis dropping and protects recovering gluteal muscles.
- The NHS describes many people returning to driving and lighter work around six weeks, while strength and stamina keep improving for months afterward.
- Days two and three are commonly the toughest because local anesthetic has worn off and swelling peaks, so the second week usually feels noticeably easier.
- Every step squeezes the calf muscles and lowers clot risk, which the CDC identifies as highest in the weeks after hip surgery, so short frequent walks are prevention as well as rehabilitation.
Most people stand and take their first supported steps within 24 hours of robotic hip replacement, often the same day, using a walker or frame. Many move to crutches or a single stick over the following days to weeks, and a majority walk unaided by around six to twelve weeks. Exact timing depends on the surgical approach, anesthesia, strength before surgery and your team's instructions.
The first question is rarely about the robot. It arrives in the pre-op clinic, usually from the person holding the coat and the car keys: ‘So when does she actually get up?’ The surgeon has just spent ten minutes on CT planning, cup angles and a robotic arm that holds the reamer steady, and the family wants to know about the hallway.
It is the right question. Walking after robotic hip replacement is the thing you will notice first and measure yourself against for months, and it follows a fairly predictable arc: a frame in the corridor, crutches in the kitchen, then one day you realize you left the stick by the door and did not go back for it.
What follows is that arc, stage by stage, with the honest caveat that the robot changes how the implant is placed far more than it changes how quickly your muscles trust the new joint.
What actually happens in robotic hip replacement, and why the robot walks nobody
A total hip replacement swaps the worn ball-and-socket joint for an artificial one: a cup in the pelvis (the acetabular component) and a stem with a ball inside the thigh bone (the femoral component). The Mayo Clinic describes the operation as removing damaged bone and cartilage and replacing them with metal, ceramic or very hard plastic parts. That part is identical whether or not a robot is in the room.
The ‘robotic’ label describes planning and precision, not an autonomous machine. Before surgery, a CT scan or advanced imaging builds a three-dimensional model of your pelvis and femur. The surgeon uses that model to plan the size of the components, the angle of the cup and how the leg length will be restored. During the operation, a robotic arm helps the surgeon keep the reaming and cup placement within that plan, resisting movement outside the intended zone. The surgeon still makes the incision, still prepares the bone and still decides when the fit is right.
Why does this matter for walking? Because the things that let you stand on day one are the anesthetic wearing off, pain being controlled, the muscles around the hip being intact enough to steady you and a physiotherapist showing you how to load the leg. Component position matters for how the hip feels over years and for dislocation risk. It does not shorten the hours between the operating room and your first steps in any way that has been proven in mainstream evidence.
So when someone says a robot means you will ‘walk out the same day’, treat that as a description of a well-run recovery pathway, not a property of the technology.
Walking after robotic hip replacement: what the first 24 hours usually look like
Picture the afternoon of surgery. The spinal or general anesthetic has faded enough that you can feel and move your feet. A nurse checks your blood pressure sitting up, then standing, because the first hazard on day one is not the hip but a drop in blood pressure that makes you lightheaded. If that check is fine, a physiotherapist or nurse brings a walking frame to the bedside.

The NHS notes that most people are helped to get up and walk on the day of the operation or the day after, and the Mayo Clinic describes the same expectation. The first walk is short: from bed to chair, then a few meters along the corridor with someone beside you. You will be shown how to sit down slowly, which leg to lead with and how to keep the operated leg from crossing the midline if your surgeon has given hip precautions.
What surprises people is how normal weight-bearing is. Most modern hip components are fixed so that full weight-bearing is allowed straight away, unless the bone was fragile or a fracture was repaired. Your team will tell you clearly if any restriction applies; assume full weight is allowed only when they say so.
By the evening, many people have walked twice. By the next morning, the goal is usually the bathroom independently with the frame, then the corridor again. Same-day discharge exists in some pathways, but the NHS describes a typical hospital stay of a few days, and the right length is the one your team judges safe for you, not the shortest one you read about.
Walker to crutches to unaided: what each stage means and how you progress
Walking aids are not a ranking of how well you are doing. They are tools chosen for balance, pain and confidence at each moment, and the order below is typical rather than fixed. Some people skip the frame entirely; others keep a single stick outdoors for months by preference.
| Stage | Typical window | What it does for you | Common sign you are ready to move on |
|---|---|---|---|
| Walking frame or walker | Day of surgery to first days | Four points of contact for blood-pressure dips, wobbly balance and early pain | Walking corridor lengths without leaning heavily on the frame |
| Two crutches or two sticks | First days to a few weeks | Offloads the hip while letting you walk with a more natural arm swing | Even step lengths and a pain-controlled gait |
| One crutch or one stick, held on the opposite side | Roughly weeks two to six, varies widely | Steadies the pelvis so the hip muscles are not overworked | No limp when the stick is lifted for a few steps |
| Unaided | Often by 6–12 weeks | Full independence indoors, then outdoors | Cleared by your physiotherapist or surgeon |
The timing figures in the table draw on recovery guidance from the NHS, the Mayo Clinic and Cleveland Clinic, which describe most people returning to everyday activities within about six to twelve weeks. They are ranges, not targets.
Two rules make the transitions safer. First, the stick goes in the hand opposite the operated hip, which feels wrong until you try it and notice the pelvis stop dipping. Second, the change of aid is decided in daylight with your physiotherapist, not at night on a trip to the bathroom.
How long does it take to recover from a robotic hip replacement?
Recovery has two clocks, and mixing them up causes most of the disappointment. The short clock is function: sitting, standing, walking, dressing. The long clock is strength and endurance, and it runs for months after the wound has healed.
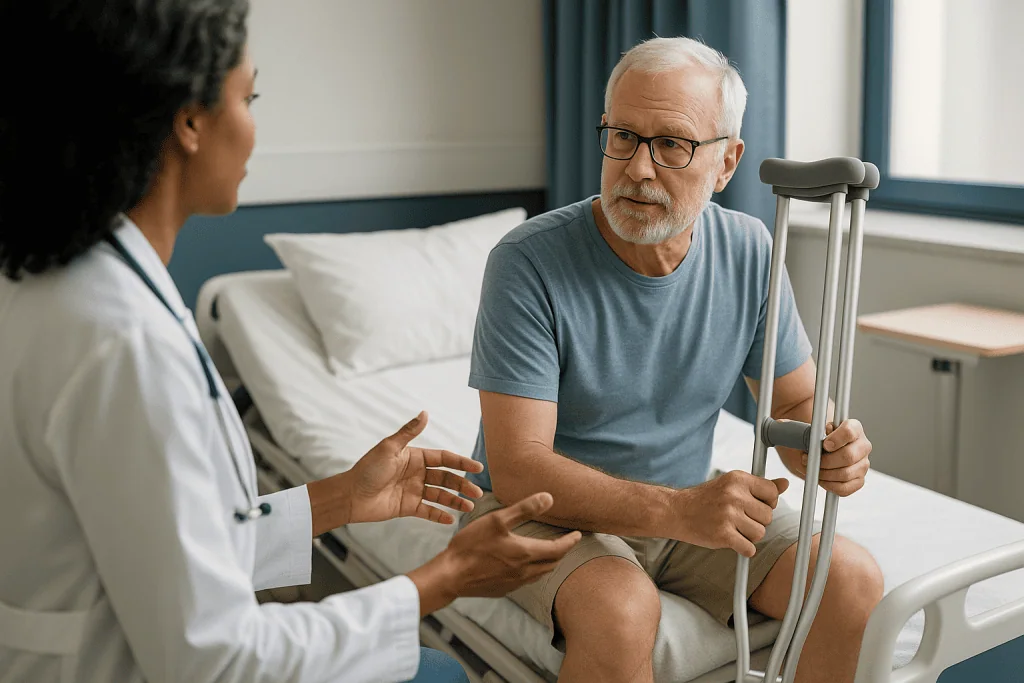
On the short clock, the NHS describes leaving hospital within days, walking with a frame or crutches at home, and many people returning to driving and lighter work around six weeks, always subject to their surgeon’s advice. Cleveland Clinic gives a similar picture, describing most people back to usual daily activities within roughly six to twelve weeks. The Mayo Clinic notes that people are typically doing well by around three months, while adding that individual recovery varies.
On the long clock, the muscles that stabilize the pelvis (the gluteal muscles at the side and back of the hip) had often spent years working around a stiff, painful joint. They do not wake up because the joint is new. They rebuild through repetition: standing on one leg at the kitchen counter, stepping up a stair, walking a little further each week. Many people keep noticing gains in stamina and in the smoothness of their gait well past the three-month mark.
Where does ‘robotic’ fit? The evidence base on robotic assistance concentrates on how accurately the components are placed. Whether that accuracy translates into faster walking milestones in the first weeks has not been shown consistently in mainstream guidance, and no major body sets a separate, shorter timeline for robotic cases. Plan your recovery with the standard hip replacement ranges above, and let any earlier progress be a pleasant surprise rather than an expectation.
Who is usually up and walking early, and who is usually asked to wait
Two people can have the same operation on the same morning and walk very differently by evening. The differences are rarely mysterious.
Early walkers tend to share a few features. They were still walking regularly before surgery, even if slowly and with pain, so their leg muscles and balance were in use. They have no restriction on weight-bearing because the implant is press-fit or cemented into sound bone. Their blood pressure behaves when they stand. Their pain is controlled without heavy sedation. They live in a body that has done stairs recently.
People who are often asked to wait, or to progress more slowly, include those whose surgeon has set partial weight-bearing because the bone was thin, a fracture was fixed at the same time or a bone graft was used. The surgeon will say exactly how much weight the leg may take, and a physiotherapist will teach you what that feels like through your foot. Others include people with significant heart or lung conditions who need a slower mobilization while the anesthetic clears, people with balance disorders or neuropathy who need extra supervision, and anyone whose blood pressure keeps dropping on standing.
Age alone is not a reason to wait. The NHS and the Mayo Clinic both describe hip replacement for a wide range of adults, and the day-one goal of standing with a frame is the same for a person in their fifties as for a person in their eighties. What changes is the pace of progression and how much supervision is wise.
If you are told to wait or to limit weight, ask why in one sentence, and ask what will signal that the restriction can be lifted. A restriction with a reason is much easier to respect than one that feels arbitrary.
Can you do too much walking after a hip replacement?
Yes, and the way it shows up is specific. Overdoing it rarely damages the implant, which is designed for decades of steps. It shows up as a hip that is hotter and more swollen the next morning, a limp that had gone and has come back, and a night of poorer sleep because the thigh aches when you turn.
The pattern to aim for is frequent and short rather than rare and long. In the first two weeks, the NHS and MedlinePlus discharge guidance both describe walking several times a day around the home, gradually increasing distance, alongside the specific exercises your physiotherapist gives you. A useful test is the 24-hour rule: if pain or swelling after a walk has not settled back to your baseline by the next morning, the walk was too long, and the next one should be shorter, not skipped.
Swelling in the thigh and calf is expected for weeks. It comes from surgical bleeding into the tissues and from fluid pooling when you are upright. Lying with the leg raised for twenty minutes a few times a day helps, and so does the calf pumping that comes with walking itself. New, one-sided calf swelling with tenderness is a different matter and belongs in the red-flag section below.
The other version of ‘too much’ is walking badly for a long time. A limp that you push through for an hour teaches the pelvis to drop and the spine to compensate. Better to walk ten good minutes with a stick than forty limping minutes without it. The stick is not a setback; it is how you protect the pattern you are trying to build.
What is the hardest day after hip replacement?
Ask a ward nurse and you will usually hear ‘day two or three’. Ask someone six months out and they may say ‘the first night at home’. Both are right, and neither is the day of surgery.
On the operating day, the spinal or regional anesthetic is still doing much of the work, and local anesthetic infiltrated around the joint by the surgeon often lasts into the night. By the second and third day those effects have gone, the tissues are at their most swollen and bruised, and you are moving more, so you feel more. This is when the thigh feels heavy and the outside of the hip is tender to lie on. It is expected, and it is also the point at which walking short distances several times a day starts to feel like a chore rather than a novelty.
The first night at home is hard for a different reason. Hospital beds are high and firm and have rails; your own bed is low and soft and has a cat on it. Getting in and out without bending the hip past the angle your team allowed takes concentration. A firm chair with arms, a raised toilet seat and a bed you can sit on with your feet flat on the floor make a real difference, and MedlinePlus lists exactly these adjustments in its discharge guidance.
The honest reassurance is that the trajectory turns around quickly. Most people describe the second week as noticeably easier than the first, with pain becoming a background ache rather than the main event. If it is going the other way, worsening rather than easing after the first few days, that is a call to your team, not a sign you should push harder.
Is it okay to sleep on my side after a hip replacement, and what are hip precautions?
Hip precautions are movement limits designed to stop the new ball slipping out of the new cup before the soft tissues around the joint have healed. Whether you get them, and for how long, depends mainly on the surgical approach: the direction the surgeon used to reach the joint.
With a posterior approach (from the back), MedlinePlus describes the classic set: do not bend the hip past a right angle, do not cross the legs or ankles, and do not turn the operated foot inward. With an anterior approach (from the front), the risky movements are different and some surgeons use fewer restrictions. Your own list is the only one that counts.
On sleeping, MedlinePlus advises lying on your back at first, or on the non-operated side with a pillow between the knees so the operated leg cannot drop across the midline. Sleeping directly on the operated side is usually uncomfortable in the early weeks because the incision and the tender muscle on the outside of the hip take the pressure. Many people are told it is permitted once the wound has healed and it no longer hurts, but the timing is your surgeon’s decision.
A few practical points that help the first weeks:
- A pillow between the knees at night keeps the hip in a safe, neutral position without effort.
- A long-handled shoehorn and a sock aid let you dress without folding forward past the allowed angle.
- Sit in chairs where your knees sit at or below your hips; low sofas are the commonest place people break the rule without noticing.
Precautions usually ease over the first six to twelve weeks, but ask your team for the date and the reason rather than assuming.
Stairs, getting into a car and walking outdoors: the milestones after the ward
The ward corridor is flat, well lit and has handrails. Your street is none of those things, so the transitions after discharge deserve their own attention.
Stairs come before discharge in most pathways. The physiotherapist teaches a rhythm that most people remember with a rhyme: up with the good leg first, down with the operated leg first, with the crutch or stick moving with the operated leg. If your home has stairs, you will usually be asked to climb a flight on the ward before you are cleared to leave. Once home, treat the stairs as a task to be done a few times a day with purpose, not a place to linger.
Getting into a car is where hip precautions are easiest to break. The technique is to push the seat back and recline it slightly, back into the seat with the operated leg extended, then swing both legs in together, keeping the knees apart. A plastic bag on the seat helps you pivot. Driving itself is separate from being a passenger: the NHS describes many people returning to driving around six weeks after surgery, when they can control the pedals and perform an emergency stop, and your surgeon and insurer have the final say.
Walking outdoors adds slopes, curbs, uneven paving and wind. Keep the stick outdoors longer than indoors if it gives you confidence; there is no prize for being early. A first outdoor walk of a few minutes to the end of the road and back, on a dry day with someone alongside, is a sensible template. Distance grows week by week, and the 24-hour swelling rule from earlier applies just as much outside as in.
Pain control and anesthesia: how they shape walking after robotic hip replacement
You cannot walk well on a hip you cannot bear to load, and you cannot walk safely when you are too drowsy to trust your feet. The art of early mobilization sits between those two problems.
Most modern hip replacement pathways use a spinal anesthetic (an injection into the lower back that numbs the legs for a few hours) or a general anesthetic, often combined with local anesthetic placed around the joint by the surgeon. The Mayo Clinic and Cleveland Clinic both describe this layered approach. The local anesthetic is why the first evening can feel better than the second day; it fades, and the regular pain plan has to take over.
That plan is usually built in layers rather than relying on one strong medicine. Anti-inflammatory medicines, if your kidneys and stomach allow them, dampen the swelling that drives much of the ache. Paracetamol-type medicines add a steady background effect. Opioid medicines are reserved for breakthrough pain and for the hour before physiotherapy, because their trade-off is drowsiness, constipation and a higher fall risk. Which layers you receive, and for how long, is a decision for the prescribing clinician who knows your history. Never change a prescribed medicine on your own account because a website suggested it.
A practical rhythm used on many wards: take your scheduled pain medicine, wait for it to work, then walk. Ice packs wrapped in a cloth on the outer hip for fifteen to twenty minutes after walking help many people; MedlinePlus lists cold therapy among sensible home measures. Aim for pain that is present but manageable, roughly a score you would call moderate rather than severe, so that you can concentrate on your gait rather than on the pain.
Blood clots after hip replacement: why walking is prevention, not just recovery
A deep vein thrombosis (DVT) is a clot in the deep veins of the leg; a pulmonary embolism is a piece of that clot that travels to the lungs. Hip replacement is one of the higher-risk operations for both, which is why clot prevention starts before you leave the operating room.
The CDC lists major surgery, especially of the hip and knee, and prolonged immobility among the leading risk factors for these clots, with risk highest in the weeks after surgery. Three things reduce it. The first is movement: every step squeezes the calf muscles and pushes blood back toward the heart, which is why walking on the day of surgery is framed as clot prevention as much as rehabilitation. The second is mechanical: compression stockings or inflatable calf sleeves in hospital. The third is medicine: most people go home on an anticoagulant, a medicine that makes blood less likely to clot, for a period set by the surgical team. The class, the duration and any monitoring are decisions for your clinicians.
Between walks, the ankle pumps you were taught matter more than they feel like they should. Pointing the toes down and pulling them back up twenty times each hour you are sitting keeps the calf pump active. Long, motionless spells in a reclining chair are the habit to avoid in the first weeks.
Signs that need same-day medical attention include new swelling, warmth or pain in one calf or thigh that is different from the general surgical swelling, and, more urgently, sudden breathlessness, chest pain or coughing up blood. Those last three are emergencies, and the right response is emergency services, not waiting for the clinic to open.
What people often get wrong about walking after robotic hip replacement
Myths gather around any operation with a good reputation, and this one has collected a set of its own.
‘The robot means faster recovery.’ Robotic assistance is about placing the components accurately according to a plan. Mainstream guidance from the Mayo Clinic, the NHS and Cleveland Clinic gives the same walking and recovery ranges regardless of whether a robot was used. Any speed advantage in the first weeks remains unproven.
‘Using a stick means I am behind.’ A stick in the opposite hand stops the pelvis dropping and protects the gluteal muscles while they recover. Walking well with a stick beats limping without one, and the stick usually retires itself when it is no longer needed.
‘No pain means I can do anything.’ Good pain control, especially in the first days when local anesthetic is still active, can outrun what the tissues are ready for. Follow the distance and precaution guidance, not the absence of pain.
‘Full recovery means six weeks.’ Six weeks is roughly when many people drive and return to lighter work, per the NHS. Strength and stamina in the hip muscles keep improving for months.
‘I should rest the leg for the first week.’ The opposite is true. Short, frequent walks from day one are the standard advice in NHS and MedlinePlus discharge guidance, both for the hip and for preventing clots.
‘Hip precautions are for life.’ Most are temporary, tied to soft-tissue healing, and are eased by your surgeon. The long-term advice is simpler: stay active, keep your weight where your team recommends and report any new pain or instability.
‘Both hips replaced means twice as long.’ Not necessarily, but it is a different recovery with more supervision, and it needs its own plan from your team.
Questions to ask your care team before and after surgery
The pre-assessment clinic and the first physiotherapy session are the two moments when a short list of questions changes the whole recovery. Bring these written down; the answers are specific to you, and they will not match a general article exactly.
- Which surgical approach are you planning, and does that mean I will have hip precautions? For how long?
- Am I allowed to put my full weight through the leg from day one, or is there a limit, and what is the reason?
- Which walking aid will I start with, and who decides when I change to the next one?
- How many times a day should I walk in the first two weeks, and how do I know a walk was too long?
- Which exercises matter most in the first month, and which can wait?
- How long will I take a clot-prevention medicine, and what signs of a clot should I look for?
- How is my pain plan layered, and which medicine should I time before physiotherapy?
- When is it reasonable for me to sleep on my operated side?
- What is your guidance on driving, and on when I can be a passenger in a low car?
- What does my follow-up schedule look like, and who do I call outside clinic hours?
One more question is worth asking directly, because people are often shy about it: ‘What would make you want to see me sooner than planned?’ The answer gives you a personal red-flag list to sit alongside the general one below, and it tells you that calling is expected, not a nuisance.
Write the answers on the discharge paperwork so the information travels with you, and share it with whoever will be at home in the first week. A second pair of ears at the physiotherapy session is worth more than any leaflet.
When to call your doctor: red-flag signs after hip replacement
Most of what you feel in the first weeks is expected: an aching thigh, a tender outer hip, bruising that drifts down toward the knee, swelling that is worse by evening and better by morning. The signs below are different in kind, not just degree, and they are the reasons to pick up the phone rather than wait for the next appointment.
Call your surgical team or seek same-day care if you notice:
- A fever, chills or feeling generally unwell in the days after discharge.
- Increasing redness, warmth, swelling or opening at the wound, or any discharge that is cloudy, colored or smells.
- Pain that is getting worse rather than easing after the first few days, or pain that no longer responds to your prescribed plan.
- New calf or thigh swelling and tenderness on one side that is different from your general surgical swelling.
- A sudden inability to bear weight on the leg, a leg that suddenly looks shorter or turned, or a popping sensation with severe pain, which can signal dislocation.
- New numbness, weakness or a foot that drags, which can indicate nerve irritation.
Call emergency services immediately for sudden breathlessness, chest pain, coughing up blood, fainting or a rapid heartbeat. The CDC lists these as signs of a clot reaching the lungs, and the time to act is minutes, not hours.
A fall in the first weeks, even one that seemed minor, also warrants a call so your team can decide whether an examination or X-ray is needed. The guidance across MedlinePlus, the NHS and the Mayo Clinic is consistent: your treating team would rather hear from you about something that turns out to be nothing than not hear about something that mattered. Every decision about the next step, including whether to change any medicine or restriction, sits with them.
Frequently asked questions
When can I walk unaided after hip replacement?
Many people walk without any aid indoors somewhere between six and twelve weeks, with outdoor confidence often following a little later. The Mayo Clinic and Cleveland Clinic describe most people returning to usual daily activities within that window. The decision is made with your physiotherapist or surgeon, based on whether you walk without a limp when the stick is lifted, not on a calendar date.
What is the typical hip replacement recovery time?
Function returns in weeks, strength in months. The NHS describes a hospital stay of a few days, walking with a frame or crutches at home, and driving and lighter work around six weeks for many people. The Mayo Clinic notes most people are doing well by about three months, while gains in stamina and gait smoothness can continue beyond that. Individual timelines vary with approach, health and prior activity.
How long does it take to recover from a robotic hip replacement compared with a standard one?
No major guideline sets a separate, shorter recovery timeline for robotic cases. The robot helps the surgeon place the cup and stem according to a CT-based plan; the anesthesia, incision, muscle recovery and rehabilitation are the same. Use the standard ranges from the NHS and Mayo Clinic, and treat any earlier progress as welcome rather than expected.
Can you do too much walking after a hip replacement?
Yes. The signs are a hip that is hotter and more swollen the next morning, a limp that returns and disturbed sleep from a heavy thigh. Frequent short walks are the standard advice in NHS and MedlinePlus guidance. A practical rule: if swelling or pain has not settled to your baseline within 24 hours, the next walk should be shorter, not skipped.
What is the hardest day after hip replacement?
Days two and three are commonly the hardest on the ward, because the local anesthetic placed during surgery has worn off and tissue swelling peaks. The first night at home is a close second, as low beds and soft chairs make hip precautions harder to keep. Most people find the second week noticeably easier; pain that worsens instead is a reason to call your team.
Is it okay to sleep on my side after a hip replacement?
Early on, MedlinePlus advises sleeping on your back or on the non-operated side with a pillow between the knees to keep the operated leg from crossing the midline. Lying directly on the operated hip is usually uncomfortable until the wound and outer hip muscle settle. Many surgeons permit it once healed and comfortable, but the timing is your surgeon’s call.
How long will I be walking with a walker after hip replacement?
Usually only days. The walker or frame covers the period when blood pressure can dip on standing and balance is uncertain, typically from the day of surgery into the first week at home. Most people then move to two crutches or sticks, and later to one stick held on the opposite side. Your physiotherapist guides each change; some people skip the frame entirely.
When can I climb stairs after hip replacement?
Most people practice stairs with a physiotherapist before leaving hospital, usually within the first few days. The pattern is up with the non-operated leg first, down with the operated leg first, with the stick moving alongside the operated leg. If your home has stairs, you will typically be asked to manage a flight on the ward before discharge.
Why is walking so important for preventing blood clots after hip surgery?
Each step contracts the calf muscles and pushes blood back toward the heart, which counters the pooling that lets clots form. The CDC identifies hip and knee surgery and immobility as leading risk factors, with risk highest in the weeks after the operation. Walking works alongside compression devices and any anticoagulant medicine your team prescribes, not instead of them.
What are the signs of dislocation after hip replacement?
Sudden severe pain in the hip, a popping or shifting sensation, a leg that suddenly looks shorter or turned inward or outward, and an inability to bear weight are the classic signs. Dislocation is uncommon but needs urgent assessment, so call your surgical team or emergency services rather than trying to move the leg back yourself.
References
- NHS: Hip replacement, recovery
- MedlinePlus: Hip replacement, discharge
- Cleveland Clinic: Hip replacement
- CDC: About venous thromboembolism (blood clots)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Flying Home After Joint Replacement: Timing, Clot Precautions and Airport Metal Detectors
Most people can fly after joint replacement once they are walking independently, their wound is settled and their surgical team has cleared them, which…

What Does Foot Deformity Surgery Recovery Involve? From Cast to Special Shoe to Walking
Foot deformity surgery recovery usually moves through stages: a cast, splint or boot that protects healing bone for the first weeks, then a stiff…

Diaper Changes, Bathing and Dressing With a Pavlik Harness: A Daily Care Guide for Parents
During Pavlik harness diaper changes, the harness stays on and the diaper goes underneath the leg straps. Lift your baby by sliding a hand…
How Is Hip Replacement Surgery Performed? The Operation Explained From Incision to Closure
Hip replacement surgery is done by removing the worn ball-and-socket joint and fitting an artificial one. Under spinal or general anesthesia, the surgeon makes…

Recovery After Trauma Surgery: Why Physiotherapy Starts Early and How Milestones Are Set
Trauma surgery recovery usually begins within a day of the operation, when a physiotherapist helps the patient sit, breathe deeply and, where the repair…

Total vs Partial Shoulder Replacement: Which Joint Surfaces Are Replaced and Why
A total shoulder replacement resurfaces both sides of the ball-and-socket joint: the rounded top of the upper arm bone and the shallow socket on…