

When Does Thyroid Disease Need an Endocrinologist? From Routine Checks to Specialist Care
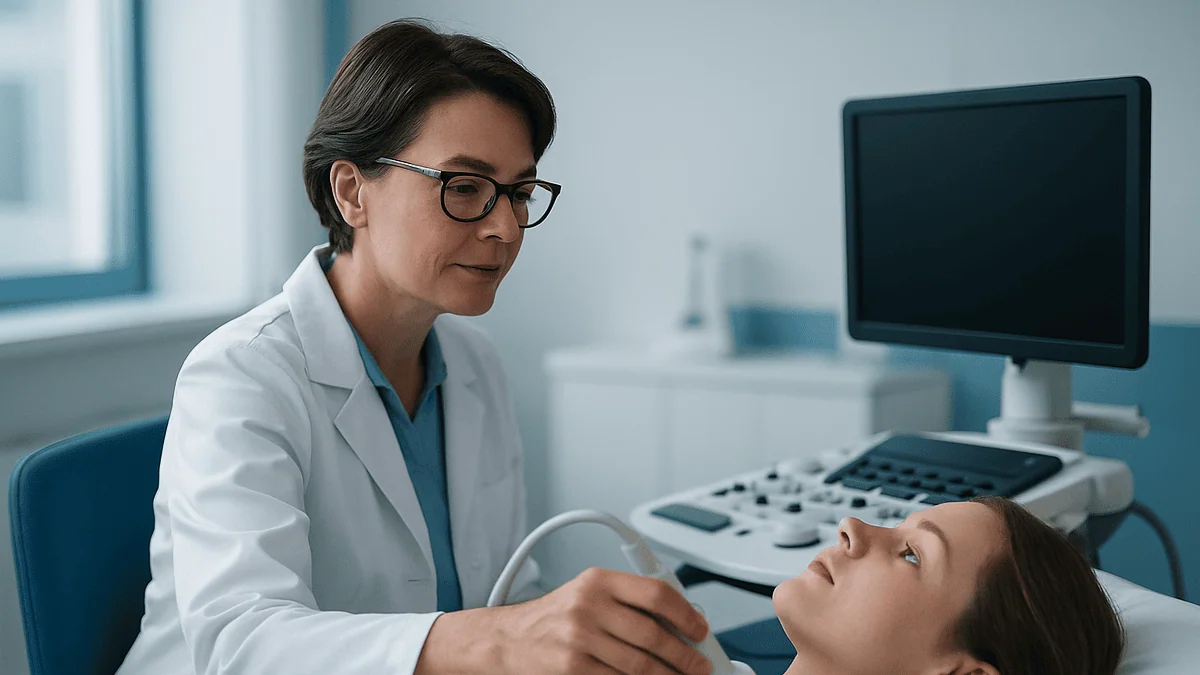
Key Takeaways
- Nearly five in a hundred Americans aged twelve and older have hypothyroidism, and the large majority are managed entirely in primary care with an annual blood test once stable.
- Hyperthyroidism, thyroid nodules, pregnancy and childhood thyroid disease are the four situations in which specialist referral is standard rather than optional across NHS and NIDDK guidance.
- TSH is rechecked roughly six to eight weeks after any change in hormone replacement because that is how long the blood level takes to reach a steady state.
- A single mildly raised TSH in someone who feels well is usually repeated rather than treated, since illness, sleep loss and time of day all shift the value.
- The Mayo Clinic describes thyroid nodules as very common with only a small percentage cancerous; ultrasound grading, not surgery, is the usual first step.
- Fever or severe sore throat while taking antithyroid medicine warrants an urgent blood count, because it can signal a rare but serious drop in white blood cells.
Most thyroid disease is managed well by a primary care clinician with periodic blood tests. Referral to an endocrinologist is usually considered for an overactive thyroid, a thyroid nodule or enlarged gland, thyroid problems before or during pregnancy, symptoms that persist despite normal blood results, hypothyroidism that is hard to stabilize, thyroid disease in children, or suspected thyroid cancer. The referral decision rests with your treating clinician.
The lab result arrives in the patient portal before the doctor has a chance to call. One line is flagged in red: TSH, slightly above the reference range. By evening, a search history that began with “what is TSH” has drifted to “when to see an endocrinologist for thyroid,” and a small, ordinary blood test has grown into a question about whether you need a specialist at all.
It is a fair question, and the honest answer is more interesting than yes or no. The thyroid is one of the few organs whose most common disorder can be handled almost entirely by numbers, a well-chosen tablet and a yearly check. It is also one of the few organs whose less common disorders genuinely reward the attention of someone who thinks about hormones all day.
Knowing which side of that line you are on saves worry, saves appointments and, occasionally, saves a diagnosis from being missed. This article walks through that line as the major guideline bodies describe it.
What does an endocrinologist actually do for the thyroid?
An endocrinologist is a physician who trained first in internal medicine and then spent additional years studying glands and the hormones they release. The thyroid is one of those glands: a butterfly-shaped organ low in the front of the neck that releases two hormones, thyroxine (T4) and triiodothyronine (T3), which set the pace of nearly every cell’s energy use.
That pace is regulated from above. The pituitary gland in the brain releases thyroid-stimulating hormone (TSH), which tells the thyroid to make more or less. When thyroid hormone runs low, TSH climbs; when it runs high, TSH falls. This inverse relationship is the reason a single TSH value carries so much weight in thyroid care, and why interpreting it well is a skill rather than a lookup.
So what does the specialist add? Three things, mostly. The first is pattern recognition across unusual combinations of results, such as a normal TSH alongside a low T4, which points toward the pituitary rather than the thyroid itself. The second is comfort with treatments that carry more consequence, including antithyroid medicines, radioactive iodine and coordinating with surgeons. The third is experience with the hard edges of thyroid disease: pregnancy, children, thyroid eye disease, nodules and cancer follow-up.
What an endocrinologist does not do is replace your primary care clinician for routine hypothyroidism. Guidance from the National Institute of Diabetes and Digestive and Kidney Diseases describes underactive thyroid as a condition typically diagnosed and treated in general practice, with specialist input reserved for specific situations. That division of labor is not a shortcut. It reflects how predictable the common form of the disease usually is.
When to see an endocrinologist for thyroid: the situations most guidelines agree on
Across NHS, NIDDK and major clinic guidance, a consistent shortlist emerges. None of these means something is seriously wrong; each means the decision-making benefits from a specialist’s judgment.
- An overactive thyroid (hyperthyroidism). Treatment choices carry trade-offs that are best weighed by someone who manages them regularly, and the NHS routinely routes these patients to a specialist.
- A thyroid nodule, lump or visibly enlarged gland (goiter). Most nodules are benign, but deciding which ones need an ultrasound-guided needle biopsy is specialist territory.
- Thyroid disease before, during or soon after pregnancy. Hormone needs shift across trimesters and matter for the developing baby.
- Hypothyroidism that will not settle. If blood tests keep swinging despite consistent treatment, or you still feel unwell once they are normal, a second set of eyes is reasonable.
- Unusual laboratory patterns. Results that do not fit the usual inverse TSH relationship raise the possibility of a pituitary cause.
- Thyroid disease in a child or teenager. Growth and development add a layer that pediatric endocrinologists are trained for.
- Known or suspected thyroid cancer, or a personal history of neck radiation.
- Thyroid eye disease, where bulging, gritty or double vision accompanies Graves’ disease.
Notice what is missing from that list: a single mildly abnormal TSH in someone who feels well. Guidance from the NHS advises repeating the test rather than acting on one result, because TSH fluctuates with illness, sleep loss and even time of day. If your clinician suggests waiting a few weeks and rechecking, that is not dismissal. It is the standard first move.
How thyroid testing works, and what the numbers can and cannot tell you
Almost every thyroid decision begins with a blood test, so it helps to understand what is being measured. TSH is usually checked first. Because the pituitary reacts to tiny shifts in thyroid hormone, TSH often moves before symptoms appear, which makes it a sensitive early signal. If TSH is abnormal, laboratories typically add free T4, the active hormone circulating unbound in the blood, and sometimes T3.

Reading the pair together is where interpretation lives. A high TSH with a low free T4 is classic primary hypothyroidism: the gland is underperforming and the pituitary is shouting. A low TSH with a high free T4 is overt hyperthyroidism. A high TSH with a normal free T4 is called subclinical hypothyroidism, a gray zone in which the gland is compensating and guidelines often favor monitoring over treatment, depending on how high the TSH sits, whether antibodies are present and whether pregnancy is planned.
Antibody tests add a layer of explanation rather than urgency. Thyroid peroxidase antibodies point toward Hashimoto’s disease, the autoimmune cause behind most hypothyroidism in iodine-sufficient countries, according to NIDDK. TSH receptor antibodies suggest Graves’ disease, the most common cause of hyperthyroidism.
What the numbers cannot do is measure how you feel. Fatigue, weight change and low mood overlap with dozens of other conditions, and a normal thyroid panel does not rule those out. A specialist’s contribution is often knowing when to stop testing the thyroid and start looking elsewhere.
Imaging enters only when the gland’s structure is in question. Ultrasound describes a nodule’s size, edges and internal texture; a radioactive iodine uptake scan shows whether an overactive gland is uniformly busy or driven by one hot spot. Neither is needed for uncomplicated hypothyroidism.
Endocrinologist vs primary care for thyroid: who is usually managed where, and who is asked to wait
The clearest way to think about this is by likelihood of surprise. Where the course is predictable, primary care is not just adequate but often better, because the clinician who knows your blood pressure, cholesterol and sleep is watching the whole picture. Where the course can turn, a specialist earns the appointment.
Usually managed in primary care: established hypothyroidism on stable treatment with normal TSH; subclinical hypothyroidism under observation in someone who is not pregnant and feels well; a diffusely enlarged thyroid without nodules in a person with normal hormone levels.
Usually referred: newly diagnosed hyperthyroidism; any palpable nodule or ultrasound finding needing risk assessment; thyroid disease in pregnancy or during fertility treatment; children; hypothyroidism that remains unstable after repeated adjustments; suspicion of a pituitary cause; thyroid cancer at any stage.
Usually asked to wait: a single borderline TSH in someone feeling well, which the NHS and NIDDK both recommend repeating rather than treating; a normal thyroid panel with non-specific symptoms, where the more useful next step is a broader workup in primary care; or a request for a specialist opinion based on a home test or a supplement marketed for the thyroid, which most endocrinologists would want retested in a clinical laboratory first.
Being asked to wait is not the same as being told nothing is wrong. Repeating a TSH in six to eight weeks, an interval NIDDK describes for rechecking after any change, filters out the transient dips and spikes that a viral illness or a rough month of sleep can produce. It also gives your clinician a trend instead of a snapshot, and trends are what drive good thyroid decisions.
Do I need an endocrinologist for hypothyroidism? Usually not, and here is why
Hypothyroidism is common. NIDDK estimates that nearly five in every hundred Americans aged twelve and older have it, most often from Hashimoto’s disease, in which the immune system slowly damages the gland. The treatment is unusual in medicine for its simplicity: a synthetic version of the missing hormone, levothyroxine, taken to replace what the gland no longer produces.

Because the medicine is identical in action to the body’s own T4, the goal is not to suppress a disease but to restore a level. TSH is the gauge. After starting or adjusting treatment, TSH is typically rechecked after several weeks, since the hormone has a half-life of about a week and needs time to reach a steady state. Once TSH sits in range and symptoms have settled, the NHS describes moving to a blood test roughly once a year.
That rhythm, adjust, wait, recheck, then annual review, is well within the scope of primary care, and most people never need more. The realistic expectation, per NIDDK, is that symptoms begin to ease within a few weeks of reaching the right level, although some, particularly fatigue and weight changes, can lag behind the blood test.
So when does hypothyroidism justify a specialist? When the pattern breaks. Repeated dose changes without a stable result may point to absorption problems, interactions with other medicines or supplements, or inconsistent timing. Persistent symptoms despite a normal TSH deserve a wider look, sometimes at the thyroid and often at everything else. A very high TSH at diagnosis, heart disease, older age or pregnancy plans all shift the conversation toward referral. Your prescribing clinician makes those calls; the point here is that needing one is the exception.
Why hyperthyroidism is referred more often than hypothyroidism
An overactive thyroid is less common, affecting about one in a hundred Americans according to NIDDK, but it changes the referral math because the treatments are not interchangeable and each has consequences worth discussing at length.
The usual driver is Graves’ disease, an autoimmune condition in which antibodies mimic TSH and keep the gland running at full tilt. Less often the cause is one or more overactive nodules, or a temporary inflammation called thyroiditis that can swing hormone levels high and then low over months. Telling these apart matters, because thyroiditis often resolves on its own while Graves’ disease usually does not.
Three treatment routes exist. Antithyroid medicines block hormone production; the NHS notes they can take one to two months before levels begin to fall, and they carry uncommon but serious side effects that require awareness and monitoring. Radioactive iodine is swallowed as a capsule or liquid, concentrates in the gland and gradually shrinks its activity over weeks to months, frequently leading to permanent hypothyroidism that then needs lifelong replacement. Surgery removes part or all of the gland and is favored when a goiter is large, when eye disease is severe or when other options are unsuitable.
Choosing among these involves age, pregnancy plans, eye involvement, gland size and personal preference. Beta-blockers may be used alongside any of them to steady the racing heart and tremor while the underlying problem is addressed.
This is precisely the kind of layered decision an endocrinologist is trained for, and the NHS describes specialist referral as the norm once hyperthyroidism is confirmed. It is also a condition where delay has real costs, since untreated excess hormone strains the heart and thins bone.
Thyroid nodule specialist: endocrinologist, radiologist or surgeon?
Few findings unsettle people like a lump in the neck, so it is worth stating plainly what mainstream sources say. The Mayo Clinic describes thyroid nodules as very common and notes that only a small percentage turn out to be cancerous. Many are found by accident on scans ordered for something else entirely, a carotid ultrasound or a CT of the chest, and cause no symptoms at all.
The first specialist you meet is often not a person but a machine. Ultrasound characterizes a nodule by size, whether it is solid or fluid-filled, how bright it appears, whether its borders are sharp and whether it contains tiny calcium specks. Radiologists grade these features into a risk category that guides whether a fine-needle aspiration, a thin-needle biopsy done under ultrasound guidance, is warranted. Many low-risk nodules are simply measured again in a year or two.
Where does the endocrinologist fit? Typically as the coordinator. They interpret the ultrasound report alongside your blood tests, because a nodule in an overactive gland is investigated differently from one in a normal gland, and they arrange or perform the biopsy. If the result is benign, they set the surveillance interval. If it is indeterminate, they discuss further testing. If it suggests cancer, they bring in a surgeon and, when needed, a nuclear medicine team.
A surgeon, then, is rarely the first stop unless the nodule is causing swallowing or breathing difficulty from its size. The sensible sequence, in guideline terms, is ultrasound, risk grading, biopsy where indicated, then specialist discussion. Anyone with a nodule and a history of childhood radiation to the head or neck, or a family history of thyroid cancer, should expect a lower threshold for investigation.
Routine check or specialist care? A scenario-by-scenario summary
The table below distills the pathway most guidance describes. It is a map of typical practice, not a rulebook; your clinician may reasonably take a different route based on your history.
| Situation | Usual first step | Typical setting | What tends to trigger referral |
|---|---|---|---|
| Single mildly raised TSH, feeling well | Repeat test in several weeks | Primary care | Persistent rise, antibodies, pregnancy plans |
| Confirmed hypothyroidism | Hormone replacement, recheck TSH | Primary care | Unstable results, ongoing symptoms, heart disease |
| Confirmed hyperthyroidism | Confirm cause, start treatment | Endocrinology | Referral is standard once confirmed |
| Thyroid nodule found | Ultrasound and risk grading | Endocrinology or shared | Suspicious features, size, radiation history |
| Thyroid disease in pregnancy | Early, more frequent testing | Endocrinology with obstetrics | Referral is standard |
| Symptoms with normal tests | Broader medical workup | Primary care | Unusual lab pattern, pituitary suspicion |
| Child or teenager | Confirm and assess growth | Pediatric endocrinology | Referral is standard |
Two patterns stand out. Every row that involves a structural problem, a hormone excess or a second life at stake moves toward specialist care almost automatically. Every row that involves a mild deficiency in an otherwise well adult stays in primary care, at least initially.
The middle column also carries a quiet lesson: the first step is nearly always more information rather than more treatment. Thyroid medicine rewards patience in the testing phase because the gland and its pituitary supervisor respond slowly. Acting on one number tends to create a second problem while solving the first.
Pregnancy, children and older adults: when age and life stage change the answer
Three groups shift the referral threshold sharply downward, for reasons that have little to do with how sick they are.
Pregnancy. The developing baby relies on the mother’s thyroid hormone until its own gland matures, and pregnancy itself raises hormone demand. NIDDK notes that women with hypothyroidism often need adjustment during pregnancy, and that untreated deficiency is associated with complications for both mother and child. Hyperthyroidism in pregnancy is more delicate still, because treatment choices are constrained and radioactive iodine is never used. Anyone with known thyroid disease who is planning a pregnancy, or who discovers one, should expect early testing and, in most systems, coordinated care between an endocrinologist and the obstetric team. Postpartum thyroiditis, a temporary swing that can follow delivery, is another reason new mothers with unexplained fatigue or palpitations are tested.
Children and teenagers. Thyroid hormone drives growth and brain development, so pediatric thyroid disease is assessed with a different toolkit that includes growth charts and pubertal timing. Congenital hypothyroidism is screened for at birth in the United States, and children who test positive are managed by pediatric endocrinologists from the first weeks of life. Acquired disease in older children, most often autoimmune, is likewise typically referred.
Older adults. Here the logic runs the other way. TSH drifts upward with age in many healthy people, and a mildly raised value in someone in their seventies may need no treatment at all. Over-replacement carries its own risk, particularly for heart rhythm and bone density, so clinicians often accept a slightly higher TSH target. Referral is more likely when heart disease, atrial fibrillation or osteoporosis complicate the picture, not because the thyroid itself is behaving unusually.
What the first weeks after a referral to an endocrinologist for thyroid usually look like
People often picture a specialist visit as a single decisive appointment. In thyroid care it is more often the start of a short, structured cycle of testing and waiting, and knowing that in advance makes the process far less frustrating.
Before the visit. Expect to be asked for recent results and, frequently, a fresh set drawn a week or two beforehand so the specialist sees a current picture. Bring a list of every medicine and supplement you take, including iron, calcium and biotin, all of which can interfere with either absorption or the laboratory assay itself.
The consultation. Much of it is history and examination: how long symptoms have been present, family history, prior neck radiation, menstrual changes, a careful feel of the neck. If a nodule is the issue, ultrasound may be done at the same visit or scheduled shortly after. If hyperthyroidism is the issue, an uptake scan may be ordered to distinguish Graves’ disease from a hot nodule or thyroiditis.
The following weeks. Whatever is started, the body’s response is slow by design. NIDDK describes rechecking TSH roughly six to eight weeks after any change in hormone replacement, because that is how long the blood level takes to settle. For antithyroid medicine, the NHS notes that noticeable improvement commonly takes one to two months, with blood tests along the way to watch both thyroid levels and blood counts. Radioactive iodine works over weeks to months, and the follow-up schedule tracks the gradual shift toward an underactive gland.
Handing back. Once a plan is stable, many endocrinologists return routine monitoring to primary care with clear instructions on targets and when to re-refer. That handover is a sign the plan is working, not that you have been discharged from concern.
Thyroid symptoms with normal blood tests: what the evidence actually says
This is the situation that generates the most searches and the most disappointment. You feel exhausted, cold, foggy or heavier, and every thyroid number comes back in range. Does that mean the test is missing something, and is that a reason to see an endocrinologist?
Sometimes, and it helps to separate the two questions. On the first, the TSH assay is robust. It detects primary thyroid failure early and reliably, and mainstream sources including the Mayo Clinic treat a normal TSH with a normal free T4 as strong evidence against thyroid disease as the cause of symptoms. There are recognized exceptions: pituitary disorders in which TSH fails to rise despite low hormone, certain medicines that distort results, and rare resistance syndromes. These are uncommon, and they are exactly what a specialist is trained to spot from the pattern of results.
On the second question, the more useful referral is often not to endocrinology at all. Fatigue and weight gain overlap with anemia, sleep apnea, depression, vitamin D deficiency, perimenopause, medication effects and simple overwork. A primary care clinician can screen for most of these in one visit. Sending someone with a normal thyroid panel to an endocrinologist frequently ends with the specialist confirming the thyroid is fine and gently redirecting.
Where the evidence does not support the popular narrative is in treating normal results as hidden hypothyroidism. Trials of thyroid hormone in people with normal or only marginally raised TSH have not shown consistent improvement in fatigue or weight, and the treatment carries real risk when levels are pushed too far. If your clinician declines to treat a normal number, that reflects the evidence rather than indifference. Asking what else could explain the symptoms is the productive next question.
What people often get wrong about thyroid care and specialists
Thyroid disease attracts more confident misinformation than almost any other common condition, partly because its symptoms are so ordinary. A few corrections, each grounded in mainstream guidance.
“A specialist will find what my doctor missed.” Sometimes true for unusual patterns. For straightforward hypothyroidism, the endocrinologist and the primary care clinician are looking at the same TSH and following the same guidelines. A second opinion is reasonable when results are inconsistent, not simply because the first opinion was unwelcome.
“My TSH is normal but not optimal.” Reference ranges are wide because healthy people vary. Chasing a narrower personal target with more hormone than the body needs raises the risk of heart rhythm problems and bone loss, which NIDDK lists among the consequences of excess thyroid hormone.
“Iodine or thyroid supplements will help.” In iodine-sufficient countries, most hypothyroidism is autoimmune and extra iodine does not fix it; in Hashimoto’s disease it can worsen things. Products marketed for thyroid support sometimes contain actual animal thyroid hormone in unlabeled amounts, and biotin in many supplements can falsely distort laboratory results.
“Once I’m on treatment, I’m done with testing.” Hormone needs change with weight, age, pregnancy, other medicines and the natural progression of autoimmune disease. Annual testing, as the NHS recommends, exists because stable does not mean permanent.
“Nodules mean cancer.” The Mayo Clinic is explicit that only a small proportion are malignant, and most are watched rather than removed.
“Hyperthyroidism is the easy one because you lose weight.” Untreated hormone excess is arguably the more dangerous state in the short term, straining the heart and, rarely, tipping into thyroid storm. It is referred more readily for good reason.
Questions to ask your care team before and after referral
A good consultation is shaped as much by what you ask as by what you are told. The questions below are the ones endocrinologists and primary care clinicians tend to appreciate, because each one leads to a decision rather than a reassurance.
If you are deciding whether to be referred:
- What in my results or history makes you think a specialist would change the plan?
- If we repeat the test first, what result would prompt referral and what would let us keep watching?
- Are there other causes of my symptoms we should rule out at the same time?
If you have hypothyroidism:
- What TSH range are we aiming for, and why that range for me specifically?
- How long after this change should I expect to feel different, and when will we retest?
- Which of my other medicines or supplements could affect absorption or the blood test?
If you have hyperthyroidism or a nodule:
- What is the likely cause, and does it change which treatments make sense?
- What are the trade-offs of each option for someone my age, with my plans and my other conditions?
- If this nodule is low risk, how often will it be measured, and what change would prompt a biopsy?
- Who is my point of contact between appointments if something changes?
If you are planning a pregnancy:
- Should my testing frequency or target change before I conceive?
- Who will manage my thyroid during pregnancy, and how will they coordinate with my obstetric care?
Write the answers down. Thyroid plans unfold over months, and the details of a target range or a follow-up interval are easy to lose between visits. If the answer to any question is “we don’t know yet,” that is often honest rather than evasive; the next test usually exists to find out.
When to call your doctor: red-flag signs that should not wait for a routine review
Most thyroid problems move slowly, which is why routine testing works. A small number of situations do not, and they deserve a same-day call or, in some cases, emergency care regardless of where you are in the referral process.
Seek emergency care immediately if you have:
- A very fast or irregular heartbeat with fever, confusion, agitation or vomiting, especially with known hyperthyroidism. This combination can signal thyroid storm, a rare but life-threatening surge described by NIDDK and the NHS.
- Severe drowsiness, confusion, very slow breathing or a body temperature that feels markedly low in someone with untreated or under-treated hypothyroidism. This can indicate myxedema coma, another rare emergency.
- Sudden difficulty breathing or swallowing, or a neck swelling that has enlarged quickly.
- Fever, severe sore throat or mouth ulcers while taking antithyroid medicine. The NHS advises urgent blood testing because these can be early signs of a dangerous drop in white blood cells.
- Sudden vision loss, double vision or eye pain with Graves’ disease.
Call your clinician promptly, within days, if you notice:
- A new lump in the neck, a hoarse voice lasting more than a few weeks, or swollen glands that do not settle.
- Palpitations, tremor, unexplained weight loss or heat intolerance developing on hormone replacement, which may mean the level has overshot.
- A positive pregnancy test when you have any thyroid condition, since testing and targets usually change early.
- Chest pain or breathlessness on exertion that is new, particularly if you are older or have heart disease.
- Symptoms returning after a long stable period, or a missed annual blood test.
None of these lists replaces judgment. If something feels wrong and you cannot explain it, the right move is a phone call, not a search. Your treating team can decide quickly whether it is a laboratory draw today, an appointment this week or nothing to worry about, and each of those is a better outcome than waiting.
Frequently asked questions
Do I need an endocrinologist for hypothyroidism if my levels are stable?
Usually not. Stable hypothyroidism on consistent hormone replacement with a TSH in range is managed in primary care in most health systems, with a blood test about once a year according to the NHS. Referral becomes reasonable if results keep shifting despite adjustments, if symptoms persist with normal tests, if you are planning a pregnancy, or if heart disease or older age complicates the target range. Your prescribing clinician decides.
What is the difference between an endocrinologist vs primary care for thyroid problems?
Both use the same blood tests and guidelines. A primary care clinician manages the predictable course of common hypothyroidism and watches your overall health. An endocrinologist adds depth for hyperthyroidism treatment choices, nodule assessment and biopsy, pregnancy, children, unusual laboratory patterns and cancer follow-up. Many people see a specialist briefly, then return to primary care once a plan is stable.
How long does it take to get a referral to an endocrinologist for thyroid disease?
It varies widely by health system, insurance and local specialist availability, so no single timeframe applies. Referrals for hyperthyroidism, suspicious nodules or pregnancy are generally prioritized over routine hypothyroidism questions. If you are waiting, ask your clinician what to do if symptoms change and whether treatment or repeat testing should begin in the meantime rather than pausing until the appointment.
Should I see a thyroid nodule specialist or a surgeon first?
An endocrinologist or your primary care clinician is the usual first stop, because the initial steps are ultrasound and risk grading rather than surgery. The Mayo Clinic notes most nodules are benign and many are simply monitored. A surgeon becomes involved if a biopsy suggests cancer, if the nodule is large enough to affect swallowing or breathing, or if an overactive nodule is best removed.
Can a thyroid problem be missed if my TSH is normal?
Rarely. TSH is a sensitive marker for primary thyroid failure, and a normal TSH with normal free T4 makes thyroid disease an unlikely cause of symptoms. Exceptions include pituitary disorders, certain medicines and supplements such as biotin that distort results, and rare hormone resistance. If symptoms persist, a broader workup for anemia, sleep disorders, mood and other causes is usually more productive than repeated thyroid testing.
Why is hyperthyroidism referred to a specialist more often than hypothyroidism?
Because the treatments differ in consequence and are not interchangeable. Antithyroid medicine, radioactive iodine and surgery each carry distinct trade-offs involving age, pregnancy plans, eye disease and gland size, and the NHS describes specialist referral as standard once hyperthyroidism is confirmed. Excess hormone also strains the heart and bone in the short term, so decisions are made with more urgency.
What should I bring to my first endocrinology appointment?
Recent thyroid results, any ultrasound or scan reports, and a complete list of medicines and supplements including iron, calcium and biotin, which can affect absorption or laboratory readings. Note when symptoms began, family history of thyroid or autoimmune disease, any past neck radiation and, for women, menstrual or pregnancy details. A written list of questions helps, since plans often unfold over several visits.
Do I need an endocrinologist if I have thyroid disease and want to get pregnant?
Most guidance says yes, or at least a clinician experienced in thyroid care during pregnancy. Hormone needs rise in pregnancy, NIDDK notes that adjustments are common, and untreated deficiency or excess is linked to complications for mother and baby. Testing is typically more frequent and targets shift by trimester. Coordination between endocrinology and obstetric teams is the usual arrangement.
Is it normal to still feel tired after starting thyroid medicine?
Often, for a while. NIDDK describes symptoms improving over weeks once levels are corrected, but fatigue and weight changes can lag behind the blood test, and TSH itself takes several weeks to settle after any change. If tiredness persists once TSH has been in range for a few months, raise it with your clinician; the cause may lie outside the thyroid altogether.
When should thyroid symptoms be treated as an emergency?
Seek emergency care for a very fast or irregular heartbeat with fever, confusion or vomiting, which can indicate thyroid storm; for severe drowsiness, confusion or very slow breathing in untreated hypothyroidism; for sudden trouble breathing or swallowing from neck swelling; and for fever or severe sore throat while on antithyroid medicine. New vision changes with Graves’ disease also need urgent assessment.
References
- Hypothyroidism (Underactive Thyroid) – NIDDK, National Institutes of Health
- Hyperthyroidism (Overactive Thyroid) – NIDDK, National Institutes of Health
- Underactive thyroid (hypothyroidism) – NHS
- Overactive thyroid (hyperthyroidism) – NHS
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Hashimoto Thyroiditis Myths: Gluten, Diet Fixes and What Endocrinologists Actually Recommend
Most popular Hashimoto diet myths do not hold up to evidence. No food causes or reverses Hashimoto thyroiditis, and guidelines do not require gluten-free…

Adrenal Crisis Explained: Warning Signs Your Care Team Wants You to Recognize Early
Adrenal crisis warning signs include sudden severe weakness, persistent vomiting or diarrhea, sharp pain in the abdomen, lower back or legs, dizziness or fainting…

Life After Total Thyroidectomy: Hormone Replacement, Follow-Up Blood Tests and Energy Levels
Life after total thyroidectomy means taking a daily thyroid hormone replacement for life, because the body can no longer make its own. Blood tests,…

Recovery After Pituitary Tumor Surgery: Nasal Care, Fluid Balance and Vision Checks
Pituitary surgery recovery usually involves a short hospital stay followed by several weeks of gradual healing at home. The three things care teams watch…

Adrenal Insufficiency After Cushing Treatment: Symptoms to Report and Why Follow-Up Matters
Adrenal insufficiency after Cushing surgery is expected rather than a sign of failure: once the cortisol-producing tumor is removed, the long-suppressed pituitary-adrenal system cannot…

Why Does Adrenal Function Take Time to Return After Cushing Syndrome Treatment?
Adrenal function takes time to return after Cushing syndrome treatment because months or years of excess cortisol switch off the brain and pituitary signals…