

Which Tests Build a Cardiometabolic Risk Assessment? Fasting Labs, ECG and Blood Pressure
Key Takeaways
- The American Heart Association counts a reading of 130/80 mmHg or higher as stage 1 hypertension, while the NHS uses 140/90 in clinic or 135/85 at home, and both require repeated readings before diagnosis.
- HbA1c reflects average blood sugar over the previous 2–3 months because glucose binds to hemoglobin for the lifespan of a red blood cell, according to the Mayo Clinic.
- Metabolic syndrome is defined by MedlinePlus as three or more of five features: large waist, high triglycerides, low HDL, high blood pressure and high fasting glucose.
- A resting ECG can show rhythm problems or evidence of past heart damage but cannot see narrowed coronary arteries, so a normal tracing is not a clean bill of health.
- Many labs still request a 9–12 hour fast before a lipid panel, mainly because triglycerides rise after meals, though non-fasting panels are increasingly accepted for routine screening.
- Risk calculators combine age, sex, smoking, blood pressure, cholesterol and diabetes status into a ten-year estimate that guides priorities but does not predict any one person's future.
A cardiometabolic risk assessment usually combines a blood pressure measurement, a fasting or non-fasting lipid panel (cholesterol and triglycerides), a blood sugar test such as fasting glucose or HbA1c, a waist or body measurement, and often a resting ECG. No single result labels a person as high or low risk; clinicians read the tests together, alongside age, family history and smoking, to estimate risk and plan next steps.
The envelope was thin, almost apologetic. Inside was an invitation to a routine health check, the kind that arrives once you cross a certain birthday. Priya turned 47 that spring. Her father had his first heart attack at 52, and she had spent years telling herself she would get around to being checked. Now the appointment card was on the fridge, and with it came a practical question: what will they actually do?
Most people picture a stethoscope and a quick chat. The reality is more structured. Cardiometabolic risk assessment tests are a small, deliberate set of measurements designed to see how the heart, blood vessels and metabolism are working together long before anyone feels unwell. Some need a blood draw, some a cuff on the arm, one involves sticky electrodes and a few quiet minutes on a couch.
None of them hurt much. All of them tell a story, but only when read side by side. This guide walks through each one, what it can and cannot show, and how a clinician turns a page of numbers into a plan.
What is cardiometabolic risk, and why do doctors test for it?
Cardiometabolic risk is the combined likelihood that a person will develop heart disease, stroke or type 2 diabetes, based on a cluster of related factors rather than one isolated problem. The word itself is a fusion: cardio for the heart and circulation, metabolic for how the body handles sugar, fat and energy. The two systems are not separate. Raised blood sugar stiffens artery walls over time; excess fat around the abdomen drives inflammation and raises blood pressure; high triglycerides and low protective cholesterol tend to travel together.
This is why a good assessment refuses to look at one number in isolation. The Mayo Clinic frames a cholesterol test as one piece of a broader picture that includes blood pressure, blood sugar, age and smoking status, and MedlinePlus describes metabolic syndrome as a group of conditions that raise heart disease and diabetes risk when they occur together. A person with a borderline cholesterol result and nothing else worrying is in a very different position from someone with the same cholesterol plus raised blood pressure and a large waist.
The quiet feature of these conditions is that they rarely announce themselves early. High blood pressure is often described as having no symptoms until it has already done damage, which is precisely why the NHS recommends that adults over 40 have it checked at least every five years. The purpose of testing is not to hunt for disease so much as to measure trends while there is still room to change them.
Think of it less as a verdict and more as a weather report: a set of readings that tells you which way conditions are moving, and how much notice you have.
Which cardiometabolic risk assessment tests come first?
Across major guideline bodies, including the NHS and the American Heart Association, the core set is remarkably consistent. It starts with things that cost nothing but attention: your age, sex, family history of early heart disease, whether you smoke, how active you are, and any diagnosed conditions. Then come the measurements.
| Test | What it measures | Preparation | Typical time |
|---|---|---|---|
| Blood pressure | Force of blood against artery walls, recorded as two numbers | Sit quietly for a few minutes; avoid caffeine and smoking beforehand | A few minutes per reading |
| Lipid panel | Total, LDL and HDL cholesterol plus triglycerides | Some labs ask for a 9–12 hour fast, others do not | One blood draw |
| Fasting glucose or HbA1c | Current blood sugar, or the average over 2–3 months | Fasting for glucose; none for HbA1c | Same blood draw |
| Waist and weight | Abdominal fat distribution and body mass index | None | Under a minute |
| Resting ECG | Electrical activity and rhythm of the heart | None; loose clothing helps | A few minutes |
Fasting times and the HbA1c window are those described by the Mayo Clinic; the ECG timing is also theirs. What matters most, in my view, is the order of priority. Blood pressure and the lipid panel carry the most weight in every risk calculator used in routine care. Blood sugar comes next because it flags diabetes and prediabetes, both of which multiply cardiovascular risk. The ECG is valuable but supporting evidence: it can reveal rhythm problems or signs of past strain, yet a normal tracing does not rule out narrowed arteries.
Some clinics add kidney function, liver enzymes or a full blood count to the same draw. These are reasonable but secondary. If time or blood is limited, the cuff and the lipid tube come first.
What actually happens during the appointment?
The visit is undramatic by design. You arrive, ideally having fasted if the lab has asked for it, and the first step is usually conversation. A nurse or clinician asks about your medical history, medicines, smoking, alcohol, activity and any relatives who developed heart disease or diabetes before their sixties. Answer honestly; family history in particular shifts the interpretation of everything that follows.
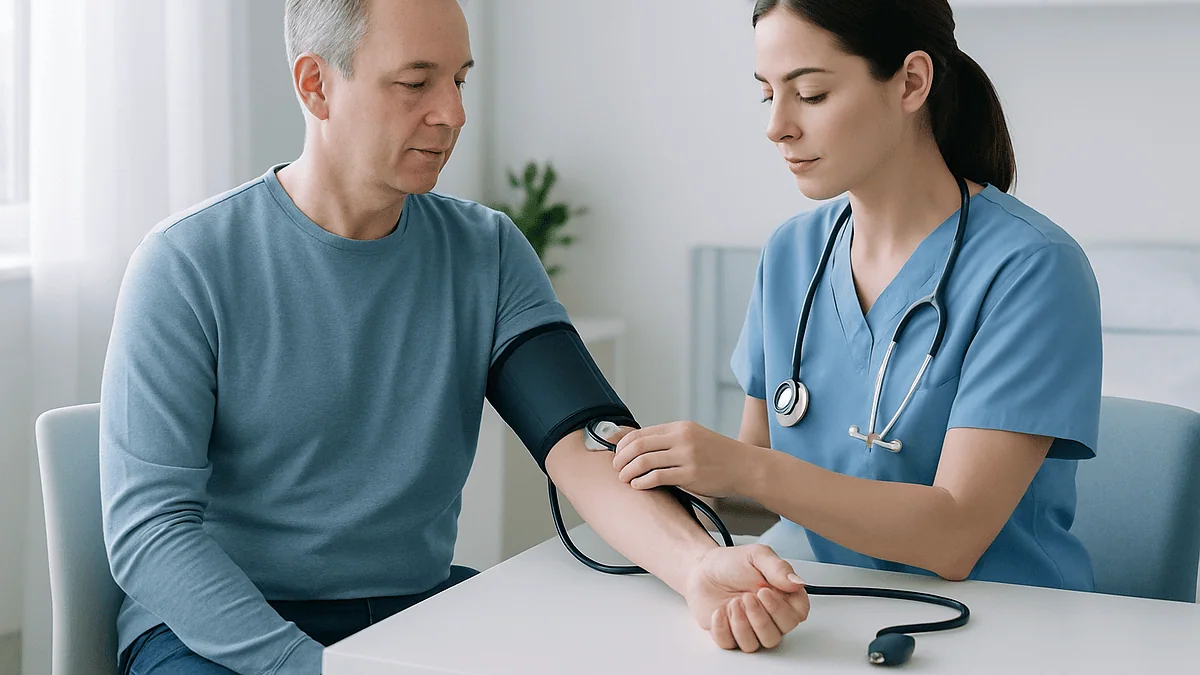
Next comes the cuff. You sit with your back supported, feet flat, arm resting at heart level, and stay quiet while the cuff inflates. Both the NHS and the American Heart Association note that talking, crossing your legs or having just climbed the stairs can push the reading up. A careful clinician will take at least two readings and may use both arms.
Height, weight and waist circumference follow. The waist is measured at roughly the midpoint between the bottom of the ribs and the top of the hip bones, not where your trousers sit.
The blood draw is a single needle in the crook of the elbow, filling one or more small tubes. The Mayo Clinic describes the cholesterol test as taking only a few minutes, with brief soreness at the site afterward. The same sample usually covers glucose or HbA1c.
If an ECG is included, you lie on a couch while small adhesive electrodes are placed on your chest, arms and legs. Electrodes are sensors that detect the heart’s electrical signal through the skin; nothing is sent into the body. You stay still for a short recording, then the stickers come off. The Mayo Clinic puts the whole procedure at a few minutes.
Priya’s appointment, for what it is worth, took under 40 minutes door to door.
Blood pressure: why one reading is never the whole story
Blood pressure is recorded as two numbers. The top, systolic, is the pressure when the heart squeezes; the bottom, diastolic, is the pressure between beats when the heart refills. The American Heart Association groups readings into ranges: normal below 120/80 mmHg, elevated when systolic is 120–129 with diastolic under 80, stage 1 hypertension at 130–139 or 80–89, stage 2 at 140/90 or higher, and a hypertensive crisis above 180/120. The NHS uses a slightly different framework, treating 140/90 or above in a clinic, or 135/85 at home, as high.
Those different thresholds are not a contradiction; they reflect how much a reading moves. Pressure rises with stress, pain, caffeine, a full bladder and the simple fact of being in a medical setting, a pattern often called white-coat hypertension. It can also be lower in clinic than at home, which is called masked hypertension. For this reason the NHS notes that a single high reading rarely leads to a diagnosis on its own; clinicians usually ask for repeat readings, home monitoring or a 24-hour wearable monitor before drawing conclusions.
Why does blood pressure sit at the top of every risk calculation? Because it acts on every artery in the body at once. Sustained high pressure thickens vessel walls, strains the heart muscle and accelerates the build-up of fatty plaque. The CDC and AHA both describe it as a leading contributor to heart attack and stroke, and one that typically produces no symptoms.
The practical lesson for the day of your assessment: arrive a few minutes early, sit, breathe, and do not rehearse your worries while the cuff inflates. And if the first number looks alarming, ask for it to be repeated after a rest.
What does a fasting blood test for heart health actually measure?
The centerpiece of the blood work is the lipid panel. Lipids are fats carried in the blood, and the panel breaks them into four figures. Total cholesterol is the overall amount. LDL, low-density lipoprotein, is the type that deposits in artery walls and is often called bad cholesterol. HDL, high-density lipoprotein, carries cholesterol away from the arteries and is considered protective. Triglycerides are a separate fat that rises with excess calories, alcohol and untreated diabetes.
The Mayo Clinic notes that a total cholesterol below 200 mg/dL is generally considered desirable for adults, but it also cautions that the number your clinician cares about most is usually LDL, interpreted in the context of your other risks. Someone with diabetes or a prior heart event will have a much tighter target than someone with no other concerns, and that target is set by the treating team, not a reference range.
Fasting deserves a word because it causes more confusion than any other part of the process. Triglycerides climb for several hours after a meal, which is why many labs still ask for a 9–12 hour fast, with water allowed, according to the Mayo Clinic. Evidence over the last decade has shown that non-fasting panels are accurate enough for most routine risk screening, and a growing number of services no longer require fasting at all. If you are unsure, follow whatever instruction your lab gave; if none was given, ask before you eat breakfast.
One more note: cholesterol is not a moral measure. Genetics account for a large share of LDL levels, and some people with careful diets carry high readings because of inherited conditions. The test describes what is happening; it does not assign blame.
Blood sugar tests: fasting glucose versus HbA1c
Two tests are used to check how the body is handling sugar, and they answer different questions. A fasting glucose test is a snapshot: the level of glucose in the blood after an overnight fast, when insulin should have brought it down to a baseline. HbA1c, sometimes written A1C or glycated hemoglobin, is a film rather than a photo. Glucose sticks to hemoglobin inside red blood cells, and because those cells live for roughly three months, the percentage of coated hemoglobin reflects average blood sugar over the previous 2–3 months, as the Mayo Clinic explains.
The Mayo Clinic gives these HbA1c interpretations: below 5.7% is in the normal range, 5.7% to 6.4% indicates prediabetes, and 6.5% or higher on two separate tests indicates diabetes. Prediabetes means blood sugar is higher than normal but not yet at the diabetes threshold, and it matters here because it already raises cardiovascular risk and often coexists with high blood pressure and abnormal lipids.
Each test has blind spots. Fasting glucose can be normal in someone whose sugar spikes sharply after meals. HbA1c can be misleading in conditions that change red blood cell lifespan, such as certain anemias, recent significant blood loss or some inherited hemoglobin variants, and in pregnancy. That is why a clinician who sees a borderline result will often repeat it, switch to the other test, or occasionally request an oral glucose tolerance test, in which sugar is measured before and two hours after a standard sweet drink.
For most adults attending a routine assessment, HbA1c is now the convenient first choice because it needs no fasting and is less swayed by a nervous morning. What it cannot do is diagnose on its own; confirmation and interpretation belong to your care team.
Metabolic syndrome blood tests and the tape measure
Metabolic syndrome is not a disease in itself but a pattern. MedlinePlus defines it as having at least three of five features: a large waist, high triglycerides, low HDL cholesterol, high blood pressure, and high fasting blood sugar. Notice that four of the five come directly from the tests already described. The fifth requires nothing more sophisticated than a tape measure.
Waist circumference earns its place because fat stored around the abdominal organs behaves differently from fat under the skin. Visceral fat, the deep kind wrapped around the liver and intestines, is metabolically active: it releases fatty acids and inflammatory signals that blunt insulin’s effect and push blood pressure and triglycerides upward. Two people with identical weight can carry very different risk depending on where that weight sits, which is why the Cleveland Clinic and MedlinePlus both list waist size rather than weight alone among the defining criteria.
Body mass index, or BMI, is calculated from height and weight and still appears on most assessment forms. It is a useful population tool and a blunt individual one; it cannot distinguish muscle from fat or say where fat is stored. Read it as context, not a conclusion.
The reason this cluster is flagged separately is that the features amplify one another. Insulin resistance, the state in which cells respond sluggishly to insulin, sits underneath most of them and tends to worsen if nothing changes. Identifying the pattern early gives a person and their clinician a clear target: the same changes in activity, diet, sleep and, where prescribed, medication tend to improve several of the five measures at once. The assessment does not label anyone; it points to where effort will pay off most.
ECG vs blood pressure check: what each one can and cannot show
People often assume the ECG is the heart test and the cuff is a formality. In routine risk assessment it is closer to the reverse.
A blood pressure check measures the load on the arteries. It says nothing about the heart’s rhythm or structure, but it captures the single most modifiable driver of stroke and heart failure, and it can be repeated at home for pennies of effort. A resting ECG, an electrocardiogram, records the heart’s electrical activity across a few seconds. The Mayo Clinic lists what it can reveal: an irregular rhythm such as atrial fibrillation, evidence of a previous heart attack, thickening of the heart muscle, and clues about the heart’s electrical conduction.
What the ECG cannot do is see inside the coronary arteries. A person can have significant narrowing and a perfectly normal resting tracing, because the recording only shows trouble when the heart is being stressed or has already been injured. This is why the ECG in a screening setting is best understood as a baseline and a rhythm check rather than a clearance certificate.
The two tests complement each other in a specific way. Years of high blood pressure can thicken the left ventricle, the heart’s main pumping chamber, and that thickening sometimes shows on an ECG. A raised cuff reading plus an ECG suggesting strain tells a different story than either finding alone.
If symptoms rather than screening prompt the visit, the picture changes: chest tightness on exertion may lead to an exercise ECG, an echocardiogram (an ultrasound of the heart) or imaging of the arteries. Those are decisions for the treating team, made on the basis of the whole assessment rather than one line of a report.
Who is usually offered these tests, and who is asked to wait?
Guideline bodies converge on a similar starting point: adults in midlife with no known heart disease. The NHS recommends blood pressure checks at least every five years from age 40, and its structured health check covers the same core measurements for adults aged 40 to 74 without an existing diagnosis. The American Heart Association encourages cholesterol and blood pressure awareness from early adulthood, with the frequency increasing as risk factors accumulate.
Earlier or more frequent assessment is generally appropriate for people with a first-degree relative who developed heart disease early, those who smoke, people with diabetes or kidney disease, people living with obesity, anyone with a history of pregnancy complications such as gestational diabetes or preeclampsia, and people from ethnic backgrounds with higher baseline risk of type 2 diabetes. Certain inflammatory conditions and some psychiatric medicines also raise risk and may prompt earlier checks.
Who is asked to wait? Usually not because testing is harmful but because timing affects accuracy. Someone recovering from a significant illness, surgery or a bout of flu may have temporarily disturbed cholesterol, glucose or blood pressure, and clinicians often prefer to test after recovery. HbA1c is unreliable in pregnancy and in some anemias, so a different test may be chosen. A person already under specialist care for heart disease or diabetes is not typically enrolled in a screening pathway, because they are being monitored more closely elsewhere.
Younger adults with no risk factors are not excluded, but the yield is lower and the interval between checks longer. The right schedule for any individual is set by their clinician, weighing history against the practical question of what a result would change.
How are cardiometabolic risk assessment tests read together?
The single most useful thing to understand about these tests is that no clinician reads them one at a time. They are fed into a risk calculator, a validated equation that estimates the probability of a heart attack or stroke over a defined period, usually ten years. Different countries use different tools, but all combine age, sex, smoking status, systolic blood pressure, total and HDL cholesterol, and the presence of diabetes; many add ethnicity, family history, kidney function and body mass index.
The result is a percentage, and this is where nuance matters. A ten-year risk estimate is a population statistic applied to an individual: it says that among a hundred people with your profile, roughly this many would be expected to have an event. It does not say which ones. Its value is in ranking priorities and framing a conversation, not in predicting your future.
Guidelines then attach thresholds to those estimates. Above a certain risk level, most bodies suggest discussing preventive medication alongside lifestyle change. Statins, for example, are a class of medicine that lowers LDL cholesterol by reducing its production in the liver; their benefit accrues over years, and whether one is appropriate depends on the overall estimate, personal preference and other health conditions. Blood pressure medicines work through several mechanisms, from relaxing vessel walls to reducing fluid volume, and are typically introduced and adjusted over weeks with repeat readings. Every one of those decisions belongs with the prescribing clinician.
Where the picture is unclear, some services consider a coronary artery calcium scan, a low-dose CT that counts calcified plaque in the heart arteries. The Mayo Clinic describes it as a way to refine risk when standard tools leave a person in a gray zone, not as a routine screen for everyone.
What the following days and weeks usually look like
For most people, the aftermath is quiet. Blood results typically come back within days, and many services now share them electronically before anyone has called. Resist the urge to interpret each line against an internet reference range; the ranges printed on a report are laboratory population values, not personalized targets.
If everything falls within expected limits, the usual outcome is a brief message or a short conversation, a note of your estimated risk, and advice on when to be checked again. The NHS interval of at least every five years for blood pressure is the outer bound; people with borderline results are often invited back sooner.
Borderline findings trigger repetition rather than alarm. A raised clinic blood pressure typically leads to a request for home readings over about a week, or a 24-hour ambulatory monitor, before any diagnosis is made. A prediabetes-range HbA1c usually prompts a repeat test and a conversation about activity, diet and weight. An unexpected lipid result may be repeated fasting if the first sample was not.
If the assessment does lead to a prescription, expect a follow-up appointment for repeat measurements. Blood pressure medicines are commonly reviewed after several weeks; cholesterol-lowering therapy is usually rechecked with a repeat lipid panel a few months in. These timelines vary by service and by the medicine chosen, and the clinician who prescribes will set them.
An abnormal ECG follows a different path. Some findings are harmless variants; others prompt an echocardiogram or a referral to a cardiology clinic. Either way, someone will contact you, and it is reasonable to ask how soon.
Priya’s results, for the record, came back in four days. Her cholesterol was higher than she expected, her blood pressure was fine, and the conversation that followed was about her father, not about fear.
What people often get wrong about heart and metabolic screening
A normal ECG means my heart is fine. It means the rhythm and electrical pattern were normal during a few seconds at rest. The Mayo Clinic is explicit that the test cannot detect narrowed arteries unless they have already caused damage. The lipid panel and blood pressure tell you far more about future risk.
I feel well, so my blood pressure must be fine. The CDC describes high blood pressure as usually having no signs or symptoms. Feeling well is not information about your arteries.
Cholesterol is all about diet. Diet matters, but inherited factors set much of the baseline. Familial hypercholesterolemia, a genetic condition causing very high LDL from birth, affects people who eat carefully. A high result is a reason to investigate, not a reason for guilt.
One high reading is a diagnosis. The NHS notes that a diagnosis of high blood pressure normally requires repeated raised readings, often confirmed at home. The same principle applies to HbA1c and glucose, which the Mayo Clinic says should be confirmed on a second test before diabetes is diagnosed.
Thin people do not need this. Weight is one factor among many. Waist distribution, family history, smoking and blood sugar can all be unfavorable in someone of average weight.
The ten-year risk percentage is my personal forecast. It is a population estimate applied to your profile. It guides priorities; it does not predict your particular future.
Supplements can replace testing or treatment. No over-the-counter product has been shown in guideline-grade evidence to substitute for blood pressure control or LDL lowering where those are indicated. Discuss anything you take with your clinician, because some products interact with prescribed medicines.
Questions to ask your care team
A good assessment ends with a conversation, and the quality of that conversation depends partly on what you bring to it. These questions tend to produce useful answers.
- What is my estimated ten-year risk, and which of my results contributed most to it?
- Which of these numbers can I realistically change, and which are largely fixed by age or genetics?
- Do any of my results need repeating before we draw conclusions, and should I measure blood pressure at home?
- Was my lipid panel fasting or non-fasting, and does that change how you read it?
- Is HbA1c a reliable test for me, given my medical history?
- If my ECG showed anything, is it a normal variant or something that needs follow-up?
- Would additional tests such as kidney function, lipoprotein(a) or a calcium score change what you would recommend?
- If you are suggesting a medicine, how does it work, what would we expect to see change, and when would we recheck?
- What specific changes in activity, diet, sleep or smoking would move my numbers most, based on my profile?
- When should I be reassessed, and what would prompt an earlier visit?
Bring a written list of medicines and supplements, including anything herbal, and a note of any relatives with heart disease, stroke or diabetes and the age at which they were diagnosed. If you monitor blood pressure at home, bring the log.
Ask, too, how results will be shared and whom to contact if something looks unclear. Understanding the plan is part of the plan, and no clinician minds being asked to explain a number twice.
When to call your doctor
Routine screening is not urgent, but some situations are, and they do not wait for an appointment card.
Call emergency services immediately if you or someone nearby has chest pain or pressure lasting more than a few minutes, especially with pain spreading to the arm, jaw or back, breathlessness, sweating or nausea; sudden weakness or numbness on one side of the body, facial drooping or difficulty speaking; or a blood pressure reading above 180/120 mmHg accompanied by chest pain, shortness of breath, severe headache, vision changes or confusion. The American Heart Association classifies this as a hypertensive emergency.
Contact your doctor promptly, within days rather than weeks, if home blood pressure readings are consistently at or above 140/90 mmHg (or 135/85 in the NHS home framework); if you notice a new irregular or racing heartbeat, unexplained fainting, or breathlessness on exertion that is new for you; if you develop excessive thirst, frequent urination, unexplained weight loss or blurred vision, which can accompany high blood sugar; or if you experience calf pain, swelling or unexplained bruising after starting a new medicine.
Also get in touch if a result you received electronically is flagged abnormal and no one has contacted you, if you are unsure whether to fast before a repeat test, or if a new symptom appears between scheduled checks. Clinicians would far rather field an unnecessary call than miss an early warning.
Whatever the results of a cardiometabolic risk assessment, the interpretation and the plan sit with the team who ordered it. This article explains the tests; it cannot read yours.
Frequently asked questions
What is cardiometabolic risk in plain language?
It is the combined chance of developing heart disease, stroke or type 2 diabetes, based on linked factors such as blood pressure, cholesterol, blood sugar, waist size and smoking. These factors tend to reinforce one another, so clinicians assess them together rather than one at a time and use the overall pattern to decide what needs attention first.
Do I need a fasting blood test for heart health, or can I eat first?
It depends on the laboratory. The Mayo Clinic notes that some services ask for a 9–12 hour fast, with water allowed, because triglycerides rise after eating; others accept non-fasting samples for routine screening. HbA1c never requires fasting. Follow the instruction you were given, and if none was given, ask before breakfast on the day.
Which metabolic syndrome blood tests are included?
The blood tests are triglycerides, HDL cholesterol and fasting glucose, all drawn from a single sample. Combined with blood pressure and waist circumference, they make up the five features MedlinePlus lists; having three or more meets the definition. Total and LDL cholesterol are usually measured at the same time because they inform overall cardiovascular risk.
ECG vs blood pressure check: which is more important for screening?
For estimating future risk in someone without symptoms, blood pressure carries far more weight; it feeds directly into every risk calculator, while a resting ECG does not. The ECG is useful for detecting rhythm problems or signs of past strain, but the Mayo Clinic notes it cannot reveal narrowed arteries. Both are informative; they answer different questions.
How long does a cardiometabolic risk assessment take?
Typically well under an hour. Blood pressure takes a few minutes per reading, the blood draw a few minutes, and the Mayo Clinic describes a resting ECG as taking only a few minutes once electrodes are attached. Most of the appointment is conversation about history, lifestyle and family, which is where much of the risk picture actually comes from.
Can I have a normal ECG and still have heart disease?
Yes. A resting ECG records electrical activity over a few seconds and, according to the Mayo Clinic, may be normal even when coronary arteries are significantly narrowed, because the tracing changes mainly during stress or after damage. This is why blood pressure, lipids and blood sugar, not the ECG, form the core of routine risk estimation.
What is the difference between fasting glucose and HbA1c?
Fasting glucose is a snapshot of blood sugar after an overnight fast. HbA1c measures the share of hemoglobin coated in glucose, reflecting the average over roughly 2–3 months, per the Mayo Clinic. HbA1c needs no fasting but can be unreliable in some anemias and in pregnancy, so clinicians choose the test that suits the individual.
How often should these tests be repeated?
The NHS advises adults over 40 to have blood pressure checked at least every five years, and its structured health check runs on the same interval for adults aged 40 to 74 without existing disease. People with borderline results, diabetes, a strong family history or other risk factors are usually reviewed sooner; the schedule is set by the clinician.
What happens if my ten-year risk score is high?
A higher estimate usually opens a conversation about which factors are driving it and how to change them. Guidelines suggest discussing preventive medicines such as statins or blood pressure treatment above certain thresholds, alongside changes to activity, diet and smoking. Whether to start anything, and what, is a shared decision with your prescribing clinician.
Will the assessment tell me whether I have diabetes?
It can raise the question but rarely settles it in one visit. The Mayo Clinic states that an HbA1c of 6.5% or higher indicates diabetes only when confirmed on two separate tests, and the same principle of repetition applies to fasting glucose. A single result outside the expected range leads to a repeat test and a discussion, not an immediate diagnosis.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Fever or Breathlessness During Endocarditis Treatment: When to Contact Your Care Team
Fever or new breathlessness during endocarditis treatment should always be reported to your care team the same day. A temperature can take several days…
Coronary Artery Bypass Surgery (CABG) Explained: How Graft Vessels Restore Blood Flow
Coronary artery bypass grafting (CABG) is open-heart surgery in which a surgeon takes a healthy blood vessel from elsewhere in the body and attaches…

After Coronary Artery Bypass Surgery: The Lifestyle Changes That Help Protect Your Grafts
The lifestyle changes with the strongest evidence for protecting bypass grafts after CABG are stopping smoking completely, attending cardiac rehabilitation, eating a Mediterranean-style diet…

The First Two Weeks After Arrhythmia Ablation: Puncture Site Care, Walking and Work
In the first two weeks after arrhythmia ablation, most people rest for a day or two, keep the groin puncture site clean and dry,…

24-Hour ECG (Holter): Sleeping, Showering and What to Expect
You can sleep normally with a 24-hour ECG. Keep the recorder beside you on the mattress or nightstand rather than under your body, sleep…

What to Ask Before Starting Targeted Pulmonary Hypertension Medicines
Before starting targeted pulmonary hypertension medicines, ask your specialist which of the five diagnostic groups you fall into, whether a right heart catheterization confirmed…