

Who Is Assessed for a Stem Cell Transplant in Multiple Myeloma, and When Does It Happen?

Key Takeaways
- In myeloma, a stem cell transplant almost always uses the person's own cells, so no donor search is needed and the procedure involves no surgery.
- Eligibility rests on heart, lung, kidney and liver function, everyday fitness and disease response to induction, not on a fixed age cutoff.
- The transplant usually happens after several months of combination drug therapy, with the full path from diagnosis to infusion often spanning roughly four to eight months.
- New blood cells typically begin to appear about ten to fourteen days after infusion, but full immune recovery can take a year or more and childhood vaccines must be repeated.
- Randomized trials show early transplant lengthens the time before myeloma returns, while overall survival differences have been less consistent, which is why deferring with stored cells is a recognized option.
- People judged unsuitable for transplant receive the same modern drug classes in a non-transplant pathway that is a standard of care in its own right.
In multiple myeloma, a stem cell transplant is usually considered for people whose overall fitness, organ function and other health conditions suggest they can tolerate high-dose chemotherapy, rather than on age alone. The assessment normally happens after a few months of initial drug treatment has reduced the disease, and the transplant team, not a single test, decides whether and when to proceed.
The folder comes home from the first hematology appointment thick with printouts, and one phrase is circled: transplant candidate, to be assessed. A daughter reads it aloud at the kitchen table, and her father, seventy-one and still splitting his own firewood, asks the obvious question. Assessed how? Against what?
That question sits at the center of stem cell transplant multiple myeloma eligibility, and the honest answer is that the yardstick has moved. Twenty years ago many programs drew a line at a birthday. Today the people deciding are more interested in how far you can walk, how your kidneys and heart are working, and how the disease has responded to the first rounds of medicine.
This explainer walks through what a transplant actually is in myeloma, who tends to be offered one, who is usually asked to wait or to take another route, and what the timeline looks like from diagnosis to the day the cells go back in. It corrects a few stubborn myths along the way. Every decision described here belongs to you and your treating team.
What does stem cell transplant multiple myeloma eligibility actually mean?
Multiple myeloma is a cancer of plasma cells, the white blood cells in bone marrow that normally make antibodies. When those cells turn cancerous they crowd out healthy blood production, damage bone and can strain the kidneys. Because myeloma lives in the marrow itself, one way to treat it is to give chemotherapy strong enough to wipe out the marrow, then rescue the body with its own previously collected blood-forming stem cells. That rescue is the transplant.
Eligibility, then, is not a judgment about whether someone deserves the procedure. It is a clinical estimate of whether their body can absorb the high-dose chemotherapy and the several weeks of low blood counts that follow, and recover well enough to benefit. The Mayo Clinic frames the decision as depending on the person’s overall health and the risk of the procedure, not on a single number.
Three questions drive the assessment. First, how well are the major organs working, especially the heart, lungs, kidneys and liver? Second, how active and independent is the person day to day? Third, has the myeloma responded to the initial drug treatment, often called induction, so that the transplant has a well-controlled disease to consolidate?
The National Cancer Institute treatment summary describes two broad groups: people who are candidates for high-dose therapy with stem cell rescue and people who are not, with treatment plans designed differently for each. That split matters from the very first visit, because it shapes which medicines are chosen for induction and how long they run before stem cells are collected. Being placed in the second group is not a dead end; it means a different, well-established path.
How an autologous stem cell transplant myeloma procedure works, step by step
The word autologous means the cells come from you. In myeloma this is by far the most common type of transplant. An allogeneic transplant, using a donor’s cells, is used far less often in myeloma because it carries a higher risk of serious complications and is generally reserved for specific situations or clinical trials, as the NCI summary notes.
Here is the sequence in plain language.
- Induction. Several cycles of combination drug therapy shrink the myeloma over a period of months. The aim is a deep response before collection.
- Mobilization. Blood-forming stem cells normally stay in the marrow. A growth-factor medicine, sometimes with a mobilizing agent, coaxes them into the bloodstream so they can be gathered.
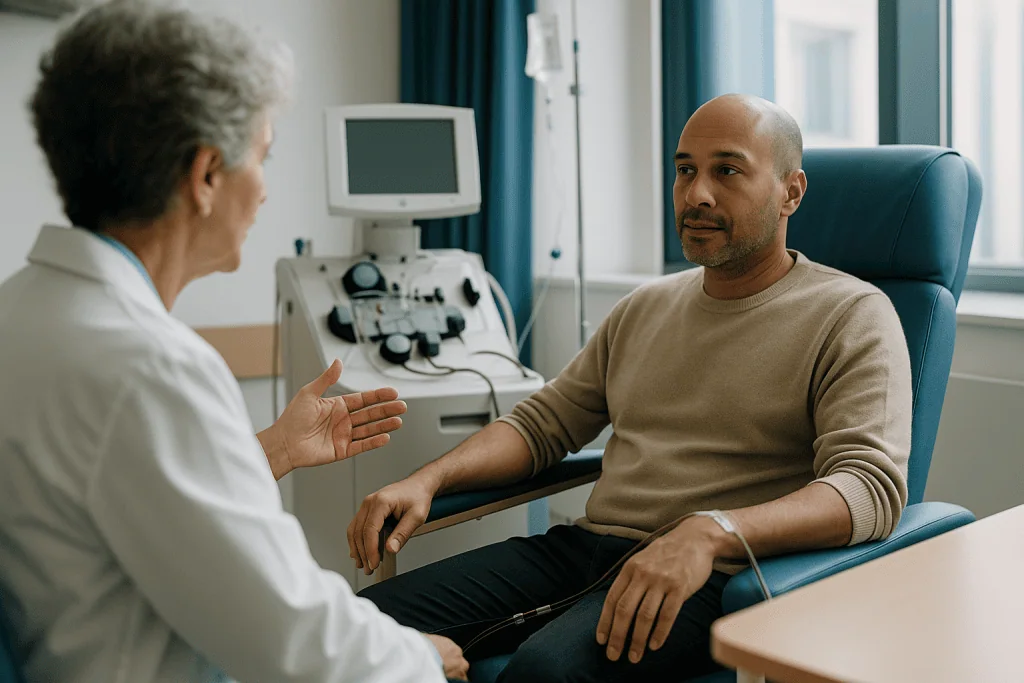
- Collection. Blood is drawn through a line, run through a machine that separates out the stem cells, and returned. This is called apheresis. It may take one or more sessions. The cells are frozen and stored.
- Conditioning. A high dose of a chemotherapy drug, most often an alkylating agent, is given to destroy the marrow and the myeloma cells within it.
- Infusion. A day or two later the thawed cells are given back through the line, much like a blood transfusion. This is the transplant itself.
- Engraftment. The cells travel to the marrow and begin producing new blood cells. Until they do, the person has almost no immune defense.
MedlinePlus explains that the reinfused cells find their way to the marrow on their own and that new blood cells typically start to appear within about two weeks. The Mayo Clinic describes the hospital or close-monitoring phase as lasting several weeks. Throughout, the transplant does not add anything foreign to the body; it resets the marrow and gives the high-dose chemotherapy room to work.
Who is usually offered a transplant, and who is usually asked to wait?
The people most often offered an autologous transplant share a profile: they are reasonably active, their heart and lungs can handle the stress of a hospital stay with low blood counts, their kidney function is adequate or can be supported, and their myeloma has responded to induction. The NHS puts it simply, noting that intensive treatment with a stem cell transplant is usually only suitable for people who are younger or fit enough to cope with it.
Fitness here is functional, not athletic. Transplant teams often use a performance status scale, a standardized description of how much of the day a person spends up and about versus resting. Someone who manages their own household and walks to the shops is typically viewed differently from someone who needs help with basic tasks, even if both are the same age.
Who is asked to wait? Several groups, and the reasons differ.
- People whose myeloma has not yet responded enough to induction. The team may change the drug combination and reassess.
- People with an active infection, uncontrolled diabetes, or a recent heart event, where a delay of weeks or months lets the problem settle.
- People whose kidneys are recovering from myeloma-related damage. Kidney function can improve as the disease is controlled, which may change the picture.
- People who are frail at diagnosis but whose strength returns once bone pain and anemia are treated.
Waiting is not the same as being ruled out. The Mayo Clinic notes that treatment plans are individualized and revisited, and many programs reassess candidacy after induction rather than deciding at the first visit. Some people are also offered collection and storage of their stem cells now, with the transplant itself deferred until the disease returns, an approach discussed later in this article.
What disqualifies you from a stem cell transplant?
People searching this question usually want a list of hard stops. In practice, very few conditions are absolute. What exists instead is a set of factors that raise risk to a level most teams consider unacceptable when weighed against the expected benefit.

The factors that most often lead a team to advise against high-dose therapy include:
- Serious heart disease. Significantly reduced pumping function, unstable angina or uncontrolled rhythm problems make the fluid shifts, infections and anemia of the transplant period dangerous.
- Severe lung disease. Reduced lung reserve leaves little margin if pneumonia develops while counts are low.
- Advanced liver disease. The liver processes the conditioning chemotherapy; if it is failing, drug toxicity rises sharply.
- Poor performance status. Spending most of the day in bed at baseline predicts a much harder recovery.
- Uncontrolled infection. Not a permanent barrier, but a reason to pause until it is treated.
- Myeloma that is not responding to any induction regimen. High-dose therapy works best as consolidation of a response, not as rescue from refractory disease.
Kidney impairment deserves its own note. Myeloma frequently affects the kidneys, and severe impairment once excluded people from transplant. The NCI summary indicates that people on dialysis can undergo autologous transplant at experienced centers with adjusted conditioning, though the risks are higher. So kidney disease is a modifier, not an automatic exclusion.
Two things are commonly mistaken for disqualifiers and are not: age by itself, and having other stable chronic conditions such as well-controlled hypertension or thyroid disease. The assessment looks at how those conditions are behaving, not whether they exist. The final call always rests with the transplant physician, who weighs the whole picture rather than any single line on a list.
Is there an age limit for stem cell transplant in myeloma?
The short answer is that most programs no longer treat a birthday as a wall. The NCI summary describes autologous transplant as an option for selected patients, including older adults in good health, and the Mayo Clinic frames candidacy around overall health rather than a fixed cutoff. Older clinical trials often enrolled people under sixty-five, which is where the widely quoted limit came from, but that reflected trial design more than biology.
What has replaced the age line is a more careful look at physiologic age. Two seventy-year-olds can sit at opposite ends of the fitness spectrum. Transplant teams increasingly use a geriatric or frailty assessment, a structured set of questions and simple tests covering walking speed, grip strength, independence in daily activities, mood, nutrition and the number and severity of other illnesses. This gives a more honest estimate of how someone will cope with three weeks of near-zero white cells than a date of birth ever could.
Age does still matter in a few specific ways. Older adults tend to have more coexisting conditions, and the conditioning dose is sometimes reduced for people over a certain age or with kidney impairment; the prescribing team decides that, and this article does not discuss dosing. Recovery of energy and appetite can be slower, and the practical demands of the post-transplant weeks, when a caregiver must be present and the home must be kept clean, can be harder to arrange.
The message for the seventy-one-year-old at the kitchen table is therefore mixed but hopeful: age alone will not exclude him, and his firewood habit is exactly the kind of evidence a frailty assessment is designed to capture. Whether transplant is the right choice for him still depends on his heart, kidneys and disease response, and on what he wants from treatment.
When does the transplant happen in the treatment timeline?
A transplant is almost never the first thing that happens after a myeloma diagnosis. It arrives after induction, the initial phase of combination drug therapy. Both the Mayo Clinic and the NHS describe this order: drug treatment first to bring the disease under control, then, for suitable people, high-dose chemotherapy with stem cell rescue.
Induction typically runs for several months. The NCI summary describes regimens given in cycles, commonly three to six cycles before collection, which in calendar terms is often three to five months, though the exact length depends on response and the regimen chosen. During this stretch the team tracks the myeloma protein in blood and urine, imaging of bones, and marrow tests to see how deeply the disease is responding.
Once the response is judged adequate, collection is scheduled. Mobilization and apheresis usually occupy about a week to two weeks. The cells are then frozen, and a gap of several weeks often follows to let the body recover from induction and to complete any remaining pre-transplant tests. Conditioning and infusion follow, then the engraftment period in hospital or under daily outpatient monitoring.
Put together, the path from diagnosis to transplant commonly spans roughly four to eight months, a range consistent with the sequence described in the Mayo Clinic and NCI resources, though individual timelines vary widely. After transplant, many people go on to maintenance therapy, a lower-intensity ongoing treatment intended to hold the response; the Mayo Clinic notes that maintenance may continue for an extended period.
Why not transplant immediately? Because the high-dose chemotherapy is most useful when it is consolidating an existing response. Induction also gives the team time to see how the disease behaves, to correct kidney and bone problems, and to complete the fitness assessment properly rather than under pressure.
Transplant-eligible vs transplant-ineligible myeloma: how the pathways compare
The two broad pathways share a great deal. Both begin with combination drug therapy, both aim for the deepest response that can be achieved safely, and both usually continue with some form of ongoing treatment. The differences lie in intensity, timing and the kind of monitoring required. The table below summarizes typical features described in the NCI, Mayo Clinic and NHS resources; individual plans vary.
| Feature | Transplant-eligible pathway | Transplant-ineligible pathway |
|---|---|---|
| Initial treatment | Combination drug induction for several months | Combination drug therapy, often continued longer |
| Stem cell collection | Yes, after induction | Not usually |
| High-dose chemotherapy | Yes, as conditioning before infusion | No |
| Hospital or intensive monitoring | Typically several weeks around the transplant | Mostly outpatient |
| Period of very low blood counts | Yes, roughly two weeks until engraftment | Usually milder and shorter |
| Ongoing maintenance | Common | Common, sometimes as continuous therapy |
| Who it suits | Fit people with adequate organ function | People with frailty, major organ problems or a preference to avoid intensive treatment |
Two honest points about this comparison. First, being in the ineligible group does not mean weaker treatment. Modern drug combinations have made the non-transplant pathway far more effective than it was a generation ago, and the NCI summary describes it as a standard approach with its own robust evidence. Second, the groups are not fixed. Someone judged unfit at diagnosis can become a candidate after induction improves their kidneys and anemia, and someone initially eligible may choose to defer or decline.
The table is a map, not a verdict. Where you sit on it is a conversation with your team, and it can be revisited.
What are the myeloma transplant eligibility criteria checked at the assessment visit?
The assessment visit is part medical work-up and part frank conversation. Expect it to take most of a day, sometimes spread over two, and to involve several members of the transplant team: a physician, a coordinator nurse, often a pharmacist, a social worker and a dietitian.
The medical tests usually include:
- Blood tests for kidney and liver function, blood counts and the myeloma protein.
- An echocardiogram or similar scan to measure how well the heart pumps.
- Lung function tests, which measure how much air the lungs can move and how well they exchange oxygen.
- A bone marrow biopsy to confirm the current level of disease.
- Screening for infections that could flare when the immune system is suppressed.
- A dental check, because mouth infections are a common source of trouble when counts are low.
The functional side matters just as much. The team will ask about walking, stairs, shopping, cooking and whether help is needed with any of these. A formal frailty screen may be done. Mood and cognition are assessed, since the weeks after transplant demand concentration on medicines, hygiene and symptoms.
Then comes the part people underestimate: the social assessment. The Mayo Clinic and MedlinePlus both stress that a reliable caregiver and a safe, clean home environment are practical requirements, because the person will be sent home while their immune system is still recovering. The coordinator will want to know who can stay with you, how far you live from the center, and whether you can get to daily or twice-weekly appointments in the first weeks.
None of these items is scored in isolation. The team meets, weighs the findings together, and then talks with you about what they recommend and why. You are entitled to ask which finding weighed most heavily, and what, if anything, could change it.
Should I get a stem cell transplant for multiple myeloma, or can it wait?
This is the question behind all the others, and it does not have a single correct answer. What the evidence supports is a set of trade-offs, which your team can help you weigh against your own priorities.
The argument for going ahead early rests on depth and durability of response. The NCI treatment summary describes randomized trials in which people who received high-dose therapy with stem cell rescue after induction had longer periods before the disease returned than those treated with drugs alone. That is a real and consistent finding. The same summary notes that differences in how long people lived overall have been less clear-cut in the era of newer drugs, partly because people who delay transplant can still receive it later.
That leads to the second option: collect and store the cells now, continue drug treatment, and hold the transplant in reserve for when the disease returns. This deferred approach keeps the option open while avoiding the intensive weeks now. Its downside is uncertainty; fitness can decline with time, and a later transplant may be harder to tolerate.
A third path is to decline transplant altogether and rely on drug therapy, which for some people, particularly those with other health priorities or a strong wish to avoid hospitalization, is entirely reasonable.
How to think it through:
- How deep is my response after induction, and how does that change the expected benefit?
- What are my personal risks of serious complications, given my heart, lungs and kidneys?
- What would the weeks of recovery mean for my work, caregiving responsibilities and daily life?
- If I defer, how will we decide when to use the stored cells?
No article can answer these for you. What it can say is that both early and deferred strategies are recognized in mainstream guidance, that neither is a promise, and that the decision should rest with you and your treating team after a full discussion.
What do the days and weeks after the stem cell infusion usually look like?
The infusion itself is often anticlimactic. The thawed cells are given through the central line over an hour or so; some people notice a garlic-like taste or smell from the preservative used in freezing, a harmless and well-known effect described by MedlinePlus. Then the waiting begins.
Over the following week the conditioning chemotherapy takes full effect. Blood counts fall to their lowest, usually around day five to ten. This is when the hard part arrives: mouth sores, nausea, diarrhea and profound fatigue are common, and most people run a fever at some point, which is treated promptly with antibiotics because there are almost no white cells to fight infection. Blood and platelet transfusions are frequently needed. The NHS stem cell transplant guidance describes this as the period of highest risk and closest monitoring.
Engraftment, the moment new blood cells begin to appear, typically occurs around ten to fourteen days after infusion, consistent with the roughly two-week window MedlinePlus describes. Energy does not return that quickly, but the fever risk falls and the mouth begins to heal.
Discharge home often follows within about two to three weeks of infusion, depending on the program and on how smoothly recovery goes. Home comes with rules: a caregiver present, careful food hygiene, avoiding crowds and sick contacts, and frequent clinic visits for blood checks.
The longer arc is measured in months. The NHS notes that it can take up to a year or more for the immune system to recover fully. Childhood vaccinations usually need to be repeated on a schedule the team sets, since the high-dose chemotherapy erases prior immunity. Fatigue commonly lingers for several months, and many people describe the third month as the point where they start to feel like themselves again. Maintenance therapy, if planned, typically begins once counts have stabilized.
What are the risks of a stem cell transplant for myeloma, stated plainly?
An autologous transplant is safer than it was, and safer than a donor transplant, but it remains an intensive treatment with real dangers. Being told this clearly is part of informed consent, and the Mayo Clinic and NHS both list the following as the main concerns.
Infection. During the low-count period, ordinary bacteria from the gut or skin can cause serious bloodstream infections. Fungal and viral infections can follow in the months of immune recovery. This is the leading cause of serious harm.
Bleeding. Very low platelets mean even minor injuries can bleed excessively; transfusions are given when counts fall below a threshold the team sets.
Organ stress. High-dose chemotherapy and the fluids, antibiotics and transfusions around it can strain the kidneys, heart and lungs. People with borderline function beforehand are watched most closely.
Mucositis. Painful inflammation of the mouth and gut lining, often severe enough to require strong pain relief and intravenous nutrition for a period.
Delayed or failed engraftment. Uncommon with a good cell collection, but the reason a minimum cell count is required before conditioning proceeds.
Later effects. Persistent fatigue, fertility loss, and a small increased risk of a second blood cancer years later, which the NCI summary notes as a recognized long-term risk of alkylating chemotherapy.
Death from the procedure. Treatment-related mortality with autologous transplant in myeloma is low at experienced centers, but it is not zero, and your team will discuss your individual estimate rather than a generic figure.
Against these risks stands the benefit described earlier: a deeper, longer-lasting response for many people. The balance is personal. Someone with a very deep response after induction may weigh the risks differently from someone whose disease has been slow to respond, and the team’s role is to help you see your own numbers, not a population average.
What are the alternatives if a transplant is not advised, and what newer treatments exist?
People searching for the most promising myeloma treatments are usually asking a practical question: if I am not a transplant candidate, or if I choose not to have one, what is left? The answer is more than most expect.
The backbone of non-transplant care is combination drug therapy using several classes that attack myeloma in different ways. The Mayo Clinic and NCI resources describe these classes: proteasome inhibitors, which block the machinery myeloma cells use to dispose of waste proteins; immunomodulatory drugs, which alter the immune environment the cancer depends on; monoclonal antibodies, which bind to a marker on the surface of myeloma cells and flag them for destruction; and corticosteroids, which have a direct anti-myeloma effect. Given together and continued as ongoing therapy, these regimens have substantially improved outcomes for people who do not undergo transplant, as the NCI summary describes.
Newer immune-based approaches, including therapies that engineer a person’s own T cells to recognize myeloma and antibodies designed to pull T cells toward the cancer, have entered mainstream use for myeloma that has returned after earlier treatments. The NCI summary lists these among approved options in the relapsed setting. Where they fit for newly diagnosed disease, and whether they might one day replace high-dose chemotherapy for some people, are active research questions. Trials are ongoing, and it would be inaccurate to present them as proven alternatives to transplant at diagnosis today.
Supportive treatments run alongside any pathway: bone-strengthening medicines to reduce fractures, radiotherapy to painful bone lesions, treatment of anemia, and kidney protection. The NHS treatment guidance emphasizes these as central to living well with myeloma, not as afterthoughts.
Clinical trials are a legitimate option at every stage. Asking your team whether a trial is open to you is a fair question, and joining one is never required to receive standard care.
Coverage, logistics and the questions about payment people are afraid to ask
One of the most common searches around this topic is whether a public or private insurance program pays for a stem cell transplant in myeloma. This article does not give cost or coverage figures, and the honest answer is that coverage rules vary by plan, by country and by the specifics of a person’s situation. What can be said is that autologous transplant for myeloma is an established, guideline-supported treatment, and transplant programs routinely have staff whose job is to work through coverage before treatment begins.
Practical steps that help:
- Ask the transplant coordinator early who handles insurance authorization and when that process starts. It often runs in parallel with induction.
- Ask whether a financial counselor or social worker is available, and request a meeting before collection is scheduled.
- Ask which parts of the pathway, such as storage of frozen cells, outpatient monitoring and maintenance therapy, are handled separately.
- Keep a single folder for correspondence with the insurer and the program.
Beyond payment, the logistics deserve equal attention. The MedlinePlus transplant overview and the Mayo Clinic both note that a caregiver is expected to be available, often around the clock, for the first weeks at home. Employers may need documentation for extended leave for both the patient and the caregiver. Distance from the center matters because early complications need same-day assessment; some programs ask people who live far away to stay nearby for a period after discharge.
Fertility is another practical matter that should be raised before conditioning, not after. High-dose chemotherapy commonly causes permanent infertility, and options to preserve fertility exist but must be arranged in advance.
None of these questions should feel embarrassing. Transplant teams field them daily, and raising them early is one of the most useful things a person can do to make the transplant weeks go smoothly.
What people often get wrong about stem cell transplants in myeloma
Myths cluster around this treatment, partly because the phrase stem cell transplant sounds like something else entirely. Here are the ones worth correcting.
Myth: a transplant is surgery. It is not. No operation is involved. The cells are collected through a line in the blood and returned the same way. The demanding part is the chemotherapy, not the infusion.
Myth: the stem cells fight the cancer. In an autologous transplant they do not. They are your own healthy blood-forming cells, and their job is to rebuild the marrow after high-dose chemotherapy has done the anti-myeloma work. This is why the procedure is sometimes described more accurately as high-dose chemotherapy with stem cell rescue.
Myth: it needs a donor match. Almost all myeloma transplants use the person’s own cells, so no donor search is required. Donor transplants exist but are uncommon in myeloma.
Myth: being over sixty-five rules you out. As discussed earlier, fitness and organ function guide the decision, and older adults in good health are routinely assessed.
Myth: a transplant means the disease is gone for good. Myeloma is generally considered a controllable but recurring condition, and mainstream guidance including the Mayo Clinic describes transplant as a way to achieve a deeper and longer-lasting response, not a permanent end to the disease. Maintenance therapy and ongoing monitoring continue afterward.
Myth: if you are not eligible, treatment is weaker. The non-transplant pathway uses the same modern drug classes and is a standard of care in its own right.
Myth: the hard part is over at discharge. Immune recovery takes months, fatigue can persist well into the first year, and vaccinations must be repeated. Planning for that long tail matters as much as planning for the hospital stay.
Questions to ask your care team before deciding
A good assessment conversation runs in both directions. These questions are drawn from what people commonly wish they had asked. Bring a companion and write the answers down.
About eligibility
- Based on my tests so far, do you consider me a candidate for high-dose therapy with stem cell rescue, and which findings weighed most in that judgment?
- Is there anything, such as kidney recovery or improved fitness, that could change my eligibility if we reassess after induction?
- Will you use a frailty or geriatric assessment, and can I see the results?
About timing
- How many cycles of induction do you anticipate before collection, and what response are you looking for?
- If you recommend collecting cells but deferring the transplant, how would we decide when to use them?
- How long are stored cells kept, and how is that monitored?
About risks and recovery
- What is my individual risk of serious complications, given my heart, lungs and kidneys, rather than the average?
- How long do you expect me to be in hospital or under daily monitoring, and how far away can I live during that period?
- What will maintenance therapy involve afterward, and for roughly how long?
- How will my vaccinations be handled after transplant?
About alternatives
- If I decline or defer transplant, what would my drug treatment plan look like instead?
- Is there a clinical trial that fits my situation, and would joining it change my transplant options?
- Should I speak with a fertility specialist before conditioning?
About support
- Who is my main point of contact for questions between visits, and how do I reach the team out of hours?
- What does my caregiver need to know and be able to do?
You are not obliged to decide at the assessment visit. Asking for time to think, or for a second conversation, is normal and is usually welcomed.
When to call your doctor: red-flag signs before, during and after transplant
Myeloma itself, the induction drugs, and the transplant period each carry warning signs that need prompt attention. Your team will give you a direct number; use it. The signs below are drawn from the Mayo Clinic, NHS and MedlinePlus guidance and are not a self-diagnosis tool.
Call the same day, or go to emergency care, if you notice:
- A fever, chills or shivering, at any point after collection and especially after conditioning. When white cells are low, a fever can signal a bloodstream infection that becomes dangerous within hours.
- Unusual bleeding: nosebleeds that will not stop, blood in urine or stool, or widespread small purple spots on the skin.
- Shortness of breath, chest pain or a racing heartbeat, which can indicate infection, fluid overload, a clot or heart strain.
- Confusion, severe drowsiness or a sudden change in alertness, which in myeloma can reflect a high calcium level, infection or kidney problems.
- Passing very little urine, or swelling of the legs, which may point to kidney trouble.
- Severe or new back pain, or weakness or numbness in the legs, which can signal a fracture or pressure on the spinal cord and needs urgent assessment.
- A new rash, especially if painful or blistering, which may be a reactivated viral infection.
Call within a day or two if:
- Mouth sores stop you from drinking enough fluids.
- Vomiting or diarrhea lasts more than a day or you cannot keep medicines down.
- Pain, redness or discharge appears around the central line.
- You develop a persistent cough or sore throat.
During induction, before any transplant, the same principles apply: fever, breathlessness, severe bone pain and reduced urine output all warrant a call. Transplant teams would far rather hear about a symptom that turns out to be minor than learn of a serious one late. Your treating team decides what each sign means for you; this list exists so that you know when to reach them.
Frequently asked questions
What disqualifies you from a stem cell transplant for multiple myeloma?
Very few conditions are absolute disqualifiers; most are risk factors weighed together. The ones that most often lead a team to advise against high-dose therapy are significantly reduced heart function, severe lung or liver disease, spending most of the day in bed at baseline, an uncontrolled infection, and myeloma that has not responded to any induction regimen. Age by itself and stable chronic conditions are not disqualifiers. The transplant physician makes the final judgment.
Is there an age limit for a stem cell transplant in myeloma?
Most programs no longer use a fixed age cutoff. The widely quoted limit of sixty-five came from older clinical trial designs rather than biology. Today teams assess physiologic age through organ function tests and frailty screens covering walking, strength, independence and other illnesses. Older adults in good health are routinely assessed and may be offered transplant, sometimes with adjusted conditioning decided by the prescribing team.
Should I get a stem cell transplant for multiple myeloma?
That decision belongs to you and your treating team after weighing your individual risks and goals. Evidence summarized by the National Cancer Institute shows early transplant after induction lengthens the time before myeloma returns, while overall survival differences have been less clear with modern drugs. Alternatives include collecting and storing cells while deferring the transplant, or drug therapy alone. Each is a recognized approach with different trade-offs.
Does insurance or Medicare pay for a stem cell transplant for multiple myeloma?
Coverage depends on the specific plan, the country and the individual situation, and this article does not provide cost or coverage figures. Autologous transplant for myeloma is an established, guideline-supported treatment, and transplant programs typically have coordinators or financial counselors whose role is to work through authorization before treatment begins. Ask early who handles this and when the process starts, since it often runs alongside induction.
What are the most promising newer treatments for multiple myeloma?
Newer immune-based therapies, including treatments that engineer a person’s own T cells to recognize myeloma and antibodies that direct T cells toward the cancer, are approved for myeloma that has returned after earlier treatment. Whether they can replace high-dose chemotherapy for newly diagnosed disease is still under study in clinical trials. Established drug classes such as proteasome inhibitors, immunomodulatory drugs and monoclonal antibodies remain the backbone of both transplant and non-transplant pathways.
How long after diagnosis does the transplant usually happen?
Commonly within roughly four to eight months, though individual timelines vary. Induction drug therapy typically runs three to six cycles over three to five months, followed by about one to two weeks of stem cell mobilization and collection, then a recovery gap of several weeks before conditioning chemotherapy and infusion. The team sets the pace based on how the disease responds and on completing the fitness assessment.
How long is the hospital stay for an autologous stem cell transplant in myeloma?
Discharge often follows within about two to three weeks of the infusion, depending on the program and how smoothly recovery goes. Some centers manage part of this period as daily outpatient monitoring rather than an inpatient stay. New blood cells typically appear around ten to fourteen days after infusion, and going home requires a caregiver, a clean environment and frequent clinic visits for blood checks during the following weeks.
Can you have a stem cell transplant if your kidneys are damaged by myeloma?
Often yes, though the risks are higher and the approach is adjusted. Kidney impairment was once an exclusion, but the National Cancer Institute summary notes that people with severe impairment, including those on dialysis, can undergo autologous transplant at experienced centers with modified conditioning. Kidney function also frequently improves as the myeloma is controlled during induction, which may change the assessment. The transplant physician decides in each case.
What is the difference between transplant-eligible and transplant-ineligible myeloma?
The terms describe two treatment pathways. Transplant-eligible people receive induction drug therapy, then stem cell collection, high-dose chemotherapy and infusion of their own cells, followed by maintenance. Transplant-ineligible people receive combination drug therapy, often continued longer, without the high-dose step. The classification depends on fitness and organ function, is not fixed, and does not mean weaker treatment for the second group.
What are the main risks of a stem cell transplant for myeloma?
Infection during the low-count period is the leading danger, followed by bleeding from low platelets, painful mouth and gut inflammation, strain on the kidneys, heart and lungs, and delayed engraftment. Longer-term effects include persistent fatigue, infertility and a small increased risk of a second blood cancer years later. Treatment-related death is uncommon at experienced centers but not zero, and your team will discuss your individual risk rather than a general figure.
References
- NHS: Multiple myeloma treatment
- NHS: Stem cell and bone marrow transplants
- MedlinePlus: Bone marrow transplant
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Why Leukemia and Lymphoma Plans Are Built by Hematology and Oncology Together
Leukemia and lymphoma begin in blood-forming and immune cells, so the specialists who read blood counts and bone marrow (hematology) and those who plan…

Mouth Sores and Taste Changes During Chemotherapy: Daily Care That Makes Eating Easier
Mouth sores during chemotherapy (oral mucositis) happen because chemotherapy damages the fast-dividing cells lining the mouth. They usually appear 5 to 10 days after…

After Ureteral Tumor Surgery: Stents, Catheters and the Return to Normal Activity
After surgery for a ureteral tumor, a temporary ureteral stent (a soft tube keeping the ureter open) and a bladder catheter are common. The…
What a CyberKnife Session Feels Like: No Incision, No Frame, Just Lying Still
Most people describe a CyberKnife session as uneventful: you lie still on a padded table, often in a soft mesh mask or body cradle,…

Preparing for Brachytherapy: Fasting, Bowel Preparation and the Anesthesia Check
To prepare for brachytherapy, most people are asked to stop eating for roughly six hours and clear fluids for about two hours before anesthesia,…

When Is a Stem Cell Transplant Part of Acute Lymphocytic Leukemia Treatment?
A stem cell transplant is usually considered for acute lymphocytic leukemia when chemotherapy alone is unlikely to keep the disease away: high-risk genetic features,…