

Venipuncture: What Happens When Blood Is Drawn — and Why It Rarely Hurts

Key Takeaways
- A standard blood-draw needle is 21 to 23 gauge — under a millimeter wide — and crosses only about two millimeters of pain-sensitive skin, which is why most sticks register as a brief pinch.
- A routine panel of two to four tubes removes roughly two tablespoons of blood, under 1 percent of the average adult's 5-liter supply, and the fluid is replaced within about a day or two.
- Best-practice guidelines call for releasing the tourniquet within about one minute, because longer application concentrates the trapped blood and can artificially distort results like potassium.
- The median cubital vein at the inner elbow is the preferred site because it's superficial, anchored so it doesn't roll, and safely distant from major nerves and the brachial artery.
- Applied tension — repeatedly clenching your leg, abdominal, and arm muscles for 10 to 15 seconds — props up blood pressure and is an evidence-backed way to prevent needle-related fainting.
- Drinking water in the hours before a draw plumps flattened veins, and plain water is almost always permitted even before fasting tests — confirm with your clinician when the test is ordered.
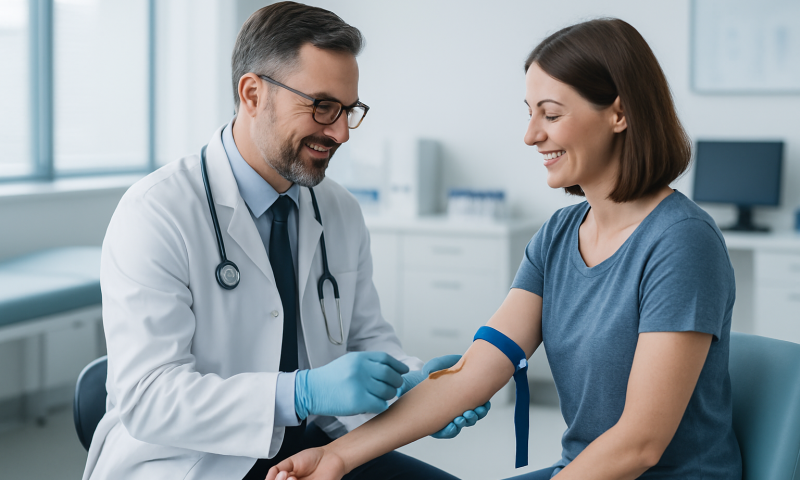
Venipuncture is the routine procedure of drawing blood from a vein, usually at the inner elbow, using a thin sterile needle. A trained phlebotomist cleans the skin, applies a brief tourniquet, inserts the needle for a few seconds per tube, then applies pressure. Because the needle is narrow and the puncture lasts seconds, most people feel only a quick pinch, and complications such as small bruises are typically minor.
There’s a small ritual that plays out millions of times a day: a chair with a wide armrest, a rubber strap, a stranger asking about your weekend while tapping the crook of your elbow. Most people look away. A few watch with clinical fascination. Almost everyone braces for something worse than what actually happens.
The gap between expectation and reality is the most interesting thing about a blood draw. The needle is thinner than a strand of spaghetti. The puncture itself lasts less time than a paper cut takes to register. Yet the anticipation can raise a person’s heart rate more than a brisk walk up two flights of stairs.
Understanding what’s happening on the other side of that armrest — why that particular vein, why the strap, why so many tubes — turns an anxious minute into a mildly interesting one. And the evidence says that shift matters more than you’d think.
What is a venipuncture procedure, exactly?
Strip away the Latin and venipuncture means puncturing a vein — deliberately, briefly, and with a very specific choreography. According to MedlinePlus, the standard sequence runs like this: the phlebotomist confirms your identity (usually name and date of birth, checked against the tube labels), wraps an elastic band around your upper arm, and asks you to make a loose fist. That band makes the veins below it swell slightly, so one can be seen or felt more easily.
The skin gets cleaned with an antiseptic wipe, which does more of the work of preventing infection than most people realize. Then comes the part everyone dreads and almost no one remembers accurately: a thin needle slides into the vein at a shallow angle, roughly 15 to 30 degrees. Blood flows into one or more vacuum-sealed tubes that fill themselves — nobody is pulling blood out of you with force during a routine draw.
Once the last tube fills, the band comes off, the needle comes out, and gauze goes on with firm pressure. Total needle-in-vein time for a typical panel: often under 60 seconds. The paperwork usually takes longer.
Every step exists for a reason. The identity check prevents the single most dangerous lab error — the mislabeled tube. The fist helps the vein stand up. The pressure afterward is what determines whether you bruise. Small procedure, tight script.
Is venipuncture the same as phlebotomy?
Nearly — and the distinction is more about scope than substance. Venipuncture is the specific act of puncturing a vein with a needle, whether that’s to collect blood, start an intravenous line, or give something into the bloodstream. Phlebotomy is the broader practice of drawing blood for testing, donation, or occasionally treatment, and it’s also the name of the profession: the person holding the needle is a phlebotomist.
So every blood draw involves venipuncture, but not every venipuncture is phlebotomy. A nurse placing an IV before surgery performs venipuncture without drawing a single tube. Meanwhile, phlebotomy can occasionally happen without a vein at all — a fingerstick for a drop of blood is technically capillary collection, still under the phlebotomy umbrella.
One more wrinkle that confuses people searching online: venepuncture, with an extra e, is simply the British spelling. The NHS uses it; American sources like MedlinePlus and the Cleveland Clinic drop the middle e. Same needle, same vein, different dictionary.
Why does the terminology matter to you as a patient? Mostly because it explains who’s allowed to do what. Phlebotomists train specifically in blood collection — vein selection, tube handling, the order tubes must be filled — and in many settings they perform thousands of draws a year. That repetition is a large part of why a draw from an experienced phlebotomist so often feels like nothing.
What are the three types of venipuncture?
When people ask this, they usually mean the three standard methods a phlebotomist chooses from, and the choice depends almost entirely on your veins.
- The evacuated tube system is the workhorse: a straight needle attached to a holder, with vacuum tubes that click in one after another. It’s fastest for multi-tube draws and the default for adults with sturdy, visible veins.
- The butterfly needle (formally, a winged infusion set) is a shorter, thinner needle with plastic wings and a flexible tube. It gives the phlebotomist finer control at a shallower angle, which is why it’s favored for children, older adults with fragile veins, hand veins, and anyone whose veins are small or prone to moving.
- The syringe method lets the phlebotomist control suction by hand. Delicate veins can collapse under the abrupt pull of a vacuum tube; a slow, gentle draw with a syringe keeps them open.
Two other blood collections exist outside this trio and are worth knowing so you’re not surprised. Capillary sampling — the fingerstick or, in newborns, a heel stick — collects drops rather than tubes. And arterial puncture, usually at the wrist, samples oxygen-rich blood from an artery for specific respiratory tests; it’s a different procedure done by different clinicians, and honestly, it’s the one that earns the wince.
If you know your veins are difficult, it’s entirely reasonable to say so and ask about a butterfly. Good phlebotomists appreciate the intel.
Why the crook of your elbow is prime real estate
Phlebotomists could theoretically draw from dozens of veins. They keep returning to one: the median cubital vein, running diagonally across the inner elbow. Its popularity comes down to three anatomical gifts.
First, it sits close to the surface, often visible as a faint blue-green line, so there’s less guesswork. Second, it’s anchored by surrounding connective tissue, which means it holds still when the needle approaches — unlike hand veins, which are notorious for sliding sideways at the worst moment. Third, and most important for comfort and safety, it sits at a respectful distance from the nearby major nerves and the brachial artery. A needle in the median cubital vein has a wide margin of error.
When that vein isn’t cooperative, the phlebotomist works down a mental list: the cephalic vein along the thumb side of the forearm, the basilic vein on the pinky side (used more cautiously, since it runs closer to a nerve and artery), then the veins on the back of the hand.
Some sites are deliberately avoided. The underside of the wrist is off the table in standard practice — nerves and tendons crowd too close to the surface there. An arm on the same side as certain past surgeries, or one with an IV already running, may also be skipped. If a phlebotomist studies both your arms before choosing, that’s not indecision. That’s the job done properly.
Why doesn't it hurt more? The anatomy of a nearly painless stick
Here’s the honest physiology: your body’s pain sensors are heavily concentrated in the skin itself, particularly the outermost layers. The vein wall below has comparatively sparse pain innervation. So the moment that genuinely registers is the needle crossing perhaps two millimeters of skin — a fraction of a second — after which most people feel pressure at most.
The hardware helps too. A standard draw needle is typically 21 to 23 gauge, which translates to an outer diameter under a millimeter — around 0.8 millimeters for a 21-gauge. Butterfly needles run thinner still. Compare that with a sewing pin (about 0.6 millimeters) and you get a sense of scale: this is a very small object moving very briefly through tissue.
Technique multiplies the effect. A smooth, confident insertion at the correct shallow angle stimulates fewer pain receptors than a slow or hesitant one, which is one concrete reason experience matters. The vacuum tubes then do the collecting passively; nothing during the draw itself should hurt, though some people notice a dull ache from the tourniquet’s squeeze.
None of this means pain is imaginary when it happens. A stick that catches a nerve fiber produces a sharp, electric sensation — rare, but real, and worth mentioning immediately so the phlebotomist can withdraw and reposition. Pain levels also genuinely vary between people and between days; hydration, anxiety, and plain luck all play roles. “Rarely hurts” is the evidence-based average, not a promise.
What the tourniquet actually does — and why it comes off fast
That elastic strap is doing something cleverer than it looks. It compresses your arm just enough to slow blood returning through the veins while letting arterial blood keep flowing in. Blood arrives, can’t leave as quickly, and the veins below the strap plump up like a garden hose with a kinked end. A vein that was a flat, invisible thread becomes a firm, bouncy target.
Placement matters — usually three to four inches above the intended site. So does timing, and this is a detail worth appreciating: best-practice guidelines, including the World Health Organization’s phlebotomy standards, call for releasing the tourniquet within about one minute. Leave it on longer and blood in the trapped section starts to concentrate as fluid seeps out of the vessels. That hemoconcentration can subtly distort results — potassium and protein measurements are particularly sensitive to it — meaning a sloppy tourniquet can manufacture an abnormal lab value out of thin air.
This is also why vigorous, prolonged fist-pumping is discouraged. Repeatedly clenching the fist can shift potassium out of muscle cells into the local blood, nudging that number upward before the needle even arrives. A gentle, held fist is fine; enthusiastic pumping is counterproductive.
If your result ever comes back with a note about a possible collection issue and a request to redraw, this is often the backstory: not a health problem, just physics interfering with chemistry.
Why so many tubes — and what the cap colors mean
Watching four or five tubes click on and off the same needle raises a fair question: couldn’t they just fill one big one? They can’t, and the reason is chemistry. Different tests need blood in different states — clotted, unclotted, preserved — so each color-coded cap contains a different additive coating the tube’s inside wall. Mixing states in one tube would ruin most of the tests.
| Cap color | What’s inside | Commonly used for |
|---|---|---|
| Light blue | An additive that precisely prevents clotting | Clotting and coagulation tests |
| Red or gold | No anticoagulant; blood is allowed to clot | Serum chemistry — cholesterol, liver and kidney markers |
| Green | An additive that keeps blood liquid for plasma tests | Certain chemistry panels, often urgent ones |
| Lavender | An additive that binds calcium so cells stay intact and unclotted | Complete blood count |
| Gray | A preservative that stops cells from consuming sugar | Glucose testing |
The tubes are also filled in a strict sequence — the “order of draw” — so that a trace of one tube’s additive can’t hitchhike into the next and skew its result. Afterward, each tube gets gently inverted several times, never shaken. Rough handling ruptures red blood cells, a problem called hemolysis, and a hemolyzed sample often means an apologetic phone call and a second appointment. Gentleness, it turns out, is quality control.
How much blood do they really take?
Less than your eyes suggest. A standard collection tube holds between 4 and 10 milliliters, and most routine panels need two to four tubes. Call it 20 to 30 milliliters altogether — about two tablespoons.
Now the denominator: an average adult carries roughly 5 liters of blood, about 10 pints. A typical draw removes under 1 percent of it. For comparison, a whole-blood donation takes around 470 milliliters — a full pint, fifteen to twenty times a routine lab draw — and healthy donors walk out after a snack and a short rest.
Your body barely registers the withdrawal. The fluid portion, plasma, is replenished within about 24 to 48 hours, largely from what you drink. Red blood cells take longer — your bone marrow replaces a donation’s worth over several weeks — but the few milliliters lost to lab tubes are a rounding error against the roughly 2 million red cells your marrow produces every second.
The picture changes only at the extremes. Hospitalized patients drawn multiple times daily for weeks can experience meaningful cumulative loss, which is why hospitals increasingly use smaller pediatric tubes for frequent testing. Newborns, with a total blood volume that can be measured in cups rather than liters, get proportionally tiny samples for the same reason. For an outpatient having an annual panel, though, the math is comfortably boring — and boring, in laboratory medicine, is exactly what you want.
Needle fear is real, common — and worth taking seriously
If needles make you anxious, you have a great deal of company. Research summarized by Harvard Health suggests a majority of children and up to one in four adults have significant needle fear, and a meaningful fraction of adults avoid blood tests or medical care because of it. That avoidance is the real harm — not the fear itself, which is a normal, ancient response to sharp objects approaching your skin.
What actually helps, according to the evidence?
- Say it out loud. Telling the phlebotomist you’re nervous isn’t weakness; it changes how they work. They’ll talk you through it or distract you, whichever you prefer, and they’ll watch you for early signs of faintness.
- Don’t watch. Looking away genuinely reduces reported pain for many people. Fix your eyes on a poster, a window, your phone.
- Breathe long and slow. Extended exhales activate the calming branch of the nervous system. Anxiety amplifies pain perception through well-mapped pathways; dialing it down isn’t a platitude, it’s neurology.
- Bring distraction. A podcast in one earbud, a conversation, a cold pack held in the other hand — anything that occupies attention competes with pain signals.
- Ask about numbing options. For children and severely fearful adults, clinicians can sometimes apply a topical numbing product beforehand; ask your care team what’s available and appropriate.
For phobia severe enough to keep you from needed care, exposure-based therapy with a mental health professional has solid supporting evidence. Fear this common has been studied thoroughly, and it responds to treatment.
Why some people faint — and the muscle trick that helps
Fainting around needles isn’t fragility and isn’t in your head, at least not in the dismissive sense. It’s a vasovagal response: an overreaction of the vagus nerve that abruptly drops your heart rate and blood pressure, briefly starving the brain of blood flow. The warning signs arrive in a recognizable cluster — warmth, sweating, ringing ears, tunnel vision, a gray wash over your sight — usually with enough lead time to act, as the Cleveland Clinic describes.
The first countermeasure is positional. Blood pressure has a much harder time dropping dangerously when you’re horizontal, which is why anyone with a fainting history should ask to lie down for the draw. Phlebotomy chairs recline for exactly this reason, and no one will blink at the request. Say it before the needle, not during.
The second is a technique with real evidence behind it, called applied tension. Tense the large muscles of your legs, abdomen, and non-draw arm — squeeze hard for 10 to 15 seconds, release briefly, repeat. The muscle contraction props up your blood pressure, directly opposing the vasovagal drop. It was developed specifically for blood-and-needle fainting and it works while you sit in the chair.
If you do feel the wave coming mid-draw, speak up immediately. A faint that’s announced becomes a non-event: recline, cold compress, a few minutes of rest. A faint that’s hidden out of embarrassment becomes a fall. Phlebotomists have seen hundreds of both; they will always prefer the first.
Bruises, soreness, and what counts as normal afterward
A blood draw ends with a hole in a vein, so a little leakage is unremarkable. When blood seeps into the surrounding tissue before the puncture seals, it pools under the skin as a bruise — technically a hematoma — that may bloom over a day or two, cycle through purple, green, and yellow, and fade within one to two weeks. Tender, unsightly, harmless.
Whether you bruise mostly comes down to the two minutes after the needle. Firm, direct pressure on the gauze — actual pressure, not a decorative touch — for two to five minutes gives the vein wall time to seal. Bending the elbow over the gauze, the instinctive move, is actually less effective than straight-arm pressure and may make bruising more likely. Keep the bandage on for a few hours, and give that arm a pass on heavy lifting — gym sessions, grocery hauls, toddlers — for the rest of the day.
Some people simply bruise more readily: older adults with thinner skin and more fragile vessels, and anyone taking medicines that affect clotting. If that’s you, mention it beforehand; the phlebotomist will hold pressure longer and may choose the site more conservatively.
Mild soreness at the site for a day is within normal range. A small firm lump under a fresh bruise usually is too — it’s the pooled blood, and it resorbs on its own. What’s not routine is covered a few sections down, and it’s worth reading.
"I have rolling veins": what a hard stick really means
Some people announce it like a confession the moment they sit down: I’m a hard stick. Usually they’re right, and usually it’s not mysterious. A few well-understood factors make veins genuinely harder to access.
Dehydration is the big, fixable one. When you’re low on fluid, blood volume drops and veins flatten — the garden hose at half pressure. Fasting draws are notorious for this because people skip water along with breakfast, which is almost never required. Cold is the second: chilly exam rooms constrict surface vessels, which is why a phlebotomist may wrap your arm in a warm pack before trying. Body composition matters too — veins can sit deeper under tissue — as does age, since older veins are often more fragile and less anchored. And veins that have been accessed many times, in people with chronic conditions requiring frequent draws, can develop scarring that makes them tougher targets.
“Rolling” veins are real: hand veins especially are loosely tethered and can slide away from the needle. The fix is technique — the phlebotomist anchors the vein by pulling the skin taut below the site — not extra force.
What should happen when sticks fail? Best-practice guidance is refreshingly humble: after two unsuccessful attempts, the phlebotomist should hand off to a colleague rather than keep trying. You’re allowed to invoke that. “Could someone else give it a try?” is a reasonable, standard request, not an insult — and experienced phlebotomists make the same call on themselves.
How to make your next blood draw easier
You have more influence over a smooth draw than you might expect, and most of it happens before you arrive.
- Drink water — genuinely, deliberately. A couple of glasses in the hours beforehand plumps your veins and makes them easier to find and puncture. Unless you’ve been told to restrict fluids, plain water is almost always allowed even before fasting tests. This single habit prevents more difficult draws than anything else on this list.
- Confirm the fasting rules. Some tests require 8 to 12 hours without food; many require nothing at all. Ask when the test is ordered rather than guessing — fasting unnecessarily makes you miserable, and eating before a true fasting test can distort sugar and triglyceride results enough to require a redo.
- Stay warm. Wear sleeves you can push up easily, and if your hands are icy in the waiting room, run warm water over your arms or ask for a warm pack.
- Share your history. Fainting episodes, difficult past draws, a preferred arm or vein, medicines that affect clotting — thirty seconds of information changes how the phlebotomist approaches you.
- Schedule strategically. If you must fast, book the first morning slot so the fast ends at breakfast. Morning draws also matter for tests with daily hormone rhythms, where your clinician may specify a time window.
None of this is elaborate. Hydrated veins, accurate instructions, and honest communication cover most of what separates a forgettable draw from a frustrating one.
Where your blood goes after it leaves your arm
The part you never see is arguably the most impressive. Within minutes of the draw, your labeled tubes begin a tightly tracked journey. Barcodes tie each tube to your identity and your clinician’s orders; from this point, machines and technologists scan those codes at every handoff, because a sample attributed to the wrong person is the laboratory’s nightmare scenario.
Tubes destined for serum tests rest upright for a set time while the blood clots, then ride a centrifuge spinning at thousands of revolutions per minute. Centrifugal force layers the sample like a parfait: heavy red cells at the bottom, a thin pale band of white cells and platelets in the middle, straw-colored serum or plasma on top. Most chemistry tests analyze only that top layer.
Analysis itself is largely automated. Modern chemistry analyzers sip microliters from each tube and run dozens of measurements in minutes, with quality-control samples of known values run alongside to prove the instruments are honest. A complete blood count happens on a separate analyzer that counts and sizes cells one by one as they stream past a detector. Anything flagged as unusual gets human eyes — a technologist reviewing, sometimes literally examining your cells under a microscope.
Turnaround varies: common panels often result the same day, specialized tests may take a week or travel to a reference laboratory. When your results appear in a patient portal, that two-tablespoon sample has typically been scanned, spun, sampled, verified, and double-checked more times than most packages you’ve ever shipped.
When to see a doctor after a blood draw
Serious complications from venipuncture are genuinely uncommon, but they exist, and knowing the difference between a normal bruise and a problem is part of being an informed patient.
Contact your healthcare provider if you notice any of the following:
- Signs of infection at the site — spreading redness, increasing warmth, swelling, pus, or a fever developing in the days after the draw. Infection after venipuncture is rare thanks to antiseptic technique, but it needs prompt attention when it occurs.
- Numbness, tingling, or electric, shooting pain in the arm or hand that persists beyond a few hours. A fleeting zing during the stick can happen; sensation changes that linger may indicate nerve irritation and should be evaluated.
- A rapidly expanding, firm, or intensely painful swelling at the site rather than an ordinary flat bruise — especially if the arm feels tight.
- Bleeding that won’t stop after 15 minutes of firm, continuous pressure, particularly if you take medicines that affect clotting.
- Pain that worsens after the second day instead of easing, or a bruise still spreading after several days.
- The arm becoming pale, cold, or dusky — extremely rare, but a same-day call, not a wait-and-see.
The reassuring context: an ordinary bruise, a day of mild tenderness, and a small temporary lump under the skin are all within the range of normal and resolve on their own. The list above describes the exceptions precisely so you can stop worrying about everything that isn’t on it.
Frequently asked questions
What is a venipuncture procedure?
Venipuncture is the standard procedure for drawing blood from a vein with a sterile needle, usually at the inner elbow. A phlebotomist verifies your identity, applies a tourniquet to make the vein swell, cleans the skin with antiseptic, inserts a thin needle at a shallow angle, and fills one or more vacuum tubes. The needle is typically in the vein for under a minute, after which pressure and a bandage finish the job.
What is the difference between phlebotomy and venipuncture?
Venipuncture is the specific act of puncturing a vein — for a blood draw, an IV line, or an injection — while phlebotomy is the broader practice of collecting blood for testing or donation, and the name of the profession. Every routine blood draw is both. But an IV placement is venipuncture without phlebotomy, and a fingerstick is phlebotomy without venipuncture, since it samples capillary blood rather than a vein.
Is venepuncture the same as phlebotomy?
Venepuncture is simply the British spelling of venipuncture, used by the NHS and other UK sources; American references like MedlinePlus drop the middle e. The procedure is identical. As for phlebotomy, the terms overlap heavily but aren’t perfect synonyms: venepuncture means puncturing a vein for any purpose, while phlebotomy specifically refers to drawing blood, most often for laboratory testing or donation.
What are the three types of venipuncture?
The three standard methods are the evacuated tube system (a straight needle with self-filling vacuum tubes, the default for sturdy adult veins), the butterfly needle (a smaller winged needle offering finer control, favored for children, hand veins, and fragile or small veins), and the syringe method (manual, gentle suction for veins that might collapse under vacuum pressure). Fingersticks and arterial punctures are separate types of blood collection, not venipuncture methods.
Does venipuncture hurt?
For most people, no more than a quick pinch lasting under a second. Pain receptors are concentrated in the skin, which the needle crosses in a fraction of a second; the vein itself has far fewer. The needle is under a millimeter wide, and vacuum tubes fill passively without painful pulling. Sharp, electric, or lingering pain is uncommon and worth reporting immediately, since it can mean the needle should be repositioned.
How much blood is taken during a routine blood draw?
Usually 20 to 30 milliliters — about two tablespoons — across two to four tubes, each holding 4 to 10 milliliters. That’s under 1 percent of the roughly 5 liters of blood an average adult carries. For perspective, a whole-blood donation removes about 470 milliliters, fifteen to twenty times more, and healthy donors recover routinely. Your body restores the fluid within a day or two, mostly from what you drink.
Why do I bruise after a blood draw?
A bruise forms when a small amount of blood leaks from the punctured vein into surrounding tissue before the hole seals. It’s harmless and typically fades within one to two weeks. The best prevention is firm, straight-arm pressure on the site for two to five minutes after the needle comes out — bending the elbow over the gauze is less effective. Older adults and people on medicines affecting clotting bruise more easily and should mention it beforehand.
What should I do if I feel faint during a blood draw?
Tell the phlebotomist immediately — an announced faint becomes a non-event, while a hidden one risks a fall. Warning signs include warmth, sweating, ringing ears, and tunnel vision. Ask to lie down before the draw if you have a fainting history; blood pressure can’t drop as dangerously when you’re horizontal. The applied tension technique — clenching your leg and abdominal muscles for 10 to 15 seconds, repeatedly — also helps keep blood pressure up.
Can I drink water before a fasting blood test?
Almost always yes — plain water is typically allowed and actively encouraged, since good hydration plumps your veins and makes the draw easier and more comfortable. Fasting instructions generally mean no food or caloric drinks for 8 to 12 hours, depending on the test; coffee, tea, juice, and gum usually count as breaking the fast. Because rules vary by test, confirm the specifics with your care team when the test is ordered.
How long should I keep the bandage on, and when can I exercise?
Keep the bandage on for a few hours — long enough for the puncture to seal fully — then remove it to let the skin breathe. Skip heavy lifting and strenuous exercise with that arm for the rest of the day, since straining can reopen the vein puncture and cause bruising. Ordinary activities like typing, driving, and walking are fine immediately. If bleeding restarts, apply firm pressure for several minutes with the arm straight.
References
- Venipuncture — MedlinePlus Medical Encyclopedia
- Blood tests — NHS
- WHO guidelines on drawing blood: best practices in phlebotomy
- Vasovagal Syncope — Cleveland Clinic
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

B12 and Folate Blood Tests: What Is Measured and Why They Travel Together
A B12 blood test measures the amount of vitamin B12 circulating in your serum, usually in picograms per milliliter, while a folate test measures…

The ESR (Sed Rate) Test: How It Works and Why It Travels With CRP
The erythrocyte sedimentation rate (ESR, or sed rate) measures how far red blood cells settle in a vertical tube in one hour, in millimeters.…

Mammogram Age: When to Start and How Often, by Guideline
Most US guidelines now advise that women at average risk begin screening mammograms at age 40. The US Preventive Services Task Force recommends one…
The GGT Blood Test: The Liver Enzyme That Completes the Panel
The GGT blood test measures gamma-glutamyl transferase, an enzyme concentrated in the liver and bile ducts. Clinicians order it to help detect liver or…

The Hemolyzed Sample: Why Labs Sometimes Ask You to Come Back
A hemolyzed blood sample means red blood cells broke apart before testing, spilling their contents and skewing results such as potassium and certain enzymes.…

The Comprehensive Metabolic Panel: 14 Values, One Tube, Explained
A comprehensive metabolic panel (CMP) is a blood test that measures 14 substances to assess blood sugar, kidney function, liver health, electrolyte balance, and…