

After Herniated Disc Surgery: Wound Leaks, Fever and New Weakness That Need a Prompt Call

Key Takeaways
- A temperature of 100.4°F (38°C) or higher after the first two days, or a fever that returns, is the standard reporting threshold in discharge guidance.
- Clear, watery fluid from the wound paired with a headache that eases lying flat points toward a spinal fluid leak from a dural tear, a recognized discectomy risk.
- New weakness, or weakness that appears after improvement, can signal a hematoma or recurrent fragment pressing on the nerve and needs same-day assessment.
- Trouble passing urine, incontinence or numbness in the saddle area after surgery is treated as a possible cauda equina syndrome and warrants emergency care.
- Deep disc-space infection often shows up as severe night-time back pain without fever, sometimes weeks after the operation.
- The disc is not rebuilt by surgery; published series place recurrent herniation in roughly the 5 to 15 percent range over following years, so returning leg pain deserves a call.
After herniated disc surgery, the signs that need a prompt call are fluid leaking from the wound, a temperature of 100.4°F (38°C) or higher, spreading redness or pus, new or worsening leg weakness, numbness in the groin or inner thighs, trouble passing urine or controlling bowels, a headache that eases when lying flat, and calf pain or breathlessness. Your surgical team decides what each sign means.
Day four. The heavy ache in your leg is gone, which still feels slightly unreal, and you have started to trust the stairs again. Then you notice the dressing is damp. Not soaked, just damp, with a faint yellow ring. Is that normal? You look at the discharge sheet, then at the phone, then at the dressing again.
Most people who have a discectomy, the operation that removes the piece of disc pressing on a nerve, recover without drama. The wound seals, the swelling settles, the nerve slowly wakes up. But a small number run into problems that are far easier to handle early than late, and the difference between “early” and “late” is often a single phone call that someone was unsure about making.
This explainer walks through the herniated disc surgery warning signs that matter most: what leaks, fevers and new weakness can mean, what ordinary healing looks like alongside them, and how to describe what you are seeing so your care team can act.
What actually happens during herniated disc surgery
A disc is the cushion between two vertebrae, a tough outer ring around a soft center. When the outer ring splits and the soft center pushes out, that bulge can press on a spinal nerve. The pressure, and the inflammation around it, is what produces sciatica, the shooting pain down the leg that most surgical patients know well.
The standard operation is a discectomy. Under general anesthesia, the surgeon makes a small incision over the affected level, moves the back muscles aside, and often removes a sliver of bone from the vertebra (a laminotomy) to reach the nerve. The fragment of disc pressing on the nerve is removed. Only the loose or protruding part comes out; the rest of the disc stays, because it still does the job of cushioning the spine. Microdiscectomy means the same steps done through a smaller opening with a microscope or magnifying lenses, and many centers use tubes or endoscopes to reduce muscle disruption further, as described by Johns Hopkins Medicine.
The operation usually lasts around an hour, and the Mayo Clinic notes that many people go home the same day or after one night. Because the nerve has been squeezed for weeks or months, relief of pain is often quick, while numbness or weakness can lag behind. That difference between what heals fast and what heals slowly is the reason a new symptom, rather than a lingering old one, is what deserves attention in the weeks that follow.
Herniated disc surgery warning signs: why the first two weeks matter most
Surgeons think about the recovery period in layers. In the first 48 hours the concern is bleeding and anesthesia after-effects. From about day three to day fourteen, the wound and the deep tissue are most vulnerable to infection and to leaks of spinal fluid. Blood clots can form in the legs during any stretch of reduced mobility. And throughout, the nerve itself can be irritated by a new bleed, swelling or, rarely, a fresh fragment of disc.
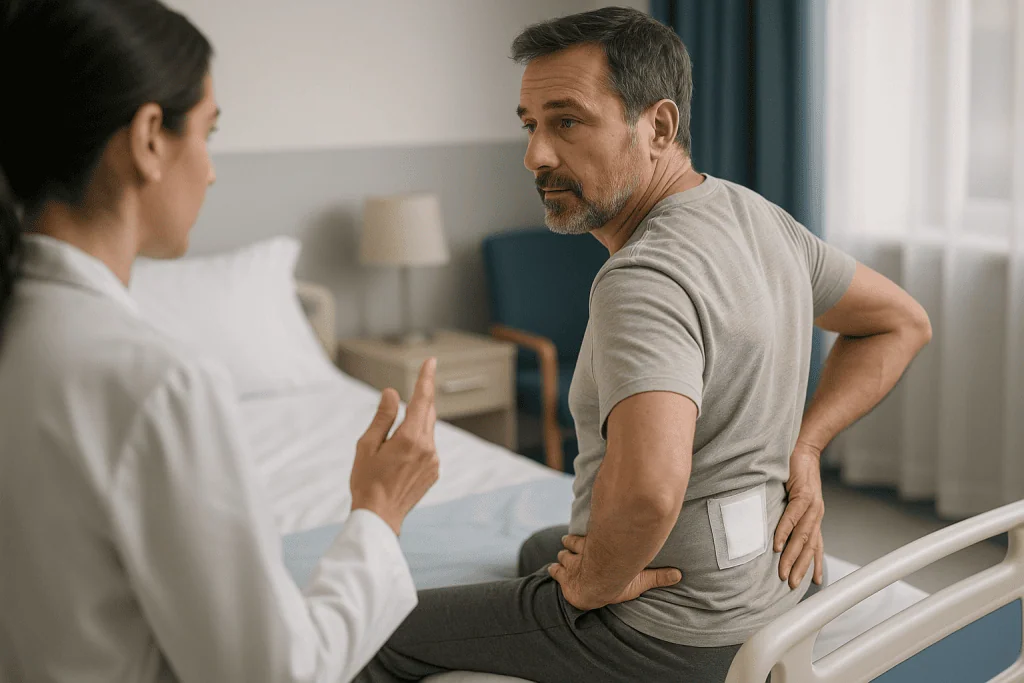
That layering explains why discharge instructions from sources such as MedlinePlus concentrate on a short list: fever, wound changes, leg symptoms and bladder or bowel changes. Each corresponds to a complication that is most treatable when caught early.
Ordinary healing has its own noise. Expect the incision to be tender and slightly firm, expect some bruising, expect the operated area to feel stiff by evening. Nerve pain can flare briefly around days two to five as anesthetic wears off and swelling peaks; clinicians sometimes call this a “post-operative flare”. Tingling in the leg that comes and goes is common as the nerve recovers.
The distinction that helps most is direction of travel. Symptoms that are gradually improving, even with bumps, are usually the healing process. Symptoms that are new, or that were improving and then reverse, are the ones to report. Nobody expects you to diagnose the cause. The job at home is simply to notice, describe and call, and the rest of this article is about doing that well.
Wound leaks after a discectomy: what clear, bloody or cloudy fluid can mean
A small amount of pinkish or pale yellow staining on the dressing in the first two or three days is common. It is a mix of blood and serous fluid, the thin liquid tissues release while healing. It should decrease each day and stop.
Three patterns are different. The first is fluid that keeps coming, especially clear, watery fluid that soaks a dressing or trickles out when you stand. Behind the nerves sits the dura, a membrane holding cerebrospinal fluid (CSF), the clear liquid that bathes the brain and spinal cord. If the dura was nicked during surgery, or a repair has not sealed, CSF can track to the skin. The NHS lists a dural tear as one of the recognized risks of lumbar decompression. A telltale companion is a headache that eases within minutes of lying flat and returns on sitting up, sometimes with nausea or neck stiffness. Persistent CSF leaks matter because they can delay wound healing and open a route for infection.
The second pattern is thick, cloudy or foul-smelling discharge, particularly with redness spreading beyond the incision edges, increasing warmth, or a wound that was closed and has opened. That is the picture of a surgical site infection, which the CDC describes as typically appearing within 30 days of an operation.
The third is fresh, bright red bleeding that does not stop with firm pressure. It is uncommon after this operation but needs a same-day call.
Do not test the fluid yourself, and do not re-dress the wound with home remedies. Photograph the dressing, note the time, and phone the surgical team. Describing color, volume and how long it has been happening is exactly the information they need.
Fever after herniated disc surgery: signs of infection after discectomy
A mild temperature in the first day or two is common after any operation. Anesthesia, fluid shifts and the inflammatory response to tissue injury all nudge body temperature upward. The threshold most discharge instructions use, including MedlinePlus, is 100.4°F (38°C). A reading at or above that level, or any fever that appears after the first 48 hours or returns after settling, should be reported.

The timing carries information. Fever in the first two days often reflects the lungs: shallow breathing after anesthesia lets small airways collapse, so deep breathing, coughing and walking are protective. Fever from day three onward, especially with wound changes, is more suggestive of infection at the incision or in the deeper tissue.
The CDC notes that surgical site infections affect roughly 1 to 3 in every 100 people having surgery overall. Spine surgery rates vary with the procedure and the person; risk rises with diabetes, smoking, obesity, longer operations and steroid use. Beyond the skin, a deep infection can involve the disc space itself, called discitis. Its calling card is often not the wound at all but new, severe back pain that is worse at night and with any movement, sometimes weeks after surgery, with or without fever.
Infections at this depth are treated with antibiotics chosen against the specific organism, sometimes with drainage or washout in the operating room. The decision on tests and treatment sits with the surgical team, which is why an early call matters more than trying to gauge severity at home. Bring a thermometer reading, the time, and a list of any other changes you have noticed.
New weakness or numbness after herniated disc surgery: the sign that should never wait
Here is the pattern that surgeons want to hear about the same day: a leg that was working after surgery and is now weaker. Not the foot that was already weak before the operation and has not yet recovered. New weakness, or a clear step backward.
The most common early cause is a hematoma, a collection of blood in the space where the surgery was done. Because the spinal canal is a rigid tube, even a modest clot can press on nerves. It tends to declare itself within hours to a few days, with rising back pain followed by leg numbness, weakness or bladder difficulty. The Mayo Clinic lists bleeding and nerve injury among the recognized risks of discectomy. A second cause is recurrent herniation, where another fragment of the same disc pushes out through the original tear; it can happen early, after a cough or an awkward lift, or months later. A third is nerve inflammation, which produces more pain than weakness and usually settles.
How do you check without a checklist? Compare sides doing ordinary things. Can you rise onto your toes and heels? Does the foot drag or slap when you walk? Is there a new numb patch you can map with a fingertip? Report what has changed since discharge, not what was already there.
Timing shapes urgency. Weakness that develops over hours, or weakness together with any change in bladder control, is an emergency evaluation, not a wait-for-Monday matter. Compressed nerves recover best when pressure is relieved early, and imaging can distinguish the causes quickly. Leave the interpretation to the team; your task is to make the call promptly.
Cauda equina symptoms after surgery: bladder, bowel and saddle numbness
Below the level where the spinal cord ends, the nerve roots hang in a bundle that anatomists named the cauda equina, Latin for “horse’s tail”. These nerves control the bladder, the bowel, sexual function and sensation in the area that would touch a saddle. When something compresses the whole bundle, the result is cauda equina syndrome, a rare but genuine surgical emergency, as Johns Hopkins Medicine describes.
After a discectomy, the culprits are the same as for new weakness: a post-operative hematoma or a large recurrent fragment. The signs are specific. Difficulty starting to urinate, or not feeling the bladder fill, or passing urine without realizing it. Loss of the urge to open the bowels, or leakage. Numbness or a strange, distant feeling around the genitals, anus and inner thighs. Weakness in both legs rather than one. Sometimes new pain radiating down both sides.
Two sources of confusion deserve a plain answer. First, difficulty passing urine in the first day after surgery is common because anesthesia and certain pain medicines relax the bladder; hospital staff monitor for it. That is different from new bladder change appearing after you have been passing urine normally at home. Second, opioid pain medicines cause constipation, which is not the same as losing the sensation of needing to go. If you cannot tell the difference, that uncertainty itself justifies a call.
Cauda equina syndrome is usually confirmed with an urgent MRI and treated with prompt decompression. Outcomes for bladder and bowel function depend in part on how quickly pressure is relieved, which is why every reputable guideline treats these symptoms as “go now” rather than “phone in the morning”. Keep the emergency number where you can find it.
Calf pain and breathlessness: blood clots after spine surgery
Any operation followed by days of lying and sitting more than usual raises the risk of deep vein thrombosis (DVT), a clot in a deep leg vein. The mechanism is simple plumbing: calf muscles act as pumps that push blood back toward the heart, and when they stop squeezing, blood pools and can clot. Surgery also shifts the blood into a clotting-prone state for a few weeks.
The classic signs are swelling of one calf compared with the other, a deep ache or tightness that is worse on standing, warmth and a slightly reddish or bluish tinge. It is easy to dismiss because the operated leg may already ache, but a DVT usually feels different in character and location, more in the muscle belly than along the nerve’s path.
The dangerous progression is a pulmonary embolism, when part of the clot travels to the lungs. Sudden shortness of breath, sharp chest pain that worsens on breathing in, a racing heart, coughing up blood or feeling faint are emergency symptoms. Call emergency services rather than the surgeon’s office.
Prevention is mostly movement. The NHS recovery guidance encourages walking as soon as it is safe, often within a day of surgery, and building up gently. Ankle pumps in bed, staying hydrated and avoiding long stretches of sitting all help. Compression stockings or blood-thinning injections are used for some people based on individual risk, a decision that belongs to the surgical team. If you were prescribed either, the instructions you were given override anything general here.
Clot risk does not end at discharge; it tapers over several weeks. A new, one-sided calf symptom at week three still deserves the same phone call as one at day three.
Herniated disc surgery warning signs at a glance: normal, call today, call now
The table below is a triage aid, not a diagnostic tool. Where a symptom could fit more than one row, treat it as the more urgent one and let the team downgrade it.
| What you notice | Usually part of healing | Call the surgical team today | Emergency care now |
|---|---|---|---|
| Wound | Light pink or yellow staining in the first 2–3 days, fading daily | Ongoing clear watery leak; cloudy or smelly discharge; spreading redness; wound edges opening | Bleeding that does not stop with 10 minutes of firm pressure |
| Temperature | Feeling warm in the first 24–48 hours with normal readings | 100.4°F (38°C) or higher; fever after day 2; fever returning | High fever with confusion, rigors or rapid breathing |
| Back pain | Incision soreness and stiffness easing over 1–2 weeks | New severe back pain, worse at night or with any movement, especially weeks after surgery | Rapidly escalating back pain with leg or bladder change |
| Leg symptoms | Tingling that comes and goes; pre-existing numbness slow to improve | New numb patch; pain that returns after clear improvement | New or worsening weakness; foot drop; weakness in both legs |
| Bladder and bowel | Constipation from pain medicines | Hesitancy or reduced sensation you are unsure about | Retention, incontinence, saddle numbness |
| Headache | Mild, after poor sleep or caffeine change | Headache that eases lying flat and returns on sitting | Severe headache with neck stiffness and fever |
| Legs and chest | Mild ankle puffiness in both legs | One calf swollen, warm or tender | Sudden breathlessness, chest pain, coughing blood, fainting |
Thresholds are drawn from discharge guidance such as MedlinePlus and the NHS. Your own team’s written instructions take precedence wherever they differ.
Who usually has this surgery, and who is usually asked to wait
Discectomy is not the first answer to a herniated disc. The NHS notes that most herniations settle with time, activity and pain management, typically improving over several weeks, because the extruded material shrinks and inflammation fades. Surgery is generally considered when leg pain from a confirmed nerve compression on MRI persists after a fair trial of non-surgical care, or when pain is so severe that daily function has collapsed.
A smaller group is offered surgery promptly rather than after waiting: those with progressive weakness in the leg or foot, and anyone with cauda equina syndrome, where delay risks permanent bladder and bowel dysfunction. Here the operation is about protecting nerve function rather than relieving pain.
People are usually asked to wait, or steered toward other options, when the main complaint is back pain rather than leg pain. Removing a disc fragment relieves nerve pressure; it does little for pain that comes from the disc, joints and muscles themselves. Waiting is also common when the MRI findings do not match the symptoms, when the herniation is small and recent, or when medical conditions such as poorly controlled diabetes, active infection or heavy smoking raise complication risk and can be improved first. The Cleveland Clinic describes this stepped approach in plain terms.
Why does this matter for warning signs? Because the reason you had surgery shapes what “better” should look like. Someone operated on for foot weakness may take months to see strength return, and slow recovery is not a warning sign. Someone operated on for pain who wakes with new weakness has a different story, and that is a call. Ask your surgeon before discharge which symptoms they expect to linger in your case; it makes every later judgment easier.
How long does it take to recover from herniated disc surgery? Discectomy recovery time by week
Recovery has a shape, and knowing it helps you tell a setback from a normal plateau.
Days 1 to 3. Most people walk within a day, as the NHS describes, and go home the same day or after one night. Leg pain is often dramatically better; incision pain and stiffness take its place. Short, frequent walks are the main therapy.
Week 1 to 2. Wound care and the highest-alert window for infection and leaks. Walking distance grows daily. Most surgeons ask people to avoid bending at the waist, lifting more than a light bag and twisting, often summarized as “no bending, lifting, twisting”. Sitting for long periods tends to be uncomfortable; short sits, then a walk, works better. A wound check or stitch removal usually falls around the end of this window.
Weeks 2 to 6. Energy returns. The NHS recovery page suggests that people in desk-based roles often return to work around 4–6 weeks, while heavy manual work usually takes longer; driving typically resumes once you can perform an emergency stop comfortably and are off sedating medicines, and your team and insurer should confirm timing. Physical therapy, where prescribed, usually begins here, focusing on walking tolerance, gentle core activation and posture rather than strength work.
Weeks 6 to 12. Gradual return to normal lifting and exercise under guidance. Nerve symptoms continue to improve slowly; numbness in particular can take months, and some residual numbness can be permanent, as the Mayo Clinic notes.
These are typical ranges, not promises. Age, fitness before surgery, how long the nerve was compressed and the physical demands of your job all shift the timeline, and your surgeon’s plan for you overrides any general schedule.
Can the same disc herniate again? Recurrent disc herniation after surgery
Yes. A discectomy removes the fragment that escaped but cannot rebuild the torn outer ring, so the remaining disc material can push through the same defect. People often ask how many times one disc can herniate; there is no fixed number, though each recurrence tends to leave less material to extrude and a stiffer, narrower disc space.
How common is it? Patient references such as the Mayo Clinic describe recurrence as a recognized risk affecting a minority of people, and published series typically report figures in the region of roughly 5 to 15 percent over the years following surgery, with substantial variation by study design and follow-up length. Treat any single number you see online with caution; the honest summary is “uncommon, but real enough to plan for”.
Risk factors that surgeons discuss include a large defect in the outer ring, smoking, diabetes, obesity, heavy manual work and returning to strenuous lifting too early. Some of these can be changed and some cannot.
What does recurrence feel like? Often a replay of the original leg pain, sometimes triggered by a cough, sneeze or awkward lift, though it can also arrive gradually. Early recurrence in the first weeks is one reason new leg pain after clear improvement belongs on the call list. Recurrence is diagnosed with MRI, and treatment follows the same logic as a first herniation: non-surgical care unless there is significant weakness, cauda equina symptoms or intractable pain, in which case a repeat operation is considered. After more than one recurrence, some surgeons discuss fusion, joining the two vertebrae so the disc space no longer moves, which trades motion for stability. Whether that trade makes sense is an individual conversation with the treating team.
Is herniated disc surgery worth it? Risks of L4-L5 disc surgery, weighed honestly
“Worth it” only has an answer against an alternative, and the alternative for most herniations is continued non-surgical care. Trials that compared the two paths found that surgery tends to relieve leg pain faster in the months after treatment, while many people who avoided surgery caught up over one to two years. That summary, reflected in the Mayo Clinic’s framing of who benefits, means the value of surgery is largely about time: how many months of severe pain you are prepared to trade against a small set of surgical risks.
The L4-L5 and L5-S1 levels are where most lumbar herniations occur, so the risk list for L4-L5 surgery is the general list for discectomy. The NHS and Mayo Clinic describe them in similar terms: wound infection; a dural tear with spinal fluid leak; bleeding, occasionally forming a hematoma that presses on nerves; injury to a nerve root, which at L4-L5 can affect ankle lift and cause foot drop; recurrent herniation; persistent or returning symptoms; and rare complications of anesthesia or blood clots. Very rare events include injury to blood vessels in front of the spine.
Against those, the risks of not operating are worth naming plainly too: prolonged pain that limits sleep and work, deconditioning, and, in the presence of progressive weakness, the chance that a compressed nerve does not fully recover.
Neither column contains a guarantee. What the evidence supports is a considered choice made with your surgeon, based on your symptoms, your imaging, your work and your tolerance for uncertainty. If leg pain dominates and the MRI matches, surgery is a reasonable option with a well-described risk profile; if back pain dominates, the calculation usually shifts the other way.
What people often get wrong about herniated disc surgery warning signs
“Some leaking is normal, so all leaking is normal.” Light staining that fades over a couple of days is normal. Fluid that keeps coming, or that is clear and watery, or that starts after the wound was dry, is not, and a positional headache alongside it points toward spinal fluid.
“No fever means no infection.” Deep infections in the disc space frequently present with worsening back pain and normal temperature, sometimes weeks later. Fever is one signal, not the only one.
“Pain returning means the surgery failed.” A pain flare around days two to five, or a temporary return of tingling as the nerve recovers, is common. What matters is trajectory and whether new weakness or bladder change accompanies it. Recurrent herniation is a possibility, but it is confirmed by imaging, not by a bad day.
“Numbness should be gone by now.” The Mayo Clinic is explicit that numbness can persist for months and may not fully resolve, particularly when the nerve was compressed for a long time before surgery.
“Bed rest protects the surgery.” The opposite is closer to the truth. Walking early lowers clot risk, helps the lungs and keeps the back mobile; what surgeons restrict is bending, lifting and twisting, not walking.
“The surgeon fixed the disc.” The operation removed the piece pressing on the nerve. The disc remains injured, which is why the same level can herniate again and why long-term back care still matters.
“Constipation is a red flag for cauda equina.” Constipation from opioid pain medicines is expected. Losing the sensation of needing to go, leaking without warning, or numbness around the saddle area is the red flag. If you cannot tell which you have, call.
Questions to ask your care team before you go home
The best time to sort out warning signs is before you need to. Write these down and keep the answers with your discharge paperwork.
- Which of my current symptoms do you expect to persist, and for roughly how long? (This tells you what is not a warning sign in your specific case.)
- Was there a dural tear or any other event during surgery that changes what I should watch for?
- What exactly should the wound look like at day 3, day 7 and day 14? Can I shower, and when?
- What temperature reading do you want reported, and at what time of day should I check if I feel unwell?
- Which number do I call during office hours, which after hours, and which symptoms should send me to emergency care rather than the phone?
- Am I on any medicine to prevent blood clots, and how long should I keep moving on a schedule?
- What are my specific limits on bending, lifting, sitting and driving, and when will they be reviewed?
- When is my wound check and follow-up, and who removes any stitches or clips?
- If pain medicines are prescribed, what is the plan for tapering them, and who do I ask if I have side effects?
- What is my plan for physical therapy, and when does it start?
- If my leg pain comes back, what would you want to know before deciding on imaging?
- Is there anything about my health, such as diabetes, smoking or steroid use, that puts me at higher risk of infection or slow healing?
Discharge guidance from MedlinePlus covers the general answers, but your surgeon’s answers for you are the ones that count. If a family member or friend is helping at home, have them listen too; a second set of ears remembers different things.
When to call your doctor
Call the surgical team the same day if you notice any of these: a temperature of 100.4°F (38°C) or higher, or any fever appearing after the first two days; fluid that keeps leaking from the wound, especially clear watery fluid; cloudy, thick or foul-smelling discharge; redness spreading beyond the incision, increasing warmth or the wound opening; new severe back pain, particularly pain that is worse at night or with every movement; leg pain that returns after clear improvement; a new numb patch; a headache that eases when you lie flat and returns on sitting; or one calf that is swollen, warm or tender.
Go to emergency care, or call emergency services, without waiting for a call back if you have: new or worsening weakness in a leg or foot, or weakness in both legs; difficulty passing urine, loss of bladder or bowel control, or numbness around the genitals, anus or inner thighs; sudden shortness of breath, chest pain, coughing up blood or fainting; bleeding from the wound that does not stop after ten minutes of firm pressure; or a high fever with confusion, shaking chills or rapid breathing.
These thresholds reflect discharge guidance from MedlinePlus, the NHS and cauda equina information from Johns Hopkins Medicine. When you call, have ready your surgery date, the symptom, when it started, your temperature and a photo of the wound if relevant.
One principle covers everything above: after spine surgery, an unnecessary phone call costs a few minutes, while a missed one can cost nerve function. Surgical teams would rather hear from you. Every decision about tests and treatment rests with them; your part is to notice early and describe clearly.
Frequently asked questions
What are the most important herniated disc surgery warning signs in the first two weeks?
Fever of 100.4°F (38°C) or higher, ongoing wound leakage, spreading redness or pus, new leg weakness, saddle numbness, bladder or bowel change, a positional headache and one-sided calf swelling. Each corresponds to a complication that is most treatable early. Report new symptoms or reversals of improvement; lingering pre-existing numbness is usually expected.
How long does it take to recover from herniated disc surgery?
Most people walk within a day and go home within one to two days; desk-based work often resumes around 4–6 weeks according to NHS recovery guidance, with heavier work taking longer. Leg pain frequently eases quickly, while numbness can take months and may not fully resolve. Your surgeon’s timeline for your circumstances is the one to follow.
What are the signs of infection after discectomy?
Redness spreading beyond the incision, increasing warmth, cloudy or foul-smelling discharge, a wound that opens, and fever at or above 100.4°F (38°C). Deep infection in the disc space may cause severe, worsening back pain that is worse at night, sometimes without fever and sometimes weeks after surgery. Any of these should be reported the same day.
What are cauda equina symptoms after surgery, and how urgent are they?
Difficulty starting or feeling urination, incontinence of urine or stool, numbness around the genitals, anus or inner thighs, and weakness in both legs. They suggest pressure on the bundle of nerves at the base of the spine and are treated as an emergency because bladder and bowel recovery depends partly on how quickly pressure is relieved. Go to emergency care immediately.
Is herniated disc surgery worth it?
It depends on what you are comparing it with. Trials suggest surgery relieves leg pain faster in the months after treatment, while many people managed without surgery improve over one to two years. Surgery carries small risks of infection, dural tear, nerve injury and recurrence. It is generally most reasonable when leg pain dominates, MRI matches symptoms and non-surgical care has not helped.
How many times can you herniate the same disc?
There is no fixed limit. Surgery removes the escaped fragment but cannot repair the torn outer ring, so the remaining material can push through again. Recurrence affects a minority, with published series often in the 5 to 15 percent range. Each recurrence leaves less disc material and a stiffer segment, and after repeated recurrences some surgeons discuss fusion as an option.
What are the risks associated with L4-L5 disc bulge surgery?
The main risks are wound infection, a dural tear with spinal fluid leak, bleeding that can form a nerve-compressing hematoma, nerve root injury (which at L4-L5 can affect ankle lift), recurrent herniation, persistent symptoms, blood clots and anesthetic complications. Very rarely, blood vessels in front of the spine can be injured. Your surgeon can put these in the context of your health.
Is it normal for the wound to leak after herniated disc surgery?
Light pink or pale yellow staining in the first two or three days that fades daily is common. Fluid that keeps coming, clear watery fluid, discharge that starts after the wound was dry, or anything cloudy or foul-smelling is not, and should be reported the same day. Photograph the dressing and note the time before calling.
Why does my back pain feel worse a few days after discectomy?
A flare around days two to five is common as local anesthetic wears off and swelling peaks; incision soreness and stiffness usually ease over one to two weeks. The pattern that needs a call is different: new severe pain that escalates, is worse at night or with every movement, or comes with fever, leg weakness or bladder change.
What does recurrent disc herniation after surgery feel like?
Often a replay of the original leg pain, sometimes triggered by a cough, sneeze or awkward lift, occasionally arriving gradually. It can occur within weeks or years later. Diagnosis needs an MRI, and treatment follows the same logic as a first herniation, with repeat surgery considered for significant weakness, cauda equina symptoms or intractable pain.
References
- MedlinePlus: Spine surgery – discharge
- NHS: Lumbar decompression surgery – Recovery
- Cleveland Clinic: Herniated Disk
- CDC: About Surgical Site Infections
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Is Scoliosis Surgery Recommended? Curve Size, Progression and Symptoms That Matter
Scoliosis surgery is usually recommended when a curve measures about 45 to 50 degrees or more on the Cobb angle, is still progressing, and…
Why Repeat X-Rays Matter During Scoliosis Bracing: Checking Fit, Growth and Curve Control
Repeat X-rays during scoliosis bracing let the care team measure the Cobb angle, check how well the brace is holding the curve, and track…

Who Is a Candidate for Nucleoplasty? Contained Disc Herniations and Who Needs Another Option
A nucleoplasty candidate is typically an adult with leg-dominant pain from a small, contained lumbar disc herniation, confirmed on MRI, whose symptoms have not…

Questions to Ask Before Spinal Stenosis Surgery: Levels, Fusion and the Recovery Plan
Before spinal stenosis surgery, ask your surgeon which spinal levels will be treated and why, whether a fusion is planned or decompression alone is…
Schroth Method Results: What Consistent Practice Can Realistically Change and What It Cannot
Consistent Schroth practice most reliably changes posture, trunk symmetry, breathing mechanics, muscle endurance, and how a person feels about their back. Small randomized trials…

When Does a Herniated Disc Need Surgery? Weakness, Persistent Sciatica and Time Limits
A herniated disc usually needs surgery only when a nerve is being damaged or when pain has outlasted a fair trial of nonsurgical care.…