

Before Chalazion Surgery: Medication Checks, Bleeding History and the Ride Home

Key Takeaways
- A chalazion is a sterile blocked oil gland, not an infection, which is why antibiotics have no direct target and warm compresses remain the first-line approach.
- Incision and curettage is usually performed through the inner surface of the eyelid under local anesthetic, so most people have no visible skin scar and no stitches.
- Never stop an anticoagulant or antiplatelet medicine yourself before chalazion surgery; the prescribing doctor and surgeon decide together, and often the drug is continued.
- A careful bleeding history, including dental bleeding, heavy periods and family clotting disorders, is the main pre-operative screen, since routine blood tests are not standard for minor eyelid procedures.
- A firm eye pad is usually worn for several hours or overnight, removing depth perception and part of the visual field, so arrange a driver or escort home.
- Firmness in the lid for a week or two after surgery is normal healing tissue; a lump that grows or returns at the same site needs a follow-up review.
Preparing for chalazion surgery is mostly about information rather than fasting or special equipment. Before the procedure, tell your eye care team every medicine and supplement you take, especially blood thinners, aspirin or antiplatelet drugs, and any history of unusual bleeding or bruising. Arrange someone to drive you home, because the eye is often padded afterward. Your treating team decides whether any medicine should be adjusted.
The lump has been there for six weeks. It is not painful anymore, just a firm, rubbery bead under the upper lid that catches the light in every photograph and makes the eye look half-asleep. The warm flannel routine has been faithfully done, morning and night, and the bead has barely shrunk. The eye doctor has now said the word that was quietly dreaded: a small procedure.
What follows is a familiar scramble. Should the morning aspirin be skipped? Does a daily blood thinner matter for something this small? Will it hurt? Can you just drive yourself home afterward? None of these questions are silly, and all of them have reasonable, evidence-based answers.
Preparing for chalazion surgery is less about fasting and hospital gowns and more about a short, honest conversation with your care team before the day. This article walks through what that conversation should cover, what actually happens in the room, and what the days afterward usually look like.
What preparing for chalazion surgery really involves
A chalazion is a firm, usually painless lump in the eyelid caused by a blocked meibomian gland, one of the tiny oil glands that line the lid margin and keep tears from evaporating too quickly. When the gland’s opening clogs, oil backs up, leaks into the surrounding tissue, and the body walls it off into a slow, rubbery swelling. According to MedlinePlus, many chalazia settle on their own within a month or so, especially with regular warm compresses, which is why surgery is rarely the first step.
When a chalazion persists, keeps returning, blurs vision by pressing on the cornea, or simply will not shrink, an eye care clinician may offer a minor procedure called incision and curettage. In plain terms, that means a small cut and a gentle scrape to empty the trapped material. It is almost always done under local anesthetic, meaning a numbing injection into the lid while you stay awake.
Because the operation is quick and the wound is tiny, preparation looks different from what most people imagine. There is usually no fasting, no overnight stay, and no sedation for adults. What matters instead is a short medical conversation covering three things: the medicines you take, your personal and family bleeding history, and how you will get home with an eye pad on.
Those three topics form the backbone of this guide. Each one exists because of a concrete mechanism. The eyelid has a dense blood supply, so anything that thins the blood changes how much bleeding the surgeon sees and how much bruising you carry afterward. The eye pad changes your depth perception and your legal fitness to drive. Treat the pre-op questions as the real preparation, and the day itself tends to feel much smaller than the worry beforehand.
How chalazion incision and curettage actually works
Picture a clinic treatment room rather than an operating theater. You lie back on a reclining chair, the skin around the eye is cleaned with antiseptic, and a drop of anesthetic goes onto the eye surface. The clinician then injects a local anesthetic into the eyelid around the lump. Most people describe this as a sharp pinch and a brief sting that fades within a minute as the tissue numbs.
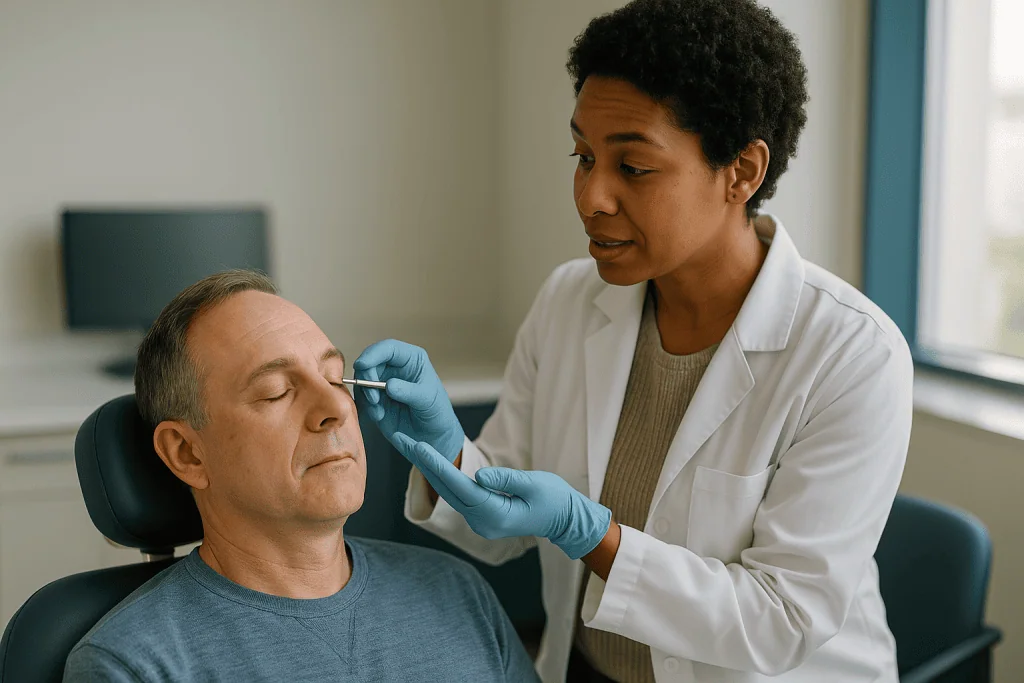
Once the lid is numb, a small clamp is placed around the chalazion. The clamp does two useful things: it holds the lid steady and it squeezes the surrounding blood vessels, which keeps bleeding to a minimum. The surgeon then everts the lid, turning it inside out so that the cut can be made on the inner, conjunctival surface rather than through the skin. A short vertical incision is made into the lump, and a small spoon-shaped instrument, the curette, is used to scrape out the thick, granular contents and the lining of the cyst wall.
Scraping the wall matters more than draining the fluid. A chalazion is not a water balloon; it is a pocket of inflamed, fatty material with a lining that can refill if left behind. Cleveland Clinic describes the procedure as taking only a few minutes once the area is numb, which matches most people’s experience.
Stitches are usually unnecessary because the cut faces inward and the lid tissue heals quickly against itself. Antibiotic ointment is often applied, the clamp comes off, gentle pressure is held, and a firm eye pad goes on. That pad is the reason for the ride home discussed later. Some lumps that have broken through the skin, or that sit very near the surface, may be approached through the outer skin instead, and in that case a stitch or two may be placed.
Who is usually offered chalazion surgery, and who is usually asked to wait
The honest answer is that most people with a chalazion are asked to wait, at least at first. Mayo Clinic and MedlinePlus both describe warm compresses and gentle lid massage as the mainstay of early care, because a lump that is still soft and inflamed often drains on its own once the gland opening softens. Operating on a fresh, angry chalazion can also be messier, with more bleeding and a higher chance that inflamed tissue is left behind.
Surgery tends to be discussed when the lump has become firm and quiet but has not gone away after several weeks of consistent compress use, when it is large enough to press on the eye and distort vision, when it has recurred in the same spot, or when it affects a child’s developing vision. For adults, an alternative that may be offered is a steroid injection into the lump, which aims to calm the inflammation without a cut. The choice between injection and incision depends on size, position, skin color (steroid injections can occasionally lighten the skin), and the clinician’s judgment.
Several groups are commonly asked to pause before surgery. A person on anticoagulant medicine whose prescribing doctor has not been consulted. Someone with an active eyelid infection, where the lid is hot, red and tender, since that picture suggests a stye or cellulitis rather than a quiet chalazion. Anyone whose lump has returned repeatedly in exactly the same place, particularly in older adults, because a recurrent “chalazion” occasionally turns out to be something else, and the surgeon may want tissue sent for examination.
Children are a special case. The procedure is the same, but young children usually cannot hold still under local anesthetic, so a general anesthetic in a day-surgery setting may be arranged. Preparation for that pathway, including fasting instructions, comes from the anesthetic team and should be followed exactly.
Medication checks: why blood thinners and antiplatelets matter for a tiny cut
It seems disproportionate that a two-minute eyelid procedure prompts a medication review, but the mechanism is straightforward. The eyelid is one of the most richly supplied tissues in the body, and the surgeon works through a clamp precisely because bleeding obscures the field. Anything that reduces the blood’s ability to clot changes how clean the view is and how much bruising you carry home.

Two broad classes deserve a mention by name, not as advice but so that you recognize them on your own list. Anticoagulants, sometimes called blood thinners, are medicines such as warfarin or the newer direct oral anticoagulants that slow the clotting cascade itself. Antiplatelet drugs, including low-dose aspirin and clopidogrel, work differently: they stop platelets, the tiny cell fragments that plug a cut, from sticking together. Both groups are usually prescribed for a serious reason, such as a previous stroke, heart valve, stent or clot, and stopping them carries its own risk.
This is the single most important sentence in this section: do not stop or alter any prescribed medicine on your own before chalazion surgery. For many minor eyelid procedures, surgeons choose to operate with these medicines continued, accepting more bruising rather than exposing a patient to a clot. For others, the eye team will contact the prescribing doctor to agree a plan. The decision is theirs, made together, and it depends on why you take the drug.
Bring a written or photographed list of everything, including over-the-counter pain relievers, fish oil, high-dose vitamin E, ginkgo and other supplements that can mildly affect platelet function. People regularly forget these because they do not feel like medicines. Also mention any steroid tablets or inhalers, diabetes medicines, and anything that affects blood pressure, since all of these can influence healing or bleeding in small ways the team will want to know about.
Your bleeding history: the questions you will be asked and why they matter
Expect a short set of questions that sound unrelated to your eyelid. Do you bruise easily? Did you bleed for an unusually long time after a dental extraction, a cut, or childbirth? Has anyone in your family been diagnosed with a bleeding disorder such as hemophilia or von Willebrand disease? Have you ever needed a transfusion after a minor operation?
These questions exist because a formal blood test before a minor eyelid procedure is not routine, and a careful history is actually a more sensitive screen for most inherited clotting problems than a standard laboratory panel. Von Willebrand disease, the most common inherited bleeding disorder, often shows up as heavy periods, nosebleeds and prolonged bleeding after dental work rather than anything dramatic. Many people reach adulthood without a diagnosis and only discover it when a surgeon asks the right question.
If anything in your answers raises a flag, the team may do three things. They may send blood tests to check platelet count and clotting times. They may discuss the procedure with a hematologist, a doctor who specializes in blood disorders. Or they may simply plan for a little more care on the day: a slightly longer period with the clamp on, a firmer pad, and a longer wait in the clinic before you leave.
Liver disease and heavy alcohol use also belong in this conversation, because the liver manufactures most clotting proteins. So does kidney disease, which can affect how platelets behave. None of these conditions necessarily rules out surgery. They simply shape how it is done.
One practical tip from the clinic side: people frequently answer “no” to bruising questions and then mention, almost as an aside, that their arms are always covered in marks. Say the aside first. Small details give the surgeon a truer picture than a tidy yes-or-no answer, and nobody is judged for having fragile skin or a family history they cannot control.
Does chalazion surgery hurt? An honest account of each stage
The short version: the injection stings, the procedure itself is pressure rather than pain, and the following day or two feel bruised and gritty. Most people say the anticipation was worse than the event.
Break it down by stage. The anesthetic drop on the eye surface stings for a few seconds. The injection into the lid is the part most people remember; the needle is fine, but the lid is sensitive and the fluid stretches tissue as it goes in. The sting is typically over within a minute. Some surgeons apply a numbing gel or press a cold pack to the lid first to dull that sensation, and it is perfectly reasonable to ask whether that is offered.
Once the lid is numb, the clamp produces a squeezing, tugging feeling. You may hear or feel the scraping, which can be unpleasant in the way dental work is unpleasant, but it should not be sharp. If it is sharp, say so immediately. More anesthetic can be added, and no surgeon wants a patient white-knuckling the armrest.
Afterward, as the numbness wears off over a couple of hours, the lid feels sore, heavy and bruised, rather like the day after a knock to the eye. A plain over-the-counter pain reliever of the kind your team recommends is usually enough; many eye clinics specifically suggest avoiding aspirin-based products for pain in the days after, because of the platelet effect described earlier, but that choice belongs to your team. A cold compress in the first day can ease swelling.
Grittiness and mild watering are common for a few days because the cut sits on the inner lid surface and brushes the eye each time you blink. That sensation settles as the surface heals. Severe, worsening pain is not expected and is covered under red flags later in this article.
The ride home: why you should not drive yourself after chalazion surgery
The eye pad is the detail that catches people out. After the procedure, a firm dressing is usually taped over the closed eye to apply pressure and limit bleeding, and clinics commonly ask that it stay on for several hours or until the next morning. With one eye covered, you lose binocular depth perception, the overlap between two slightly different views that lets you judge distance. You also lose roughly a third of your visual field on that side. Neither is safe behind the wheel, and in many places driving with an eye pad would not meet legal vision standards for a license.
Even without the pad, the operated eye is likely to be watering, blurry from ointment, and sensitive to glare. The unoperated eye works fine, but your brain needs both inputs to merge smoothly, and the mismatch can be disorienting for the first hours.
Plan the journey before the day. The simplest option is a friend or family member who can drive, wait, and take you home. Public transport or a taxi is acceptable for most adults who feel steady, but being escorted is still wise, because stairs, curbs and crowded platforms are harder to judge with one eye. If sedation or a general anesthetic is used, which is typical for children and occasionally for very anxious adults, a responsible adult must accompany the patient home and stay with them overnight. That rule is not negotiable in day-surgery units.
Also think about the evening. Reading, screens and cooking are all slightly awkward one-eyed, and bending forward or lifting heavy items can increase pressure in the head and encourage oozing from the wound. Lay out what you will need, prepare a simple meal in advance, and keep the first night quiet. Most people are back to ordinary tasks, with the pad off, by the following day.
Preparing for chalazion surgery: a one-page summary table
The table below gathers the practical points in one place. It is a prompt for conversation with your team, not a substitute for their instructions, which take priority if anything differs.
| Area | What to do or tell | Why it matters |
|---|---|---|
| Medicines | Bring a full list, including aspirin, supplements and herbal products; do not stop anything yourself | Blood thinners and antiplatelets change bleeding; the prescribing doctor decides any changes |
| Bleeding history | Mention easy bruising, prolonged bleeding after dental work, heavy periods, family bleeding disorders, liver or kidney disease | History is the main screen for clotting problems before minor eyelid surgery |
| Allergies | List reactions to anesthetics, antibiotics, iodine, latex or tape | Antiseptic, local anesthetic, ointment and dressings are all used |
| Eating and drinking | Usually no fasting for local anesthetic; follow fasting instructions exactly if general anesthetic or sedation is planned | Fasting is an anesthetic safety rule, not an eyelid rule |
| On the day | No eye makeup, no contact lens in the operated eye, bring glasses and sunglasses | Makeup and lenses raise infection risk; glare is uncomfortable afterward |
| Transport | Arrange a driver or escort; no driving with an eye pad | One covered eye removes depth perception and part of the visual field |
| Afterward | Clear a quiet evening; know how to reach the clinic | Oozing, discomfort and a pad make the first hours awkward |
Two rows deserve emphasis. Allergies are easy to forget because the procedure feels too small to involve drugs, yet it uses four or five products on and around the eye. And the makeup row is more than cosmetic: mascara and eyeliner sit exactly where the incision will be, and particles can be carried into the wound. Arrive bare-faced around the eyes, with clean lashes, and leave contact lenses out of the operated eye until the team says otherwise.
Chalazion surgery recovery time: what the first days and weeks usually look like
Recovery is quick but not instant, and knowing the usual rhythm prevents unnecessary alarm. These are typical patterns described by Cleveland Clinic and Johns Hopkins patient guidance, not guarantees; your own lid will follow its own schedule.
The first day is the pad day. Expect the dressing to stay on for several hours to overnight, some blood-tinged tears when it comes off, and a lid that is swollen, purple and tender. Ointment often makes vision smeary. A cold compress for short spells helps swelling, and sleeping with the head slightly raised reduces morning puffiness.
Days two to seven are the bruise days. The swelling peaks around the second day and then recedes. Bruising fades through the usual palette from purple to yellow over one to two weeks, as hemoglobin in the bruise breaks down. Many people feel presentable with glasses by day three or four. The lump itself may still be partly palpable because the lid is thickened by healing, which is a normal finding at this stage rather than a sign of failure.
Weeks two to four are the settling period. The inner wound has usually closed by the end of the first week, but residual firmness in the lid can take several weeks to soften as the inflammation fully resolves. A follow-up visit, if arranged, usually sits somewhere in this window so the clinician can confirm the gland area is quiet and that nothing needs a second look.
Work and daily life depend on the job. Desk-based tasks are often possible the day after; dusty, dirty or water-exposed work, swimming and contact sports are generally paused until the team is satisfied the wound has sealed, commonly a week or more. Flying is not restricted by the eyelid itself, though a pad and an unfamiliar airport are a poor combination in the first day.
Is it normal for a chalazion to be still there after surgery?
This is one of the most searched questions after the procedure, and the reassuring answer is that a lump-like feeling in the first week or two is expected. Scraping out the cyst leaves a cavity that fills with healing tissue, swelling and a small amount of blood. To the fingertip, that can feel remarkably similar to the original chalazion. The key difference is the trajectory: post-operative firmness softens week by week, while a true persistent chalazion stays the same or grows.
Several things can mean the lump has genuinely not gone. Sometimes a chalazion is actually a cluster of blocked lobules rather than one pocket, and the scrape empties the main chamber but leaves a smaller neighbor. Sometimes inflamed tissue at the edges was deliberately left to avoid damaging the lid margin or the lash roots. And sometimes a fresh chalazion forms in an adjacent gland, which is common in people with underlying blepharitis, a chronic inflammation of the lid margins that makes gland blockage more likely in the first place.
Recurrence rates after incision and curettage vary widely between studies and depend heavily on lump size and whether lid hygiene is maintained afterward, so no single figure applies to everyone. What the evidence consistently shows is that treating the underlying lid-margin condition reduces repeat blockages. Warm compresses, lid cleaning and management of any rosacea or dry eye are therefore not optional extras after surgery; they are the long-term plan.
Two situations warrant a conversation rather than patience. If the lump is clearly larger or more painful at two weeks than at one, or if it has returned in exactly the same spot after a previous excision, the clinician may want to look again. In recurrent same-site lumps, particularly in older adults, tissue is sometimes sent for laboratory examination to rule out rarer eyelid conditions, which is a routine precaution rather than a cause for alarm.
What about antibiotics such as doxycycline? Separating infection from blockage
People frequently ask whether a course of a tetracycline-class antibiotic, doxycycline being the familiar generic name, could spare them the procedure. The question deserves a precise answer, because it rests on a common confusion between a chalazion and a stye.
A stye, in medical terms a hordeolum, is an acute bacterial infection of a lash follicle or lid gland. It is hot, red, tender and often comes to a head. A chalazion is a sterile blockage: there is usually no active infection, which is why it is firm and painless and why a swab would grow nothing useful. Antibiotics act on bacteria, so for a quiet chalazion they have no direct target. NHS guidance on styes and chalazia emphasizes warm compresses rather than antibiotics for this reason.
Why, then, are tetracycline-class drugs sometimes prescribed? Not primarily for their antibacterial action. At lower levels, these medicines have anti-inflammatory effects and alter the composition of the oil the meibomian glands produce. Clinicians sometimes use them for people with chronic blepharitis or ocular rosacea who develop repeated chalazia, aiming to reduce the frequency of new blockages rather than to shrink an existing lump. The evidence for this preventive role comes from small studies and expert consensus rather than large trials, so it is best described as a reasonable option in selected patients, not a proven treatment for the lump itself.
Topical antibiotic ointment after surgery is a different matter: it is applied briefly to protect a fresh wound, not to treat the chalazion. Whether any oral medicine suits you depends on your other conditions, sun exposure, pregnancy status and interactions with your existing prescriptions. That is a decision for your eye care clinician and prescribing doctor together, and nothing in this section should be read as a recommendation to start, stop or request a particular drug.
What people often get wrong about chalazion surgery
Myths cluster around small procedures because people rarely discuss them, so a few corrections are worth the space.
It is not laser surgery. Searches for “how to prepare for laser eye surgery” lead many people astray, because chalazion removal has nothing in common with refractive laser procedures on the cornea. No laser is used, no part of the eye itself is touched, and the preparation rules for refractive surgery, such as stopping contact lenses for weeks beforehand, do not apply. The only contact-lens rule here is to leave the lens out of the operated eye on the day and until the lid wound has sealed.
Stopping your blood thinner is not a sensible precaution. It is the opposite. Bruising from an eyelid procedure is cosmetic and temporary; a clot in a stent or a stroke is not. Any change to anticoagulant or antiplatelet therapy is made by the prescribing doctor, in discussion with the surgeon, and often the decision is to continue.
Squeezing the lump at home does not speed things up. Pressing hard can rupture the cyst into the surrounding lid tissue, spreading inflammation and sometimes creating the hot, swollen picture of a secondary infection. Warmth and gentle massage along the lid, toward the lashes, is the technique that is actually supported.
A scar across the eyelid is not the usual outcome. Because the incision is normally made on the inner lid surface, there is typically no visible skin mark at all. Skin-side approaches, reserved for lumps that have already broken through or sit very superficially, leave a fine line that fades.
Finally, surgery does not fix the reason the gland blocked. If the lid margins are inflamed, more chalazia can follow. Long-term lid hygiene is the part of the plan that actually changes the odds.
Questions to ask your care team before the day
A good pre-operative conversation is short but specific. Bring these questions written down, because clinic appointments move quickly and the most useful ones are easy to forget under mild nerves.
- Which approach do you plan, through the inner lid or through the skin, and will there be stitches?
- Would a steroid injection be a reasonable alternative in my case, and what are its trade-offs for me?
- Here is my full medicine and supplement list. Does anything on it need a plan, and who will contact my prescribing doctor if so?
- I have told you about my bruising and bleeding history. Does that change how you will do the procedure or how long I stay afterward?
- Will the eye be padded, and for how long? When can I drive again?
- Do you use a numbing gel or cold pack before the injection?
- What pain relief do you suggest afterward, and is there anything I should avoid?
- When can I return to work, exercise, swimming and contact lenses?
- Will you send any tissue for laboratory examination, and if so, when will I hear the result?
- What should I do about lid hygiene afterward to reduce the chance of another chalazion?
- Is there a follow-up appointment, and how do I reach someone if I am worried over a weekend?
Notice that almost none of these questions is about the cut itself. That is deliberate. The surgical part of chalazion surgery is routine for the clinician; the parts that go wrong, in the sense of causing avoidable stress, are logistics and communication. A patient who leaves the clinic knowing when the pad comes off, who is driving, what to take for soreness and whom to call has already removed most of the uncertainty.
If a question is answered in a way you do not understand, ask for it in plainer words. Clinicians will not mind. A clear, shared plan protects both sides, and every decision in it, from medicines to timing, rests with the treating team rather than with a search engine.
When to call your doctor: red-flag signs after chalazion surgery
Most recoveries are uneventful: a bruised, gritty lid that improves day by day. Contact your eye care team the same day, or seek urgent care if they are unreachable, if any of the following appears.
- Bleeding that soaks through the pad or does not stop with ten to fifteen minutes of firm, gentle pressure over a closed eye, particularly if you take an anticoagulant or antiplatelet medicine.
- Pain that worsens after the first day rather than easing, or pain severe enough that ordinary pain relief does not touch it.
- Spreading redness, heat or swelling of the lid and surrounding skin, especially if it extends toward the cheek or brow, or if you develop a fever or feel generally unwell. These can indicate cellulitis, a bacterial infection of the soft tissue around the eye, which needs prompt treatment.
- Any change in vision in the operated eye beyond ointment-related blurring: a drop in sharpness, double vision, or a new shadow.
- Difficulty moving the eye, or pain on eye movement, or an eye that appears pushed forward. These are signs that infection may involve the tissues behind the eye, which is a medical emergency.
- Thick yellow or green discharge, or a crust that keeps reforming after cleaning.
- A lump that is clearly growing or returning at the same site over the following weeks, or new lumps appearing in quick succession.
Keep the clinic’s number and out-of-hours advice in your phone before the day. Eyelid problems are easier to settle early, and no clinician will consider a cautious call a nuisance. If you cannot reach your eye team and the symptoms involve vision change, eye movement or fever, go to an emergency department rather than waiting for the next morning. Everything else on this list is urgent but not an emergency, and a same-day phone call is the right first step.
Frequently asked questions
How bad does chalazion surgery hurt?
For most people the only sharp part is the numbing injection into the eyelid, which stings for under a minute. Once numb, the clamp and scraping feel like pressure and tugging rather than pain. Afterward the lid feels bruised, heavy and gritty for a few days, usually manageable with plain pain relief recommended by your team. Pain that worsens after the first day is not expected and should be reported.
Do I need to stop aspirin or blood thinners before chalazion surgery?
Not on your own. Aspirin, clopidogrel and anticoagulants such as warfarin or direct oral anticoagulants affect bleeding, so your eye team needs to know about them, but whether to continue, pause or adjust is a decision made by the prescribing doctor together with the surgeon. For many minor eyelid procedures the medicine is continued and extra bruising is accepted, because stopping it carries a greater risk.
What is the typical chalazion surgery recovery time?
Most people wear an eye pad for several hours to overnight, see swelling peak around day two, and watch bruising fade over one to two weeks. The inner wound usually seals within about a week, while residual lid firmness can take several weeks to soften. Desk work is often possible the next day; swimming, dusty work and contact sports are generally paused until the team confirms the wound has healed.
Is it normal for a chalazion to be still there after surgery?
A lump-like firmness in the first one to two weeks is normal, because the emptied cavity fills with swelling and healing tissue that feels similar to the original chalazion. The difference is direction: healing firmness softens week by week. A lump that stays the same, grows, becomes painful, or returns at exactly the same site should be reviewed by your eye care clinician.
What does chalazion removal aftercare involve?
Keep the pad on for as long as instructed, then apply any prescribed ointment or drops, use a cold compress in short spells for swelling, and avoid rubbing the eye. Keep the lid clean with cooled boiled water or a lid wipe, leave contact lenses out of that eye, and skip eye makeup until the team clears you. Long-term warm compresses and lid hygiene reduce the chance of new chalazia.
Is doxycycline an effective treatment for a chalazion?
Not for an existing lump, because a chalazion is a sterile blockage rather than a bacterial infection. Tetracycline-class medicines are sometimes prescribed for people with chronic blepharitis or ocular rosacea who get repeated chalazia, using their anti-inflammatory and oil-modifying effects to reduce new blockages. That evidence comes from small studies and expert consensus, and any decision to use such a medicine belongs to your prescribing clinician.
Can I drive myself home after chalazion surgery?
No. A firm eye pad is usually applied to control bleeding, and driving with one eye covered removes depth perception and part of your visual field, which is unsafe and in many places would not meet licensing standards. Even without the pad, the operated eye is watery and smeared with ointment. Arrange a driver or escort, and if sedation or general anesthetic is used, a responsible adult must stay with you overnight.
Do I need to fast before chalazion surgery?
Usually not for adults having the procedure under local anesthetic, since you remain awake and fasting is an anesthetic safety rule rather than an eyelid rule. If sedation or a general anesthetic is planned, which is typical for young children and occasionally for very anxious adults, the anesthetic team will give exact fasting instructions that must be followed. If you are unsure which applies to you, ask the clinic beforehand.
Will chalazion surgery leave a scar on my eyelid?
Usually there is no visible scar, because the incision is normally made on the inner conjunctival surface of the lid, which heals without stitches and is hidden when the eye is open. A skin-side approach is sometimes needed for lumps that have already broken through or sit very close to the surface; that leaves a fine line that typically fades. Ask your surgeon which approach is planned.
Is chalazion surgery the same as laser eye surgery?
No. Chalazion removal is a minor eyelid procedure using a small blade and a curette under local anesthetic; no laser is involved and the eye itself is not operated on. Laser eye surgery reshapes the cornea to correct vision and has entirely different preparation, including stopping contact lenses for weeks beforehand. The only lens rule for chalazion surgery is to leave the lens out of the operated eye until the wound heals.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Does Corneal Disease Move From Drops to Surgery? How Specialists Weigh the Two Paths
Corneal disease usually moves from drops to surgery when the problem becomes structural rather than active: an infection that has healed but left a…
What Happens During an Ophthalmic Laser Session: Drops, the Lens on Your Eye and the Flashes
During an ophthalmic laser session you sit at a slit-lamp style machine while the eye is numbed with anesthetic drops and, for retinal work,…
How Glaucoma Damages the Optic Nerve Silently and Why Treatment Aims at Eye Pressure
Glaucoma damages the optic nerve by slowly killing the retinal nerve fibers that carry images from the eye to the brain, usually without pain…

Caring for Someone After Eye Surgery: Drop Schedules, Shields and the First Night Back
Caring for someone after eye surgery mostly means keeping to the written drop schedule without touching the eye, making sure the protective shield goes…

Macular Hole, Macular Pucker and Macular Edema: How the Main Macular Diseases Differ
The main types of macular disease damage the small patch of central retina in different ways. A macular hole is a small gap in…

Preparing for Cataract Surgery: Lens Measurements, Medication Review and Drop Schedules
Cataract surgery preparation usually involves a pre-assessment visit where the eye is measured to calculate the power of the replacement lens, a review of…