

Botulinum Toxin Beyond Wrinkles: How It Is Used for Chronic Migraine and Other Conditions

Key Takeaways
- Botulinum toxin was used medically for crossed eyes and eyelid spasm years before its cosmetic use existed, and the wrinkle effect was first noticed as a side effect.
- The molecule works by blocking release of acetylcholine at nerve endings, which is why it can quiet an overactive muscle, a sweat gland or a spasming bladder wall using the same mechanism.
- For migraine, the evidence supports use only in chronic migraine (15 or more headache days a month), and the NHS pathway reserves it for adults who have not responded to at least three other preventives.
- Effects typically begin within one to three days, peak over one to two weeks and fade after roughly three to four months, so medical treatment is a repeating cycle rather than a single procedure.
- Autoimmune disease is not a general barrier, but nerve-muscle junction disorders such as myasthenia gravis are a specific caution because the toxin can deepen existing weakness.
- Trouble swallowing, breathing or speaking, or spreading weakness in the days to weeks after injection, are signs of toxin acting beyond its target and need same-day medical contact.
Botulinum toxin, widely known by the brand shorthand Botox, is a prescription medicine that temporarily blocks the nerve signal that makes a muscle contract or a gland secrete. Regulators have approved it for chronic migraine, cervical dystonia, eyelid spasm, limb spasticity, overactive bladder and severe underarm sweating. Effects usually appear within days and fade over roughly three to four months, so treatment is repeated under a specialist's care.
The neurologist has just said the words, and the woman across the desk is trying not to look surprised. She has come in about headaches that swallow half of every month, and the suggestion on the table is a medicine she has only ever associated with celebrity foreheads. Her first question is the one almost everyone asks: isn’t that the wrinkle stuff?
It is, and it isn’t. Searches for botox for medical conditions have grown alongside a quiet clinical reality: the cosmetic use that made this molecule famous was a late arrival. Eye specialists were injecting it to straighten crossed eyes and calm spasming eyelids years before anyone thought about frown lines.
What follows is the conversation that patient deserved before she left the room: what the toxin does inside a nerve ending, which conditions it is approved to treat, what the weeks after an injection session tend to feel like, and where the evidence is solid, thin or simply absent.
Botox for medical conditions: why the shorthand hides a bigger story
One word does a lot of work here. “Botox” is the brand name of a single formulation of onabotulinumtoxinA, but in everyday speech it has become the generic label for an entire class of medicines called botulinum neurotoxins. Several formulations exist, they are not interchangeable unit for unit, and specialists choose among them for reasons that have nothing to do with marketing. This article uses the general term botulinum toxin, and treats the branded shorthand only as the phrase people type into a search bar.
The history matters because it explains the medicine’s odd reputation. In the late twentieth century, ophthalmologists began using tiny purified amounts of the toxin to weaken overactive eye muscles in strabismus (misaligned eyes) and blepharospasm (uncontrollable eyelid squeezing). Patients noticed that the frown lines between their brows softened as a side effect. Cosmetic use followed, and the marketing budget followed that.
By volume of prescriptions, cosmetic injections still dominate. By clinical weight, the medical indications are the more consequential story. A person with cervical dystonia whose neck is pulled sideways by muscles they cannot relax, a stroke survivor whose clenched hand will not open, a child with cerebral palsy whose calf muscles pull the foot into a tiptoe, someone leaking urine because a spinal cord injury has left the bladder in spasm: these are the patients for whom the same molecule is a serious medicine rather than a grooming choice.
Mayo Clinic’s overview of the procedure lists the approved medical uses alongside the cosmetic ones without ranking them, and that neutrality is the right frame. The molecule does not know why it was injected. It simply does one thing, very precisely, wherever it lands.
How does botulinum toxin actually work in the body?
Every time you decide to move a muscle, a nerve releases a chemical messenger called acetylcholine into the tiny gap where nerve meets muscle. The muscle fiber reads that message and contracts. Sweat glands and the smooth muscle of the bladder wall respond to the same messenger through their own nerve supply.

Botulinum toxin is a protein made by the bacterium Clostridium botulinum. Once a purified, measured amount is injected into a target muscle or gland, the protein is taken up into the local nerve endings. Inside, it cuts a piece of the molecular machinery that the nerve uses to release acetylcholine. The message is never sent. The muscle fibers supplied by those particular nerve endings go quiet; the sweat gland stops receiving its instruction to secrete.
Three features of this mechanism explain almost everything patients ask about.
- It is local. The toxin acts where it is placed, which is why an injector’s anatomical knowledge matters more than anything else about the appointment.
- It is temporary. Nerve endings slowly rebuild the cut machinery and sprout new terminals. Function returns, which is why medical treatment is repeated rather than done once.
- It is dose-dependent. A tiny amount weakens; a larger amount paralyzes. Specialists are titrating for partial relaxation, not shutdown.
This is also why the same molecule that treats disease can, in vastly larger and uncontrolled quantities, cause botulism, the food-borne paralysis described by the CDC. Medical botulinum toxin is measured in units so small they are not meaningfully expressed in milligrams, and the drug sheets published through MedlinePlus describe the therapeutic and dangerous scenarios as entirely different worlds. Understanding that the medicine and the poison share a mechanism, but not a dose range, dissolves most of the fear people bring into the room.
Which medical conditions is botulinum toxin approved to treat?
Approval lists differ slightly between regulators and between toxin formulations, but a stable core has emerged. Mayo Clinic, Cleveland Clinic and MedlinePlus describe the following indications as established medical uses in adults, with some also approved in children.
| Condition | What is being calmed | What the patient usually notices |
|---|---|---|
| Chronic migraine | Pain-signaling nerve endings around the head and neck | Fewer headache days per month |
| Cervical dystonia | Overactive neck muscles pulling the head into a twist or tilt | Easier head posture, less neck pain |
| Blepharospasm and hemifacial spasm | Eyelid and facial muscles contracting involuntarily | Eyes stay open; face stops twitching |
| Strabismus | An eye muscle pulling the eye out of alignment | Improved eye alignment |
| Limb spasticity (after stroke, brain injury, cerebral palsy) | Muscles locked in tight flexion or extension | Easier stretching, dressing, hygiene, bracing |
| Overactive bladder and neurogenic bladder | Bladder wall muscle contracting too often | Fewer urgency and leakage episodes |
| Severe axillary hyperhidrosis | Nerve supply to underarm sweat glands | Markedly reduced sweating |
| Sialorrhea | Nerve supply to salivary glands | Less drooling |
Two words in that table need defining. Spasticity is muscle stiffness caused by damage to the brain or spinal cord, which leaves muscles receiving a constant “tighten” signal. Hyperhidrosis is sweating far beyond what temperature or activity requires.
Beyond this list sits a wide off-label territory, where a clinician prescribes for a purpose the regulator has not formally reviewed. Jaw clenching (bruxism), anal fissure, achalasia (a swallowing disorder), certain tremors and chronic pelvic pain all appear in specialist practice. Off-label does not mean disproven; it means the evidence has not gone through the approval pathway, and the strength of that evidence varies enormously from one use to the next. Your specialist should be able to tell you which side of that line your condition sits on.
Botox for chronic migraine: what the evidence shows
Chronic migraine has a strict definition: headache on 15 or more days a month for more than three months, with migraine features on at least eight of those days, as the NHS describes it. That threshold matters, because botulinum toxin has not been shown to help people with episodic migraine, who have fewer headache days. Trials in that group were disappointing. The medicine earned its approval specifically in the chronic form.
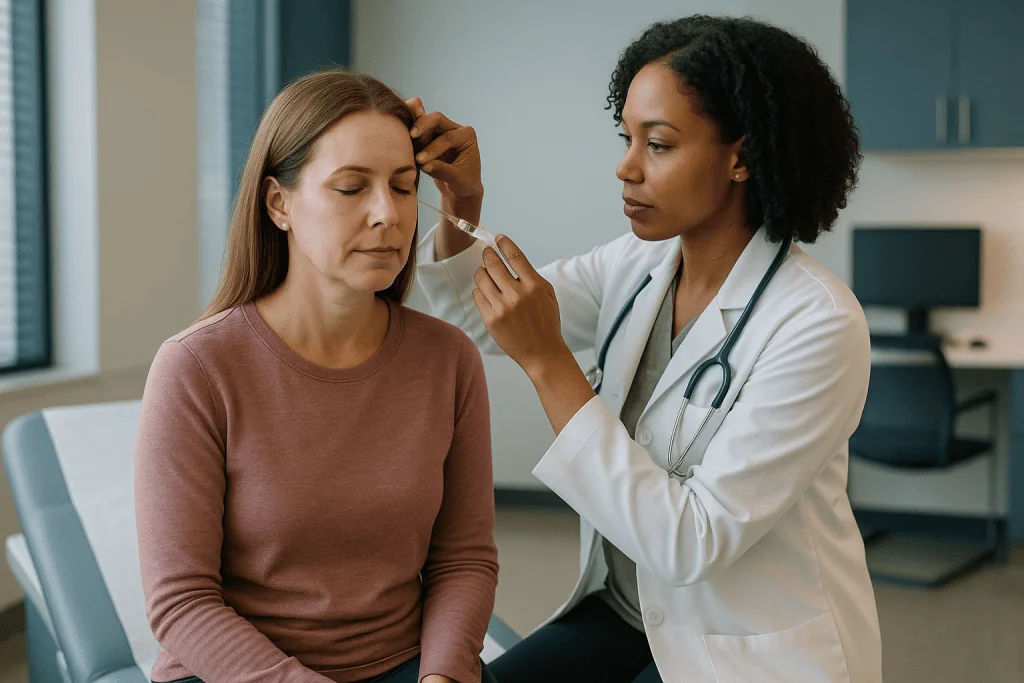
How a muscle relaxant helps a headache is a fair question, and the honest answer is that muscle relaxation is probably not the point. Current thinking, described in Mayo Clinic’s overview, is that the toxin is taken up by sensory nerve endings in the scalp, forehead, temples and neck and reduces their release of pain-signaling chemicals, dampening the cascade that builds into a migraine attack. It is being used as a nerve modulator, not a cosmetic.
The NHS treatment guidance, which follows the national NICE recommendation, reserves botulinum toxin for adults with chronic migraine who have already tried at least three other preventive medicines without adequate benefit. Response is judged over time rather than after a single session. The guidance describes reassessing after a couple of treatment cycles and stopping if the number of headache days has not fallen meaningfully or if the pattern has shifted back toward episodic migraine, which counts as a good outcome rather than a failure.
What does “meaningful” look like? In the pivotal trials, people receiving the toxin had on average roughly two fewer headache days per month than those receiving placebo injections, on top of a substantial placebo response in both groups. That is a real but modest gap on average, and averages conceal wide individual variation. Some people notice a transformation; others feel nothing. Nobody can predict in advance which group a given patient will join, and any clinician who promises otherwise has stepped beyond the evidence.
What happens at a chronic migraine injection appointment?
The room is ordinary. There is no anesthesia, no gown, no recovery bay. Most people arrive, sit in a chair, and leave within half an hour, able to drive themselves home.
The specialist, usually a neurologist or headache clinician, follows a standardized map of injection points across the forehead, temples, back of the head, upper neck and shoulders. The map exists because the approval trials used a fixed pattern, and departing from it means departing from the evidence. Some clinicians add a few extra points where a particular patient’s pain concentrates. The needle is very fine; most people describe the sensation as a series of quick pinches, with the neck and shoulder sites often the most noticeable. A cold pack afterward is usually all the comfort measure anyone needs.
A few practical details tend to surprise first-timers.
- You will be asked to keep your head upright and avoid rubbing or massaging the injected areas for the rest of the day, to limit the toxin drifting to muscles it was not intended for.
- Small bumps at the injection sites settle within an hour or so; mild bruising can take a few days.
- A dull, achy head or neck for a day or two afterward is common and is not a sign the treatment has failed.
Headache diaries are the unglamorous backbone of this treatment. Because response is judged on headache days per month, your team will want a reliable record from before the first session through the following cycles. Phone apps work; so does a paper calendar. Without it, the reassessment the NHS guidance calls for becomes guesswork, and decisions about whether to continue rest on impression rather than data. Bring the diary to every visit.
Botox for excessive sweating, overactive bladder and muscle spasm
The migraine story gets the headlines, but three other uses show the mechanism at its most direct.
Severe underarm sweating is, in some ways, the cleanest application. Sweat glands respond to acetylcholine from nearby nerve endings; block the release, and the gland falls quiet. A grid of shallow injections across each armpit, sometimes after a starch-iodine test to map exactly where the sweating is heaviest, reduces output within a week or so. Cleveland Clinic and Mayo Clinic describe this as an established option for people whose sweating has not responded to prescription-strength antiperspirants. Effects on the palms and soles are also studied but are harder to deliver comfortably and are used less often.
Overactive bladder works on the same principle with a different route. A urologist passes a thin camera through the urethra and places small injections directly into the bladder wall, usually under local anesthesia in the clinic. The muscle contracts less forcefully and less often, so urgency and leakage episodes fall. This is used for idiopathic overactive bladder that has not responded to bladder training and oral medicines, and for the neurogenic bladder that follows spinal cord injury or multiple sclerosis. The trade-off is specific and worth knowing before you agree: some people find that the bladder empties incompletely afterward and need to learn intermittent self-catheterization for a period, and urinary tract infections are more common in the weeks after injection, as MedlinePlus notes.
Spasticity and dystonia are where the toxin has been used longest. In a stroke survivor with a fist that will not open, or a child with cerebral palsy walking on tiptoe, weakening the overactive muscles does not restore normal movement. What it does is create a window, typically a few months, in which stretching, splinting and physical therapy can achieve what they could not against a rigid muscle. Clinicians often use ultrasound or electrical guidance to find the exact muscle, because in a forearm the target may be one of a dozen small muscles lying side by side.
Who is botulinum toxin usually for, and who is asked to wait?
Across all its medical uses, the same pattern appears: botulinum toxin is rarely a first step. It tends to enter the picture when simpler measures have been tried in earnest.
For chronic migraine, the NHS pathway asks for adequate trials of other preventive medicines first. For overactive bladder, bladder retraining and oral medicines come before injections. For hyperhidrosis, clinical-strength antiperspirants are the starting point. For spasticity, physiotherapy and positioning continue throughout, with the toxin layered on top when a specific muscle group is blocking progress. The reason is not that the toxin is dangerous; it is that it is invasive, repeated, and specialist-dependent, and good medicine reaches for the simplest effective tool first.
Certain situations prompt a specialist to pause or decline, and MedlinePlus and Mayo Clinic list them consistently.
- An active infection at the planned injection site, which is a reason to reschedule rather than cancel.
- Known allergy to any botulinum toxin product or to its inactive ingredients.
- Pregnancy or breastfeeding, where safety data are limited and most clinicians defer unless the indication is compelling.
- Disorders of the nerve-muscle junction such as myasthenia gravis, Lambert-Eaton syndrome or amyotrophic lateral sclerosis, where even a small additional weakening effect can be hazardous.
- Swallowing or breathing difficulties, particularly when neck or jaw muscles are the target.
Medicines matter too. Aminoglycoside antibiotics, some muscle relaxants and other drugs that affect nerve transmission can amplify the toxin’s effect, and blood thinners raise the chance of bruising, so a full medication list belongs in every pre-treatment conversation. Age is not a barrier in itself: approved uses span children with cerebral palsy to older adults after stroke. The question is never “is this person eligible” in the abstract but “is this the right next step for this person, with this condition, at this point”, and that judgment sits with the treating team.
Can people with autoimmune conditions have botulinum toxin?
This question comes up constantly, and the answer is more reassuring, and more specific, than most people expect.
Having an autoimmune disease is not, on its own, a reason to avoid botulinum toxin. People with rheumatoid arthritis, lupus, inflammatory bowel disease, psoriasis or Hashimoto’s thyroiditis receive the medicine for migraine, dystonia, bladder problems and sweating in routine practice. The toxin does not act on the immune system in the way that immunosuppressant drugs do, and it is not known to trigger flares of these conditions.
The caution is narrower and concerns one particular family of autoimmune disorders: those that already attack the junction between nerve and muscle. Myasthenia gravis is the prominent example. In that disease, antibodies damage the receptors that receive acetylcholine, so muscles already struggle to hear the nerve’s message. Adding a medicine whose job is to quiet that message further can tip a person into dangerous weakness, including of the breathing and swallowing muscles. MedlinePlus lists myasthenia gravis and related conditions as diagnoses you must tell your prescriber about before any injection. Multiple sclerosis is a different case: it is autoimmune, it affects nerves, but it is not a junction disorder, and people with MS are among the most common recipients of bladder and spasticity injections.
A second, subtler immune issue is worth knowing. A small proportion of people who receive repeated injections over years develop neutralizing antibodies against the toxin protein itself, and the medicine gradually stops working for them. This is not an allergy and is not more common in people with other autoimmune conditions; it is simply the body learning to recognize a foreign protein. Specialists reduce the risk by using the smallest effective amount and spacing sessions, which is one reason the interval between treatments is not shortened just because effects seem to fade early. If a treatment that once worked stops working, this is one of the possibilities your team will consider.
What do the days and weeks after treatment look like?
Botulinum toxin does not work on the day it is given, and knowing the shape of the timeline spares a great deal of unnecessary worry.
Day one to three: not much. Tiny injection bumps have flattened. There may be tenderness, bruising or a mild ache in the treated area. For migraine patients, a flat, bruised-feeling headache in the first day or two is common. For bladder injections, mild burning on urination or a trace of blood can occur. Nothing about your muscles feels different yet, because the toxin is still being absorbed into nerve endings and has not yet cut its target.
Day three to fourteen: the effect arrives. Mayo Clinic describes the first noticeable change within one to three days for most uses, building to a full effect over one to two weeks. A dystonia patient feels the neck pull ease. A person treated for sweating notices a drier shirt. A spastic limb becomes easier to stretch, and this is exactly when physiotherapy should intensify.
Weeks two to twelve: the plateau. For chronic migraine, this is where the headache diary earns its keep, because the benefit is measured in fewer bad days across the month rather than a feeling on any single day. Some people report that the first cycle does little and the second or third does more, which is why the NHS guidance judges response over more than one cycle.
Around month three to four: the fade. Nerve endings have rebuilt their release machinery, and function returns. Cleveland Clinic gives three to four months as the typical duration for most medical uses, with some spasticity and bladder patients reporting longer. Retreatment is planned around this natural cycle, and the interval is set by the specialist, not shortened on request, partly to protect against the antibody problem described earlier. None of these ranges is a promise; they are the center of a wide distribution.
What are the risks and side effects of medical botulinum toxin?
Risk with this medicine follows a simple rule: it is almost entirely about where the toxin goes. Placed accurately in the intended muscle, side effects are usually minor and local. Drifting into a neighbor, or in rare cases spreading further, is where the real problems lie.
Common, local, temporary effects include pain, bruising and swelling at the injection site, a short-lived headache, and flu-like tiredness for a day or two. These are described across Mayo Clinic, Cleveland Clinic and MedlinePlus and generally settle without any treatment.
Site-specific effects follow the anatomy of each indication.
- Around the eyes: drooping eyelid, dry eye, double vision or difficulty closing the eye fully.
- Neck and jaw: difficulty swallowing, hoarseness, weakness lifting the head. Swallowing trouble after cervical dystonia injections is the best-known example and can last weeks.
- Forehead and scalp for migraine: eyebrow droop, neck weakness, neck pain.
- Bladder: urinary retention needing temporary catheterization, urinary tract infection.
- Limbs: excessive weakness of the treated limb, falls if the leg is involved.
The rare serious concern is distant spread of the toxin, producing generalized weakness, trouble breathing, trouble swallowing or speaking, and loss of bladder control, hours to weeks after injection. Regulators require a prominent warning about this on all botulinum toxin products. It has been reported most often in children treated for spasticity with large total amounts, and in adults with pre-existing swallowing or breathing problems. It is uncommon, and it is precisely why the medicine is prescribed by specialists rather than handed out casually, and why the “when to call your doctor” list at the end of this article deserves a careful read.
Allergic reactions, including hives and, very rarely, anaphylaxis, have been described but are unusual. Alternatives always exist and are covered below; the choice between them belongs in a conversation with your treating team, not in a magazine.
Does insurance pay for Botox for medical reasons?
This is the most searched question about medical botulinum toxin, and it deserves a direct answer even though no dollar figure belongs in a clinical explainer.
Coverage in the United States turns on a distinction insurers hold firmly: whether the injection is treating a diagnosed medical condition or altering appearance. Cosmetic use is essentially never covered. Medical use for a regulator-approved indication, such as chronic migraine, cervical dystonia, blepharospasm, spasticity, overactive bladder or severe hyperhidrosis, is commonly covered by commercial plans, Medicare and Medicaid, though the rules and paperwork vary widely between plans and between states.
“Commonly covered” comes with conditions, and knowing them in advance saves months.
- Most plans require prior authorization, meaning the prescriber submits documentation and the insurer approves before the first session.
- For chronic migraine, plans typically want evidence that the diagnosis meets the strict definition and that several other preventive medicines have been tried and failed or were not tolerated. Headache diaries help here too.
- Continued coverage is often tied to documented benefit, echoing the clinical reassessment the NHS guidance describes.
- Off-label uses are much less likely to be covered, and appeals in that territory succeed unevenly.
Two practical points. First, the specialist’s office usually handles the authorization process and is used to it; ask whether they will, and how long it typically takes. Second, the toxin itself and the injection procedure may be billed as separate items, and where the vial comes from (the clinic’s supply or a specialty pharmacy shipping to the clinic) can affect how it is processed. This article deliberately does not describe how to obtain the medicine outside a clinical setting; there is no safe way to do so.
Coverage does not equal appropriateness. An insurer’s approval is a financial decision about a category, not a medical judgment about you. That judgment remains with the treating team.
What is the new treatment instead of Botox?
People asking this usually mean one of two things: a different medicine for their condition, or a newer version of the toxin itself. Both exist, and neither is universally better.
For chronic migraine, the notable development of recent years is a class of medicines targeting calcitonin gene-related peptide, or CGRP, a chemical released during migraine attacks that widens blood vessels and transmits pain. Monoclonal antibodies against CGRP or its receptor are given by injection at home or by infusion, and a group of oral tablets called gepants block the same pathway. The NHS migraine treatment page describes these as preventive options alongside, not instead of, botulinum toxin. Head-to-head evidence is still limited; some people use both classes together under specialist supervision, and choice depends on other health conditions, side-effect profiles and coverage rather than on which arrived more recently.
Older preventive classes remain in use: certain blood pressure medicines, anti-seizure medicines and antidepressants, all prescribed at preventive rather than their original purposes. Nerve blocks and non-invasive neuromodulation devices that stimulate the vagus or trigeminal nerve are further options with a smaller evidence base.
For other conditions, alternatives differ. Overactive bladder has oral anticholinergics and beta-3 agonists, tibial nerve stimulation and, for resistant cases, an implanted sacral nerve stimulator. Hyperhidrosis has prescription antiperspirants, iontophoresis (passing a gentle current through water) and, rarely, surgery. Spasticity has oral muscle relaxants, intrathecal pump therapy and orthopedic procedures.
As for the toxin itself, several formulations are approved, including some engineered for longer duration in cosmetic use, and formulations made without certain accessory proteins in the hope of lowering antibody formation. Whether these translate into better medical outcomes is not yet established in high-quality comparative trials. “Newer” is a date, not a verdict. The right alternative for you is a question for your specialist, who knows your history and the evidence for each option.
What people often get wrong about medical botulinum toxin
Myths gather around famous molecules, and this one has attracted more than most.
“It’s a poison, so it must be dangerous.” The bacterium’s toxin causes botulism, a genuine emergency described by the CDC. The medicine is a purified, precisely measured fraction of a fraction of the amount involved in food-borne poisoning, injected locally rather than absorbed through the gut. The mechanism is shared; the dose range is not remotely comparable. Decades of use in children and adults support its safety when prescribed and injected by trained specialists.
“It freezes muscles and stops you feeling anything.” It weakens the specific muscle it is placed in. It does not numb skin or block sensation. The forehead of a migraine patient still feels touch; it simply frowns less forcefully.
“If it works for migraine, it should work for any headache.” The evidence is confined to chronic migraine as strictly defined. Episodic migraine trials were negative, and tension-type headache is not an indication.
“One treatment and you’re done.” Nerve endings regenerate. Medical use is a repeating cycle, typically around every three to four months according to Cleveland Clinic, for as long as it keeps helping.
“More often is better.” Shortening the interval raises the chance of antibody formation and does not extend the effect. The schedule is set by the specialist for a reason.
“It’s just cosmetic doctors doing this on the side.” Medical botulinum toxin is delivered by neurologists, urologists, ophthalmologists, rehabilitation physicians and dermatologists, often with ultrasound or electrical guidance, in a clinical pathway that looks nothing like an aesthetic appointment.
“It treats depression.” Small trials injecting frown muscles have reported mood changes, but the evidence is early, inconsistent and not part of any guideline. Presenting it as an established treatment would be dishonest.
“Natural alternatives do the same thing.” No supplement or topical product blocks acetylcholine release at the nerve ending. Claims otherwise are marketing, not pharmacology.
Questions to ask your care team
The best appointments are the ones where the patient arrives with a short list and leaves with fewer unknowns. These questions are worth writing down.
- Is my condition one that botulinum toxin is formally approved to treat, or is this an off-label use? If off-label, how strong is the evidence?
- What have I already tried, and why do you think this is the right next step rather than another option?
- Which formulation are you using, and does that matter for my situation?
- Will you use ultrasound or electrical guidance to locate the muscle? For limb spasticity and some neck injections this changes accuracy.
- What specific improvement are we looking for, and how will we measure it? Ask for a number: headache days per month, leakage episodes per day, range of motion in degrees.
- How many cycles will we try before deciding whether to continue or stop?
- What side effects are most likely with the sites you are injecting, and how long do they usually last?
- Which of my current medicines or conditions could interact with the toxin? Mention any nerve-muscle disorder, swallowing or breathing problem, blood thinner, or planned pregnancy.
- What should I do, and not do, in the first day after injection?
- If the effect seems to wear off early, what happens: do we wait for the scheduled interval, adjust the plan, or investigate antibodies?
- Who do I contact, and how quickly, if I notice trouble swallowing, breathing or new weakness?
- Does your office handle insurance authorization, and what documentation will they need from me?
- What is the alternative if this does not help, and what is the alternative if I decide against it altogether?
Write the answers down or bring someone to listen. Repeating treatments over months and years means this is a long relationship with a care team, and a shared understanding at the start pays off at every visit that follows.
When to call your doctor
Most people go home after botulinum toxin injections and get on with their day. A small number develop problems that need prompt attention, and because the toxin’s effect builds over days and lasts months, symptoms can appear well after you have left the clinic. The regulator-required warning on every botulinum toxin product, summarized in MedlinePlus, describes signs of the toxin acting beyond its intended site. Treat the following as reasons to call the same day, or to seek emergency care if they are severe or worsening.
- Difficulty swallowing, choking on food or liquids, or food feeling stuck.
- Difficulty breathing, shortness of breath, or a weak cough.
- Trouble speaking, slurred speech or a hoarse voice that does not clear.
- Generalized muscle weakness, particularly if it spreads beyond the treated area, or new difficulty holding your head up.
- Drooping of the eyelids or face, double or blurred vision, or difficulty closing an eye that was not expected from the treatment.
- Loss of bladder control, or, after bladder injections, inability to pass urine at all, severe lower abdominal pain, fever or foul-smelling urine.
- Hives, facial swelling, wheezing or feeling faint soon after injection, which may signal an allergic reaction and warrants emergency care.
- Spreading redness, warmth, increasing pain or pus at an injection site, suggesting infection.
- Any fall or near-fall after leg injections for spasticity.
Swallowing and breathing symptoms are the ones that matter most, because the muscles involved can weaken further over the following days rather than improve. Do not wait to see whether they settle. Contact the team that performed the injection, or your nearest emergency department if you cannot reach them, and tell whoever you speak to that you have recently received botulinum toxin and where.
Everything else in this article is background. The decision to start, continue, adjust or stop this treatment belongs to you and your treating specialists, informed by your history, your goals and the evidence as it applies to you.
Frequently asked questions
Can you get Botox for medical reasons?
Yes. Botulinum toxin is a prescription medicine with regulator-approved medical uses including chronic migraine, cervical dystonia, blepharospasm, strabismus, limb spasticity, overactive bladder and severe underarm sweating. It is prescribed and injected by specialists such as neurologists, urologists, ophthalmologists and rehabilitation physicians, usually after simpler treatments have been tried. Whether it is appropriate for a particular person depends on the diagnosis, prior treatments and other health conditions, and that decision rests with the treating team.
Does insurance pay for Botox for medical reasons?
Often, for approved medical indications, though rules vary by plan and state. Cosmetic use is essentially never covered. For conditions such as chronic migraine, dystonia, spasticity or overactive bladder, most plans require prior authorization, documentation of the diagnosis and evidence that other treatments were tried first. Continued coverage is frequently tied to documented benefit. Off-label uses are less likely to be covered. The prescribing office usually manages the authorization process; ask them how long it typically takes.
What is the new treatment instead of Botox for migraine?
The main newer class is medicines that block calcitonin gene-related peptide (CGRP), a chemical involved in migraine attacks. These include injectable monoclonal antibodies and oral tablets called gepants. The NHS lists them as preventive options alongside botulinum toxin rather than as replacements. Head-to-head comparisons are limited, and some people use both under specialist supervision. Older preventive classes, nerve blocks and neuromodulation devices remain options. Which is right for you depends on your history and is a decision for your specialist.
Can people with autoimmune conditions have botulinum toxin?
Usually, yes. Conditions such as rheumatoid arthritis, lupus, psoriasis or inflammatory bowel disease are not reasons to avoid it, and it is not known to trigger flares. The specific caution is for autoimmune disorders of the nerve-muscle junction, especially myasthenia gravis and Lambert-Eaton syndrome, where the toxin can worsen weakness dangerously. Multiple sclerosis is not in that category, and people with MS commonly receive bladder and spasticity injections. Always disclose every diagnosis to your prescriber.
How does Botox for chronic migraine work if it is a muscle relaxant?
Muscle relaxation is probably not the mechanism. The toxin is thought to be taken up by pain-sensing nerve endings in the scalp, temples, forehead and neck, where it reduces the release of pain-signaling chemicals that build into a migraine attack. In effect it is acting as a nerve modulator. This also explains why it helps chronic migraine but not tension-type headache or episodic migraine, where trials did not show benefit.
How long does medical botulinum toxin take to work and how long does it last?
Most people notice the first effects within one to three days, with the full effect developing over one to two weeks, according to Mayo Clinic. The benefit then lasts roughly three to four months for most medical uses, as Cleveland Clinic describes, before nerve endings recover and treatment is repeated. For chronic migraine, response is judged across more than one cycle using a headache diary rather than after a single session. These are typical ranges, not guarantees.
What are the medical uses of botox beyond migraine?
Approved uses include cervical dystonia (involuntary neck twisting), blepharospasm (eyelid spasm), hemifacial spasm, strabismus, limb spasticity after stroke, brain injury or cerebral palsy, overactive bladder and neurogenic bladder, severe axillary hyperhidrosis and sialorrhea (drooling). Off-label uses in specialist practice include jaw clenching, anal fissure, achalasia and some tremors, with evidence that varies widely in quality. Your specialist can tell you which category your condition falls into.
Does botox for excessive sweating work anywhere on the body?
It is approved for severe underarm sweating that has not responded to prescription-strength antiperspirants, and Mayo Clinic and Cleveland Clinic describe it as an established option there. Palms, soles and the face have been treated in studies and specialist practice, but injections in those areas are more painful, can cause temporary hand weakness, and are used less routinely. A starch-iodine test may be used first to map exactly where sweating is heaviest.
What happens after botox for overactive bladder?
Urgency and leakage episodes usually fall within one to two weeks as the bladder muscle contracts less forcefully. Two specific effects are worth knowing in advance: some people empty the bladder incompletely afterward and need to learn temporary intermittent self-catheterization, and urinary tract infections are more common in the weeks after injection, as MedlinePlus notes. Fever, inability to pass urine or severe lower abdominal pain should be reported the same day.
Is botulinum toxin the same thing that causes botulism?
The same protein, at incomparably different doses and routes. Botulism, described by the CDC, results from swallowing or producing large uncontrolled amounts of toxin that spread through the body. The medicine is a purified, precisely measured fraction injected locally into a muscle or gland, where it acts on nearby nerve endings. Decades of specialist use in adults and children support its safety when prescribed appropriately. Signs of the toxin spreading beyond its target are rare but should prompt immediate medical contact.
References
- NHS: Migraine, treatment
- MedlinePlus: OnabotulinumtoxinA injection
- Cleveland Clinic: Botulinum toxin injections
- CDC: About botulism
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Dermabrasion vs Dermaplaning: Deep Resurfacing and Surface Exfoliation Are Not the Same
Dermabrasion and dermaplaning are different procedures that happen to share a name. Dermabrasion is a surgical resurfacing treatment: under anesthesia, a clinician uses a…

How 3D Planning Models Shape Joint Surface Reconstruction Before the First Incision
3D planning for joint surface reconstruction uses a patient's own CT or cone-beam scan to build a digital and often printed replica of the…

Blepharoplasty Recovery Time: Upper, Lower and Combined: Week by Week
Most people look socially presentable 10 to 14 days after blepharoplasty. Upper eyelid surgery alone typically allows a return to desk work in about…

Is IPL Photorejuvenation Suitable for Your Skin Type? Why Tone and Tan Matter Before Treatment
IPL photorejuvenation is generally considered safest on lighter skin (Fitzpatrick types I to III) because its broad-spectrum light is absorbed by melanin in the…

Hand Rejuvenation With Fillers vs Fat Transfer: How Specialists Choose Between Them
Hand fillers and fat transfer both restore lost volume on the back of the hand, but they suit different people. Fillers are an office…

Does Laser Resurfacing Hurt? Numbing Options and How Comfort Changes With Laser Depth
Laser resurfacing is usually uncomfortable rather than severely painful, and the sensation scales with depth. Light non-ablative treatments feel like brief heat or a…